

Breastfeeding and Nipple Sensation After Breast Reduction: What Can Change and What Returns
Key Takeaways
- Breastfeeding after reduction is common in observational studies, but exclusive breastfeeding is less frequent than in people without surgery, according to a systematic review in PLoS One.
- The pedicle, the tissue column that keeps the nipple attached during surgery, matters more for milk and sensation than the visible scar pattern.
- Free nipple grafting divides all ducts and nerves to the nipple, so breastfeeding is generally not expected and numbness is usually permanent.
- Surgical guidance from Mayo Clinic and Cleveland Clinic describes sensory change as temporary or permanent, with recovery continuing over roughly the first year.
- Severed milk ducts can occasionally reconnect over time, and pregnancy stimulates remaining gland tissue, so later pregnancies may go better than the first.
- A copy of your operative report tells a future lactation consultant far more than your memory, so ask for it before you leave the hospital.
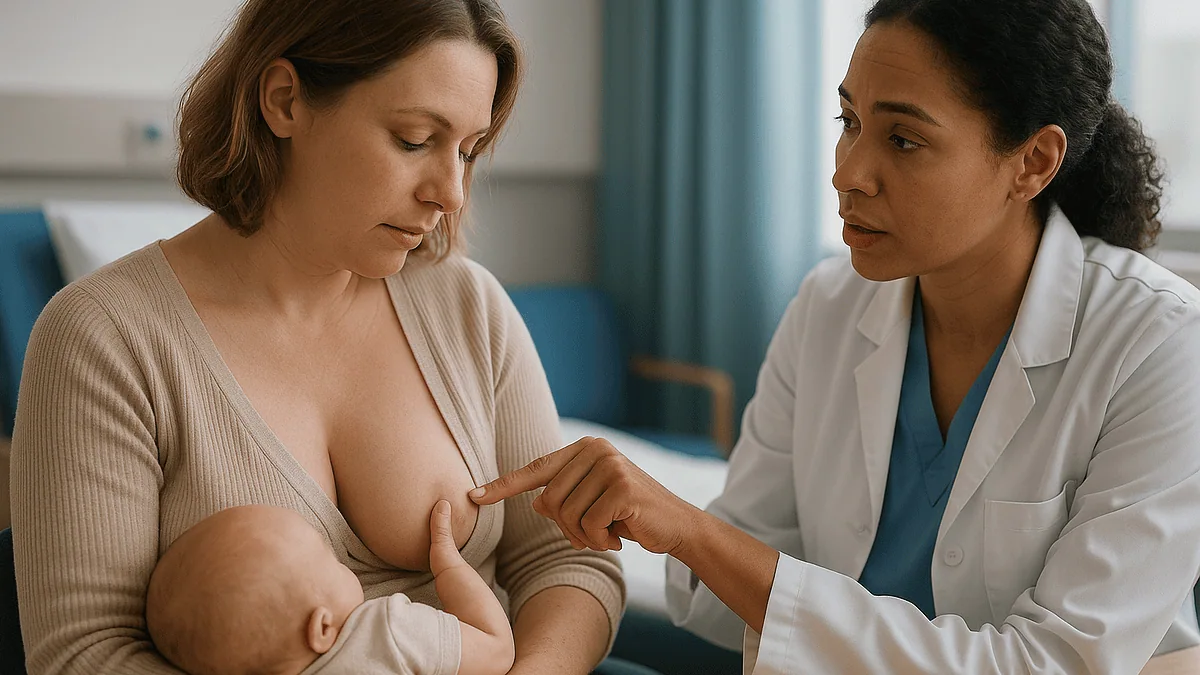
Many people can breastfeed after breast reduction, though exclusive breastfeeding is less common than among those who have not had surgery, and supply depends on how much gland and duct tissue stays connected to the nipple. Nipple sensation frequently changes; numbness often improves over the following months, yet some change can be permanent. Results vary by technique and individual, so plans belong with your surgical and feeding team.
She is thirty-one, has carried heavy breasts since her teens, and has finally booked a consultation. The shoulder grooves from her bra straps are real. So is the folder of questions on her phone, and the one she has not typed out yet: if I do this now, will I still be able to feed a baby later, and will my nipples feel like mine?
It is one of the most common things surgeons hear, and one of the least well answered online. Breastfeeding after breast reduction is neither guaranteed nor ruled out. Nipple sensation is neither always lost nor always spared. What actually happens depends on anatomy, on the technique chosen, and on things nobody can fully predict before the operation.
This explainer walks through the plumbing and the wiring of the breast, what the research genuinely shows, what tends to return with time, and how to have a franker conversation with the people who will be holding the scalpel.
How breast reduction works, and where milk and sensation travel
A breast reduction, known medically as reduction mammaplasty, removes glandular tissue, fat and skin to make the breast smaller and lighter, then lifts and repositions the nipple. Mayo Clinic describes it as a procedure usually chosen for chronic back, neck and shoulder pain, skin irritation under the breast and restricted activity, with a cosmetic element that matters to many but is rarely the only driver.
To understand what the operation can and cannot protect, picture two systems running through the breast. The first is a branching tree of milk-making lobules feeding into ducts that converge on the nipple; think of a river delta emptying at a single point. The second is a web of sensory nerves, the most important of which enter the breast from the side of the chest wall and run inward toward the nipple and areola.
Both systems pass through exactly the tissue a surgeon is reshaping. Whether they survive depends on how much of the breast is removed and, above all, on how the nipple stays attached during the operation. When the nipple remains connected to a column of tissue containing ducts, vessels and nerves, milk and feeling have a route to follow afterwards. When that column is thin, or when the nipple has to be removed and replaced as a graft, the routes are interrupted.
None of this is a criticism of the surgery. Reduction relieves symptoms that can be disabling, and MedlinePlus notes that most people are pleased with the change in comfort. The honest framing is trade-offs: the same cut that lightens the load also passes through the delta and the wiring, and the extent of that crossing shapes what comes back.
Why the pedicle decides so much
Surgeons call the strip of living tissue that keeps the nipple attached to its blood supply during the operation a pedicle. It is the single most important word in this whole topic, and most patients have never heard it.
The pedicle can be designed from different directions. An inferior pedicle carries the nipple on tissue rising from the lower breast; a superior or superomedial pedicle carries it on tissue from above or from the inner upper quadrant; a central pedicle keeps a column directly beneath the nipple. Each design preserves a different slice of the duct tree and a different share of the nerves. Because the main sensory nerves approach from the outer chest wall, designs that keep more of the lateral and central tissue tend to leave more of the wiring intact, though individual anatomy varies enough that no design can promise a result.
Size matters as well. A modest reduction leaves much of the gland in place and often keeps most ducts open to the nipple. A very large reduction, where the nipple must be moved a long distance, stretches the pedicle thin and may leave fewer functioning ducts. Cleveland Clinic’s overview of the procedure lists changes in nipple sensation and difficulty breastfeeding among the recognized risks precisely for these reasons.
Here is the practical point. If future breastfeeding matters to you, the conversation is not “reduction: yes or no.” It is “which pedicle, how much tissue, and how will you decide on the day?” Surgeons plan the pedicle before the first incision and sometimes adjust it during the operation based on what they find. Stating your priority early gives them room to weigh it alongside safety, symmetry and blood supply, which always come first.
Can you breastfeed after breast reduction? What the research shows
The short version: often yes, though not always fully. A systematic review of observational studies published in PLoS One examined breastfeeding after reduction mammaplasty and found that many women who had undergone the surgery went on to breastfeed, while exclusive breastfeeding, meaning the baby receives breast milk alone, was less common than among women without prior surgery. The authors were careful to note that studies differed in technique, follow-up and how they defined breastfeeding, so a single tidy percentage would misrepresent the evidence.
Why the gap between “some milk” and “only milk”? Producing milk requires three things working together: functioning gland tissue, open ducts to carry milk to the nipple, and intact nerve signals from the nipple that tell the brain to release prolactin and oxytocin, the hormones that drive production and let-down. A reduction can partially interrupt any of the three. Gland left behind still makes milk, but if some ducts were cut, that milk has no exit and the affected lobules gradually shut down. If nerve supply is reduced, the hormonal response to suckling may be blunted.
Two features of the research deserve attention. First, the passage of time since surgery may help; ducts can recanalize, meaning severed ends occasionally reconnect, and pregnancy itself stimulates gland growth. Second, the strongest predictor across studies was the surgical approach, particularly whether the nipple stayed attached on a pedicle rather than being grafted.
What this means for one person cannot be read off a table. It means breastfeeding after breast reduction is a realistic goal worth planning for, with the expectation that some supplementation may be needed and that a lactation professional should be part of the plan from the start.
Nipple sensation after breast reduction: what changes
Sensation is the part people whisper about. It matters for comfort, for intimacy and, less obviously, for breastfeeding, because the nipple is the sensor that triggers milk release.

Mayo Clinic and the NHS both list altered nipple or breast sensation among the expected effects of reduction, describing it as sometimes temporary and sometimes permanent. The word “altered” is deliberate. Some people wake up with nipples that feel numb, as though anesthetized at the dentist. Others report the opposite: hypersensitivity, tingling or a buzzing discomfort when fabric brushes the skin. A smaller number describe patchy sensation, where one area feels normal and a neighboring one feels distant. All of these reflect nerves that have been stretched, bruised or divided.
Nerves recover in a particular way. Stretched or bruised fibers, a state called neurapraxia, often resume function as swelling settles. Fibers that were cut can regrow from the healthy end at a slow crawl, roughly the pace of a fingernail growing, and may or may not reach their original destination. Hypersensitivity is often a sign of that regrowth, unpleasant but frequently a phase rather than a destination.
What tips the odds toward preserved feeling? The same factors that protect milk supply: a pedicle that carries the key lateral nerves, a smaller distance the nipple has to move, and less total tissue removal. Free nipple grafting, discussed later, is the technique most closely associated with permanent numbness.
Erectile response of the nipple, the way it stiffens with cold or touch, follows a separate path through tiny muscle fibers and their nerves. It may return on a different schedule from skin sensation, or not at all. Asking your surgeon about each type of sensation separately gives a more useful picture than a single “will I feel it?”
Does nipple sensation come back after breast reduction, and roughly when?
For many people, partly or largely yes. For some, not fully. The timeline is measured in months, not weeks.
Guidance from Mayo Clinic and Cleveland Clinic frames sensory change after reduction as either temporary or permanent, with improvement continuing across the first year. Clinicians generally hesitate to label a change permanent before that point, because nerve regrowth is slow and continues quietly long after the scars have faded. Early numbness that starts to tingle is usually a good sign; it suggests nerves are reconnecting.
A rough shape of what people commonly describe, always with wide individual variation:
- The first days: swelling and dressings dominate, and most sensation is muted or absent around the nipple and lower breast.
- The first weeks: as swelling recedes, areas of feeling reappear. Some describe electric or itchy sensations along incision lines, which reflect healing nerve endings.
- The following months: gradual filling in of sensation, often uneven, sometimes with a period of hypersensitivity.
- Around a year: the pattern usually stabilizes, and what remains altered at that stage is more likely to stay that way.
Nothing here should be read as a promise. Someone whose nipple remained on a robust pedicle and moved a short distance has a different starting point from someone who needed a very large reduction. Age, smoking status and the presence of complications such as infection or poor blood supply to the nipple also play a role, which is why surgeons ask people who smoke to stop before surgery.
If sensation matters greatly to you, ask two things: which nerves the planned technique is designed to preserve, and how your surgeon documents and follows sensory recovery at review appointments so changes are tracked rather than guessed.
Who is usually offered a reduction, and who is asked to wait
Reduction is generally considered for people whose breast size causes physical symptoms: persistent neck, shoulder or back pain, indentations from bra straps, recurrent rashes or infections in the fold beneath the breast, difficulty exercising, or poor posture driven by weight on the chest. Mayo Clinic notes that the procedure can be done at any adult age, sometimes before breasts have fully developed when symptoms are severe, though most surgeons prefer to wait until growth has finished.
The NHS and Mayo Clinic both describe circumstances where a surgeon may recommend delaying. They matter here because several of them overlap directly with the breastfeeding question.
- Planning a pregnancy soon: pregnancy and lactation change breast size and shape, and many surgeons suggest completing childbearing first if breastfeeding is a priority, so that the operation does not interrupt ducts before they are ever used.
- Currently breastfeeding or recently weaned: surgeons usually wait until the gland has returned to its resting state, so that they operate on stable tissue.
- Planning significant weight loss: breast volume changes with body weight, and operating before the change can leave a result that later needs revision.
- Smoking: nicotine narrows small blood vessels and raises the risk of poor wound healing and loss of blood supply to the nipple; people are asked to stop well in advance.
- Uncontrolled diabetes, active infection or conditions that impair healing.
None of these are moral judgments; they are timing decisions aimed at a safer operation and a more durable result. Someone who wants both symptom relief now and breastfeeding later is not being unreasonable. Surgeons manage exactly that trade-off routinely by choosing a technique that preserves more tissue and nerve, accepting that the result may be slightly larger than the person first imagined.
The decision about timing sits with the treating team, weighed against the burden of living with symptoms for several more years.
Reduction techniques compared: what each tends to preserve
People often arrive at consultation having read about “the lollipop” or “the anchor.” Those names describe scar patterns, which are visible and easy to compare. For milk and sensation, the invisible decision, the pedicle, matters more. The table below summarizes typical tendencies described in surgical literature and in overviews from Mayo Clinic and Cleveland Clinic. It is a guide to questions, not a prediction for any individual.
| Approach | What stays attached to the nipple | Typical implications for milk ducts | Typical implications for sensation |
|---|---|---|---|
| Inferior pedicle | Column of tissue from the lower breast | Preserves central ducts beneath the nipple; widely used for larger reductions | Often keeps a portion of the lateral nerve branches |
| Superior or superomedial pedicle | Tissue from above or inner upper breast | Keeps duct tissue in the pedicle; more gland removed from lower pole | Variable; depends on how much lateral tissue is retained |
| Central pedicle | Direct column beneath the nipple | Retains the core of the duct system | Frequently cited as favorable for nerve preservation |
| Free nipple graft | Nipple removed and reattached as a skin graft | Ducts fully divided; breastfeeding generally not expected | Numbness usually permanent; pigment may fade |
Scar pattern, whether around the areola only, a vertical “lollipop,” or the inverted-T “anchor,” is chosen mostly by how much skin needs removing, and it can be combined with different pedicles. So two people with identical scars may have had very different internal operations, which is why comparing photos online tells you little about feeding or feeling.
Ask your surgeon which pedicle they intend, why it suits your anatomy, and what would make them change plan during surgery. Free nipple grafting is usually reserved for very large reductions where a long pedicle could not safely carry blood to the nipple; safety of the nipple’s blood supply outranks every other goal.
What the first days and weeks after surgery usually look like
The operation is done under general anesthetic and usually takes a few hours, according to the NHS. Some people go home the same day; others stay one night. What follows is a fairly predictable arc, described here as typical ranges rather than promises.
The first few days bring swelling, bruising and a feeling of tightness across the chest. Dressings cover the incisions, and a soft supportive bra is worn around the clock. Small drains are sometimes placed to remove fluid and are usually taken out within a few days. Pain is generally managed with medicines prescribed by the surgical team, and the plan for them belongs with that team.
The NHS advises that most people need a week or two off work and should avoid strenuous activity, heavy lifting and driving until cleared, with full recovery taking several weeks. Mayo Clinic gives similar guidance and notes that swelling can take longer to settle completely. Stitches are often dissolvable; where they are not, they are removed at a clinic visit.
Nipple appearance is closely watched during this stretch. Surgeons and nurses check color and warmth because a nipple that is losing blood supply changes color early, when action is still possible. A little crusting or a scab at the edge of the areola is common; darkening, dusky purple or black patches are not, and warrant a same-day call.
Sensation in these weeks is unreliable and should not be taken as the final result. Scars will look their worst before they look their best, typically reddening and thickening over the early months before slowly fading over a year or more. Supportive bras, sun protection for scars and following the specific activity timeline from your own team are the practical levers within your control.
Milk supply after breast reduction: what to expect and how it is assessed
Milk supply after breast reduction is often described as “partial,” and that word deserves unpacking. Some lobules still connect to the nipple and will drain normally. Others may have lost their exit. In the early days after birth those disconnected areas fill, become firm, and then quiet down over a week or two as the body reabsorbs milk that cannot leave. The connected areas keep going. The result can be anything from a full supply to a modest one, and it is not knowable in advance.
Assessment is the job of the postnatal team, midwife, health visitor, pediatrician or lactation consultant, and it rests on the baby rather than the breast. Weight trajectory is the anchor: newborns commonly lose a little weight in the first days and are expected to regain it over the following weeks, and a plotted growth chart is more informative than any single weigh-in. Alongside weight, clinicians look at the pattern of wet and dirty diapers, the baby’s alertness and settled behavior after feeds, and audible swallowing at the breast. Feeling “empty” or having soft breasts is not itself a sign of low supply and is a frequent source of unnecessary worry.
If supply turns out to be limited, the usual approaches are frequent, effective milk removal, since supply responds to demand, and supplementing with expressed milk or formula in a way that keeps the baby at the breast. Some people use an at-breast supplementer, a thin tube that delivers extra milk while the baby suckles, so that stimulation and bonding continue. Whether supplementation is needed, how much, and for how long are clinical decisions made with the feeding team based on the baby’s growth.
Partial breastfeeding is still breastfeeding. Any breast milk offers benefits, and a plan built around what the body can do tends to last longer than one built around an all-or-nothing goal.
Free nipple graft and breastfeeding: the exception that needs plain talk
Most of this article assumes the nipple stayed attached. A free nipple graft is different. Here the surgeon removes the nipple and areola entirely, reduces and reshapes the breast, and then places the nipple back onto its new position as a skin graft, where it heals by growing new tiny blood vessels from the tissue beneath.
Because every duct and every nerve to the nipple is divided, breastfeeding is generally not expected afterwards. Small amounts of milk may occasionally form in remaining gland tissue, but without a duct pathway it has no reliable route to the baby, and the nerve signal from suckling that would normally boost prolactin is absent. Sensation is usually permanently reduced or lost, and the grafted skin can lose some of its pigment and its ability to become erect. These are consistent findings in surgical overviews, including those from Cleveland Clinic, which list difficulty breastfeeding and altered sensation as more likely with this method.
Why would anyone choose it? Usually nobody chooses it in the abstract. It is used when the breast is so large that a pedicle long enough to carry the nipple to its new position would be too thin to keep it alive. In that situation, a graft that heals reliably is safer than a pedicle that might fail and cost the nipple altogether. Surgeons may also consider it when other health factors make blood supply precarious.
If you are told a free graft is likely, it is entirely fair to ask whether a staged approach, a slightly larger final size or a different pedicle design could keep the nipple attached, and to hear the reasoning. It is also fair to decide that symptom relief outweighs future breastfeeding. Either way, the choice should be made with full knowledge, before the operation rather than discovered afterward.
Preparing to breastfeed after breast reduction: what genuinely helps
Preparation begins before the surgery, continues through pregnancy, and pays off in the first hours after birth. Little of it is glamorous; most of it is communication.
Before surgery, say the words out loud: “I would like to breastfeed in the future.” Ask for it to be documented, and ask which technique the surgeon plans as a result. Request that your operative report, the surgeon’s written account of exactly what was done, be available to you afterwards. Years later, a lactation consultant reading it will learn far more from “superomedial pedicle, moderate resection” than from your memory of the scars.
During pregnancy, tell the midwife or obstetric team about the surgery early. Breast changes in pregnancy, such as increased fullness and darkening of the areola, are reassuring signs that gland tissue is responding to hormones. Their absence is not proof of a problem but is worth mentioning. Arranging to meet a lactation professional before the birth means the plan is ready rather than improvised at three in the morning.
After birth, the priorities are the same as for anyone, only more deliberate: skin-to-skin contact soon after delivery, feeding early and often, and paying attention to the baby’s latch. Because nipple sensation may be reduced, some people do not feel the usual cues that the baby is latched poorly, so a trained eye watching a few feeds is especially valuable. Hand expression in the first days, which staff can teach, helps establish supply and reveals which parts of the breast are draining.
Finally, set expectations with the people around you. Partners and relatives who understand that supplementing may be part of the plan are less likely to frame it as failure. The measure of a good outcome is a thriving baby and a parent who felt supported, not a particular number of milliliters.
What people often get wrong
Myths cluster around this topic, partly because the honest answer is “it depends,” and “it depends” travels badly online. A few worth correcting.
“Breast reduction means you can never breastfeed.” Not so. The systematic review evidence shows many women breastfed after reduction, particularly when the nipple stayed on a pedicle. The realistic caveat is that exclusive breastfeeding is less common, not that feeding is impossible.
“If the scar is small, the damage is small.” Scar pattern reflects how much skin was removed, not how the nipple was carried or how much gland came out. Two identical scars can hide very different operations.
“Numbness at six weeks means it is permanent.” Nerve recovery continues for months, and surgical guidance describes improvement across the first year. Early tingling or hypersensitivity is often a sign of regrowth, not a complication.
“Leaking milk after surgery years later means something is wrong.” Small amounts of discharge can occur for various reasons and should be checked, but leaking during a later pregnancy is a normal sign that gland tissue is working.
“Milk supply can be tested before pregnancy.” There is no reliable pre-pregnancy test of lactation capacity. Imaging can show tissue but cannot show whether ducts will carry milk under hormonal stimulation.
“A larger reduction is always better value.” Removing more tissue generally raises the risk to ducts and nerves. A surgeon suggesting a slightly larger final size to protect function is offering a trade-off, not being timid.
“Herbal supplements will restore supply.” Evidence for herbal galactagogues, substances claimed to increase milk, is limited and inconsistent, and some interact with other medicines. Frequent milk removal has far stronger support. Anything taken during lactation should be discussed with the prescribing clinician or pharmacist first.
Questions to ask your care team
A consultation moves quickly, and the questions that matter most for feeding and sensation are rarely the ones a surgeon raises first. Bringing a written list changes the conversation. These are phrased so you can use them directly.
- Which pedicle technique do you plan for me, and why does it suit my anatomy?
- How far will my nipple need to move, and does that distance affect the chance of preserving ducts and nerves?
- Is there any chance you would need to convert to a free nipple graft during the operation? What would prompt that decision?
- If I tell you breastfeeding is a priority, how does that change the plan, including the likely final size?
- Which sensory nerves does this approach aim to preserve, and how will we track sensation at follow-up?
- What signs of poor nipple blood supply should I watch for in the first days, and who do I call?
- Can I have a copy of my operative report to share with a lactation consultant later?
- How long do you suggest waiting after surgery before planning a pregnancy?
- What is your advice on smoking, weight stability and other factors before surgery?
- If breastfeeding proves limited, who in the postnatal team can help me build a partial-supply plan?
For the maternity side, once pregnant, add: does my history of reduction change how you will monitor early feeding, and can I meet a lactation specialist before the birth?
Notice what the list does not include: any question about guarantees. Surgeons cannot give them, and one who does is overpromising. The most useful answers describe reasoning and contingency. Write those down, because the details fade quickly and matter later. Every decision, from technique to timing to how feeding is supported, remains with your surgical and postnatal teams, informed by what you tell them you value.
When to call your doctor
Two periods deserve particular vigilance: the first weeks after reduction surgery, and the early weeks of breastfeeding later on. In both, calling early is better than waiting to see.
After surgery, contact your surgical team the same day, or seek urgent care if you cannot reach them, for any of the following:
- A nipple or areola that turns dusky, purple, very pale or black, or feels cold compared with the other side; this may signal compromised blood supply.
- Rapid, one-sided swelling, especially if tense, painful and bruised, which can indicate bleeding under the skin.
- Spreading redness, increasing pain, warmth, pus or a foul smell from an incision, or a fever.
- Wound edges that open or skin that darkens along the incision lines.
- Calf pain or swelling, chest pain or sudden breathlessness, which can be signs of a blood clot and are emergencies.
During breastfeeding, the NHS describes mastitis, inflammation of breast tissue that may become infected, as a red, hot, swollen and painful area often with flu-like symptoms. Contact a clinician promptly if symptoms do not begin to ease within a day or two of frequent feeding and rest, if you develop a fever or feel unwell, if there is a firm lump that persists, or if you notice pus or blood in your milk. A previous reduction does not cause mastitis, but areas that drain poorly may be more prone to blockage, so know the signs.
For the baby, seek same-day advice if there are fewer wet diapers than expected for age, dark urine or brick-dust staining beyond the first days, persistent sleepiness with reluctance to feed, jaundice that is deepening, or weight loss the team considers excessive. These are the signals clinicians use to judge whether supply is adequate, and they are far more reliable than how your breasts feel.
Bring your surgical history to every one of these conversations. It shapes how your team interprets what they see.
Frequently asked questions
Can you breastfeed after breast reduction?
Often yes, at least partially. Research summarized in a PLoS One systematic review found that many women breastfed after reduction mammaplasty, though exclusive breastfeeding was less common than in those without surgery. The outcome depends on how much gland remained, whether ducts stayed connected to the nipple, and whether nerve supply was preserved. Techniques that keep the nipple on a pedicle give the better chance; free nipple grafts generally do not.
Does nipple sensation come back after breast reduction?
For many people it improves substantially, though not always to exactly how it felt before. Mayo Clinic and Cleveland Clinic describe altered sensation as either temporary or permanent, with recovery continuing over the months after surgery. Early numbness that begins to tingle is usually a sign of nerve regrowth. Clinicians typically wait around a year before considering a remaining change permanent. Technique, reduction size and smoking status all influence the result.
How long after breast reduction should I wait before getting pregnant?
There is no universal number, and the timing decision sits with your surgeon. Most advise letting the breasts heal fully and scars mature, which the NHS describes as taking several weeks for general recovery and a year or more for scars to settle. Waiting longer may also allow some divided ducts to reconnect. Ask your surgeon for their specific recommendation based on your operation, and tell your maternity team about the surgery early.
What is milk supply after breast reduction usually like?
It ranges from full to modest and cannot be predicted before birth. Gland tissue still connected to the nipple produces and drains milk; areas whose ducts were cut fill briefly, then quiet down. Adequacy is judged by the baby, through weight gain, diaper output and behavior after feeds, not by how full the breasts feel. If supply is limited, frequent milk removal and planned supplementation, ideally at the breast, are the usual approaches.
Is free nipple graft breastfeeding ever possible?
It is generally not expected. A free nipple graft removes and reattaches the nipple as a skin graft, dividing all ducts and nerves. Remaining gland may make small amounts of milk, but there is no reliable duct pathway to the baby and no nerve-driven hormonal response to suckling. Surgeons reserve the technique for very large reductions where a pedicle could not safely keep the nipple alive, prioritizing its survival over function.
Will my nipples be hypersensitive after surgery, and is that normal?
Hypersensitivity, tingling or electric sensations are common during recovery and often reflect nerves reconnecting rather than a problem. Many people find soft fabrics or a light silicone pad over the nipple helps in the interim. It usually eases over the following months. Report it at follow-up so your team can track it, and seek advice sooner if it is accompanied by redness, discharge, color change or increasing pain.
Does the scar pattern, anchor or lollipop, affect breastfeeding?
Not directly. Scar pattern reflects how much skin was removed and is separate from the pedicle, the internal tissue column that carries ducts and nerves to the nipple. Two people with identical scars may have had different pedicles and very different amounts of gland removed. When asking about future breastfeeding, focus on the pedicle design, the distance the nipple will move and the amount of tissue removed.
Can any test before pregnancy tell me whether I will produce milk?
No reliable test exists. Imaging can show how much breast tissue remains but cannot show whether ducts will carry milk under the hormonal stimulation of pregnancy. Signs during pregnancy, such as breast growth, tenderness and areolar darkening, are encouraging but not definitive. The real test is the early postnatal period, which is why meeting a lactation professional in advance and having your operative report available are the most useful preparations.
Are there medicines that increase milk supply after breast reduction?
Some prescription medicines are used off-label as galactagogues because they raise prolactin, the hormone that drives milk production, and some herbal products are marketed for the same purpose. Evidence for both is limited and mixed, and frequent, effective milk removal has stronger support. Any decision about medicines during lactation, including whether they are appropriate for you, rests with the prescribing clinician, who will weigh potential benefits against side effects.
Does a previous reduction make mastitis more likely when breastfeeding?
The surgery itself does not cause mastitis, but areas of the breast that drain poorly because ducts were divided may be more prone to blockage, which is one route to inflammation. The NHS describes mastitis as a hot, red, swollen, painful area often with flu-like symptoms. Frequent feeding, varied positions and prompt attention to firm areas help. Contact a clinician if symptoms do not ease within a day or two or you develop a fever.
References
- NHS: Breast reduction (female)
- MedlinePlus: Breast reduction
- PubMed: The impact of breast reduction surgery on breastfeeding: Systematic review of observational studies (PLoS One)
- NHS: Mastitis
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Breast Lift (Mastopexy) After Pregnancy and Breastfeeding: When Timing Makes Sense
A breast lift after pregnancy (mastopexy) can reposition breasts that have descended after childbirth and breastfeeding, but timing matters. Surgeons generally ask that breastfeeding…

Breast Reduction Recovery: Timeline, Support Garments and Returning to Daily Life
Most people need one to two weeks off work after breast reduction surgery, about six weeks before strenuous exercise or heavy lifting, and several…

How Breast Fat Transfer Is Done: Liposuction, Fat Purification and Layered Injection
A fat transfer breast augmentation procedure moves a person's own fat from one body area to the breasts in three stages: liposuction removes fat…
Breast Augmentation Before Future Pregnancies: Breastfeeding, Changes and Planning Timing
Having breast augmentation before pregnancy is medically possible, and most people with implants can later carry a pregnancy and breastfeed. The trade-off is unpredictability:…

Recovery After Breast Fat Transfer: Healing Two Areas, Garments and Sleeping Positions
Fat transfer breast recovery means healing two areas at once: the breasts that received the fat and the liposuction donor site. Most people return…

After Gynecomastia Surgery: Swelling That Is Expected vs Fluid Build-Up That Needs a Check
After gynecomastia surgery, soft, symmetric swelling and bruising across both sides of the chest are expected and usually settle over several weeks. Fluid build-up…