

Earwax Removal: Safe Methods, the Cotton-Bud Problem and Why Ear Candling Is Dangerous
Key Takeaways
- The ear canal moves wax outward at roughly the speed a fingernail grows, so an ear that hears normally and feels comfortable does not need cleaning inside.
- In the 2018 Cochrane review of ten randomised trials, plain water or saline cleared wax about as well as oil or commercial carbamide peroxide drops, with low-certainty evidence overall.
- Cotton buds are wider than the deep ear canal, so each swab compacts wax against the eardrum, which is how most impactions are manufactured at home.
- Ear candles burned over a bowl leave the same brown residue as those burned over an ear, and regulators have documented burns, perforations and candle wax lodged in the canal.
- Clinic irrigation uses body-temperature water along the canal wall; microsuction uses no water, which is why it is preferred for anyone with a perforation, ear tubes or previous surgery.
- Sudden hearing loss that does not clear within hours needs same-day assessment, because inner-ear hearing loss is treated very differently from a wax plug.
Earwax removal is rarely necessary because the ear canal cleans itself, but when wax blocks hearing or causes discomfort, the safest home approach is softening drops such as olive oil, almond oil, saline or carbamide peroxide used as the package directs for several days. Cotton buds push wax deeper, and ear candling has no proven benefit and causes burns and eardrum injuries. Persistent blockage, pain, discharge or sudden hearing loss needs a clinician.
Scroll for sixty seconds on any short-video app and you will meet a tiny camera travelling down an ear canal, a satisfying plug of amber wax lifted out by suction, and, a few swipes later, a hollow candle burning above someone’s head. Those clips are why earwax removal is one of the most searched ear-health phrases right now. As of June 2025, ear-cleaning videos rack up billions of views, and ear candling, a practice regulators have warned about for over a decade, has found a second life as wellness content.
The irony is that the ear canal is one of the few body parts that genuinely cleans itself. Most people never need to remove wax at all. The small group who do, roughly 1 in 20 adults and more than 1 in 3 older adults with troublesome build-up, deserve clear, evidence-based advice rather than a viral trick.
This piece sorts the methods that work from the ones that merely look impressive, explains why the humble cotton bud causes so much trouble, and gives you a plain checklist of when to stop experimenting and book an appointment.
What changed recently in earwax removal advice
Three shifts explain the current wave of interest, and none of them is a miracle product.
First, the videos. Microsuction, which means removing wax with a fine vacuum tube under a microscope or camera, photographs beautifully, and clinics worldwide now film routine procedures for social media. That has normalised the idea that wax is dirt to be hunted, which is not how ear specialists see it.
Second, guideline language has tightened. The 2017 update to the American clinical practice guideline on earwax impaction, the version still referenced by Mayo Clinic and Cleveland Clinic patient pages, made two points explicit: clinicians should not remove wax that is not causing symptoms, and patients should be told to avoid both cotton buds and ear candles. The NHS followed a similar path. Since the 2018 NICE hearing-loss guidance in England, many general practices stopped offering traditional syringing, and the NHS now steers people toward softening drops first and professional irrigation or microsuction only when drops fail.
Third, the evidence base was formally graded. A 2018 Cochrane review, indexed in PubMed, pooled ten randomised trials of ear drops involving about 600 participants and concluded that softening drops probably help clear wax but that no single product, including plain water or saline, is clearly better than another. The authors rated the overall certainty as low.
The United States Food and Drug Administration had already issued a consumer warning about ear candles in 2010, citing burns, perforated eardrums and candle wax lodged in the canal. Nothing since has reversed that position. So what changed is not the science. What changed is that millions of people are now watching, and asking.
What earwax is and why your ear canal is self-cleaning
Earwax has a clinical name, cerumen, and a job description. It is a blend of dead skin cells, hair, and secretions from two sets of glands in the outer third of the ear canal. The mixture is slightly acidic, mildly water-repellent and faintly antimicrobial, which is why MedlinePlus describes it as protective rather than dirty.

The canal itself is only about 2.5 centimetres long, roughly the length of a paperclip, and it has an elegant maintenance system. The skin lining it grows outward from the eardrum toward the opening, carrying wax with it at about the speed a fingernail grows. Chewing and talking move the jaw joint, which sits just in front of the canal, and that gentle massage nudges old wax toward the exit, where it dries, flakes and falls out unnoticed.
Two genetically determined types exist. Wet wax, honey-coloured and sticky, is common in people of European and African ancestry. Dry wax, grey and flaky, is more typical in East Asian populations. Neither is healthier, and colour alone says little about infection. Darker, harder wax usually just means older wax.
Why does the system fail for some people? Narrow or hairy canals, eczema or psoriasis of the ear skin, frequent earplug or earbud use, and hearing aids that block the natural outward flow all raise the odds of build-up. Age matters too. Wax glands shrink and secretions become drier with time, which is one reason older adults are disproportionately affected.
The practical lesson is simple and often ignored: an ear that hears normally and feels comfortable does not need cleaning inside the canal. Washing the outer ear with a flannel is the entire routine most people require.
How do you know earwax has become a problem?
Impaction is the medical term for wax that has accumulated enough to cause symptoms or stop a clinician seeing the eardrum. It rarely announces itself dramatically. More often it creeps in.
The classic signs, as listed by the NHS and Mayo Clinic, are a feeling of fullness or pressure, muffled or reduced hearing in one ear, earache, itching, ringing or buzzing (tinnitus), and sometimes a mild dizziness. A cough with no chest symptoms can also occur, because a nerve branch in the ear canal shares a pathway with the throat.
Here is an underappreciated pattern: symptoms often appear suddenly after a shower or swim. Water swells a wax plug that was sitting quietly, the canal closes completely, and hearing drops within minutes. People understandably fear a stroke or an infection. Usually it is wax, but sudden hearing loss should still be checked promptly, because true sudden sensorineural hearing loss, which is an inner-ear problem, is an emergency that is treated very differently.
Hearing aid users deserve a special mention. Wax clogs the receiver, muffles the output, and causes feedback whistling. An audiologist or hearing aid provider often spots impaction before the wearer notices anything.
What impaction is not: it is not usually a cause of fever, severe pain, or discharge. Those point toward infection of the outer canal (otitis externa, often called swimmer’s ear) or of the middle ear behind the eardrum. Trying to clear wax from an infected ear tends to make things worse, which is why the symptom pattern matters before you reach for anything.
How to clean ear wax safely at home with softening drops
If you have the muffled, blocked sensation and no red flags, the method every mainstream source agrees on is softening. The aim is to loosen the plug so the ear’s own transport system, or a gentle rinse, can finish the job.
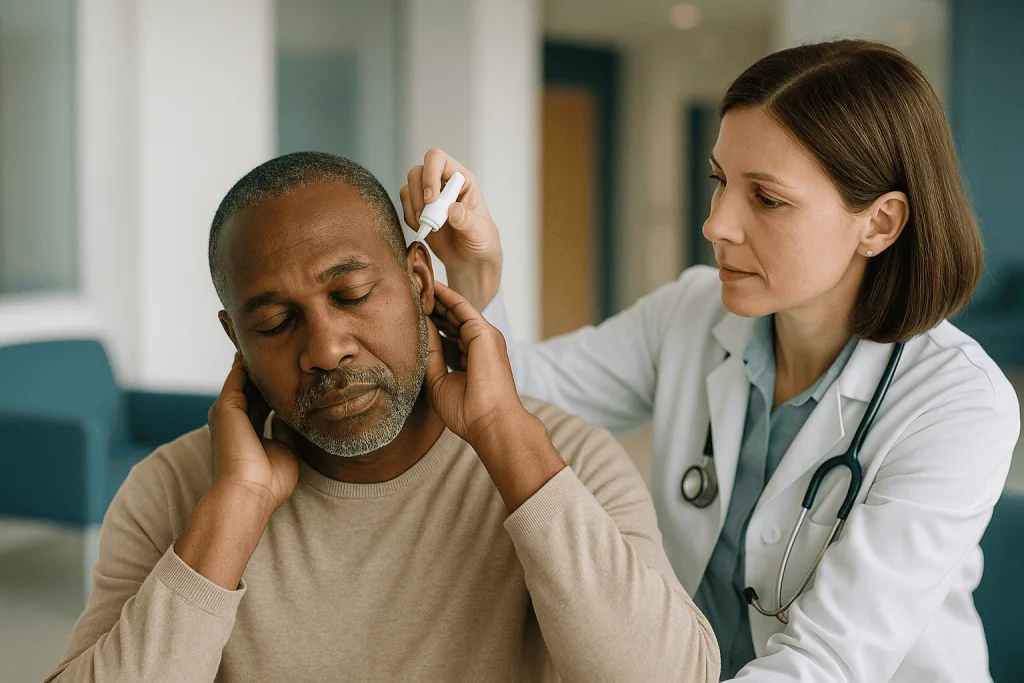
Common options fall into three families. Oil-based drops include olive oil, almond oil and mineral oil. Water-based drops include saline, sodium bicarbonate solution, and dilute hydrogen peroxide. Peroxide-based commercial drops contain carbamide peroxide, a compound that releases oxygen bubbles and helps break wax apart.
The technique is the same whatever you choose. Warm the bottle in your hands so the liquid is close to body temperature; cold drops can trigger brief dizziness. Lie on your side with the affected ear up, let the drops in as the label directs, and stay there a few minutes before sitting up and letting the excess run onto a tissue. Repeat as the product label advises, typically for several days. Avoid plugging the ear with cotton afterwards; it wicks the drops straight back out.
The NHS suggests giving drops time, generally up to a couple of weeks for stubborn wax, before concluding they have failed. The wax may fall out as a crumbly plug, or the ear may simply clear quietly overnight. Hearing can feel briefly worse during treatment, because softened wax expands before it moves. That is expected, not a sign of harm.
What not to use: anything not formulated or recommended for ears, hot liquids, and never any object inserted into the canal. If your ear has ever had a perforation, surgery or grommets (small ventilation tubes placed in the eardrum), skip home drops entirely until a clinician has looked.
Can baby oil be used to remove earwax?
Baby oil is essentially mineral oil with fragrance, and mineral oil appears on several mainstream lists of acceptable earwax softeners, including those published by MedlinePlus and Mayo Clinic. So the short answer is that plain mineral oil can be used as a softening agent in an ear with an intact eardrum, but it is not more effective than other options and it carries two small caveats.
The first caveat is fragrance. Scented baby oil contains additives that some ear-canal skin finds irritating, particularly in people with eczema. If you want an oil, a plain, unscented pharmacy mineral oil or culinary olive or almond oil is the more conservative choice. The second caveat is nut allergy: almond oil is not appropriate for anyone allergic to tree nuts.
Does oil actually work better than water? The honest answer from the 2018 Cochrane review is that it probably does not. Trials comparing oil-based drops, water-based drops and commercial products found no convincing winner, and in some comparisons plain water or saline performed as well as anything else. Oil has one practical advantage: it is gentle, lubricating and unlikely to sting, which matters for repeated use in dry, itchy ears. Its disadvantage is that it does not dissolve wax so much as soften its edges, so it may need more days to show results.
Many clinics ask patients to use oil for several days before an irrigation or microsuction appointment because softened wax comes out faster and with less discomfort. That is the most evidence-aligned role for baby oil: preparation, not a standalone miracle.
If you have used oil for two weeks and the ear is still blocked, more oil is not the answer. That is the moment to be seen.
How to use an over-the-counter earwax removal kit safely
Most pharmacy earwax kits contain carbamide peroxide drops and a soft rubber bulb syringe. Carbamide peroxide is a compound that slowly releases hydrogen peroxide and oxygen when it meets moisture, so the fizzing you hear is chemistry, not infection, and the bubbles mechanically loosen the wax.
The kit instructions, not this article, govern how many drops and how often. The general sequence is consistent across brands, and worth understanding so you do not improvise.
- Use the drops exactly as the package insert states, lying with the ear up, for the number of days specified.
- Only then, if the kit includes a bulb syringe, rinse gently with lukewarm water, aiming the stream toward the canal wall rather than straight at the eardrum.
- Tilt the head to let water and loosened wax drain, and dry the outer ear with a towel.
Several groups should not use these kits without medical advice, and the labels say so: anyone with ear pain, drainage, a known or suspected perforated eardrum, ear tubes, recent ear surgery, or a history of recurrent outer-ear infection. Diabetes and conditions that weaken the immune system also raise the risk of a serious outer-ear infection after irrigation, so a clinician’s assessment is wise first.
Side effects are usually mild: temporary crackling, warmth, brief dizziness from cool water, and a day or two of itch. Sharp pain, bleeding or sudden worsening of hearing means stop and seek care.
A final honest point about effectiveness. Because the evidence base does not show commercial drops outperforming saline or oil, the main advantage of a kit is convenience. Choose it if the format suits you, not because the packaging promises more.
The cotton-bud problem: why swabs make earwax worse
Cotton buds are the single most common cause of the problem they are meant to solve, and the mechanism is almost embarrassingly simple. The bud is wider than the deep ear canal. When it goes in, it scrapes a little wax off the walls and compacts the rest into a dense plug against the eardrum, beyond the reach of the ear’s natural outward conveyor belt. Repeat that daily and you manufacture impaction.
Clinicians describe a recognisable picture: a shiny, scoured outer canal and a wall of hard wax deep inside, often with a few cotton fibres embedded in it. The person feels clean and hears worse.
The second harm is injury. The canal skin is thin and sits directly on bone; a swab scratches it easily, and scratches invite infection. Deeper still, the eardrum is a membrane about the thickness of a sheet of paper. A slip, a child bumping an elbow, or simply pushing too far can perforate it. Emergency department data from the United States have for years listed cotton-tip applicators as a leading cause of ear injury in children, with most incidents happening at home during cleaning.
The third harm is the itch cycle. Swabbing strips the protective, slightly acidic wax layer, the skin dries and itches, the person swabs again for relief, and the canal becomes raw and prone to otitis externa.
What about the earbud-like metal and plastic picks, spiral tools and camera-tipped scoops sold online? Mainstream sources treat them the same way as swabs: anything inserted into the canal by an untrained hand risks compaction and injury. The outer ear, the part you can see, can be wiped with a damp cloth. Beyond that, the ear is not a place for tools.
Why ear candling is dangerous and does not remove earwax
Ear candling involves inserting the narrow end of a hollow, wax-coated fabric cone into the ear canal and lighting the other end, on the theory that warm air and gentle suction draw out wax, toxins and even sinus debris. It is centuries old in various forms and currently thriving on video platforms. It does not work, and it causes real harm.
Start with the physics. Measured pressure inside a burning ear candle is negligible, nowhere near enough to lift wax that is adherent to the canal skin. Studies that burned candles over a model ear and over no ear at all found the same brown, waxy residue inside the cone either way. The residue that practitioners show clients is candle wax and soot, not cerumen. Several laboratory assessments also found that candling deposited candle wax into the canal rather than removing anything.
Then the injuries. The United States Food and Drug Administration warned consumers in 2010 after reports of burns to the face, ear canal and eardrum, perforated eardrums, canal blockage with candle wax that required surgical removal, and hot wax dripping onto the eardrum. There are case reports of hair and clothing catching fire. Children are at particular risk because they move unpredictably.
Regulators in Canada have gone further, stating that ear candles have no proven medical benefit and are not authorised for sale as medical devices. Mayo Clinic and Cleveland Clinic both list ear candling among the things never to do.
Why does the practice persist? Candling feels relaxing, the warmth is pleasant, and the residue looks convincing. Those are powerful sensory arguments. The evidence, though, is one-sided: no demonstrated benefit, documented and sometimes permanent harm. Among all the methods in this article, ear candling is the only one with no safe version.
What happens at an earwax removal appointment?
If drops fail or you are in a group that should not self-treat, a clinician has three main tools. Each has a distinct feel, and knowing what to expect takes the anxiety out of the visit.
The appointment starts with otoscopy, meaning a lit magnifying scope is used to look into the canal. This confirms wax is the problem, checks the eardrum where visible, and rules out infection or a foreign object. If the eardrum cannot be seen and there is any doubt about its integrity, the clinician will choose a method that does not rely on water.
Irrigation, the modern replacement for old-fashioned syringing, uses an electronic pump to send a controlled, body-temperature stream of water along the canal wall. The wax floats out into a basin held under the ear. It feels odd and noisy, like a waterfall inside your head, and it is over in a minute or two per ear. Softening drops beforehand make it far more likely to succeed on the first attempt.
Microsuction uses a fine suction tube under a microscope or endoscope. There is no water, so it is the preferred method for people with perforations, tubes, previous ear surgery or infection. It is loud, with a crackling, hoovering sound, but precise, and the clinician can see exactly what is being removed.
Manual removal uses small instruments, a curette (a tiny loop or scoop) or forceps, under direct vision. It suits hard, dry plugs near the canal opening.
Afterwards the clinician looks again, checks the eardrum, and advises on preventing recurrence. Many people are startled by how loud the world sounds for the first hour. That is normal.
Earwax removal methods compared at a glance
The table below gathers what the mainstream sources say about each approach, including how strong the supporting evidence is. It is a summary, not a prescription; who should use what depends on the state of the eardrum, which only an examination can confirm.
| Method | How it works | Evidence for effectiveness | Main risks | Who should avoid it |
|---|---|---|---|---|
| Oil drops (olive, almond, mineral) | Softens and lubricates wax | Randomised trials, low certainty; similar to other drops | Irritation from fragrance; nut allergy | Known or suspected perforation, tubes |
| Water-based drops (saline, bicarbonate) | Hydrates and disintegrates wax | Randomised trials, low certainty; comparable to commercial drops | Mild stinging | Perforation, active infection |
| Carbamide peroxide drops | Releases oxygen bubbles that break up wax | Randomised trials, low certainty; no clear advantage over saline | Itch, crackling, brief dizziness | Pain, discharge, perforation, surgery |
| Clinic irrigation | Controlled water stream flushes softened wax | Widely used; observational data and expert consensus | Dizziness, rare perforation or infection | Perforation, tubes, prior surgery, otitis externa |
| Microsuction | Suction under magnification | Observational data and expert consensus; preferred when water unsafe | Noise, brief dizziness, rare skin trauma | Few; needs a skilled operator |
| Cotton buds and picks | Scrapes outer canal | No evidence of benefit | Compaction, perforation, infection | Everyone, inside the canal |
| Ear candling | Claimed suction from burning cone | Studies show no wax removed | Burns, perforation, candle wax in canal | Everyone |
Two patterns stand out. The first is that the softening drops cluster together: pick the one that suits your skin and your allergies rather than hunting for a superior formula. The second is that the two most-viewed methods on social media, home scooping and candling, sit at the bottom on both benefit and safety.
What the evidence actually says about earwax removal
Grading the evidence honestly means separating three tiers.
Tier one, randomised trials, covers softening drops. The 2018 Cochrane review identified ten trials, about 600 participants, comparing oil-based, water-based and commercial drops with each other, with placebo, or with no treatment. The headline: drops probably help clear wax better than doing nothing, but head-to-head comparisons showed no consistent winner, and plain water or saline matched commercial products in several trials. The reviewers graded certainty as low because trials were small, used different definitions of success, and often had design flaws. A small number of trials tested dropping water before irrigation and found it improved the chance of a successful first flush.
Tier two, observational data and expert consensus, covers clinic procedures. Irrigation and microsuction have not been pitted against each other in large randomised trials. Their use rests on decades of clinical experience, case series documenting complication rates, and guideline committee consensus. Complication rates for irrigation are low but not zero: dizziness is common and transient, perforation and infection are rare. Microsuction is favoured when the eardrum is compromised precisely because of expert opinion that avoiding water is safer, not because of a trial.
Tier three, evidence of harm, covers cotton buds and ear candling. Here the data are mostly injury registries and case reports, which cannot prove benefit or harm with certainty but do establish mechanisms and real-world frequency. For candling, controlled experiments burning candles over model ears add a rare piece of positive proof that nothing is removed.
The practical reading is unglamorous. Softening drops, almost any kind, for stubborn wax; professional removal when they fail; nothing inserted into the canal at home. The strength of that conclusion comes less from one landmark trial than from every tier pointing the same way.
Common myths about earwax that viral videos keep repeating
Myth: wax is dirt and a clean ear has none. Wax is a secretion with protective, lubricating and mildly antimicrobial roles. A canal with a thin, even film of wax is healthier than a scrubbed one, which is why aggressive cleaning leads to itch and infection.
Myth: the brown residue inside a burned ear candle came from the ear. Candles burned over a bowl, a table or a model ear produce the identical residue. It is melted candle wax and soot. Ear candling removes nothing and has caused documented burns and perforations.
Myth: cotton buds are fine if you are careful. The canal narrows beyond the part you can see and the bud is wider than that passage. Even a gentle swab pushes some wax inward. Over months that is how plugs form, and the tip only has to slip once to injure the eardrum.
Myth: hydrogen peroxide fizzing means infection is being killed. Peroxide and carbamide peroxide fizz on contact with any organic material, including healthy wax and skin. The bubbles are useful mechanically, but the sound tells you nothing about infection.
Myth: dark wax means infection. Dark, hard wax is usually old wax. Infection shows itself with pain, swelling, discharge and often a smell, not with colour alone.
Myth: everyone should have a professional ear clean once a year. Guidelines explicitly advise against removing wax that is not causing symptoms. Removal is treatment for a problem, not maintenance, and each unnecessary procedure carries a small risk.
Myth: more drops, more often, works faster. Softening is a slow process. Exceeding label directions does not speed it up and can irritate the canal. Give the recommended course its full time, then seek help if the ear remains blocked.
Is pain after earwax removal normal, and who should skip home methods
Mild discomfort for a day or two after irrigation or microsuction is common and expected. The canal skin has just been disturbed, possibly for the first time in years, and the eardrum is suddenly exposed to air and sound. People describe a raw, tender feeling, a sense of coolness, brief dizziness, and sometimes a dull ache. Hearing can seem uncomfortably loud until the brain readjusts.
What is not normal is pain that increases rather than fades, pain severe enough to disturb sleep, any discharge beyond a little water, bleeding, a new persistent ringing, or hearing that is worse after the procedure than before. Those can signal a scratch that has become infected, a perforation, or wax that was pushed rather than removed. Contact the clinic that performed the procedure, or another clinician, the same day.
Prevention of problems starts with knowing who should not attempt home removal at all. The NHS, Mayo Clinic and Cleveland Clinic lists overlap closely:
- Anyone with a known or suspected perforated eardrum, ear tubes, or previous ear surgery, because fluid can reach the middle ear.
- Anyone with current ear pain, discharge, or a recent outer-ear infection.
- People with diabetes or a weakened immune system, who face a higher risk of a severe outer-ear infection after irrigation.
- Anyone with hearing in only one ear, where the stakes of any complication are higher.
- Young children, whose canals are small and who cannot reliably report pain.
Hearing aid users are not excluded from softening drops but should ask their provider about drop timing, since oil can damage some devices if the aid goes back in too soon.
Aftercare is simple: keep the ear dry for a day or so if advised, do not insert anything, and let the new wax layer re-form. If your wax tends to recur, a clinician may suggest a periodic softening routine. That decision belongs to them, tailored to your ears.
When to see a doctor about earwax
Most blocked ears clear with patience and drops. A specific set of signs means you should stop home treatment and be examined, and a smaller set means you should be seen the same day.
Book a routine appointment if:
- Softening drops used as directed for up to two weeks have not relieved the blockage.
- You have had impaction before and recognise the same pattern returning.
- You wear hearing aids and notice feedback, muffled sound or reduced battery life, which often signal wax.
- You are in one of the groups that should not self-treat, including perforation, tubes, surgery, diabetes or immune suppression.
- A child has a persistently blocked or itchy ear; children should not be treated with home irrigation.
Seek care the same day, or urgently, if:
- Hearing drops suddenly and does not return within a few hours, particularly without a shower or swim beforehand, because sudden sensorineural hearing loss is time-sensitive.
- There is severe or worsening ear pain, fever, or swelling of the ear or face.
- Fluid, pus or blood is draining from the ear.
- You have vertigo, meaning the room spins, or persistent vomiting.
- Something has been inserted into the ear and you suspect injury, or an ear candle has been used and you feel pain or hear poorly.
- You notice facial weakness on the same side.
Expect the clinician to look first, treat second. Sometimes the finding is not wax at all: an infection, a skin condition, a foreign body, or fluid behind the eardrum can mimic blockage, and each calls for different care. Any decision about drops, irrigation, microsuction or follow-up rests with the clinician who has actually seen your eardrum. Their advice overrides any general guidance, including this article.
Frequently asked questions
How do you clean ear wax at home safely?
Wipe only the outer ear with a damp cloth and leave the canal alone unless it feels blocked. If it does, use softening drops such as olive oil, saline or carbamide peroxide as the label directs, lying with the ear up, for several days. Never insert cotton buds, picks or candles. If two weeks of drops have not cleared the ear, or you have pain or discharge, see a clinician for irrigation or microsuction.
Is it normal to have pain after having ear wax removed by a doctor?
Mild tenderness, a raw feeling, brief dizziness and oversensitivity to sound for a day or two are normal after irrigation or microsuction. Pain that worsens, keeps you awake, or comes with discharge, bleeding, new ringing or reduced hearing is not normal and can signal infection, a scratch or a perforation. Contact the clinic or another clinician the same day if that happens.
How do you use an over-the-counter earwax removal kit?
Follow the package insert exactly for the number of drops and days; this article does not replace it. In general you apply carbamide peroxide drops lying with the ear up, wait a few minutes, and repeat for the stated period before gently rinsing with lukewarm water using the bulb syringe if one is included. Do not use a kit if you have ear pain, discharge, a perforated eardrum, ear tubes or recent surgery.
Can baby oil be used to remove earwax?
Plain mineral oil, which is what baby oil mostly is, appears on mainstream lists of acceptable wax softeners for ears with an intact eardrum. Fragrance in scented baby oil can irritate sensitive canal skin, so unscented mineral, olive or almond oil is a gentler choice. Trials show oil works about as well as water or commercial drops, and it is most useful as preparation before professional removal.
Is ear candling safe if done by a trained practitioner?
No. Ear candling has no demonstrated benefit regardless of who performs it, and the risks come from the method itself: burns to the face and canal, perforated eardrums, and candle wax deposited inside the ear that sometimes needs surgical removal. Regulators in the United States and Canada have warned against it. Mainstream medical sources list it among practices to avoid entirely.
Does ear candling actually pull wax out of the ear?
No. Measurements show the burning candle produces negligible suction, far too little to move wax stuck to the canal skin. The brown residue found inside a used candle appears whether it is burned over an ear, a bowl or open air, because it is melted candle wax and soot. Laboratory tests have found candling leaves candle wax in the canal rather than removing cerumen.
Why is hearing worse after using earwax drops?
Softening drops make the plug swell before it breaks up, so a partially blocked ear can briefly become fully blocked. This is expected and usually passes within a few days as wax loosens and moves out. If hearing stays worse after the full labelled course, or if pain or discharge develops, stop and see a clinician rather than adding more drops.
How often should earwax be removed?
Only when it causes symptoms such as blocked hearing, fullness, itch or hearing aid problems. Guidelines advise against removing wax that is not troubling you, because the wax is protective and every procedure carries a small risk. Some people prone to recurrent build-up are advised a periodic softening routine, but that schedule should come from the clinician who has examined their ears.
Can earwax cause dizziness or tinnitus?
Yes, a wax plug pressing on the eardrum can cause mild dizziness, ringing or buzzing, and a feeling of imbalance, and these often ease once the wax is removed. True spinning vertigo, persistent vomiting, or tinnitus with sudden hearing loss points to inner-ear causes rather than wax and should be assessed urgently rather than treated with drops.
Why do GP practices no longer offer ear syringing?
Traditional metal-syringe flushing carried a higher risk of perforation and infection than modern methods, and in England guidance since 2018 steered care toward softening drops first, then electronic irrigation or microsuction. Many practices stopped syringing as a result. The NHS now advises using drops for a couple of weeks and seeking professional removal only if they fail.
References
- NHS: Earwax build-up
- Cleveland Clinic: Earwax buildup and blockage
- MedlinePlus Medical Encyclopedia: Ear wax
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Eye Vitamins and Lutein: What the AREDS Trials Actually Showed
The AREDS trials showed that a specific antioxidant and zinc formula modestly slows progression in people who already have intermediate age-related macular degeneration, and…
Electric Toothbrushes, Water Flossers and Floss: What Dental Trials Show
Randomized trials pooled in a Cochrane review found that electric toothbrushes remove modestly more plaque and reduce gum inflammation slightly more than manual brushes,…

Receding Gums: Causes, Whether They Grow Back and the Treatments That Help
Receding gums happen when gum tissue pulls away from a tooth and exposes more of its root, most often because of gum disease, aggressive…

Swimmer’s Ear: Causes, Treatment and Prevention
Swimmer's ear (acute otitis externa) is an infection of the skin lining the outer ear canal, usually caused by bacteria that multiply when water,…