

Epidural Steroid Injections: What to Expect, What They Can and Cannot Fix
Key Takeaways
- Relief typically begins 2 to 7 days after the injection, not immediately, any instant improvement is the numbing medicine, which wears off the same day.
- The best evidence supports these injections for leg-dominant nerve pain like sciatica; results for pain centered in the back itself are far less consistent.
- Studies suggest roughly half to three-quarters of well-selected patients get meaningful short-term relief, with benefits clearest in the first weeks to about three months.
- You only need to take it easy for about 24 hours afterward; most people return to normal light activity the next day, and gentle walking helps rather than hurts.
- Physicians generally cap injections at three to four per year because cumulative corticosteroid exposure can affect bone density and blood sugar.
- A headache after the procedure that worsens when upright and eases lying flat occurs in roughly 1 percent of cases and warrants a same-day call to your care team.
An epidural steroid injection delivers anti-inflammatory medicine into the space surrounding irritated spinal nerves, most often to calm leg or arm pain from a herniated disc or spinal stenosis. Relief usually begins within about a week and commonly lasts from several weeks to a few months. The injection does not repair the underlying problem; evidence supports it mainly as short-term relief, ideally paired with physical rehabilitation.
By the third week of sciatica, most people have developed rituals. Sleeping in the recliner because lying flat sends fire down the leg. Standing through dinner. Loading the dishwasher one plate at a time, half-bent, like defusing something. That is usually when the phrase comes up in an exam room: epidural steroid injection.
It sounds dramatic, a needle near the spine, and the internet does not help, offering everything from miracle stories to warnings written in all caps. The truth sits in the unglamorous middle. This procedure has been performed millions of times, its benefits are real but usually temporary, and its serious risks are rare but worth understanding before you sign anything.
What follows is the conversation a good clinician would have with you if the appointment ran forty-five minutes instead of fifteen: what the injection can do, what it genuinely cannot, and how to tell whether it earned its keep.
What is an epidural steroid injection, exactly?
Your spinal cord and the nerve roots branching from it are wrapped in a protective sleeve. Just outside that sleeve sits a narrow, fat-filled corridor called the epidural space. When a disc bulges or a bony canal narrows, the nerve root passing through gets compressed and, critically, inflamed. That inflammation is what the injection targets.
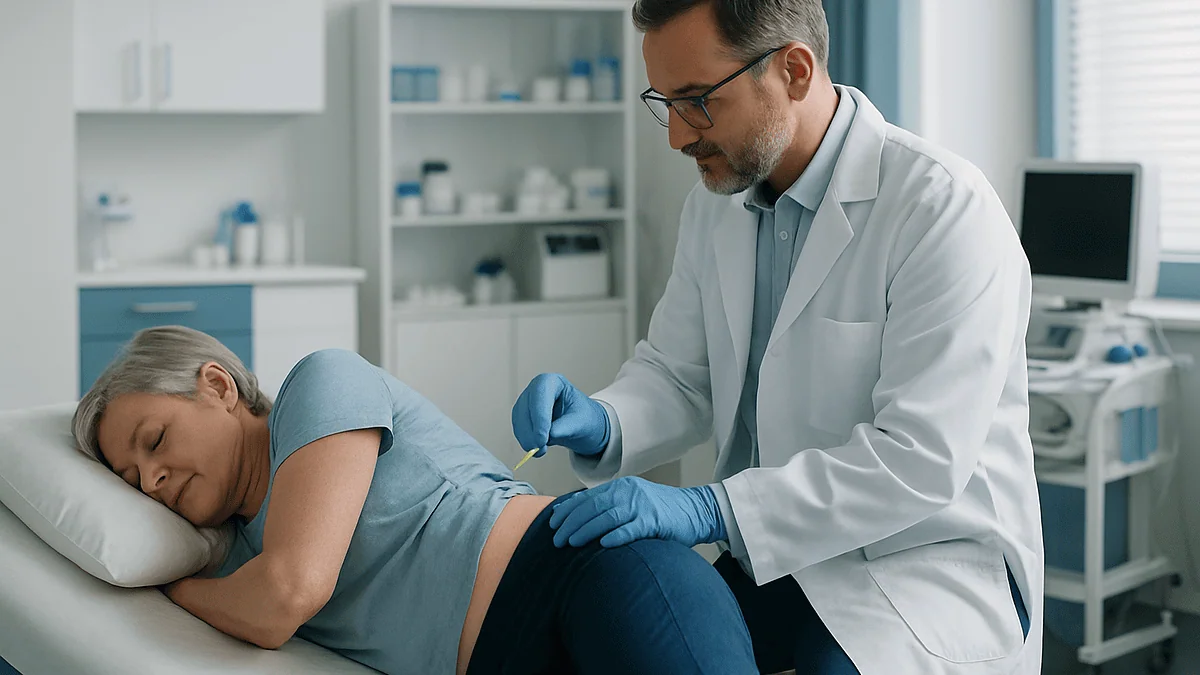
A physician guides a thin needle into the epidural space, almost always using live X-ray imaging (fluoroscopy) and a small amount of contrast dye to confirm the tip is exactly where it should be. Then a corticosteroid, a potent anti-inflammatory, is deposited near the irritated nerve, often mixed with a short-acting numbing medicine.
There are three main routes in, and your paperwork may name one of them:
- Interlaminar: between the bony plates at the back of two vertebrae, bathing a broader area.
- Transforaminal: through the small side opening where one specific nerve root exits: the most targeted approach.
- Caudal: through a natural opening at the base of the sacrum, useful when scar tissue or anatomy complicates other routes.
One clarification worth making early: this is not the epidural given during childbirth. That involves a catheter continuously delivering anesthetic to block sensation. A steroid injection is a single, brief deposit of anti-inflammatory medicine, and you walk out with your legs fully working.
What can an epidural steroid injection actually help?
The strongest case for this procedure is radicular pain, pain that radiates along a nerve’s path because the root is compressed and inflamed. In the low back, that means sciatica: pain shooting through the buttock and down the leg, sometimes with tingling or numbness into the foot. In the neck, it means pain streaking into the shoulder and arm.
The usual culprits behind that nerve irritation are:
- Herniated or bulging discs, where disc material presses on a nerve root and triggers a chemical inflammatory response around it.
- Spinal stenosis, a narrowing of the spinal canal or its side exits, common with age, that squeezes nerves, classically causing leg pain that worsens with walking and eases when you sit or lean forward.
- Degenerative disc changes that inflame nearby nerve tissue.
Here is the pattern clinicians look for: leg pain worse than back pain. When the pain radiating down the limb dominates, the odds that an inflamed nerve root is the driver, and that calming inflammation will help, go up considerably. Symptoms of relatively recent onset, measured in weeks to a few months, also tend to respond better than pain that has smoldered for years.
The goal is rarely the injection alone. At its best, it opens a window of lower pain wide enough for you to walk, sleep, and do the physical therapy that builds longer-term improvement.
What an epidural steroid injection cannot fix
This is the section most marketing skips, so let’s be plain. The injection reduces inflammation. It does not remove disc material, widen a narrowed canal, regrow cartilage, fuse an unstable segment, or reverse arthritis. If a herniated disc shrinks over the following months, and many do on their own, that is your body’s cleanup crew at work, not the medicine.
Evidence is also notably weaker for certain kinds of pain:
- Axial back painpain centered in the back itself, without radiation down a limb, responds inconsistently. Studies of epidural injections for this pattern show modest or no advantage over placebo in many trials.
- Muscle strain, ligament sprain, and general deconditioning are not epidural problems and will not respond.
- Widespread pain conditions such as fibromyalgia involve pain processing in the nervous system broadly, not a single inflamed root.
What does the research actually show about long-term outcomes? Honest reading: benefits are clearest in the first weeks to roughly three months. Whether injections reliably prevent surgery is debated; some studies suggest a subset of people avoid or delay an operation, while others find surgery rates end up similar over time. Anyone who promises an injection will fix your spine is selling certainty the evidence does not support.
Think of it as a bridge, not a repair. Bridges are genuinely useful, if there is somewhere to go on the other side, like a rehabilitation program.
What happens during the procedure, step by step
The whole visit typically runs under an hour; the injection itself often takes 15 to 30 minutes. Here is the usual sequence for a lumbar injection.
- You change into a gown and lie face-down on a procedure table, sometimes with a pillow under your hips to open the spaces between vertebrae.
- The skin is cleaned with antiseptic, and a small amount of local numbing medicine is injected: this pinch and sting is often the most uncomfortable moment.
- Using fluoroscopy, the physician advances a thin needle toward the epidural space, checking position on the screen as they go.
- A drop of contrast dye confirms the medicine will spread where intended and, just as important, that the needle is not inside a blood vessel.
- The corticosteroid mixture is injected slowly. You may feel pressure, fullness, or a brief echo of your usual pain down the leg: that is often a sign the medicine has reached the right neighborhood.
- The needle comes out, a small bandage goes on, and you rest in a recovery area for 15 to 30 minutes while staff check your blood pressure and how your legs feel.
Light sedation is available at some centers for anxious patients, though many people do fine with local numbing alone, and skipping sedation means you can usually drive yourself home. If you are sedated, a driver is mandatory.
Does it hurt? What the injection actually feels like
Ask people afterward and the most common review is some version of: the dread was worse than the needle. That is not spin. The skin and the tissue just beneath it carry most of the pain sensors, and those are numbed first. What follows is mostly pressure: a firm, odd, deep push that your brain struggles to categorize because you cannot see it happening.
Two sensations are worth knowing about in advance so they do not alarm you:
- A brief zing or jolt down the leg or arm. If the needle or the spreading medicine brushes the irritated nerve, you may feel a flash of your familiar pain. It passes in seconds. Tell the physician when it happens: the feedback is actually useful for confirming the target.
- Fullness or aching pressure as the fluid is injected into a space that is normally snug. This fades quickly.
Afterward, the numbing medicine can make the leg feel warm, heavy, or slightly weak for a few hours, which is why you rest before leaving. Some people also notice a pain flare for a day or two once the numbness wears off but before the steroid begins working: a well-known and temporary gap, not a sign the procedure failed.
If needles trigger real panic for you, say so when scheduling. Options exist, and clinicians would rather plan for anxiety than manage it mid-procedure.
How long does it take to work, and how long does relief last?
Set your expectations by the calendar, not the clock. The timeline usually unfolds in three phases.
Hours 0 to 6: If numbing medicine was included, you may feel dramatically better almost immediately. Enjoy it, but do not be fooled: this is the anesthetic, and it wears off the same day.
Days 1 to 2: A soreness gap. The numbing is gone, the steroid has not yet taken hold, and the injection site may ache. Some people feel a temporary flare of their usual pain. Ice for short stretches helps.
Days 2 to 7: The corticosteroid’s anti-inflammatory effect builds. Most people who are going to respond notice meaningful improvement within a week, though some report the full effect taking up to two weeks.
How long relief lasts varies more than any brochure admits. For many, it is several weeks to about three months. A fortunate minority get relief lasting six months or longer, often those whose underlying disc irritation was already resolving. Others get little or nothing, which itself is diagnostic information: if precisely placed anti-inflammatory medicine did not touch the pain, the inflamed nerve root may not be the main driver, and that redirects the workup.
The smartest use of a good response is momentum. Pain down 60 percent for eight weeks is exactly the opening physical therapy needs to strengthen the muscles that support your spine for the long run.
What is the success rate of an L4-L5 lumbar epidural steroid injection?
People search this exact question, and they deserve a straight answer: there is no single trustworthy percentage, because success depends on your diagnosis, symptom pattern, and how success is defined. That said, the evidence does sketch a range.
For radicular pain from a herniated disc: L4-L5 and L5-S1 are the most commonly affected levels because they bear the most load, studies generally find that roughly half to three-quarters of patients report meaningful short-term relief, often defined as at least a 50 percent pain reduction. When trials compare steroid injections against placebo or anesthetic-only injections, the steroid’s added benefit is real but modest, and it is clearest in the first weeks to three months. Long-term differences tend to shrink.
Your personal odds tilt better if:
- Leg pain clearly dominates over back pain.
- Symptoms started weeks ago, not years ago.
- Imaging findings match your symptoms: the pinched nerve on the MRI corresponds to where you hurt.
- You do not smoke and are otherwise active, both linked to better spine outcomes generally.
Odds tilt worse with pain confined to the back itself, long-standing chronic pain, or imaging that shows scattered age-related changes without one clear culprit. It is worth asking your physician directly: given my specific MRI and symptoms, what response rate would you honestly quote? A thoughtful answer to that question tells you a lot about the clinician, too.
What are the common side effects of an epidural steroid injection?
Most side effects are minor, short-lived, and traceable to one of two sources: the needle itself or the corticosteroid circulating briefly through your system. Here is how they sort out.
| Side effect | How common | Typical course |
|---|---|---|
| Soreness at the injection site | Common | 1–2 days; ice helps |
| Temporary pain flare | Fairly common | 1–3 days, then improvement |
| Facial flushing, feeling warm | Fairly common | A few hours to 2 days |
| Trouble sleeping, restlessness | Fairly common | 1–3 nights |
| Elevated blood sugar (notably in diabetes) | Common in people with diabetes | Several days; monitor closely |
| Mild headache | Occasional | Resolves within days |
| Menstrual cycle changes | Occasional | One or two cycles |
The blood sugar point deserves emphasis. Corticosteroids raise glucose, and people with diabetes can see readings climb noticeably for up to a week. If that is you, plan the injection with whoever manages your diabetes and check your levels more often afterward.
Flushing surprises people most: a hot, red face arriving a day later, sometimes with a jittery, wired feeling. It is harmless and passes, but it is far easier to tolerate when you knew it might come.
The honest answer to 'what is the dark side of epidural steroid injections?'
Type that question into a search bar and you will find forums full of alarm. Here is the sober version, because you deserve the real risk picture, not the scariest anecdote.
Rare procedural complications. If the needle nicks the membrane around the spinal fluid, a dural puncture, fluid can leak, causing a distinctive headache that worsens when you sit or stand and eases when you lie flat. This happens in roughly 1 percent of cases and is treatable. Rarer still are infection in the epidural space, bleeding that compresses nerves (epidural hematoma), and direct nerve injury. Each occurs in well under 1 percent of procedures at experienced centers using image guidance, but they are emergencies when they happen, which is why the warning signs in the next sections matter.
Catastrophic events are extraordinarily rare and have been reported mostly with certain injections in the neck, where small arteries feeding the spinal cord run close to the needle path. Technique standards have evolved specifically to reduce this risk. It is fair to ask your physician how they mitigate it.
Cumulative steroid exposure is the quieter concern. Repeated injections over time have been associated with reduced bone density, temporary suppression of your body’s own steroid production, and blood sugar effects. This, not squeamishness, is why responsible clinicians limit how many injections you receive per year and decline to repeat a shot that did nothing.
Weighed against weeks of disabling nerve pain, many people reasonably accept these odds. The point is to accept them with eyes open.
How long should you rest after an epidural steroid injection?
Less than you probably expect. The standard guidance is to take it easy for the rest of the injection day, then return to normal light activity the following morning. This is not major surgery, and prolonged bed rest actually works against a healing spine.
A practical rundown for the first 48 hours:
- Day of the procedure: Go home and be a couch person. No driving if you received sedation, arrange a ride, full stop. Skip baths, pools, and hot tubs while the puncture site seals; a shower the next day is fine at most centers (confirm your own instructions).
- First night: Expect possible site soreness. Ice for 15–20 minutes at a time works better than heat in the first day.
- Next day: Walk, work a desk job, do your usual routine. Gentle movement helps far more than stillness.
- First 24–48 hours: Hold off on strenuous exercise, heavy lifting, running, and anything that sharply loads the spine. Then resume gradually as comfort allows.
One caution about feeling suddenly great: if numbing medicine was included, the first few hours can feel like a miracle. Do not spend that borrowed comfort reorganizing the garage. The anesthetic wears off, and overexertion on a numbed spine is a classic way to trade one problem for another.
If your center gave you written aftercare instructions, those override anything general, protocols vary slightly, and yours reflects your specific procedure.
How many epidural steroid injections can you have in a year?
Most physicians cap it at three to four in a twelve-month period, with injections spaced at least a few weeks apart. That ceiling is not arbitrary insurance stinginess: it reflects the cumulative-exposure concerns covered earlier: bone density, blood sugar, and suppression of your body’s natural steroid production all track with total corticosteroid load over time.
The spacing rule has its own logic. Steroids take up to two weeks to show their full effect, so injecting again too soon means deciding before the evidence is in. And the decision to repeat should hinge on one question: did the last one help?
- Clear, meaningful relief that later fadeda repeat injection is reasonable, especially if it buys time for rehabilitation or for a disc to shrink on its own.
- Partial reliefsometimes worth one more attempt, occasionally with a different approach (transforaminal instead of interlaminar, for instance) to reach the target better.
- No relief at all from a well-placed injectionrepeating the same shot rarely changes the outcome. This result should redirect the conversation toward re-examining the diagnosis, intensifying physical therapy, or discussing surgical consultation if there is progressive weakness.
Be wary of any plan that schedules a fixed series of three injections in advance regardless of your response. Evidence does not support automatic series; each injection should earn the next one.
Epidural steroid injection vs. cortisone shot: what's the difference?
People use these terms interchangeably, and the confusion is understandable, both deliver a corticosteroid to calm inflammation. The difference is real estate.
A typical steroid shot goes into a joint (knee, shoulder, hip), a tendon sheath, or a bursa, relatively accessible spaces that a skilled clinician can often reach with landmarks alone or brief ultrasound guidance, frequently right in a clinic exam room. An epidural steroid injection targets the epidural space around the spinal nerves, a deeper and far less forgiving neighborhood. That is why it involves fluoroscopy, contrast dye, a procedure suite, and a physician with specific training in image-guided spine procedures.
Some practical contrasts:
- Target: joint or soft-tissue inflammation versus an inflamed spinal nerve root.
- Setting: often a routine office visit versus a scheduled procedure with monitoring and recovery time.
- Risk profile: both carry infection and blood sugar effects; only the epidural adds spinal-specific risks like dural puncture headache.
- What each treats: a shot in your knee will do nothing for sciatica, and an epidural will do nothing for arthritic knee pain. The medicine class is similar; the address is everything.
Both share the same fundamental honesty requirement: they treat inflammation, not the structural problem beneath it. And both count toward the reasons clinicians track your total steroid exposure across all injections, wherever in the body they land, worth mentioning if different specialists are injecting different joints.
Who should think twice, and how to prepare
Certain situations change the risk math, and a good pre-procedure conversation screens for all of them. Flag these to your care team well before injection day:
- Blood thinners or bleeding disorders. Bleeding into the epidural space is one of the rare serious risks, so anticoagulant medicines usually need coordinated adjustment, never stop them on your own; the prescribing physician and the injecting physician should agree on a plan.
- Any active infection, even a skin infection or a brewing urinary infection. Introducing bacteria near the spine is the scenario everyone works to avoid, so injections get postponed until infections clear.
- Poorly controlled diabetes. The temporary glucose spike can be significant; tighter control beforehand and a monitoring plan afterward make the procedure safer.
- Pregnancy or the possibility of it. Fluoroscopy uses X-rays, so tell your team, alternatives or timing changes exist.
- Allergies to contrast dye, antiseptics, or numbing medicines. Workarounds are available when the team knows in advance.
- Glaucoma or significant osteoporosis, both of which corticosteroids can aggravate, usually a discussion point rather than an absolute barrier.
Preparation is otherwise refreshingly simple: bring a current medication list, follow any eating instructions if sedation is planned, arrange a driver if sedated, and wear clothes you can change out of easily. One underrated tip, write down your pain score and what movements trigger it before the injection. Two weeks later, that note is the most reliable way to judge whether the shot actually worked, because memory is a famously generous editor.
When to see a doctor: red flags before and after the injection
Nerve pain is miserable, but certain symptoms mean skip the injection conversation and seek urgent care: they suggest nerve compression severe enough to cause lasting damage:
- New or worsening weakness in a leg or foot, tripping, a foot that slaps or drags.
- Numbness in the groin or inner thighs (the saddle region).
- New trouble controlling your bladder or bowels, or inability to urinate.
- Back pain with fever, unexplained weight loss, or a history of cancer.
The first three together point toward cauda equina syndrome, a genuine surgical emergency where hours matter.
After an injection, most recoveries are boring, which is exactly what you want. Contact your care team promptly, same day, if you notice:
- Fever, chills, or increasing redness, warmth, or drainage at the injection site.
- A severe headache that worsens when you sit or stand and improves lying flat: the signature of a spinal fluid leak, which is treatable.
- Rapidly worsening back pain out of proportion to expected soreness, which can signal bleeding or infection in the epidural space.
- New weakness, numbness spreading beyond your usual pattern, or any bladder or bowel changes.
And a lower-stakes but important call: if two weeks have passed with zero improvement, tell your physician rather than quietly waiting for a scheduled follow-up. A failed injection is useful diagnostic information, and the sooner it is on the record, the sooner the plan can evolve.
Questions worth asking before you say yes
The best predictor of a good outcome is not the needle: it is the quality of the thinking before the needle. Bring these questions to your consultation and listen for specific, unhurried answers:
- What exactly is my diagnosis, and does my MRI match my symptoms? An injection aimed at an incidental imaging finding rarely helps.
- What happens if we wait six weeks instead? Many disc herniations improve on their own; the honest answer sometimes favors patience, and a clinician willing to say so has earned trust.
- What response rate would you quote for someone with my specific picture? Vague reassurance is a yellow flag; a range with caveats is a green one.
- What is the plan around the injection? The strongest evidence pairs a good response with physical therapy. An injection floating alone, with no rehab plan attached, wastes its best feature: the window it opens.
- How will we define success, and what is plan B if it fails? Agree on this before the procedure, not after.
If a personal opinion is permitted after all this evidence: the epidural steroid injection is neither the miracle its fans describe nor the menace its critics warn about. It is a decent, temporary, well-studied tool, most valuable to the person who uses the quiet weeks it buys to get stronger, and least valuable to the person who treats it as the whole plan. Which one you become is, encouragingly, mostly up to you.
Frequently asked questions
What is the dark side of the epidural steroid injection?
The main downsides are that relief is usually temporary, serious complications, though rare, include infection, bleeding near the spine, and spinal fluid leak headaches, and repeated injections carry cumulative steroid effects on bone density and blood sugar. Catastrophic nerve injuries are extraordinarily rare and mostly linked to certain neck injections. For most people with leg-dominant nerve pain, the realistic trade-off is modest, well-understood risk in exchange for weeks to months of relief.
What is the success rate of an L4-L5 lumbar epidural steroid injection?
There is no single reliable number, but studies of injections for radicular pain from disc herniation, L4-L5 is one of the most commonly affected levels, generally find that roughly half to three-quarters of patients get meaningful short-term relief. Odds improve when leg pain dominates over back pain, symptoms are recent, and imaging clearly matches the symptoms. Benefits over placebo are modest and strongest in the first three months.
What are the side effects of an epidural steroid injection?
Common, short-lived side effects include soreness at the injection site, a temporary pain flare for a day or two, facial flushing, trouble sleeping for a few nights, and elevated blood sugar, especially relevant for people with diabetes. Rare but serious complications include infection, bleeding in the epidural space, nerve injury, and a positional headache from spinal fluid leak, which occurs in roughly 1 percent of cases and is treatable.
How long should you rest after an epidural steroid injection?
Take it easy for the rest of the injection day, then resume normal light activity the next morning. Avoid strenuous exercise, heavy lifting, and driving (if you were sedated) for 24 hours, and skip baths, pools, and hot tubs briefly while the site heals. Extended bed rest is not recommended, gentle walking actually supports recovery. Follow your own center’s written aftercare instructions if they differ.
How long does relief from an epidural steroid injection last?
Most people who respond get relief lasting several weeks to about three months, and a smaller group reports six months or longer. The steroid’s effect builds over 2 to 7 days, sometimes up to two weeks. Duration varies widely with the underlying diagnosis. The most durable outcomes tend to occur when the pain-relief window is used for physical therapy, or when the underlying disc problem is already resolving on its own.
Does an epidural steroid injection hurt?
Most people report pressure and a brief sting rather than severe pain, and many say the anticipation was worse than the procedure. The skin is numbed first, so what follows is mostly a deep pressure sensation. A quick zing down the leg can occur if the needle or medicine contacts the irritated nerve: it passes in seconds. Light sedation is available at many centers for people with significant needle anxiety.
Can an epidural steroid injection make pain worse?
Temporarily, yes: a pain flare for one to three days after the injection is fairly common, occurring once the numbing medicine wears off but before the steroid takes effect. This resolves on its own and does not predict failure. Lasting worsening is rare; rapidly escalating pain, fever, new weakness, or bladder or bowel changes after an injection are not normal flares and warrant same-day medical attention.
How many epidural steroid injections can you have per year?
Most physicians limit patients to three or four injections in a twelve-month period, spaced at least several weeks apart. The cap exists because corticosteroid exposure accumulates across injections and can affect bone density, blood sugar, and the body’s own steroid production. A repeat injection generally makes sense only if the previous one produced clear relief; repeating a shot that did nothing rarely changes the outcome.
Is an epidural steroid injection the same as the epidural given during childbirth?
No. A labor epidural delivers a continuous flow of anesthetic through a catheter to block sensation across a broad region for hours. An epidural steroid injection is a single, brief deposit of anti-inflammatory medicine near an irritated nerve root, guided by live X-ray imaging. They share the same anatomical space and little else, after a steroid injection, you walk out with your legs fully functional.
Can an epidural steroid injection help you avoid back surgery?
Sometimes, though the evidence is mixed. Some studies suggest a subset of patients with disc-related nerve pain delay or avoid surgery after successful injections, often because the disc problem improves on its own during the pain-relief window. Other research finds long-term surgery rates end up similar. The injection is best viewed as a bridge that buys time for natural healing and rehabilitation, not as a guaranteed surgical off-ramp.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Long Does a Cortisone Shot Last? Duration, Honestly Answered
Relief from a cortisone shot most often lasts between six weeks and six months, though the range is wide: some people feel better for…

How Long Sciatica Lasts and Whether It Goes Away on Its Own
Most episodes of sciatica ease within about four to six weeks, and the majority of people improve without surgery. Pain often fades gradually and…
PRP Injections: What Platelet-Rich Plasma Can Do: Per the Evidence
PRP (platelet-rich plasma) injections concentrate platelets from your own blood and inject them into damaged tissue to encourage healing. Evidence is strongest for chronic…

Recovery After an Implanted Neuromodulation Device: Wound Care, Programming Visits and Activity
Recovery after a neuromodulation implant such as a spinal cord stimulator usually means keeping two small incisions clean and dry for the first one…

Inside an Epidural Injection for Sciatica: Imaging, Contrast and the Minutes That Follow
An epidural injection for sciatica places a corticosteroid, usually with a local anesthetic, into the epidural space around irritated spinal nerves, guided by live…

How Long Does Facet Denervation Relief Last and What Happens When Nerves Regrow?
Relief after facet denervation, a procedure that heats the tiny medial branch nerves so they stop carrying pain signals from an arthritic spinal joint,…