

Getting Ready for a Planned Cesarean Delivery: Fasting Rules, Blood Tests and the Night Before

Key Takeaways
- A planned cesarean is usually scheduled from 39 weeks because babies delivered earlier without a medical reason are more likely to have breathing problems after birth.
- The two near-universal pre-operative blood tests are a full blood count, to detect anemia and check platelets before a spinal injection, and a group and save, which records your blood type so matched blood can be prepared quickly if needed.
- Modern fasting guidance separates food from clear fluids, typically asking for no food for several hours but allowing water until about two hours before surgery; your anesthetist sets the exact times.
- Do not shave the incision area yourself; razor micro-cuts raise infection risk, and hospitals clip hair only if it would interfere with the operation.
- The operation itself typically lasts about 40 to 50 minutes, with the baby usually born within the first few minutes and the remaining time spent closing the uterus and abdominal wall.
- Hospital stays after a planned cesarean are usually around three to four days, and full recovery typically takes about six weeks, during which lifting is limited to roughly the weight of your baby.
Preparing for a planned cesarean usually means a pre-operative appointment with blood tests to check for anemia and record your blood group, a consent discussion, fasting from food and most drinks for a set number of hours decided by the anesthesia team, a shower, removal of jewelry and nail polish, and arriving early with a packed bag. Your maternity team gives the exact instructions and timings.
The date is written on the calendar in a different color from everything else. It sits there for weeks, and then suddenly it is tomorrow. The hospital bag is by the door, the car seat has been fitted and refitted, and someone has asked for the third time whether you are allowed a cup of tea in the morning.
That question, and a dozen like it, is what planned c section preparation really comes down to. Not the big decision, which has already been made with your obstetrician, but the small practical ones: when to stop eating, which blood tests are taken and why, what to wear, what to pack, and what the night before should actually look like.
This explainer walks through each of those steps in the order you will meet them, using guideline-level evidence rather than forum folklore. Your own team’s written instructions always take priority over any general figure here.
What planned c section preparation actually involves
A cesarean delivery is an operation in which the baby is born through a cut in the abdomen and the uterus (the womb). When it is planned, the date is chosen in advance rather than decided during labor, and that single difference changes almost everything about how you prepare. There is time for a proper conversation, time for tests, and time to sleep in your own bed the night before.
Planned c section preparation runs along a few parallel tracks. The clinical track includes a pre-operative appointment, blood tests, a review of your medicines and allergies, and a consent discussion in which the obstetrician explains why the operation is being recommended, what the alternatives are and what the risks look like for you specifically. The practical track covers fasting, showering, what to wear and what to pack. The home track is about who looks after older children, who drives, and who can help with lifting for the first weeks.
The operation itself is shorter than most people picture. According to the NHS, a cesarean usually takes about 40 to 50 minutes from start to finish, and the baby is normally delivered within the first few minutes; the rest of the time is spent closing the uterus and the abdominal wall in layers. Most planned cesareans are done under a regional anesthetic, which numbs the lower body while you stay awake, so a birth partner can usually be in the room.
Knowing that shape in advance matters. People who understand what each step is for tend to find the fasting easier to tolerate, the blood tests less mysterious and the early morning less daunting. Preparation is not a test you can fail; it is a series of small, sensible tasks that make a safe operation a little safer.
Who is usually offered a planned cesarean, and who is usually asked to wait
A planned cesarean is recommended when the obstetric team judges that it is the safer route for mother, baby or both. The NHS lists the common reasons: a baby lying bottom-first (breech) that cannot be turned, a placenta sitting low over the cervix (placenta previa), twins where the first baby is not head-down, certain infections such as a first episode of genital herpes late in pregnancy or HIV that is not well controlled, and some maternal medical conditions. A previous cesarean is another frequent reason, although many people who have had one can still plan a vaginal birth after discussion.

Some people ask for a cesarean without a medical indication, often because of a previous difficult birth or severe anxiety about labor. Guidance in the UK says that request should be met with a full discussion of benefits and risks, and support such as counseling where anxiety is the driver; if the person still prefers a cesarean after that conversation, it may be offered. The decision sits with the person and their treating team together.
Timing is where people are most often asked to wait. The NHS states that a planned cesarean is usually carried out from the 39th week of pregnancy, because babies born earlier are more likely to have breathing problems. An earlier date is set only when there is a medical reason that outweighs that risk, for example a placenta previa that has bled or a maternal condition that is worsening.
Two other situations can shift the plan. If you develop a fever, a chest infection or another acute illness close to the date, the anesthesia team may postpone. And if labor starts before your scheduled day, the plan does not simply fall away: you are asked to call the maternity unit immediately, and the operation is usually brought forward as an unplanned rather than emergency procedure.
The pre-operative appointment: what happens and what to bring
Most units arrange a pre-operative appointment in the days before the operation, and the NHS describes it as the point where the practical preparation is set in motion. Expect it to take longer than a routine antenatal visit. A midwife or nurse checks your blood pressure, pulse and temperature, listens to the baby’s heartbeat, confirms your due date and the reason for the cesarean, and asks about previous operations, anesthetics and any reactions to them.
Blood is taken, which the next section covers in detail. Some units also take a nasal or skin swab to screen for bacteria such as MRSA, a type of staphylococcus resistant to common antibiotics; if it is found, you may be given a body wash or nasal ointment to use before surgery. Not every unit screens, so do not be alarmed either way.
Your medicines are reviewed line by line. Bring every prescription, over-the-counter product and supplement you take, including iron, vitamins and herbal remedies. Some medicines are continued right up to the morning of surgery with a sip of water; a few, particularly blood-thinning medicines, are paused on a timetable set by the anesthetist. Do not stop or start anything on your own.
You will usually be asked to read and sign a consent form. This is not a formality. It should name the operation, the reasons for it, the main risks (bleeding, infection, blood clots, injury to nearby organs, breathing difficulty for the baby, and implications for future pregnancies) and the alternatives. Ask for anything you do not understand to be explained again.
Finally, you receive the fasting instructions and arrival time in writing, and often an acid-reducing medicine to take at home. Keep that sheet somewhere visible. It overrides every general figure in this article.
Blood tests before c section: what they check and why
Two blood tests are near-universal before a planned cesarean, and the NHS names both: a full blood count and a group and save.
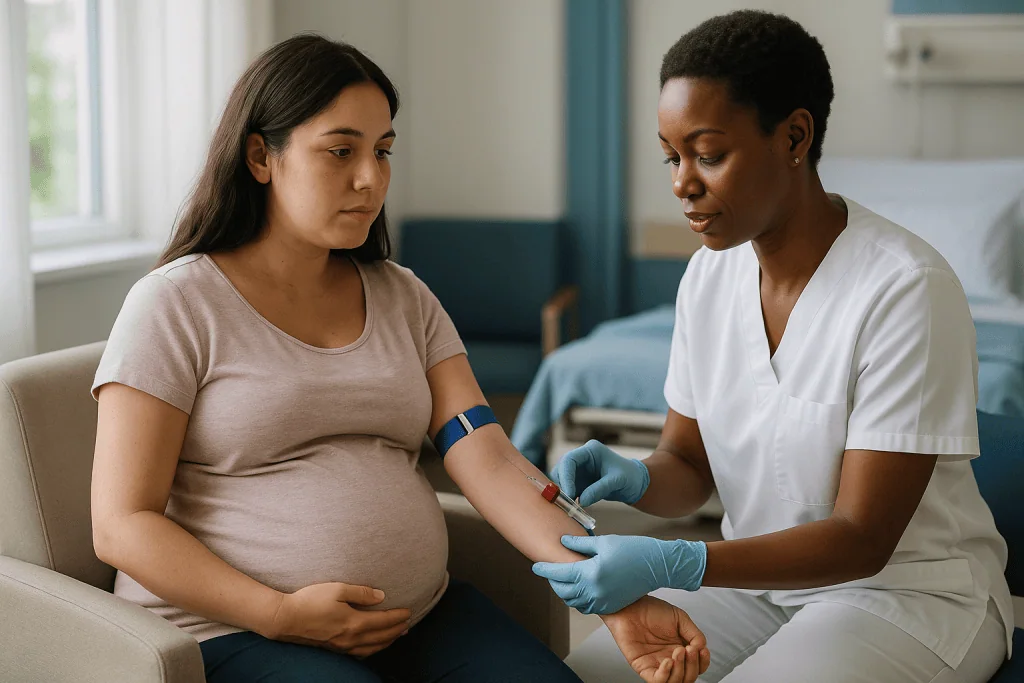
A full blood count measures the cells in your blood. The number that matters most here is hemoglobin, the protein in red blood cells that carries oxygen. Pregnancy dilutes the blood and increases iron demand, so anemia (a low hemoglobin level) is common in the third trimester. A cesarean involves more blood loss than an uncomplicated vaginal birth, so starting the operation already anemic leaves less reserve. If the count is low, the team can treat it before the day, usually with iron prescribed by the clinician. The same test reports platelets, the small cell fragments that help blood clot. The anesthetist checks this figure because a spinal or epidural injection is placed close to the spinal cord, and a low platelet count raises the risk of bleeding around it.
Group and save identifies your blood group and screens for antibodies against red cells. The sample is held in the laboratory so that, in the uncommon event of heavy bleeding, matched blood can be prepared quickly rather than from scratch. People with a history of previous transfusion, a low-lying placenta or anti-D antibodies may have additional cross-matching done in advance.
Depending on your history, further tests may be added: kidney and liver function and clotting studies if there is high blood pressure or suspected pre-eclampsia, a blood sugar check in gestational diabetes, or repeat infection screening. None of these are routine for everyone.
Timing matters because results are only valid for a limited window set by the laboratory; if your date moves, the group and save may be repeated. Ask at the appointment whether anything in your results changes the plan, and who will call you if it does.
Fasting before c section: how long, and why the rules exist
Fasting is the instruction people worry about most, so it helps to understand what it is protecting against. The concern is aspiration: stomach contents coming back up and entering the lungs while protective reflexes are dampened by anesthesia. Pregnancy makes this more likely because the enlarged uterus presses on the stomach and hormones slow its emptying. Even when a spinal anesthetic is planned, the team prepares as though a general anesthetic might become necessary, because occasionally it does.
Modern guidance is less austere than the old ‘nothing after midnight’. Anesthesia society recommendations widely used in maternity units allow clear fluids until about two hours before the operation and ask for no food for about six hours, with heavy or fatty meals needing longer. The NHS confirms that you will be told not to eat or drink for a set period, and the exact clock is set by your anesthetist based on your slot in the operating list. Someone booked first thing will have a different cutoff from someone booked late morning.
Clear fluids mean liquids you can see through: water, diluted squash, black tea or coffee without milk. Milk, juice with pulp, soup and smoothies count as food. So do chewing gum, boiled sweets and mints, which stimulate stomach acid. Many units actively encourage drinking water up to the permitted time, because arriving dehydrated makes placing a cannula harder and can worsen the drop in blood pressure that follows a spinal.
Medicines are a separate conversation. Most regular medicines can be taken on time with a small sip of water, and an acid-reducing medicine is often prescribed for the night before and the morning of surgery to make stomach contents less harmful if aspiration did occur. Ask specifically which of your medicines to take and which to hold.
The night before c section: a realistic checklist
The evening before is less about doing things and more about not doing the wrong ones. Eat a normal, moderately light dinner before your fasting window begins; a plate of pasta or rice with vegetables and lean protein empties from the stomach faster than a large fried or very fatty meal, which is why anesthetists ask for a longer gap after those. Finish eating before the time on your instruction sheet, and set a phone alarm for the last permitted drink.
Shower or bathe with ordinary soap and wash your hair; the NHS recommends this because it reduces the number of bacteria on the skin. Do not shave or wax the area where the incision will be. Shaving causes tiny cuts that bacteria can colonize, and surgical guidance favors leaving hair alone or trimming it with clippers in hospital only if it would get in the way.
Remove nail polish, gel nails and false eyelashes, and skip makeup in the morning. This is not vanity policing: the pulse oximeter clipped to a fingertip reads oxygen levels through the nail, and the anesthetist watches your lip and skin color during the operation. Take out piercings and leave jewelry at home; a plain ring can sometimes be taped, but ask.
Practical tasks for the evening include:
- Lay out loose clothing that sits above the bikini line, and flat slip-on shoes.
- Charge your phone and pack a long cable; sockets near hospital beds are rarely convenient.
- Put your instruction sheet, notes and identification in the bag.
- Confirm who is driving, where they will park and who is minding other children or pets.
Then stop. Sleep is often patchy, and that is normal. A short walk, a warm drink inside the allowed window and an early night do more good than a final frantic clean.
What to pack for c section: the hospital bag, without the overpacking
The NHS says a hospital stay after a cesarean is usually around three or four days, although some units support an earlier discharge when everything is going well. Pack for that length and for the fact that you will be moving slowly, bending reluctantly and feeding frequently.
For yourself, think about the incision first. It sits low across the abdomen, just above the pubic hairline, so anything with a waistband at that height will rub. High-waisted, soft cotton underwear a size or two larger than usual, and loose joggers or a dress, are the kindest choices. Front-opening nightwear makes feeding and wound checks easier. Add maternity pads (bleeding after a cesarean is lighter than after a vaginal birth but still real), nursing bras if you plan to breastfeed, toiletries, lip balm for the dry air, glasses rather than contact lenses, and slippers with grip for those first unsteady walks.
Bring the paperwork: your maternity notes, the pre-operative instruction sheet and any birth preferences you have written. A pillow from home can help you brace against the wound when coughing or laughing. Snacks for after the operation are welcome once the team says you can eat, which is often within hours of a regional anesthetic.
For the baby, the list is short: a fitted car seat, several vests and sleepsuits, a hat, nappies, cotton wool or wipes, and a blanket. Formula and bottles only if you are planning to use them. For a birth partner, a water bottle, snacks, a phone charger and comfortable layers; operating theaters are kept cool.
Leave at home anything valuable, anything you would be upset to lose, and the half-suitcase of ‘just in case’. Hospitals have a way of making an overstuffed bag feel like one more thing to lift.
The morning of surgery: what actually happens, step by step
You arrive early, often two hours or more before your slot, so the team can complete checks without rushing. A midwife confirms your identity, checks your blood pressure and temperature, listens to the baby, and asks when you last ate and drank. You change into a gown and are measured for anti-embolism stockings, the tight knee- or thigh-length socks that squeeze the calves to reduce the risk of a blood clot forming in the legs during and after surgery.
The anesthetist visits, reviews your blood results, examines your back and talks through the anesthetic plan. The obstetrician confirms consent and marks nothing on your abdomen in most cases, since the incision site is standard. If your partner is coming into theater, they are given scrubs, a hat and shoe covers.
In the anesthetic room or theater, a cannula (a small plastic tube) is placed in a vein in the hand or arm and a drip started. The spinal or epidural is placed while you sit forward or curl on your side; the sensation is pressure and a brief sting from local anesthetic. Once your legs feel warm and heavy, a urinary catheter, a soft tube that drains the bladder, is inserted; you will not feel it because the area is already numb.
Before the first incision, antibiotics are given through the drip to lower the risk of wound infection, and the whole team pauses for a safety checklist that confirms your name, the procedure and any allergies. A screen is raised at chest height. Most people describe the delivery itself as tugging and pressure rather than pain. Where mother and baby are well, skin-to-skin contact in theater and delayed cord clamping are increasingly routine. You then move to a recovery area for close monitoring while the anesthetic wears off.
Anesthesia for a planned cesarean: spinal, epidural, and when general is used
Three forms of anesthesia are used for cesarean delivery, and the NHS notes that a regional technique, which numbs the lower half of the body while you stay awake, is the usual choice for a planned operation.
A spinal anesthetic is a single injection through the lower back into the fluid surrounding the spinal cord. It works within minutes and produces dense numbness from roughly the chest down. Because it is a one-off injection, its duration is limited, which is well matched to an operation lasting under an hour. An epidural places a very fine tube in the space just outside that fluid-filled sac, so medicine can be topped up over time; it is more often used when an epidural is already in place during labor, or combined with a spinal when a longer procedure is anticipated.
Awake does not mean uncomfortable. You should feel no pain, although pressure, pulling and movement are expected, and many people are surprised by how much they can sense. Common side effects include a drop in blood pressure that can cause nausea or lightheadedness (the anesthetist treats this as it happens), shivering, and itching. A headache that is worse when upright can occur in a small minority in the days afterward and has a specific treatment, so report it.
A general anesthetic, where you are asleep, is used when regional anesthesia is unsafe or impossible: certain bleeding or clotting disorders, some spinal conditions, infection at the injection site, or when a regional block fails or time is critical. A birth partner is usually not present for a general, and the first meeting with the baby happens in recovery.
For preparation, this means telling the anesthetist about back problems, previous anesthetic reactions, blood-thinning medicines and any family history of anesthesia complications. Those details shape the plan more than anything you can read in advance.
Planned c section preparation at a glance: a timeline table
Timelines vary between units, and your written instructions always win. With that caveat, the sequence below reflects what mainstream maternity guidance describes for an uncomplicated planned cesarean. Treat it as a map rather than a schedule.
| When | What usually happens | What you can do |
|---|---|---|
| Weeks before | Decision made with obstetrician; date set from around 39 weeks unless medically indicated earlier (NHS) | Write down questions; arrange childcare, transport and help at home |
| Pre-operative appointment | Observations, full blood count, group and save, medicines review, consent, fasting sheet | Bring all medicines and supplements; ask who calls if results change the plan |
| Day before | Normal activity; last normal meal before the fasting window | Shower; remove nail polish and jewelry; pack; charge phone |
| Fasting window | No food for the stated hours; clear fluids until the stated cutoff; acid-reducing medicine if prescribed | Set alarms; drink water within the allowed time; take agreed medicines with a sip |
| Morning of surgery | Early arrival, checks, stockings, anesthetist review, cannula | Wear loose clothes; bring notes and instruction sheet |
| In theater | Spinal or epidural, catheter, antibiotics, safety checklist, birth within minutes, closure; about 40–50 minutes total (NHS) | Ask about skin-to-skin and who announces the sex if you want to |
| First hours | Recovery monitoring, feeding support, pain relief, feeling returns to legs | Report pain, nausea or itching early; sip fluids when permitted |
| Days 1 to 4 | Catheter out, walking, wound check, clot prevention; discharge usually within 3–4 days (NHS) | Move little and often; keep the wound clean and dry |
Two patterns stand out. Almost everything in the right-hand column is small and achievable the evening before. And the figures that people fixate on, the fasting hours and the arrival time, are the ones most likely to be individualized by your team, so they belong on your instruction sheet, not in your memory.
The first days and weeks after: what recovery usually looks like
Preparation does not stop at the theater door, and knowing the typical arc of recovery helps you arrange the right support. The NHS describes a hospital stay of around three or four days, with many people up and walking within a day. Early movement is not optional cheerfulness; it reduces the risk of blood clots and chest infections and helps the bowel wake up.
The urinary catheter is usually removed once you can walk to the bathroom, often the day after surgery. Pain is managed with regular pain relief from classes such as acetaminophen (paracetamol) and anti-inflammatory medicines, with stronger options available if needed; the ward team sets what and when. Clot prevention continues with stockings and, for many people, a daily blood-thinning injection for a period decided by the obstetrician based on individual risk factors.
The wound is covered with a dressing for the first day or so. Afterward, the NHS advice is to keep it clean and dry, wear loose cotton clothing, and look at it daily for redness, swelling, discharge or separation. Dissolvable stitches disappear on their own; non-dissolvable stitches or clips are removed by a midwife, usually within the first week.
At home, the NHS suggests that recovery typically takes about six weeks, although the first two are the hardest. Mayo Clinic’s practical rule is to avoid lifting anything heavier than your baby during that early period. Driving can resume when you can sit comfortably, turn to check mirrors and perform an emergency stop without hesitation, and your insurer has no objection; the NHS notes this is often several weeks.
A postnatal check with your doctor is usually offered around six to eight weeks, when future birth options, including vaginal birth after cesarean, can be discussed. None of these timelines are promises; they are the ranges most people fall within.
What people often get wrong about preparing for a cesarean
Several durable myths shape how people prepare, and most of them make the day harder rather than safer.
The first is that fasting means nothing at all from midnight. Older practice did say that, but current anesthesia guidance distinguishes food from clear fluids, and many units encourage water until about two hours before surgery. Arriving parched is not a virtue; it makes cannulation harder and blood pressure less stable. Follow the times on your sheet, not the rule a relative remembers.
The second is that you should shave the bikini area yourself the night before. Surgical infection-prevention guidance points the other way: razor shaving creates micro-abrasions that bacteria colonize, so hair is left alone or clipped in hospital only if it would interfere with the incision.
Third, a planned cesarean is often framed as the risk-free option. It avoids the uncertainties of labor, but it is major abdominal surgery with its own risks, which is exactly why the consent discussion covers bleeding, infection, clots and implications for future pregnancies. Preparation is partly about reducing those risks: stockings, antibiotics, early walking and a hemoglobin check all exist for a reason.
Fourth, people assume that being awake means feeling everything. A working spinal removes pain; it does not remove sensation. Pressure, tugging and the odd lurch are normal and are not a sign the anesthetic has failed. Say so if anything feels sharp, and the anesthetist will act.
Fifth, the belief that an earlier date is just as good. The NHS places planned cesareans from 39 weeks because the baby’s lungs are still maturing before then, and earlier delivery without a medical reason increases breathing problems after birth.
Last, that you cannot hold your baby in theater. Where both are well, skin-to-skin contact during closure is common practice and worth asking for.
Questions to ask your care team before a planned cesarean
A good pre-operative appointment is a two-way conversation, and the questions you bring often reveal what the team has assumed you already know. Write them down beforehand, because the appointment moves quickly and pregnancy memory is real.
About the decision and timing:
- What is the specific reason for recommending a cesarean in my case, and what would happen if I chose to wait or to plan a vaginal birth?
- Why has this date been chosen, and what should I do if labor starts or my waters break before it?
- How many weeks will I be, and does my situation justify an earlier date than 39 weeks?
About preparation:
- What are my exact fasting times for food and for clear fluids, and which of my medicines should I take on the morning?
- Did my blood tests show anemia or anything else, and does it change the plan?
- Will I need any screening wash, acid-reducing medicine or blood-thinning injections before or after?
About the operation:
- Which anesthetic is planned for me and why, and what happens if it does not work well enough?
- Can my partner be in the room, and can we have skin-to-skin and delayed cord clamping if the baby is well?
- Who will be in theater, and who do I speak to if I feel unwell during the operation?
About afterward:
- How long do you expect me to stay, and what are the criteria for going home?
- What wound care and activity limits do you advise, and when should I expect my follow-up check?
- Who do I call, day or night, if I am worried after discharge?
Ask for the answers in writing where possible. The fasting times and the out-of-hours number are the two you will want to find at three in the morning.
When to call your doctor before and after a planned cesarean
A scheduled date can create a false sense that nothing needs attention until then. It does. In the days before surgery, contact your maternity unit straight away, at any hour, if you notice regular painful contractions or a gush or trickle of fluid from the vagina, since labor or ruptured membranes change the plan. Call for any vaginal bleeding, for a reduction or change in your baby’s movements, or for a severe headache, visual disturbance, sudden swelling of the face and hands, or pain under the ribs, which can signal pre-eclampsia. Fever, a productive cough or vomiting that stops you keeping fluids down should also be reported, because they may affect the anesthetic.
After the operation, the NHS and Mayo Clinic highlight these red flags:
- Heavy vaginal bleeding that soaks a pad within an hour, or passing large clots.
- Fever, chills or feeling generally unwell.
- Redness, swelling, increasing pain, discharge or opening of the wound.
- Severe or worsening abdominal pain, or a hard, tender abdomen.
- Pain, swelling or warmth in one calf, which may indicate a clot.
- Chest pain, breathlessness or coughing up blood, which require emergency services immediately.
- Pain or burning when passing urine, or difficulty passing urine at all.
- Foul-smelling vaginal discharge.
- Low mood that does not lift, intrusive thoughts, or any thought of harming yourself or your baby.
None of these should be sat on until the next appointment. Maternity units run 24-hour advice lines precisely for this period, and midwives would far rather hear from you about something that turns out to be minor than miss something that is not. If a symptom feels like an emergency, treat it as one and call emergency services.
Frequently asked questions
How long is fasting before c section surgery?
Most anesthesia services ask for no food for about six hours before a cesarean, longer after a heavy or fatty meal, and allow clear fluids such as water until about two hours before. The exact times depend on your slot on the operating list and are written on your pre-operative instruction sheet, which always overrides any general figure. Chewing gum and sweets count as food.
Which blood tests before c section are routine?
A full blood count and a group and save are routine. The full blood count checks hemoglobin for anemia and platelets for safe placement of a spinal or epidural; the group and save records your blood type and screens for antibodies so matched blood can be prepared quickly if bleeding is heavier than expected. Extra tests are added only for specific conditions.
What should I do the night before c section?
Eat a normal, moderately light dinner before your fasting window starts, shower with ordinary soap, remove nail polish, jewelry and piercings, and leave body hair alone. Lay out loose clothes that sit above the bikini line, charge your phone, pack your notes and instruction sheet, and confirm transport and childcare. Then rest; patchy sleep is normal and not harmful.
What to pack for c section recovery in hospital?
Pack for a stay of around three to four days: high-waisted soft underwear and loose trousers that do not sit on the incision, front-opening nightwear, maternity pads, nursing bras if relevant, toiletries, slippers with grip, glasses, a long phone cable and your maternity notes. For the baby, a fitted car seat, vests, sleepsuits, a hat, nappies and a blanket are enough.
Can I drink water the morning of a planned cesarean?
Usually yes, up to the clear-fluid cutoff on your instruction sheet, which in many units is about two hours before the operation. Clear fluids are liquids you can see through, so milk, juice with pulp and smoothies do not count. Staying hydrated within the allowed window makes placing a cannula easier and helps blood pressure after a spinal.
Should I shave before a c section?
No. Surgical infection-prevention guidance advises against shaving the operation site yourself because razors cause tiny skin breaks that bacteria can colonize. If hair would get in the way of the incision, theater staff remove it with clippers on the day. Showering with ordinary soap the night before or the morning of surgery is the preparation that actually helps.
Why is a planned c section done at 39 weeks?
The NHS states that planned cesareans are usually carried out from the 39th week because babies born earlier are more likely to have breathing problems after birth, as their lungs are still maturing. An earlier date is chosen only when a medical reason for mother or baby outweighs that risk, which is a judgment made by the obstetric team.
Will I be awake during a planned cesarean?
Usually yes. Most planned cesareans use a spinal or epidural anesthetic that numbs the body from the chest down while you stay awake, so a birth partner can be present and skin-to-skin contact is often possible. A general anesthetic is used when regional anesthesia is unsafe or does not work well enough; your anesthetist will explain which applies to you.
What happens if I go into labor before my planned c section date?
Call your maternity unit immediately if you have regular contractions, your waters break or you bleed. The plan does not disappear; in most cases the cesarean is brought forward as an unplanned rather than emergency operation, and the team reassesses whether anything about the anesthetic or timing needs to change. Keep the unit’s number saved in your phone.
How long does it take to recover from a planned c section?
The NHS describes a hospital stay of around three to four days and a typical recovery of about six weeks, with the first two weeks the most limiting. Early walking is encouraged, lifting is restricted to roughly the weight of your baby, and driving resumes when you can brake comfortably and your insurer agrees. Individual recovery varies and is reviewed at your postnatal check.
References
- NHS: Caesarean section
- NHS: Caesarean section, what happens
- NHS: Caesarean section, recovery
- MedlinePlus: C-section
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Fasting and Timing for Gestational Diabetes Screening: How to Prepare for the Glucose Test
Preparation depends on which glucose test you are having. The one-hour screening test usually needs no fasting; you eat normally, drink the glucose solution…

Who Needs Closer Pregnancy Monitoring? Twins, Diabetes, Blood Pressure and Other Reasons
Closer pregnancy monitoring is usually offered when a pregnancy carries a higher chance of complications for the mother, the baby, or both. Common reasons…

How Does the Glucose Tolerance Test Work? Gestational Diabetes Screening Explained Plainly
The glucose tolerance test in pregnancy measures how quickly your body clears sugar from the blood after a measured glucose drink. You usually fast…

Flying After Amniocentesis: How Long International Patients Wait Before Traveling Home
No major guideline sets a fixed number of days for flying after amniocentesis. Standard aftercare is to rest for the remainder of the procedure…

When Diet Alone Is Not Enough: How Gestational Diabetes Treatment Steps Up Under Supervision
Insulin is usually needed for gestational diabetes when blood sugar readings stay above the targets your care team sets despite one to two weeks…

Getting Ready for a Planned Cesarean Delivery: Fasting Rules, Blood Tests and the Night Before
Planned cesarean preparation usually involves a pre-operative visit with blood tests (commonly a blood count and a blood group and antibody screen), a review…