

Heart Murmurs in Children: Why Most Are Innocent

Key Takeaways
- Studies estimate that somewhere between a third and three-quarters of healthy children have an audible murmur at some point, while congenital heart defects affect only about 1 in 100 births.
- Innocent murmurs are soft (grade 1–2 of 6), occur during the heart's squeeze phase, and typically fade when a child sits or stands; a murmur heard during the relaxation phase is never classed as innocent.
- Fever, crying, anemia, and exercise raise cardiac output and can make a flow murmur appear or get louder, which is why doctors often recheck once the child is well.
- The CDC reports that pulse oximetry screening for critical congenital heart defects, recommended since 2011 and in every state by 2018, now identifies most dangerous defects in the first days of life.
- An echocardiogram is a painless, radiation-free heart ultrasound that typically takes 30 to 45 minutes and settles most questions about whether a murmur has a structural cause.
- Observational follow-up shows that many small ventricular septal defects, the most common congenital heart defect, close on their own in the first years of life.
A heart murmur in children is an extra whooshing sound made by blood moving through the heart, and most are innocent: they come from normal flow in a healthy heart, need no treatment, and often fade with age. A smaller number point to a structural problem such as a hole or a narrowed valve, which is why a pediatrician listens carefully and may refer to a pediatric cardiologist for an echocardiogram.
Every September the same scene plays out in family clinics across the country: a seventh-grader hops onto the exam table for a sports physical, the pediatrician pauses with the stethoscope a second longer than usual, and a parent’s stomach drops. This year the pause is landing harder. As of September 2026, searches for heart murmur in children are climbing alongside back-to-school physicals and a run of viral short videos in which a parent films the moment a clinic flags “something” in a child’s heartbeat, then cuts to a dramatic hospital corridor.
The videos rarely show the ending, which is almost always undramatic. The sound is explained, an ultrasound is sometimes done, and the child goes back to soccer practice.
That gap between the dramatic clip and the quiet reality is worth closing, because the facts here are unusually reassuring and unusually well documented. What follows is what a murmur actually is, how doctors sort the harmless from the significant, and which signs genuinely deserve a prompt appointment.
What is a heart murmur in children, and what is the sound?
Put a stethoscope on a healthy chest and you hear two crisp sounds, the familiar “lub-dub” of the heart’s valves snapping shut. A murmur is anything extra: a whoosh, a hum, a soft vibration tucked between those two beats. It is a sound, not a disease. The noise comes from turbulence, which is simply blood flowing fast enough or through a narrow enough space to swirl rather than glide, the same physics that makes a garden hose hiss when you squeeze the nozzle.
In children that turbulence usually has an innocent explanation. A child’s chest wall is thin, the heart sits close to the skin, and a young heart pumps a large volume of blood relative to body size. Those three facts mean normal flow is often loud enough to hear. Mayo Clinic and MedlinePlus both describe these as innocent, functional, or physiologic murmurs, three labels for the same thing: a sound produced by a structurally normal heart.
A heart murmur in children is graded for loudness on a scale of 1 to 6. Grade 1 is so faint a clinician has to concentrate to catch it; grade 6 can be heard with the stethoscope lifted slightly off the chest. Timing matters too. A systolic murmur happens while the heart squeezes; a diastolic murmur happens while it relaxes and refills. Innocent murmurs are systolic, soft, and short. Diastolic murmurs are not considered innocent and are always investigated.
Doctors also note where on the chest the sound is loudest, whether it travels toward the neck or back, and whether it changes when the child stands, lies down, or holds a breath. Those details, gathered in about a minute, carry most of the diagnostic weight, which is why a careful exam is the first and often the only test a child needs.
What changed recently
Nothing about the biology of a murmur has changed. What has shifted, steadily over the past fifteen years and sharply in the public conversation this season, is how early and how often children’s hearts are examined.
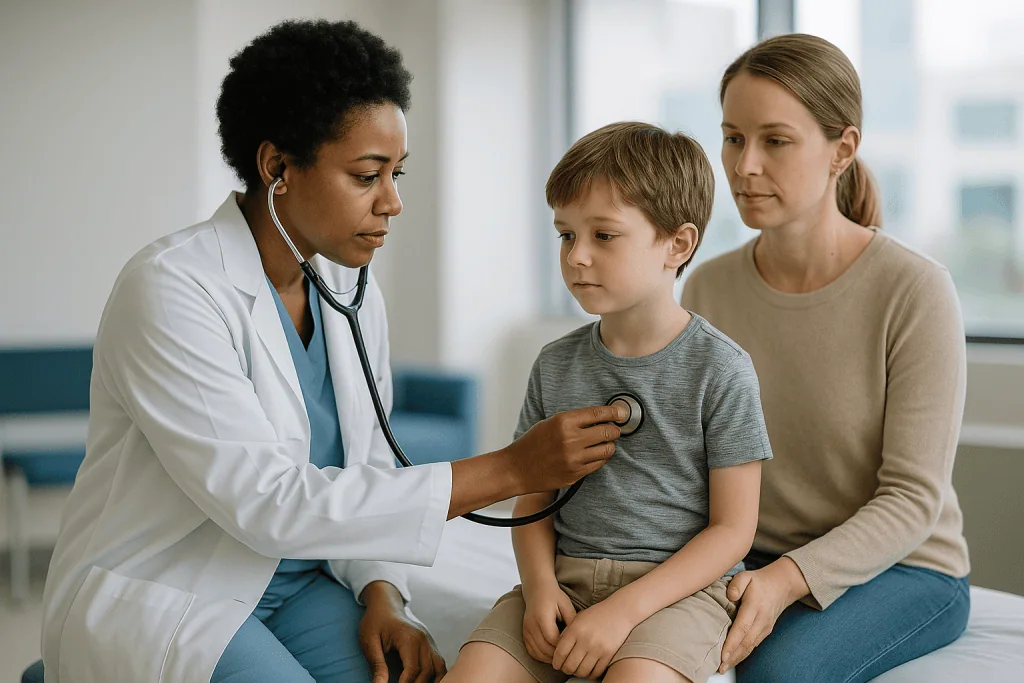
The biggest structural change came in 2011, when pulse oximetry screening for critical congenital heart defects was added to the recommended newborn screening panel in the United States. Pulse oximetry is a painless clip on a baby’s hand and foot that measures blood oxygen. The CDC reports that by 2018 every state had a screening policy in place. The practical effect is that the most dangerous heart defects, the ones that once surfaced as a collapsed newborn, are now usually caught in the first two days of life, before a stethoscope finding would ever have been the first clue.
The CDC’s current data pages estimate that congenital heart defects affect nearly 1 percent of births, roughly 40,000 babies a year in the United States, and that about one in four of those babies has a critical defect needing surgery or a procedure in the first year. Those numbers have been stable; what is new is that most of those children are identified before they leave the hospital.
Echocardiography has also become faster and more available, so a child flagged at a sports physical can often be scanned within days rather than months. That speed is good medicine, but it also feeds the viral narrative, because a referral now happens so quickly that it looks like an emergency on camera.
As of September 2026, major patient resources from the American Heart Association, Mayo Clinic, and Cleveland Clinic still say the same thing they said a decade ago: most murmurs in children are innocent and require no treatment. The guidance has not moved. The volume around it has.
How common are heart murmurs in children?
Very common, and the honest answer depends on who is listening and how hard. Studies that have pediatric cardiologists examine groups of healthy children have found a murmur in anywhere from about a third to well over half of them at some point during childhood, with some auscultation surveys reporting even higher figures when children were examined repeatedly across ages. Cleveland Clinic and Johns Hopkins both frame it the same way: a murmur is one of the most frequent findings in a routine pediatric exam.
Set that against the rate of actual heart defects. If roughly 1 in 100 babies is born with a structural heart problem, and a murmur can be heard in something like 40 to 70 of every 100 children at some stage, then the arithmetic alone tells you most of those sounds are not coming from a defect. Many children with a murmur have been examined dozens of times by the time they are twelve, and each exam is another chance to notice normal flow.
Age shapes the picture. Newborns can have a soft murmur in the first day or two as the circulation reorganizes itself after birth; a murmur that appears in the first weeks and persists is taken more seriously because that is when defects declare themselves. The peak years for innocent murmurs are roughly ages 2 to 7, when the chest is thin and the heart is relatively large and fast. Teenagers often hear nothing new at all, until a growth spurt or an athletic season brings them to a physical and a clinician listens with fresh ears.
The takeaway from the numbers is not that murmurs should be waved away. It is that the base rate strongly favors a benign explanation, so the job of the exam is to find the uncommon child whose sound means more.
The innocent heart murmur in kids: the three sounds doctors hear most
Pediatricians learn to recognize a handful of innocent murmurs by ear the way a mechanic knows the normal tick of a cooling engine. Three account for the great majority.

Still’s murmur is the classic one. It has a musical, almost vibrating quality, sometimes described as a plucked string, and it is heard low on the left side of the chest in children between about 2 and 7. It is louder when the child lies on their back and softer or gone when they sit up, a behavior that a structural problem rarely copies. MedlinePlus lists it among the typical functional murmurs of early childhood.
A pulmonary flow murmur is a soft, blowing sound heard at the upper left edge of the breastbone. It comes from blood moving briskly into the artery that feeds the lungs. It is most common from about age 8 into the mid-teens, and it tends to be louder when a child has a fever, is anxious, or has just run in from the parking lot.
A venous hum is a continuous, low humming heard just under the collarbone, usually on the right. It is not from the heart at all but from blood draining back through the large neck veins. Gently pressing on the neck, turning the head, or lying the child flat makes it vanish, which is the giveaway.
What unites them is that they are soft (grade 1 or 2 out of 6), they occur during the squeeze phase, they do not travel to the back or neck, and they change with position. A child with an innocent heart murmur in kids has a normal pulse, normal color, normal growth, and no symptoms. When all of those line up, mainstream guidance from Mayo Clinic and Cleveland Clinic is clear: no treatment, no restrictions, and frequently no further testing.
How serious is a heart murmur in children?
For most children, not serious at all. The murmur itself never causes harm; it is only a signal. The question a clinician is really asking is whether the signal comes from normal flow or from a structure that is shaped differently than it should be.
Several features push a murmur into the “needs a closer look” column. Loudness is one: a grade 3 or higher murmur, especially one that feels like a buzz under the examiner’s fingers, is more likely to reflect a real pressure difference inside the heart. Quality is another. Innocent murmurs are soft and musical; a harsh, rasping sound, or one that fills the whole squeeze phase, raises concern. Timing matters most of all. Any murmur heard during the relaxation phase is treated as significant until proven otherwise, because a healthy heart does not make turbulent noise while refilling.
Where the sound travels is informative. A murmur that radiates to the neck suggests the valve leading out of the heart; one that radiates to the back suggests the vessel to the lungs. Extra sounds, such as a sharp click or an abnormally split second heart sound, also point toward a valve.
Context can outweigh all of it. A murmur in a newborn who is feeding poorly, breathing fast, or looking dusky is urgent regardless of how it sounds. A murmur in a child who faints during exercise, tires far sooner than peers, or has chest pain with exertion deserves prompt specialist evaluation. So does a murmur in a child with a genetic condition known to involve the heart, or a family history of sudden cardiac death at a young age.
The reverse is also true. A soft, positional, systolic murmur in a thriving six-year-old with no symptoms is, by every mainstream standard, a normal finding.
What could be causing a heart murmur in a child with a fever?
This is one of the most common reasons a murmur is heard for the first time, and the explanation is usually simple. Fever speeds the heart and increases the amount of blood it pumps each minute, a response called high cardiac output. More blood moving faster through normal valves creates more turbulence, and a sound that was inaudible last month becomes easy to hear. The same thing happens with crying, pain, dehydration, and anxiety, all of which ramp up the heart in a sick child.
Pediatricians handle this by noting the murmur and then listening again once the child is well. If the sound has faded or disappeared at the follow-up visit, it was almost certainly a flow murmur amplified by illness. Mayo Clinic specifically lists fever among the situations that can make an innocent murmur appear or grow louder.
Anemia, a shortage of red blood cells, works the same way. Thinner blood flows faster, and a child who has been pale and tired may have a soft murmur that resolves when the anemia is treated.
Two rarer possibilities explain why a doctor does not simply dismiss every feverish murmur. Acute rheumatic fever is an immune reaction that can follow an untreated strep throat by two to four weeks and can inflame heart valves; it is uncommon in the United States but still occurs. Infective endocarditis, an infection of the heart’s inner lining or valves, is rare in children with normal hearts but more likely in those with known defects or certain devices; a new murmur together with days of unexplained fever is one of its classic patterns.
So the practical rule for a heart murmur in a child with a fever is reassurance plus a recheck, with faster evaluation if the fever is prolonged, the child looks unwell, or there is a history of strep throat or a heart condition.
Which heart problems can cause a murmur in a child?
When a murmur is not innocent, the cause is most often a congenital heart defect, meaning a difference in the heart’s structure present from birth. A few patterns account for most cases.
A ventricular septal defect (VSD) is a hole in the wall between the heart’s two lower pumping chambers. It is the most common congenital heart defect overall, and the murmur it makes is typically loud, harsh, and heard best along the lower left edge of the breastbone. Counterintuitively, small holes often make the loudest noise, because blood is forced through a tight gap at high pressure.
An atrial septal defect (ASD) is a hole between the upper chambers. Its murmur is softer and comes from extra blood flowing through the lung artery, which is why it can be mistaken for an innocent pulmonary flow murmur; the clue is a fixed, split second heart sound that does not change with breathing.
A patent ductus arteriosus (PDA) is a fetal blood vessel that is supposed to close after birth but stays open. It produces a continuous, machinery-like murmur beneath the left collarbone.
Valve problems make up the rest. Pulmonary stenosis and aortic stenosis are narrowed valves that force blood through a smaller opening; both produce harsh murmurs, and the aortic version radiates to the neck. A bicuspid aortic valve, a valve with two leaflets instead of three, is common and may be silent for years before an echocardiogram finds it.
Hypertrophic cardiomyopathy, a thickening of the heart muscle that can run in families, deserves a special mention because its murmur gets louder when a child stands up, the opposite of innocent murmurs. The CDC and NHS resources on congenital heart disease describe how many of these conditions are now identified in infancy, but milder forms can surface later, which is exactly why the school-age exam still matters.
What happens at the pediatrician's exam when a murmur is heard
Parents sometimes feel the stethoscope lingers forever. In reality the doctor is running through a short, deliberate checklist, and most of it has nothing to do with the sound itself.
First comes the whole child. Is growth tracking normally on the chart? Is the color pink, the breathing easy, the energy level ordinary? A murmur in a child who is thriving carries very different odds from the same sound in a child who is falling off the growth curve or breathless with feeds.
Then the pulses. The clinician feels the pulse at the wrist and in the groin at the same time; a weak or delayed pulse in the legs can point to coarctation, a narrowing of the body’s main artery. Blood pressure in an arm and sometimes a leg serves the same purpose. In infants, oxygen saturation may be checked with a fingertip or toe sensor.
Only then does the detailed listening begin, and it is deliberately theatrical. The child lies flat, then sits, then stands, and may be asked to squat and rise. Innocent murmurs typically soften or vanish when a child sits or stands, because less blood returns to the heart in that position. A murmur that grows louder on standing is a different animal. The doctor also listens over the neck, under the collarbones, and on the back.
Family history is the last piece: sudden unexplained death in a relative under 50, cardiomyopathy, or a known inherited condition raises the bar for referral.
If everything fits the innocent pattern, many pediatricians will document the murmur, explain it, and simply recheck at the next well visit. If anything does not fit, or if the parents remain worried, the next step is a pediatric cardiologist, which brings the one test that settles most questions.
What will a pediatric cardiologist do for a heart murmur?
A pediatric cardiologist for heart murmur evaluation starts exactly where the pediatrician did, with ears. Experienced specialists are remarkably accurate at sorting innocent from structural murmurs by listening alone, and some visits end after the exam with a confident “this is normal.”
When imaging is needed, the test is an echocardiogram, an ultrasound of the heart. A technologist spreads warm gel on the chest and glides a small probe across it while the child watches a cartoon; the scan typically takes 30 to 45 minutes, involves no radiation, and no needles. It shows the chambers, the walls between them, each valve opening and closing, and, using color, the direction and speed of blood flow. If there is a hole, a narrowed valve, or a leaky one, the echocardiogram shows it, and it can also measure how much the heart is being affected.
An electrocardiogram (ECG), a few minutes of stickers on the chest recording the heart’s electrical rhythm, is often done alongside. It can hint at an enlarged chamber or a muscle problem and is useful when the history includes fainting or palpitations.
A chest X-ray is used less often than it once was but can show heart size and the pattern of blood flow to the lungs. For older children with exercise symptoms, a treadmill test may be added. Infants and children who cannot lie still for an echocardiogram are occasionally given a mild sedative under supervision; that decision belongs entirely to the cardiology team.
The outcome of the visit falls into three bins. The heart is normal and the family is discharged, which is the most common result. A minor finding is identified that needs a recheck in months or years. Or a defect is found that needs treatment, in which case the cardiologist outlines options, timing, and follow-up for that specific child.
Innocent versus worrying murmurs at a glance
Clinicians carry a mental table when they listen. A simplified version of it is below. No single row decides the matter; it is the overall pattern, combined with the child’s history and exam, that guides the decision. Parents should not try to grade a murmur themselves; the table is here so the pediatrician’s reasoning makes sense.
| Feature | Typical of an innocent murmur | Prompts further evaluation |
|---|---|---|
| Loudness (scale 1–6) | Grade 1–2, soft | Grade 3 or louder, or a vibration felt by hand |
| Timing in the heartbeat | Short, during the squeeze phase only | During the relaxation phase, or filling the whole squeeze |
| Quality | Musical, vibratory, blowing | Harsh, rasping, machinery-like |
| Change with position | Softer or gone when sitting or standing | Unchanged, or louder on standing |
| Radiation | Stays in one small area | Travels to the neck, back, or armpit |
| Other heart sounds | Normal | Clicks, fixed split second sound |
| The child | Thriving, active, no symptoms | Poor growth, breathlessness, fainting, blue tinge |
| Age of first detection | Ages 2–14 at a routine visit | First days to weeks of life, persisting |
Two notes on reading this. The “age” row is a probability, not a rule; plenty of innocent murmurs are first noticed in infancy, and some defects are quiet until later childhood. And the “child” row deserves more weight than any sound: a well child with an atypical murmur usually turns out fine on echocardiography, while an unwell child with a soft murmur needs attention regardless.
Mayo Clinic, Cleveland Clinic, and MedlinePlus all describe these same distinguishing features in their patient guidance, which is reassuring in itself: there is no disagreement among mainstream sources about what separates the two groups.
Can kids grow out of a heart murmur?
Innocent murmurs, yes, and most do. The thin chest wall thickens, the heart’s output per kilogram of body weight falls as a child grows, and the sound that was obvious at five is often inaudible by fifteen. Many adults who are told they had a murmur as a child have no trace of it on a modern exam. Cleveland Clinic puts it plainly: innocent murmurs usually disappear as the child gets older, and even if one persists into adulthood it causes no problems.
The more interesting version of the question is whether a child can grow out of a murmur caused by a defect, and here the answer is sometimes, depending on the defect. Observational follow-up studies of small ventricular septal defects, particularly those in the muscular part of the wall, show that a large share close on their own in the first years of life, often by the time a child starts school. Small patent ductus vessels can also close spontaneously in the early months, especially in babies born at term. Some small atrial septal defects close or shrink in infancy as well.
Larger holes and narrowed valves do not close themselves, and that is where the cardiologist’s follow-up matters. Repeat echocardiograms over months or years track whether a defect is shrinking, stable, or beginning to strain the heart, and that trajectory, not the murmur’s loudness, drives any decision about a procedure.
One more wrinkle: a murmur can seem to vanish and reappear. A pulmonary flow murmur that fades over a healthy summer may return with a winter virus or a growth spurt. That is not a sign of anything new; it is the same flow sound reacting to the same ordinary triggers. If a pediatrician has documented a murmur as innocent, its coming and going does not require a fresh workup unless new symptoms appear.
What the evidence actually says
Readers deserve to know how firm the ground is, so here is the evidence sorted by strength.
The claim that most murmurs in children are innocent rests on decades of observational data: cross-sectional surveys in which clinicians examined large groups of healthy children, and cohort studies that followed children with murmurs to see what became of them. These consistently show a high prevalence of murmurs against a congenital heart defect rate near 1 percent. The data are observational, not randomized, but the finding is so consistent across countries and decades that no mainstream source disputes it. Grade: strong observational evidence.
The claim that a trained examiner can reliably distinguish innocent from structural murmurs by listening comes from diagnostic accuracy studies in which cardiologists’ bedside judgments were compared against echocardiography. Specialist exams perform well, with high sensitivity and specificity in several series; general pediatricians perform somewhat less consistently, which is precisely why referral pathways exist. Grade: moderate-quality diagnostic studies, dependent on examiner experience.
The claim that small ventricular septal defects often close spontaneously is supported by longitudinal echocardiographic follow-up cohorts. Grade: moderate observational evidence, with closure rates varying by defect location and size.
The value of newborn pulse oximetry screening is backed by large population studies showing earlier detection of critical defects, and it carries a formal public health recommendation in the United States. Grade: strong observational and implementation evidence; there are no randomized trials, for obvious ethical reasons.
Where is the evidence thin? There is no randomized trial on whether to image every murmur or only atypical ones; that decision is guided by expert consensus and cost of missed diagnoses, and practice varies. The precise prevalence figure for innocent murmurs also varies widely because it depends on who listens and how often. In short, the reassuring headline is robust; the fine print is expert opinion informed by good observational data.
Common myths about heart murmurs in children
The viral clips circulating this season lean on a few durable misconceptions. Each one has a short, evidence-based correction.
“A murmur means my child has heart disease.” A murmur means blood is making noise. In the large majority of children that noise comes from a normal heart. The base rate alone, roughly 1 in 100 children with a defect versus a murmur in a large share of all children, makes the innocent explanation the likeliest one before any test is done.
“If it were innocent, the doctor would not have referred us.” Referral is a tool for certainty, not a verdict. Many cardiologists spend a good part of their clinic reassuring families whose child was referred for a murmur that turns out to be normal, and that is the system working as designed.
“A louder murmur is a worse murmur.” Loudness is one clue among many. Small holes can produce loud murmurs because blood squeezes through a tight gap, while some serious conditions produce faint sounds or none. Timing, quality, and the child’s overall health matter more.
“Kids with murmurs cannot play sports.” A child with a documented innocent murmur has no activity restrictions. Children with specific diagnosed conditions may have individualized guidance from their cardiologist, but that is a conversation about a diagnosis, not about a sound.
“A murmur that comes back after disappearing is a new problem.” Innocent flow murmurs routinely fade and return with fever, exercise, anemia, or growth. The pattern is expected.
“A heart murmur in children always needs an echocardiogram.” Not according to mainstream guidance. When the exam fits the innocent pattern in a well child, Mayo Clinic and Cleveland Clinic both describe watchful follow-up as appropriate. Imaging is for atypical findings, symptoms, or uncertainty, and the choice belongs to the examining clinician.
When to see a doctor
Most murmurs are found by a doctor, not a parent, so the practical question is when a known or suspected murmur needs a prompt appointment rather than the next routine visit. The symptoms below are the ones pediatric and cardiology sources consistently flag. They matter whether or not a murmur has ever been mentioned.
- In a baby: fast or labored breathing, sweating or tiring during feeds, poor weight gain, or a blue or gray tinge to the lips, tongue, or skin.
- Fainting or near-fainting, especially during or just after exercise.
- Chest pain with exertion, or a racing, pounding heartbeat that comes on without an obvious reason.
- Becoming breathless or exhausted far sooner than other children during play or sport.
- A murmur first heard in the first days or weeks of life that does not go away.
- Fever lasting more than a few days with a new murmur, particularly after a recent strep throat or in a child with a known heart condition.
- A family history of sudden unexplained death under age 50, cardiomyopathy, or an inherited heart condition.
Seek emergency care immediately for a child who is struggling to breathe, turning blue, collapsing, or who cannot be roused.
For everything else, the pediatrician is the right starting point. Bring notes on when the murmur was first mentioned, what the child was doing at the time, any illnesses since, and the family history. If a referral to a pediatric cardiologist is made, ask what the clinician heard, what the specialist will be looking for, and whether any activity should be limited in the meantime; for an innocent murmur the answer is usually none.
Every decision about testing, follow-up, activity, and treatment for a child with a murmur belongs to the clinician who has examined that child. This article explains the reasoning; it cannot replace the exam.
Frequently asked questions
How serious is a heart murmur in children?
Usually not serious at all; most are innocent sounds from a normal heart and need no treatment. A murmur becomes a concern when it is loud, harsh, heard during the heart’s relaxation phase, louder on standing, or found in a child who is breathless, fainting, growing poorly, or blue-tinged. Those cases are referred to a pediatric cardiologist for an echocardiogram to find the cause.
What will a pediatric cardiologist do for a heart murmur?
The cardiologist repeats a detailed listening exam in several positions, checks pulses and blood pressure, reviews family history, and often orders an echocardiogram, a painless heart ultrasound. An ECG may be added. Most children are found to have a normal heart and are discharged; a minority have a defect that is then followed or treated according to the cardiologist’s plan.
Can kids grow out of a heart murmur?
Innocent murmurs usually fade as the chest wall thickens and the heart’s output per body weight falls, often disappearing by the teenage years. Some structural causes also resolve: observational studies show many small ventricular septal defects and some small patent ductus vessels close on their own in early childhood. Larger defects do not close by themselves and are monitored by a cardiologist.
What could be causing a heart murmur in a child with a fever?
Most often the fever itself: a faster heart pumping more blood creates turbulence that makes a normal flow sound audible, and it typically disappears when the child recovers. Anemia can do the same. Rarely, prolonged fever with a new murmur can signal rheumatic fever after strep throat or an infection of the heart lining, so a doctor rechecks and investigates if the fever persists.
What does an innocent heart murmur in kids sound like?
To a clinician it is a soft, short, musical or blowing sound during the squeeze phase of the heartbeat, graded 1 or 2 on a 6-point loudness scale. The best-known type, Still’s murmur, has a vibrating, plucked-string quality and is loudest when a child lies flat. Innocent murmurs stay in one area and do not travel to the neck or back.
Does every child with a murmur need an echocardiogram?
No. Mainstream guidance from Mayo Clinic and Cleveland Clinic describes watchful follow-up as appropriate when the exam fits the innocent pattern in a well child. An echocardiogram is used when the murmur has atypical features, the child has symptoms, there is a concerning family history, or the pediatrician is uncertain. The decision rests with the examining clinician.
Can a child with a heart murmur play sports?
A child with a documented innocent murmur has no activity restrictions and can take part fully in sports. If a murmur has not yet been evaluated and the child has fainting, chest pain, or unusual breathlessness with exercise, those symptoms should be assessed before strenuous activity. Children with a diagnosed heart condition receive individualized guidance from their cardiologist.
Why was my newborn's murmur treated differently from my six-year-old's?
Because the odds differ by age. In the first days and weeks of life, the circulation is still adjusting and congenital defects tend to declare themselves, so a persistent newborn murmur is investigated more readily. By school age, a soft positional murmur in a thriving child is overwhelmingly likely to be innocent, and pediatricians weigh that base rate heavily.
Is a loud heart murmur in a child worse than a quiet one?
Not necessarily. Loudness is one clue among several, and small holes between heart chambers can produce surprisingly loud murmurs because blood is forced through a narrow gap. Timing in the heartbeat, harshness, radiation to the neck or back, changes with standing, and the child’s overall health and growth carry more weight in deciding whether imaging is needed.
What should I ask the doctor if my child has a heart murmur?
Useful questions include: what did you hear and where, does it fit an innocent pattern, do you want to recheck it when my child is well, is a cardiology referral or echocardiogram needed, should any activity be limited in the meantime, and which symptoms should bring us back sooner. Bringing notes on illnesses and family heart history helps the doctor answer.
References
- MedlinePlus: Heart murmurs and other sounds
- Cleveland Clinic: Heart murmur
- CDC: Data and statistics on congenital heart defects
- NHS: Congenital heart disease
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Incomplete Kawasaki Disease: How Pediatricians Decide to Treat When Not Every Sign Appears
Incomplete Kawasaki disease is diagnosed when a child has prolonged, unexplained fever with only two or three of the five classic signs instead of…

How Viral Croup Is Assessed and Treated: Oxygen Checks, Airway Swelling and Monitoring
Viral croup is treated by calming the child, checking oxygen levels and breathing effort, and reducing airway swelling. Most children need only rest, fluids…

When Whooping Cough Needs Hospital Care: Monitoring, Breathing Support and Hydration
Whooping cough (pertussis) needs hospital care mainly when a baby under about six months, or anyone with severe disease, has pauses in breathing, turns…

Is Bronchiolitis Contagious? Daycare Return, Sibling Contact and Hand Hygiene Explained
Bronchiolitis itself is not passed from child to child; the viruses that cause it are. The most common one, RSV, is usually contagious for…

How a Developmental Delay Assessment Works: Hearing, Vision, Milestones and Specialist Reviews
A developmental delay assessment is a staged evaluation of how a child is progressing in movement, language, thinking and social skills. It usually begins…

How Much Exercise Do Kids Need? The Guidelines and Why Play Counts
Children aged 5 to 17 need an average of at least 60 minutes a day of moderate-to-vigorous physical activity across the week, according to…