

How Arm Liposuction Is Performed: Incision Points, Cannula Passes and Time Under Anesthesia

Key Takeaways
- Arm liposuction uses two or three openings of about 3 to 5 mm, most often at the elbow crease and the back fold of the armpit, so the surgeon can tunnel through the fat from two directions.
- Tumescent fluid, a mix of salt water, local anesthetic and epinephrine, is infused before suction and is the main reason modern liposuction involves far less bleeding than older techniques.
- The NHS gives a typical liposuction operating time of one to three hours, and an arm-only procedure usually sits toward the shorter end, with marking and infusion included in that window.
- Liposuction removes fat but cannot tighten skin; patients whose main concern is loose, draping skin are usually assessed for an arm lift (brachioplasty), which leaves a longer scar.
- Arms commonly look the same size or larger in the first week because of retained fluid, inflammation and bruising, and the Mayo Clinic notes final contour can take several months to appear.
- Published guidance suggests one to two weeks off work, compression for several weeks and avoiding strenuous activity for about four to six weeks, with the exact plan set by your surgical team.
Arm liposuction removes fat from the upper arm through two or three small skin openings, usually near the elbow crease and the back fold of the armpit. After the area is filled with tumescent fluid, a thin hollow tube called a cannula is passed back and forth to loosen and suction fat. It is done under local anesthesia with sedation or general anesthesia, and published operating times for liposuction run roughly one to three hours.
She had already decided which jacket she was wearing to the consultation: the one with sleeves that stop just above the elbow, the one she had bought and never worn outside the house. Her question for the surgeon was not whether the procedure existed. It was mechanical, almost engineering-minded. Where exactly do the openings go? What is the tube doing under the skin? How long will I be asleep?
Those are the right questions, and they are rarely answered in plain language. Most pages about how arm liposuction is done jump straight to gallery photos or to a comparison with an arm lift. Fewer explain that the operation is essentially a sequence of three events: numbing and swelling the fat layer with fluid, tunneling through it with a cannula, and then managing the body’s reaction for the weeks that follow.
This article walks through each of those events, the choices a surgical team makes along the way, and the honest limits of what fat removal can change in an arm.
How is arm liposuction done, step by step?
Strip away the branding and the devices, and arm liposuction is a four-stage procedure. Each stage has a job, and understanding the job makes the rest of the explanation fall into place.
The first stage is marking. With the patient standing, because fat settles differently when lying down, the surgeon draws the zone to be treated on the back and outer upper arm, plus the small areas where fullness often spills toward the armpit. Standing marks are the map the surgeon will follow once the patient is horizontal and the landmarks flatten out.
The second stage is anesthesia and fluid. Once the patient is comfortable, the fat layer is infused with tumescent fluid, a mixture of salt water, a local anesthetic and a tiny amount of epinephrine (a medicine that narrows blood vessels). The Mayo Clinic describes this as the most common liposuction technique; the fluid firms the fat so it is easier to remove and reduces bleeding.
The third stage is the actual fat removal. Through openings a few millimeters long, a cannula, which is a narrow hollow metal tube attached to suction, is passed repeatedly through the fat in a fan pattern. Some surgeons add energy to this step: ultrasound, laser or a motorized back-and-forth movement of the cannula. These are variations on the same principle rather than different operations.
The fourth stage is closure and compression. Openings may be closed with a stitch or left partly open so fluid can drain, and the arm is wrapped in a compression sleeve. According to the NHS, most people go home the same day or after one night, depending on how much was treated and the type of anesthesia used. The operation ends there; the result does not. The arm the patient sees in the first weeks is a swollen draft.
Where do the incisions go on the arm?
Readers often picture a long cut. In reality, the openings for arm liposuction are closer to the size of a grain of rice, typically 3 to 5 mm, just wide enough to admit the cannula. What matters more than their size is their placement, because placement decides two things: whether the surgeon can reach the whole treatment zone, and whether the marks will be visible when the arm is at rest.

Three sites are used most often, alone or in combination:
- The elbow crease or just above it on the inner side, which gives a straight line of access up the back of the arm.
- The posterior axillary fold, the ridge of skin at the back of the armpit, which allows the surgeon to work downward and reach the fullness near the shoulder.
- Occasionally a third point on the back of the arm itself, when the surgeon needs to cross-hatch the fat from a different direction.
Working from two directions is not decoration. Tunnels that cross each other at an angle break the fat up more evenly than tunnels that all run the same way, and uneven removal is one of the recognized complications listed by the Mayo Clinic under contour irregularities.
The scars from these openings usually fade to small pale dots, though the NHS notes that scarring is a possibility with any liposuction and that scars can be more noticeable in some skin types. If you are prone to raised or dark scars, that history belongs in the consultation; it may shift where the surgeon chooses to enter and how the openings are closed.
What is tumescent fluid, and why does it matter so much?
The word tumescent simply means swollen. Before any fat is removed, the surgeon pumps enough fluid into the arm’s fat layer that the tissue becomes firm and slightly pale, sometimes two or three times the volume that will eventually be suctioned out. To someone watching for the first time, this step looks like it is going the wrong way. The arm gets bigger before it gets smaller.
The fluid does three things at once. The salt water separates fat cells from the surrounding connective tissue, so they come away with less tearing. The local anesthetic numbs the area, which is why some arm procedures can be done with light sedation rather than general anesthesia. The epinephrine constricts small blood vessels, and that is the component with the biggest safety effect: it dramatically reduces blood loss compared with older dry techniques, as described by MedlinePlus.
There is a trade-off, and it is the one worth understanding. The local anesthetic in tumescent fluid is absorbed into the bloodstream over the hours after surgery. Surgeons calculate the total amount based on body weight and the areas treated; the Mayo Clinic lists lidocaine toxicity as a rare but recognized liposuction risk, and it is one of the reasons surgeons limit how many areas are treated in a single session. This article does not discuss amounts, because that calculation is the anesthesia team’s responsibility and depends entirely on the individual.
After the infusion, there is usually a pause of 10 to 20 minutes while the epinephrine takes effect. Patients under sedation are often unaware of this interval, but it is part of why a seemingly small procedure still occupies an operating room for a meaningful block of time.
Cannula passes: what the surgeon is actually doing under the skin
Once the fluid has settled, the surgeon introduces the cannula through one of the small openings and begins a repetitive motion that looks almost like gentle sawing. Each forward-and-back movement is a pass. Over the course of an arm, there may be several hundred of them, and the skill lies in distributing those passes so no single spot is overworked.
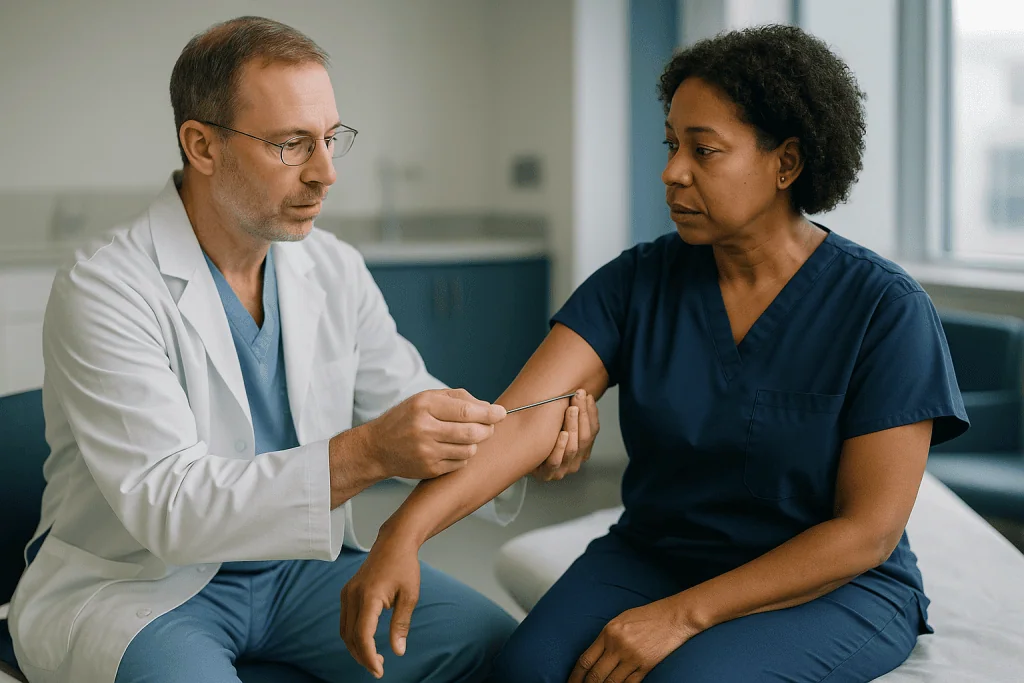
Picture the fat layer as a block of soft cheese, and the cannula as a straw pushed through it again and again from the same hole. Each push leaves a tunnel. Spread the tunnels evenly, from two entry points at different angles, and the block shrinks uniformly. Concentrate them in one place and you get a dent. That dent, once healed, is very difficult to correct, which is why experienced surgeons remove slightly less than they could and leave a thin, even cushion of fat beneath the skin.
Cannulas for the arm tend to be narrower than those used for the abdomen or thighs, because the arm’s fat layer is thinner and the skin above it is less forgiving. The surgeon’s non-dominant hand rests on the outside of the arm throughout, feeling the tip of the cannula through the skin and judging thickness by pinch. This tactile feedback, not a screen, is the primary guide.
Energy-assisted variants change the feel of the step rather than its goal. Ultrasound-assisted liposuction uses sound waves to liquefy fat before suction; laser-assisted uses light energy to do something similar; power-assisted uses a motorized cannula that vibrates rapidly, reducing the physical effort of each pass. The Mayo Clinic describes all three as variations in current use. None of them has been shown in guideline-level evidence to produce a reliably better arm result than careful tumescent technique, and the choice usually reflects the surgeon’s training and the characteristics of the patient’s tissue.
Time under anesthesia: local, sedation or general, and how long?
The anesthesia question is where arm liposuction differs most from one patient to the next, and where the answer should come from the anesthesia team rather than a website. Three broad approaches exist.
Local anesthesia alone means the tumescent fluid does all the numbing, and the patient is awake. Local with sedation adds medicine through a vein that produces relaxation or light sleep; the patient breathes on their own. General anesthesia means the patient is fully unconscious and breathing is supported. MedlinePlus notes that smaller-volume liposuction is often done under local anesthesia with sedation, while larger or multi-area procedures tend to use general anesthesia. Arms, treated on their own, frequently fall into the first category, but body size, anxiety, other medical conditions and whether other areas are being treated in the same session all move the decision.
As for duration, the NHS gives a typical liposuction operating time of one to three hours. An arm-only procedure usually sits toward the shorter end of that window, but the clock in the operating room includes the marking, the fluid infusion and the waiting period for the epinephrine, not just the suction itself. Add recovery-room observation, and a morning procedure typically becomes an afternoon discharge.
Why does time under anesthesia matter beyond convenience? Longer procedures carry slightly higher risks of blood clots in the legs, body-temperature drop and fluid shifts, which is why guidelines favor limiting the total volume and number of areas treated in one sitting. If a surgeon proposes combining arm liposuction with other areas, asking how that changes the anesthesia plan and the expected duration is a reasonable and welcome question.
Who is arm liposuction usually for, and who is usually asked to wait?
The honest summary is that arm liposuction works best for the patient who needs it least. The procedure removes fat; it does not tighten skin, build muscle or change the shape of the bone and tendon that give an arm its underlying outline. The people who do well tend to share a short list of features.
Candidates typically have a body weight that is stable and within a modest range of their personal healthy weight. The Mayo Clinic is explicit that liposuction is a contouring procedure, not a weight-loss method, and that good candidates have firm, elastic skin and no serious health conditions. On the arm, that means a pocket of fullness you can pinch between thumb and finger that does not disappear with exercise, sitting above skin that snaps back rather than hanging.
Surgeons commonly ask people to wait, or to consider a different approach, in several situations:
- When the main concern is loose, draping skin rather than fat, because removing the fat beneath loose skin can make the drape more obvious.
- During active weight loss, pregnancy or breastfeeding, or soon after major weight change, because the arm’s contour is still moving.
- When smoking or nicotine use is ongoing, since nicotine impairs wound healing; the NHS and Mayo Clinic both flag this across cosmetic surgery.
- When there is a history of blood clots, bleeding disorders, poorly controlled diabetes or heart or kidney disease, because these change the risk profile of anesthesia and fluid shifts.
- When expectations are centered on a specific photograph or a specific measurement rather than on general improvement.
None of these is a permanent no. They are reasons to pause, optimize and sometimes revisit the question. The decision rests with the surgical team, who will weigh skin quality, health history and goals together rather than any one factor alone.
Arm lipo vs arm lift: which addresses what?
This is the comparison people search for most, and it is also the one that causes the most disappointment when it is skipped. Liposuction and brachioplasty (the medical term for an arm lift, an operation that removes excess skin along the inner arm) solve different problems and leave very different marks.
| Feature | Arm liposuction | Arm lift (brachioplasty) |
|---|---|---|
| What it removes | Fat only | Skin, often with some fat |
| Best suited to | Good skin elasticity, localized fullness | Loose, hanging skin, often after major weight loss |
| Incisions | Two to three openings of a few millimeters | A scar running from armpit toward elbow, length varies |
| Anesthesia | Local with sedation or general | Usually general |
| Typical operating time (published liposuction range) | 1–3 hours per the NHS, arms often shorter | Longer; depends on extent |
| Main trade-off | Cannot tighten skin | Visible permanent scar |
The table hides one nuance. Many patients fall between the two columns: moderate fat, mildly loose skin. For them, surgeons sometimes combine the procedures, using liposuction to debulk and a shorter skin excision confined to the armpit to tighten. Others recommend liposuction first and reassess once swelling settles, because skin that was stretched by fat sometimes retracts more than expected, particularly in younger patients.
What the evidence cannot tell you is which column you belong in. That judgment comes from a pinch test, an assessment of skin recoil and a conversation about how you feel about a scar. The Cleveland Clinic frames liposuction as most effective when skin can contract to the new contour, and that single sentence is the hinge on which the arm lipo vs arm lift decision turns.
How painful is arm liposuction, honestly?
Pain after liposuction is usually described as deep soreness rather than sharp pain, and the arm has a specific character to it. Because the treated zone sits over muscles you use constantly, the triceps and the muscles that lift the shoulder, ordinary movements such as reaching for a cupboard or pushing up from a chair tend to remind you of the surgery for the first several days.
Three things shape how much discomfort a person feels. The first is the extent of the procedure: more passes and a larger treatment zone mean more bruising. The second is the tumescent fluid itself, which continues to provide some numbing for hours after surgery; many patients report the first evening as surprisingly manageable and the second and third days as the peak. The third is the compression sleeve, which some people find reassuring and others find the most irritating part of recovery.
The Mayo Clinic describes pain, swelling and bruising as expected after liposuction and notes that the surgeon may prescribe pain relief. This article does not discuss which medicines or how much; that plan comes from the prescribing clinician and depends on your health history. What can be said generally is that most patients transition from prescription to over-the-counter relief within days, and that numbness or tingling in the treated skin is common and usually temporary, though the Mayo Clinic lists lasting numbness among possible complications.
A practical note that rarely appears in brochures: the back of the arm is hard to see and hard to ice. Arranging help for the first two or three days, especially with tasks that involve lifting the arms above the head, does more for comfort than any single product.
Arm liposuction recovery time: what the first weeks usually look like
Recovery from arm liposuction is less a straight line than a series of plateaus. The timelines below are typical ranges drawn from published patient guidance, not promises; your own surgeon’s instructions take precedence.
In the first 48 to 72 hours, expect the arms to feel heavy, tight and bruised. Fluid may seep from the openings, which is normal and is one reason surgeons sometimes leave them unstitched. The compression sleeve stays on almost continuously. Short walks around the house are encouraged from the first day, because moving the legs reduces the risk of blood clots, a point emphasized by the CDC for anyone recovering from surgery.
By the end of the first week, bruising is usually at its most colorful and starting to shift from purple toward yellow. Many people with desk-based work return at this point; the NHS suggests allowing one to two weeks off work after liposuction, longer if your job is physical. The Mayo Clinic gives a similar picture: a few days before returning to work and a few weeks before resuming normal activities.
Weeks two through six are the compression and patience phase. The NHS advises wearing the elasticated garment for several weeks and avoiding strenuous activity for about four to six weeks. Lifting weights, swimming and racket sports fall into that category; walking does not.
From six weeks onward, the arm begins to look like the arm. Swelling continues to resolve slowly, and the Mayo Clinic notes it may take several months for the final contour to appear. Firmness or lumpiness in the treated area during this period is common and usually softens; your surgeon may suggest gentle massage, and the follow-up visits during these months are where small concerns get caught early.
Do my arms still look bigger after arm lipo?
Yes, at first, and the reason is physical rather than a sign that something went wrong. Three separate processes make a freshly treated arm larger than the arm that walked into the operating room.
The first is residual tumescent fluid. Not all of what was infused comes back out through the cannula; the remainder is absorbed over the following days, and until it is, the arm carries extra volume. The second is inflammation. Every tunnel the cannula made is a small injury, and the body responds by sending fluid and immune cells to the area. The third is bruising, which is blood that has leaked into the tissue and adds both color and bulk.
Put together, these mean the arm measured in the first week can be the same size as before surgery or slightly larger. MedlinePlus notes that swelling after liposuction may last for weeks and that the final result is not visible until it subsides. Compression garments exist precisely to limit how much fluid accumulates and to help the skin settle onto its new foundation.
A less obvious reason arms can look bigger is comparison. People tend to photograph the arm from the angle that bothered them most, often with the arm raised and the triceps relaxed, which is the position in which any arm looks fullest. Clinics take standardized photos with the arms in a fixed position for this reason. Taking your own at the same angle, in the same light, once a month, gives a fairer picture than daily mirror checks.
There is one scenario in which arms genuinely remain larger than hoped: when loose skin was the real issue. Removing the fat beneath skin that has lost its elasticity reduces volume but can leave the outline unchanged or softer. This is the single most common source of disappointment with arm liposuction, and it is why the skin assessment at consultation matters more than any device.
What are the risks and complications of arm liposuction?
Liposuction is common, but it is surgery, and the arm has features that shape its risk profile. The list below reflects complications recognized in mainstream patient guidance; frequencies vary with the extent of surgery, the patient’s health and the setting, and a surgeon should be able to discuss their own experience with each.
Contour irregularities are the most frequent concern. The Mayo Clinic describes the possibility of bumpy, wavy or withered-looking skin from uneven fat removal, poor skin elasticity or unusual healing. On the arm, where the fat layer is thin, the margin between enough and too much is narrow.
Fluid accumulation, known as a seroma, can form a soft pocket under the skin that sometimes needs to be drained with a needle. Numbness, temporary or occasionally permanent, follows from small sensory nerves being disturbed by the cannula; the back of the arm and the area near the elbow are the usual sites. Infection is uncommon but possible at the entry points. Asymmetry between the two arms is a recognized outcome, since no two arms start identical.
Rarer but more serious events include internal puncture if the cannula travels too deep, fat embolism (fragments of fat entering the bloodstream and lodging in the lungs), blood clots in the legs, and problems with the heart or kidneys from large fluid shifts. The Mayo Clinic also lists lidocaine toxicity from the tumescent anesthetic. These risks rise with the volume of fat removed and the number of areas treated in one session, which is the clinical rationale for staging larger procedures.
The NHS adds a point that is easy to overlook: cosmetic surgery can sometimes produce results that do not match expectations, and a second procedure to refine the outcome is sometimes needed. Discussing in advance how a surgeon handles revisions is part of informed consent, not pessimism.
What people often get wrong about how arm liposuction is done
A handful of beliefs come up in nearly every consultation, and each one shapes expectations in ways that lead to disappointment. Correcting them is more useful than any gallery.
The first myth is that the fat is sucked out like a vacuum from one hole. In practice, the cannula does most of its work mechanically, by tunneling and loosening; suction simply carries away what has been freed. That is why the technique and the pattern of passes matter more than the power of the machine.
The second is that a device name guarantees a smoother result. Ultrasound, laser and power-assisted systems are legitimate tools, but the Cleveland Clinic and Mayo Clinic describe them as variations in technique rather than demonstrated upgrades. There is no guideline-level evidence that any single device produces reliably better arm outcomes.
The third is that liposuction tightens skin. It does not. Some skin retraction can occur, and younger, more elastic skin retracts more, but the operation removes volume only. If the skin was loose before, it will be at best as loose afterward.
The fourth is that removed fat cannot come back. The specific fat cells taken out are gone, but the remaining cells can enlarge with weight gain. The Mayo Clinic is clear that results are lasting as long as weight stays stable, and that weight gain after liposuction changes fat distribution across the body.
The fifth is that the result is visible at the first follow-up. The arm at one week is swollen, bruised and holding fluid. Judging the outcome before three months, and ideally six, is judging a draft.
The last is subtler: that a small procedure means a small decision. Arm liposuction carries real, if uncommon, risks, and it leaves permanent though usually tiny marks. Treating it with the seriousness of any surgery is the attitude most likely to produce a result you live comfortably with.
Questions to ask your care team before arm liposuction
A good consultation feels less like a sales meeting and more like an exam you are giving the surgeon. The questions below are organized around the three stages of the procedure this article has described, plus the aftermath. Write down the answers; comparing notes between consultations is one of the few ways a patient can judge consistency.
On candidacy and planning:
- Based on my skin elasticity, is liposuction alone likely to give the change I am describing, or would you be having a different conversation with me about an arm lift?
- Which specific zones of the arm will you treat, and where will the openings be placed?
- What would make you decide, on the day, to remove less than planned?
On anesthesia and the operation:
- Which type of anesthesia do you recommend for me, and who will be providing it?
- How long do you expect me to be under, including the infusion and waiting time?
- Which technique do you use, and why do you prefer it for arms?
- If other areas are treated in the same session, how does that change the safety plan?
On recovery and outcomes:
- How long should I wear compression, and what is the plan if I develop a fluid pocket?
- When will you take follow-up photographs, and at what point do you consider the result final?
- How do you handle asymmetry or irregularity if it appears, and when would you consider a revision?
- Who do I call out of hours, and which symptoms mean I should go straight to emergency care?
One final question is about the surgeon rather than the surgery: how often do you perform liposuction of the arms specifically, and may I see outcomes at six months or later rather than at six weeks? Later photographs reveal skin behavior; early ones mostly show swelling. The NHS advises checking the qualifications and registration of anyone performing cosmetic surgery, and that advice applies regardless of where in the world the consultation takes place.
When to call your doctor after arm liposuction
Most recovery from arm liposuction is uneventful, and most of what feels alarming in the first week, including bruising that spreads toward the elbow, pinkish fluid leaking from the openings and skin that feels numb or tingly, is expected. The goal of this section is to separate those from the signs that need a phone call or a trip to emergency care. When in doubt, call; surgical teams would far rather hear about a false alarm than miss a real one.
Contact your surgical team the same day if you notice:
- Increasing redness, warmth or swelling around an opening, or pus-like drainage, which can signal infection.
- A fever, or chills, in the days after surgery.
- One arm becoming markedly more swollen, tense or painful than the other, especially if the swelling is rapid, which may indicate bleeding or a large fluid collection.
- Pain that worsens after the third day rather than easing, or that is not controlled by the plan you were given.
- Skin over the treated area turning dusky, dark or blistered.
Seek emergency care immediately, without waiting for a callback, if you experience:
- Shortness of breath, chest pain, a racing heartbeat or coughing up blood, which can be signs of a blood clot traveling to the lungs or of fat embolism.
- Pain, swelling, warmth or redness in a calf, which the CDC lists among warning signs of a deep vein clot.
- Confusion, ringing in the ears, a metallic taste, numbness around the mouth, dizziness or seizure in the hours after surgery; the Mayo Clinic notes that reactions to the local anesthetic in tumescent fluid are rare but serious.
- Fainting, severe weakness or very little urine output, which can reflect fluid shifts affecting the heart or kidneys.
Keep the surgical team’s after-hours number somewhere other than your phone, in case the phone is the thing you cannot find. Every decision about assessment and treatment of these symptoms belongs with the clinicians who know your procedure and your history.
Frequently asked questions
How painful is arm liposuction?
Most people describe deep soreness and tightness rather than sharp pain, usually peaking around the second or third day and easing over the first week. Because the treated area sits over muscles used for reaching and lifting, everyday arm movements are the main trigger. The Mayo Clinic lists pain, swelling and bruising as expected after liposuction; the specific pain-relief plan comes from your prescribing clinician and depends on your health history.
Is liposuction on arms worth it?
That depends almost entirely on skin elasticity and expectations. Arm liposuction reliably reduces fat volume in people with firm skin and a localized pocket of fullness, but it does not tighten loose skin, so someone whose main concern is draping tissue may see little change in outline. No guideline publishes satisfaction figures for arm liposuction specifically, so the honest answer comes from an in-person skin assessment and a frank conversation about what you want changed.
Do my arms still look bigger after arm lipo?
Often yes in the first one to two weeks, because retained tumescent fluid, inflammation and bruising add volume. MedlinePlus notes that swelling after liposuction can last for weeks and that the final result is not visible until it subsides, and the Mayo Clinic says full contour can take several months. If arms remain larger than hoped after that period, loose skin rather than residual fat is the most common explanation.
How much does lipo on arms cost?
This article does not publish price or cost figures, because they vary widely with the extent of treatment, the type of anesthesia, the facility and the region, and any single number would be misleading. Cosmetic liposuction is generally not covered by health insurance. Ask your surgical team for a written, itemized estimate that includes the surgeon, anesthesia, facility, compression garments and follow-up visits, and ask how revisions are handled.
Will arm liposuction scars be visible?
The openings are usually a few millimeters long and are placed in the elbow crease and the back fold of the armpit, where they tend to fade to small pale dots over months. The NHS notes that scarring is possible after any liposuction and may be more noticeable in some skin types. If you have a history of raised or darkened scars, tell your surgeon, as it can influence where the openings are placed and how they are closed.
Is arm liposuction done under local or general anesthesia?
Either, depending on the extent of the procedure and your health. MedlinePlus notes that smaller-volume liposuction is often done under local anesthesia with sedation, while larger or multi-area procedures usually use general anesthesia. Arms treated alone frequently qualify for local with sedation, because the tumescent fluid itself provides numbing. The anesthesia team makes the final decision after reviewing your medical history, other areas being treated and your own preferences.
How long is arm liposuction recovery time before I can work out?
Published guidance from the NHS suggests avoiding strenuous activity for around four to six weeks after liposuction, with light walking encouraged from the first day to reduce clot risk. Upper-body resistance training, swimming and racket sports fall into the strenuous category for the arms. These are typical ranges rather than rules; your surgeon will clear specific activities based on how your swelling and skin are settling at follow-up.
How long do you wear a compression sleeve after arm liposuction?
The NHS describes wearing an elasticated support garment for several weeks after liposuction, and many surgeons ask for near-continuous wear in the early period followed by daytime-only wear later. Compression limits fluid accumulation, reduces swelling and helps the skin settle onto the new contour. The exact schedule varies with how much was treated and how your arm is healing, so follow the instructions from your own surgical team rather than a generic timeline.
What is the difference between arm lipo vs arm lift?
Arm liposuction removes fat through small openings and relies on the skin shrinking to fit; an arm lift, or brachioplasty, removes loose skin through a longer incision running along the inner arm. Liposuction suits people with good skin elasticity and localized fullness, while an arm lift is usually considered when skin hangs, often after significant weight loss. Some patients are offered a combination. The deciding factor is skin quality, assessed in person.
Does fat come back after arm liposuction?
The specific fat cells removed do not regrow, but the remaining fat cells in the arm and elsewhere can enlarge with weight gain. The Mayo Clinic notes that liposuction results are lasting as long as weight remains stable, and that gaining weight afterward changes how fat is distributed across the body. Maintaining a steady weight through ordinary diet and activity is the main factor in keeping the contour achieved.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
What Pectoral Augmentation Results Look Like Over Time: Realistic Expectations for Men
Pectoral augmentation results change for months after surgery. In the first week the chest usually looks swollen, high and tight; over 6 to 12…

What Are the Risks of Aesthetic Genital Surgery? Infection, Wound Healing and Sensation
Aesthetic genital surgery carries the general risks of any operation, including bleeding, infection and reactions to anesthesia, plus risks specific to this area: wound…

Laser Liposuction Recovery: Compression Garment Days, Walking Early and Returning to Work
Laser liposuction recovery typically involves wearing a compression garment for several weeks, walking gently from the first day to lower clot risk, and returning…

How BBL and Lipofilling Is Performed: Liposuction, Fat Purification and Careful Transfer
A BBL lipofilling procedure reshapes the buttocks with a person's own fat in three stages. Liposuction removes fat from areas such as the abdomen,…

Mommy Makeover vs Staged Surgeries: Is One Combined Operation the Safer Choice for You?
Neither path is automatically safer. A mommy makeover combines abdominal and breast procedures under one anesthetic, which means a single recovery but a longer…
When Do Arm Liposuction Results Show? Swelling, Sleeve Time and the Final Arm Contour
Arm liposuction results appear in stages rather than all at once. Bruising and the heaviest swelling usually ease over the first few weeks, a…