

How Corneal Cross-Linking Is Performed for Keratoconus: Drops, Light and Recovery Time

Key Takeaways
- Cross-linking stiffens the cornea by using riboflavin and ultraviolet-A light to create new collagen bonds, mimicking in about an hour a process that normally takes decades of aging.
- The standard, regulator-approved technique removes the corneal surface layer first, which is why the first two to four days involve real discomfort until that layer regrows.
- The goal is to stop the cone from steepening, not to sharpen vision; most people still need glasses or rigid or scleral lenses afterward, usually refitted a few months later.
- Vision is typically worse than baseline for the first several weeks because of swelling and a temporary haze that peaks around the first month before fading.
- A Cochrane review indexed by the NIH rated the randomized-trial evidence for cross-linking as limited and low quality, even though longer clinical series and regulatory approval support the epithelium-off protocol.
- Because a minority of corneas continue to progress after treatment, repeat corneal mapping at several months and then yearly is the only way to confirm the procedure did its job.
Corneal cross-linking for keratoconus is an outpatient eye procedure that uses riboflavin (vitamin B2) drops and ultraviolet-A light to stiffen a weakened cornea and slow its bulging. In the standard version, the surface layer is removed first, riboflavin soaks in, and the light is applied; the visit typically takes about an hour. Surface healing takes roughly a week, vision settles over weeks to months, and the goal is stability rather than sharper sight.
The chart on the wall never seemed to change, yet somehow the letters kept getting harder to read. A new glasses prescription each year, then rigid contact lenses, then the quiet comment from the eye doctor: your cornea is thinning, and the shape is drifting. That is often the moment a person first hears the words corneal cross linking procedure, usually with a follow-up question already forming: what exactly are you going to do to my eye?
The answer is less dramatic than it sounds. No cutting, no implants, no stitches. The whole idea rests on a vitamin drop and a specific wavelength of light doing what years of sunshine quietly do to everyone’s cornea anyway, only faster and on purpose.
This explainer walks through the procedure step by step: what the drops are for, what the light does, what the first evening feels like, how long vision takes to settle, and what the evidence honestly can and cannot promise. Every treatment decision stays with the team looking at your own scans.
Why does a keratoconus cornea need strengthening in the first place?
The cornea is the clear front window of the eye, and in a healthy adult it measures roughly half a millimeter thick, about the depth of five sheets of paper stacked together. It holds its dome shape because of collagen, the same structural protein found in tendons and skin. Collagen fibers in the cornea run in tidy, layered sheets bound to one another by chemical bridges called cross-links. Those bridges are what give the tissue its stiffness.
Keratoconus is a condition in which the cornea gradually thins and weakens, so that normal eye pressure pushes it outward into a cone shape. Mayo Clinic describes it as typically beginning in the teenage years or early twenties and progressing slowly for ten years or more before it tends to settle on its own. An irregular cone bends light unevenly, which is why glasses stop working well and why people describe ghosting, halos and multiple images rather than simple blur.
Two things about that natural history matter for the procedure. First, the cornea usually stiffens with age anyway, because cross-links accumulate over a lifetime and glycation from ordinary sugar chemistry adds more. That is one reason keratoconus so often stabilizes in middle age. Second, the damage done while the cornea is still soft, in the teens and twenties, is largely permanent. A cone that has already formed does not flatten back to a smooth dome.
Cross-linking borrows the first fact to protect against the second. It creates new collagen bridges quickly, in about an hour, rather than over decades, with the aim of freezing the shape where it is. The cornea that comes out of the room is stiffer, not thicker and not smoother. Understanding that single distinction prevents most of the disappointment people report later.
What is the corneal cross linking procedure, in plain language?
Strip away the equipment and the corneal cross linking procedure has three ingredients: a vitamin, a light and oxygen. Riboflavin is vitamin B2, a yellow compound your body already uses in energy metabolism. When riboflavin absorbs ultraviolet-A light, the same long-wavelength UV that passes through window glass, it becomes energized and hands that energy to nearby oxygen molecules. The result is a brief burst of reactive oxygen species inside the corneal tissue.
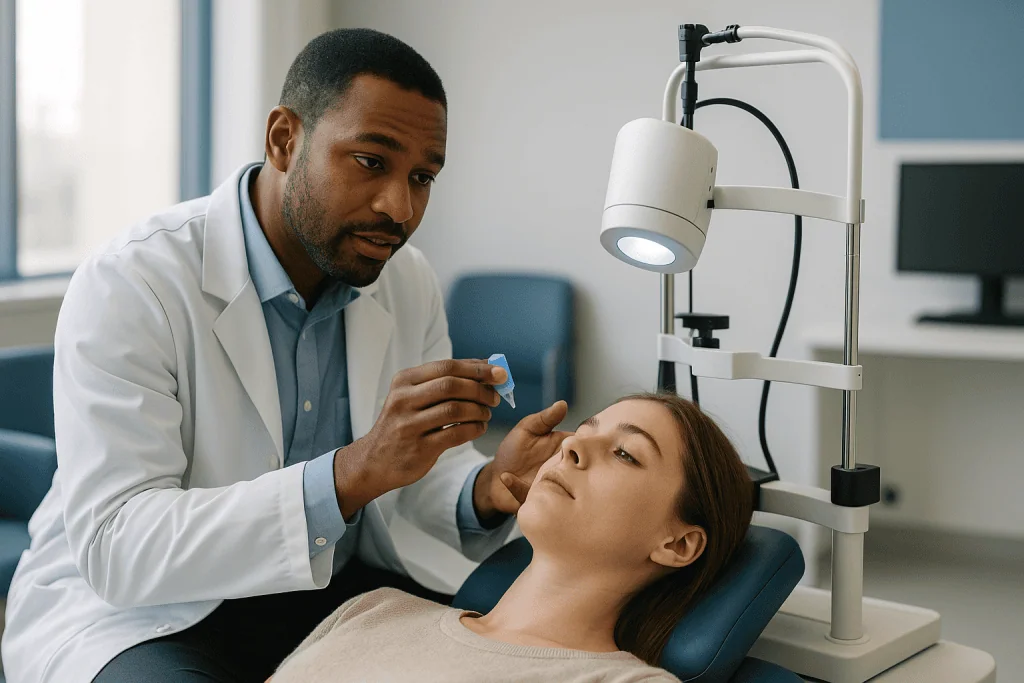
Those reactive molecules do something useful. They encourage new chemical bonds to form between collagen fibers and between the proteins that pack around them. Cleveland Clinic summarizes the effect plainly: the treatment strengthens and stiffens the cornea so the cone is less likely to keep steepening. The effect is concentrated in the front portion of the cornea, roughly the outer two-thirds, which is where most of the stiffness lives anyway.
The riboflavin does a second job that people rarely hear about. Because it absorbs UV so strongly, it acts as a shield for the deeper layers of the eye. The lens and retina sit behind the cornea and would not enjoy a direct dose of ultraviolet light. A cornea fully saturated with yellow riboflavin absorbs most of the energy in its front layers, and this is exactly why surgeons insist on a minimum corneal thickness before treating, and why the soaking phase is not rushed.
The epithelium, the thin skin-like surface layer of the cornea, is a barrier to riboflavin. It is designed to keep things out. In the standard technique the surgeon gently removes it over the central cornea so the drops can penetrate; this is the epithelium-off, or epi-off, approach. Techniques that try to push riboflavin through an intact surface exist and are covered later, but the removal step explains almost everything about what the first few days feel like.
Who is usually offered cross-linking, and who is asked to wait?
Cross-linking is not offered to everyone who has keratoconus. Its purpose is to stop progression, so the strongest candidates are people whose corneas are demonstrably still changing. Ophthalmologists look for steepening on repeated corneal maps, thinning on successive measurements, or a shifting glasses prescription over months. Cleveland Clinic and Johns Hopkins both frame the treatment as being for progressive keratoconus and for a related weakening called corneal ectasia that can occasionally follow laser vision correction.
Age enters the conversation in two directions. Younger patients, especially teenagers, tend to progress faster, and many specialists treat them sooner and monitor less patiently, because the cornea has more soft years ahead of it. Older adults whose maps have not moved in years may be told the condition has done what it is going to do, and that stiffening an already stable cornea offers little.
Several groups are commonly asked to wait or to consider other options, and the reasons are practical rather than arbitrary:
- Corneas thinner than the threshold the surgeon’s protocol requires, because the riboflavin shield for the inner eye depends on adequate depth.
- Active eye infection, significant dry eye or surface disease, which would complicate healing of the removed epithelium.
- Central corneal scarring dense enough that stabilizing the shape would not improve function.
- Pregnancy or breastfeeding, where many teams defer because corneal shape can shift with hormonal changes and safety data are limited.
- A history of herpes eye infection, which ultraviolet exposure can reactivate.
None of these is a permanent no. Thin-cornea protocols using swelling drops exist, surface disease can be treated first, and a stable map may simply mean more monitoring rather than intervention. The judgment call sits with the treating team, who are weighing your particular scan against your age and your own rate of change.
What happens before the procedure: mapping, measurements and consent
The appointments before cross-linking are often longer than the treatment itself, and that is deliberate. The surgeon needs a baseline precise enough that any future change can be trusted as real rather than as measurement noise.

Corneal topography and tomography are the workhorses. Topography maps the curvature of the front surface, producing the familiar color heat map where warm colors mark steep areas. Tomography images the cornea in cross-section and adds thickness at every point, plus the shape of the back surface, which often shows keratoconus before the front does. A pachymetry reading, simply the thickness at the thinnest point, decides whether the standard protocol is safe.
Expect a refraction and a corrected-vision check, a slit-lamp examination of the surface, and a look at the retina through dilated pupils. If you wear rigid or scleral contact lenses, you will probably be asked to leave them out for a period before the scans, since lenses temporarily mold the cornea and can hide its true shape. Your team will tell you how long; it varies with lens type.
Consent conversations should cover the goal in honest terms. Mayo Clinic describes cross-linking as a treatment that may slow or stop progression and might help avoid a future corneal transplant; it is not described as a way to restore clear vision. You should hear about the healing period, the temporary drop in vision, the possibility of infection or haze, and the small chance that the cornea keeps progressing despite treatment.
Practical instructions usually include arranging a driver, since the treated eye will be light-sensitive and blurred, planning a few days off work or school, stocking sunglasses, and clarifying which of your regular medicines to continue. Eye drops used after the procedure are typically prescribed in advance so they are waiting at home. Only one eye is normally treated per session, with the second scheduled once the first has settled.
Step by step: the corneal cross linking procedure on the day
Cross-linking is done awake, sitting or lying under a microscope, in a clinic or day-surgery room. Cleveland Clinic puts the total time at about 60 to 90 minutes, most of it spent waiting for drops to soak in and a light to shine. Nothing about it is fast, and that slowness is the point.
The eye is numbed with anesthetic drops, and a small speculum, a soft clip that holds the lids open, is placed so you cannot blink the treatment away. You will feel pressure from the clip and see bright light, but the cornea itself should not hurt while the anesthetic is working.
For the standard epithelium-off technique, the surgeon then removes the surface layer over the central cornea, an area roughly the size of a pencil eraser. This can be done with a blunt instrument, an alcohol solution that loosens the cells, or a brush. It takes a minute or two. People describe a sensation of something being wiped across the eye rather than pain.
Riboflavin drops follow, applied repeatedly over about half an hour according to Cleveland Clinic’s description of the procedure. The staff watch the cornea turn yellow and check with the slit lamp that the dye has reached the inner chamber of the eye, a sign of full saturation. Corneal thickness is often measured again at this stage; if the tissue has thinned during soaking, some protocols pause to swell it before proceeding.
Then the light. A device positioned a few centimeters from the eye delivers ultraviolet-A at a controlled intensity while you look at a fixation target. Standard protocols use a longer, lower-intensity exposure of about 30 minutes, again per Cleveland Clinic; accelerated protocols deliver the same total energy faster. The surgeon adds more riboflavin during the light phase to keep the cornea saturated. When the light switches off, the eye is rinsed, a drop of antibiotic is placed, and a bandage contact lens, a soft lens worn purely for comfort and protection, is set over the raw surface. A clear shield goes on, and you go home.
Epi-off vs epi-on cross linking: what is the real difference?
The single biggest fork in the road is whether the epithelium comes off. The standard approach removes it. The epithelium-on, or epi-on, approach leaves it in place and tries to coax riboflavin through with chemical additives, longer soaking, or mild electrical current. The appeal of epi-on is obvious: less pain, faster recovery and lower infection risk, because the surface barrier is never breached. The uncertainty is whether enough riboflavin and oxygen reach the deeper collagen to produce the same stiffening.
Cleveland Clinic notes that the epithelium-off protocol is the one approved by the US Food and Drug Administration for progressive keratoconus, while epi-on techniques remain under study. That does not make epi-on ineffective; it means the evidence base is thinner and the protocols are still being refined. A treating team offering epi-on should be able to say plainly whether it is within a clinical trial and what data support their particular method.
| Feature | Epithelium-off (standard) | Epithelium-on (investigational in some settings) |
|---|---|---|
| Surface layer | Removed over central cornea | Left intact |
| Riboflavin penetration | Direct, well documented | Reduced; relies on additives or assisted delivery |
| Discomfort in first days | Moderate to significant until surface heals | Usually mild |
| Bandage contact lens | Typically worn for several days | Often not needed |
| Return of usable vision | Days to weeks | Often quicker |
| Infection and haze risk | Present, because surface is open | Lower, because barrier is preserved |
| Strength of stabilization evidence | Larger and longer-followed body of evidence | Smaller, evolving evidence base |
Accelerated protocols are a separate variable, not the same as epi-on. They shorten the light phase by raising intensity, and can be used with either surface approach. Whether faster delivery stiffens the cornea as thoroughly is still an active research question, because oxygen in the tissue is consumed quickly at high intensity. Ask which combination you are being offered and why.
Is corneal cross linking painful? What the first evening feels like
The honest answer is: not during, often yes afterward, and the reason is the missing epithelium rather than the light. The cornea carries one of the densest concentrations of nerve endings in the body, which is why a single eyelash on the surface feels enormous. Removing the surface cells exposes those nerves the same way a scraped knee exposes skin nerves, and the anesthetic drops used during treatment wear off within an hour or two of leaving.
Most people describe the first night as the hardest. Common descriptions include a gritty, sandy feeling, watering, aching, and marked sensitivity to light. Cleveland Clinic notes pain and light sensitivity are expected for a few days and that most people are far more comfortable once the surface has closed. The bandage contact lens takes the edge off by covering the raw area so the lid does not drag across it with every blink.
Discomfort tends to peak within the first day or two and then fall away as new epithelial cells migrate inward from the edges. This healing is quick by the body’s standards; a scrape in the middle of the cornea typically closes in a matter of days, which Cleveland Clinic describes as several days to about a week. Once it seals, the pain usually drops sharply, sometimes overnight.
Teams manage the interval with a mix of measures. Cold compresses over closed lids, dim rooms, and dark glasses help. Lubricating drops keep the surface wet. Your surgeon may prescribe or suggest pain relief, and the choice, amount and duration are theirs to decide based on your other medicines and health. Prescription drops after the procedure typically include an antibiotic to protect the open surface and a steroid to calm inflammation; their schedule and how to taper them are set by the prescribing clinician and should be followed exactly.
One caution belongs here rather than in the red-flag section, because it is so tempting: do not rub the eye, and do not use leftover anesthetic drops at home. Numbing drops used repeatedly slow healing and can damage the surface. Pain that is escalating rather than easing after the second day is a reason to call, covered below.
The first week: what recovery looks like day by day
The first week is about the surface. Everything else, the actual strengthening and the settling of vision, unfolds later and more quietly.
On the day itself and the next, expect blur, tearing, light sensitivity and discomfort. Vision through the bandage lens is hazy, and the treated eye may be difficult to open in bright rooms. Most people rest in a dim space, sleep with the plastic shield taped on, and keep to the drop schedule their team set. Screens are hard to tolerate, not dangerous, and the untreated eye carries the load.
Around the second to fourth day the epithelium is usually well on its way to closing, and pain generally eases in step. A first follow-up visit commonly falls in this window so the surgeon can check healing under the slit lamp, look for any sign of infection, and remove the bandage lens once the surface is intact. Cleveland Clinic and Johns Hopkins both describe the first check as occurring within the first several days.
By the end of the week the eye typically feels closer to normal, though still easily irritated and dry. Vision remains blurred, often worse than before treatment, and this is expected. The freshly healed epithelium is irregular, like new plaster before it is sanded, and the cornea itself is mildly swollen from the UV reaction. Steroid drops, if prescribed, are usually continuing at this point under the clinician’s direction.
Practical rules for the week are consistent across mainstream guidance:
- No water in the eye: no swimming, no splashing the face directly, careful in the shower.
- No eye makeup, no rubbing, no contact lens wear in the treated eye until cleared.
- Dark glasses outdoors, since UV sensitivity is heightened and the pupil may still be dilated.
- Avoid dusty or smoky environments where possible while the surface is fresh.
Return to desk work or school is often possible within a few days to a week, depending on comfort and how much the untreated eye compensates. Heavy physical work, contact sports and dusty trades usually wait longer. Your team sets those dates based on what they see at follow-up, not on a calendar.
Corneal cross linking recovery time: weeks two to twelve and beyond
Recovery from cross-linking has a curious shape. Comfort returns within about a week, but vision often gets worse before it gets better, and the strengthening itself is measured in months. Knowing the curve in advance spares a lot of unnecessary worry.
Through the second and third weeks, vision commonly remains blurrier than baseline. Cleveland Clinic notes that eyesight is often worse for the first weeks and that improvement, where it comes, arrives gradually. Two things are happening. The cornea is still mildly swollen, and a faint haze, a cloudiness in the front stroma from the cross-linking reaction itself, is common and usually peaks around the first month before fading over several months. Most of this haze is expected and clears; a small proportion of people are left with persistent haze, which is discussed under disadvantages.
Between roughly one and three months, many people notice vision drifting back toward where it started, sometimes slightly better as the cone flattens a little and the surface smooths. Mayo Clinic describes the goal of treatment as stabilization rather than improvement, and any flattening should be considered a bonus rather than the aim. Steroid drops are typically tapered and stopped during this period on the prescribing clinician’s schedule.
Glasses prescriptions are usually not updated until the cornea has settled, which many teams place at around three months or later. Rigid or scleral contact lens wearers are typically refitted after that point, because the corneal shape has changed and an old lens may no longer sit correctly. Wearing an old rigid lens too early can also irritate the healing surface.
Follow-up maps at several months and then at yearly intervals are how the team judges whether progression has actually stopped. A single stable scan means little; the pattern over one or two years is what counts. Some corneas keep steepening despite treatment, particularly in very young patients, and a second treatment is occasionally discussed. Others show flattening that continues slowly for years. Both trajectories are recognized in the literature, and only time and repeated measurement reveal which one applies to a given eye.
How successful is corneal cross-linking? What the evidence actually shows
This is the question people most want a number for, and the honest answer requires a distinction between what large clinical experience suggests and what high-quality trials have proven.
Mainstream patient guidance is consistent in its framing. Cleveland Clinic describes cross-linking as effective at stopping or slowing progression in most people who have it, while stressing that it does not reverse existing damage or eliminate the need for glasses or contacts. Mayo Clinic lists it as the treatment that may slow or halt progression and may reduce the likelihood of a future corneal transplant. Johns Hopkins uses similar language. None of these sources presents it as a way to restore vision, and none quotes a guaranteed figure.
Formal systematic review has been more cautious. A Cochrane review published in the NIH-indexed literature examined the randomized trials available at the time and concluded that the evidence for cross-linking’s effect on progression was limited and of low quality, largely because the trials were small, short and at risk of bias. That review did not say the treatment fails; it said the strongest form of proof was thin. Since then, longer observational series have accumulated and regulators have approved the epithelium-off protocol on the basis of trial data, but the gap between clinical confidence and randomized-trial certainty has not fully closed.
What this means for a person deciding today is roughly this. The biological mechanism is well understood and measurable in laboratory tissue. Decades of clinical follow-up across many centers point in the same direction: most treated corneas stop steepening, and a minority show modest flattening. A smaller group continue to progress and may be offered a second treatment. Whether any individual eye will land in the majority cannot be predicted with confidence from the outset.
Success, then, is best defined the way surgeons define it: a corneal map that stops changing. If you leave the consultation expecting sharper unaided vision, the evidence does not support that expectation. If you leave expecting a reasonable chance of freezing the shape where it is, you have understood the treatment correctly.
What are the disadvantages of cross-linking? Side effects and risks
Cross-linking is generally regarded as a low-risk procedure relative to corneal transplant, but low risk is not no risk, and the disadvantages deserve the same clear language as the benefits.
The most common downsides are temporary and follow from removing the epithelium. Pain, tearing and light sensitivity for several days are expected. Blurred vision for weeks is expected. A period of dry, easily irritated eye is common as surface nerves regrow, and can last months. These are not complications so much as the price of the technique.
Genuine complications are less frequent but real. Cleveland Clinic and Johns Hopkins list the recognized ones:
- Infection of the open surface, the most serious short-term risk, which is why antibiotic drops and strict hygiene matter in the first week.
- Persistent corneal haze that does not fully clear, occasionally enough to reduce vision.
- Delayed healing of the epithelium, sometimes with a sterile ulcer or scarring.
- Damage to the endothelium, the inner pump layer of the cornea, if the tissue was too thin for the energy delivered; this is the reason for thickness thresholds.
- Reactivation of herpes eye infection in people with a history of it.
- Continued progression despite treatment, requiring monitoring and possibly retreatment.
- A shift in the glasses or contact lens prescription, which can be unpredictable in direction.
Steroid drops used after the procedure carry their own class-level risks with prolonged use, including raised eye pressure and, over long periods, cataract; this is one reason the taper schedule set by the prescribing clinician should not be extended on your own.
There is also a disadvantage that rarely appears on lists: expectation mismatch. People who go in hoping to see better and come out seeing the same, after weeks of discomfort, can feel the procedure failed when by clinical measure it worked. Knowing the goal beforehand is a real protective factor.
Finally, the treatment is only as durable as follow-up allows. A cornea that is not remeasured cannot be known to be stable. Skipping the yearly maps removes the one tool that would reveal ongoing progression early, when a second treatment or other options still make sense.
What are the alternatives, and what continues alongside cross-linking?
Cross-linking rarely stands alone. It addresses the mechanics of the cornea; it does not address how well you see through it. Everything else in the keratoconus toolkit is about the second problem, and most people continue using some of it afterward.
Glasses work in early keratoconus while the cornea is still fairly regular. As the cone develops, spectacles struggle because they cannot correct irregular astigmatism, the uneven bending of light from an asymmetric surface. Soft contact lenses face the same limit.
Rigid gas-permeable lenses remain a mainstay. A hard lens creates a new smooth front surface, with the tear film filling the gap between lens and cornea, and this optical trick neutralizes most of the irregularity. Scleral lenses, larger rigid lenses that vault over the cornea and rest on the white of the eye, do the same job more comfortably for many people and are increasingly used, particularly for advanced cones or dry eyes. Mayo Clinic and Cleveland Clinic list these as standard options. After cross-linking, a refit is usually needed because the shape has changed.
Intracorneal ring segments are small arc-shaped plastic implants placed in the corneal periphery to flatten the cone mechanically. They are sometimes used with cross-linking, before or after, to improve the fit of lenses; they do not stop progression on their own.
Corneal transplant, replacing part or all of the central cornea with donor tissue, is the option when scarring or extreme thinning makes contact lenses unworkable. It is a bigger operation with a long recovery and its own risks, and one of the main hopes behind cross-linking is to reduce the number of people who eventually need it. Mayo Clinic describes transplant as reserved for advanced disease.
Doing nothing is also a legitimate choice for a stable cornea. If maps have not moved across two or more years, many specialists advise continued monitoring rather than intervention. The right sequence depends on age, thickness, progression and how you see through your current correction, and that is a discussion for your treating team, not a standardized pathway.
What people often get wrong about cross-linking
Some misunderstandings show up in almost every consultation. Correcting them early changes how the whole experience feels.
It will fix my vision. Cross-linking is aimed at shape stability, not clarity. Some people see a little better as the cone flattens slightly; many see about the same; a few see slightly differently in ways that require a new prescription. Glasses or contacts almost always remain part of life afterward.
It is a laser treatment like the ones for short sight. No tissue is removed to reshape the cornea, and no laser is used in the standard procedure. Ultraviolet-A light energizes a vitamin; it does not carve. Confusing the two leads people to expect instant sharp vision the next morning, which is precisely what does not happen.
Once it is done, keratoconus is finished. Progression usually stops, but not always, and the only way to know is repeat mapping over years. The procedure changes the odds; it does not close the file.
Both eyes are done at once. Most surgeons treat one eye per session so you can function with the other during the blurred, uncomfortable first week, and so any healing problem affects only one eye. The second eye follows when the first has settled.
Rubbing my eyes does not matter anymore. Eye rubbing is one of the few modifiable factors consistently linked with keratoconus progression in mainstream guidance, including Mayo Clinic’s. A stiffer cornea is still a cornea, and habitual rubbing, often driven by allergy, remains worth treating and unlearning.
Blur at three weeks means it failed. The temporary haze and swelling peak around the first month. Vision that is worse than baseline at this point is the expected course, not a warning sign, unless it is accompanied by pain, redness or discharge.
Epi-on is simply the newer, better version. It is gentler in the short term, but its evidence base for long-term stabilization is smaller. Newer is not automatically stronger, and a candid team will say so.
Questions to ask your care team before the corneal cross linking procedure
A good consultation is a two-way exchange, and the questions below tend to draw out the information that matters most. Bring them written down; a dilated eye and a full waiting room are not conducive to memory.
- What evidence do you have that my keratoconus is actually progressing, and how much has it changed between scans?
- How thick is my cornea at its thinnest point, and does that thickness allow the standard protocol or require a modified one?
- Which technique are you recommending: epithelium-off or epithelium-on, standard or accelerated light exposure? What is the evidence for that specific combination, and is any part of it within a research study?
- What is the realistic goal for my eye: stopping progression, a chance of some flattening, or both? What would count as success at one year?
- What is your plan for pain in the first days, and who do I call at night or over a weekend if something feels wrong?
- Which drops will I use afterward, for roughly how long, and what should I do if I miss one or run out?
- When will you check the eye after treatment, and when will you remove the bandage lens?
- When can I drive, return to work or school, exercise, swim and wear my contact lenses again?
- How long should I wait before updating my glasses or being refitted for lenses?
- If the cornea keeps progressing, what would the next step be, and how would we know?
- Is there anything about my history, such as previous herpes eye infection, dry eye, allergy or pregnancy plans, that changes your advice or timing?
- When would you plan to treat the other eye, if it needs it?
Listen for answers that acknowledge uncertainty. A team that says most people stabilize, some continue to progress, and we will know from your maps over the next two years is describing the evidence accurately. Firm promises about vision improvement or guaranteed halting are a reason to ask more, not fewer, questions.
When to call your doctor after cross-linking
The first week after cross-linking is the window in which problems are most likely and most treatable, and the treated eye is an open wound under a contact lens. Expected symptoms, such as grittiness, watering, light sensitivity and blur, should be easing by the third or fourth day. Anything moving in the other direction deserves a call the same day, not at the next scheduled visit.
Seek care urgently, using the after-hours number your team gave you, if you notice any of the following:
- Pain that is getting worse after the second day, or severe pain not controlled by the measures your team advised.
- Increasing redness, especially a deepening red ring around the cornea.
- Thick, yellow or green discharge, or crusting that reappears after cleaning.
- A sudden further drop in vision, a new dense white spot on the cornea, or a sense that the eye is filling with fog rather than clearing.
- The bandage contact lens falls out, tears or moves onto the white of the eye; do not attempt to reinsert it yourself.
- Light sensitivity so intense that you cannot open the eye at all, particularly if it is worsening rather than improving.
- Fever, or a feeling of general illness alongside eye symptoms.
- A history of herpes eye infection and any new blistering around the eyelid or a return of familiar symptoms.
Infection of a healing cornea can progress within hours, and early treatment makes a large difference to the final outcome. If in doubt, call; a clinic would rather see a healthy eye than miss an infected one.
Beyond the first weeks, contact your team if vision that had settled begins to fluctuate again, if you develop persistent haze that interferes with daily tasks, if you experience eye pain or headache while still using steroid drops, which can signal raised eye pressure, or if you find yourself unable to tolerate lenses that previously fit. Missed follow-up maps are the commonest way progression slips by unnoticed; if you have fallen out of the monitoring schedule for any reason, ask to be rebooked.
Frequently asked questions
How painful is corneal crosslinking?
The procedure itself is not painful because the eye is numbed with anesthetic drops, but the first one to three days afterward are often genuinely uncomfortable. Removing the surface layer exposes dense corneal nerves, producing a gritty, aching, light-sensitive eye until new cells cover the area, typically within about a week according to Cleveland Clinic. A bandage contact lens, dark glasses and any pain relief your team advises help. Pain that worsens after day two should be reported.
How long is recovery from corneal cross-linking?
Comfort usually returns within about a week as the surface heals, but vision often stays blurrier than before for several weeks and settles over roughly three months, per Cleveland Clinic and Johns Hopkins descriptions of the recovery course. Glasses and contact lens refits generally wait until then. The strengthening effect and any slight flattening are assessed over months to years through repeat corneal mapping, so full recovery is better measured in scans than in days.
What are the disadvantages of cross-linking?
The main drawbacks are a painful, light-sensitive first few days, weeks of blurred vision, and dry, irritable eyes that can persist for months. Less common complications include infection of the healing surface, persistent haze, delayed healing, damage to the inner corneal layer if the cornea was too thin, and reactivation of herpes eye infection. Some corneas keep progressing despite treatment, and the procedure does not improve vision on its own.
How successful is corneal cross-linking?
Mainstream guidance from Cleveland Clinic and Mayo Clinic describes cross-linking as stopping or slowing progression in most people, while an NIH-indexed Cochrane review judged the randomized-trial evidence to be limited and low quality. Success is defined as a cornea that stops steepening on repeat maps, not as clearer vision. A minority continue to progress and may be offered retreatment, and no individual outcome can be predicted in advance.
What is the difference between epi-off and epi-on cross linking?
Epi-off removes the corneal surface layer so riboflavin penetrates directly; it is the protocol with the largest evidence base and regulatory approval in the US, but it means more pain and a longer healing period. Epi-on leaves the surface intact and uses additives or assisted delivery to push riboflavin through, offering a gentler recovery with lower infection risk, but its long-term stabilization data are smaller and still evolving.
Does corneal cross-linking improve vision?
Not as its purpose, and usually not by much. The treatment is designed to stiffen the cornea and halt progression. Some people experience mild flattening of the cone over months, which can slightly improve corrected vision or lens fit, while others see about the same or need a changed prescription. Mayo Clinic frames the aim as stabilization and possible avoidance of transplant rather than improved sight. Glasses or lenses remain necessary for most.
How long does the corneal cross linking procedure take?
Cleveland Clinic puts the whole visit at about 60 to 90 minutes for the standard technique. Most of that time is spent applying riboflavin drops for roughly half an hour so the cornea is fully saturated, then delivering ultraviolet-A light for a similar period. Accelerated protocols shorten the light phase. Preparation, numbing and placing a bandage lens add a few minutes at each end. Only one eye is normally treated per session.
Can I drive or work after corneal cross linking?
Not on the day, and usually not for several days. The treated eye is blurred, watering and highly light-sensitive, so you need someone to drive you home and should avoid driving until your surgeon confirms your vision meets legal standards. Many people return to desk work or school within a few days to a week as comfort allows, relying on the untreated eye. Physical, dusty or contact-heavy work waits longer, on your team’s advice.
What are common cross linking side effects in the first month?
Expected effects include blurred vision worse than baseline, light sensitivity, dryness, watering and a temporary haze in the front of the cornea that typically peaks around the first month before clearing over several months. These are part of the normal course rather than complications. Redness, discharge, escalating pain or a sudden further loss of vision are not expected and should prompt a same-day call to your care team.
Do I need cross-linking if my keratoconus is stable?
Often not. The treatment exists to stop progression, so a cornea whose maps have not changed across two or more years gains little from being stiffened, and many specialists advise continued monitoring instead. Keratoconus commonly stabilizes naturally in the thirties and forties as the cornea stiffens with age. The decision depends on your age, corneal thickness and measured rate of change, and rests with the specialist reviewing your scans.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Glaucoma Surgery Recovery: Frequent Pressure Checks, Drop Changes and Lifting Limits
Glaucoma surgery recovery usually spans several weeks, with the first month watched most closely. Expect frequent eye-pressure checks, a changed drop routine that often…

Super LASIK Recovery: Burning Hours, Blurry Evening and the Follow-Up Appointments Ahead
Super LASIK recovery follows the same pattern as standard LASIK: eyes typically burn, water and feel gritty for several hours, vision is often blurry…
LASEK PRK Recovery: The Bandage Contact Lens, the Hazy Days and When Sight Sharpens
After LASEK or PRK, a soft bandage contact lens protects the cornea while its surface layer regrows, and it is usually removed by the…

Why a Glasses Prescription Is Not a Contact Lens Prescription: What the Fitting Measures
A glasses prescription and a contact lens prescription are not interchangeable. Glasses sit about a centimeter from the eye, so the lens power is…

PRK Recovery Timeline: Hazy Days, Bandage Lens Removal and the Slow Climb to Clear Vision
A typical PRK recovery timeline runs in stages: the outer corneal layer regrows over roughly three to five days, during which the bandage contact…

Dry vs Wet Macular Degeneration: How Each Form Progresses and Why Treatment Plans Differ
Dry macular degeneration is the slow form: waste deposits called drusen and thinning of the retina's light-sensing cells gradually blur central vision over years,…