

How CT or MR Angiography Defines the Affected Aortic Segment Before Treatment Is Planned
Key Takeaways
- CT angiography images the entire aorta in seconds during a single contrast injection, while MR angiography provides similar anatomy without radiation but typically takes 15 to 90 minutes per the NHS.
- Surgeons plan by segment and zone: the 2022 ACC/AHA guideline divides the aorta into zones 0 through 11, each defined by the branch arteries it contains.
- A dissection touching the ascending aorta is Stanford type A and usually means emergency surgery; one confined beyond the left subclavian artery is type B and is often managed medically at first.
- The 2022 guideline places the usual elective repair threshold for the ascending and abdominal aorta at 5.5 cm, lower for women's abdominal aortas, for people with connective tissue disorders, and for aneurysms growing more than 0.5 cm a year.
- The NHS surveillance schedule rescans abdominal aneurysms of 3.0 to 4.4 cm yearly and those of 4.5 to 5.4 cm every three months, with referral at 5.5 cm.
- The guideline defines dissection as acute within 14 days of symptom onset, subacute from days 15 to 90 and chronic after 90 days, and the imaging appearance changes across those phases.
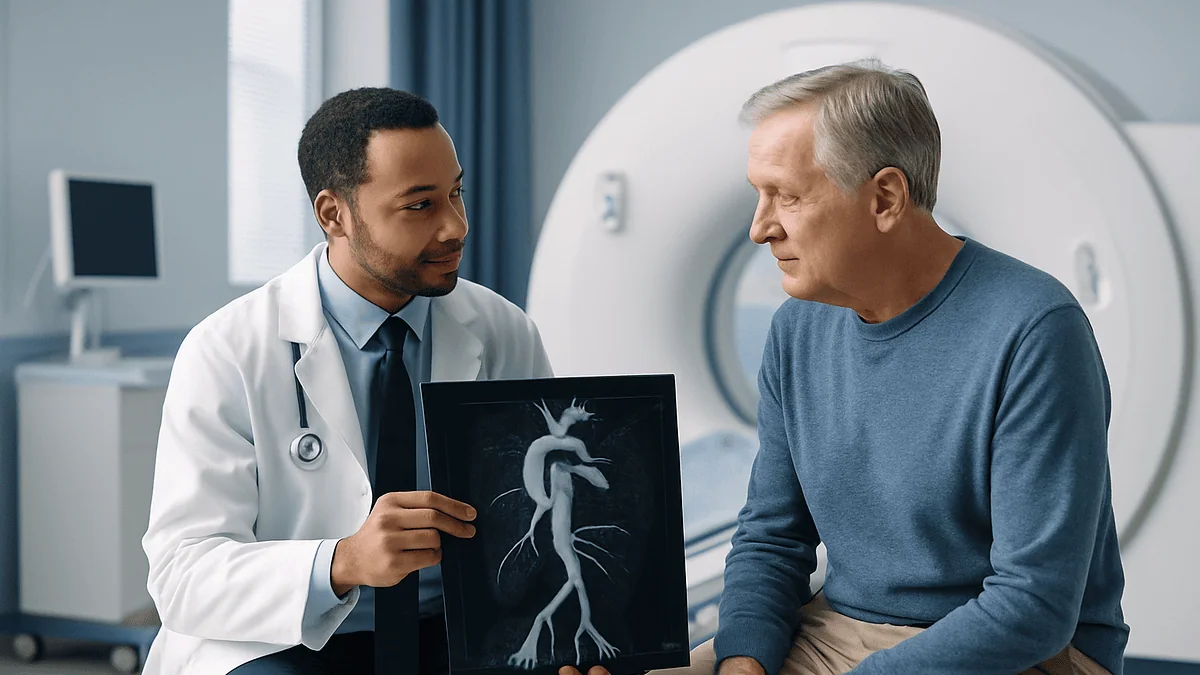
CT angiography for aortic disease uses a rapid CT scan timed to an injection of iodinated contrast to show the whole aorta in three dimensions, so the care team can measure exactly which segment is widened, torn or narrowed, how far the problem extends and which branch arteries are involved. MR angiography gives similar anatomical detail without radiation. Those measurements, not the diagnosis alone, shape the treatment plan.
The letter arrives with a phrase that sounds oddly modest: “aortic dilatation, further imaging advised.” A chest X-ray taken for a cough, or an ultrasound looking at a gallbladder, has caught a glimpse of something larger. Now there is a second appointment, a scanner, a cannula in the arm, and a report that will run to two pages of measurements.
That report is the point. Once a doctor knows the aorta is affected, the next questions are geographic. Which stretch of the vessel? How wide, how long, how close to the arteries feeding the brain, the kidneys or the gut? Is the wall stretched, split into two channels, or inflamed? CT angiography for aortic disease, and its radiation-free cousin MR angiography, exist to answer those questions with numbers a surgeon or interventional radiologist can plan around.
This article walks through what the scan shows, how the aorta is divided into segments, what the measurements mean, and what commonly happens in the days and weeks after the images are read.
Why the affected aortic segment matters more than the diagnosis itself
The aorta is one vessel, roughly the diameter of a garden hose in a healthy adult, but it behaves like several. It rises from the heart, arcs over the top of the chest, then runs down alongside the spine into the abdomen before splitting toward the legs. Each portion has different wall structure, different neighbors and different consequences when it fails.
A dilated aortic root sits millimeters from the aortic valve and the coronary arteries; treating it may involve the valve. A widened arch carries the vessels to both arms and the brain, so any repair there has to preserve or re-route those branches. A descending thoracic or abdominal segment can often be lined from the inside with a fabric-covered stent, provided there is enough healthy vessel above and below to anchor it.
That is why the 2022 American College of Cardiology and American Heart Association guideline on aortic disease asks imaging reports to describe location, maximal diameter, extent and branch involvement rather than simply stating “aneurysm” or “dissection” (Isselbacher et al., Circulation 2022, PubMed). The word aneurysm means a permanent widening of the vessel wall. Dissection means a tear in the inner lining that lets blood force its way between the wall’s layers, creating a second channel.
Two people can share the same label and need entirely different care. One may be watched for years with periodic scans; the other may be scheduled for an operation within days. The difference lies in the segment, the size and the anatomy around it, and cross-sectional angiography is the tool that reveals all three at once.
How CT angiography for aortic disease actually works
Angiography simply means imaging blood vessels. In CT angiography, a ring of X-ray detectors spins around the body while the table slides through, building hundreds of thin cross-sectional slices that a computer stacks into a three-dimensional picture (Johns Hopkins Medicine, Computed Tomography Angiography). On its own, CT shows soft tissue and blood as similar shades of gray. The trick is timing.
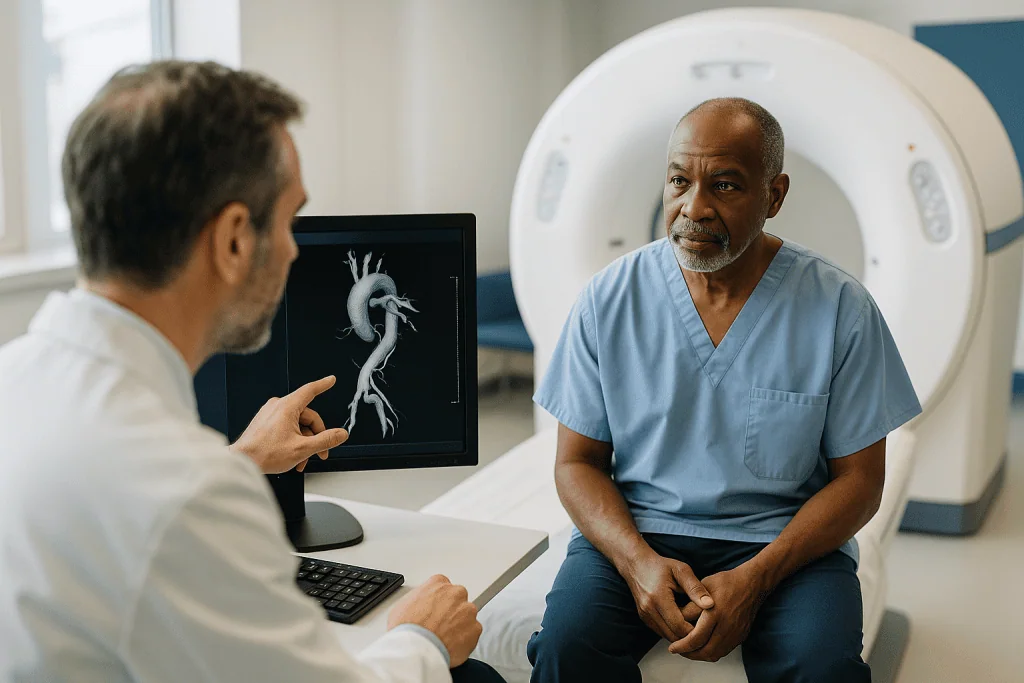
An iodine-based contrast agent is injected through a vein, usually in the arm. Iodine absorbs X-rays strongly, so for a brief window the blood inside the aorta glows white against the darker wall. Modern scanners can capture the entire aorta, from the heart to the pelvis, in a few seconds during a single breath-hold, and the injection is timed so that the images are acquired exactly as the contrast fills the aorta rather than the veins.
Many protocols use more than one pass. A scan taken before any contrast is given can reveal fresh blood trapped in the aortic wall, a condition called intramural hematoma, which shows up as a crescent slightly brighter than the surrounding tissue. The arterial pass then maps the lumen, the open channel through which blood flows. A delayed pass a minute or so later can show slow leaks, or contrast seeping into a dissection’s second channel.
For the aortic root and the first part of the ascending aorta, motion is the enemy. The heart tugs those segments with every beat, and blur can mimic a tear. Electrocardiogram gating, which synchronizes each slice to a quiet moment in the cardiac cycle, freezes that motion. The guideline specifically recommends gated acquisition when the root or ascending aorta is the question (Isselbacher et al., 2022).
The result is not a single picture but a dataset. Radiologists scroll through it, rotate it and reslice it perpendicular to the vessel’s own curve to make measurements that a straight axial slice would distort.
What MR angiography of the aorta adds, and when it is chosen instead
Magnetic resonance angiography, or MRA, reaches similar anatomical answers by a different route. Instead of X-rays, it uses a strong magnetic field and radio waves to map hydrogen atoms in the body’s water and fat (NHS, MRI scan). There is no ionizing radiation, which is why it is often favored for people who will need repeated scans over many years, for younger patients and for those with inherited aortic conditions who begin surveillance in their teens or twenties.
MRA can be performed with a gadolinium-based contrast agent injected into a vein, or with newer non-contrast sequences that use the movement of blood itself to create the image. It also captures information that CT struggles with: the direction and speed of flow in a dissection’s two channels, the degree of aortic valve leakage, and the function of the heart muscle, all within the same appointment.
The trade-offs are practical. An MRI examination typically lasts between 15 and 90 minutes depending on how many sequences are needed (NHS, MRI scan), compared with seconds of scanning for CT. Patients must lie still in a narrower tunnel, and some implanted devices, older pacemakers among them, are not compatible with the magnet. Calcium in the aortic wall, which surgeons want to see before deciding where to clamp or stitch, is nearly invisible on MR.
The 2022 guideline treats CT angiography as the usual first choice in acute settings, where speed and availability decide, and regards MR angiography as an equivalent alternative for planned assessment and long-term follow-up (Isselbacher et al., 2022). In practice, many people will have both over the course of their care: CT to define the problem quickly, MR to watch it over time without accumulating radiation dose.
The map the care team reads: aortic segments, zones and landing sites
Radiologists and surgeons share a common vocabulary for dividing the aorta. The broad segments are the root (where the valve and coronary arteries sit), the ascending aorta, the arch, the descending thoracic aorta, the thoracoabdominal transition where the vessel passes through the diaphragm, and the abdominal aorta, itself split into the portion above the renal arteries and the portion below.

For planning stent-graft procedures, the guideline endorses a finer numbering system, zones 0 through 11, that runs from the ascending aorta to the iliac arteries in the pelvis (Isselbacher et al., 2022). Each zone is defined by the branch vessels it contains. Zone 0 includes the origin of the innominate artery; zone 2 contains the left subclavian; zones 5 through 9 carry the celiac, superior mesenteric and renal arteries. Naming the zone tells the team immediately which organs’ blood supply must be protected.
| Region | Key branches | Why the segment matters for planning |
|---|---|---|
| Root and ascending | Coronary arteries, aortic valve | Repair is open surgery; valve may need attention; ECG-gated imaging essential |
| Arch | Innominate, left carotid, left subclavian | Brain and arm supply must be preserved or rerouted |
| Descending thoracic | Intercostal arteries, spinal cord supply | Often suitable for stent graft if healthy landing zone exists |
| Thoracoabdominal | Celiac, superior mesenteric, renal | Most complex repairs; branched or fenestrated devices, or open surgery |
| Infrarenal abdominal | Inferior mesenteric, iliac bifurcation | Most common aneurysm site; neck length and angulation decide device suitability |
The report then attaches numbers to the map. Maximal diameter is measured perpendicular to the vessel’s centerline, because an oblique cut through a curved tube exaggerates width. Length of the diseased segment, the distance of healthy aorta above and below it (the “neck” or landing zone), the angle at which the aorta bends, the amount of clot lining the wall, and the diameter of the iliac arteries through which a device would travel are all recorded. Each of those figures maps to a specific decision about whether, how and by what route the segment can be treated.
Dissection on the scan: entry tears, two lumens and Stanford type A versus B
When the problem is a dissection rather than an aneurysm, the report answers a different set of questions. The most urgent is whether the ascending aorta is involved. The Stanford system, used in both the guideline and everyday clinical language, labels any dissection that touches the ascending aorta as type A, and any dissection confined to the descending aorta, beyond the left subclavian artery, as type B (Mayo Clinic, Aortic dissection). Type A generally leads to emergency open surgery; uncomplicated type B is often managed initially with blood pressure control and close imaging, with intervention reserved for specific complications.
CT angiography shows the separation as a thin flap dividing the vessel into a true lumen, the original channel, and a false lumen, the new one created within the wall. The radiologist looks for the primary entry tear, the point where blood first breaks through, and for re-entry tears further along. The location and size of the entry tear matter for stent-graft planning, since the device’s purpose is to cover it.
The scan also reports which branch arteries arise from which lumen. A kidney or a loop of bowel fed only by a compressed false lumen may be starved of blood, a state called malperfusion. Malperfusion turns an uncomplicated type B dissection into a complicated one, and the guideline lists it among the findings that shift management toward intervention (Isselbacher et al., 2022).
Timing is described too. The guideline defines dissection as acute within the first 14 days after symptom onset, subacute from days 15 to 90, and chronic beyond 90 days (Isselbacher et al., 2022). The same flap looks different across those phases; an acute flap is thin and mobile, a chronic one thickened and fixed, and the distinction influences whether and when an endovascular repair is likely to remodel the vessel.
Who is usually offered CT or MR angiography, and who is usually asked to wait
The scans described here are not screening tests for the general population. They are ordered when there is already a reason to look closely at the aorta. Common triggers include an aneurysm found on ultrasound or another scan, symptoms that raise concern for dissection, a known inherited condition such as Marfan or Loeys-Dietz syndrome, a bicuspid aortic valve, a first-degree relative with aortic disease, or planned surgery on the heart or great vessels (Isselbacher et al., 2022).
Screening for abdominal aortic aneurysm, by contrast, is usually done with ultrasound, which involves no contrast or radiation. In the UK, for example, men are invited for a single ultrasound at age 65 (NHS, Abdominal aortic aneurysm). Ultrasound measures diameter well but cannot map the arch, the descending thoracic aorta or the branch anatomy, so it hands over to CT or MR when the aneurysm approaches the size at which repair is considered, or when it lies above the kidneys.
Who is asked to wait? Someone with a small aneurysm that is stable on ultrasound generally does not need cross-sectional imaging at every visit; the added detail would not change the plan. Someone whose kidney function is impaired may have CT deferred while the team weighs the contrast risk against the urgency, or may be offered non-contrast MR instead. A person in the early weeks of pregnancy will usually have MR without gadolinium rather than CT, unless the situation is an emergency, in which case the guideline is clear that a suspected dissection should never wait for a safer modality.
The deciding factor is always whether the extra information would change what happens next. When it would, the scan is booked promptly. When it would not, the treating team may reasonably choose to watch with simpler tools.
CT angiogram of the aorta: what to expect on the day
Most people arrive having been asked to avoid eating for a few hours, though clear fluids are usually encouraged. A blood test checking kidney function is often done beforehand, because iodinated contrast is cleared by the kidneys (Johns Hopkins Medicine, Computed Tomography Angiography). Anyone with a prior reaction to contrast, asthma, diabetes treated with certain tablets, or thyroid disease should mention it; the team may adjust preparation or choose MR.
A radiographer places a small cannula in a vein, typically at the elbow. You lie on a narrow table that moves through the scanner’s open ring. If the root or ascending aorta is being assessed, sticky electrodes on the chest let the scanner track your heartbeat. Some centers give a short-acting medicine to slow the heart briefly for sharper gated images; that decision belongs to the radiology team and is explained beforehand.
When the contrast is injected, a warm flush spreads through the body and many people feel a strong, momentary urge to pass urine. Both sensations are normal and pass within a minute. A recorded voice asks you to hold your breath, the table glides, and the scan itself is over in seconds. The cannula is removed, and most people are free to leave shortly afterward, drinking extra fluids for the rest of the day to help clear the contrast.
If MR angiography has been chosen, expect the longer session described earlier, ear protection against the machine’s knocking sounds, and repeated instructions to hold your breath for short sequences. A gadolinium injection, if used, causes little or no sensation.
The images are read by a radiologist, often with software that traces the aorta’s centerline automatically. Results are usually discussed at a following appointment or, in urgent cases, within the same admission.
Contrast, kidneys and radiation: the trade-offs worth understanding
Every imaging choice has a cost in the clinical sense, and the honest way to describe it is to name the risks and set them against what the scan achieves.
Iodinated contrast can, in a small proportion of people, cause an allergic-type reaction ranging from hives to, rarely, a severe response requiring treatment. It can also temporarily reduce kidney function, particularly in people whose kidneys are already impaired or who are dehydrated (Johns Hopkins Medicine, Computed Tomography Angiography). That is why kidney blood tests are checked first, fluids are encouraged, and alternatives are considered when the risk is judged high.
CT involves ionizing radiation. A single aortic CT angiogram delivers a dose that mainstream bodies consider acceptable for the information it provides, and the risk of any single scan is small. The concern is cumulative. A person diagnosed with an aneurysm in their forties may need dozens of scans over a lifetime, and the guideline explicitly recommends MR for long-term surveillance in younger patients to limit accumulated exposure (Isselbacher et al., 2022). Newer scanners and lower-dose protocols have reduced dose substantially compared with older technology, though the exact figure varies by machine and patient size.
Gadolinium contrast used in MR carries its own, generally lower, list of concerns. Severe allergic reactions are rare. In people with very poor kidney function, older gadolinium agents were linked to a rare skin and organ scarring condition, which is why kidney function is checked here as well and why newer agents are preferred (NHS, MRI scan).
Weighed against these is the alternative: not knowing precisely where a potentially fatal problem lies. For most people facing aortic disease, that uncertainty carries far more risk than the scan. The decision about which test, and how often, still rests with the treating team, who can put the numbers in the context of your kidneys, your age and your history.
What the following days and weeks usually look like
Once the images are read, the path splits according to what they show.
If the scan confirms an aneurysm below the size threshold for repair, the typical outcome is a surveillance plan rather than a procedure. For abdominal aneurysms, the NHS schedule offers a useful illustration: aneurysms between 3.0 and 4.4 cm are rescanned yearly, those between 4.5 and 5.4 cm every three months, and those of 5.5 cm or more are referred to a vascular specialist to discuss repair (NHS, Abdominal aortic aneurysm). Thoracic aneurysms follow similar logic with intervals set by the treating team. Surveillance is usually done with ultrasound for the abdominal aorta and MR or CT for the chest, and a new baseline scan is often repeated at six months after first diagnosis to establish whether the aneurysm is growing (Isselbacher et al., 2022).
During this period, the emphasis falls on the factors that influence growth: blood pressure control, stopping smoking, and treatment of cholesterol where indicated. Where medicines are prescribed, they aim to lower the force on the vessel wall; how and whether they are used is a matter for the prescribing clinician.
If the scan shows an aneurysm at or above threshold, or a dissection, the next weeks involve planning meetings, further tests of heart and lung fitness, and a discussion of open versus endovascular options in light of the anatomy the scan revealed. A stent-graft procedure requires the device to be sized precisely from the CT measurements, which sometimes means a wait while a custom device is made.
After any repair, imaging does not stop. The guideline recommends CT or MR at set intervals in the first year after an endovascular procedure and then lifelong, at least annually, to check that the device remains sealed and the aorta has not enlarged elsewhere (Isselbacher et al., 2022). Many patients describe this as the hardest adjustment: the operation ends, but the scanning does not.
Aortic aneurysm size for surgery: how the measurements feed the decision
Diameter is the single number patients remember, and for good reason. The risk of rupture or dissection rises steeply as the aorta widens, and repair carries its own risk, so guidelines set thresholds where the balance tips.
For the ascending aorta in a person without a connective tissue disorder, the 2022 guideline places the usual threshold for elective repair at 5.5 cm, with a lower threshold of 5.0 cm considered reasonable in experienced surgical centers or when other risk factors are present (Isselbacher et al., 2022). People with Marfan syndrome and related conditions are offered repair at smaller diameters, often around 5.0 cm or lower depending on family history and rate of growth. For the abdominal aorta, 5.5 cm in men and 5.0 cm in women are the commonly cited thresholds, reflecting the smaller baseline size of the female aorta (Isselbacher et al., 2022; NHS, Abdominal aortic aneurysm).
Diameter is not the whole story, and this is where imaging earns its keep. Rapid growth, generally defined in the guideline as more than 0.5 cm in a year on comparable scans, can prompt repair below the absolute threshold. The team also indexes diameter to body size, since a 4.8 cm aorta means something different in a person of small stature than in a very tall one. Symptoms attributed to the aneurysm, a saccular rather than uniform shape, and planned surgery on the aortic valve for other reasons all shift the calculation.
For endovascular repair specifically, the CT measurements decide feasibility. A stent graft needs a segment of relatively straight, healthy aorta of adequate length above and below the aneurysm to seal against, and access arteries in the pelvis wide enough to admit the delivery system. When the anatomy does not meet those criteria, open surgery or a fenestrated device with openings for branch vessels is discussed instead. The scan does not make the decision, but it defines the options the team can offer.
What are the warning signs of aortic dissection, and when should you see a doctor?
Because dissection can occur in someone with no prior aortic diagnosis, its warning signs deserve plain description, with the caveat that no list can substitute for assessment by a clinician.
The classic presentation is sudden, severe pain in the chest, upper back or between the shoulder blades, often described as tearing or ripping, and reaching maximum intensity within moments rather than building gradually (Mayo Clinic, Aortic dissection). The pain may travel as the tear extends, moving from chest to back or down into the abdomen. Accompanying features can include fainting, shortness of breath, a stroke-like weakness or difficulty speaking on one side, a pulse that is noticeably weaker in one arm than the other, or a leg that suddenly turns pale and cold.
Not every dissection follows the script. Some people report a milder or more diffuse pain, and dissection is occasionally mistaken for a heart attack, a pulled muscle or severe indigestion until imaging tells the truth. This is precisely why CT angiography is performed urgently when the clinical picture raises suspicion; the scan can confirm or exclude a dissection within minutes, and the guideline supports low thresholds for imaging in anyone with sudden severe chest or back pain and risk factors such as high blood pressure, a known aneurysm, a connective tissue disorder or a family history (Isselbacher et al., 2022).
When to seek care: sudden severe chest, back or abdominal pain, especially if it is the worst pain you have experienced or arrives with fainting, weakness on one side, difficulty speaking, or a cold and painful limb, is an emergency. Call your local emergency number rather than driving yourself. If you have a known aneurysm and develop new persistent pain in the same region, even without those features, contact your care team or emergency services the same day.
What people often get wrong about aortic imaging
“An ultrasound already found it, so the CT is just a repeat.” Ultrasound measures diameter at the point the probe can reach. It cannot reliably see the thoracic aorta behind the breastbone, define the branch arteries, or measure the landing zones a stent graft would need. The two tests answer different questions.
“A bigger number on this scan means the aneurysm grew.” Small differences between scans are often measurement differences rather than growth. A CT read perpendicular to the centerline may give a smaller figure than an ultrasound taken obliquely, and different readers vary by a millimeter or two. That is why the guideline asks for comparable techniques and side-by-side reading before concluding that an aneurysm is enlarging (Isselbacher et al., 2022).
“MR is always safer, so it should always be chosen.” MR avoids radiation, but it takes longer, is unsuitable for some implants, misses wall calcium and is less available in emergencies. For a suspected acute dissection, waiting for MR could be dangerous; CT is the guideline’s first-line choice in that setting.
“Once repaired, the aorta is fixed for good.” Repair treats the segment addressed. The rest of the aorta remains the same tissue, subject to the same pressures, and endovascular devices can develop leaks around their edges. Lifelong surveillance imaging is part of the treatment, not an optional extra.
“Contrast damages the kidneys of everyone who receives it.” Temporary reductions in kidney function are uncommon in people with normal baseline function who are well hydrated. The risk is real but concentrated in those with existing kidney disease, which is why it is checked beforehand and why alternatives exist.
“If I have no symptoms, the aorta must be fine.” Most aneurysms cause no symptoms until they are large or rupture (MedlinePlus, Aortic Aneurysm). The absence of pain is reassuring about the present moment, not about the diameter.
Questions to ask your care team about your scan results
A two-page radiology report can feel like a foreign language. These questions help translate it into a plan you understand, and they signal to the team what matters to you.
- Which segment of my aorta is affected, and where exactly does the abnormal portion begin and end?
- What is the maximal diameter, and was it measured perpendicular to the vessel’s centerline? How does it compare with my previous scans, if any?
- Are any branch arteries involved, and if so, which organs do they supply?
- If this is a dissection, is it type A or type B, where is the entry tear, and are both kidneys and the bowel receiving blood normally?
- Is my anatomy suitable for an endovascular repair, or would open surgery be the option if treatment is needed? What features of the scan led to that view?
- How fast, if at all, is the aneurysm growing, and what rate would change the plan?
- What interval of follow-up imaging do you recommend, and will it be ultrasound, MR or CT? Why that choice for me?
- Given my kidney function and age, what are the specific risks of contrast and radiation in my case?
- Should my parents, siblings or children be offered screening because of this finding?
- What symptoms should prompt me to seek emergency care before my next scheduled appointment?
- Which blood pressure target are you aiming for, and how will we know it is being achieved?
Bring a copy of the report and ask for a printed or digital summary of the answers. Aortic disease is managed over years, sometimes by several teams, and a clear record of the measurements at each stage helps everyone involved make consistent decisions.
When to call your doctor
People living with a diagnosed aortic condition, or recovering from an aortic scan or procedure, should know which situations need a same-day call and which need an ambulance.
Call emergency services immediately for any of the following: sudden severe pain in the chest, back, or abdomen, particularly if it is tearing in quality or the worst pain you have known; fainting or near-fainting with pain; sudden weakness, numbness, facial drooping or trouble speaking; a limb that becomes suddenly cold, pale, painful or numb; severe shortness of breath; or a pulsing abdominal mass with pain. Any of these in a person with a known aneurysm or dissection should be treated as a possible rupture or extension until proven otherwise (Mayo Clinic, Aortic dissection; NHS, Abdominal aortic aneurysm).
Contact your care team the same day if you develop new, persistent, dull pain in the region of your known aneurysm; a fever with chills after a recent endovascular procedure; new swelling, redness or discharge at a groin or arm puncture site; a marked drop in urine output or swelling of the legs in the days after a contrast scan, which may signal a kidney reaction; or hives, wheeze or facial swelling in the hours after a contrast injection that did not resolve quickly.
Raise at your next appointment questions about blood pressure readings that are consistently above the target you were given, new medicines prescribed by other clinicians, plans for pregnancy, or upcoming surgery elsewhere in the body, all of which can affect how the aorta is managed.
None of these lists replaces clinical judgment. When in doubt about a symptom, the safer choice is to call. Aortic disease is one of the conditions where minutes matter, and no member of a care team will fault a patient for asking.
Frequently asked questions
What is the difference between CT angiography and a standard CT scan of the chest?
The difference is contrast timing. A standard CT may be done without contrast or with contrast given for general soft-tissue detail, whereas CT angiography times the scan to the moment iodinated contrast fills the arteries, making the aortic lumen bright and any tear, clot or widening measurable. Angiographic protocols also often add ECG gating and thinner slices to capture the aortic root without motion blur.
What is the life expectancy after surgery for aortic dissection?
There is no single figure that applies to an individual. Outcome after dissection repair depends on age, whether the ascending aorta was involved, whether organs were deprived of blood before surgery, other health conditions, and how well blood pressure is controlled afterward. The 2022 ACC/AHA guideline emphasizes that lifelong imaging surveillance and risk-factor control substantially influence the long-term course, which is why follow-up scanning continues after the operation.
What is the most common cause of an aortic aneurysm?
For the abdominal aorta, the most common contributor is atherosclerosis, the buildup of fatty and calcified plaque that weakens the vessel wall, with smoking, high blood pressure, age and male sex as major risk factors (MedlinePlus, Aortic Aneurysm). Thoracic aneurysms more often involve inherited connective tissue conditions, bicuspid aortic valve or long-standing hypertension. Family history raises risk for both, which is why relatives may be offered screening.
Can indigestion be a symptom of an aortic aneurysm?
Occasionally an abdominal aneurysm causes vague, persistent discomfort in the upper abdomen or back that people describe as indigestion, but most aneurysms cause no symptoms at all until they are large (NHS, Abdominal aortic aneurysm). Ordinary indigestion is far more common and usually relates to meals. New, persistent or unexplained abdominal or back pain, especially in someone with risk factors, deserves a medical assessment rather than self-diagnosis.
How long does a CT angiogram of the aorta take, and what does it feel like?
The scanning itself takes only seconds, typically during one or two breath-holds, though the appointment includes cannula placement, positioning and sometimes a blood test. During the contrast injection most people feel a brief warm flush spreading through the body and a momentary sensation of needing to urinate; both pass within about a minute. There is no pain from the scan, and most people leave shortly afterward.
Is MR angiography of the aorta as accurate as CT for planning treatment?
For measuring diameter, length and branch involvement, the 2022 ACC/AHA guideline regards MR angiography as an equivalent alternative to CT in non-emergency settings and often prefers it for repeated surveillance in younger people. MR adds flow and valve information, but it does not show wall calcium well, takes longer, and is less available urgently. Many teams use CT for initial definition and MR for follow-up.
What aortic aneurysm size usually leads to surgery being discussed?
Guidelines commonly cite 5.5 cm for the ascending and abdominal aorta in men, 5.0 cm for the abdominal aorta in women, and lower thresholds for people with Marfan syndrome or similar conditions (Isselbacher et al., 2022). Rapid growth above 0.5 cm per year, symptoms attributed to the aneurysm, or a saccular shape can prompt earlier discussion. The decision always weighs individual risk with the treating team.
Do I need to stop any medicines before a CT angiogram?
Usually very few, but some diabetes tablets and certain other medicines may be paused briefly around iodinated contrast because of kidney considerations, and this is decided by the radiology team based on your kidney function. Never stop a prescribed medicine on your own before a scan. Bring a current list to the appointment and follow the written instructions you are given; if none were provided, ask before the day.
Why does the aorta need scanning again after it has been repaired?
Because repair treats one segment and the rest of the aorta remains the same tissue under the same pressure. After endovascular repair, imaging checks that the stent graft is sealed and that no blood is leaking around it into the aneurysm sac, a problem called an endoleak. The 2022 guideline recommends imaging at set intervals in the first year and then at least annually for life.
What are the warning signs of aortic dissection that should never be ignored?
Sudden severe chest or back pain that peaks within moments, often described as tearing, is the hallmark, particularly when it travels, comes with fainting, causes stroke-like weakness or speech difficulty, or leaves one arm or leg cold and pulseless (Mayo Clinic, Aortic dissection). These are emergencies requiring an ambulance, not a routine appointment. Milder or atypical pain in someone with a known aneurysm should also prompt same-day contact with the care team.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Prediabetes Diet: What to Eat to Push Blood Sugar Back Into Range
A prediabetes diet centers on high-fiber vegetables, legumes, whole grains, fruit, nuts, lean proteins and unsaturated fats, while shrinking sugary drinks, refined grains and…

How Long Is Recovery After Endovascular Surgery? Access-Site Care and Activity Limits
Recovery after endovascular surgery is usually measured in days to a few weeks rather than months. Most people leave the hospital within about one…

What Preparing for Robotic Cardiac Surgery Involves: Angiography, Echo and a Medicine Review
Preparing for robotic cardiac surgery usually involves three strands: imaging that maps the heart and vessels (coronary angiography and echocardiography, often with a chest…

Statin Side Effects: Muscle Aches, Diabetes Risk and the Nocebo Effect, Explained
Statins side effects are usually mild and less common than many people believe. Muscle aches are the most reported complaint, yet blinded trials show…

Can Stress Raise Cholesterol? What the Research Shows and How to Lower Both
Stress can raise cholesterol, though usually indirectly and modestly. Stress hormones such as cortisol and adrenaline release fatty acids and glucose into the blood,…

Blood Pressure Chart: What Your Numbers Mean at Every Age
A blood pressure chart sorts readings into categories. Normal is below 120/80 mmHg; elevated is 120 to 129 on top with a bottom number…