

How Does Whooping Cough Progress Through Its Three Stages and Why Does Timing Matter?

Key Takeaways
- The pertussis incubation period is usually 5–10 days but can stretch to 21, which is why exposed contacts are watched for a full three weeks.
- The catarrhal stage looks like an ordinary cold yet is the most contagious phase, and it is the only phase in which antibiotics may make the illness itself milder.
- Coughing fits typically last one to six weeks and can extend to ten, followed by a convalescent cough that can persist for three months or more and rebound with new colds.
- Untreated, a person remains contagious for about three weeks after coughing fits begin; with an appropriate antibiotic, that shrinks to five days.
- Most adults and many infants never produce the classic whoop, so a prolonged cough in bursts should be assessed regardless of the sound.
- About one in three infants under one year with pertussis need hospital care, and among hospitalized infants roughly one in a hundred die, which is why early treatment of coughing adults and household contacts matters most.
Whooping cough moves through three stages: a catarrhal stage of cold-like symptoms lasting about one to two weeks, a paroxysmal stage of violent coughing fits that typically lasts one to six weeks but can stretch to ten, and a convalescent stage of slow recovery over weeks to months. Timing matters because antibiotics work best, and contagiousness is highest, in the first two to three weeks, before the characteristic cough appears.
The pediatrician’s waiting room is quiet at 8 a.m., and the mother in the corner keeps checking her phone. Her four-year-old has had a runny nose for ten days. Nothing dramatic. Then, last night, he coughed so hard he could not draw breath, turned an alarming shade of red, and finally gasped in a long, thin, high-pitched inhale before doing it all over again. She searched the sound. The results all said the same thing: whooping cough stages, and you may already be in the second one.
That story captures the frustrating design of pertussis, the bacterial infection behind whooping cough. It arrives disguised as a cold, reveals itself only once the bacteria have done much of their damage, and lingers for so long that some countries call it the hundred-day cough.
Understanding those three phases is not academic. Where a person sits on the timeline shapes whether antibiotics help, who around them needs protecting, and which test will actually find the infection.
What are the three whooping cough stages at a glance?
Doctors describe pertussis in three overlapping phases, and the names are old-fashioned enough to need translating. Catarrhal simply means the runny-nose phase. Paroxysmal refers to paroxysms, which are sudden fits of coughing. Convalescent means recovery. The timings below come from the Centers for Disease Control and Prevention (CDC) clinical guidance and describe typical courses, not guarantees for any individual.
| Stage | Typical duration | What it usually looks like | Why the timing matters |
|---|---|---|---|
| Incubation (before symptoms) | Usually 5–10 days; up to 21 days | No symptoms; bacteria multiplying in the airway lining | Explains why exposed people are watched for three weeks |
| Stage 1: Catarrhal | About 1–2 weeks | Runny nose, mild cough, low or no fever | Most contagious; antibiotics most useful |
| Stage 2: Paroxysmal | 1–6 weeks; may last up to 10 | Coughing fits, whoop, vomiting after coughing, exhaustion | Diagnosis often made here; infants at highest risk |
| Stage 3: Convalescent | Weeks to months | Fits fade in frequency and force; cough can rebound with new colds | Usually no longer contagious; recovery is slow |
Two features of this table deserve emphasis. The first is that stage one is indistinguishable from an ordinary cold on symptoms alone, which is exactly when the infection spreads most freely. The second is the sheer length of the whole course. From the first sniffle to the last cough, a typical case can run two to three months, which is why a parent who is told the illness will “run its course” often wants to know what that course actually contains.
The sections that follow walk through each phase and then return to the question that sits underneath all of them: why a few days earlier or later can change what a clinician is able to do.
How does whooping cough actually work inside the airway?
Pertussis is caused by a bacterium called Bordetella pertussis. It travels in the droplets a person releases when coughing or sneezing, and once inhaled it attaches to the tiny hair-like projections, called cilia, that line the upper airway. Cilia normally sweep mucus and debris up and out of the lungs in a constant, gentle escalator motion.
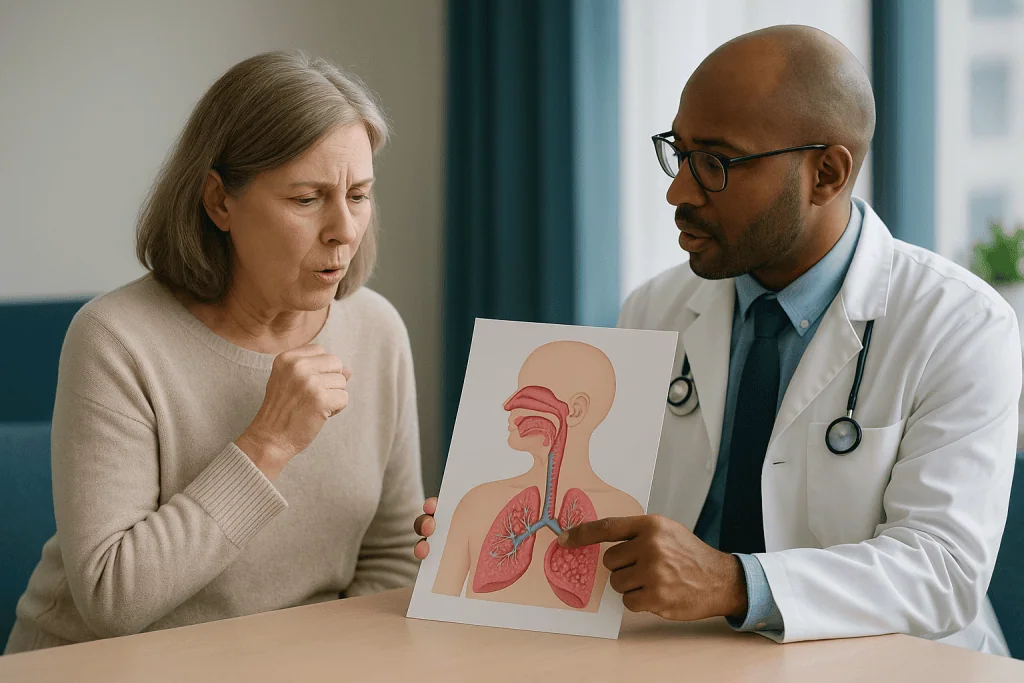
The bacteria do two things at once. They multiply along that lining, and they release toxins. According to the CDC, these toxins paralyze the cilia and inflame the airway, so the mucus escalator stops working. Secretions pool. The airway swells. The body’s only remaining way to clear the thick mucus is a cough, and not a normal one: a forceful, repeating burst that continues until the lungs are nearly empty, followed by the desperate inhale that produces the whoop.
Here is the detail that explains almost everything about timing. The toxins are the problem, and toxins outlast the bacteria that made them. Antibiotics can kill Bordetella pertussis, but they cannot undo damage that has already been done to the airway lining. By the time the classic coughing fits arrive, the bacterial numbers are often already falling on their own, while the injured cilia will take weeks to regrow. That is why, as the Mayo Clinic notes, antibiotics started late in the illness do little to shorten the cough, even though they still reduce the chance of passing the infection to others.
It also explains why the cough looks the way it does. Between fits, many people, particularly older children and adults, seem well. The airway is not constantly obstructed; it is intermittently overwhelmed, and each fit is the body doing manual labor that the cilia would normally do for free.
Stage one: why the catarrhal phase looks like an ordinary cold
For the first week or two, pertussis hides in plain sight. The CDC describes the catarrhal stage as a runny nose, occasional mild cough, low-grade fever or none at all, and sometimes watery eyes. There is nothing in that list that would prompt most people to stay home, let alone see a doctor. A person can go to work, send a child to daycare, hold a newborn niece, and feel entirely reasonable doing so.
Yet this is the period of peak contagiousness. The bacteria are at their most numerous in the nose and throat before the immune system and the toxins have thinned their ranks. The CDC states that people with pertussis are infectious from the very start of the catarrhal stage through roughly the third week after coughing fits begin, or until five days after starting an effective antibiotic. In practical terms, the window of greatest spread is almost entirely spent in a phase that nobody recognizes.
A few subtle clues sometimes exist, and they are worth knowing without turning them into a self-diagnosis checklist. The cough in early pertussis tends to be dry and tends to get gradually worse rather than better after a week, which is the opposite of a typical viral cold. Fever is usually absent or slight. In babies under a year, the NHS notes, the early phase may involve very little coughing at all; parents may instead notice pauses in breathing or a change in color, which are covered later in this article.
What clinicians actually rely on during this stage is context. A known exposure at school, a household member with a prolonged cough, or a local outbreak changes how a runny nose is interpreted. That is why the single most useful thing a person can do in stage one is mention any known contact with a coughing illness, even if it seems minor.
Stage two: what the paroxysmal stage feels like, and why the whoop is not universal
Somewhere in the second week, the cough changes character. A paroxysm is a rapid series of coughs, often five to fifteen in a row, on a single breath, with no chance to inhale between them. The CDC describes what follows: a long, high-pitched inhale (the whoop), sometimes vomiting from the force of the fit, sometimes a blue or purple tinge around the lips from the temporary lack of oxygen, then profound tiredness. Fits are often worse at night and can be triggered by feeding, crying, laughing, or a change in air temperature.

Between fits, many people look surprisingly normal, which can be disorienting for a parent who watched their child struggle to breathe an hour earlier. The fits themselves typically increase in frequency through the first one to two weeks of this stage, plateau for two to three weeks, then slowly ease. The CDC gives one to six weeks as the usual span, with some cases extending to ten.
The whoop is famous, but it is not required. The Mayo Clinic and the NHS both point out that adults and adolescents, especially those with some vaccine-induced or past-infection immunity, often have a prolonged hacking cough without any whoop at all. Infants under about six months may be too weak to generate one; their fits may end in a gasp, a silence, or an episode of apnea, which is a pause in breathing. So the absence of a whoop rules nothing out.
The physical toll of stage two in older patients comes from repetition rather than from any single fit. Over weeks of forceful coughing, the CDC lists rib fractures, loss of bladder control, fainting, weight loss from vomiting and disrupted sleep, and abdominal hernias as recognized complications in teenagers and adults. These are mechanical injuries from the cough itself, not signs of the infection worsening, and they are one reason a long cough deserves medical attention even when the person feels otherwise fine.
Stage three: the long convalescent tail
Recovery from pertussis is not a switch flipping off. It is a slow dimming. In the convalescent stage the coughing fits become less frequent and less violent, the whoop fades, and appetite and sleep gradually return. The CDC describes this phase as lasting weeks to months, and the NHS is blunt about the reality: the cough can persist for three months or longer even after the person is no longer infectious.
Two features of this stage catch people off guard. The first is the rebound. For months after pertussis, a new viral cold can reawaken the coughing fits, sometimes convincingly enough that families fear a relapse. The mechanism is not a return of Bordetella pertussis; it is an airway that is still healing and still hyper-reactive, responding to a fresh irritant with the same exaggerated cough reflex it learned during stage two. Clinicians generally regard this as an expected part of recovery rather than a new infection, though only a clinician can make that call for a particular patient.
The second surprise is how ordinary life resumes while the cough continues. Children return to school, adults return to work, and yet the cough remains a nightly companion. This is where families most often ask whether anything can speed things up. The honest answer, drawn from the Mayo Clinic and NHS guidance, is that no medicine reliably shortens the convalescent cough. Over-the-counter cough suppressants are not recommended for young children and have little evidence of benefit in pertussis at any age. What helps is time, rest, fluids, small frequent meals, and a home kept as free as possible of smoke and other airway irritants.
The name “hundred-day cough,” used in several East Asian languages, is a folk estimate rather than a clinical one, but it captures the expectation well. If the whooping cough stages are thought of as a journey, stage three is the longest and least eventful leg.
How quickly does whooping cough progress from exposure to coughing fits?
People often ask this because they are counting backward from a known exposure or forward from a cold that will not quit. The answer has a wide range, and the range itself is the point.
The pertussis incubation period, meaning the time between breathing in the bacteria and the first symptom, is usually 5–10 days, according to the CDC, but can extend to 21 days. That three-week outer limit is why public health teams ask exposed households to watch for symptoms for a full 21 days rather than one week.
Once the runny nose appears, the catarrhal stage typically lasts one to two weeks before the cough turns into distinct fits. So a plausible timeline from exposure to the first true paroxysm is anywhere from about ten days to five weeks. For a parent, that means a child exposed at a birthday party might not cough alarmingly until a month later, by which time the party is long forgotten and the connection is easy to miss.
Progression is also uneven across ages. The Mayo Clinic notes that infants may skip a recognizable catarrhal stage almost entirely and present with apnea or feeding difficulty within days. Adults with partial immunity may never develop classic fits and instead drift from a mild cough into a persistent one without a clear moment of change. The tidy three-stage model is most accurate for unvaccinated older children, who happen to be the group in whom the disease was first described.
Why does any of this matter beyond curiosity? Because every intervention in pertussis has a clock attached. The diagnostic test that works, the antibiotic decision, the advice to household contacts, and the decision about school or work all depend on estimating where on this timeline a person currently stands. The next section deals with the most consequential of those clocks.
Why does timing matter for treatment, and how long is whooping cough contagious?
Antibiotics for pertussis, usually a class called macrolides, work by killing Bordetella pertussis in the airway. The CDC is explicit that they are most effective when started during the catarrhal stage, before coughing fits begin, because that is when live bacteria are most abundant and the toxin damage is still limited. Started early, they may make the illness milder. Started once the fits are established, they do little for the cough itself, because the toxins have already injured the cilia.
That does not make later antibiotics useless. Their second job is to stop transmission. The CDC states that a person with pertussis remains contagious until five days after beginning an appropriate antibiotic, compared with roughly three weeks after the onset of coughing fits without treatment. For a household with a newborn or a pregnant member, cutting the contagious period from weeks to days is a meaningful outcome even when the patient’s own cough is unchanged.
Guidance therefore sets a window. The CDC recommends antibiotic treatment for people with pertussis within three weeks of cough onset, extended to six weeks for infants under one year and for pregnant women, particularly in the third trimester. Beyond those windows, the bacteria have usually cleared on their own, the person is generally no longer contagious, and antibiotics are not routinely recommended. The prescribing clinician weighs the exact timing, the patient’s age, and who lives at home; nothing in this article replaces that judgment, and no one should start, stop, or change an antibiotic without it.
The same clock governs isolation advice. The NHS advises staying away from school, nursery, or work until 48 hours after starting antibiotics, or until three weeks after the cough began if antibiotics are not used. Many people find the asymmetry striking: the illness lasts months, the contagious window is measured in weeks, and the treatable window is shorter still.
How is whooping cough diagnosed at each stage?
The stage a person is in also decides which test can find the infection, and this is a frequent source of confusion when a test comes back negative in someone who clearly has the illness.
Culture, which means growing the bacteria from a swab of the back of the nose, is the traditional gold standard but is only reliable in the first two weeks or so of symptoms. After that, bacterial numbers fall and the culture may be negative even in true pertussis. Polymerase chain reaction, or PCR, detects fragments of the bacterium’s genetic material and stays useful longer; the CDC describes its best performance within the first three to four weeks of cough. Serology, a blood test for antibodies, comes into its own later, when the cough has persisted for several weeks and the bacteria themselves are gone.
In practice, a clinician who suspects pertussis in a coughing child at week two will usually take a nasopharyngeal swab for PCR. The swab passes through the nostril to the back of the nose and throat; it is uncomfortable for a few seconds and children often cry, but it is not painful in a lasting way. Preparing a child by explaining that it feels like a tickle that makes the eyes water, and holding them securely and calmly, tends to make it quicker for everyone.
Because testing lags behind symptoms, clinicians are often permitted to treat on clinical suspicion and epidemiological grounds, meaning a compatible cough plus a known exposure or a local outbreak, without waiting for laboratory confirmation. The CDC’s clinical case definition for surveillance purposes centers on a cough of at least two weeks with fits, a whoop, post-cough vomiting, or apnea in infants. A negative test late in the illness does not overturn a diagnosis made on that basis, and a treating team may reasonably keep the label of pertussis even when the laboratory cannot confirm it.
Who is most at risk, and who is usually asked to wait and watch?
Pertussis is not equally dangerous to everyone, and the whooping cough stages play out very differently depending on age and immunity. This shapes who is tested and treated promptly and who is managed more conservatively.
Infants under one year, and especially those under six months, sit at the top of every guideline’s concern. They are too young to have completed their own vaccine series, their airways are narrow, and they can develop apnea rather than a cough. The CDC reports that about one in three infants under one who get pertussis need hospital care. For this group, clinicians tend to act early: testing, treatment within the extended six-week window, and a low threshold for hospital observation.
Pregnant women, particularly in the third trimester, are prioritized not mainly for their own sake but because treating them protects the newborn, who is at the greatest risk of severe disease in the first weeks of life. People with chronic lung conditions, weakened immune systems, or other significant illnesses are also generally treated without delay.
Close household contacts occupy the next tier. The CDC recommends post-exposure antibiotics for household contacts and for other exposed people who are themselves at high risk or who live with someone at high risk, ideally within three weeks of exposure. Whether a given contact receives them is a clinician’s decision based on the exposure and the household.
Who is asked to wait? Otherwise healthy adolescents and adults who have coughed for more than three weeks, with no infants, pregnant people, or vulnerable contacts at home, often fall outside the treatment window. For them, the bacteria have usually gone, antibiotics would not change the cough, and the management is supportive. That can feel like being turned away, but it reflects the biology described earlier rather than any lack of concern. Vaccination status also matters at every tier: routine childhood immunization and adolescent and adult boosters are the main reason severe pertussis is now rare in older children.
Whooping cough in babies: why the stages look different under one year
The textbook three-stage pattern was written for older children, and parents of infants can be dangerously reassured by it. In a baby, pertussis may never produce a whoop, may never produce much of a cough at all, and may announce itself first through breathing pauses.
Apnea is the word to know. It means a pause in breathing, and in infants with pertussis it can occur during or after a coughing spell, or with no obvious cough at all. The NHS lists it alongside color change, meaning a blue or gray tinge to the lips or face, as a reason to seek emergency help. The CDC reports that among infants under one year who are hospitalized with pertussis, about two in three have apnea, about one in five develop pneumonia, and roughly one in a hundred have seizures. Poor feeding, because a baby cannot coordinate sucking, swallowing, and breathing while the airway is congested, is another early sign that often precedes any recognizable cough.
Where do babies catch it? Studies cited by the CDC repeatedly identify parents, older siblings, and other household adults as the most common source, usually while those relatives are in their own catarrhal stage and believe they have a cold. This is the logic behind vaccinating during pregnancy, which allows protective antibodies to cross the placenta and cover the newborn’s first vulnerable weeks, and behind encouraging everyone who will be close to a newborn to be up to date on their own boosters. The timing of those vaccines follows national schedules and is a conversation for the prenatal and pediatric teams.
Hospital care for an infant with pertussis is mostly supportive: monitoring for apnea, oxygen if needed, gentle suction of secretions, help with feeding, and antibiotics decided by the treating team. Parents are usually encouraged to stay, hold, and feed their baby, because calm reduces the crying that can trigger fits. Recovery follows the same slow convalescent curve as in older children, often with more medical follow-up along the way.
Whooping cough symptoms in adults: the cough that gets dismissed
Adults are often surprised to learn they can catch pertussis at all. Protection from childhood vaccines and from past infection wanes over years, which is why adolescent and adult boosters exist. When an adult with faded immunity meets the bacteria, the whooping cough stages tend to blur into something that looks less like a childhood disease and more like a stubborn bronchitis.
The Mayo Clinic and the NHS describe adult pertussis as a prolonged, often dry cough, frequently worse at night, that may come in bursts but rarely produces the classic whoop. Post-cough vomiting and gagging are common. Fever is usually absent. Between fits the adult feels reasonably well, goes to work, and reassures colleagues that it is just a cold that will not leave. Weeks pass.
The physical complications in adults come from the cough’s mechanics rather than from the infection itself. The CDC lists rib fractures, urinary incontinence, fainting, sleep loss, and weight loss among the recognized effects of prolonged paroxysms in adults. None of these are signs of a worsening infection, but they are reasons a cough of more than three weeks deserves assessment rather than another bottle of lozenges.
The greater significance of adult pertussis is what it does to the people around the adult. An undiagnosed adult in the catarrhal or early paroxysmal stage is precisely the household member most likely to pass the infection to a newborn grandchild or an unvaccinated infant. That is why guidelines emphasize prompt evaluation of any prolonged cough in someone who lives with, cares for, or is about to visit a young baby, and why the treatment window is extended for pregnant women.
One practical point: adults frequently arrive at the doctor after three weeks of coughing, which is the point at which antibiotics stop being routinely recommended and diagnosis shifts to blood tests. The earlier a long cough is mentioned, the more options remain. The decision about testing and treatment rests with the clinician who examines the patient.
What gets mistaken for whooping cough, and what whooping cough gets mistaken for?
The confusion runs in both directions, and it is one of the most searched questions about this illness.
Pertussis is most often mistaken for a common cold, bronchitis, or a lingering post-viral cough, particularly in adults and adolescents where the whoop is absent. Asthma is another frequent alternative label, since both produce coughing fits at night. In infants, the early presentation of poor feeding and breathing pauses can be attributed to reflux or to a viral illness such as respiratory syncytial virus, which itself can cause apnea in young babies.
In the other direction, several conditions can produce a cough dramatic enough to make parents suspect pertussis. Croup, a viral infection of the voice box, causes a barking cough and a harsh, raspy inhale called stridor, which is easily confused with a whoop by someone who has never heard either. The differences matter: croup usually has a hoarse voice and a fever, and it typically resolves within days rather than weeks. Bronchiolitis, an infection of the small airways in babies, produces wheezing and fast breathing more than discrete fits. Adenovirus, mycoplasma, and other bacteria in the same family as Bordetella pertussis can produce pertussis-like coughs of shorter duration.
Distinguishing these is not a job for a checklist or a phone recording, though a video of a coughing fit can genuinely help a clinician who cannot witness one in the office. What tends to separate pertussis from its impostors is the pattern over time: a cough that intensifies rather than improves after the first week, comes in violent clusters with a well interval between them, ends in vomiting or a gasp, and shows no sign of leaving after two to three weeks. A clinician weighs that pattern alongside exposure history, vaccination status, and, when the timing allows, laboratory testing. The diagnosis is theirs to make.
How dangerous is whooping cough, and what does the evidence say about survival?
Fear does not help anyone manage this illness, so it is worth being precise about where the danger actually lies. For older children, adolescents, and adults, pertussis is exhausting, disruptive, and occasionally injurious, but it is very rarely life-threatening. The serious risk is concentrated almost entirely in infants.
The CDC’s complication data, drawn from national surveillance, gives the clearest picture. About one in three infants under one year who get pertussis need hospital care. Among those hospitalized infants, roughly two in three have apnea, about one in five develop pneumonia, around one in a hundred have seizures, and about one in a hundred die. Encephalopathy, meaning disease of the brain, occurs in approximately one in three hundred hospitalized infants. Pneumonia is the most common cause of death.
Those figures describe the hospitalized infant population, not the general population, and they should not be read as a personal prognosis for any child. Nor do they translate into a simple “survival rate” for whooping cough as a whole; for adolescents and adults, deaths are so uncommon that the CDC does not present a comparable figure, and complications such as rib fractures and fainting, while unpleasant, are not fatal.
Two facts temper the infant numbers. The first is that the youngest infants are protected by antibodies passed across the placenta when the mother is vaccinated during pregnancy, and by the cocoon of vaccinated adults and siblings around them. The second is that severe pertussis in infants is treatable with supportive hospital care, and the great majority of hospitalized babies recover fully.
The honest summary is this: pertussis in a healthy ten-year-old is a miserable two months; pertussis in a six-week-old is a medical emergency. The timing of the stages matters most because the interventions that protect that six-week-old, treating the coughing adult early and treating exposed household members, must happen in the first weeks, long before anyone hears a whoop.
What do the following weeks usually look like at home?
Most pertussis is managed at home, and families frequently say the hardest part is not any single symptom but the length of the road. Knowing what the weeks typically contain makes them easier to walk.
Week one to two after diagnosis, if antibiotics have been prescribed, is usually spent completing them exactly as directed and staying out of school or work until the clinician’s advice allows a return; the NHS gives 48 hours after starting treatment as the usual point. The cough will not improve noticeably during this time, and that is expected. Nights are often the worst. Many parents sleep in the same room so they can sit a child up during a fit, which tends to shorten it.
Comfort measures are simple and rest on guidance from the NHS and the Mayo Clinic rather than on any product. Small, frequent meals and drinks are easier to keep down than large ones, and offering them after a fit rather than before reduces vomiting. A cool, clean, smoke-free room with the air kept free of dust, strong fragrances, and fireplace smoke removes common triggers. A cool-mist humidifier may loosen secretions for some people; if used, it needs daily cleaning. Cough medicines are not recommended for young children and have no proven benefit in pertussis.
Weeks three to six are typically the plateau: fits at a steady frequency, then a slow decline. This is when exhaustion sets in for caregivers, and when it is reasonable to ask relatives for practical help so that whoever is doing the night shifts can sleep during the day.
From around week six onward, most people enter the convalescent stage. Fits become rarer and milder. The first cold to come along may briefly bring them back, which is normal. Follow-up with the pediatric or primary care team is usually arranged for infants and for anyone whose course is not following this pattern, and any concern about breathing, feeding, or color always overrides the schedule.
What people often get wrong about the whooping cough stages
Myths about pertussis are durable partly because the disease itself behaves counterintuitively. Correcting a few of them changes decisions.
“No whoop, no whooping cough.” The whoop is absent in most adults, many adolescents, and many infants. The NHS and the Mayo Clinic both make this point. A prolonged cough in bursts, with or without the sound, is what should prompt assessment.
“Antibiotics will stop the cough.” They will not, once the fits are established. Their late-stage value is in stopping spread. Expecting the cough to vanish after a course of antibiotics sets families up for disappointment and, worse, for doubting a correct diagnosis.
“If the cough keeps going, the infection is still there.” By week three or four the bacteria have usually gone. The cough persists because the airway lining is still repairing itself. A rebound during a new cold is the healing airway overreacting, not the pertussis returning.
“Vaccinated children cannot get it.” Vaccination greatly reduces the risk and the severity, but protection fades over years, which is why boosters exist. A vaccinated child with pertussis usually has a milder, shorter illness, and that milder illness can still spread to an infant.
“Once you have had it, you are immune for life.” Immunity from infection also wanes. Adults who had pertussis in childhood can catch it again decades later.
“It is only dangerous if the child has a fever.” Pertussis characteristically causes little or no fever, even when severe. In infants, the danger signs are breathing pauses, color change, and feeding failure, not temperature.
“Cough syrup will help a child sleep through it.” Guidelines advise against cough and cold medicines in young children, and no over-the-counter product has been shown to help pertussis. Positioning, small feeds, and a clean, cool room are what the evidence supports.
Questions to ask your care team
A consultation about a prolonged cough moves quickly, and the questions that matter most are easy to forget in the room. These are the ones families and adult patients most often wish they had asked, phrased so the answers come from the clinician rather than from the internet.
- Based on when the cough started, which stage do you think we are in, and how does that affect what you can offer?
- Is testing worthwhile at this point, and which test are you using? If it comes back negative, will that change the diagnosis?
- Am I, or is my child, still within the window where antibiotics are recommended? If not, what is the reasoning?
- Who else in the household or in regular contact should be assessed or offered preventive antibiotics, and by when?
- Is there a baby, a pregnant person, or someone with a weakened immune system in our circle who needs to be kept away, and for how long?
- When can school, nursery, or work resume, and does that date depend on treatment?
- What should a coughing fit look like at home, and what specifically would make you want to see us again the same day?
- For an infant: what signs of breathing trouble or feeding difficulty should send us straight to emergency care rather than to your office?
- Are our vaccinations, including adult and adolescent boosters and any recommended during pregnancy, up to date, and where in the schedule does everyone stand?
- How long should we expect the cough to last, and at what point would a persisting cough concern you?
- Is there any follow-up appointment planned, or is it up to us to make contact?
Writing the answers down, or asking permission to record the conversation, is entirely reasonable. Bringing a short video of a coughing fit is often more informative than any description. The decisions about testing, treatment, isolation, and follow-up belong to the treating team, who can weigh the individual circumstances that no article can see.
When to call your doctor, and when to call emergency services
Most people with pertussis do not need emergency care, but the exceptions are serious and are concentrated in the youngest patients. The following signs, drawn from NHS and CDC guidance, are the ones that should override waiting for a scheduled appointment.
Call emergency services, or go to the nearest emergency department, if a baby or child:
- Stops breathing, has pauses in breathing, or their breathing becomes very shallow or labored between coughs.
- Turns blue, gray, or very pale around the lips, tongue, or face during or after a fit, or the color does not return promptly afterward.
- Has a seizure, becomes unusually floppy, or is difficult to rouse.
- Is under six months old and has coughing fits, or is any age and cannot catch their breath after a fit.
- Is unable to feed or drink, or shows signs of dehydration such as no wet diapers for many hours, a dry mouth, or a sunken soft spot on the head.
Contact your doctor promptly, the same day where possible, if:
- Anyone in the household has a cough that has lasted more than two to three weeks or is coming in violent bursts, particularly if there is a baby or a pregnant person at home.
- A child or adult is vomiting after coughing, losing weight, or becoming exhausted from lack of sleep.
- Chest pain, a fever that develops later in the illness, or thick discolored sputum appear, which can suggest pneumonia.
- An adult faints during fits, notices rib pain, or develops urinary leakage with coughing.
- Anyone at home has been in contact with a confirmed case, so that preventive treatment can be considered within the recommended window.
When in doubt, call. Clinicians would much rather assess a cough that turns out to be a cold than miss pertussis in a household with a newborn. And if a coughing fit is happening in front of you and the person is struggling for breath, that is the moment for emergency services, not for a phone search.
Frequently asked questions
How quickly does whooping cough progress from a cold to coughing fits?
Usually within one to two weeks of the first cold-like symptoms, according to CDC clinical guidance. Because the incubation period before any symptom is typically 5–10 days and can be as long as 21, the full span from exposure to the first violent coughing fit can range from about ten days to five weeks. Infants may progress faster and skip the cold-like phase almost entirely.
How long is whooping cough contagious?
From the very first cold-like symptoms until about three weeks after the coughing fits begin, if untreated. Starting an appropriate antibiotic shortens this to five days after the first dose, according to the CDC. Because the most contagious period overlaps with the phase that looks like a common cold, most transmission happens before anyone realizes the illness is pertussis. Return to school or work follows the treating clinician’s advice.
What gets mistaken for whooping cough?
Croup is the most common impostor, because its barking cough and harsh inhale can sound like a whoop; croup usually comes with hoarseness and fever and resolves in days. Bronchiolitis, asthma, other bacteria in the same family, and viral coughs are also confused with it. In the other direction, pertussis itself is often mislabeled as bronchitis or a lingering cold in adults. A clinician separates these by pattern over time, exposure history, and testing.
Is whooping cough going around right now?
Pertussis circulates continuously and rises in cycles roughly every three to five years, according to the CDC, so there is nearly always some activity somewhere. Whether it is currently elevated in a particular community is a question for the local or state health department, which publishes case counts. A prolonged cough in a household with an infant deserves assessment regardless of what the local numbers show.
What is the survival rate of whooping cough?
For older children, adolescents, and adults, death from pertussis is extremely rare and the CDC does not publish a general survival figure. The serious risk is in infants: about one in three under one year need hospital care, and among those hospitalized roughly one in a hundred die, most often from pneumonia. These are population figures from CDC surveillance, not a prognosis for any individual child.
Why do antibiotics not stop the cough once whooping cough has started?
Because the cough is caused by toxins that have already damaged the airway lining, not by the live bacteria. Antibiotics kill the bacteria, which reduces spread to others, but the injured cilia take weeks to regrow regardless. The Mayo Clinic and CDC both note that antibiotics started after coughing fits are established rarely shorten the illness. Whether to prescribe them at that point is the clinician’s decision, based mainly on protecting contacts.
What does whooping cough look like in babies who never whoop?
In infants, especially under six months, pertussis may show as pauses in breathing, a blue or gray tinge around the lips, gagging, or difficulty feeding, with little or no cough. The NHS lists breathing pauses and color change as reasons for emergency care. Because babies are usually infected by a coughing parent or sibling in the cold-like stage, any prolonged cough in a household with a newborn should be assessed promptly.
What are the whooping cough symptoms in adults?
A prolonged, often dry cough in bursts, frequently worse at night, sometimes ending in gagging or vomiting, and usually without fever or a whoop. Between fits adults often feel well. Complications from the force of coughing include rib fractures, fainting, urinary leakage, and weight loss, according to the CDC. A cough lasting more than two to three weeks deserves assessment, particularly if an infant or pregnant person is at home.
Can you get whooping cough if you were vaccinated?
Yes, although it is less likely and usually milder. Protection from both vaccination and past infection fades over years, which is why adolescent and adult boosters are part of national schedules. A vaccinated person who catches pertussis typically has a shorter, less severe illness but can still transmit it to an unprotected infant. Questions about which boosters someone is due for belong with their primary care or prenatal team.
How long does the cough last after whooping cough?
Often for weeks to months after the fits fade. The NHS notes that the cough can persist for three months or more, well after the person has stopped being contagious. During this convalescent stage a new viral cold can temporarily bring the fits back, which reflects a still-healing airway rather than a return of the infection. A cough that worsens, produces discolored sputum, or comes with fever should be reviewed by a doctor.
References
- CDC: Clinical Features of Pertussis
- CDC: About Whooping Cough
- NHS: Whooping cough
- MedlinePlus: Whooping Cough
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Pediatric Movement Disorders Are Diagnosed: Examination, History and When Imaging Is Added
Movement disorders in children are diagnosed mainly through a detailed history and a hands-on neurological examination, often supported by home video of the movements.…

How Does Early-Onset Differ From Late-Onset Neonatal Sepsis? Care Planning in the NICU
Early-onset neonatal sepsis appears within the first 72 hours of life (some definitions extend to 7 days) and comes from bacteria passed from the…

Traveling With Whooping Cough: Why Flying Waits Until Treatment and Isolation Are Complete
Flying with whooping cough is generally discouraged for as long as a person is contagious. Public health guidance treats someone as infectious from the…

Fifth Disease, Roseola and Other Childhood Rashes: A Parent’s Identification Guide
Roseola is a common viral infection of infants and toddlers that causes three to five days of high fever followed, as the fever breaks,…

What Does an Early Intervention Therapy Session for Infants Involve? Floor Play and Team Roles
An early intervention therapy session for an infant usually happens at home, on the floor, and lasts about as long as the baby can…

How Are Goals Set in Pediatric Physical Therapy for Cerebral Palsy and Developmental Delay?
Goals in pediatric physical therapy for cerebral palsy and developmental delay are set together by the therapist, the family and, when possible, the child,…