

How Eye Injections for Wet Macular Degeneration Are Given and How the Schedule Is Set
Key Takeaways
- Anti-VEGF injections work by binding vascular endothelial growth factor, the messenger that makes abnormal vessels under the macula grow and leak; they target the leak, not the aged retina itself.
- The medicine is placed through the white of the eye into the vitreous gel after numbing drops and antiseptic; the injection itself takes seconds and most people describe pressure rather than pain.
- Treatment usually opens with a loading phase of roughly monthly injections over the first few months, after which intervals are individualized, typically within about one to three months according to the NHS.
- Treat-and-extend schedules lengthen the gap when the OCT scan shows a dry retina and shorten it when fluid returns, aiming to stay one step ahead of the wearing-off of the drug.
- The commonest after-effects are grittiness, watering, floaters and a red patch on the white of the eye that fades like a bruise; worsening pain, spreading redness or falling vision in the following days are emergencies.
- Long-term studies link most vision loss during treatment to stretched or missed intervals rather than to the medicine failing, which is why keeping appointments matters as much as the injection itself.
Eye injections for wet macular degeneration place an anti-VEGF medicine into the jelly of the eye, where it blocks the growth signal that makes abnormal vessels leak under the macula. Numbing drops and antiseptic come first; the injection itself takes seconds. Doctors usually begin with a run of monthly treatments, then set later intervals based on repeat retinal scans, extending when the retina stays dry and shortening when fluid returns.
The letter arrived on a Tuesday, and Ruth read it twice at the kitchen table: a wet macular degeneration diagnosis, a first injection booked, and a line about “ongoing treatment” that told her everything and nothing. She wanted to know three things before that appointment. Does a needle in the eye hurt? How often does it happen? And who decides?
Those are the right questions, and this guide answers them in order. Understanding how eye injections for macular degeneration work, from the drop that numbs the surface to the scan that sets your next date, takes most of the dread out of a treatment that many people go on to describe as a routine, if never quite pleasant, part of their calendar.
Along the way we correct the myths that circulate in waiting rooms and family group chats, and we are honest about what the evidence can and cannot promise. Every decision about your own eyes stays with the team looking after them.
Why a leaking blood vessel changes everything: wet AMD explained
The macula is the small central patch of the retina, roughly the size of a pencil eraser, that lets you read a bus number, thread a needle or recognize a face across a room. Age-related macular degeneration (AMD) is a slow wearing-down of that patch, and it is the leading cause of central vision loss in adults over 50 in high-income countries, according to the National Eye Institute (NEI).
There are two forms, and the distinction matters for treatment. In dry AMD, waste deposits called drusen build up beneath the retina and light-sensing cells thin out over years. In wet AMD, fragile new blood vessels sprout from the layer beneath the retina, grow where they do not belong and leak fluid or blood. That leak lifts and distorts the macula, which is why straight door frames can suddenly look bent and why words on a page seem to have a hole in the middle.
Dry AMD is far more common, but the wet form accounts for a disproportionate share of severe vision loss, and it can move quickly, over weeks rather than years (NEI; NHS). That speed is the reason wet AMD is treated as a priority in eye clinics and the reason the injections exist at all.
Here is the idea worth holding onto: the injections do not rebuild a worn macula. They target the leak. Fluid that sits under the retina damages cells the longer it stays, so the whole logic of treatment, and of the schedule you will read about later, is to keep the retina as dry as possible for as long as possible. Everything else, from the frequency of visits to the scans you will have at each one, follows from that single aim.
How eye injections for macular degeneration work, in plain language
The abnormal vessels in wet AMD grow because the retina, short of oxygen and nutrients, releases a chemical messenger called vascular endothelial growth factor, or VEGF. VEGF is normally useful; it tells the body to build new blood supply after injury. In the ageing macula the signal misfires, and the vessels it produces are leaky and disorganized.
Anti-VEGF medicines are antibodies or antibody-like proteins engineered to bind to VEGF and stop it reaching the receptors on vessel walls. With the signal blocked, the abnormal vessels stop growing, leak less and often shrink back. Fluid that has pooled under the macula can be reabsorbed, and the retina settles closer to its normal shape (Mayo Clinic; NHS).
The medicine has to reach the back of the eye, and eye drops cannot get there in useful amounts. So it is placed directly into the vitreous, the clear gel that fills the eyeball. The technical term is an intravitreal injection: intra meaning into, vitreal meaning the gel. From there the drug diffuses backward to the retina and is gradually cleared by the eye over weeks. Because the medicine is broken down and washed out, its effect fades, VEGF activity rises again, and the vessels may resume leaking. That wearing-off is the physiological reason treatment repeats rather than a sign that anything has gone wrong.
Several anti-VEGF agents are in use. They differ in molecular design and in how long their effect tends to last, which is one of the variables your retina specialist weighs when planning intervals. Which agent you receive is a clinical judgment made by the treating team based on your scans, your other health conditions and local guidance; nothing about that choice belongs in a magazine article, and you should treat any source that tells you otherwise with caution.
What actually happens in the injection chair, step by step
Most people are surprised by how brief the procedure is. The visit takes longer than the injection, largely because of checks and scans on either side of it.
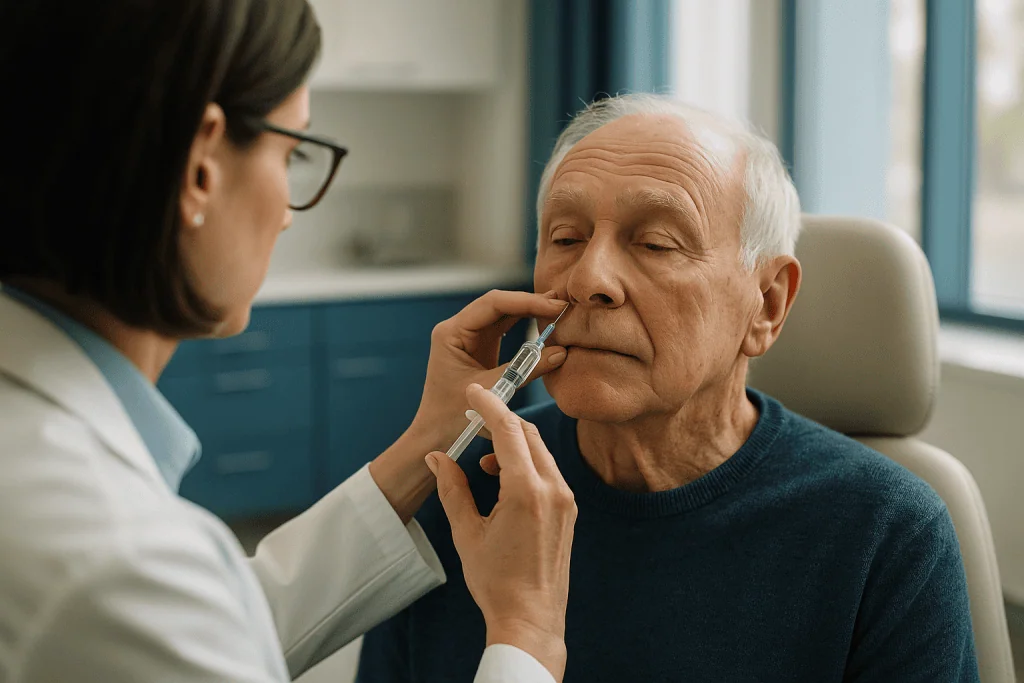
You sit in a reclining chair or lie back. A nurse or technician checks your vision and often measures eye pressure. Anesthetic drops numb the surface of the eye; some clinics add a small gel or a tiny injection of numbing medicine under the outer membrane for people who find drops alone insufficient. An antiseptic, usually a dilute iodine solution, is applied to the eye and eyelids to reduce the risk of infection, and a small speculum holds the lids open so you cannot blink at the wrong moment (Cleveland Clinic; NHS).
The doctor marks a spot on the white of the eye, a few millimeters from the edge of the colored iris and well away from the lens and retina. You are asked to look in a particular direction, generally away from the needle. The injection itself takes a few seconds. Most people describe pressure rather than sharp pain, and many say the antiseptic sting afterward is the most memorable sensation of the whole appointment.
Immediately afterward, the doctor may check that you can see hand movements or count fingers, confirming that blood flow to the optic nerve is fine. The speculum comes out, the eye may be rinsed, and you can usually leave within minutes. Some clinics prescribe antibiotic drops for a few days; others, following more recent evidence, do not. Follow whatever your own team advises.
Two practical points: bring sunglasses, because your pupil may have been dilated for scans and the antiseptic leaves the eye sensitive; and arrange a lift or public transport for the first visit, since you will not know how your vision reacts until you have been through it once.
Who is usually offered injections, and who is usually asked to wait
Anti-VEGF injections are the standard first-line treatment for active wet AMD, meaning there is evidence on imaging of new vessel growth or fluid under or within the retina (NHS; Mayo Clinic). Age itself is not a barrier; many people in their eighties and nineties are treated, because the alternative is progressive loss of central sight.

Guideline-level practice, including NHS and NICE guidance in the United Kingdom, generally recommends starting treatment promptly once wet AMD is confirmed, because delay allows more fluid-related damage. This is why a referral for suspected wet AMD is usually classed as urgent and why a first injection is often given within days of the scan.
Who is asked to wait, or offered something else? Broadly, three groups:
- People with dry AMD. Anti-VEGF injections have no role here because there is no VEGF-driven leak to block. Care centers on monitoring, lifestyle measures and, for some with intermediate disease, specific antioxidant supplement formulas studied in NIH trials. Newer injectable treatments for advanced dry AMD (geographic atrophy, where patches of retina die away) exist in some countries, but they work through a different pathway, aim to slow expansion rather than restore sight, and are a separate decision entirely (NEI).
- People whose wet AMD is inactive or already scarred. If the vessels have burned out and left a fibrous scar with no fluid, injections cannot recover the lost cells, and a specialist may recommend observation instead.
- People with an active eye infection, or very recent eye surgery, where injecting would carry extra risk until the eye has settled.
Photodynamic therapy, a laser-plus-light-sensitive-dye technique that predates anti-VEGF drugs, is now used only in specific situations, sometimes alongside injections (Mayo Clinic). Which pathway fits your eye is a judgment for the retina specialist who has your scans in front of them.
How the anti-VEGF injection schedule is set: the loading phase and what comes next
The first stretch of treatment is the most predictable. Most specialists begin with a loading phase: a series of injections given at roughly monthly intervals over the first few months, regardless of how quickly the eye seems to respond (NHS; Mayo Clinic). The purpose is to get the leak fully under control and drain existing fluid before anyone tries to stretch the gaps.
After that, the calendar becomes individual. Your specialist is weighing several things at every visit:
- Whether the retinal scan shows fluid, and if so, how much and where.
- Whether your measured vision has held steady, improved or slipped since the last check.
- Whether there is fresh bleeding or new vessel growth.
- How long the medicine’s effect has lasted in your eye in previous cycles.
- Practical realities: your ability to travel, other health conditions, and whether the second eye also needs treatment.
The NHS describes ongoing treatment as typically continuing at intervals of about one to three months, extended or shortened according to response. Some people settle at the longer end of that range for years; others need closer follow-up. Neither pattern is a failure. It reflects how active the disease is in that particular eye and how long a given drug’s effect persists in that particular person.
What you should not expect is a fixed number of treatments with a finish line. Wet AMD is a chronic condition, and most people remain under some form of ongoing review even when injections become infrequent. Stopping altogether is possible when the disease has been quiet for a long time, but it is a decision made cautiously and with a plan for rapid re-access if symptoms return. If you are ever unsure why your next appointment is sooner or later than the last, ask; a good team will show you the scan and explain what changed.
Treat and extend, fixed monthly or as needed: the three schedule styles compared
Three broad approaches to timing have been studied and are in everyday use. Clinics often blend them, and the labels matter less than understanding the trade-offs your doctor is balancing.
| Approach | How the interval is decided | Main advantage | Main drawback |
|---|---|---|---|
| Fixed monthly (or fixed interval) | Injection at every visit, on a set cycle, regardless of scan findings | Retina rarely gets the chance to become wet; simple to plan | Most visits and injections; some are given to eyes that may not have needed one that month |
| As needed (PRN) | Monthly scan; inject only if fluid, bleeding or vision loss is found | Fewest injections | Just as many visits; treats after the leak has reappeared rather than before, and evidence suggests vision can drift down over time if fluid is repeatedly allowed back |
| Treat and extend | Inject at every visit; if the retina is dry, lengthen the gap to the next visit by a set step; if fluid returns, shorten it | Fewer visits than monthly, aims to treat before fluid recurs, learns each eye’s own rhythm | Requires careful record-keeping and some trial and error to find the right interval |
Treat and extend macular degeneration protocols have become the most widely adopted model in many health systems because they try to stay one step ahead of the leak while sparing people unnecessary trips (Mayo Clinic). The logic is that each eye has a characteristic interval after which VEGF activity outpaces the fading drug, and the goal is to find that interval and then sit just inside it.
None of this is a menu you choose from. It is a framework your specialist applies, and it may shift over time as newer, longer-acting agents change what is possible.
What the scan is telling your doctor, and why fluid drives the calendar
At most visits you will have an optical coherence tomography scan, usually shortened to OCT. It is a painless imaging test that uses light waves to build a cross-section of the retina, layer by layer, in a few seconds. You rest your chin on a support, look at a target, and the machine does the rest. No dye, no injection, no contact with the eye.
The OCT is the workhorse of wet AMD management because it shows the thing the injections are meant to control: fluid. On the image, fluid appears as dark pockets, either under the retina, within its layers, or beneath the pigment layer at the base. Your doctor is looking at whether those pockets are present, how large they are compared with the last scan, and whether the overall retinal thickness has risen or fallen (Cleveland Clinic; Mayo Clinic).
Vision testing matters too, but it lags. You may see well while a small amount of fluid has crept back, or see poorly for a while after fluid has cleared because the retina takes time to recover. The scan detects change earlier and more objectively than a letter chart, which is why it, rather than how you feel your eye is doing, usually drives the decision to extend or shorten the interval.
At the first visit, and sometimes later, you may also have a fluorescein angiogram, in which a yellow dye is injected into an arm vein and photographs track it through the retinal vessels to show exactly where the leak is. Some clinics now use OCT angiography, a dye-free alternative, for the same purpose.
A useful habit: ask to see your scan. Watching the dark pocket shrink from one visit to the next makes the point of the injections concrete, and understanding why an interval was shortened keeps a minor setback from feeling like a catastrophe.
What the first day and first week after an injection usually look like
The commonest question after a first injection is some version of “is this normal?” For the great majority of people, the answer is yes, and the pattern is predictable.
In the first few hours the eye typically feels gritty, watery and light-sensitive, mainly from the antiseptic and the speculum rather than the needle. Vision is often blurry, partly from dilating drops and partly from a little medicine floating in the gel; some people notice small dark specks or a swirl that drifts across their sight for a day or so. A red patch on the white of the eye is common and is a small surface bleed where the needle passed through; it looks alarming and is painless, and it fades over one to two weeks like any bruise (NHS; Mayo Clinic).
By the next morning most people report the grittiness has largely settled. Mild aching that responds to a simple over-the-counter pain reliever, if your team has said that is fine for you, can last a day or two. Vision usually returns to its pre-injection baseline within a day, though it may take several weeks to see any improvement from fluid clearing, and for many people the realistic goal is stability rather than a dramatic gain.
Through the first week you can generally read, watch television and walk as normal. Driving is a matter of whether your vision meets the legal standard on that day; most people avoid it for the rest of injection day at least.
What changes over the longer run is familiarity. People who have been through several cycles tend to describe injection day as an inconvenience rather than an ordeal, and many return to normal activities the same afternoon. The recovery is, in most cases, measured in hours, not days.
What not to do after an eye injection for macular degeneration
Aftercare advice is simple, and it is aimed almost entirely at one risk: infection getting into the eye through the tiny needle track before it seals. Follow your own clinic’s written instructions if they differ from the general points here.
In the first few days, most teams advise against:
- Rubbing or pressing on the treated eye. The grittiness tempts you; blink or use lubricating drops instead if your team has approved them.
- Swimming, hot tubs and saunas, which expose the eye to water that is not sterile.
- Eye makeup, false lashes or anything applied close to the lid margin.
- Dusty or dirty environments, such as heavy gardening, sanding or mucking out animals, without eye protection.
- Getting soap, shampoo or shower water directly into the eye; showering with eyes closed is fine.
You do not need to lie flat, keep your head still or avoid bending, and there is no need to stop reading or using screens. Air travel is not restricted by the injection itself, though most people prefer not to fly on the same day simply because their vision is blurred.
Continue your usual medicines, including blood thinners, unless your own doctor has told you otherwise. Anti-VEGF injections are routinely given to people taking anticoagulants, and stopping them without advice carries far more risk than the small surface bleed the needle may cause.
One further point, easily overlooked: do not skip the next appointment because the eye feels fine. Feeling fine is not a reliable guide to whether fluid has returned, and the wearing-off of anti-VEGF medicines is the reason the schedule exists. If you cannot make a date, ring the clinic to rearrange rather than letting the interval stretch by default. Long unplanned gaps are one of the most common reasons that a well-controlled eye loses ground (NEI; NHS).
Wet AMD injection side effects: the common, the uncommon and the serious
Every honest explainer separates what usually happens from what rarely happens, because the two are easily confused in the anxious first weeks.
Common and expected: surface irritation, watering, light sensitivity, a red patch on the white of the eye, floaters for a day, mild ache and temporary blurring. These are effects of the procedure rather than the medicine, they resolve on their own and they are not a reason to change the plan (Mayo Clinic; NHS).
Uncommon: a temporary rise in eye pressure just after injection, usually monitored and short-lived; inflammation inside the eye, which causes aching, redness and blur over a few days and is treated with anti-inflammatory drops; a small tear or bleed in the retina; and cataract formation being hastened if the lens is nudged, which is rare with modern technique.
Serious but rare: endophthalmitis, an infection inside the eyeball. It is the complication the antiseptic and speculum are designed to prevent, and mainstream sources describe it as rare per injection. When it does occur it develops over one to several days and is an emergency, which is why the red-flag list later in this article matters. Retinal detachment, where the retina peels away from its supporting layer, is another rare emergency with its own warning signs (Cleveland Clinic).
A question people ask quietly is whether a medicine that blocks blood-vessel growth could affect the heart or brain. The amount that escapes the eye into the bloodstream is tiny, and large trials have not shown a clear excess of heart attack or stroke overall, though specialists take extra care in people with a recent stroke and will weigh that history when choosing an agent. Tell your team about any cardiovascular event, past or new.
Risk is cumulative in the sense that each injection carries its own small chance; it does not build up in the tissue. That is one reason treat-and-extend approaches try to use no more injections than the eye needs.
How eye injections for macular degeneration work over years: durability and missed visits
Because wet AMD is chronic, the more useful question is not whether the injections work at the start but what happens across a decade. Here the evidence is sobering in places and encouraging in others.
In trials and real-world audits, anti-VEGF treatment reliably reduces fluid and, in a large proportion of eyes, stabilizes vision; a smaller share gain lines on the chart, and a minority continue to lose sight despite treatment, often because scarring or dry-type cell loss is progressing underneath the wet disease (NHS; Mayo Clinic). Long-term registry studies suggest that gains achieved in the first year tend to erode gradually over subsequent years, and the single strongest predictor of that erosion is under-treatment: intervals that stretched, visits that were missed, fluid left sitting.
That is why specialists talk about adherence with such conviction. The medicine does not stop working in a biological sense; it wears off on a timetable, and if the next dose arrives late, vessels leak in the gap. Eyes treated on schedule tend to hold their vision better than eyes treated erratically. Where a person genuinely cannot attend as often as ideal, a longer-acting agent or a modified schedule may be discussed, and that is a conversation to have openly rather than by quietly cancelling appointments.
Some people do develop a plateau where an agent seems to hold fluid less well than before. Switching to a different anti-VEGF medicine is a recognized option in that situation, and newer agents with longer durability have widened intervals for many people. None of this is a personal choice; it belongs to the specialist reading your scans.
Finally, the second eye. Having wet AMD in one eye raises the risk in the other, so most clinics scan both at each visit and ask you to monitor the untreated eye at home. Catching a new leak early in the fellow eye is one of the clearest wins in the whole field.
What people often get wrong about wet AMD injections
Waiting-room folklore is persistent, and some of it does real harm. These are the misunderstandings retina teams hear most often.
“The needle goes into the center of the eye.” It enters through the white of the eye at the side, well clear of the iris, lens and central retina. You are looking away from it, and the numbed surface means most people feel pressure rather than pain.
“If my vision is not better after the first injection, it has failed.” Fluid clears over weeks, and the aim for many people is to stop further loss rather than to restore sight already gone. Response is judged on scans over the loading phase, not on how the first day felt.
“Once the eye is dry, I can stop.” Dryness on a scan is the medicine doing its job; it is not evidence that the underlying disease has switched off. Stopping is possible in some long-quiet eyes, but only as a planned decision with a safety net for prompt return (NHS).
“The injections will make me go blind.” Serious complications are rare, and the untreated disease is far more likely to cost central vision than the treatment is. Even in advanced AMD, peripheral vision is generally preserved, so complete blindness is uncommon (NEI).
“A supplement can replace the injections.” The antioxidant formulas studied in NIH trials were tested in intermediate dry AMD to slow progression; they do not treat an active leak and are not a substitute for anti-VEGF treatment.
“Newer means I should ask to switch.” Longer-acting agents help some people, but the choice depends on your scans, your history and local guidance. Ask about options, and let the specialist decide.
“Blood thinners must be stopped before each injection.” They are not routinely stopped. Never alter prescribed medicines without your own doctor’s advice.
Questions to ask your care team
A first retina appointment moves fast. Writing questions down beforehand, and bringing someone to listen with you, makes the difference between leaving reassured and leaving with a leaflet you cannot read because your pupils are dilated. Consider asking:
- Is the wet AMD active now, and does the scan show fluid under, within or beneath the retina?
- What is the aim of treatment for my eye: stabilizing vision, improving it, or protecting what remains?
- Which schedule approach do you use, and what will decide whether my interval is extended or shortened?
- Roughly how many visits should I expect in the first few months, so that I can plan transport and time off?
- Will I have a scan at every visit, and can I see it?
- How will I know if the medicine is wearing off between visits, and what should I do if I notice a change?
- What symptoms after an injection mean I should call the same day, and which number do I ring out of hours?
- Do you want me to use any drops afterward, and for how long?
- Should I keep taking all my usual medicines, including blood thinners?
- How is my other eye, and how should I monitor it at home?
- Am I safe to drive, and how will that be reassessed over time?
- Would low-vision services, magnifiers or a certification of sight impairment help me now, regardless of how treatment goes?
- If I struggle to attend as often as recommended, are there options we should discuss rather than missing appointments?
The answers will be specific to your eye, and they may change over time. What should not change is the willingness of the team to explain. If a clinic cannot tell you why your next appointment is when it is, ask again, politely, until someone can.
When to call your doctor
Most sensations after an injection are harmless and fade within a day or two. A small number are not, and because the serious complications are time-critical, the rule is simple: if you are unsure, call the clinic or the emergency number you were given rather than waiting for the next scheduled visit.
Contact your eye team the same day, or attend an emergency department if you cannot reach them, for any of the following after an injection (NHS; Mayo Clinic; Cleveland Clinic):
- Pain that is worsening rather than easing, especially a deep ache that develops from the day after treatment onward.
- Increasing redness of the eye, particularly if it is spreading and the eye feels tender.
- Vision that is getting worse after initially settling, or a sudden drop in sight.
- A sudden shower of new floaters, flashes of light, or a dark curtain or shadow moving across part of your vision, which can signal retinal detachment.
- Marked sensitivity to light together with pain or blur.
- Discharge or pus from the eye, or a swollen, sticky lid.
Between appointments, and for the untreated eye at all times, call promptly if you notice new distortion, with straight lines appearing wavy, a new blank or blurred patch in the center of your vision, or a noticeable change on the Amsler grid or reading test your team has given you. New leaks respond best when treated early, and a missed early signal is far more costly than an unnecessary phone call.
None of this replaces the individual advice you receive. Keep the clinic’s contact details somewhere you can find them with blurred vision, tell whoever lives with you what the warning signs are, and treat any of the symptoms above as urgent regardless of the hour.
Frequently asked questions
What is the success rate of eye injections for macular degeneration?
Mainstream sources such as the NHS and Mayo Clinic describe anti-VEGF injections as stabilizing vision in most treated eyes and improving it in a smaller share, while a minority continue to lose sight despite treatment. Exact percentages vary widely between trials and real-world audits and depend on how early treatment starts and how consistently intervals are kept, so a single figure would be misleading. Your specialist can tell you what your own scans suggest.
How long does it take to recover from macular degeneration injections?
Most people feel largely back to normal within a day. Grittiness, watering and blur typically ease over a few hours, a red patch on the white of the eye can take one to two weeks to fade, and any improvement in vision from fluid clearing may take several weeks to show. There is no lying flat or extended time off; the main precautions are avoiding rubbing the eye and non-sterile water for a few days.
What not to do after an eye injection for macular degeneration?
For the first few days, avoid rubbing the eye, swimming, hot tubs, eye makeup and dusty work without protection, all to reduce the small chance of infection through the needle track. You do not need to stop reading, screens, bending or your usual medicines, including blood thinners, unless your own doctor says so. The most important thing not to do is skip the next appointment because the eye feels fine.
How many years does it take to go blind with dry macular degeneration?
Dry AMD usually progresses slowly, over many years, and most people never lose all their sight because peripheral vision is generally preserved even in advanced disease, according to the National Eye Institute. Some people stay at an early stage indefinitely; others develop geographic atrophy, where central vision fades gradually over years. The bigger risk is conversion to wet AMD, which can move over weeks, so regular monitoring and prompt reporting of new distortion matter.
What is a typical anti-VEGF injection schedule for wet AMD?
Treatment commonly begins with a loading phase of roughly monthly injections over the first few months, then continues at individualized intervals that the NHS describes as typically about one to three months. The interval is set by the retina specialist at each visit based on the OCT scan and your vision, extended when the retina stays dry and shortened if fluid returns. The schedule is a clinical judgment, not a fixed course with a finish line.
What does treat and extend mean in macular degeneration treatment?
Treat and extend is a scheduling approach in which you receive an injection at every visit and the gap to the next visit is lengthened by a set step if the scan shows a dry retina, or shortened if fluid has reappeared. The aim is to find the longest interval at which your eye stays dry and treat just before the medicine wears off, using fewer visits than fixed monthly injections while avoiding repeated leaks.
What are the common wet AMD injection side effects?
The usual after-effects are surface irritation, watering, light sensitivity, temporary blur, floaters for a day and a painless red patch on the white of the eye. Less common are a short rise in eye pressure or inflammation inside the eye treated with drops. Serious complications, including infection inside the eye and retinal detachment, are rare but urgent, which is why worsening pain, spreading redness or falling vision after an injection should be reported the same day.
Do eye injections for macular degeneration hurt?
Most people report pressure or a brief sting rather than sharp pain, because anesthetic drops or gel numb the surface first and the needle enters the white of the eye while you look away. The antiseptic used to prevent infection often causes more discomfort afterward than the injection itself, leaving the eye gritty and watery for a few hours. Tell your team if numbing felt inadequate; other anesthetic options exist.
Can wet macular degeneration injections ever be stopped?
Sometimes, but cautiously. In eyes that have stayed dry on scans for a long period, a specialist may extend intervals to the point of monitoring without injecting, with a plan for prompt re-treatment if fluid or symptoms return. Wet AMD is a chronic condition and the underlying tendency to leak does not disappear, so stopping is a planned clinical decision rather than something to do because the eye feels fine.
Why do the injections need to be repeated?
Anti-VEGF medicines are gradually broken down and cleared from the eye over weeks, and as the drug level falls, VEGF activity rises and the abnormal vessels can begin leaking again. Repetition is built into how the treatment works rather than a sign it is failing. Newer, longer-acting agents have lengthened intervals for many people, but nearly everyone with active wet AMD remains under ongoing review with periodic injections.
References
- National Eye Institute (NIH): Age-Related Macular Degeneration (AMD)
- Cleveland Clinic: Macular Degeneration
- MedlinePlus: Macular Degeneration
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Can Laser Eye Surgery Correct Farsightedness? What Makes Someone a Candidate
Yes. Laser eye surgery, including LASIK and surface procedures such as PRK, can correct mild to moderate farsightedness (hyperopia) by steepening the central cornea…

Warm Compresses, Injection or Minor Surgery: How Chalazion Treatment Steps Up
Chalazion treatment usually begins with warm compresses and gentle eyelid cleaning for several weeks, because most of these blocked-gland lumps soften and drain on…

Eye Surgery Prep Checklist: Medication Lists, Allergies, Fasting Rules and the Drop Plan
To prepare for eye surgery, bring your care team a complete written list of every medicine, supplement and allergy, follow the fasting rules given…

Laser-Assisted vs Conventional Cataract Surgery: Where the Differences Actually Lie
Laser-assisted and conventional cataract surgery remove the cloudy lens and replace it with an artificial one; the laser automates the opening incisions and softens…
Thyroid Eye Disease and Oculoplastic Surgery: Why Timing Waits for the Disease to Settle
Thyroid eye disease surgery is usually planned only after the inflammatory active phase has burned out and eye measurements have stayed stable for several…

What Happens During a Full Eye Examination: Vision, Pressure, Dilation and Imaging
A full eye examination usually moves through a set order: a conversation about your health and symptoms, a letter-chart test of sharpness, refraction to…