

How Is a Pulmonary Embolism Treated? Anticoagulants, Thrombolysis and Catheter Options

Key Takeaways
- Anticoagulants, the mainstay of pulmonary embolism treatment, do not dissolve the clot; they stop it growing while the body's own enzymes clear it over weeks to months.
- Guidelines start from a minimum of three months of anticoagulation, with the decision to extend driven by whether the clot was provoked, persistent risk factors and individual bleeding risk.
- Systemic thrombolysis is reserved for high-risk pulmonary embolism with shock, because in stable patients trials show it reduces early deterioration but increases major bleeding without a clear survival benefit.
- Catheter-directed clot removal can rapidly relieve right-heart strain, but large trials have not yet shown a long-term advantage over anticoagulation alone in intermediate-risk patients.
- A vena cava filter is intended for people who cannot take anticoagulants or who clot despite them, and guidelines favor removing it once medicine becomes possible.
- The CDC estimates that about one-third of people who have had a deep vein thrombosis or pulmonary embolism will have another within ten years, which is why recurrence risk shapes treatment length.
A pulmonary embolism is treated mainly with anticoagulant medicines, which stop the clot from growing and prevent new ones while the body gradually dissolves the blockage; most people take them for at least three months. When a clot is large enough to strain the heart, doctors may add clot-dissolving thrombolysis, catheter-based clot removal or, rarely, surgery. The choice depends on how unstable the person is and their bleeding risk, and rests with the treating team.
It is usually the calmness that unsettles people. One minute you are being wheeled in from a CT scanner, short of breath and frightened; the next, a physician is drawing a lopsided lung on a whiteboard and saying, almost casually, that the clot is “probably going to be managed with blood thinners.” Just that? A clot in the lung, and the plan is a medicine that does not even remove it?
That gap between how dramatic a pulmonary embolism sounds and how quiet its treatment often looks is the source of most questions people carry home. If you have typed how is pulmonary embolism treated into a search bar at two in the morning, you are likely trying to close that gap.
This explainer walks through what the clot is doing, why anticoagulants are the backbone of care, when doctors reach for stronger tools such as thrombolysis or catheter procedures, and what the weeks afterward tend to feel like. It leans on what mainstream guidelines actually say, and it flags where the evidence is thinner than the confident headlines suggest.
How is pulmonary embolism treated? The short version
A pulmonary embolism, or PE, is a blood clot that has traveled through the veins and lodged in an artery of the lung. In most people it began as a deep vein thrombosis, a clot in a deep leg or pelvic vein, that broke free. Treating it means doing two things at once: protecting the person from the clot that is already there, and stopping more clot from forming or traveling.
For the large majority, the tool for both jobs is an anticoagulant, a medicine that slows the blood’s clotting system. The NHS and Mayo Clinic both describe anticoagulation as the standard first treatment, continued for at least three months, with the exact medicine, route and duration decided by the prescribing clinician. Anticoagulants do not dissolve the clot. They hold the line while the body’s own clot-clearing enzymes do the slow work.
A smaller group needs more than that. When the clot is large enough to drop blood pressure or strain the right side of the heart, doctors may use thrombolysis (a medicine that actively breaks the clot apart), a catheter passed through the veins to fragment or suck out clot, or in rare cases open surgery to remove it. These options carry higher bleeding or procedural risk, so they are reserved for people in whom the clot itself is the more immediate danger.
Around those choices sits a set of supporting decisions: whether to treat at home or in hospital, whether a filter in the main abdominal vein is warranted, how long to continue medicine, and how to reduce the chance of a repeat clot. Each of those decisions depends on the individual, which is why two people with “a PE” can leave the emergency department with quite different plans.
What actually happens when a clot reaches the lung
Picture the lung’s blood supply as a tree. The pulmonary artery is the trunk, dividing again and again into branches until the vessels are finer than a hair, wrapped around the air sacs where oxygen crosses into the blood. A clot that breaks off from a leg vein rides the bloodstream to the right side of the heart and is pumped into that tree, traveling until it reaches a branch too narrow to pass.
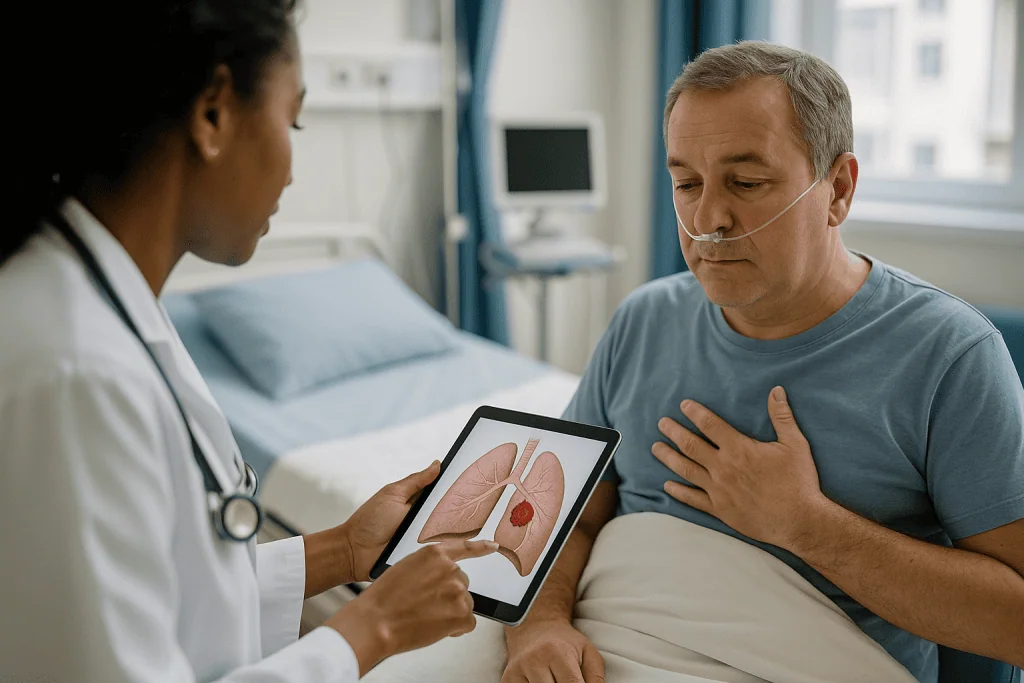
Two problems follow. First, the lung tissue beyond the blockage is still filling with air but no longer receiving blood, so that air is wasted. The person breathes faster to compensate, which is why sudden breathlessness is so common. Second, the heart’s right ventricle, the chamber that pumps blood into the lungs, must now push against a partly blocked system. A small clot barely registers. A large one, or a shower of many, can make that thin-walled chamber balloon and struggle within minutes.
The body responds immediately. An enzyme system called fibrinolysis begins nibbling at the clot’s protein scaffold, a process that takes days to weeks rather than hours. Cleveland Clinic notes that clots typically break down over weeks to months once anticoagulation is under way. The medicine’s role is to make sure the clot stops growing while that happens, and that the leg vein it came from does not send another.
This explains something patients often find counterintuitive: the treatment that saves most lives does not touch the lung at all. It works upstream, in the blood chemistry, buying the lungs and heart time to recover on their own. Only when time is the one thing the person does not have do doctors intervene directly on the clot.
Why doctors sort a pulmonary embolism by risk before treating it
The most consequential decision in PE care happens before any prescription is written. Clinicians place each person into a risk category, because the same clot can be a nuisance in one body and an emergency in another.
The categories used by major cardiology and chest guidelines look roughly like this. High risk means the clot is causing shock: blood pressure has fallen dangerously and organs are not being perfused. Intermediate risk means blood pressure is holding, but scans or blood tests show the right ventricle is under strain. Low risk means the heart is coping and the person is stable. The labels sound tidy; in practice, doctors reassess them repeatedly during the first hours, because people can move between them.
Several tools feed that judgment. A CT pulmonary angiogram, a contrast-dye scan of the lung arteries, shows where the clot is and how much of the tree it occupies. An echocardiogram, an ultrasound of the heart, reveals whether the right ventricle is enlarged or weak. Blood tests for troponin and natriuretic peptides, proteins released when heart muscle is stressed or stretched, add a chemical signal. Clinical scoring systems combine age, heart rate, oxygen level and other conditions into a single estimate of short-term danger.
The point of all this sorting is proportionality. Thrombolysis carries a real risk of serious bleeding, including into the brain, so it is justified only when the clot poses a greater risk than the drug. Anticoagulation alone carries a smaller bleeding risk and suits the many people whose hearts are coping. Asking your team which category they placed you in, and what moved you there, is one of the most useful questions you can ask.
Blood thinners for pulmonary embolism: how anticoagulants really work
“Blood thinner” is a misnomer that has stuck. Anticoagulants do not change the blood’s thickness. They interfere with the cascade of clotting proteins, so that when a clot tries to grow, the chemistry stalls. The existing clot is left in place for the body to dismantle.

Three broad classes are in common use, and MedlinePlus and Mayo Clinic describe them in patient terms. Heparins, including low-molecular-weight heparin, are given by injection and act within hours; they are often the first medicine used in hospital and are frequently preferred during pregnancy and in some people with cancer. Direct oral anticoagulants, sometimes shortened to DOACs, block a single clotting protein such as factor Xa or thrombin; they are taken by mouth, work quickly, and do not require routine blood-level monitoring, which is why many guidelines now list them as a first option for people without contraindications. Vitamin K antagonists, of which warfarin is the generic example, work more slowly by reducing production of several clotting proteins; they need regular blood tests measuring the INR, a ratio that shows how slowly blood is clotting, and they interact with many foods and medicines. Warfarin remains the usual choice for people with certain mechanical heart valves or antiphospholipid syndrome, an autoimmune clotting condition.
Which class a person receives is not a ranking of strength. It reflects kidney function, weight, other medicines, cancer, pregnancy, the ability to attend monitoring, and preference. Cleveland Clinic notes that warfarin takes several days to reach its full effect, which is why an injectable heparin is often overlapped at the start. None of these details should be read as a reason to request or refuse a particular medicine; they are the variables your prescriber is already weighing.
Pulmonary embolism thrombolysis: when clot-dissolving drugs are used
Thrombolysis is the treatment most people imagine when they hear “clot in the lung.” A thrombolytic, sometimes called a clot buster, is a medicine given through a vein that switches on the body’s own fibrinolytic system at full force, breaking clots apart over hours rather than weeks. Mayo Clinic describes these drugs as reserved for life-threatening situations because of the bleeding they can provoke.
The logic is a trade-off. Thrombolytics act everywhere in the circulation, not just in the lung. A clot in the pulmonary artery dissolves, but so does the protective clot sealing a recent wound, an ulcer or a fragile brain vessel. Bleeding into the brain is the most feared complication, and major guidelines weigh it heavily. That is why systemic thrombolysis is standard for high-risk PE, where the person is in shock and likely to die without rapid clot clearance, and generally not routine for intermediate-risk PE, where trials have shown that it reduces early deterioration but at the cost of more major bleeding, without a clear survival advantage overall.
Doctors also screen for absolute contraindications: recent stroke, active bleeding, recent major surgery or head injury, and certain brain conditions. In those situations the danger of the drug outweighs the danger of the clot, and the team looks toward catheter or surgical options instead.
Where thrombolysis is used, monitoring is intensive. The person is usually in a critical care setting, with frequent checks of blood pressure, oxygen and signs of bleeding, and anticoagulation is resumed afterward. Recovery of the right ventricle can be visible on an echocardiogram within days. Whether you were, or would have been, a candidate is a fair question to ask, and the honest answer for most people with PE is no, because most people with PE were never in the group where the benefit outweighs the harm.
Catheter-directed treatment and surgical embolectomy
Between medicine alone and open surgery sits a set of procedures done through the blood vessels. Catheter-directed therapy means threading a thin, flexible tube from a vein in the groin or neck up into the pulmonary artery under X-ray guidance, then working on the clot from the inside. Mayo Clinic and Johns Hopkins both list these as options when clots are large or when systemic clot-dissolving drugs are too risky.
Two broad techniques exist. In catheter-directed thrombolysis, a much smaller quantity of clot-dissolving drug is dripped directly onto the clot, with the aim of achieving the local effect while exposing the rest of the body to less of the medicine; some systems add ultrasound energy to loosen the clot’s structure. In mechanical thrombectomy, devices physically fragment, suction or capture the clot and pull it out without any thrombolytic, which appeals for people who cannot receive those drugs at all.
Here the evidence deserves an honest caveat. Observational studies and small trials show that these procedures can rapidly reduce strain on the right ventricle, and complication rates in experienced centers are reported as low. What has not yet been settled by large randomized trials is whether they improve long-term survival or quality of life compared with anticoagulation alone in intermediate-risk patients. Guidelines therefore describe them as reasonable options in selected people, particularly when clinical deterioration is under way or systemic thrombolysis is contraindicated, rather than as standard first-line care.
Surgical pulmonary embolectomy, opening the chest and removing the clot directly with the heart supported by a bypass machine, is the oldest of these interventions and now the rarest. It remains an option for people in shock in whom thrombolysis has failed or cannot be given, and in specialized situations such as clot trapped in the heart itself. Most people with PE will never meet the criteria for any of these procedures.
Do I need a vena cava filter?
An inferior vena cava filter is a small metal cage placed inside the large vein that carries blood from the legs to the heart. The idea is mechanical: catch any clot breaking off from the legs before it can reach the lungs. Mayo Clinic describes filters as an option for people who cannot take anticoagulants or in whom anticoagulants have not prevented further clots.
People are sometimes surprised that filters are not routine after a PE. The reason lies in what they do and do not do. A filter does nothing to the clot already in the lung, nothing to the clot in the leg, and nothing to the tendency to form clots. It simply intercepts travel. Meanwhile it introduces its own problems: filters can themselves become a site of clotting, the vein around them can block, and legs can swell. Guidelines therefore favor anticoagulation for anyone who can safely receive it, and recommend a filter mainly when anticoagulation is genuinely contraindicated, for example because of active serious bleeding, or when a person has a recurrent PE despite adequate anticoagulation.
Modern filters are often designed to be retrievable. When the reason for placement passes, for instance once bleeding has resolved and anticoagulation can start, the filter can be removed through a catheter. Guidelines encourage that removal rather than leaving devices in place indefinitely, because long-term complications accumulate.
If a filter has been suggested for you, useful questions include why anticoagulation is not possible right now, whether the filter is intended to be temporary, and who will track the plan for removing it. If a filter has not been suggested, that is not an oversight; it usually means your team judged that medicine alone protects you better than a device would.
Who is treated at home, who stays in hospital, and who is asked to wait
A generation ago nearly everyone with a PE spent days on a ward. That has changed. The NHS notes that some people with a low-risk pulmonary embolism can now be treated without an overnight stay or discharged early, provided certain conditions are met.
Home or early-discharge treatment is usually considered when the heart is not under strain, oxygen levels are normal on room air, pain is controlled, there is no active bleeding or high bleeding risk, kidney function allows the chosen medicine, and the person has support at home and can return quickly if anything changes. Clinical scores help formalize this, but the human factors matter as much: someone who lives alone with no phone signal and a two-hour drive from help is a different proposition from someone with a partner and a hospital ten minutes away.
Hospital admission remains the norm for intermediate- and high-risk PE, for people whose pain or breathlessness needs supplemental oxygen, and for those with serious other illnesses, pregnancy, or a bleeding concern that needs watching in the first days.
Then there is a small group who are asked to wait, or more precisely to be watched. When a scan shows a tiny clot in a very small peripheral branch, sometimes called a subsegmental PE, and there is no clot in the leg veins and the person is at low risk, some guidelines allow a strategy of close surveillance with repeat leg ultrasounds instead of immediate anticoagulation. The reasoning is that such tiny findings may sometimes be imaging artifacts, and the bleeding risk of months of medicine may not be justified. The evidence here is still developing, and this option depends heavily on individual circumstances. If it is offered to you, it reflects a specific low-risk situation, not a general view that small clots do not matter.
Pulmonary embolism treatment options compared
Seeing the choices side by side helps make sense of why one person leaves the emergency department with a prescription and another spends a night in intensive care. The table below summarizes the main approaches in plain terms, drawing on the descriptions given by the NHS, Mayo Clinic and MedlinePlus. It is a map, not a menu; only your treating team can say which square you are in.
| Approach | What it does | Usually considered for | Main trade-off |
|---|---|---|---|
| Anticoagulation alone | Stops clot growth and new clots while the body dissolves the existing one | Most people with PE, including all low-risk and many intermediate-risk cases | Bleeding risk, which is modest but real; daily medicine for months |
| Systemic thrombolysis | Actively dissolves clot throughout the circulation within hours | High-risk PE with shock; selected intermediate-risk patients who deteriorate | Higher risk of major bleeding, including in the brain |
| Catheter-directed therapy | Delivers clot-dissolving drug locally or removes clot mechanically through a vein | Selected intermediate- or high-risk patients, especially when systemic thrombolysis is contraindicated | Procedural risks; long-term benefit over anticoagulation still under study |
| Surgical embolectomy | Removes clot directly through open chest surgery | High-risk PE when other options fail or cannot be used | Major surgery; rarely needed |
| Vena cava filter | Traps clots traveling from the legs toward the lungs | People who cannot take anticoagulants or have recurrent PE despite them | Does not treat existing clot; device complications; ideally removed later |
| Surveillance without anticoagulation | Monitors with repeat ultrasounds rather than treating immediately | Selected very small peripheral clots with no leg clot and low risk | Small chance of missing progression; requires reliable follow-up |
One pattern stands out: the more aggressive the intervention, the smaller the group it is meant for. That inversion is deliberate. It reflects decades of evidence that, for most people with PE, the clot is a slow problem that a slow solution handles well, and that speed brings dangers of its own.
How long do you stay on anticoagulants after a pulmonary embolism?
Three months is the number almost every guideline starts from. The NHS states that people usually take anticoagulant medicine for at least three months, and Mayo Clinic gives the same minimum. That window covers the period in which the original clot is dissolving and the risk of an early repeat is highest. What happens after three months is where the conversation becomes individual.
Doctors think about it in terms of provocation. A provoked PE follows a clear, temporary trigger: major surgery, a leg in a cast, a long period of immobility, a hospital stay. Once the trigger is gone, the clotting tendency usually returns to baseline, and treatment often ends after the initial course. An unprovoked PE arrives with no identifiable cause, which suggests an underlying tendency that will not simply pass. In that situation guidelines lean toward longer, sometimes indefinite, anticoagulation, revisited at intervals.
Persistent risk factors push in the same direction. Active cancer, certain inherited clotting disorders, antiphospholipid syndrome, or a second clot after a first are all reasons a prescriber may recommend continuing. The CDC notes that about one-third of people who have had a deep vein thrombosis or PE will have another within ten years, which is why the recurrence question is taken seriously.
Against that sits bleeding. Every additional month on an anticoagulant carries a small chance of a serious bleed, and that chance rises with age, kidney disease, alcohol use, falls and some other medicines. The decision to extend is therefore a genuine balance rather than a default, and it is one your prescriber should discuss with you openly, including how confident they are about your recurrence risk. If the plan is indefinite, it is reasonable to ask how often it will be reviewed. What is not reasonable, for safety, is stopping on your own when you feel better; the clot risk does not follow symptoms.
Pulmonary embolism recovery time: what the first days, weeks and months look like
Recovery from a PE is measured on three overlapping clocks: the clot, the heart, and the person.
The first days. Breathlessness and chest pain often ease noticeably within days of starting anticoagulation, even though the clot has barely changed. That is partly because the body stops adding to it, and partly because inflammation around the affected lung settles. Cleveland Clinic notes that clots take weeks to months to dissolve. People are encouraged to walk early rather than lie still, since movement helps prevent further leg clots. Fatigue, however, can be profound and out of proportion to what shows on any test.
The first weeks. Most people return to ordinary daily activity within a few weeks, and many to work, depending on how physically demanding it is and how they feel. Follow-up usually includes a review of the medicine, checking for side effects, and confirming any blood test monitoring is in place. Stamina builds gradually; a walk that felt impossible on day three may be routine by week four.
The first months. Mayo Clinic and Johns Hopkins both note that full recovery can take months. A minority of people, particularly those who had larger clots or existing lung or heart disease, notice lingering breathlessness on exertion. If it persists beyond a few months, clinicians look for chronic thromboembolic pulmonary hypertension, a condition in which clot residue scars the lung arteries and raises pressure in them. It is uncommon but treatable in specialist hands, which is why persistent symptoms deserve reassessment rather than reassurance.
Anxiety belongs on this timeline too. Many people describe hypervigilance about every twinge in the chest for months afterward. That is a normal response to a frightening event, not a sign the clot is back, but it is worth telling your team about, because it responds to support.
Living with anticoagulation: bleeding, activity, travel and pregnancy
Anticoagulants ask for a few adjustments in daily life, most of which become second nature quickly. Bleeding is the central one. Minor bleeding, such as gums when brushing, longer-lasting nosebleeds or easier bruising, is common and usually not dangerous, but the American Heart Association and NHS both stress that any bleeding that will not stop, blood in urine or stool, black stools, or coughing or vomiting blood needs urgent assessment.
Practical steps reduce risk. A soft toothbrush and an electric razor are standard advice. Contact sports and activities with a high chance of head injury are generally discouraged while on treatment; walking, swimming, cycling on quiet routes and gym work are usually fine once the person feels ready. Alcohol adds to bleeding risk and interacts with warfarin in particular, so moderation matters. Every new medicine, including over-the-counter pain relievers and herbal supplements, should be checked with a pharmacist or prescriber, because anti-inflammatory painkillers and some supplements raise bleeding risk, and several antibiotics and antifungals alter warfarin levels.
Travel raises predictable questions. Mayo Clinic advises moving around at least every hour on long journeys, keeping hydrated and, where recommended, wearing compression stockings. Being on an effective anticoagulant reduces the risk of a new travel-related clot, but it does not remove it, and most clinicians prefer that people are stable and well past the acute phase before long-haul flights; the specific timing is a conversation with your own team rather than a fixed rule.
Pregnancy needs specialist input. Some oral anticoagulants are not used in pregnancy because they cross the placenta, and injectable heparins are usually preferred. Anyone who could become pregnant while on treatment should discuss contraception and planning with their prescriber early. None of this is meant to be limiting; it is the ordinary housekeeping of a medicine that, used carefully, protects far more than it threatens.
What people often get wrong about pulmonary embolism treatment
“The medicine dissolves the clot.” It does not. Anticoagulants prevent growth and new clots; the body’s own enzymes do the dissolving over weeks. Only thrombolytics actively break clot apart, and they are reserved for the most severe cases.
“If it were serious, they would have done a procedure.” The opposite is closer to the truth. Anticoagulation alone is the recommended treatment for most PE because it is effective and carries less risk. Procedures are not a sign of better care; they are a sign of a more dangerous clot.
“I feel fine, so I can stop early.” Symptoms fade well before the clot has cleared or the recurrence risk has settled. The NHS minimum of three months exists because early stopping leaves a window of vulnerability that the person cannot feel.
“Blood thinners thin the blood, so I’ll bleed to death from a cut.” Ordinary cuts still clot, just more slowly. Serious bleeding is uncommon and usually involves the gut, urinary tract or brain, which is why those specific signs are the ones to watch.
“A filter will protect me forever.” A filter catches traveling clot; it does not stop clots forming and can cause its own problems. Guidelines favor removing it once anticoagulation is possible.
“Bed rest helps the clot stay put.” Early walking is encouraged once anticoagulation has begun. Immobility raises the risk of further leg clots.
“A PE means something is badly wrong with my heart or lungs.” Most PEs come from leg veins in people whose hearts and lungs were previously healthy. The organs are victims of the clot, not its cause.
“Once treated, it can never come back.” Recurrence is possible, which is why the provoked-versus-unprovoked question shapes how long treatment lasts. Knowing your own recurrence risk, rather than assuming zero, is part of managing the condition well.
Questions to ask your care team
The hours after a PE diagnosis are not the moment most people think clearly, and follow-up appointments are short. Writing questions down beforehand changes the quality of the conversation. These are the ones clinicians often wish patients had asked.
- Which risk category was my PE placed in, and what findings put it there? Was my heart under strain on the scan or blood tests?
- Do you know what caused this clot, or is it unprovoked? Does that change how long I will be treated?
- Which class of anticoagulant have you chosen for me, and why that one rather than another? Does it need blood test monitoring?
- What is my personal bleeding risk on this medicine, and what would make you reconsider the plan?
- How long do you expect me to take it, and when will that decision be reviewed?
- Was I a candidate for thrombolysis or a catheter procedure? If not, what would have made me one?
- Which of my current medicines, supplements or foods interact with this treatment?
- What symptoms should prompt me to call you, and which mean I should go straight to emergency care?
- When can I return to work, exercise, driving and long-distance travel?
- If I am still breathless in a few months, what tests would you consider, and should I ask about pulmonary hypertension?
- Do I need testing for an inherited clotting condition, and would the result change my care or my family’s?
- If I could become pregnant, or plan surgery or dental work, what should I do first?
- Who do I contact between appointments if I have a question about the medicine?
You are not expected to understand every answer on the first pass. Asking a nurse, pharmacist or the prescriber to repeat or write down the plan is normal, and bringing someone with you to appointments helps more than most people expect.
When to call your doctor
Two kinds of trouble can follow a pulmonary embolism: the clot problem returning or worsening, and the treatment causing bleeding. Both have signals that should not be sat on.
Call emergency services immediately if you develop sudden or worsening breathlessness, sharp chest pain that is worse when you breathe in, coughing up blood, a racing heartbeat with lightheadedness, fainting or near-fainting, or lips or fingertips turning blue or gray. The NHS and Mayo Clinic list these as signs of a possible new or extending clot, and they warrant the same urgency as the original event. Sudden weakness on one side of the body, difficulty speaking, a severe unexplained headache or confusion may signal bleeding into the brain and are equally urgent.
Seek same-day care for bleeding that does not stop after firm pressure, vomiting blood or material that looks like coffee grounds, red or black stools, blood in the urine, a nosebleed lasting more than a few minutes, or a fall or blow to the head while on anticoagulants, even if you feel fine afterward.
Contact your care team within a day or two if you notice new swelling, warmth or pain in one leg, which can indicate a fresh deep vein thrombosis; unusual bruising; persistent dizziness; a rash or other possible reaction to the medicine; if you have vomited or been unable to take your medicine; if you have started a new prescription or over-the-counter product; or if you become pregnant or plan to.
Symptoms that linger without worsening, such as ongoing tiredness or breathlessness on stairs beyond a few months, also deserve a review, since they can point to chronic thromboembolic pulmonary hypertension or another cause that responds to assessment. Your treating team knows your scan, your medicine and your history; when in doubt, the call costs nothing and the information they give will be specific to you.
Frequently asked questions
What are four signs of pulmonary embolism?
The four signs clinicians most often describe are sudden breathlessness, chest pain that sharpens when breathing in, coughing that may bring up blood, and a rapid heartbeat with lightheadedness or fainting. Swelling or pain in one leg frequently accompanies them because most clots begin there. These features overlap with heart attack, pneumonia and anxiety, so they cannot be sorted out at home; sudden onset of any of them needs emergency assessment rather than watching and waiting.
Does a pulmonary embolism go away completely?
In most people the clot dissolves fully over weeks to months once anticoagulation prevents further growth, and lung function returns to normal. A minority are left with residual clot that scars the lung arteries, which can lead to chronic thromboembolic pulmonary hypertension; persistent breathlessness months later is the cue to check for it. The underlying tendency to clot may or may not resolve, which is why doctors distinguish provoked from unprovoked events when planning long-term care.
What is the survival rate of pulmonary embolism?
There is no single survival figure, because outcomes depend heavily on how large the clot is and whether the heart is under strain when treatment begins. People in the low-risk category, which includes most diagnosed cases, generally do well on anticoagulation alone, while high-risk PE with shock is a genuine emergency where thrombolysis or procedures are used. Rather than a population percentage, ask your team which risk category applied to you and what that means for your recovery.
How long does it take to recover from pulmonary embolism?
Pulmonary embolism recovery time varies widely. Breathlessness and chest pain often improve within days of starting anticoagulants, many people resume normal daily activity within a few weeks, and Mayo Clinic and Johns Hopkins note that full recovery can take months. Fatigue frequently outlasts the other symptoms. People with larger clots or existing heart or lung disease tend to recover more slowly, and breathlessness persisting beyond a few months should be reassessed rather than assumed to be normal.
How long does pulmonary embolism last once treatment starts?
The clot itself typically breaks down over weeks to months, according to Cleveland Clinic, even though symptoms usually ease much sooner. Anticoagulant treatment continues for at least three months regardless of how quickly you feel better, because the recurrence risk stays elevated during that window. Whether treatment then stops or continues depends on the cause of the clot and your bleeding risk, a decision made with your prescriber rather than by the calendar.
Which blood thinners for pulmonary embolism are commonly used?
Three classes are in common use: injectable heparins including low-molecular-weight heparin, direct oral anticoagulants that block a single clotting protein such as factor Xa or thrombin, and vitamin K antagonists such as warfarin that need regular INR blood tests. The choice depends on kidney function, pregnancy, cancer, other medicines, monitoring access and preference rather than on one being stronger. Your prescriber selects the class and duration; none of this is a reason to request or refuse a particular medicine.
Can a pulmonary embolism be treated at home?
Some people can. The NHS notes that low-risk pulmonary embolism may be managed with early discharge or without an overnight stay when the heart is not under strain, oxygen levels are normal, bleeding risk is low and reliable support and rapid access to care exist at home. Anyone with signs of right-heart strain, a need for oxygen, pregnancy or significant other illness is usually admitted. The decision is made by the emergency team using scans, blood tests and clinical scoring.
Is pulmonary embolism thrombolysis given to everyone?
No. Systemic thrombolysis is reserved for high-risk pulmonary embolism, where blood pressure has collapsed and the clot is immediately life-threatening, because the drug can cause serious bleeding, including in the brain. For stable patients with some heart strain, trials have shown fewer early deteriorations but more major bleeding, so guidelines do not recommend it routinely. People with recent stroke, active bleeding or recent major surgery generally cannot receive it, and catheter or surgical options are considered instead.
Can I fly after a pulmonary embolism?
Most people can travel again, but timing is individual. Clinicians generally prefer that you are stable, established on anticoagulation and past the acute phase before long-haul flights, and your own team should set the date. Mayo Clinic advises moving around at least every hour on long journeys, staying hydrated and wearing compression stockings where recommended. Carry your medicine in hand luggage, know how to reach care at your destination, and confirm the plan with your prescriber before booking.
Will I need blood thinners forever after a pulmonary embolism?
Not necessarily. When a clear temporary trigger such as surgery or immobility caused the clot, treatment often ends after the initial course of at least three months. When no cause is found, or a persistent risk such as cancer or an inherited clotting disorder exists, guidelines lean toward longer or indefinite treatment, balanced against bleeding risk and reviewed at intervals. The CDC’s finding that about one-third of people have a recurrence within ten years is part of that calculation.
References
- NHS – Pulmonary embolism
- CDC – About Venous Thromboembolism (Blood Clots)
- MedlinePlus – Pulmonary Embolism
- Cleveland Clinic – Pulmonary Embolism
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Stroke Volume Explained: The Heart’s Output per Beat
Stroke volume is the amount of blood the heart's left ventricle pumps out with a single contraction — roughly 70 milliliters in a healthy…

Does Insulin Cause Weight Gain? Why It Happens and How to Manage It
Insulin therapy can contribute to modest weight gain — in long-term trials, roughly 4 kilograms (about 9 pounds) over several years, with most of…
What Happens During an Echocardiogram, and How Long Does the Scan Usually Take?
A standard echocardiogram, the ultrasound scan of the heart done through the chest wall, usually takes 15 to 60 minutes according to the NHS,…

Type 1 vs Type 2 Diabetes: The Difference, and Which Is More Serious
Type 1 diabetes is an autoimmune condition in which the immune system destroys the pancreas's insulin-producing cells, so insulin must be replaced from diagnosis…

How to Lower Cholesterol Naturally: What Moves LDL Without a Prescription
You can lower LDL cholesterol meaningfully without medication by replacing saturated fats with unsaturated ones, eating 5 to 10 grams of soluble fiber daily…

ECG Explained: What It Shows, How Long It Takes and What Happens
An ECG (electrocardiogram) records your heart's electrical activity through sticky skin electrodes, showing heart rate, rhythm, and patterns that can suggest arrhythmias, reduced blood…