

How Long Viral Croup Usually Lasts: Why Nights Feel Worse and When the Bark Fades

Key Takeaways
- The barking, whistling phase of croup usually lasts about three to five days, while an ordinary cough can trail on for up to two weeks as the underlying cold clears.
- Halving the radius of a child's airway raises resistance to airflow roughly sixteen-fold, which is why a millimeter of swelling that an adult would never notice makes a toddler sound alarming.
- Symptoms are reliably worst at night, most often on the second or third night, in part because the body's natural anti-inflammatory hormone cortisol dips to its lowest levels overnight.
- A single dose of a corticosteroid begins to reduce airway swelling within a few hours and lasts about two to three days, covering the nights that are usually hardest.
- Nebulized epinephrine can open a swollen airway within about 30 minutes but wears off after roughly two hours, which is why children who receive it are observed for a few hours before going home.
- Randomized trials have not shown that steam or humidified air improves croup, and hot steam carries a real scald risk, so calm, upright and hydrated is the better home plan.
Viral croup usually runs its course in about three to seven days. The barking cough and noisy breathing tend to be worst on the first two or three nights, ease during the day, and then fade as airway swelling settles; a milder cough may linger up to two weeks. Most children recover at home, but noisy breathing at rest, blue lips, or struggling to breathe need urgent medical care.
It is 2 a.m. and the sound coming from the next room is not a cough you have heard before. It is a seal at a zoo, or a small dog behind a fence: harsh, hollow, repeating. You lift your toddler out of the crib and notice a thin whistling noise every time she breathes in. She is upset, which makes the whistle louder, which makes her more upset. And you are standing in the hallway in the dark trying to decide whether this is an emergency or a long night.
For most families it is a long night. Croup is one of the most common reasons a small child is brought to an emergency department after dark, and one of the most common reasons a family is sent home a few hours later, tired but reassured. Knowing how long does croup last, why the darkness seems to make it worse, and which signs genuinely change the plan is what turns panic into a workable routine.
This explainer walks through the whole arc: the first bark, the worst nights, what medicines actually do, and the moment the noise finally fades.
How long does croup last? The typical arc from first bark to last cough
Croup is an infection that makes the lining of the voice box and windpipe swell, and swelling follows a fairly predictable curve. Mayo Clinic describes a typical illness lasting about three to five days, while the NHS notes that many children are clearly better within roughly 48 hours and that a lingering cough can stretch to about two weeks. Those two statements are not in conflict. The dangerous-sounding part, the bark and the whistle, is short. The ordinary cold that travels with it is longer.
A common pattern looks like this. A day or two of runny nose, mild fever and a scratchy voice come first. Then, often abruptly on the first or second evening, the cough changes character and the breathing gets noisy. The second night is very often the hardest, and the third can be nearly as rough. By the fourth or fifth day, most children are barking less, breathing quietly at rest, and interested in toys and snacks again. What remains is a wet, unremarkable cough as the rest of the cold clears.
Which days are worst for croup? Mainstream summaries from Mayo Clinic and Cleveland Clinic consistently describe symptoms peaking around the second or third night before easing, though a child who starts with a rough first night may already be on the downslope by night three. Fever, when present, tends to settle in the first few days.
Two caveats matter. Some children have recurrent or spasmodic croup, in which the barking episodes return on other nights, sometimes over months, often without fever. And a small number of children get worse rather than better, which is why the red-flag section later in this article is not optional reading. The typical arc is a guide, never a promise.
What actually happens inside a child's airway during croup
The medical name is laryngotracheitis, which simply means inflammation of the larynx (the voice box) and trachea (the windpipe). The virus infects the lining of these tubes, and the body responds the way it does to any infection: blood flow increases, fluid leaks into the tissue, and the lining swells. The narrowest stretch of a young child’s airway sits just below the vocal cords, an area called the subglottis, and that is exactly where the swelling does its damage.
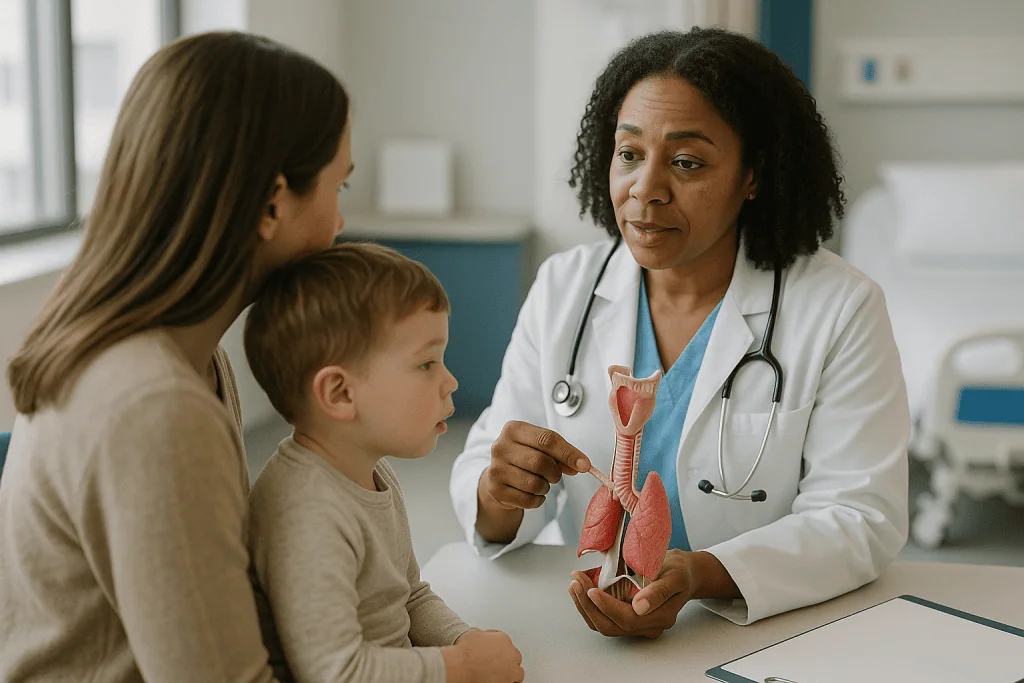
Here is why a small child is hit so much harder than an adult with the same virus. Airflow through a tube depends dramatically on its radius. Halve the radius and resistance to flow rises roughly sixteen-fold, a relationship described in the NIH-hosted StatPearls review of croup. A toddler’s subglottic airway is only a few millimeters across to begin with, so a millimeter of swelling steals a large fraction of the opening. In an adult the same millimeter is barely noticed.
The signature sounds come straight from that narrowing. The barking cough is air forced through a swollen, half-closed voice box. Stridor, the high-pitched whistle heard when the child breathes in, is turbulent air squeezing through the tight spot. Hoarseness comes from swollen vocal cords that can no longer vibrate cleanly.
Effort matters, too. When a child cries or panics, she breathes faster and harder, pulling the soft walls of the narrowed airway inward and making the whistle louder. That is why a calm child on a parent’s lap can sound almost normal while the same child, frightened, sounds alarming. The airway has not changed; the airflow has. Understanding this single mechanism explains almost everything about croup, from why it is worse at night to why medicines that shrink swelling work at all.
What viruses cause croup, and is croup contagious?
Croup is almost always viral. The parainfluenza viruses are the leading cause, with type 1 responsible for the largest share and the seasonal autumn peaks that pediatric wards know well, according to the CDC. Other culprits include respiratory syncytial virus (RSV), influenza, adenovirus, rhinovirus and the virus that causes COVID-19. Bacteria are a rare cause, which is why antibiotics have no role in ordinary croup.
Is croup contagious? The virus is; the croup is not. That distinction confuses many parents. What passes from child to child through coughs, sneezes and unwashed hands is a common cold virus. Whether a given child develops croup depends on age, airway size and individual tendency. One sibling gets a runny nose, another gets the bark, and a parent who catches the same virus gets a sore throat and a hoarse voice. Cleveland Clinic advises treating a child with croup as contagious for about three days after the illness begins or until the fever is gone, whichever is longer.
Practical steps follow the usual respiratory playbook:
- Handwashing after wiping noses, before meals and after diaper changes.
- Keeping shared cups, pacifiers and toothbrushes separate during the illness.
- Cleaning high-touch surfaces such as doorknobs and toys.
- Keeping the child home from daycare or school while feverish and clearly unwell.
Can my kid go to school with croup? The honest answer is that most children with active croup do not want to, and should not, for the first few days. Once the fever has cleared and the child is eating, playing and breathing quietly, many daycare and school policies allow a return even if a mild cough persists. Check the specific policy, and let your child’s energy level be the deciding vote.
Why is a croup cough at night so much worse?
Parents describe it the same way every time: fine at dinner, alarming at midnight, oddly cheerful at breakfast. The nighttime pattern is one of the most reliable features of croup and is noted by MedlinePlus, Mayo Clinic and the NHS alike. The reasons are partly biological and partly circumstantial.

The leading biological explanation involves cortisol, the body’s own anti-inflammatory steroid hormone. Cortisol follows a daily rhythm, rising toward morning and falling to its lowest point in the late night. Less natural anti-inflammatory hormone circulating means a little more swelling in an airway that has no room to spare. This is a well-established rhythm and a widely proposed mechanism, though it has not been isolated as the single cause.
Position plays a part. Lying flat lets secretions pool around the voice box and slightly changes airway shape. Overnight, bedrooms tend to be cooler and drier, and dry air irritates an already inflamed lining. Sleep also thickens the mucus that has been draining all day.
Then there is the loop of fear and effort described earlier. A child wakes coughing, does not understand the noise she is making, cries, breathes harder, and the stridor grows. A parent hears the change, tenses, and the child reads that tension instantly. None of this reflects a truly worsening infection, but it is impossible to tell from the hallway.
The daytime lull can mislead in the other direction. A child who sounds nearly well at 10 a.m. may have a difficult second night ahead, which is why clinicians ask about the previous night rather than the current appearance. If you are deciding whether to seek advice, describe how the child breathed at rest in the dark, not how she looks in the waiting room.
Croup in babies, toddlers and school-age kids: why age changes everything
Croup is overwhelmingly a disease of small airways, so age is the biggest risk factor. Mayo Clinic puts the most affected group at six months to three years, with cases tapering off as the airway grows. Boys are affected somewhat more often than girls, and autumn and early winter are the busiest seasons because that is when parainfluenza circulates.
Croup in babies under six months is uncommon and is treated with more caution. The airway is at its smallest, the infant cannot sit up or communicate distress, and other causes of noisy breathing, including structural narrowing present from birth, need to be considered. Most guidance suggests that an infant this young with stridor should be assessed in person rather than managed by phone.
Toddlers between one and three carry the classic picture: the seal-like bark, the hoarse cry, the whistle on breathing in, and the nights-are-worse rhythm. This is also the age at which parents most often find themselves in an emergency department after midnight, and the age at which the reassuring three-to-five-day course described by Mayo Clinic applies most cleanly.
School-age children get croup less often because a little swelling in a larger airway causes less trouble. When a child over six develops a persistent barking cough, clinicians tend to look harder at alternatives: asthma, an inhaled foreign body, a bacterial infection of the windpipe, or whooping cough. The same is true of a teenager or adult with croup-like symptoms, which is rare and usually prompts closer examination.
Recurrent croup, sometimes called spasmodic croup, is its own category. These children wake with sudden barking and stridor, often without fever or a preceding cold, improve within hours, and may repeat the episode weeks later. Allergy, reflux and airway sensitivity have all been suggested as contributors. A child with repeated episodes is usually reviewed by a pediatrician to rule out a structural cause.
Who is usually watched at home, and who is asked to come in
Most croup is mild, and most children are cared for at home. The dividing line clinicians use is simple to describe: what does the breathing sound like when the child is calm and at rest? A bark with a hoarse voice but quiet breathing between coughs is mild croup. Stridor that you can hear while the child sits quietly on your lap, or a chest that pulls in at the ribs and neck with each breath, moves the illness into moderate territory and usually earns an in-person assessment.
Emergency clinicians often formalize this with the Westley croup score, a bedside tally of stridor, chest retractions, air entry, color and alertness. Parents do not need to calculate it, but knowing that these five things are what the clinician is watching helps you report the right details.
Some children are asked to come in at a lower threshold regardless of how the cough sounds. The NIH-hosted StatPearls review and NHS guidance both flag groups where the margin for error is smaller:
- Infants under six months.
- Children with a known narrow airway, previous airway surgery, or conditions such as Down syndrome that affect airway size.
- Children born very prematurely or with chronic lung or heart disease.
- Children who have previously had severe croup needing hospital treatment.
- Families who live far from emergency care or cannot easily return if things change.
Who is asked to wait? A well-hydrated, alert toddler with a bark and no resting stridor is often advised to stay home, keep calm, and call back if the night brings changes. Many guidelines still recommend a single dose of a corticosteroid for even mild croup, so “wait” does not always mean “no treatment.” Whether your child fits either path is a decision for the clinician who examines her, informed by what you describe from the night before.
Mild, moderate and severe croup at a glance
Severity in croup is about breathing effort at rest, not about how loud the cough is. A child can bark like a sea lion and be perfectly safe; a child can be quiet and be in trouble. The table below summarizes the categories most clinicians use, drawn from the descriptions in the NHS, Mayo Clinic and StatPearls references. It is a guide to the conversation with your care team, not a tool for deciding alone.
| Severity | What you typically see | Where care usually happens | Usual pattern over time |
|---|---|---|---|
| Mild | Barking cough, hoarse voice; stridor only when crying or upset; breathing quiet at rest; child alert and drinking | Home, often after a phone or in-person check; a single corticosteroid dose is commonly prescribed | Worst on nights two and three; bark fading by day four or five |
| Moderate | Stridor audible at rest; visible pulling-in at the ribs or base of the neck; child still alert and consolable | Urgent care or emergency assessment; corticosteroid; observation for several hours | Usually improves within hours of treatment; many go home the same day |
| Severe | Loud stridor at rest or stridor that has gone quiet because less air is moving; marked chest retractions; agitation or unusual drowsiness | Emergency department; nebulized epinephrine plus corticosteroid; oxygen if needed; admission likely | Rapid response to nebulized medicine expected; observed because the effect wears off in about two hours |
| Impending airway failure | Pale, gray or blue color; exhausted, floppy or unresponsive; very little air movement | Emergency services immediately; intensive care | Rare; a small minority of admitted children need breathing support |
One point in the table deserves emphasis. Stridor that fades while the child is getting more tired is not improvement. It can mean too little air is moving to make a sound. Improvement looks like quieter breathing in a child who is also more alert, more comfortable and more interested in the world.
How croup treatment works: what a corticosteroid and a nebulized medicine actually do
Since the problem in croup is swelling in a tight space, the treatments target swelling. Two classes of medicine do almost all the work, and both are decisions for the prescribing clinician; nothing here is a recommendation or a dose.
Corticosteroids. These are anti-inflammatory medicines that quiet the immune response causing the airway lining to swell. The one most often used in croup is dexamethasone, usually given as a single oral dose; prednisolone is an alternative in some settings. The effect is not instant. The NIH-hosted StatPearls review describes benefit beginning within a few hours, and because dexamethasone is long-acting, one dose covers roughly the next two to three days, which conveniently spans the nights that are usually worst. A Cochrane systematic review indexed on PubMed found that corticosteroids reduce return visits and shorten emergency department and hospital stays compared with placebo. This is the treatment with the strongest evidence in croup, and it is why a child sent home from the emergency department at 3 a.m. often has a far quieter second night than parents expect.
Nebulized epinephrine. For moderate or severe croup, epinephrine (adrenaline) is breathed in as a fine mist. It works differently: it constricts the tiny blood vessels in the swollen lining, squeezing fluid out of the tissue and physically widening the airway. Relief typically arrives within about 30 minutes, but the effect fades after roughly two hours, according to StatPearls. That short duration is why children who receive it are observed for a few hours rather than discharged immediately; clinicians want to see that the corticosteroid has taken over before the epinephrine wears off.
What is not used. Antibiotics do not treat viruses. Over-the-counter cough and cold medicines are not advised for young children, and the NHS specifically warns against them under age six. Oxygen is given only when levels are low. A breathing tube is reserved for the rare child whose airway is closing despite everything else.
How long does croup last after treatment? What the next days and nights usually look like
Treatment changes the shape of the curve, not its total length. A corticosteroid can make the worst night noticeably gentler, but the cold that carries the virus still has to run its course. Here is a realistic sequence for a child with typical, uncomplicated croup, tied to the three-to-five-day frame from Mayo Clinic and the up-to-two-week tail described by the NHS.
The first 24 hours after assessment. If a corticosteroid was given, many parents notice that the bark is still there but the whistling on breathing in has softened or disappeared by bedtime. Fever may continue. The child is often tired and clingy and eats less than usual. Fluids matter more than food.
Nights two and three. Still the hardest stretch, treated or not. Expect coughing spells, some hoarse crying, and possibly stridor when the child is upset that settles when she is calm. Sleeping in the same room, or taking turns, lets you check breathing at rest without a hallway sprint. If stridor persists while she is calm, or breathing looks like hard work, that is the moment to call.
Days four and five. The voice starts coming back. The cough loses its seal-like quality and turns into an ordinary wet cough. Appetite and play return, which is a better sign of recovery than any single symptom.
The second week. A cough that lingers a few more days is common and is the tail of the cold, not a sign that croup is returning. What should not happen is a new fever, a return of resting stridor, or a child who looks sicker as the week goes on. Those patterns point to something else, such as a secondary bacterial infection, and warrant a fresh look from the care team.
Comfort at home: what helps, and what the evidence says about steam
Home care for croup is mostly about keeping a child calm, upright and hydrated while swelling settles on its own schedule. The interventions with the best support are the least dramatic ones.
Calm is a treatment. Because crying tightens the airway loop described earlier, anything that soothes the child helps the breathing: a lap, a favorite show, a quiet voice, dim light. The NHS advice to stay calm yourself is not a platitude; children read parental fear quickly.
Upright and hydrated. Sitting up, or sleeping slightly propped for older toddlers with a raised mattress rather than pillows for infants, eases drainage. Small frequent drinks keep secretions thin. A hoarse child may refuse solid food for a day or two; that is acceptable if fluids are going in and urine output is normal.
Fever comfort. Age-appropriate fever reducers, used exactly as the pharmacist or clinician advises, can make a miserable child more comfortable and therefore calmer. They do not shorten the illness.
Steam and humidifiers. For generations, the standard advice was to run a hot shower and sit in the steamy bathroom. Randomized trials indexed on PubMed and summarized in the StatPearls review have not shown that humidified air improves croup severity scores, and hot steam carries a real risk of scald burns in a squirming toddler. A cool-mist humidifier is unlikely to harm and may make a dry room more comfortable, but it should not be relied on to treat the airway.
Cold night air. Many parents swear by a few minutes at an open window or on the porch. The evidence is anecdotal, though the calm, the change of scene and the cooler air plausibly help the effort side of the equation. It is reasonable if the child is dressed warmly and you are watching breathing closely, not a substitute for seeking care when red flags appear.
Avoid tobacco smoke, over-the-counter cough syrups in young children, and any attempt to look down the throat with a spoon or flashlight, which can provoke gagging and worsen the airway.
What people often get wrong about croup
Croup attracts myths partly because it sounds so much worse than it usually is. Here are the misunderstandings that come up most often, and what the evidence says instead.
“There must be a fastest way to get rid of it.” There is no shortcut through a viral infection. A corticosteroid shortens and softens the worst of the swelling, and nebulized epinephrine buys hours in an emergency, but the virus still takes its three to seven days. Anyone promising a quick fix is selling something.
“Antibiotics will help.” They will not. Croup is viral in nearly every case, and antibiotics have no effect on viruses. They are reserved for the rare bacterial complication a clinician has actually diagnosed.
“Croup turns into pneumonia.” Croup lives in the upper airway; pneumonia is infection deep in the lungs. One does not become the other. The same virus can occasionally involve the lower airways, and a secondary bacterial infection can follow any viral illness, but this is uncommon. New fever after improvement, fast breathing without the barking sound, or a child who looks progressively sicker are the things to report, not a lingering cough alone.
“Steam is the treatment.” Trials have not shown benefit, and hot steam burns children. Calm, upright, hydrated is the better mantra.
“A quieter child is a better child.” Sometimes. But stridor that fades as a child grows drowsy and floppy is a warning, not a relief. Judge recovery by alertness and comfort alongside the sound.
“One steroid dose is dangerous.” A single short course is very different from long-term steroid use. The Cochrane review indexed on PubMed found the benefits clear; questions about side effects for your particular child belong with the prescribing clinician, not with a search engine.
“Only babies get croup.” Toddlers are the classic patients, and preschoolers and occasionally older children get it too.
Barking cough in toddlers: when it might not be croup
The seal-like bark is so distinctive that it is easy to assume every noisy toddler has croup. Most do. Clinicians, though, keep a short list of look-alikes in mind, because a few of them behave very differently and need very different care. Knowing the list helps you give a useful history rather than diagnosing at home.
Bacterial tracheitis is a bacterial infection of the windpipe that can follow viral croup. The tell is a child who seemed to be improving and then gets worse: high fever, looks toxic, thick secretions, and stridor that does not respond to the usual croup medicines. It is uncommon and treated in hospital.
Epiglottitis, swelling of the flap that covers the airway during swallowing, has become rare since routine vaccination against Haemophilus influenzae type b. It looks different from croup: a very frightened child sitting forward, drooling, unable to swallow, with a muffled rather than hoarse voice and usually no barking cough. It is an emergency.
An inhaled object such as a piece of food or a small toy can cause sudden coughing and stridor in a child who was perfectly well seconds earlier, with no fever and no preceding cold. The abrupt onset is the clue.
Whooping cough (pertussis) produces long coughing fits ending in a gasp or vomit rather than a bark, and it drags on for weeks. Vaccination status matters here.
Allergic reaction can swell the airway quickly, often with hives, lip or face swelling, and a recent new food or medicine.
Asthma tends to produce wheeze on breathing out, rather than stridor on breathing in, and usually lacks the bark.
Spasmodic croup, discussed earlier, mimics viral croup at night but without fever or a cold, and tends to recur.
None of this means you should sort your child into a category at 2 a.m. It means the details you notice, especially how fast it started and whether there was a cold first, are exactly what the clinician needs.
Questions to ask your care team
A croup visit, whether by phone, video or in person, often happens in the middle of the night when nobody is at their sharpest. Having a short list ready helps you leave with a plan you actually understand. These are the questions clinicians most often wish parents had asked.
- How severe does my child’s croup look to you right now, and what were you listening and looking for when you decided?
- Are you prescribing a corticosteroid? How soon should I expect it to start working, and how long will its effect last?
- If my child received a nebulized medicine, how long should we stay for observation, and what are we watching for before we go home?
- What exactly should the breathing sound like when my child is calm and at rest tonight? What sound or sign means I should call back or come in?
- Is there anything about my child specifically, such as age, prematurity or a past airway problem, that changes the usual advice?
- How should I manage fever and fluids at home? Are there any medicines I should avoid at this age?
- Should my child be seen again in the next day or two even if things improve, or only if something changes?
- How long should my child stay home from daycare or school, and when is she no longer considered contagious?
- If this happens again next month, is that expected, or does it need a follow-up appointment to look for another cause?
- Who do I call overnight if I am worried, and at what point do I skip the phone and use emergency services?
Write the answers down, or ask the clinician to. A discharge note that says “return if stridor at rest, retractions, drowsiness, or blue lips” is far more useful at 4 a.m. than a memory of a hurried conversation. And if the answer to any question is “we are not sure yet,” that honesty is a good sign, not a bad one; croup is a watch-and-reassess illness, and a team that says so is doing it right.
When to call your doctor: red-flag signs
Most children with croup never need this section, but every parent should read it before the second night rather than during it. The signs below come from NHS, Mayo Clinic and MedlinePlus guidance and are the ones that change the plan from home care to urgent assessment.
Call emergency services or go to the nearest emergency department immediately if your child:
- Has lips, tongue or face that look blue, gray or unusually pale.
- Is struggling to breathe: the skin pulls in sharply at the ribs, the base of the neck or under the breastbone with every breath, or the nostrils flare.
- Makes stridor (the high-pitched noise on breathing in) constantly while calm and at rest, or the stridor becomes very loud or very quiet as she tires.
- Is unusually drowsy, floppy, hard to wake, or too breathless to cry or speak.
- Is drooling, cannot swallow, or is sitting rigidly forward with her chin out.
- Seems to have inhaled an object, or has sudden face or lip swelling with hives.
Contact your doctor or nurse line the same day if:
- Stridor is present at rest but your child is otherwise alert and comfortable.
- Symptoms are not improving after three to four days, or improved and then worsened with new or higher fever.
- Your child is drinking much less than usual, has fewer wet diapers, or has a dry mouth and no tears.
- Your child is under six months old with any croup symptoms, or has a known airway, heart or lung condition.
- The bark keeps coming back on different nights over weeks.
When in doubt, call. Clinicians would far rather hear about a child who turns out to be fine than see one who arrived late. Whatever the reason for the noise in the next room, the decision about what happens next always sits with the team who can examine your child, and your job is simply to describe what you heard in the dark as clearly as you can.
Frequently asked questions
What is the fastest way to treat croup?
There is no shortcut through the virus, but a single dose of a corticosteroid prescribed by a clinician is the treatment with the strongest evidence for reducing airway swelling, with effects beginning within a few hours. In an emergency, nebulized epinephrine works within about 30 minutes. At home, the fastest relief comes from calming the child, since crying tightens the airway and makes the breathing noise louder. Steam, antibiotics and cough syrups do not speed recovery.
What days are worst for croup?
The second and third nights are usually the hardest, according to the descriptions in Mayo Clinic and Cleveland Clinic guidance. The illness often starts with a day or two of cold symptoms, then the bark and stridor arrive abruptly one evening, peak over the next night or two, and begin fading by the fourth or fifth day. Daytime lulls are normal and do not mean the coming night will be easy.
Can croup turn to pneumonia?
Croup does not turn into pneumonia. Croup is swelling in the upper airway; pneumonia is infection in the lungs. The same virus can occasionally involve the lower airways, and a secondary bacterial infection can follow any viral illness, but this is uncommon. Warning signs that something else is developing include a new fever after improvement, fast breathing without the barking sound, or a child who looks progressively sicker rather than better.
Can my kid go to school with croup?
Not during the first few days, when the child is feverish, unwell and most contagious. Cleveland Clinic suggests treating a child as contagious for about three days after the illness begins or until fever is gone, whichever is longer. Once the fever has cleared and the child is eating, playing and breathing quietly, many daycare and school policies allow a return even with a mild lingering cough. Check your specific policy.
Is croup contagious to adults and older siblings?
The virus is contagious; the croup itself is not. Parainfluenza and other croup viruses spread through coughs, sneezes and hands, but an adult or older child who catches them typically develops a sore throat, hoarse voice or ordinary cold because a larger airway tolerates the swelling easily. Younger siblings with small airways are the ones most likely to develop the bark. Handwashing and keeping cups and pacifiers separate reduce spread.
How long does croup in babies last, and is it different?
The course is similar, typically three to five days for the noisy phase, but croup in babies under six months is uncommon and treated more cautiously because the airway is at its smallest and other causes of noisy breathing need to be ruled out. Most guidance advises in-person assessment for any infant this young with stridor rather than home management by phone. Your pediatrician decides the pathway.
Why does my child keep getting croup?
Some children have recurrent or spasmodic croup: sudden nighttime barking and stridor, often without fever or a cold first, that settles within hours and returns weeks or months later. Allergy, reflux and an airway that is simply sensitive have all been proposed as contributors. Repeated episodes are usually reviewed by a pediatrician, and sometimes an ear, nose and throat specialist, to make sure there is no structural narrowing behind the pattern.
Does a humidifier or steam help croup?
Randomized trials indexed on PubMed have not shown that humidified air improves croup severity scores, and hot steam from a shower or kettle carries a real risk of scald burns in a struggling toddler. A cool-mist humidifier may make a dry room more comfortable and is unlikely to harm, but it should not be relied on to treat the airway. Calm, upright positioning and fluids have better support.
Should I take my child outside into cold night air?
The evidence is anecdotal, though many parents find it helps. The likely benefit comes from the calm, the change of scene and cooler air easing the effort of breathing rather than from shrinking the swelling itself. It is reasonable for a few minutes if the child is dressed warmly and you are watching breathing closely. It is never a substitute for seeking care when stridor persists at rest or breathing looks like hard work.
Is a barking cough in toddlers always croup?
Usually, but not always. Sudden coughing and stridor in a previously well child with no cold and no fever raises the possibility of an inhaled object or an allergic reaction. A child who was improving and then developed high fever and worsening stridor may have bacterial tracheitis. Drooling, inability to swallow and a muffled voice suggest epiglottitis, now rare with vaccination. Describe how fast it started and whether a cold came first.
References
- Croup – MedlinePlus Medical Encyclopedia
- Croup – NHS
- About Human Parainfluenza Viruses – CDC
- Croup – StatPearls, NIH National Library of Medicine
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
What Does Recovery After Pediatric Cardiac Surgery Look Like? Intensive Care, Ward and Home
Recovery after child heart surgery usually moves through three stages: a monitored intensive care phase of roughly 2 to 4 days after open-heart procedures,…

Is Kawasaki Disease Contagious? Myths About Causes, Spread and Who Gets It, Corrected
No. Kawasaki disease is not contagious. It is an inflammatory illness of the blood vessels, most common in children under five, and it does…

When Toddlers Stop Napping, and How to Handle the Transition
Most children stop napping somewhere between ages 3 and 5, although a small number give up daytime sleep closer to age 2 and some…

Febrile Seizures: What They Look Like and Whether They Can Be Prevented
Febrile seizures are brief convulsions triggered by fever in children roughly 6 months to 5 years old. They look frightening, stiffening, rhythmic jerking, unresponsiveness, but most…

Newborn Jaundice: Causes, When to Worry and How Long It Lasts
Newborn jaundice happens because a baby's body breaks down red blood cells faster than the still-immature liver can clear the yellow pigment bilirubin. It…

Are All Babies Born with Blue Eyes? How Eye Colour Develops and When It Settles
No. The idea that all babies are born with blue eyes is a myth. Most newborns worldwide have brown eyes, because eye color depends…