

How TMJ Disorder Is Diagnosed: Jaw Movement Tests, Bite Checks and When Imaging Is Needed
Key Takeaways
- TMD is diagnosed primarily by history and hands-on examination; imaging is reserved for locking, trauma, suspected arthritis, or symptoms that persist despite conservative care.
- Clinicians measure comfortable and maximum mouth opening with a ruler and watch whether the chin deviates or deflects, which helps distinguish a muscle problem from a disc that is catching.
- The three-finger test is an informal screen, not a diagnosis; finger widths vary too much between people for it to stand alone, and it says nothing about pain or joint sounds.
- A painless jaw click is common and, according to Mayo Clinic, generally does not need treatment unless it comes with pain or restricted movement.
- MRI is the only imaging that shows the cartilage disc directly, while CT shows bone detail, which is why the choice of scan depends on whether disc displacement or arthritis is suspected.
- The NIH estimates TMD affects about 5 to 12 percent of people and is more common in women, and the NHS notes it often improves within weeks to months with conservative measures.
TMJ disorder is diagnosed mainly by a clinical examination, not a scan. A dentist or doctor takes a detailed history, watches and measures how far and how straight the jaw opens, listens and feels for joint sounds, presses on the jaw and chewing muscles, and checks how the teeth meet. Imaging such as X-ray, CT or MRI is reserved for cases where the exam suggests joint damage, a locked jaw, or another condition that needs ruling out.
The click started as a party trick. Somewhere in her late twenties, she noticed her jaw made a small pop when she yawned, and friends found it funny. A few years later the pop had company: a dull ache in front of her left ear by mid-afternoon, a tightness in her cheeks on waking, and a morning when a bagel felt like a dare. She did what most people do. She searched, found a dozen pages promising a quick fix, and felt more confused than when she began.
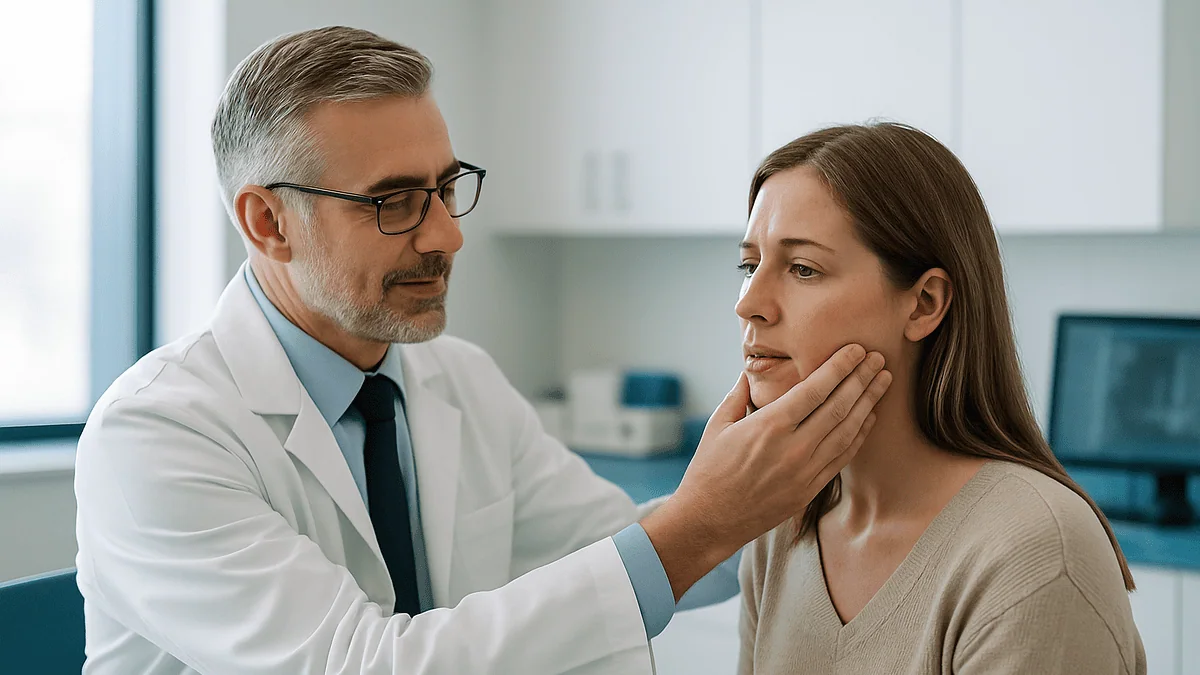
What she actually needed was not a gadget but a good examination. A tmj diagnosis is one of the more hands-on encounters in medicine: a clinician watching your jaw open, measuring the gap with a small ruler, pressing on muscles you did not know you had, and asking about your sleep, your stress and your teeth.
This explainer walks through that visit step by step, including the honest answer to the question almost everyone asks in the chair: do I need a scan?
What does a TMJ diagnosis actually involve?
Start with the joint itself. The temporomandibular joint (TMJ) is the hinge on each side of your head where the lower jaw meets the skull, just in front of the ear. Between the two bones sits a small cushion of cartilage called the articular disc, and around it run the muscles that let you chew, speak and yawn. When this system hurts, catches or stops moving well, clinicians use the umbrella term temporomandibular disorder, or TMD, which covers problems in the joint, the disc, the muscles, or all three.
The National Institute of Dental and Craniofacial Research estimates that TMD affects roughly 5 to 12 percent of the population, and that it is more common in women than men. Most people who have it never see a specialist because symptoms settle. For those who do seek help, a tmj diagnosis rests on three legs: what you describe, what the examiner can see and feel, and, only when needed, what a picture of the joint reveals.
That order matters. Unlike a broken wrist, where the X-ray tells the story, jaw pain is usually a story the joint cannot tell on film. Two people can have identical scans and completely different experiences, and a perfectly normal-looking joint can hurt a great deal because the surrounding muscles are working overtime. Guidelines from Mayo Clinic and the NHS therefore describe the diagnosis as primarily clinical, with imaging playing a supporting role.
Expect the visit to feel less like a test you can pass or fail and more like a structured conversation with a physical exam attached. The clinician is building a picture of where the pain comes from, how the jaw moves, and whether anything about the pattern points away from TMD toward something that needs different care.
How is TMD diagnosed? It begins with the conversation
Before anyone touches your face, the examiner listens. The history is not small talk; it is often the most informative part of the whole visit, because TMD tends to declare itself through patterns rather than through any single finding.

You will likely be asked when the pain began, whether it is on one side or both, and what makes it better or worse. Pain that flares after a long meal, a dental appointment with the mouth held open, or a stressful week points toward muscle involvement. A joint that catches, locks or feels as if it slips out of place suggests the disc is not tracking smoothly over the bone. Morning jaw stiffness or a partner who mentions nighttime grinding raises the question of bruxism, the clinical name for clenching or grinding the teeth, often during sleep.
Clinicians also ask about the neighbors. Headaches, ear fullness, neck tension and ringing in the ears frequently travel with TMD, and Cleveland Clinic notes that many people are first evaluated for an ear problem before the jaw is considered. Questions about recent injury, arthritis elsewhere in the body, and any history of joint hypermobility help sort out whether this is a local problem or part of a broader condition.
Internationally, many specialists structure this conversation around a validated set of criteria known as the Diagnostic Criteria for Temporomandibular Disorders, which pairs a standardized questionnaire with a standardized exam so that two clinicians in different places reach the same conclusion. You may not be told the name, but if you are handed a form asking you to rate pain over the past month and to point to where it hurts on a diagram, that is what is happening. Bring notes; a rough diary of when the jaw hurts, what you were eating or doing, and how long each episode lasted is more useful than any home remedy list you found online.
Jaw movement tests: what the clinician is measuring
Now the hands-on part. The clinician asks you to open as wide as you comfortably can and places a small ruler between your upper and lower front teeth. This is not theater. Healthy adult mouths open in a range wide enough to fit roughly three stacked fingers, and a measurable reduction is one of the clearest objective signs available in a condition that is otherwise hard to quantify.
Three measurements usually follow. The first is comfortable opening, how far you can go before it hurts. The second is maximum opening, how far you can go at all, sometimes with the examiner gently assisting to see whether the limit is pain or a true mechanical block. A jaw that stops abruptly and will not go further even with help behaves differently from one that could open but is guarding against pain. The third set involves sideways and forward movements, sliding the jaw left, right and out. Restriction in one direction often points to the joint on the opposite side.
Watch the path, not just the distance. As you open, the clinician looks at the midline of your chin. A jaw that swerves toward one side then corrects, a movement called deviation, suggests a disc that catches and releases. A jaw that drifts steadily to one side and stays there, called deflection, suggests the joint on that side is not translating forward normally.
Each result is recorded, and this is where the exam earns its keep over time. Mayo Clinic describes observing range of motion as a standard step in evaluation, and repeating the same measurements at a follow-up visit turns a vague sense of “a bit better” into a number. Progress, or its absence, becomes visible on paper, which matters when deciding whether the plan is working or whether imaging should now be considered.
What is the 3 finger test for TMJ, and how reliable is it?
Type “3 finger test for tmj” into a search bar and you will find videos of people stacking their index, middle and ring fingers and trying to fit them between their front teeth. The idea is simple: if three fingers fit, opening is within a normal range; if only two fit, the jaw is restricted.

Here is the honest version. The three-finger check is a rough screening habit borrowed from clinical practice, where examiners sometimes use finger widths as a quick estimate before reaching for the ruler. It has real limits. Finger widths vary from person to person by a centimeter or more, so a small-handed person with a slightly tight jaw may pass while a large-handed person with a perfectly normal jaw may fail. It also says nothing about pain, sounds, deviation of the midline, or whether the restriction comes from muscle guarding or from a disc that is physically blocking the joint.
What the test can do is prompt a useful observation. If you could once fit three fingers and now cannot, or if opening that wide has become painful, that change is worth mentioning to a dentist or doctor. What it cannot do is diagnose anything, and it should not be used to reassure yourself that a locked or painful jaw is fine.
Clinicians also avoid forcing the jaw open during such a check. A joint that is catching can be pushed into a more stubborn lock, and repeatedly stretching an inflamed joint tends to make it angrier, not looser. Consider the finger test a conversation starter, not a verdict. Where a validated approach is needed, the ruler measurements and the structured criteria described earlier are what the evidence actually supports, and the NHS advises that persistent or worsening symptoms be assessed by a dentist or GP rather than self-managed indefinitely.
Bite checks: what your teeth tell the examiner
Ask you to bite down, and the examiner learns a surprising amount. The way your upper and lower teeth meet is called occlusion, and while the old belief that a “bad bite” causes most TMD has not held up in research, the bite still offers clues about how the jaw is being used.
The first thing an examiner looks for is wear. Flattened cusps, tiny chips along the edges of front teeth, and shiny polished facets where enamel has been ground against enamel are the fingerprints of bruxism. Cleveland Clinic lists teeth grinding and clenching among the common contributors to TMD, and worn teeth in someone with morning jaw ache tell a coherent story. Scalloped edges along the tongue or a ridge of thickened tissue inside the cheeks can point the same way.
The examiner may also ask you to tap your teeth together, then slide side to side, watching whether any single tooth takes the first hit or the jaw has to shift to find a comfortable resting position. A recent crown or filling that sits slightly high can change the way the jaw closes and set off a bout of muscle pain, which is why you will be asked about recent dental work.
A word of caution here, because this is where myths flourish. Finding an uneven bite does not mean the bite caused the pain, and it certainly does not mean the teeth need to be reshaped. Mayo Clinic notes that irreversible treatments aimed at changing the bite lack strong evidence and are generally not recommended as a first step. The bite check is diagnostic information, one piece among many, and it is most useful for spotting habits such as clenching that you and your care team can then address in reversible ways.
Palpation: why they press on your face, jaw and neck
Palpation simply means examining by touch, and in a TMD evaluation it is where the diagnosis often comes into focus. The examiner presses with the fingertips on specific muscles and on the joint itself, asking each time whether it hurts and whether the pain stays put or spreads somewhere else.
Two muscles get the most attention. The masseter is the thick slab of muscle you can feel bulging at the angle of your jaw when you clench; it does the heavy lifting in chewing. The temporalis is the fan-shaped muscle at your temple, and tenderness there is one reason TMD so often masquerades as a tension headache. Behind and below these, the examiner may reach the muscles along the side of the neck and under the jaw, because the head, neck and jaw work as one unit and pain routinely travels between them.
The joint itself is felt just in front of the ear opening, sometimes with a fingertip placed gently in the ear canal while you open and close, which lets the examiner feel the rounded head of the jawbone moving. Tenderness directly over the joint suggests inflammation of the joint lining or capsule; tenderness in the muscles with a comfortable joint suggests a muscular problem. This distinction shapes everything that follows, including whether imaging would add anything.
Referred pain is the phenomenon the examiner is listening for when asking “does that hurt anywhere else?” A tender spot in the masseter can send pain to a back tooth, to the ear, or up into the temple, which is why some people have had healthy teeth checked repeatedly before the jaw muscles were ever examined. Johns Hopkins describes this overlap between jaw, ear and tooth pain as one reason a careful physical exam matters. None of it should be forceful; steady, moderate pressure is enough to find what is tender.
Clicks, pops and crepitus: what jaw sounds mean and don't mean
Jaw noises worry people out of proportion to their significance, so it helps to know the vocabulary the examiner uses. A click or pop is a single, discrete sound, usually made when the articular disc, that cartilage cushion, slips back into position over the jawbone as you open, or out of position as you close. Crepitus is a grating or gravelly sound, like sand between the bones, and it suggests the joint surfaces themselves have roughened, as happens in arthritis.
The examiner listens, sometimes with a stethoscope, sometimes just by placing fingers over the joint while you open and close several times. They note whether the sound happens on opening, closing or both; whether it occurs at the same point each time; and whether it comes with pain or a momentary catch.
Now the reassuring part, and it is genuinely reassuring. A painless click on its own is common and, according to Mayo Clinic, does not need treatment if it is not accompanied by pain or limitation. Many people click for decades without the joint ever deteriorating. Sounds become diagnostically meaningful when they arrive with other findings: a click plus a jaw that occasionally sticks suggests the disc is displacing and reducing; a click that has recently disappeared alongside a newly restricted opening can mean the disc has displaced and stopped reducing, which is the classic mechanism of a locked jaw.
Crepitus deserves a closer look because it hints at changes in the bone rather than the soft cushion, and this is one of the situations in which imaging is more likely to be discussed. Even then, the decision depends on the whole picture. An older joint that grates quietly but moves fully and painlessly may need nothing more than a note in the record and a follow-up.
Is it TMJ or something else? Ruling out the look-alikes
Part of every tmj diagnosis is the quiet work of ruling other things out. Pain in front of the ear has many possible owners, and a clinician’s job is to make sure the jaw is not taking blame for a neighbor.
Dental causes come first. A cracked molar, an abscess or a wisdom tooth pushing through can all produce pain that radiates along the jaw, which is why a dentist will often tap individual teeth, test them with cold, and sometimes take a small dental X-ray even when the joint is the suspected culprit. Ear infections and blocked ear tubes produce fullness and ache that sit almost exactly where the joint does; a quick look in the ear with an otoscope sorts this out in seconds. Sinus pressure can mimic pain in the upper jaw and cheek.
Nerve pain is a more important distinction. Trigeminal neuralgia, a condition of the main facial nerve, produces sudden, electric-shock jolts lasting seconds, quite different from the deep, dull ache of a tired muscle. Salivary gland stones or infections cause swelling under the jaw that worsens with eating. Rarely, pain in the jaw can be a symptom of heart trouble; the American Heart Association lists jaw pain among the less typical presentations of a heart attack, particularly in women, and any jaw pain arriving with chest pressure, breathlessness or sweating is an emergency, not a dental question.
Systemic joint disease matters too. Rheumatoid arthritis and related conditions can involve the TMJ, and a history of swollen or stiff joints elsewhere will prompt different questions and possibly blood tests. None of this means your clinician doubts you. It means a good diagnosis is as much about what the problem is not as about what it is, and each of these alternatives has its own path of care.
TMJ MRI or CT scan: when imaging is actually needed
The question everyone asks. Given how convincingly a scan seems to settle other joint problems, it can be frustrating to hear that the jaw is usually different. But the reasoning is sound: most TMD is muscular or involves a disc problem that behaves predictably on examination, and pictures rarely change the plan. Imaging enters the conversation when the exam suggests structural damage, when the jaw is locked and will not open, when symptoms persist despite reasonable conservative care, or when another condition needs excluding.
Each type of image answers a different question, and knowing which is which helps you understand why a particular one is chosen.
| Test | What it shows best | When it tends to be considered |
|---|---|---|
| Clinical exam | Muscle tenderness, range and path of movement, sounds, bite | Every evaluation; sufficient for most people |
| Panoramic dental X-ray | Teeth, jawbone outline, gross bony changes | Excluding dental causes; a first broad look |
| CT or cone-beam CT | Fine bony detail, arthritis, fractures, bone shape | Crepitus with restriction, injury, suspected bony disease |
| MRI | The disc, its position, joint fluid, inflammation | Suspected disc displacement, locking, persistent unexplained joint pain |
Mayo Clinic lists these same modalities as options when the exam alone does not settle the question. MRI is the only one that shows the soft cartilage disc directly, which is why it is favored when locking suggests the disc has slipped. CT shows bone, so it wins when the concern is arthritis or a fracture after a blow to the chin. Neither is ordered casually, because scans have costs beyond money: CT involves radiation, MRI requires lying still in a tube for a stretch, and both can reveal incidental findings that cause worry without changing care. A joint that looks imperfect on MRI in someone with no symptoms is common, and treating the picture rather than the person is a well-documented trap.
Who is usually offered imaging, and who is usually asked to wait
Think of imaging as a tool with a job description. Clinicians tend to reach for it in a handful of situations, and these are worth knowing so that the decision feels like reasoning rather than reluctance.
People more likely to be offered a scan include those whose jaw has locked, either open or closed, and cannot be released; those with a history of significant trauma to the face or chin; those whose exam reveals grating crepitus together with restricted or painful movement, raising the question of arthritis; those whose symptoms have persisted or worsened despite several weeks of appropriate conservative care; and those with features that do not fit the usual TMD pattern, such as swelling, numbness, a change in how the teeth meet that appeared suddenly, or pain that is steadily progressive rather than fluctuating.
People who are typically asked to wait are those whose story and exam point clearly to muscle-based pain: tender chewing muscles, a joint that is not itself sore, movement that is a little restricted by discomfort but not mechanically blocked, and painless clicking. For this group, which is the majority, both the NHS and Mayo Clinic describe starting with conservative measures and reassessing. The NHS notes that TMD often improves within a few weeks to months with simple self-care. If the exam findings improve on schedule, a scan would have added radiation, time and anxiety without changing a single decision.
“Wait” does not mean “ignored.” It means the examiner has enough information to act and has set a review point. If that review shows no progress, the calculus shifts, and imaging becomes reasonable. Children and teenagers are approached with extra caution around CT because their tissues are more radiation-sensitive; when imaging is needed for a young person, MRI or a limited dental X-ray is often preferred. In every case, the choice sits with the treating team, weighing what the picture could change against what it costs.
What causes TMJ flare-ups, and why the history often beats the scan
People searching “what causes tmj flare ups” are usually trying to make sense of a pain that comes and goes without obvious reason. The diagnostic visit is the right place to untangle this, because the triggers you describe often locate the problem more precisely than any image.
Clenching and grinding sit at the top of the list. Many people clench during concentration, in traffic, or during sleep without any awareness of it, and the chewing muscles respond the way any overworked muscle does, with soreness and fatigue. Cleveland Clinic and the NHS both identify bruxism and stress as frequent contributors. Sustained wide opening is another; a long dental appointment, a large sandwich, or a bout of vigorous yawning can set off a muscular flare in a susceptible jaw.
Habits count. Chewing gum for hours, biting nails or pen caps, resting the chin on a hand, cradling a phone between ear and shoulder, and sleeping face-down with the jaw pushed to one side all load the joint or its muscles asymmetrically. Posture during long screen sessions, with the head craned forward, tightens the neck muscles that share workload with the jaw. Poor sleep and periods of high stress lower the threshold at which all of this becomes painful.
Arthritis-related flares behave differently, often worse in the morning and in cold weather, and accompanied by grating rather than clicking. Injury, even a minor knock or whiplash from a rear-end collision months earlier, can set off a pattern that outlasts the original event.
Notice that almost none of these causes would appear on a scan. This is the practical reason clinicians spend so long on the history: the mechanism behind your flare-ups is usually behavioral or muscular, and it is identified by asking, not by imaging. The diagnosis, in this sense, is also the first step in management, because naming a trigger is the beginning of changing it.
What the weeks after a TMJ diagnosis usually look like
Leaving the appointment, most people carry a diagnosis of muscle-related or disc-related TMD and a set of conservative first steps rather than a prescription for a procedure. Understanding the typical arc helps you judge whether things are on track.
The first week or two is usually about unloading the system. Clinicians commonly suggest softer foods, cutting food into smaller pieces, avoiding gum and very chewy items, supporting a yawn with a fist under the chin, and paying attention to daytime clenching. Warmth over tender muscles, gentle stretching within a comfortable range, and attention to sleep and stress are frequently part of the plan. Mayo Clinic describes short courses of over-the-counter pain relief or, in some cases, prescribed muscle relaxants as options a clinician might discuss; any decision about medicine, including whether to use one at all, belongs to the prescribing clinician and depends on your health history.
By the third or fourth week, many people notice the pattern softening, with fewer painful mornings and wider comfortable opening. The NHS indicates that TMD frequently improves within a few weeks to months. Some clinicians arrange a review at roughly this point, repeating the ruler measurements and palpation to compare with the first visit. Improvement confirms the working diagnosis and the plan. A plateau prompts a rethink: perhaps a custom night guard, an appliance made by a dentist to sit over the teeth and reduce grinding forces during sleep, or a referral to physical therapy for jaw and neck exercises.
Persistence beyond a couple of months despite genuine adherence, or any worsening, is the natural point at which imaging and specialist referral re-enter the discussion. A minority of people have disc or joint problems that require more, and the staged approach is designed to find them without subjecting everyone else to interventions they do not need. Improvement is often gradual and uneven; a bad day within an improving month is not a failure.
What people often get wrong about TMJ diagnosis
Misconceptions cluster thickly around the jaw, and several of them shape how people approach the diagnostic visit. Clearing them up early makes the whole process less stressful.
The first is that a click means the joint is damaged and will only get worse. In reality, painless clicking is common, frequently stable for years, and, as Mayo Clinic notes, not something that requires treatment in itself. The second is that a scan is the gold standard. For most TMD it is not; the examination is, and imaging is a supplement for specific situations rather than a routine confirmation.
The third misconception is that a “bad bite” is the root cause and fixing the teeth fixes the jaw. Research has moved firmly away from this view, and Mayo Clinic advises caution about irreversible procedures such as reshaping teeth or extensive bite adjustment, which lack strong supporting evidence. The fourth is the mirror image: that TMD is “all stress” and therefore not a real physical problem. Stress is a genuine contributor because it drives clenching, but the sore muscles and the slipping disc are entirely real, and the exam findings are measurable.
The fifth is that ear symptoms rule the jaw out. Fullness, popping and ringing in the ear travel with TMD often enough that ear specialists routinely refer patients back to the dentist. The sixth is that surgery is the endpoint for anyone whose jaw keeps hurting. Surgical treatment is uncommon and reserved for structural problems confirmed on imaging that have not responded to conservative care, which is a small fraction of people.
Finally, there is the belief that a diagnosis should arrive with a single clear cause. TMD is usually multifactorial: a susceptible joint, a clenching habit, a stressful stretch, and a long dental appointment might each contribute a piece. The examiner’s job is to identify the modifiable pieces, not to find one villain.
Questions to ask your care team
The most useful diagnostic visits are two-way. Arriving with questions keeps the conversation focused on your situation rather than on generic advice, and the answers tell you a good deal about how confident the diagnosis is.
Consider asking:
- Based on the exam, does my pain seem to come mainly from the muscles, the joint itself, or both? Understanding this helps you make sense of why certain measures are suggested.
- Did you find any signs of clenching or grinding, such as tooth wear, and how confident are you that this is contributing?
- What did the range-of-motion measurements show, and what numbers would you hope to see at a follow-up visit?
- Is there anything about my history or exam that points toward a cause other than TMD, and has that been checked?
- Do I need imaging now? If not, what specific changes would make you reconsider?
- Which of the first steps you are recommending are reversible, and are any of them permanent?
- How long should I give this plan before we reassess, and how will we judge whether it is working?
- Are there activities or habits you noticed that I should change, and are there any I should avoid entirely for now?
- If my jaw locks, what should I do in the moment, and whom should I contact?
- Would a referral to physical therapy, a dentist who focuses on jaw disorders, or another specialist be helpful, and at what stage?
Write the answers down or ask whether the clinic can provide a summary. A diagnosis of TMD is often a working diagnosis, refined over one or two visits, and having the reasoning in front of you makes it easier to notice progress and to describe changes accurately if the picture shifts. The treating team is the right place to bring any information you have gathered elsewhere, including this article, so that it can be weighed against your own exam findings.
When to call your doctor
Most TMD is uncomfortable rather than dangerous, and the ordinary ache of an overworked jaw does not need urgent attention. Certain signs, though, change the picture and warrant a prompt call to a dentist or doctor, or, for the most serious, emergency care.
Seek same-day assessment if your jaw locks open or closed and you cannot move it back, if pain is suddenly severe rather than gradually worsening, or if the way your teeth fit together changes abruptly, since these may indicate a displaced disc or, after injury, a fracture. Swelling, redness or warmth over the joint, especially together with fever, chills or feeling generally unwell, is uncommon in ordinary TMD and raises the possibility of an infection in or around the joint; people searching for “symptoms of a TMJ infection” should know that fever and visible swelling are the features that separate it from routine jaw pain and that it needs medical evaluation quickly.
Numbness or tingling of the face, lip or chin, drooping of one side of the face, difficulty swallowing, or a lump under the jaw that does not settle should be reviewed promptly, because these point away from the joint toward nerves, glands or other structures. Jaw pain that arrives with chest pressure, shortness of breath, sweating, nausea or pain spreading to the arm is a possible sign of a heart attack; the American Heart Association includes jaw pain among the less typical warning signs, and this situation calls for emergency services immediately, not a dental appointment.
Less dramatic but still worth a call: pain that has persisted or steadily worsened over several weeks despite following the plan, a jaw that increasingly catches or restricts, new grating sounds with limited movement, or headaches that are changing in character. None of these are emergencies, but each is a reason the treating team may want to re-examine you and revisit the question of imaging or referral. Trust your sense that something has shifted; that observation is diagnostic information too.
Frequently asked questions
What is the 3 finger test for TMJ?
The three-finger test is an informal check in which you stack your index, middle and ring fingers and see whether they fit vertically between your front teeth. Fitting three fingers suggests mouth opening is in a normal range. It is only a rough screen: finger widths vary widely, and the test ignores pain, clicking and how straight the jaw moves. A clinician measures opening with a ruler and interprets it alongside the rest of the exam.
How is TMD diagnosed by a dentist or doctor?
TMD is diagnosed clinically. The clinician takes a detailed history of your pain, triggers and habits, then measures how far and how straight your jaw opens, listens and feels for clicks or grating, presses on the chewing muscles and the joint to locate tenderness, and checks how your teeth meet. Many use standardized diagnostic criteria so results are consistent. Imaging such as X-ray, CT or MRI is added only when the exam raises specific concerns.
Do I need a TMJ MRI or CT scan?
Most people with jaw pain do not need a scan, because the examination usually identifies a muscle or disc problem well enough to guide care. Imaging is typically considered when the jaw locks, after a significant injury, when grating sounds suggest arthritis, or when symptoms persist despite several weeks of conservative measures. MRI shows the soft cartilage disc; CT shows bone. Your treating team weighs what a picture could change before ordering one.
How do you fix TMJ pain?
There is no single fix, but most TMD is managed with reversible measures: softer foods, avoiding gum and wide yawning, reducing clenching, warmth and gentle stretching, attention to sleep and stress, and sometimes a dentist-made night guard or physical therapy. Clinicians may discuss short-term pain relief or other medicines; those decisions belong with the prescribing clinician. The NHS notes symptoms often improve within weeks to months. Irreversible procedures are reserved for confirmed structural problems that have not responded.
What are the symptoms of a TMJ infection?
Infection of the TMJ is rare, and what distinguishes it from ordinary TMD is that it looks and feels like an infection: swelling, redness or warmth over the joint in front of the ear, often with fever, chills or feeling generally unwell, and a jaw that becomes very painful to move. Routine TMD does not cause fever or visible swelling. Anyone with these features should seek prompt medical assessment rather than waiting to see if it settles.
What should you avoid if you have TMJ?
Clinicians commonly advise avoiding activities that overload the joint or its muscles: chewing gum, very hard or chewy foods, biting nails or pens, opening extremely wide, resting your chin on your hand, and cradling a phone between ear and shoulder. Deliberately clicking the jaw or forcing it open to test it can aggravate an irritated joint. These are general suggestions from sources such as the NHS; your treating team can tailor them to your exam findings.
What causes TMJ flare-ups?
Flare-ups are usually driven by load on the jaw muscles and joint rather than by structural change. Common triggers include daytime or nighttime clenching, stress and poor sleep, prolonged wide opening such as a long dental visit, hard or chewy foods, gum, and posture habits that strain the neck. Arthritis-related flares tend to be worse in the morning. Identifying your triggers during the diagnostic history is often more useful than any scan.
Can TMJ cause ear pain and ringing?
Yes. The temporomandibular joint sits directly in front of the ear canal and shares nerve pathways with the ear, so TMD frequently produces ear fullness, aching, popping sensations and sometimes ringing. Many people are first evaluated for an ear infection before the jaw is considered. A clinician will look in the ear to rule out an ear problem and then examine the joint and chewing muscles to see whether the jaw explains the symptoms.
Is a clicking jaw always a sign of TMJ disorder?
No. Clicking alone, without pain or restricted movement, is common and does not by itself mean you have a disorder that needs treatment. The sound usually comes from the cartilage disc moving over the jawbone. Clicking becomes more meaningful when it appears alongside pain, catching, locking, or a recent change in how far you can open. A grating sound rather than a click is more likely to prompt further evaluation.
How long does it take to get a TMJ diagnosis?
A working diagnosis is usually reached at the first appointment, since the history and physical examination provide most of the information. It is often confirmed at a follow-up visit several weeks later, when measurements are repeated to see whether the expected improvement has occurred. If imaging is needed, the timeline depends on scheduling. The diagnosis is refined over time rather than delivered as a single verdict, and the treating team sets the review points.
References
- NHS: Temporomandibular disorder (TMD)
- NIH National Institute of Dental and Craniofacial Research: TMD (Temporomandibular Disorders)
- Cleveland Clinic: Temporomandibular Disorders (TMD)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Wisdom Teeth Recovery: A Realistic Day-by-Day Healing Guide
Most people feel the worst of wisdom teeth recovery during the first two to three days, when swelling and soreness peak, then improve steadily.…

Clear Aligner Milestones: Tray Changes, Refinements and the Retainer Phase
Clear aligner treatment moves through predictable milestones: a digital scan and treatment plan, the first tray and an adjustment week, tray changes roughly every…

After Fluoride Application: Waiting to Eat, Drink and Brush So the Varnish Can Work
After fluoride varnish, most dental teams ask you to avoid all food and drink for about 30 minutes, then choose soft, cool or lukewarm…
What Happens During a Tooth Extraction? Numbing, Loosening the Tooth and Closing the Socket
A tooth extraction procedure has three stages. First, the dentist numbs the tooth and surrounding gum with a local anesthetic injection, so you feel…
Wisdom Teeth Removal Cost: Simple vs Surgical Extraction Pricing
Surgical wisdom tooth extraction sits at EUR 130-250 per tooth in our guide range for international patients, compared with roughly GBP 250-600 in the…

How Halitosis Is Diagnosed: Breath Assessment, Gum Checks and Finding the Source
Halitosis diagnosis starts with a clinician smelling the breath from the mouth and nose separately and rating it on a standard scale, then examining…