

Inside a Pediatric Dialysis Session: Access Checks, Monitoring and Comfort for Your Child

Key Takeaways
- A typical in-center hemodialysis session for a child lasts about four hours and happens three times a week, with the first quarter-hour spent on weight, blood pressure and access checks rather than on the machine.
- A nurse checks a fistula or graft before every run by feeling for the buzzing thrill and listening for the whooshing bruit; the absence of either can mean a clot and is an urgent call.
- Peritoneal dialysis is often chosen for infants and young children because it needs no needles and can run overnight at home for roughly eight to ten hours while the child sleeps.
- Most in-session discomfort comes from removing fluid too fast, which is why the target weight is renegotiated as a child grows and why the nurse can slow or pause fluid removal at any moment.
- Cloudy drained fluid in a child on peritoneal dialysis is the classic sign of peritonitis and needs a same-day call, even without fever.
- For most children, dialysis is a bridge to transplant or, in acute kidney injury, to recovery of their own kidneys; it clears waste and fluid but does not replace the kidney's hormonal work.
In a pediatric dialysis session, a nurse first checks the child's access site, records weight, blood pressure and pulse, then connects the child to the dialysis circuit. Hemodialysis typically runs for around four hours, usually three times a week, with vital signs monitored throughout and comfort measures such as numbing cream, play and schoolwork built in. Peritoneal dialysis happens at home, often overnight, using the lining of the abdomen as the filter.
It is ten to seven on a Tuesday, and a mother is zipping a backpack that holds a math workbook, a tablet with headphones, a fleece blanket and a stuffed otter with one ear worn thin. Her nine-year-old will spend most of the school morning in a reclining chair with two needles in his forearm. She has done this drive dozens of times. It still tightens her chest.
Parents in her position tend to type the same late-night query in different words, and one version is simply pediatric dialysis session: what happens. The answer matters, because a child who understands the order of events, and a parent who knows what the nurse is listening for and why the machine beeps, usually walks in calmer than one who has been left to imagine it.
This explainer walks through a typical session in a children’s unit and a typical home exchange, from the first handshake to the drive home, and answers the harder questions families ask once the routine settles in.
What happens in a pediatric dialysis session, from arrival to going home
A hemodialysis visit follows a rhythm that children learn quickly. Hemodialysis is the form of dialysis in which blood leaves the body through a needle or catheter, passes through a filter that removes waste and extra fluid, and returns through a second line. The National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) describes a standard in-center treatment as lasting about four hours and taking place three times a week, and the NHS gives the same range for most patients.
The first ten to fifteen minutes belong to checks, not machines. The child is weighed, ideally in the same light clothing each time, so the team can compare against the target weight set at the last visit. Blood pressure and pulse are recorded, temperature is taken, and the nurse examines the access site with eyes, fingers and a stethoscope. Only then is the child seated and the circuit prepared.
Connection is the moment most children dislike, and the moment most units have worked hardest to soften. A topical local anesthetic cream, applied about an hour before, numbs the skin over a fistula or graft. For a child with a central venous catheter, a soft tube that sits in a large vein near the heart, there are no needles at all; the nurse cleans the caps and attaches the lines.
During the run the child reads, watches, sleeps or does homework while the nurse records readings at regular intervals and responds to alarms. At the end, blood is returned, needles come out, pressure is held on the site until bleeding stops, and a second weight and blood pressure are taken before the family leaves.
Hemodialysis or peritoneal dialysis: which one will my child have?
Children can be treated with either of two forms of dialysis, and the choice depends on age, body size, the health of the abdomen, the family’s home situation and the plans for transplant. The kidney team makes the recommendation; parents contribute the practical details only they know.
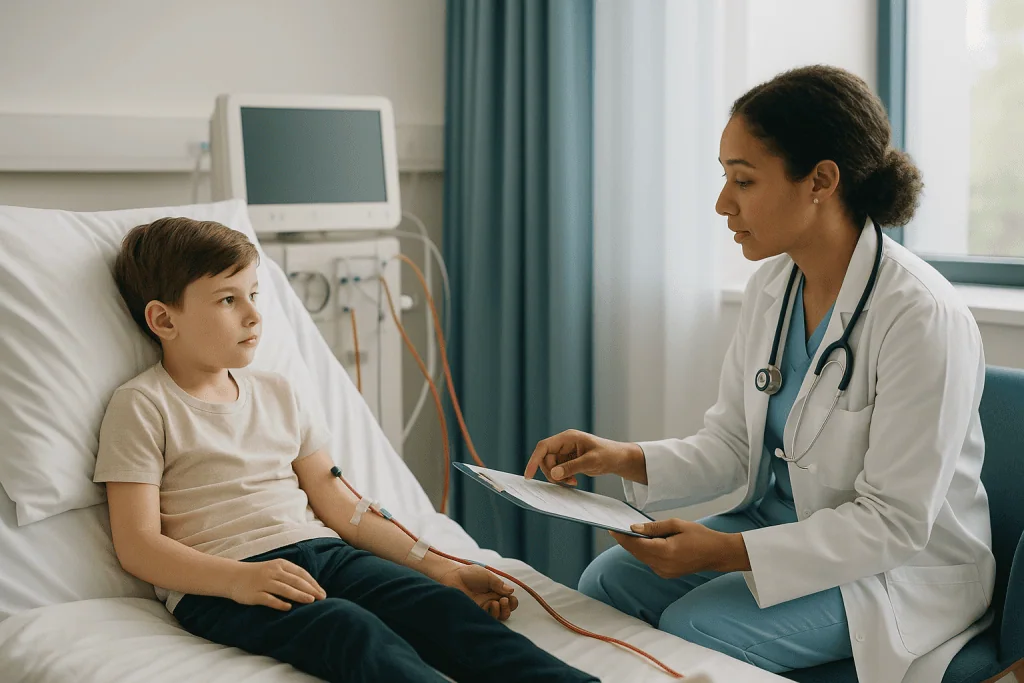
Peritoneal dialysis (PD) uses the peritoneum, the thin membrane lining the abdominal cavity, as a natural filter. A sterile fluid is run into the abdomen through a soft catheter, waste and water move across the membrane into the fluid over a few hours, and the fluid is then drained. The NIDDK notes that PD is commonly chosen for infants and young children because it avoids needles and can be done at home, including overnight while the child sleeps.
| Feature | Hemodialysis (HD) | Peritoneal dialysis (PD) |
|---|---|---|
| Where it happens | Usually in a children’s unit; home HD exists but is less common | At home, after training |
| Typical schedule | About 4 hours, 3 times a week (NHS, NIDDK) | Daily; either 3–5 exchanges by day or 8–10 hours overnight by machine (NHS) |
| Access | Fistula, graft or central venous catheter | Catheter in the abdominal wall |
| Needles | Two per session with a fistula or graft; none with a catheter | None |
| Main risk to watch | Low blood pressure, access clotting or infection | Peritonitis (infection of the lining), catheter problems |
| Diet and fluid | Stricter, because treatment is intermittent | Often more flexible, because treatment is daily |
Neither is the better option in the abstract. A toddler in a rural area, a teenager who wants weekends free and a child with previous abdominal surgery will each land in a different place, and children sometimes switch from one to the other as circumstances change.
Who is usually offered dialysis, and who is usually asked to wait
Dialysis is a treatment for kidney failure, the point at which the kidneys can no longer clear enough waste and fluid to keep the body safe. MedlinePlus and the NHS both describe this stage as kidney function below roughly 15 percent of normal, although the number alone rarely triggers treatment in a child.
Pediatric nephrologists look at the whole picture. Signs that dialysis is needed soon include fluid building up that medicines can no longer control, potassium or acid levels in the blood that threaten the heart, nausea and poor appetite that are stalling growth, and a child who is simply too tired to live like a child. In an acute crisis, such as severe acute kidney injury after a serious illness, dialysis may start urgently and stop again once the kidneys recover.
Children with chronic kidney disease who still have some function are often asked to wait. Waiting is not neglect. Every month of native kidney function spared is a month without needles, fluid limits and travel, and the team uses that time to create an access, train the family, plan nutrition and, where appropriate, work up a living or deceased donor transplant. In some cases a transplant is arranged before dialysis is ever needed; the NIDDK describes this preemptive route as an option for some children.
A small group of children are not offered dialysis at all, usually when other serious conditions mean the burden would outweigh any benefit. Those conversations happen slowly, with palliative care support, and belong entirely to the family and their treating team.
Dialysis access care for children: why nurses look, listen and feel before every run
The access is the child’s lifeline, and the pre-session check is the least glamorous and most important part of the visit. There are three common types. An arteriovenous fistula is a surgical connection between an artery and a vein, usually in the forearm or upper arm, that makes the vein wide and strong enough for repeated needling. An arteriovenous graft does the same job with a soft synthetic tube when a child’s veins are too small. A central venous catheter is a tunnelled line into a large vein near the heart, common in infants and in children waiting for a fistula to mature.
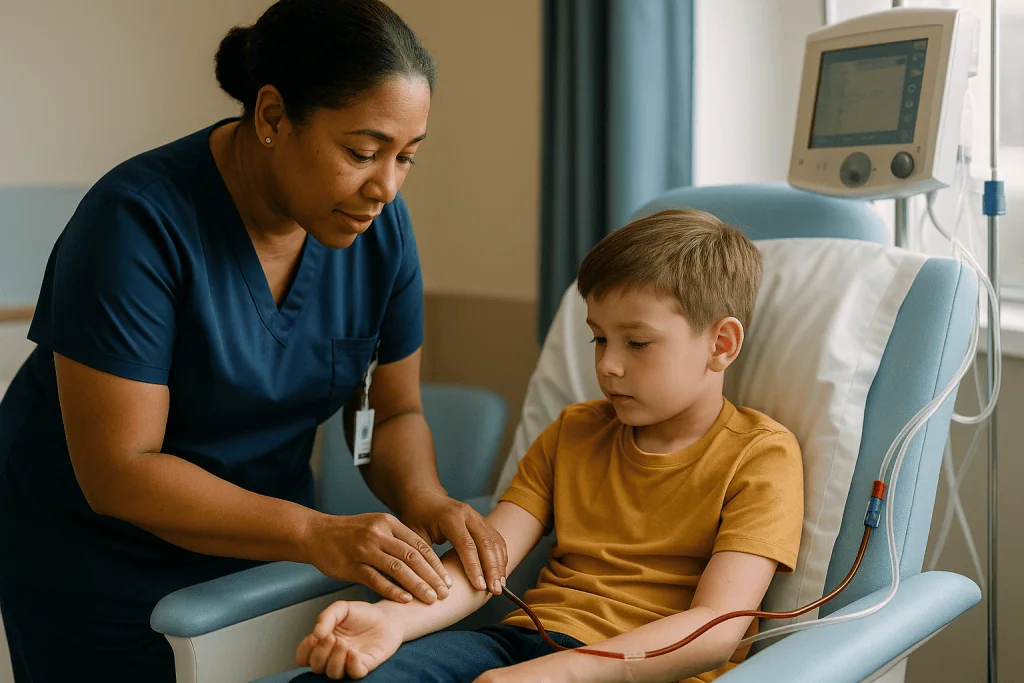
For a fistula or graft, the nurse feels for a thrill, the buzzing vibration of fast blood flow, and listens with a stethoscope for a bruit, the whooshing sound that means the same thing. A weakened thrill, a high-pitched sound, swelling, redness or a new bulge can signal narrowing or a clot, and the team may order an ultrasound rather than proceed blindly. The NIDDK explains that a new fistula often needs two to three months to mature before it can be used, which is why access planning starts well before dialysis does.
For a catheter, the check is about infection and flow. The nurse inspects the exit site for redness, discharge or tenderness, confirms the dressing is intact and dry, and flushes each lumen. Catheters carry a higher infection risk than fistulas, so families are taught to keep the dressing covered during baths and to avoid swimming unless the team agrees.
Parents can help by feeling the thrill at home once a day and by knowing the rule most units teach: no blood pressure cuffs, blood draws or tight sleeves on the access arm.
Weighing in, target weight, and the numbers the nurse watches during the run
Two numbers frame every hemodialysis session. The first is the pre-dialysis weight. The second is the target weight, sometimes called dry weight, the weight at which the child has no excess fluid but is not so depleted that blood pressure falls. The difference between them tells the team how much fluid to remove, and this is negotiated, not dictated. A child who has grown a centimeter, had a stomach bug or started a new medicine may need a fresh target.
Fluid removal is where most in-session discomfort originates. Take off too much or too fast and blood pressure drops, producing dizziness, cramps, nausea or a sudden yawn and pallor that experienced nurses spot before the child says a word. The NHS lists low blood pressure and muscle cramps among the most common side effects of hemodialysis, and the machine allows the rate to be slowed or paused at any moment.
Through the run, the nurse records blood pressure and heart rate at set intervals, often more frequently in younger children whose blood volume is small relative to the circuit. The machine itself monitors pressures in the arterial and venous lines, detects air, and tracks the temperature and composition of the dialysate, the cleansing fluid on the other side of the filter. An anticoagulant, a medicine that slows clotting, is usually run into the circuit so blood does not clot in the tubing; the type and amount are set by the prescribing clinician.
Alarms sound often and rarely mean danger. A child shifting position can kink a line and set off a pressure alarm; a nurse silences it, adjusts the arm, and the run continues. Explaining this on day one prevents weeks of flinching.
Is dialysis painful for kids? Comfort measures that actually help
Honest answer: the needles can hurt, and almost everything else is more boring than painful. Children’s units treat comfort as clinical work rather than a nicety, because a frightened child moves, and movement makes access harder to needle and more likely to bleed.
Pain control starts before arrival. A topical local anesthetic cream, applied under a dressing about an hour beforehand, numbs the skin over a fistula or graft; many families put it on at home so it has time to work. Some units use a buttonhole technique, needling the same tract each time so a blunt needle slides in with less sensation, though this is a team decision that weighs infection risk. Cold spray, vibration devices and simply letting the child count down are used alongside.
Distraction is the second pillar. Child life specialists, where a unit has them, plan activities around the run: crafts that can be done one-handed, board games, film time, or a tablet mounted on the chair. Older children often bring schoolwork, and many units liaise with schools so that dialysis mornings are not lost learning time.
Environment matters too. Blankets, because cooled blood returning to the body can make a child feel chilled; a favorite snack if the dietitian agrees; the same nurse where possible; and a consistent chair position. Teenagers frequently ask for privacy and headphones rather than play, and good units listen.
Parents’ own calm is part of the toolkit. Children read faces. A parent who knows the alarm sequence and has a plan for the cramps, from gentle leg stretching to asking the nurse to slow fluid removal, gives the child permission to relax.
Peritoneal dialysis for children: what a home exchange looks like
For families doing peritoneal dialysis, the session is a kitchen-table or bedside routine rather than a hospital visit, and it starts with hands. Handwashing is the single most effective defense against peritonitis, an infection of the abdominal lining, and training programs spend a surprising amount of time on it. Masks are worn during connection, pets are kept out of the room, and the catheter exit site is cleaned and re-dressed on a schedule set by the team.
There are two ways to run PD. In continuous ambulatory peritoneal dialysis (CAPD), a bag of warmed fluid is connected to the catheter and drained into the abdomen by gravity, left to dwell for several hours, then drained out into an empty bag. The NHS describes this as usually taking around 30 to 40 minutes per exchange, repeated about four times a day. In automated peritoneal dialysis (APD), a machine at the bedside performs the exchanges overnight, typically over eight to ten hours according to the NHS, so a child connects at bedtime and disconnects before school.
Monitoring at home mirrors what nurses do in a unit. Parents record weight, blood pressure and the volume drained versus the volume filled; a drained volume that is consistently lower than expected suggests fluid is being retained. The drained fluid should be clear. Cloudy fluid, especially with abdominal pain or fever, is the classic sign of peritonitis and means a same-day call to the unit.
Comfort here is about routine and dignity: a warm room, a consistent bedtime story while the machine primes, and, for older children, learning to do steps themselves so the treatment feels owned rather than imposed.
What to expect after a dialysis session
The first hour after hemodialysis is often the flattest part of the day. Fluid has been removed, blood chemistry has shifted, and the body is recalibrating. The NHS lists tiredness as the most common after-effect, and many children want a snack, a drink within their allowance and a nap. Some feel lightheaded on standing for a few hours, especially if blood pressure dipped during the run.
The access site needs a little attention. A fistula or graft is covered with a small dressing after the needles come out, and the family is asked to leave it in place for a set number of hours, usually until the next morning, then check that the site is dry and the thrill is present. Minor bruising is common; a swelling that grows quickly is not.
Headache, mild nausea and muscle cramps can trail into the evening. Gentle stretching and warmth help cramps, and the team may adjust the target weight or the rate of fluid removal at the next visit if these become a pattern. Itching is another recognized side effect, linked to phosphate and other waste products between sessions, and is managed through diet and prescribed treatment rather than over-the-counter guesswork.
Children on overnight PD usually wake with less of a post-treatment slump, because the process is gentler and daily. The main things to check in the morning are the exit site, the drained fluid and whether the machine logged any alarms.
Most children rebound within a few hours and are recognizably themselves by dinner. A child who is unusually drowsy, confused, breathless or bleeding from the access is a different matter, and the red flags in the final section apply.
The days and weeks between sessions: fluids, food, school and growth
Dialysis replaces a fraction of what healthy kidneys do, so the days between treatments carry rules. The most visible is fluid. Because a child on three-weekly hemodialysis has no way to remove water between sessions, the team sets a daily allowance based on urine output and target weight. Parents become experts in ice chips, small cups and the water content of soup and fruit.
Diet is the second pillar. Potassium, phosphate and salt are the usual concerns, and a pediatric renal dietitian translates lab results into real meals rather than a list of forbidden foods. Children on PD often have more room, because daily treatment clears waste steadily, and because they lose protein into the dialysis fluid and may need more of it. Feeding tubes are common in infants and toddlers, not as a failure but because appetite is often poor in kidney failure and growth depends on calories arriving reliably.
Growth itself is a treatment goal. The NIDDK notes that children with kidney failure often grow more slowly than their peers, and the team tracks height, weight and head circumference in infants at every review, adjusting nutrition, correcting anemia and, where indicated, discussing growth hormone treatment with the prescribing clinician.
School attendance is protected as far as possible. Many units schedule younger children in the morning and older students after lunch, provide letters for schools, and coordinate with hospital teachers. Vaccination catch-up, dental care and psychological support sit in the same review calendar.
Above all this runs the transplant pathway. For most children, dialysis is a bridge, and the weeks between sessions are also weeks of tissue typing, donor conversations and waiting-list paperwork.
How long can a child survive on dialysis? An honest answer
This is the question parents ask the search engine and rarely ask the doctor out loud. The candid answer is that no single number applies to an individual child, and this article will not invent one. Survival on dialysis depends on the cause of kidney failure, other conditions the child has, age at start, how well fluid and blood chemistry are controlled, how many infections occur, and whether and when a transplant becomes possible.
What the evidence does support is this. Dialysis in children is an established, decades-old treatment, and many children are sustained on it for years while they grow, attend school and wait for a kidney. Both the NIDDK and MedlinePlus describe dialysis as a treatment that keeps the body in balance when the kidneys fail; neither describes it as a treatment that restores kidney function. The NIDDK is equally clear that transplant is generally considered the preferred long-term treatment for children with kidney failure, because it frees them from the schedule and the dietary limits and supports better growth.
The realistic risks over years on dialysis are cardiovascular strain from fluid and blood pressure swings, infection related to access, bone and growth problems, and the emotional toll on the child and family. Teams work on each of these deliberately, and a child whose fluid is well managed, whose access stays healthy and whose transplant work-up is moving has a very different outlook from a child for whom those things are not true.
If you want a number, ask your child’s nephrologist directly. They know the diagnosis, the labs and the plan, and a good one will answer without either false comfort or bleakness.
Can a child recover from kidney failure?
Sometimes, and it depends entirely on why the kidneys failed. Kidney failure comes in two broad kinds, and conflating them causes a great deal of unnecessary despair and, occasionally, unrealistic hope.
Acute kidney injury is a sudden loss of function, often after severe dehydration, a serious infection, certain medicines, major surgery or a condition such as hemolytic uremic syndrome that follows some intestinal infections. The kidney tissue is stunned rather than destroyed. Children with acute kidney injury may need dialysis for days or weeks, and a proportion recover enough function to stop; the treating team monitors urine output and blood tests and withdraws dialysis when the kidneys demonstrate they can cope. Some are left with reduced function that needs long-term follow-up.
Chronic kidney disease is a gradual, usually permanent loss of function, most often in children from congenital abnormalities of the kidney and urinary tract, inherited conditions such as polycystic kidney disease, or long-standing glomerular disease. The NIDDK explains that damage from chronic kidney disease is generally not reversible. When it reaches kidney failure, the realistic goals are to manage the condition with dialysis and, for most children, to move to transplant. A transplanted kidney is a treatment, not a reversal; it requires lifelong medicines and monitoring, and it does not always last a lifetime, so some children go through more than one.
This is why the first weeks after a diagnosis involve so many tests. Establishing whether a child’s failure is acute, chronic, or acute-on-chronic changes everything about the plan. Ask the team which category applies and what evidence they are using to decide.
What people often get wrong about a pediatric dialysis session
Myth: dialysis is only for adults. Children of every age, including newborns, are treated with dialysis, and pediatric units adapt circuits, catheter sizes and fluid volumes to body weight. The NIDDK devotes a dedicated section to kidney failure in children precisely because the pathway differs.
Myth: the machine does everything a kidney does. Dialysis clears waste and fluid; it does not replace the kidney’s hormonal work, which is why children on dialysis are also managed for anemia, bone health and blood pressure through separate treatment plans set by their clinicians.
Myth: a beeping machine means an emergency. Most alarms are about line pressure or a moved arm. Serious events are rare and are caught by both machine safeguards and a nurse’s eye.
Myth: if my child feels fine, we can skip a session or loosen the fluid rules. Waste and fluid build silently. The consequences of a missed session show up as breathlessness, dangerous potassium levels or a much harder next run, not as instant symptoms.
Myth: peritoneal dialysis is a lesser treatment. PD is a first-line choice for many young children because it is gentler, needle-free and home-based. It has its own risks, chiefly peritonitis, which is why hygiene training is so intensive.
Myth: the numbing cream means the needle won’t be felt at all. A topical local anesthetic numbs skin, not the deeper vessel wall. Most children describe pressure rather than a sharp sting, and the sensation fades with repetition, but honesty beforehand builds more trust than a promise of nothing.
Myth: dialysis is forever. For most children it is a bridge to transplant, and for some with acute kidney injury it is a bridge to recovery of their own kidneys.
Questions to ask your care team
The best questions are specific to your child, but a short list carried into the first few appointments saves families from the frustration of remembering the important one in the parking lot.
- Is my child’s kidney failure acute, chronic or a mix, and what does that mean for how long dialysis may be needed?
- Why are you recommending hemodialysis or peritoneal dialysis for our child, and under what circumstances would you switch?
- What type of access is planned, when will it be placed, and how should we check it at home?
- How was the target weight set, and how often will it be reviewed as our child grows?
- Which side effects should we expect during and after a session, and which ones mean we should stop and call?
- What is the daily fluid allowance, and how do we count foods that are mostly water?
- Who is our dietitian, our social worker and our child life specialist, and how do we reach them between visits?
- How will school be coordinated, and can sessions be scheduled around exams or key lessons?
- Where are we on the transplant pathway, and what would move it forward?
- Who do we call at night or on a weekend, and what exactly counts as an emergency?
Write the answers down or ask permission to record them. Parents in the first month of dialysis are absorbing a new vocabulary, a new schedule and a new fear at once, and no team expects perfect recall.
Also ask what your child is allowed to decide. A six-year-old can choose which arm-side snack to bring; a fourteen-year-old may be ready to learn parts of a PD exchange. Shared control is one of the most reliable comfort measures there is.
When to call your doctor
Most sessions and most days between them pass without incident, but kidney failure narrows a child’s margin for error, and families are usually given a direct line to the dialysis unit for a reason. Use it. Nurses would far rather answer a question that turns out to be nothing than hear about a problem the next morning.
Call the unit or emergency services urgently for any of the following:
- Bleeding from a fistula, graft or catheter site that does not stop after firm pressure for ten minutes, or a rapidly enlarging swelling over the access.
- A fistula or graft with no thrill or bruit, or one that feels cold, hard or painful, which may mean a clot.
- Fever, chills or shaking, especially in a child with a central venous catheter, or redness, warmth, pus or pain at any catheter exit site.
- Cloudy peritoneal dialysis fluid, abdominal pain or a swollen, tender abdomen in a child on PD.
- Breathlessness, difficulty lying flat, sudden weight gain or swelling of the face, legs or eyelids, which can signal fluid overload.
- Muscle weakness, an irregular or very slow heartbeat, or palpitations, which can accompany high potassium.
- Confusion, unusual drowsiness, a seizure, severe headache, chest pain or fainting.
- Vomiting or diarrhea that prevents the child taking fluids or medicines, since both change fluid balance quickly.
- A missed or shortened session for any reason, so the team can reschedule and check blood chemistry.
Less urgent but still worth a same-day call: cramps or dizziness after every session, new itching or poor sleep, a child who is refusing food for more than a day, or a dressing that has come off and cannot be replaced cleanly at home.
Every decision about adjusting treatment, changing access or altering medicines belongs with the treating nephrology team. This article is a map of the territory; they hold the compass.
Frequently asked questions
How long is a dialysis session for a child?
In-center hemodialysis for children typically lasts around four hours, usually three times a week, according to the NHS and the NIDDK, though the team may adjust length and frequency for body size and blood results. Peritoneal dialysis runs differently: daytime exchanges take roughly 30 to 40 minutes each and are repeated several times a day, or a machine performs exchanges overnight over about eight to ten hours.
Is dialysis painful for kids?
The needle insertion for a fistula or graft is the main source of pain, and a topical local anesthetic cream applied beforehand reduces it to pressure for most children. Children with a central venous catheter or on peritoneal dialysis have no needles. During the run, cramps or lightheadedness can occur if fluid is removed quickly, and the nurse can slow the process when a child reports them.
What to expect after a dialysis session?
Tiredness is the most common after-effect, and many children want a snack and a rest in the first hour. Mild headache, nausea, cramps or feeling faint on standing can occur, especially if blood pressure dropped during treatment. The access dressing stays on until the next morning, and families check for bleeding and that the thrill is present. Most children feel like themselves within a few hours.
How long can a child survive on dialysis?
There is no single figure that applies to an individual child, and reputable sources do not offer one. Outlook depends on the cause of kidney failure, other health conditions, how well fluid and blood chemistry are controlled, access infections and whether a transplant becomes possible. Many children are sustained on dialysis for years while awaiting transplant, which the NIDDK describes as the preferred long-term treatment for most children.
How serious is going on dialysis?
Dialysis is started because the kidneys can no longer keep the body safe, so the underlying situation is serious by definition. The treatment itself is well established and closely monitored, and most sessions pass without incident. The main risks over time are low blood pressure during runs, access infection or clotting, peritonitis in peritoneal dialysis, and strain on the heart from fluid swings, all of which the team actively manages.
Can a child recover from kidney failure?
It depends on the cause. Acute kidney injury after dehydration, infection or certain illnesses is often reversible, and children may need dialysis only for days or weeks before their kidneys recover. Chronic kidney disease from congenital or inherited conditions is generally permanent; once it reaches kidney failure, it is managed with dialysis and, for most children, a kidney transplant. Your nephrologist can tell you which applies.
Can children do peritoneal dialysis at home?
Yes, and for infants and young children it is frequently the first choice, according to the NIDDK. After a period of training, parents perform the exchanges at home, or a machine performs them overnight while the child sleeps. The key responsibilities are strict handwashing, careful care of the catheter exit site, recording weights and drained volumes, and calling the unit promptly if the drained fluid turns cloudy.
Why does the dialysis machine keep beeping?
Most alarms relate to pressure in the blood lines and are triggered when a child bends the access arm, shifts position or the line kinks. The machine also alarms for air detection, temperature and flow changes, and it stops the blood pump automatically until a nurse checks and resets it. Serious events are uncommon, and children usually stop noticing the sounds within a few sessions.
How do I check my child's dialysis access at home?
For a fistula or graft, place your fingertips gently over the site once a day and feel for the buzzing thrill; its absence, or new pain, redness, swelling or coldness, needs an urgent call. Avoid blood pressure cuffs, blood draws and tight clothing on that arm. For a catheter, keep the dressing clean, dry and intact, and report any redness, discharge, fever or loose dressing the same day.
Will my child still be able to go to school on dialysis?
Usually yes. Many children’s units schedule younger children in the morning and students after lunch, provide hospital teaching during sessions and liaise with schools about attendance and exams. Children on overnight peritoneal dialysis often attend full days. Fatigue, appointments and fluid limits require some planning, and the unit’s social worker or child life specialist can help set up a school plan.
References
- NHS – Dialysis: What happens
- NIDDK (NIH) – Hemodialysis
- NIDDK (NIH) – Peritoneal Dialysis
- NIDDK (NIH) – Kidney Disease in Children
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Seeing a Doctor With Suspected Chickenpox: Call Ahead, Exposure History and What Is Examined
Before a chickenpox doctor visit, phone the office first so staff can keep a contagious patient away from pregnant people, newborns and others at…

Pediatric Surgery as an International Family: Planning the Stay, Companion and Follow-Up
Planning pediatric surgery abroad means coordinating three things with the treating team: a complete handover of medical records before travel, a companion arrangement so…

Before a Whooping Cough Appointment: Masks, Cough Pattern Notes and Vaccination Records
For a whooping cough doctor visit, bring vaccination records for the patient and household, a written note of when the cough began and how…

Reflux in Babies: Normal Spitting Up vs GERD
Reflux in babies is usually normal: most infants spit up milk after feeds because the muscle ring between the stomach and the esophagus is…

Enlarged Adenoids in Children: Snoring, Mouth Breathing and When Surgery Is Considered
Adenoids are a small pad of immune tissue behind a child's nose that often swells between ages three and seven and shrinks by the…

Is It Kawasaki Disease or Scarlet Fever? How Doctors Tell Fever-and-Rash Illnesses Apart
Kawasaki disease and scarlet fever can both cause several days of fever, a red rash, a strawberry tongue and later peeling skin, but they…