

Liposuction Alone or Gland Excision? How Gynecomastia Surgery Is Matched to Tissue Type

Key Takeaways
- Liposuction removes fat and excision removes gland; a cannula physically cannot extract the dense, rubbery disc that sits behind the nipple in true gynecomastia.
- Cleveland Clinic estimates roughly half to two-thirds of boys and men experience some degree of gynecomastia at some point in life.
- Mayo Clinic reports that pubertal gynecomastia usually resolves on its own within six months to two years, which is why surgeons typically ask teenagers to wait.
- Weight loss, including from GLP-1 medicines, can shrink fatty pseudogynecomastia but not glandular tissue, and may make an underlying gland more visible.
- The NHS lists thick scars, bleeding, fluid collections, uneven results and loss of nipple sensation as the specific risks of male breast reduction.
- Hormone-modulating medicines appear most useful only in the early, tender phase of gynecomastia; mature fibrous gland generally does not respond, according to Mayo Clinic.
Liposuction removes fatty tissue, while surgical excision removes the firmer glandular disc behind the nipple, so surgeons choose based on what the chest actually contains. Mostly fatty enlargement may be treated with liposuction alone, a distinct rubbery gland usually needs excision, and mixed tissue, the most common finding, is often treated with both. Skin excess, cause, age and weight stability also shape the plan, which the treating team decides with you.
He has been buying shirts a size up for eleven years. Not because they fit better, but because the drape hides a chest he stopped looking at in mirrors somewhere in his twenties. Now, sitting on paper in a consultation room, he is asked to lie back while a surgeon presses beneath his nipple with two fingers and says, almost to herself, “There’s gland here.”
That moment is where the real question of gynecomastia liposuction vs excision gets answered, and it has very little to do with which operation sounds gentler or which one a friend had. It has to do with what the tissue is made of. Fat and gland feel different, behave differently under a surgical instrument, and respond differently to weight change, medicines and time.
This explainer walks through how surgeons read a chest, why one man leaves with two tiny suction ports and another with a curved scar along the areola, what the weeks afterward usually look like, and which of the popular beliefs about this surgery do not survive contact with the evidence.
Gynecomastia liposuction vs excision: why the decision starts with a pinch
Ask a surgeon how they choose between the two operations and the honest answer is unglamorous: they pinch. Taking the tissue beneath the nipple between thumb and fingers, they feel for what is there. Fat is soft and slides. Glandular tissue is firmer, rubbery, often shaped like a flattened disc anchored directly behind the areola, the darker circle of skin around the nipple. Those few seconds of touch say more about gynecomastia liposuction vs excision than any brochure could.
Gynecomastia is enlargement of breast tissue in boys and men, driven by growth of milk-duct and supporting gland tissue rather than fat alone. Mayo Clinic describes the usual trigger as a shift in the balance between estrogen and testosterone effects on the breast, which is why it appears at hormonally busy times: infancy, puberty and later adulthood as testosterone naturally declines. Cleveland Clinic estimates that roughly half to two-thirds of boys and men experience some degree of it at some point, making it one of the least discussed common conditions in men’s health.
The mechanical point matters. A liposuction cannula, the thin hollow tube used to suction fat, glides through soft fat but skids off dense gland. Pushing harder does not help; it bruises surrounding tissue and leaves the firm core in place. Excision, the surgical removal of tissue through an incision, does the opposite job well and the fat-shaping job poorly, because it cannot blend a broad area of the chest the way suction can.
My view, after reading the guidance and listening to people who have lived through both, is that tissue type is the whole story. The technique is simply the tool matched to it. Skin elasticity is the third variable, and it gets its turn below, but fat versus gland decides the first move.
Pseudogynecomastia vs gynecomastia: fat, gland or both?
Two chests can look identical under a T-shirt and contain completely different tissue. Pseudogynecomastia is chest fullness made of fat with no real enlargement of the gland; Mayo Clinic lists it among the conditions that mimic true gynecomastia. It tends to travel with higher overall body weight, feels uniformly soft and lacks the distinct firm lump beneath the nipple. True gynecomastia has that lump, sometimes tender, sometimes coin-sized, sometimes larger, and it can occur in lean, athletic men who carry almost no fat anywhere else.

Most adults who consult a surgeon fall somewhere between: a modest disc of gland surrounded by a cushion of fat that exaggerates it. That mixed picture is why combined techniques exist, and why “which operation do I need?” rarely has a one-word answer before an examination.
Clinicians sort the picture with their hands first. Lying flat, the tissue is pressed and rolled; gland resists in a way fat does not. If the exam is unclear, or if anything is unusual such as one-sided enlargement, a hard irregular mass or nipple discharge, ultrasound or mammography may be used, as both Mayo Clinic and Cleveland Clinic describe. Imaging is not routine for every case. It is a tool for uncertainty and for ruling out the rare but real possibility of male breast cancer.
Why does the distinction matter so much to you? Because it predicts what non-surgical steps can do. Fat responds to changes in body weight. Gland does not, and weight loss can actually make an existing gland more prominent as the padding around it shrinks. Knowing which one you have saves months of chasing a result the tissue cannot deliver.
How liposuction for gynecomastia actually works
Liposuction is the removal of fat through suction. For the chest, the sequence is fairly standard. The surgeon marks the area while the patient stands, because gravity and posture change how a chest hangs. Under general anesthesia, or occasionally local anesthesia with sedation depending on the surgeon’s assessment, one or two incisions of a few millimeters are made, typically at the edge of the areola or in the fold near the armpit where scars sit in a natural crease.
Through these openings a tumescent solution is infiltrated. That word simply means the fat is swollen with a large volume of dilute salt water containing local anesthetic and a medicine that narrows blood vessels; the swelling separates fat cells and limits bleeding and bruising. Then the cannula goes in and the surgeon works it back and forth in a fan pattern, suctioning fat from the whole chest wall rather than just the mound, so the result blends into the shoulder and ribs without a shelf.
Some surgeons use cannulas that vibrate or deliver ultrasound energy to loosen firmer fat before suction. These are variants of one procedure rather than separate operations, and mainstream sources such as the NHS describe liposuction as a single technique with several ways of performing it. No variant reliably removes true glandular tissue.
What liposuction does well: reduce the fatty component, refine the contour and feather the edges so the chest reads as a chest rather than a flat patch. What it does poorly: extract the dense disc under the nipple, and tighten skin that has been stretched for years. The NHS is explicit that liposuction removes fat but does not tighten loose skin, a limitation that grows more obvious the more volume comes out.
What gynecomastia gland removal involves
Excision means cutting tissue out. For gynecomastia, the classic approach is a periareolar incision, a curved cut placed along the border where the darker areola meets paler chest skin, usually across its lower half. That boundary hides a scar well because the color change already draws the eye away from a thin line.
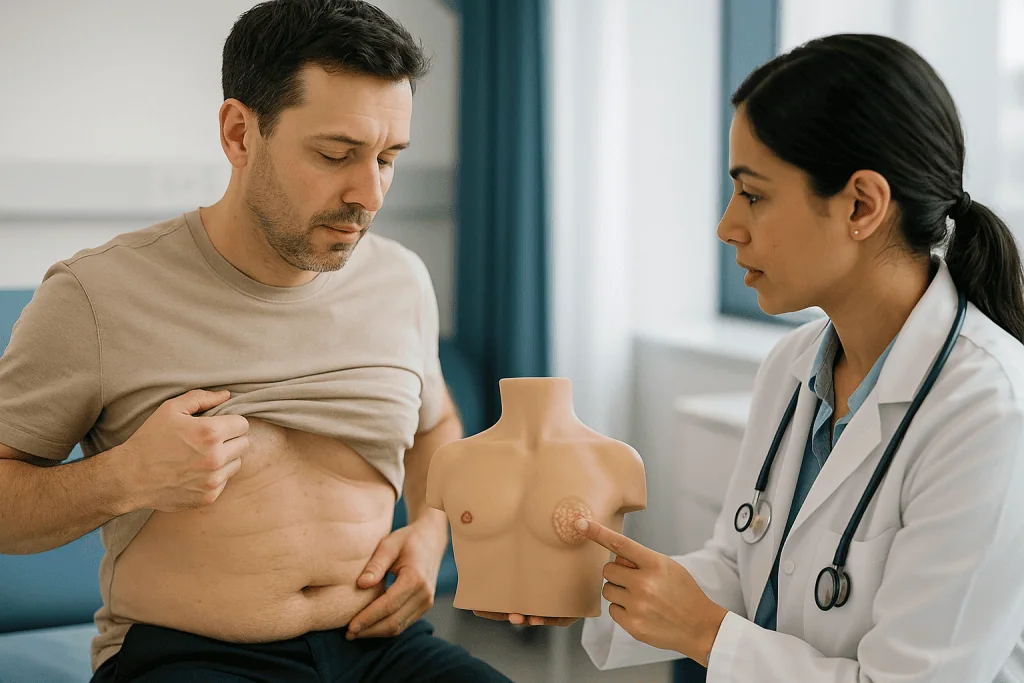
Through that opening the surgeon lifts the nipple-areola complex, identifies the firm gland beneath and frees it from the surrounding fat and from the muscle below. The disc comes out whole or in sections. The critical judgment is how much to leave. Take everything and the nipple can sink into a hollow; leave too much and the bulge persists. Surgeons deliberately preserve a thin cushion of tissue directly beneath the areola so it stays level with the surrounding chest.
Where skin has been stretched significantly, gland removal alone leaves a deflated envelope. Larger reductions may add skin excision, removing a ring of skin around the areola or, in the largest cases, using longer incisions and repositioning the nipple, as the NHS describes for male breast reduction. Those scars are more visible, and that trade-off belongs in the pre-operative conversation, not the post-operative one.
A small drain, a soft tube that lets fluid escape for a day or two, is sometimes placed after excision when the cavity left behind is large. The NHS describes the operation as taking roughly 90 minutes under general anesthetic, with many people going home the same day or after one night. Removed tissue is commonly sent to a pathology laboratory for examination, a routine step rather than a sign of concern.
Why many patients get both: the combined technique
Read a typical operating note for adult gynecomastia and you will often find both techniques on the same page. The logic is simple. Liposuction goes first, thinning the fatty component across the chest and revealing where the gland actually ends. With the fat gone, the firm disc stands out clearly and can be compared against what the surgeon felt in clinic.
Then a small periareolar incision is made and the gland is removed. Some surgeons use what is called a pull-through technique, drawing the gland out through the same tiny opening used for the cannula, which keeps the scar to a few millimeters. Others prefer the longer half-circle incision for a wider view. Both are accepted approaches; the choice reflects the size and firmness of the gland and the surgeon’s training.
Contour is the reason this combination has become routine. Excision alone tends to leave a step, a visible ledge where the removed disc met untouched fat. Liposuction alone leaves a residual lump. Doing both allows the surgeon to remove what must be removed and then blend everything around it, so the chest presents one smooth surface rather than a patch with an edge.
Not everyone needs both. A young, lean man with a purely glandular button may have excision only. An older man whose enlargement is nearly all fat, with good skin recoil, may have liposuction only. The combined plan is the most common answer to the most common presentation, not a default applied to everyone.
What matters for you is that the plan is described before surgery in terms of tissue: how much fat, how much gland, how much skin, and which tool addresses each. If a consultation ends with a technique name but no explanation of why your chest suits it, asking for that explanation is entirely reasonable.
Gynecomastia liposuction vs excision at a glance
Comparison tables flatten nuance, but this one earns its place because it puts the decision in the language surgeons actually use: what is the tissue, and what is the tool.
| Feature | Liposuction alone | Gland excision alone | Combined |
|---|---|---|---|
| Tissue addressed | Fat | Firm glandular disc | Fat and gland |
| Typical presentation | Soft, diffuse fullness; pseudogynecomastia | Small firm button in a lean chest | Mixed fat and gland, the most common adult picture |
| Incision | One or two openings of a few millimeters at the areola edge or armpit fold | Curved cut along the lower areola border | Both, or a single small opening with pull-through |
| Skin tightening | Minimal; relies on natural recoil | Minimal unless skin is also removed | Minimal unless skin is also removed |
| Main limitation | Cannot remove dense gland | Cannot blend a broad area; risk of a visible step | Longer operation; more tissue disturbed |
| Drains | Rarely | Sometimes | Sometimes |
| Anesthesia | General, or local with sedation | Usually general | Usually general |
Two things the table cannot show. First, skin quality overrides every row above. A chest with excellent recoil can lose a surprising amount of volume and shrink to fit; a chest stretched over many years or after large weight loss may need skin removal regardless of which technique handles the volume. Second, cause matters. If gynecomastia is being driven by an ongoing medicine, anabolic steroid use or a hormonal condition, removing tissue treats the effect and leaves the engine running. Mayo Clinic’s guidance is clear that identifying and addressing an underlying cause comes before deciding on surgery.
Read across the rows and a pattern emerges: none of the three is “better.” Each is correct for the chest it was designed for and wrong for the others.
Who is usually a candidate, and who is asked to wait
The people most often offered surgery share a few features. Their gynecomastia has been present and stable for a long stretch, so it is unlikely to shrink on its own. Their weight has been steady for months. Any reversible cause has been looked for and, where found, dealt with. They understand the goal is a flatter, more masculine contour rather than a guaranteed shape, and they are in reasonable general health for an anesthetic.
Adolescents are the group most frequently asked to wait. Mayo Clinic notes that gynecomastia appearing at puberty typically resolves without treatment within six months to two years. Operating early risks removing tissue that would have regressed, and a chest still growing can change around the surgical result. Surgeons generally prefer to see stability and often defer until the later teen years, with exceptions for severe or distressing cases decided with the young person, their family and, where relevant, an endocrinologist, a hormone specialist.
Men in the middle of losing or gaining weight are usually asked to reach a plateau first, because the fat-to-gland ratio, and therefore the plan, shifts as the body changes. Anyone using anabolic steroids or other body-building compounds is generally asked to stop and stabilize, since ongoing use both causes gynecomastia and predicts recurrence. Those on a prescribed medicine linked to breast enlargement are referred back to the prescriber to discuss options; the surgeon does not change that prescription, and neither should the patient without advice.
People with untreated liver, kidney or thyroid disease, or with signs pointing toward a testicular or hormonal tumor, are investigated and treated for that first. Smokers are commonly advised to stop before surgery because nicotine impairs wound healing, advice that appears throughout NHS cosmetic surgery guidance. None of these are refusals. They are sequencing decisions that make the eventual operation more likely to hold.
What happens before surgery: ruling out a cause
A good consultation spends as much time on why as on what. Mayo Clinic lists a long roster of medicines associated with gynecomastia: anti-androgens used for prostate conditions, anabolic steroids, some HIV treatments, certain anti-anxiety and antidepressant medicines, some antibiotics, ulcer medicines, several heart medicines and some chemotherapy agents. Alcohol in excess, cannabis and heroin appear on the same list, as do some herbal products containing tea tree or lavender oil.
The clinician takes a medication and supplement history, asks about timing and tenderness, and examines not only the chest but the abdomen for liver signs and the testicles for lumps or asymmetry. Blood tests may check liver, kidney and thyroid function along with testosterone and estrogen-related hormones. These are not hoops. A hormonal cause found here can change the whole plan, sometimes making surgery unnecessary and occasionally revealing something more important than the chest.
Imaging follows the exam only when it adds information. Mayo Clinic describes mammography, ultrasound and, less often, CT or MRI as options when the diagnosis is uncertain or findings raise concern. Male breast cancer is uncommon, but features such as a hard one-sided lump, fixation to skin, dimpling, nipple discharge or enlarged nodes under the arm are the reasons a surgeon pauses to investigate rather than books a date.
Then comes the frank part. The surgeon photographs the chest, grades the enlargement and skin excess using a standard clinical scale, and explains which tissue is which. Expect discussion of scar placement, the possibility of asymmetry, temporary numbness and the small chance of a revision. Consent is a conversation, not a signature, and you are entitled to leave and think it over.
Gynecomastia surgery recovery time: the first days and weeks
The first evening is mostly about tightness. A compression garment, an elastic vest that presses the chest flat, goes on in the operating room and stays on for several weeks except for washing; the NHS recommends wearing one to reduce swelling and support the new contour. Discomfort is usually described as soreness and bruising rather than sharp pain, managed with whatever your surgical team prescribes or advises.
Bruising and swelling peak over the first few days and then fade. If a drain was placed after excision, it typically comes out within a day or two. Dressings are small. Showering is often allowed within a couple of days, though rules vary by surgeon and stitch type, so the written instructions you are given take precedence over anything here.
The NHS advises that most people take around a week or two off work after male breast reduction and avoid strenuous activity, heavy lifting and vigorous exercise for several weeks, commonly in the range of four to six, until the tissues have knitted. Walking is encouraged from day one because movement lowers the risk of blood clots. Driving resumes when you can perform an emergency stop without pain and are no longer taking sedating medicines.
Numbness around the nipple is common early and usually improves over weeks to months, though the NHS notes some change in sensation can be permanent. Scars are pink and slightly raised at first and mature to paler, flatter lines over roughly a year. The chest itself keeps changing: the NHS describes final results settling over several months as swelling fully resolves and skin redraws to the new volume. Liposuction-only recoveries tend to involve fewer wound-care steps than excision with skin removal, but the garment and exercise restrictions are similar across techniques.
Risks and trade-offs, in plain clinical terms
Every operation trades a problem you have for a smaller set of problems you might get. The NHS lists the specific risks of male breast reduction as thick, obvious scars; bleeding; a collection of fluid under the skin; uneven results between sides; and loss of nipple sensation. General surgical risks apply too: infection, a reaction to anesthesia, and blood clots in the legs or lungs.
Two terms deserve translation. A seroma is a pocket of clear fluid that gathers where tissue was removed; it may need to be drawn off with a needle in clinic. A hematoma is a collection of blood in the same space, which can develop quickly in the first day or two and sometimes requires a return to the operating room. Compression garments and, in some cases, drains exist largely to reduce these two events.
Contour problems are the risk specific to this decision. Liposuction alone in a chest that contained gland leaves a persistent lump. Over-aggressive excision leaves a saucer-shaped dip beneath the nipple, sometimes called a crater deformity, which is harder to correct than under-treatment. Uneven fat removal produces ripples or a shelf at the edges. Skin that does not recoil may hang, requiring a later skin-tightening procedure.
Recurrence is possible when the driver persists, whether that is continued anabolic steroid use, an ongoing medicine, significant weight gain or a hormonal condition that went unidentified. Tissue that was fully removed does not grow back, but neighboring tissue can enlarge under the same stimulus.
Alternatives include watchful waiting, addressing weight, changing a causative medicine with the prescriber’s agreement, or hormone-modulating medicines in selected early cases. Each carries its own trade-offs, and the surgeon’s job is to lay them alongside surgery rather than in its shadow.
Can weight loss, hormone drugs or GLP-1 medicines replace surgery?
The most-searched version of this question involves glucagon-like peptide-1 receptor agonists, the injectable class that includes semaglutide, developed for diabetes and weight management. The mechanism is straightforward: they slow stomach emptying, increase feelings of fullness and reduce food intake, and the resulting weight loss reduces fat stores throughout the body, including the chest. For someone whose fullness is largely pseudogynecomastia, that fat reduction can make a visible difference.
The limit is equally clear. Glandular tissue is not fat. It does not shrink because calorie intake falls, and as the fat around it thins the disc can become more noticeable, not less. No mainstream guideline lists GLP-1 medicines as a treatment for gynecomastia, and they carry their own side effects and prescribing criteria. Whether one is appropriate for you is a decision for your own clinician based on your overall health, not on your chest.
Hormone-modulating medicines are a different conversation. Mayo Clinic describes two classes sometimes used: selective estrogen receptor modulators, which block estrogen’s effect on breast tissue, and aromatase inhibitors, which reduce the conversion of testosterone to estrogen. Both are approved for other conditions and are used for gynecomastia outside their formal indication. Mayo notes they appear most useful in the early, tender, actively growing phase and much less so once tissue has matured into firm, fibrous gland. Many adult men seeking surgery are well past that window.
Exercise deserves an honest word. Building the pectoral muscles firms the platform beneath the breast and can improve overall chest shape, but muscle sits under the gland, not in place of it. Strength training will not remove glandular tissue, and no evidence supports creams, supplements or “gyno pills” sold online. A product that promises to dissolve gland is promising something the biology does not allow.
What people often get wrong about gynecomastia surgery
The first myth is that liposuction is the gentle option and excision the serious one, so everyone should try liposuction first. In a chest with real gland, liposuction first simply means two operations. The right first move is the one matched to the tissue.
The second is that gynecomastia always signals low testosterone. It can, but Mayo Clinic frames the cause as an altered ratio between estrogen and testosterone activity, which can arise with normal hormone levels during puberty, with aging, with medicines, with liver or kidney disease, or for no identifiable reason at all. A blood test showing normal testosterone does not mean the chest is “just fat.”
Third: that scars are invisible. Periareolar scars hide well and liposuction ports are tiny, but they exist, they are pink for months, and in some skin types they thicken. Skin-removal scars are longer and more visible. Anyone promising no scar is describing a procedure that does not exist.
Fourth, the celebrity question. Search engines overflow with queries about whether a particular actor or athlete had this surgery. Several public figures have spoken openly about gynecomastia, and their candor has helped normalize a condition many men hide. Their stories are personal accounts rather than medical evidence, and their chests, training histories and possible steroid exposures are not yours. The useful takeaway is that it is common and treatable, not which technique a famous person had.
Fifth, that recovery is brutal. Most people describe soreness and the tedium of a compression vest rather than severe pain, and the NHS timelines are measured in weeks, not months of incapacity. Sixth, that it always comes back. Fully excised gland does not regenerate; recurrence generally tracks a persisting cause. Address the cause along with the tissue and the picture changes, though no surgeon can promise a permanent result.
Questions to ask your care team
Consultations are short, and the questions you forget are the ones that nag afterward. Bring a written list. These are the ones experienced patients wish they had raised.
- Based on your examination, roughly how much of my enlargement is fat, how much is gland and how much is stretched skin?
- Which technique are you recommending for each component, and what would change your mind on the day?
- Have we looked for a cause, including my medicines, supplements and hormones, and is there anything I should address before surgery?
- Where exactly will the incisions be, how long, and how do scars usually mature in skin like mine?
- Will I have a drain, and how long will I wear a compression garment?
- What are the specific risks of a dip under the nipple or a visible step, and how do you guard against them?
- If the result is uneven or a lump remains, what is your approach to revision?
- What is the typical timeline in your practice for returning to desk work, lifting and training, and what would make you extend it?
- Will the removed tissue be sent for pathology?
- Who do I contact after hours if something feels wrong, and which signs mean I should call immediately?
Listen for answers phrased in terms of your tissue rather than a fixed package. A surgeon who says “I do liposuction for everyone” or “I always excise” is describing a habit, not an assessment. You are also entitled to ask about training, how often this specific operation is performed and what happens if a complication arises, then take the information away and decide later. The decision is yours to make with the treating team, at a pace that suits you rather than the appointment calendar.
When to call your doctor
Before any surgery, some findings are not cosmetic questions and should prompt an early appointment rather than a wait-and-see plan. Mayo Clinic and Cleveland Clinic both flag a hard lump on one side only, especially if it feels fixed or irregular; nipple discharge, particularly if bloody; skin dimpling, puckering or ulceration over the breast; swollen lymph nodes under the arm; and a lump or change in a testicle. Rapid enlargement over weeks, or gynecomastia beginning alongside unexplained weight loss, fatigue or yellowing of the skin, also warrants review because it can point to a hormonal, liver or testicular cause.
After surgery, most days are quiet. A few signs are not. Call your surgical team the same day, or seek emergency care if you cannot reach them, for:
- Swelling on one side that increases quickly, becomes tense or is much larger than the other, which may indicate bleeding beneath the skin
- Spreading redness, warmth or increasing pain around an incision, or fluid that is cloudy, foul-smelling or pus-like
- Fever or chills
- An incision that opens or edges that separate
- Skin over the nipple or areola turning dusky, purple or black
- Calf pain, swelling or tenderness in one leg
- Sudden shortness of breath, chest pain or coughing up blood, which can signal a clot in the lungs and is an emergency
- Persistent vomiting or inability to keep fluids down after anesthesia
Anything that worries you between scheduled visits is a reason to phone, even if it is not on this list. Surgical teams would far rather field a call about a mild concern than see a delayed problem. Keep the after-hours number somewhere you can find it in a hurry, and make sure whoever is helping you at home knows where it is too.
Frequently asked questions
Is liposuction effective for gynecomastia?
Liposuction is effective for the fatty component of gynecomastia and for pseudogynecomastia, where fat is the whole problem. It is not effective against true glandular tissue, which is too dense for a suction cannula to remove. In mixed cases, surgeons commonly combine liposuction for contour with excision of the gland through a small incision. Whether liposuction alone is right for you depends on what your surgeon feels on examination, not on the technique’s general reputation.
Did Dwayne Johnson have gyno surgery?
The actor has spoken publicly in interviews about having gynecomastia surgery earlier in his life, though the medical details are his own and not something this article can verify. Celebrity accounts have helped normalize a very common condition, but they are personal stories rather than clinical evidence. Which technique suited a famous person’s chest, training history or hormonal picture says nothing about which technique suits yours; only an examination can answer that.
How bad is gynecomastia surgery recovery?
Most people describe soreness, tightness and bruising rather than severe pain, plus the tedium of wearing a compression vest for several weeks. The NHS advises taking around a week or two off work and avoiding strenuous exercise for several weeks, and notes that swelling can take months to settle fully. Numbness around the nipple is common early and usually improves. Excision with skin removal involves more wound care than liposuction alone, but timelines are broadly similar.
Can semaglutide or other GLP-1 medicines get rid of gynecomastia?
They can reduce fatty pseudogynecomastia by lowering overall body fat, but they do not shrink glandular tissue, which is not fat and does not respond to calorie reduction. As surrounding fat thins, an existing gland can become more noticeable. No mainstream guideline lists GLP-1 medicines as a treatment for gynecomastia. Any decision about these medicines rests with your prescribing clinician and your broader health, not with your chest contour.
How can I tell pseudogynecomastia vs gynecomastia?
Pseudogynecomastia feels uniformly soft, with no distinct lump, and usually accompanies higher body weight. True gynecomastia has a firm, rubbery disc directly behind the nipple that may be tender and can occur in lean men. Mayo Clinic notes that clinicians distinguish the two by examination, adding ultrasound or mammography when the picture is unclear or a feature raises concern. Self-assessment is unreliable, so an in-person exam is the practical route.
What is the gynecomastia surgery recovery time before I can lift weights again?
The NHS advises avoiding strenuous activity, heavy lifting and vigorous exercise for several weeks after male breast reduction, commonly around four to six, while the tissues heal and the risk of bleeding or fluid collection falls. Light walking is encouraged from the first day. Your surgeon may extend or shorten that window based on how much tissue was removed and how your healing looks at follow-up, so treat their written instructions as the final word.
Does gynecomastia gland removal leave a visible scar?
Yes, though the standard periareolar incision runs along the border of the areola, where the color change camouflages a thin line well. Scars are pink and slightly raised for months and mature to paler, flatter lines over roughly a year. The NHS lists thick, obvious scarring among the risks, and it is more likely in some skin types and with longer skin-removal incisions. Anyone promising no scar is describing a procedure that does not exist.
Can gynecomastia come back after liposuction or excision?
Fully removed glandular tissue does not regenerate, but neighboring tissue can enlarge if the underlying driver persists. Common drivers include ongoing anabolic steroid use, a causative prescribed medicine, significant weight gain or an unidentified hormonal or liver condition. This is why surgeons look for a cause before operating and why stabilizing weight matters. Removing tissue treats the effect; addressing the cause reduces the chance of it returning, though no surgeon can guarantee permanence.
Will I lose nipple sensation after gynecomastia surgery?
Temporary numbness or altered sensation around the nipple is common after both liposuction and excision, and most people notice gradual improvement over weeks to months as small nerves recover. The NHS lists loss of nipple sensation among the recognized risks and notes that in some cases the change is permanent. Excision, which works directly beneath the nipple, carries a somewhat higher chance than liposuction alone, something worth raising with your surgeon beforehand.
Can teenagers have liposuction for gynecomastia?
Usually not right away. Mayo Clinic reports that pubertal gynecomastia typically resolves without treatment within six months to two years, so operating early risks removing tissue that would have regressed and a still-growing chest can change around the result. Surgeons generally wait for stability, often into the later teen years, with exceptions for severe or distressing cases decided jointly with the young person, their family and sometimes an endocrinologist.
References
- Cleveland Clinic – Gynecomastia (Enlarged Male Breast Tissue)
- MedlinePlus – Breast enlargement in males
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

Planning This Treatment in Turkey
Our full guide for international patients: techniques, hospital stay, recovery and cost.
More from the Blog

Breast Imaging Around Fat Transfer: Why Scans Are Taken First and Reviewed Later
A mammogram after fat transfer is usually arranged so radiologists can compare the new images with a baseline scan taken before surgery. Grafted fat…

Gynecomastia Surgery Prep: Smoking, Supplements and the Tests Booked Beforehand
Preparing for gynecomastia surgery usually means stopping all nicotine for the period your surgeon sets, giving the team a complete list of medicines and…

How Does the Chest Settle After Gynaecomastia Treatment? Results Over the First Months
After gynaecomastia treatment, the chest settles in stages rather than all at once. Swelling and bruising are most noticeable in the first one to…
Combined Procedures in Breast Aesthetics: When a Lift and Implants Happen in One Operation
A combined breast lift and augmentation, also called augmentation mastopexy, reshapes and raises sagging breast tissue while placing an implant for volume, all under…

Reading a Breast Aesthetics Surgical Plan: Measurements, Options and Questions to Raise
A breast aesthetics surgical plan usually lists your chest and breast measurements, the surgeon's proposed technique, and the alternatives that were considered. Reading it…

Preparing for Breast Augmentation: Imaging, Medication Review and the Final Sizing Visit
Preparing for breast augmentation usually involves three steps spread over several weeks: a baseline breast imaging review if you are of screening age or…