

Reading a Breast Aesthetics Surgical Plan: Measurements, Options and Questions to Raise

Key Takeaways
- Base width, sternal-notch-to-nipple and nipple-to-fold distances are the three measurements that most often decide between an implant, a lift or a reduction.
- The 45-55 breast rule is an average preference from photograph ratings, useful for describing the shape you want but not a clinical requirement or a predictor of outcome.
- Mayo Clinic and the NHS both state that breast implants are not lifetime devices, so a realistic plan mentions the likelihood of future revision, removal or replacement.
- A free nipple graft in a large reduction usually means loss of nipple sensation and of the ability to breastfeed, which makes it a line to question directly on any plan.
- Nicotine narrows blood vessels during the weeks of healing, which is why smokers and vapers are commonly asked to stop well before surgery and stay stopped through recovery.
- Sudden one-sided swelling, a dusky or pale nipple, fever with spreading redness, or chest pain and breathlessness are red flags that need a same-day call or emergency care.
A breast aesthetics surgical plan usually lists your chest and breast measurements, the surgeon's proposed technique, and the alternatives that were considered. Reading it well means checking that each number, such as base width or nipple-to-fold distance, connects to a specific decision, and that risks, recovery time and reasons to wait are written down. Useful consultation questions ask why this option, what else was considered and what would change the plan.
The folder comes home in a tote bag. Inside are two pages of measurements in millimeters, a diagram with dotted lines, a paragraph headed “proposed procedure” and a signature line that still feels a long way off. Most people read it once at the kitchen table, understand about half of it, and then put it in a drawer.
That is a shame, because the surgical plan is the most honest document in the whole process. It records what the surgeon saw, what they measured, what they are proposing and, if it is written properly, what they are not proposing and why. It is also the best starting point for breast aesthetics consultation questions, because it turns a vague “I want them smaller” or “I want them fuller” into specific decisions you can ask about.
This article walks through a typical plan line by line: the numbers, the options for augmentation, lift and reduction, the reasons a surgeon might ask you to wait, and the questions that tend to matter most once the appointment is over.
What actually happens when a breast aesthetics surgical plan is written
A surgical plan is not written in the operating room. It is assembled during and after the consultation, from three sources: what you say you want, what the surgeon measures and photographs, and what your medical history allows. Understanding that sequence explains why the document reads the way it does.
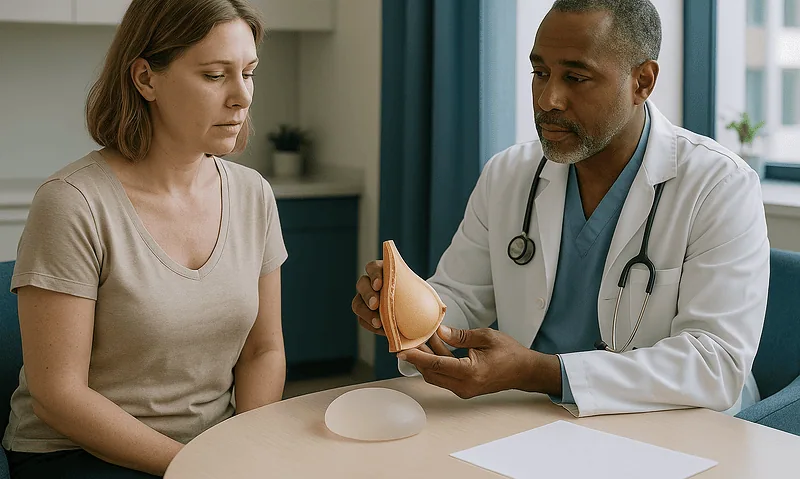
The conversation usually opens with your goals, in your own words. A good surgeon will translate “I want to fill out a swimsuit” or “my bra straps cut into my shoulders” into something measurable, because size language is unreliable; cup sizes vary between manufacturers and a “C cup” on one chest is a different volume on another. Mayo Clinic notes that this expectation-setting conversation, including what surgery can and cannot change, is a standard part of planning for breast augmentation, breast lift and breast reduction alike.
Next comes the examination. The surgeon measures the chest wall and both breasts separately, notes any difference between the two sides, checks skin quality and how much breast tissue sits above and below the nipple, and looks at the position of the nipple relative to the fold beneath the breast. Standardized photographs are taken from several angles. None of this is ceremony; each measurement rules options in or out.
Only then is a procedure proposed. The plan should state the technique, the alternatives that were considered, the incision sites, the expected scar pattern and the main risks discussed. It may include a sizing session for implants or a sketch of where tissue would be removed in a reduction. If your plan lacks any of those elements, that gap is itself one of the first breast aesthetics consultation questions to raise: what was considered and rejected, and on what grounds?
The measurements on the page and what each one means
Numbers on a breast plan look intimidating mainly because nobody explains them. Most fall into a short list, and each one drives a specific decision.
| Measurement | Plain meaning | Why it changes the plan |
|---|---|---|
| Base width | How wide the breast footprint is across the chest | An implant wider than the base tends to look unnatural and can cause the breasts to merge; it caps the implant size range |
| Sternal notch to nipple | Distance from the dip at the top of the breastbone to the nipple | Longer distances suggest the nipple sits low, pointing toward a lift or reduction rather than volume alone |
| Nipple to inframammary fold | Distance from nipple to the crease under the breast | Indicates how stretched the lower skin is and how much lower pole is available for an implant to sit behind |
| Skin pinch thickness | How much soft tissue covers the upper chest | Thin cover makes implant edges and rippling more visible and may steer placement behind the muscle |
| Ptosis grade | How far the nipple has descended relative to the fold | Determines whether a lift is needed and which scar pattern would be required |
| Asymmetry notes | Differences in volume, nipple height or fold position between sides | Nearly everyone has some; the plan should say how each difference will be handled |
Ptosis is the medical word for sagging, graded by where the nipple sits compared with the fold. Rippling means visible wrinkles in an implant shell showing through thin tissue. If either term appears on your plan without a grade or a number next to it, ask for one.
The point of reading these lines is not to second-guess the surgeon’s arithmetic. It is to confirm that each choice in the plan traces back to a measurement, and that the two sides of your chest were measured and planned separately, because they are almost never identical.
What is the 45-55 breast rule, and should it be on your plan?
The “45-55 rule” is a proportion, not a regulation. It comes from a published study in which a group of observers rated photographs of breasts and, on average, preferred a shape where roughly 45 percent of the breast volume sat above the nipple and 55 percent below, with the nipple angled slightly upward and a gently sloping upper pole. Some surgeons use it as a design target when planning implant size, placement or the amount of lift.
Two things are worth knowing before you ask about it. First, it is a preference finding, drawn from what observers found attractive in images. It is not an outcome measure, and it does not predict complications, sensation, breastfeeding or how you will feel about your own body. Second, it describes an average taste. Plenty of people prefer a fuller upper pole, and plenty prefer a more natural, lower-full shape; neither is wrong.
So should it appear on your plan? Not necessarily by name. What matters is that the plan states a shape goal in some concrete way: where the nipple should sit after surgery, how much upper fullness is intended, and how the surgeon expects the breast to settle as swelling goes down. If your surgeon references the 45-55 proportion, a fair follow-up is: “Is that the shape I said I wanted, or a default?” If they do not mention it, you lose nothing; the proportion is one framework among several.
The 45-55 breast rule is most useful as a conversation tool. It gives you vocabulary for describing upper-pole fullness and nipple position, which is exactly where patient wishes and surgical plans most often drift apart. Use it to make your preference explicit, and then let the measurements decide what is achievable on your frame.
Breast augmentation consultation questions: what the surgeon will ask you
People prepare a list to ask the surgeon and forget that the surgeon has a list too. Knowing what is coming lets you answer accurately, and the accuracy of those answers shapes the plan more than any sizing session.
Expect detailed questions about medical history. Mayo Clinic lists bleeding disorders, previous breast surgery, family history of breast cancer and current medicines, including supplements, as topics a surgeon needs to review before augmentation. Smoking and vaping come up because nicotine narrows blood vessels and slows wound healing; the NHS advises stopping well before any cosmetic surgery, and many surgeons make it a condition. Any history of blood clots, diabetes or autoimmune disease will be explored because each affects healing or anesthesia risk.
Then come the life questions. Are you planning pregnancy or breastfeeding? Has your weight been stable? What do you do for work and exercise? An ironworker, a competitive swimmer and someone who works at a desk will get different advice about implant placement and time off, because heavy overhead lifting and chest-muscle use interact with implants placed behind the muscle.
Finally, the goal questions, which are the hardest to answer well. What bothers you now: volume, shape, position, symmetry? What would “too big” look like? Have you brought photographs of results you like and, just as usefully, results you dislike? Mayo Clinic specifically encourages patients to be clear about expectations and to ask what the surgeon can realistically achieve.
One more question you may be asked, gently: why now? It is not a test. Surgeons are trained to listen for pressure from a partner, recent life upheaval or a hope that surgery will fix something it cannot. Honest answers here protect you.
Reading the implant options: placement, incision, fill and shape
An augmentation plan usually contains four choices, sometimes written as abbreviations. Each has trade-offs that mainstream sources describe consistently.
Placement describes where the implant sits. Subglandular means behind the breast tissue but in front of the chest muscle; submuscular means partly or fully behind the pectoral muscle; dual plane is a combination, with the upper implant under muscle and the lower portion under gland. Mayo Clinic notes that placement behind the muscle can reduce visible implant edges in people with thinner tissue, while placement in front may mean less discomfort early on and less movement of the implant when the muscle flexes. Your skin pinch measurement is usually the deciding factor.
Incision describes where the scar will be: in the fold under the breast, around the edge of the areola, or in the armpit. Each carries a different visibility profile and a different effect on how easily the surgeon can control the implant pocket.
Fill and shell describe the implant itself. Saline implants contain sterile salt water and deflate visibly if they leak; silicone gel implants tend to feel more like breast tissue and may leak silently, which is why Mayo Clinic and the NHS both describe periodic imaging to check silicone implants. Shells may be smooth or textured. Textured implants have been associated with a rare lymphoma known as BIA-ALCL, a cancer of the immune system that forms in the scar tissue around an implant; the NHS and Mayo Clinic describe it as rare and note it has been linked mainly to textured surfaces.
Shape is round or teardrop. Round implants add upper fullness; anatomical shapes mimic a natural slope but can rotate. If your plan names one of each option without saying why, that “why” is your question.
Lift or reduction: what to ask at a breast reduction consultation
A lift (mastopexy) reshapes and raises the breast without removing much volume; a reduction removes tissue and skin to make the breast smaller and lighter, and includes a lift as part of the operation. Plans for both hinge on the same two facts: how far the nipple has dropped, and how much tissue is coming out.
Read the scar pattern first. A periareolar pattern circles the areola only; a vertical or “lollipop” pattern adds a line from areola to fold; an anchor or inverted-T pattern adds a horizontal scar along the fold. Mayo Clinic explains that larger reductions and greater ptosis generally need the longer patterns because more skin must be removed. If your plan proposes the shortest scar for a large change, ask how the surgeon expects the shape to hold.
Next, look for the word pedicle. A pedicle is the bridge of tissue that keeps the nipple attached to its blood and nerve supply while surrounding tissue is removed. Its direction (from above, below or the side) affects sensation and breastfeeding chances. In very large reductions, a free nipple graft, where the nipple is removed and reattached as a graft, may be proposed; MedlinePlus notes this usually means loss of nipple sensation and the ability to breastfeed. That is exactly the kind of line that deserves a direct question.
Useful things to ask at a breast reduction consultation include: how much tissue in grams the plan anticipates removing from each side and why they differ; whether the surgeon expects a lift alone to satisfy your goals if weight is not the main complaint; how the nipple position was chosen; and what the plan says about drains, dressings and when you can lift your arms above shoulder height.
Who a breast aesthetics plan is usually written for, and who is asked to wait
Surgeons do not write plans for everyone who walks in, and being asked to wait is not a rejection of you. It is usually a statement about timing and risk.
Plans are typically written for adults whose breast development is complete, whose weight has been stable for a period the surgeon considers meaningful, who are not currently pregnant or breastfeeding, who do not smoke or have committed to stopping, and whose expectations match what surgery can do. The NHS states that breast enlargement is not normally offered to people under 18, and Mayo Clinic advises that implants are usually considered once breasts are fully developed. For reduction, the NHS describes assessment that may include body mass index, symptom history and whether non-surgical measures such as physiotherapy or a professionally fitted bra have been tried.
People commonly asked to wait fall into a few groups. Those planning pregnancy within the next year or two, because pregnancy and breastfeeding change breast volume and skin and can undo the result. Those who are actively losing or gaining weight, for the same reason. Smokers and vapers, until nicotine is out of the picture, because of wound healing and nipple blood supply. People with uncontrolled diabetes, a recent major illness, an active skin infection on the chest or a bleeding disorder that has not been assessed. And anyone whose consultation suggests they are seeking surgery to resolve a relationship, a low mood or a body image concern that a mental health professional should hear first; Mayo Clinic notes surgeons may refer for that conversation.
A plan that includes a “conditions before booking” list is a sign of careful practice, not obstruction. If your plan has no such list, ask what would make the surgeon postpone.
What disqualifies you from a breast reduction?
The honest answer is that very few things disqualify someone permanently; most are reasons to defer or to modify the plan. It helps to separate the three kinds of barrier you may meet.
Safety barriers relate to anesthesia and healing. Uncontrolled high blood pressure, poorly controlled diabetes, active infection, certain heart or lung conditions and untreated clotting disorders raise the risk of a general anesthetic and of wound complications. These are typically managed by your usual clinicians first, after which the surgeon reassesses.
Outcome barriers are about whether the result would last or look right. A body mass index above the threshold a particular service uses is a common reason for deferral; the NHS notes weight may be assessed before reduction because breast size can change with weight and because complication rates rise with higher BMI. Ongoing weight change, planned pregnancy and continued smoking sit here too. Nicotine matters more in reduction than in augmentation because the operation relies on keeping the nipple alive on its pedicle; MedlinePlus lists smoking among the factors that increase the risk of poor healing.
Expectation barriers are the least discussed and the most important. Reduction removes weight and reshapes, but it cannot promise a particular cup size, symmetry that is perfect, or scars that vanish. A surgeon who senses that the goal is a specific number rather than relief may decline, and that is a legitimate clinical judgment.
If you are told you are not a candidate right now, the useful questions are: what specifically would need to change, is that change measurable, and would you reassess if it changed? Written answers to those three questions turn a “no” into a plan of their own.
The risks page: reading it without panic
Consent paperwork lists everything that can go wrong, in alphabetical order, with no sense of scale. A plan that does the same is technically complete but practically useless. Here is how to read it so the risks have shape.
General surgical risks apply to any operation under anesthesia: bleeding, infection, blood clots, reaction to anesthesia and delayed wound healing. MedlinePlus and the NHS list these for both augmentation and reduction. Ask how your own history alters them; a person who has had a previous clot is not the same risk as one who has not.
Implant-specific risks include capsular contracture, where the scar tissue that naturally forms around an implant tightens and hardens the breast; rupture or leak; implant malposition; and rippling. Mayo Clinic is explicit that implants are not designed to last a lifetime and that further surgery is likely at some point, whether to replace, remove or adjust. The NHS and Mayo Clinic both describe BIA-ALCL as rare and linked mainly to textured implants, and Mayo Clinic notes some people report systemic symptoms sometimes called breast implant illness, for which the evidence remains unclear; it is honest to say that the mechanism is not established.
Lift and reduction risks center on scarring, asymmetry, changes in nipple sensation, partial or complete loss of the nipple in rare cases, fat necrosis (firm lumps where fatty tissue lost its blood supply) and difficulty breastfeeding.
The question that gives risks proportion is simple: “Of these, which ones would you expect me to encounter, which would you be surprised by, and what would we do about each?” A surgeon who answers in plain language, with your measurements in mind, has turned a list into a plan.
Sensation, breastfeeding and mammograms: the long-term lines in the plan
Most surgical plans devote a paragraph to the next six weeks and a single sentence to the next thirty years. Reverse that emphasis when you read it.
Nipple sensation can increase, decrease or disappear after any breast operation because the nerves that supply it run through the tissue being moved. MedlinePlus notes that changes are common after reduction and may be temporary or permanent, and that sensation loss is expected with a free nipple graft. Ask which nerve pathways your planned technique preserves, and what proportion of the surgeon’s own patients report lasting change; if they cannot say, that is informative too.
Breastfeeding is possible after many augmentations and some reductions, but not guaranteed. Mayo Clinic advises that implants do not usually prevent breastfeeding, while reduction, particularly with larger tissue removal or a graft, can reduce milk supply or make breastfeeding impossible. If future breastfeeding matters to you, it should appear in the plan as a design constraint, not as an afterthought.
Screening changes too. Implants can obscure part of the breast on a mammogram, so radiographers use additional views; Mayo Clinic and the NHS both advise telling the screening service that you have implants. Silicone implants may need periodic MRI or ultrasound to check for silent rupture because a leak does not always show or feel different. Reduction leaves scar tissue and sometimes calcifications that a radiologist needs to know about.
Finally, lifespan. Mayo Clinic states plainly that breast implants are not lifetime devices. A plan that mentions the likelihood of future revision, removal or replacement is not being pessimistic; it is describing the ordinary course. Ask what monitoring the surgeon recommends and who will provide it if you move or the practice changes.
What the following days and weeks usually look like
Recovery timelines in a plan should read as ranges, because healing speed depends on the procedure, your tissue and your job. The ranges below come from mainstream patient guidance, and your own team’s instructions override them.
Day of surgery and the first few days: most augmentations, lifts and reductions are done under general anesthesia, and many people go home the same day or after one night. Expect tightness, swelling and bruising. The NHS describes pain that is usually managed with the pain relief your team prescribes, and a supportive surgical bra worn day and night. Drains, if used, are removed within days. Mayo Clinic advises against lifting, pushing or pulling in the early period.
The first two weeks: the NHS suggests many people take one to two weeks off work after breast enlargement or reduction, longer for physically demanding roles. Driving is usually discouraged until you can perform an emergency stop without pain and are off sedating medicines. Stitches may be dissolvable; dressings are checked at a follow-up visit.
Weeks two to six: Mayo Clinic advises avoiding strenuous activity for at least a few weeks after augmentation and for about a month or more after reduction, with a gradual return to exercise guided by your team. The NHS describes a period of up to six weeks before heavy lifting and vigorous exercise are resumed. Swelling continues to settle and implants begin to drop into position.
Months two to twelve: scars redden, then soften and fade over many months. Final shape is judged at several months, not weeks. Sensation changes may continue to evolve. Ask your plan to state when each follow-up happens and what will be assessed at each one.
What people often get wrong about breast surgery plans
Some misunderstandings show up in almost every consultation. Correcting them early saves disappointment later.
“Bigger implants fix sagging.” They do not. Volume adds weight, and weight pulls tissue downward. If the nipple sits at or below the fold, mainstream guidance from Mayo Clinic describes a lift, with or without an implant, as the operation that addresses position. A plan that proposes an implant alone for significant ptosis deserves a question.
“A lift alone is always enough.” Sometimes it is, and it avoids implant-related risks. But a lift reshapes existing tissue; it does not create upper fullness that is not there. People who want both a higher nipple and a fuller upper pole are often offered a combination, and the plan should say which goal each part serves.
“Implants are permanent.” Mayo Clinic and the NHS both state they are not lifetime devices. Budgeting emotionally for future surgery is part of informed consent.
“Reduction gives you a chosen cup size.” Surgeons remove tissue by weight and shape by eye; bra sizing is a retail convention, not a medical unit. Expect a range, not a guarantee.
“Scars disappear.” They fade and flatten, often considerably, but they remain. The plan should show the pattern on a diagram.
“Symmetry will be perfect.” Nearly all breasts differ before surgery and will differ after, though usually less. Ask how each measured difference will be managed.
“Smoking only matters on the day.” Nicotine impairs blood supply during the weeks of healing when nipple and skin flaps are most vulnerable. The NHS advice is to stop well ahead of surgery and stay stopped through recovery.
None of these corrections is a reason to avoid surgery. They are reasons to read the plan with the right expectations.
Breast aesthetics consultation questions to ask your care team
Lists of questions circulate widely, and most are fine. The best ones share a feature: they ask for reasoning, not reassurance. Take the plan with you and work through it.
About the measurements: which of my numbers most shaped this plan? Where do my two sides differ, and how does the plan handle each difference? Is there a measurement that rules out an option I asked about?
About the technique: why this placement, incision, scar pattern or pedicle rather than the alternatives? What would make you change your mind in the operating room? If you found something unexpected, what is your default?
About the surgeon: how often do you perform this exact operation? What revision procedures have you needed to do for it, and for what reasons? Who covers if I have a problem at night or on a weekend?
About the future: what is your expected follow-up schedule? What imaging will I need and how often? If I later want implants removed or exchanged, what does that involve? How would pregnancy or a large weight change affect this result?
About recovery: when can I drive, lift my child, return to my specific job, and train again? What sensations are normal and which should prompt a call?
About the decision itself: is there any reason you would prefer I wait? Is there a non-surgical option you considered? The NHS advises taking time to reflect after a consultation rather than booking on the day, and seeking a second opinion if anything feels rushed.
Write the answers down. A plan you can explain back in your own words is a plan you have genuinely consented to.
When to call your doctor after breast surgery
Most recovery days are uneventful, and a plan should tell you what ordinary discomfort feels like so that the unusual stands out. The signs below are the ones mainstream sources agree should prompt a same-day call to your surgical team, or emergency care if severe.
Call promptly for a fever, spreading redness or warmth around an incision, increasing rather than easing pain, or any discharge that is cloudy, foul-smelling or increasing. MedlinePlus and the NHS list these as signs of possible infection, which is easier to treat early.
Call urgently if one breast becomes suddenly larger, tighter, more painful or bruised than the other in the first days; this can indicate bleeding into the surgical space (a hematoma) and may need drainage. A nipple that turns dusky, pale or dark, or skin that blisters or blackens near an incision, needs assessment the same day because it can signal compromised blood supply.
Seek emergency care for chest pain, sudden shortness of breath, coughing up blood, or a painful, swollen calf, all of which can indicate a blood clot; the risk is highest in the weeks after any operation.
In the longer term, contact your team if a breast becomes firm or changes shape, if you notice a new lump, persistent swelling, fluid collection around an implant, or a change in implant position; Mayo Clinic advises reporting these because they can reflect capsular contracture, rupture or, rarely, BIA-ALCL.
The plan should give you a direct number, the name of who answers it and what to do outside office hours. If those details are missing, ask before the day of surgery, not after. Every one of these decisions, from watchful waiting to a return to the operating room, rests with the team who knows your case.
Frequently asked questions
What should I ask at a breast reduction consultation?
Ask how much tissue the surgeon expects to remove from each side and why the amounts differ, which scar pattern and pedicle technique are planned and how they affect nipple sensation and breastfeeding, and what would make the surgeon change technique during the operation. Also ask about drains, time off work, when you can raise your arms, and what non-surgical measures were considered first.
What is the 45-55 breast rule?
It is an aesthetic proportion from a study in which observers preferred breasts with about 45 percent of volume above the nipple and 55 percent below, with the nipple tilted slightly upward. Some surgeons use it as a design target for implant sizing or lifts. It reflects average taste, not a medical standard, and it does not predict complications or how you will feel about your result.
What disqualifies you from a breast reduction?
Few things disqualify permanently; most are reasons to defer. Common ones include ongoing weight change, a body mass index above the service’s threshold, current smoking or vaping, planned pregnancy, uncontrolled diabetes or blood pressure, active infection, untreated bleeding disorders and expectations the surgery cannot meet. Ask what specifically would need to change and whether the surgeon would reassess once it does.
What questions are typically asked during a breast augmentation consultation?
Surgeons usually ask about medical history, including bleeding problems, previous breast surgery, family history of breast cancer and current medicines and supplements; about smoking, weight stability, pregnancy plans and breastfeeding intentions; about your job and exercise; and about your goals, including what bothers you now and what would look too large. Expect a gentle question about why you are considering surgery at this time.
Is a breast lift alone enough, or do I need an implant too?
A lift alone can be enough when the main concern is nipple position and shape rather than volume. It raises and reshapes existing tissue but cannot create upper fullness that is not there. If you want both a higher nipple and a fuller upper pole, a combination may be proposed. Your plan should state which goal each part of the operation serves, and why.
How do surgeons decide implant placement, in front of or behind the muscle?
The skin pinch measurement across the upper chest is usually decisive. Thin tissue cover tends to favor placement partly or fully behind the pectoral muscle, which softens visible implant edges and rippling. Thicker cover allows placement in front of the muscle, which may mean less early discomfort and less implant movement when the muscle flexes. Your activity and job also weigh in.
Can I breastfeed after breast surgery?
Often yes after augmentation, according to Mayo Clinic, though it is not guaranteed. After reduction, milk supply may be reduced, and a free nipple graft usually removes the ability to breastfeed. If breastfeeding matters to you, ask that it be written into the plan as a design constraint influencing technique, and ask which nerve and duct pathways the chosen method preserves.
How long is recovery after breast augmentation or reduction?
The NHS suggests many people take one to two weeks off work, and up to about six weeks before heavy lifting and vigorous exercise. Mayo Clinic advises avoiding strenuous activity for at least a few weeks after augmentation and about a month or more after reduction. Final shape settles over several months. Your own team’s instructions, based on your procedure and job, take priority.
Do breast implants need to be replaced?
Not on a fixed schedule, but Mayo Clinic and the NHS both state that implants are not lifetime devices and that further surgery to replace, remove or adjust them is likely at some point. Silicone implants may need periodic imaging because a leak can be silent. Ask your surgeon what monitoring they recommend and who will provide it over the long term.
How can I read my breast aesthetics surgical plan more critically?
Check that each option in the plan traces back to a specific measurement, that both sides were measured and planned separately, that alternatives considered and rejected are listed with reasons, that risks are given in plain language with your history in mind, and that follow-up, imaging and out-of-hours contact details are included. Any gap is a question to raise before you sign.
References
- NHS: Breast enlargement (implants)
- NHS: Breast reduction (female)
- MedlinePlus: Breast augmentation surgery
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Combined Procedures in Breast Aesthetics: When a Lift and Implants Happen in One Operation
A combined breast lift and augmentation, also called augmentation mastopexy, reshapes and raises sagging breast tissue while placing an implant for volume, all under…

Preparing for Breast Augmentation: Imaging, Medication Review and the Final Sizing Visit
Preparing for breast augmentation usually involves three steps spread over several weeks: a baseline breast imaging review if you are of screening age or…

How Long Do Breast Implants Last? Lifespan, Monitoring and When Replacement Is Discussed
Breast implants are not lifetime devices, but they do not expire on a fixed schedule. Many last 10 to 20 years or more, and…

How DIEP Flap Breast Reconstruction Works: Abdominal Tissue, Microsurgery and Operating Time
DIEP flap breast reconstruction rebuilds a breast using skin and fat from the lower abdomen while leaving the abdominal muscle in place. Surgeons trace…

When Is Gynaecomastia Treatment Considered? Watchful Waiting, Causes Checked and Surgery
Gynecomastia treatment is usually considered only after three things have happened: a doctor has confirmed the swelling is glandular breast tissue rather than fat,…

Questions to Ask Before Breast Reconstruction: Stages, Symmetry Surgery and Nipple Options
Before breast reconstruction, ask your plastic surgeon which technique suits your body and cancer treatment (implant or your own tissue), whether reconstruction should happen…