

Neck Lift After Major Weight Loss: How Surgeons Plan for Extra Skin and Thin Tissue

Key Takeaways
- Skin stretched for years loses fragmented elastin that cannot re-shorten, which is why loose neck skin persists after major weight loss regardless of exercise or creams.
- Surgeons planning a neck lift after weight loss often preserve or redistribute fat rather than remove it, because a thin neck can look hollow and expose the platysma muscle and salivary glands.
- Liposuction alone is usually a poor fit after significant weight loss, since it relies on skin retraction that has already failed to happen.
- Weight stability for several months to about a year is a standard precondition, because further loss or regain undoes the result and increases risk.
- Smoking and nutritional deficiencies, both common after bariatric surgery, directly threaten the blood supply and collagen repair a thin skin flap depends on.
- Rapid one-sided swelling, dusky skin, difficulty breathing or new lip weakness after surgery are red flags that warrant an immediate call to the surgical team.
A neck lift after weight loss removes redundant skin, tightens the platysma muscle and reshapes what remains of the fat beneath the chin, but surgeons plan it differently from a standard neck lift because the skin is often stretched and the tissue thin. Most teams ask that weight be stable for months first, screen nutrition and smoking, and may combine or stage procedures. Outcomes vary; the treating surgeon decides.
She kept the photo on her phone: the day she hit her goal weight, grinning in a dress two sizes down from anything she had owned in a decade. What the photo also showed, and what she noticed before anyone else did, was the soft curtain of skin hanging from her jaw to her collarbones. Her body had changed. Her neck had not kept up.
This is one of the quieter conversations in aesthetic surgery. People who lose a great deal of weight, whether through bariatric surgery, medication or years of effort, often arrive at a surgeon’s office with a question that sounds simple: can this be fixed? A neck lift after weight loss can address it, but it is not the same operation a surgeon performs on someone whose neck has aged slowly at a steady weight. The skin behaves differently. The tissue underneath is thinner. The planning has to account for both.
What follows is how surgeons think about that planning, what the operation involves, and where the evidence is honest about limits.
Why a neck lift after weight loss is planned differently
Think of a balloon inflated for a year and then let down. The rubber does not return to its original size; it hangs in folds and feels thinner where it stretched most. Skin under long-term stretch behaves in a similar way, and the neck is one of the places where that shows earliest because gravity and movement pull on it constantly.
In a conventional neck lift, the surgeon usually works with skin that has lost elasticity gradually, a modest amount of excess and a reasonably preserved layer of fat and connective tissue beneath. After major weight loss, the picture is often reversed. There can be a large surplus of skin, sometimes extending well below the jawline toward the chest, while the fat that once gave the neck a smooth contour has largely gone. The Mayo Clinic describes the neck lift as a procedure that removes excess skin and fat and tightens the muscle to improve the angle between chin and neck, and that description still holds, but the proportions of each step shift.
Surgeons planning this operation ask a different set of questions. Where is the excess actually located, and does it continue onto the face or chest? How thick is the skin when pinched, and does it have any recoil at all? Are the vertical bands of the platysma, the thin sheet of muscle under the skin of the neck, visible because they have loosened, or because there is simply nothing covering them anymore? Each answer changes the incision plan, the amount of tissue removed and whether a neck lift alone is enough.
The honest headline is this: the operation can make a real difference, but the anatomy after weight loss sets the limits. Understanding those limits before surgery is the difference between a good decision and a disappointing one.
What actually happens during the operation
Under the skin of the neck sit three structures the surgeon works with. The platysma is the broad, thin muscle that runs from the jaw down toward the collarbones; when it loosens, it forms the two vertical cords people often call bands. Beneath and around it lie pockets of fat, including the submental fat under the chin. The skin itself is the outer envelope. A neck lift addresses all three in an order the surgeon chooses based on the individual.
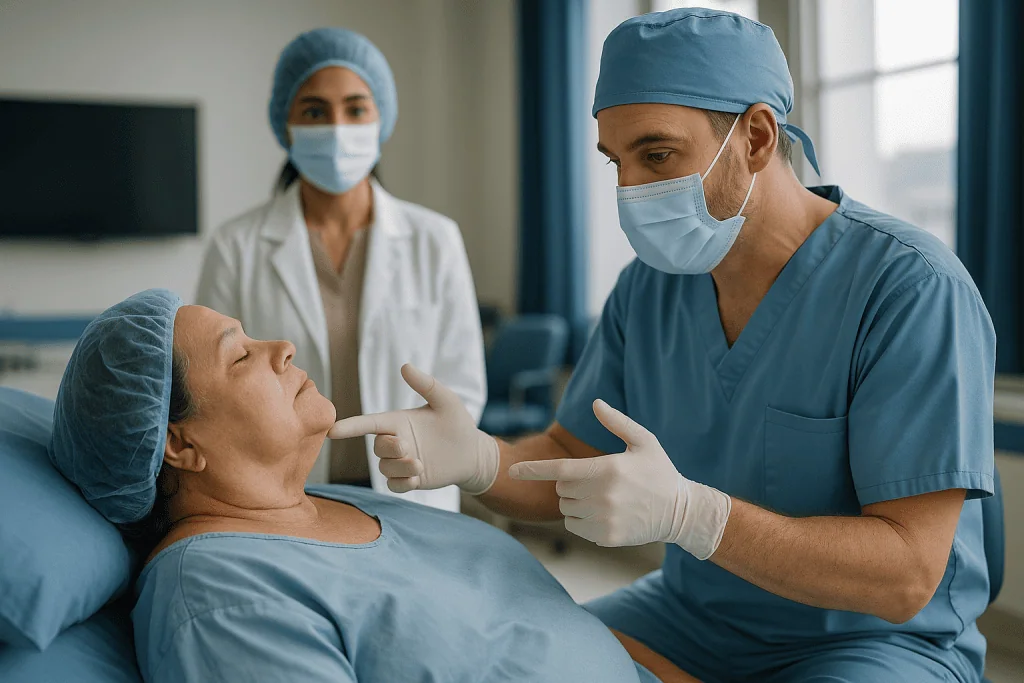
The Cleveland Clinic describes a typical sequence: incisions are placed around and behind the ears and often in the crease under the chin, the skin is lifted away from the deeper layers, the platysma is tightened by stitching its edges together in the midline or securing it toward the ear, fat is removed or repositioned as needed, and the skin is redraped and trimmed before closure. The whole procedure is performed under general anesthesia or sedation with local anesthetic, and the choice is made by the surgical and anesthesia team.
After major weight loss, two of those steps change character. Because far more skin is redundant, the surgeon may extend the incision behind the ear and along the hairline to distribute the excess without visible bunching. Because the fat has already been lost, the emphasis moves away from removal and toward keeping or even redistributing what remains so that the muscle and the salivary glands beneath do not become visible through a very thin covering.
Drains are sometimes placed for a day or two to collect fluid, and a soft compression garment is commonly worn afterward to support the tissues as they settle. None of this is standardized across all practices; the approach is tailored, and the surgeon will describe the specific plan during consultation.
Why loose neck skin after weight loss does not snap back
Skin owes its stretch and recoil to two proteins in its middle layer. Collagen provides structure; elastin provides the spring. When skin is stretched slowly over years, as it is when someone gains a significant amount of weight, both networks are physically pulled apart and reorganized. Elastin fibers that have been stretched for a long time fragment and lose their ability to shorten again. Collagen becomes disordered and thinner.
Johns Hopkins Medicine notes that after major weight loss the skin often lacks the elasticity to conform to the new, smaller body, which is why redundant folds persist even when the fat beneath them is gone. Age compounds this, because elastin production naturally slows across adulthood. So does sun exposure, which damages both proteins, and so does smoking, which reduces blood flow and impairs collagen repair.
The neck is particularly unforgiving. Its skin is thinner than the skin of the cheeks or back, it has relatively little underlying support, and it moves thousands of times a day as we speak, swallow and turn our heads. Excess skin here has nowhere to hide.
This matters for expectations. Creams, supplements and exercise can improve the quality of the skin surface or build the muscles underneath, but none of them can shorten fragmented elastin or remove a physical surplus of skin. That is a matter of biology rather than effort, and it is why a surgical option exists at all. It also explains why surgeons look carefully at how the remaining skin behaves before promising anything: skin that has lost most of its recoil will redrape less predictably after any lift.
How much loose skin will I have after losing 100 pounds?
This is one of the most searched questions on the topic, and the truthful answer is that no formula predicts it. Two people who lose the same amount of weight can look strikingly different afterward, and the difference comes down to factors that were set long before the weight came off.

Age at the time of loss matters, because younger skin retains more elastin. The length of time spent at the higher weight matters, because elastin stretched for two decades has undergone more damage than elastin stretched for two years. The speed of loss plays a role, since rapid loss gives skin little time to adapt. Genetics govern baseline skin thickness and collagen quality. Sun history and smoking history both reduce recoil. Where the weight was carried influences where the excess shows; someone whose weight sat in the face and neck will notice more there.
The NHS, in its guidance on weight loss surgery, is candid that many people who lose a large amount of weight are left with excess skin and that some go on to seek surgery to remove it. What none of the major medical sources offer is a per-pound estimate, because there is no reliable one.
Surgeons instead assess the neck directly. A pinch test shows how much skin can be gathered and how quickly it flattens back. Photographs from the front, side and with the chin down reveal where folds form. The relationship between the chin, the hyoid bone in the front of the neck and the angle of the jaw predicts how sharp a contour is achievable. The answer to “how much” is therefore always individual, and a good consultation will show rather than tell.
Thin tissue: the problem surgeons worry about most
If excess skin is the visible problem, thin tissue is the hidden one, and experienced surgeons often consider it the harder of the two.
In a neck that has not lost weight, a layer of fat and connective tissue sits between the skin and the platysma. It softens the outline of the muscle, cushions the submandibular glands that sit under the jaw on each side, and gives the surgeon something to work with when redraping skin. After major weight loss, that layer may be almost absent. The result is a neck where every underlying structure shows: the bands of the platysma, the edge of the glands, sometimes the cartilage of the voice box.
This changes the surgical goal. Removing more fat, which is routine in many neck lifts, can make a thin neck look gaunt or skeletal. Surgeons planning for this anatomy often leave fat in place, redistribute it, or discuss fat grafting, which is the transfer of a person’s own fat from elsewhere to add volume where it is missing. Whether grafted fat survives well in a previously stretched neck is not something the evidence can promise; surgeons describe it as variable.
Thin tissue also affects healing. Blood supply to the skin flap, the sheet of skin lifted during surgery, is carried in small vessels within and beneath the skin. A thinner flap has a thinner margin of safety, which is one reason smoking, which constricts those vessels, is taken so seriously before this operation.
Finally, thin skin shows irregularities. Small contour steps or scar lines that would be invisible under a cushion of fat can be noticeable when the covering is delicate. Surgeons weigh this when deciding how much to remove and where to place incisions.
Who a neck lift after weight loss is usually for, and who is asked to wait
The clearest candidate is someone whose weight has been steady for an extended period, whose overall health has been reviewed, who does not smoke, and whose main concern is genuinely the neck rather than the whole face or body. Johns Hopkins Medicine describes weight stability as a core requirement for body contouring after major weight loss, because further loss after surgery can bring back the very laxity the operation removed, and regain can stretch newly tightened tissue.
How long is long enough? Patient-education resources from Mayo Clinic and Johns Hopkins describe a period of stable weight lasting several months to about a year, and in people who have had bariatric surgery the wait is often longer because weight continues to change for a year or more afterward. The exact timing is a decision for the surgical team, who will look at the weight trend rather than a single number.
Several groups are commonly asked to wait or to address something first:
- People still actively losing weight, including those on weight-loss medicines such as GLP-1 receptor agonists, a class that slows stomach emptying and reduces appetite; the prescribing clinician and surgeon coordinate on timing, and no one should alter these medicines on their own.
- Smokers and users of nicotine products, because of the effect on skin blood supply and wound healing.
- Anyone with untreated nutritional deficiencies, which are common after bariatric surgery and impair healing.
- People with poorly controlled diabetes, high blood pressure or clotting disorders, which raise surgical risk.
- People whose expectations do not match what the anatomy allows, which a candid consultation should surface.
Being asked to wait is not a refusal. In this context it is usually the safer path to the same destination.
Surgical options compared: neck lift, platysmaplasty, lower facelift and liposuction
Several procedures overlap under the heading “neck lift,” and after weight loss the right combination depends on what has been lost and what remains. The table below summarizes what each is designed to address, in neutral terms, drawing on procedure descriptions from Mayo Clinic and the Cleveland Clinic.
| Procedure | What it addresses | Typical fit after major weight loss |
|---|---|---|
| Neck lift (cervicoplasty) | Removes excess neck skin; often combined with muscle tightening | Core procedure when skin surplus is the main issue |
| Platysmaplasty | Tightens the loosened platysma muscle to reduce vertical bands | Usually added, since bands are prominent when fat is thin |
| Lower facelift with neck lift | Repositions sagging jowls and cheek tissue along with the neck | Considered when excess extends onto the lower face |
| Neck liposuction alone | Removes fat through small cannulas without cutting skin | Rarely suitable; fat is already depleted and skin will not retract |
| Fat grafting | Adds volume using the person’s own fat | Sometimes discussed for hollow or thin areas; results variable |
| Energy-based skin tightening | Heats deeper skin to stimulate modest collagen contraction | Not a substitute for removing large amounts of skin |
The key insight for people after weight loss is that liposuction alone, which is often suggested in general articles about neck contouring, is usually the wrong tool. Liposuction relies on the skin shrinking back over a smaller volume. Skin that has already failed to shrink after losing a great deal of weight is unlikely to do so after losing a little more fat, and removing fat from an already thin neck risks making it look more hollow.
Surgeons also decide whether to combine the neck with other body contouring, such as an arm lift or abdominoplasty, in one session or stage them over time. Longer combined operations carry higher risks of blood clots and fluid shifts, so staging is common. That sequencing is the surgical team’s call, made against the whole picture of a person’s health.
How to fix a saggy neck after weight loss without surgery
The question deserves a straight answer rather than a dismissal, because the non-surgical route is where most people start and where a great deal of misleading marketing lives.
Exercise strengthens muscle, and the neck has plenty of it. Building the muscles of the neck and jaw can improve posture and may subtly change the way the head sits on the shoulders, which affects how skin folds. What exercise cannot do is shorten skin. The excess after major weight loss is a surplus of tissue, not a weakness of muscle, and no repetition count changes that. The Cleveland Clinic makes the same point about loose skin generally: muscle gain can fill some space beneath the skin, but it does not tighten the skin itself.
Topical products with retinoids, a class of vitamin A derivatives that increase skin cell turnover, and moisturizers can improve surface texture and fine lines. They act on the top layers and do not reach the fragmented elastin in the deeper skin responsible for sagging. Collagen supplements are widely sold; the evidence that swallowing collagen tightens neck skin is weak and not endorsed by mainstream medical sources.
Energy-based treatments using radiofrequency or ultrasound heat the deeper skin to provoke a healing response and modest collagen contraction. The Mayo Clinic describes these as options for mild laxity. For the amount of excess typical after losing a large proportion of body weight, they are generally considered insufficient, and a series of sessions can still leave the fundamental surplus in place.
Sun protection, not smoking and steady hydration protect the skin you have. They do not reverse stretch. The honest role of non-surgical care is to optimize skin quality, which can improve how any later surgery heals and looks.
What the consultation involves
A consultation for this operation is longer and more detailed than a general aesthetic visit, because the surgeon is assessing a history as much as an anatomy.
Expect questions about how the weight was lost, over what period, and whether it has been stable. If bariatric surgery was involved, the surgeon will want to know which operation, because procedures that bypass part of the intestine affect absorption of protein, iron, vitamin B12 and other nutrients essential to wound healing. Blood tests to check for anemia and protein levels are commonly ordered, and the Mayo Clinic notes that a medical evaluation and laboratory testing are standard before a neck lift. Any nutritional gaps are usually corrected first, with the bariatric or primary care team guiding that.
The physical examination focuses on the neck in several positions. The surgeon assesses skin thickness and recoil by pinching, maps where excess falls with the head neutral and flexed, palpates the platysma to see whether bands tighten when the jaw is clenched, and looks for prominent submandibular glands, which sit under the jawline and can become visible in a thin neck. The position of the chin and the depth of the angle between chin and neck are measured or photographed, since a receding chin or low hyoid bone limits how sharp a contour is achievable regardless of surgery.
Photographs are taken from multiple angles and become the reference for planning and for later comparison. Medical history, current medicines including any weight-loss or blood-thinning medicines, allergies and prior anesthesia experiences are reviewed.
A good consultation ends with the surgeon explaining what they would do, what they would not do, and why. If a plan is presented without any discussion of limits, that itself is worth noticing.
Preparing the body: nutrition, smoking and the weeks before surgery
Preparation for a neck lift after weight loss has one central theme: giving tissue that has already been through a lot the best possible chance to heal.
Protein comes first. Wound healing depends on building new collagen, and collagen is protein. People who have had bariatric surgery often eat smaller volumes and absorb less, and the NHS notes that lifelong vitamin and mineral supplementation is usual after such operations. Before elective surgery, the bariatric team typically reviews intake and blood work and adjusts supplements; those decisions stay with them.
Nicotine is the second priority. MedlinePlus describes how smoking narrows blood vessels and reduces oxygen delivery to healing tissue, raising the risk of wound breakdown, infection and poor scarring. In a thin neck flap where blood supply is already marginal, that risk is amplified. Surgeons commonly ask for complete abstinence from all nicotine products, including vaping and patches, for a defined period before and after surgery; the length of that period is set by the surgeon.
Medicines are reviewed individually. Some, such as aspirin, certain anti-inflammatory drugs and blood-thinning medicines, increase bleeding risk, but stopping any prescribed medicine without direction from the prescribing clinician can be dangerous. The correct step is to bring a full list to the surgeon and let the teams coordinate.
Practical preparation matters too. Someone will need to drive you home and stay the first night. Loose, front-opening clothing avoids pulling anything over the head. Pillows arranged to keep the head elevated and the neck in a neutral position, neither flexed nor twisted, are commonly recommended. Arranging time off work and help with household tasks before the day reduces the temptation to do too much afterward.
Neck lift recovery time: what the days and weeks usually look like
Recovery follows a recognizable arc, though the pace varies from person to person and no timeline is a guarantee.
In the first day or two, the neck is wrapped in a dressing and often a soft compression garment. Swelling and bruising are expected and typically peak within the first few days. The Mayo Clinic notes that tightness, numbness and a feeling of pressure in the neck are common at this stage. If drains were placed, they are usually removed within the first few days at a follow-up visit. Discomfort is managed with medicines prescribed by the surgical team.
During the first week, most people are up and walking around the house, which matters for circulation and clot prevention. Head elevation while sleeping continues. Sutures around the ears and under the chin are commonly removed within the first one to two weeks, according to Cleveland Clinic patient guidance.
The Cleveland Clinic describes many people returning to desk work and light activity within about two weeks, with visible bruising largely faded by then, while strenuous exercise, heavy lifting and anything that raises blood pressure sharply are typically deferred for several weeks on the surgeon’s instruction.
Over the following weeks and months, residual swelling settles, numbness gradually improves as small nerves recover, and scars soften and fade from pink toward pale. The Mayo Clinic advises that the final appearance takes months to emerge. Thin tissue can make swelling more visible early and can make small irregularities more noticeable until everything settles, which is one more reason to judge results only when the surgeon says the healing is complete.
Follow-up visits punctuate this period, and each is a chance to raise anything that seems off.
Risks and complications in plain language
Every operation carries risk, and it is fairer to describe these clearly than to bury them. The Mayo Clinic and Cleveland Clinic list the following as recognized complications of neck lift surgery.
Bleeding beneath the skin, called a hematoma, is the most common early problem. It shows as rapidly increasing swelling, often on one side, with tightness or pain, and usually requires prompt return to the surgeon to drain it. Infection can occur at incision lines and is managed with wound care and, where needed, antibiotics chosen by the treating team.
Nerve injury is a particular concern in the neck. A branch of the facial nerve that controls the lower lip runs close to the operative field; if it is bruised, the lip may pull unevenly when smiling, which usually resolves over weeks to months but can occasionally persist. Numbness of the skin around the ears and neck is expected and generally improves, though small patches can remain.
Skin loss, where a portion of the flap does not survive because its blood supply is compromised, is uncommon but more likely in smokers and in very thin flaps. Scarring can be wider or more raised than hoped, particularly where skin was under tension at closure. Fluid collection under the skin, called a seroma, may need drawing off with a needle. Asymmetry, contour irregularities and visible bands returning over time are possible, and some people seek a revision procedure.
General anesthesia carries its own risks, and blood clots in the legs or lungs are a recognized risk of any surgery, especially longer combined procedures. Surgeons reduce this with early walking, compression stockings and sometimes medicines that thin the blood, decided case by case.
What people often get wrong about neck lift after weight loss
“Liposuction will sort out my neck.” For most people after significant weight loss, it will not. Liposuction depends on skin contracting over a smaller volume, and skin that failed to contract after losing a large amount of weight is unlikely to behave differently after losing a small amount of fat. In a thin neck it can worsen hollowing.
“Exercise can tighten loose neck skin.” Exercise builds muscle, and muscle can change the shape beneath the skin. It cannot shorten a surplus of stretched skin, which is a structural problem of fragmented elastin rather than weak muscle.
“Turkey neck after weight loss is the same as an aging neck.” They look similar and overlap, but the underlying tissue differs. An aging neck usually retains fat that softens contours; a post-weight-loss neck often has very little, which changes the surgical plan.
“The sooner after reaching goal weight, the better.” The opposite is closer to the truth. Weight that is still moving will undo or distort the result, which is why Johns Hopkins and other sources emphasize stability first.
“Results are permanent.” The skin removed does not grow back, but aging continues, and the remaining skin, already low in elastin, will loosen again over time. Weight regain accelerates this.
“Cost tells you about quality.” This article does not quote prices, and it would be misleading to do so, because fees vary with the extent of surgery, the facility, anesthesia and geography, and a higher or lower figure says nothing about outcome. The useful questions are about training, hospital privileges, how the surgeon manages complications and what happens if a revision is needed.
“One operation will fix everything.” Staging is common and often safer, and the neck is frequently one part of a longer plan.
Questions to ask your care team
Consultations move quickly, and it helps to arrive with questions written down. These are the ones that tend to matter most for this particular operation.
- Given how my skin behaves when you pinch it, what do you realistically expect the neck to look like after healing, and what will it not fix?
- Do you consider my weight stable enough now, and if not, what would you want to see and for how long?
- Will you tighten the platysma, and how do you plan to handle the thin tissue over the muscle and glands?
- Are you planning to remove fat, preserve it or add it, and why?
- Where exactly will the incisions be, how long will they be, and how do you expect the scars to look in thin skin?
- Would you recommend addressing the lower face at the same time, or staging it separately, and what are the trade-offs?
- What blood tests or nutritional checks do you want beforehand, and who coordinates them with my bariatric or primary care team?
- How do you want me to handle my current medicines, including any weight-loss medicines, and who gives me that instruction?
- What is your policy on nicotine before and after surgery?
- Which complications do you see most often in people with my history, and how are they managed?
- Who do I contact after hours if something worries me, and where would I go?
- If the result needs a revision, how is that handled?
None of these questions is adversarial. A surgeon who welcomes them is telling you something about how they will handle the harder conversations later, if any arise.
When to call your doctor
Most recovery is uneventful, but a small number of problems need prompt attention, and thin tissue in the neck makes speed matter more than usual. Contact your surgical team, or seek emergency care if you cannot reach them, if any of the following occur.
- Swelling that increases rapidly, especially on one side, with tightness, firmness or worsening pain; this can signal bleeding under the skin and may need urgent drainage.
- Any difficulty breathing or swallowing, a sense of throat tightness, or a muffled voice, which are emergencies.
- Fever, spreading redness, warmth, increasing pain or cloudy or foul-smelling drainage from an incision, which may indicate infection.
- Skin over the neck or behind the ears turning dark, dusky, purple or black, or blistering, which can mean the blood supply is compromised.
- Bleeding that soaks dressings and does not stop with gentle pressure.
- A wound edge that opens or a suture line that separates.
- New weakness of the lower lip or an uneven smile that was not present immediately after surgery, or any new facial weakness.
- Pain, swelling or warmth in one calf, or sudden shortness of breath or chest pain, which can indicate a blood clot and require emergency care.
- Persistent nausea, vomiting or inability to keep fluids down, which risks dehydration and interferes with healing.
It is always reasonable to call about something that simply feels wrong, even if it is not on a list. Surgical teams would rather hear about a harmless concern than learn about a serious one late. Keep the after-hours number somewhere visible from the first night, and make sure whoever is helping you at home knows it too.
Frequently asked questions
How do you fix a saggy neck after weight loss?
For a large surplus of skin, the established approach is a surgical neck lift, often with platysmaplasty to tighten the underlying muscle. Non-surgical options such as radiofrequency or ultrasound skin tightening address mild laxity only and are generally considered insufficient for the amount of excess typical after major weight loss. The right plan depends on skin thickness, remaining fat and weight stability, which a surgeon assesses in person.
Can I tighten neck skin after weight loss naturally with exercise?
Exercise strengthens neck and jaw muscles and can improve posture, but it does not shorten stretched skin. The sagging after major weight loss comes from fragmented elastin and a physical surplus of tissue, neither of which muscle training reverses. Sun protection, not smoking and good nutrition help preserve skin quality and support healing if you later choose surgery, but they do not remove excess skin.
How much does a neck lift cost after weight loss?
This article does not quote prices, because fees vary widely with the extent of surgery, whether the face is included, the facility, anesthesia and location, and a figure without that context is misleading. Ask the surgical team for a written, itemized estimate that includes follow-up and how revisions are handled. Cosmetic procedures are generally not covered by insurance, though coverage rules differ and are worth checking with your insurer.
How much loose skin will I have after losing 100 pounds?
There is no reliable per-pound estimate. The amount depends on your age, how long you carried the extra weight, how quickly you lost it, genetics, sun exposure and smoking history. Two people losing the same amount can look very different. Surgeons assess the neck directly using pinch tests and photographs rather than predicting from the number on the scale.
Is turkey neck after weight loss different from an aging neck?
They look similar but differ underneath. An aging neck usually keeps a layer of fat that softens contours, while a post-weight-loss neck often has very little, leaving the platysma bands and glands more visible. That changes the surgical plan toward preserving or adding volume rather than removing it, and it makes skin quality and blood supply more important considerations.
What is the typical neck lift recovery time?
Patient guidance from the Cleveland Clinic describes many people returning to desk work and light activity within about two weeks, with bruising largely faded by then and strenuous exercise deferred for several weeks. Swelling, tightness and numbness continue to settle over months, and the Mayo Clinic notes the final appearance emerges gradually. Individual recovery varies, and your surgeon sets the timeline.
How long should my weight be stable before a neck lift after weight loss?
Patient-education resources from Johns Hopkins and Mayo Clinic describe a stable weight lasting several months to about a year, and people who have had bariatric surgery are often asked to wait longer because weight continues to change for a year or more afterward. The surgical team decides based on your weight trend, nutrition and overall health rather than a fixed date.
Can I have a neck lift while taking weight-loss medicine?
It depends on whether your weight is still changing. Medicines in the GLP-1 receptor agonist class slow stomach emptying and reduce appetite, and ongoing loss can undo surgical results. Anesthesia teams also consider stomach emptying when planning. Never stop or adjust these medicines on your own; the prescribing clinician and surgeon coordinate timing together.
Will a neck lift after weight loss leave visible scars?
Incisions are placed in the crease under the chin and around and behind the ears, sometimes extending along the hairline when there is a lot of excess skin. Scars fade from pink toward pale over months but never disappear completely, and thin skin can make them slightly more noticeable. Smoking and tension at closure increase the chance of wider scars.
Is a neck lift permanent?
The skin removed does not grow back, but aging continues and the remaining skin, already low in elastin after weight loss, will loosen again gradually. Significant weight regain stretches tightened tissue and shortens how long the result lasts. Maintaining a stable weight, protecting the skin from the sun and not smoking help preserve the outcome, though no surgeon can promise a specific duration.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
How an Endoscopic Brow Lift Is Performed: Small Incisions, Cameras and Fixation Explained
An endoscopic brow lift is done under general anesthesia or sedation through several short incisions hidden in the scalp. A pencil-thin camera lets the…

What VASER Liposuction Is: How It Works, Who It Suits and What Recovery Involves
VASER liposuction is a branded form of ultrasound-assisted liposuction. A thin probe delivers pulsed ultrasound energy into fat that has first been swollen with…

How Long Botox Takes to Work: Timeline, Peak Effect and How Long Results Last
Botulinum toxin injections, commonly known by the brand name Botox, usually begin to soften muscle movement within one to three days, with visible smoothing…

Scars After Surgery: The Healing Timeline, When to Start Treatment and Which Creams Help
Most surgeons advise starting scar treatment once the incision has fully closed and any stitches or glue are gone, typically about two weeks after…

Genioplasty Recovery Week by Week: Swelling, Numb Chin and Getting Back to Solid Foods
Genioplasty recovery time typically unfolds in stages: swelling peaks around the second or third day, most visible puffiness settles within two weeks, and desk…

Plastic Surgery for Men: What Is Actually Popular, and What a Daddy Makeover Includes
The cosmetic surgeries men choose most often are gynecomastia (male breast reduction) surgery, liposuction, eyelid lifts, rhinoplasty, and neck or facelift procedures. A daddy…