

Preparing for Restorative Dental Treatment: Medications, Diabetes and Past Anesthesia

Key Takeaways
- For most fillings, crowns and root canals, anticoagulant and antiplatelet medicines are continued rather than stopped, with bleeding controlled locally, and any change is the prescriber's decision.
- The American Heart Association now recommends preventive antibiotics before certain dental procedures only for the highest-risk cardiac conditions, such as prosthetic valves or previous endocarditis.
- A racing heart or faintness after a dental injection is usually a response to epinephrine or anxiety rather than a true allergy, and an epinephrine-free anesthetic is a common alternative.
- People with diabetes are generally asked to eat and take medicines as normal when only local anesthesia is planned; fasting applies to sedation or general anesthesia, when the diabetes team adjusts treatment.
- Numbness from dental local anesthetic typically fades within a few hours, so hot drinks and chewing on that side should wait until sensation returns.
- The so-called 3-3-3 and 50-40-30 rules are not clinical guidelines; mainstream guidance is twice-daily brushing with fluoride toothpaste for about two minutes.
Preparing for restorative dental treatment such as fillings, crowns, root canal work or implants mostly means sharing information: a complete list of your medicines including blood thinners and supplements, how your diabetes is currently controlled, any past reaction to local or general anesthesia, and heart or joint conditions. Your dentist and prescribing doctor then decide together whether anything needs adjusting; you should never change a prescribed medicine on your own.
The appointment card says “crown prep, upper left.” What it does not say is what to do about the small pill you take each morning to keep your blood from clotting, or whether the insulin pen belongs in your bag, or how to explain that the last time a dentist numbed your jaw your heart raced so hard you thought you were having an attack. Most people arrive with one of these questions half-formed and never quite ask it.
That silence is the real risk. Preparing for restorative dental treatment is rarely about what you do to your teeth the night before. It is about what your dentist knows about the rest of you before the first instrument touches enamel. Medications, blood sugar and anesthesia history shape how a routine procedure is planned, timed and, occasionally, postponed.
This explainer walks through those three areas the way a careful clinician would, with the evidence attached and the decisions left where they belong: with the team treating you.
Why preparing for restorative dental treatment starts with your medical history, not your toothbrush
“Restorative” is a broad word. In dentistry it covers any treatment that rebuilds a tooth or replaces a missing one: fillings, inlays and onlays (lab-made fillings that fit into or over a tooth), crowns (a cap that covers the whole visible tooth), bridges, root canal treatment and implants. What unites them is that a dentist removes damaged tissue and puts something durable in its place.
Every one of those procedures involves at least one of three things that interact with the rest of your body: a local anesthetic injection, bleeding from gum or bone, and a wound that has to heal. That is why the medical history form matters more than most people assume. A dentist reading that you take an anticoagulant, live with type 2 diabetes, or once fainted after an injection is not being nosy. Those three facts change how the visit is sequenced.
Consider how differently the same crown appointment can run. For one person it is a single morning with a routine injection. For another, the dentist first checks a recent blood test, books the earliest slot so a meal is not skipped for too long, chooses an anesthetic without epinephrine, and schedules an extra follow-up. The tooth work is identical. The preparation is not.
The Mayo Clinic notes that untreated decay progresses through enamel into the softer dentin and eventually the pulp, where nerves and blood vessels sit. Restorative work aims to stop that progression. Good preparation simply makes sure the body around the tooth is ready for the repair.
The rest of this article takes each area in turn, then brings them together in a summary table and a list of questions worth carrying into the consultation.
What actually happens during a filling, crown or root canal?
Most restorative visits follow the same skeleton. The dentist confirms the tooth, often with a small X-ray, then numbs the area. A local anesthetic is a medicine injected near the nerve that temporarily blocks pain signals; according to the NHS, the numbness usually wears off within a few hours. Many dental anesthetics also contain a small amount of epinephrine (adrenaline), which narrows local blood vessels so the numbness lasts longer and bleeding is reduced.
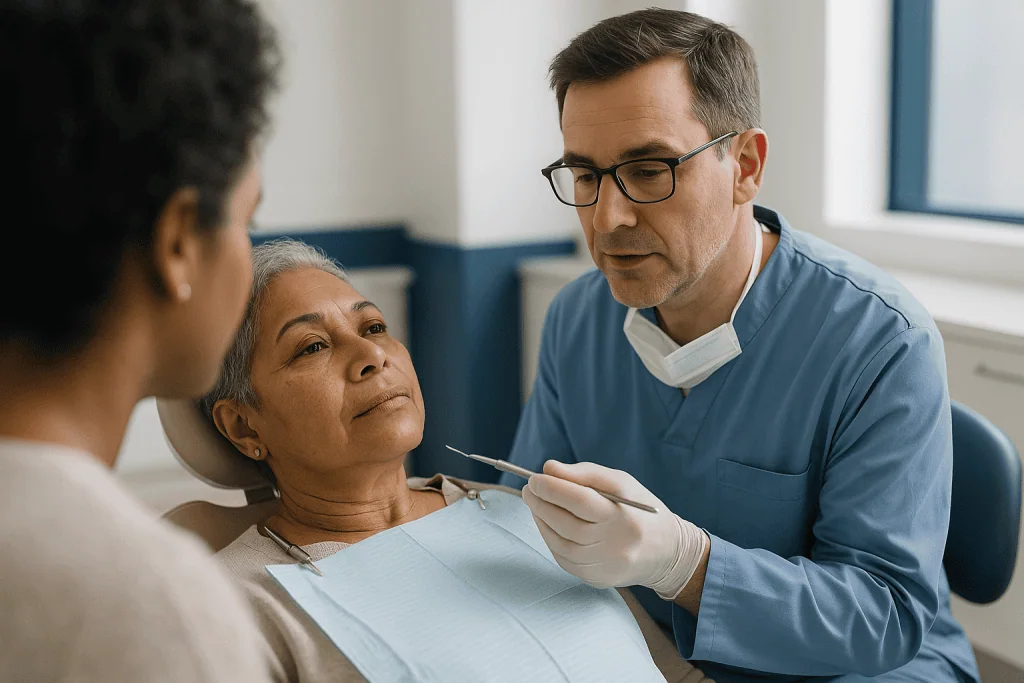
For a filling, decayed tissue is removed with a rotary or hand instrument and the cavity is filled with composite resin, glass ionomer or amalgam, then shaped and polished. For a crown, the tooth is reduced on all sides to make room for the cap, an impression or digital scan is taken, and a temporary crown protects the tooth until the final one is fitted at a second visit.
Root canal treatment goes deeper. The dentist opens the top of the tooth, removes inflamed or infected pulp from the root canals, cleans and shapes them, and seals them with a rubber-like filling material. The NHS describes this as usually taking one or two appointments, with a crown often recommended afterward because a root-treated tooth is more brittle.
An implant is different again: a titanium post is placed into the jawbone under local anesthesia, sometimes with sedation, and left to fuse with bone over several months before a crown is attached.
Notice the common threads. Every procedure involves an injection, most involve some bleeding, and all leave tissue that needs to heal. Those threads are exactly where medications, blood sugar and anesthesia history come into play.
Which medications before dental work should I tell my dentist about?
The honest answer is all of them, but a few categories deserve a spoken mention rather than a scribble on the form. Bring an up-to-date list or the boxes themselves; memory under mild anxiety is unreliable.
- Anticoagulants and antiplatelet medicines (warfarin, the newer direct oral anticoagulants, aspirin, clopidogrel). These reduce clotting and are discussed in detail below.
- Diabetes medicines, including insulin and tablets that can lower blood glucose.
- Bisphosphonates and other bone-modifying drugs, taken for osteoporosis or some cancers. They slow bone turnover and, rarely, are linked with delayed jawbone healing after procedures that disturb bone, such as implants or extractions.
- Immunosuppressants and steroids, which affect infection risk and healing.
- Blood pressure and heart rhythm medicines, because epinephrine in dental anesthetic can nudge heart rate and pressure upward.
- Supplements and herbal products. Some fish-oil, ginkgo and high-dose vitamin E preparations have mild blood-thinning effects. They count as medicines for this purpose.
Recent changes matter as much as the list itself. A dentist wants to know if a dose was altered last month, if a new medicine was added, or if you stopped something on your own. Allergies belong here too, along with the specific reaction: a rash, swelling, breathing trouble or simply nausea.
What you should not do is decide which medicines are “dental-relevant” and leave the rest off. A medicine for glaucoma, a hormone treatment or an antidepressant can each interact with anesthetics or sedatives in ways a patient would have no reason to predict. Let the clinician filter the list. That is the whole point of the conversation.
Blood thinners and dental treatment: what the evidence actually shows
Few topics generate more worried phone calls. People on warfarin or a direct oral anticoagulant often assume they must stop it before a filling or root canal. For most routine restorative work, current dental and cardiology guidance leans the other way: interrupting anticoagulation carries a real risk of stroke or clot, while bleeding from a dental procedure is usually manageable with pressure, sutures, absorbable dressings and mouthwash rinses in the chair.

Fillings and crowns typically cause little bleeding because they work on the tooth rather than soft tissue. Root canal treatment bleeds even less once the pulp is removed. Procedures that cut gum or bone, such as implants, gum surgery or extractions performed alongside restorative work, sit in a higher-bleeding category and prompt more planning.
Planning does not mean stopping. For people on warfarin, the dentist may ask for a recent INR, a blood test measuring how long blood takes to clot, so the procedure is scheduled when the result is in the expected range. For those on newer anticoagulants, the timing of the daily dose relative to the appointment is sometimes adjusted, but only by the prescribing doctor. Antiplatelet medicines after a stent or heart attack are generally continued; stopping them early is associated with serious cardiac events.
The principle to hold onto is simple: no one, including the patient, changes an anticoagulant for dental reasons without the prescriber being in the loop. If a dentist suggests a change, they will communicate with the doctor managing the medicine, or ask you to. If a well-meaning relative suggests “just skip it that morning,” that is a conversation for the clinic, not the kitchen.
Expect some oozing afterward and ask how to manage it. Prolonged bleeding that soaks through gauze for hours is a reason to call, covered later in this article.
Diabetes and dental treatment: how blood sugar changes the plan
Diabetes and the mouth have a two-way relationship. The CDC notes that people with diabetes are more likely to develop gum disease, and that severe gum disease can in turn make blood glucose harder to control. High glucose also means more sugar in saliva, feeding the bacteria that cause decay, and slower healing because high sugar impairs the small blood vessels and immune cells that repair tissue.
For a dentist planning restorative work, three practical questions follow. First, how well is the diabetes controlled right now? Many teams ask for a recent HbA1c, a blood test reflecting average glucose over roughly the previous two to three months, as described by the National Institute of Dental and Craniofacial Research. Persistently high readings may lead a dentist to prioritize gum treatment or coordinate with the diabetes team before elective implants.
Second, when should the appointment be? Early or mid-morning slots are commonly favored so that a meal is not delayed and glucose is usually more predictable. If only local anesthetic is planned, people are generally told to eat and take medicines as usual; a numb mouth afterward may make eating awkward, so a soft option at home helps.
Third, what if sedation or general anesthesia is involved? Fasting is then required, and fasting changes how insulin and some tablets behave. That adjustment is made by the doctor who prescribes them, with the anesthesia team, never by the patient guessing.
Bring your glucose meter or wear your sensor, and mention if you have had recent hypoglycemia (low blood sugar), since stress and a skipped snack can lower glucose further. A dentist who knows this can pause and check rather than mistake shakiness for nerves.
Do I need antibiotics before dental work if I have a heart condition or joint replacement?
For decades, anyone with a heart murmur was handed antibiotics before a cleaning. That practice has narrowed sharply. The American Heart Association now recommends preventive antibiotics before certain dental procedures only for people at highest risk of infective endocarditis, an infection of the heart’s inner lining or valves. The AHA lists prosthetic heart valves or valve repair material, a previous episode of endocarditis, specific forms of congenital heart disease, and heart transplant recipients who develop valve problems.
The reasoning is evidence-based. Everyday activities such as brushing and chewing release bacteria into the bloodstream far more often than an annual dental visit, so good daily oral hygiene protects the heart more than a pre-appointment antibiotic ever could. The AHA also notes that antibiotic side effects and resistance carry their own risks.
Which dental procedures count? Those that manipulate the gum tissue or the area around the root of a tooth, or perforate the mouth lining. Straightforward fillings above the gumline usually do not; root canal work, crown preparation that extends beneath the gum, and implant placement may.
Joint replacements are a separate question with a similar trajectory. Routine antibiotic cover before dental treatment is no longer generally recommended for most people with an artificial hip or knee, though the orthopedic surgeon may advise otherwise in specific circumstances, such as a compromised immune system or a history of joint infection.
If you fall into any of these groups, tell both the dentist and the cardiologist or surgeon. They decide whether an antibiotic is warranted, which one, and when. A patient’s job is to make sure the two teams know about each other.
Past reaction to dental anesthesia: what your dentist needs to know
“I’m allergic to the numbing injection” is one of the most common statements in a dental history, and one of the least often accurate. The NHS describes serious reactions to local anesthetics as rare. What people usually remember is something else entirely.
The racing heart, trembling and light-headedness that follow an injection are most often a response to the epinephrine mixed into the anesthetic, or to adrenaline released by anxiety itself. Fainting is typically a vasovagal response, a brief drop in heart rate and blood pressure triggered by pain, sight of a needle or standing up too fast. Prolonged numbness or tingling can occasionally follow a nerve being brushed by the needle. None of these are allergies, but all are worth reporting, because each has a different solution.
A true allergy to the amide local anesthetics used today, such as lidocaine or articaine, is uncommon; historical reactions were more often to preservatives or to an older class of anesthetics. If you had hives, facial swelling or breathing difficulty, say so precisely, and bring any allergy clinic letters.
General anesthesia and sedation have their own history questions. A family or personal history of malignant hyperthermia, a rare inherited reaction to certain anesthetic gases, changes drug choice completely. Difficult intubation, severe nausea after past anesthesia, or unexpected slow waking should all be mentioned. So should sleep apnea, which affects how sedatives are given.
The more specific your description, the more useful it is. “My heart pounded for ten minutes after the injection” leads a dentist to consider an epinephrine-free anesthetic. “I felt unwell” leads nowhere. Describe what happened, when, and how it resolved.
Who is usually a good candidate for restorative treatment, and who is asked to wait?
Most adults are suitable for restorative work most of the time. The question is rarely “can this person have a crown” and more often “is this the right week.”
Good timing usually looks like this: stable chronic conditions, medicines unchanged for a while, blood glucose in the range agreed with the diabetes team, blood pressure controlled, and no active infection elsewhere. In that setting, fillings, crowns and root canal treatment go ahead with standard local anesthesia.
Situations where dentists commonly pause elective work include a very recent heart attack, stroke or stent placement, because the cardiology team usually wants a recovery period and stable antiplatelet therapy before non-urgent procedures. Markedly uncontrolled diabetes, with symptoms of very high glucose, is another; the priority becomes stabilizing sugar, and implants in particular may be deferred because bone healing depends on it. Active chemotherapy or a recent course of intravenous bone-modifying medicine leads many dentists to consult the oncologist before anything that disturbs jawbone.
Pregnancy deserves a nuanced note. Routine and urgent restorative care is generally considered safe, and untreated infection carries its own risks; purely elective cosmetic work is often deferred until after delivery. Local anesthesia and shielded dental X-rays are widely regarded as acceptable when clinically needed.
Waiting is not the same as refusing. Pain and infection do not respect the calendar, so a tooth that hurts today is usually treated today, with the plan adapted rather than abandoned. What gets postponed is the optional: replacing an old but intact filling, or starting an implant sequence that can begin next month with no harm.
The people who decide are the dentist and your other clinicians, together. A short letter or phone call between them resolves most uncertainty.
When is a tooth not restorable?
Dentists lean toward saving teeth, but there is a threshold beyond which repair is unlikely to last, and knowing it helps patients understand why an extraction is sometimes recommended instead of a crown.
The first consideration is how much sound tooth remains above the gum. A crown needs a collar of healthy tooth, sometimes called a ferrule, to grip. When decay or fracture has removed most of that structure, a crown may loosen or the root may split under chewing forces. Decay that has crept well below the gumline or into the bone is hard to seal and keep dry during treatment.
The second is the root itself. A vertical root fracture, a crack running lengthwise through the root, cannot be filled and usually condemns the tooth. Roots that are very short, curved in ways that block cleaning, or already resorbed (dissolved by the body) offer little to anchor.
The third is the foundation. Advanced gum disease that has destroyed much of the supporting bone can leave a tooth mobile; restoring the crown of a tooth that wobbles at its roots rarely holds. The Mayo Clinic lists extraction as the option when decay is so severe the tooth cannot be restored.
Diabetes and medications enter this judgment too. A tooth that is borderline restorable in someone with excellent healing may be a poorer bet where glucose control is erratic or bone-modifying drugs slow repair, because a failed restoration leads to a second procedure in compromised tissue.
“Not restorable” is a clinical opinion, not a verdict on your care. Asking what makes this particular tooth unsuitable, and what replacement options exist, is a fair and expected question.
How painful is tooth restoration, really?
Fear of pain keeps more people away from restorative care than any medical condition. The realistic picture is less dramatic than the anticipation.
During the procedure, local anesthetic blocks pain from the tooth and surrounding gum. What remains is pressure, vibration and sound. Some people find the sensation of a drill on a numb tooth unsettling even when it does not hurt; telling the dentist so allows breaks, a hand signal to pause, or a discussion of sedation for longer appointments. The injection itself is often the most uncomfortable moment, a brief sting and pressure that topical numbing gel can soften.
Root canal treatment carries a fearsome reputation it largely does not earn. The NHS describes it as usually no more unpleasant than having a filling, since the inflamed nerve being removed is the source of the pain, and the procedure is performed under local anesthesia. An acutely inflamed tooth can be harder to numb completely, and dentists have techniques for that, including supplementary injections.
Afterward, expect the tooth and gum to feel tender for a few days, particularly to biting. Sensitivity to cold after a deep filling can linger for a few weeks as the pulp settles. A temporary crown may feel rough or slightly high. Over-the-counter pain relief, chosen with your pharmacist or doctor if you take other medicines, is the usual approach; this article deliberately gives no dosing.
What pain should not do is escalate. Throbbing that worsens over days, swelling, or pain that wakes you at night after the first couple of days points toward infection or a high bite and needs a call, not endurance. Discomfort that steadily fades is the expected course.
Preparing for restorative dental treatment: a summary table by situation
The details above can be condensed into a single reference. This table describes what dentists typically ask about and why; none of it substitutes for the individual instructions your own team gives you.
| Your situation | What the dentist usually wants to know | Common planning adjustments | Who decides any medicine change |
|---|---|---|---|
| Anticoagulant or antiplatelet medicine | Which medicine, why, recent INR if on warfarin | Usually continued; local bleeding control; scheduling around dose timing | Prescribing doctor with dentist |
| Diabetes | Recent HbA1c, medicines, hypoglycemia history | Morning appointments; eat normally for local anesthesia; gum health prioritized | Diabetes team, especially if fasting is needed |
| Heart valve disease, prior endocarditis, certain congenital heart conditions | Exact diagnosis, cardiologist’s advice | Preventive antibiotic considered only for highest-risk groups per AHA | Cardiologist and dentist |
| Past reaction to local anesthetic | Precise symptoms, timing, allergy testing results | Epinephrine-free anesthetic, slower injection, lying flat | Dentist, with allergist if true allergy suspected |
| Past problem with sedation or general anesthesia | Nausea, slow waking, airway difficulty, family history of malignant hyperthermia | Different agents; anesthesia team consulted | Anesthesia team |
| Bone-modifying medicines | Drug, route, duration, reason | Fillings and crowns proceed; bone-disturbing work reviewed | Prescriber and dentist |
Two patterns stand out. Almost every row says “usually continued” or “proceed,” because most restorative dentistry is compatible with most medical conditions once the team knows about them. And the final column never says “the patient.” That is deliberate. The information flows from you; the decisions flow back from the clinicians who can weigh a dental benefit against a medical risk.
If your situation spans several rows, say so early. A person with diabetes on an anticoagulant with a mechanical valve is not unusual, and a dentist who hears all three at the first visit can coordinate one set of enquiries rather than three.
What the days and weeks after restorative treatment usually look like
Recovery from most restorative dentistry is measured in days, and the pattern is fairly predictable.
The first few hours belong to the anesthetic. Numbness of lip, cheek and tongue fades over a few hours according to the NHS; until it does, hot drinks and chewing on that side risk burns or bites you cannot feel. For people with diabetes this window matters, since a planned meal may be delayed; a soft, cool option keeps glucose on track.
Days one to three bring tenderness at the injection site and around the treated tooth. Biting may feel odd on a new filling or temporary crown; a bite that feels clearly “high” on that tooth alone is worth a quick adjustment rather than a wait. Mild sensitivity to cold is common after deep fillings and typically eases over the following weeks.
For root canal treatment, the NHS notes the tooth may be tender for a few days and that a crown is usually fitted afterward to protect it. Between visits, avoid hard foods on that side; a temporary filling can chip.
People on anticoagulants may notice slight oozing or a pink tinge in saliva during the first day. Gentle pressure with clean gauze usually settles it. Those with diabetes should watch healing gums more closely; the CDC links high glucose with slower wound healing, so redness that spreads rather than shrinks over several days deserves a call.
Implants run on a longer clock. The post integrates with bone over months, during which the site should be kept clean and undisturbed, and the final crown follows once the dentist confirms stability. Follow-up visits are part of the treatment, not an optional extra, and skipping them is where otherwise smooth recoveries go quietly wrong.
What people often get wrong about preparing for dental work
Search engines are full of “rules” for dental care, and some of the most popular ones do not appear in any clinical guideline.
The 3-3-3 rule. This usually refers to brushing three times a day, for three minutes, within three minutes of eating. It is a memorable slogan, not an evidence-based standard. Mainstream guidance from the NHS and others recommends brushing twice daily with a fluoride toothpaste for about two minutes, and waiting a while after acidic food so softened enamel is not scrubbed away. Brushing more is not automatically better.
The 50-40-30 rule. Despite how often it is searched, this is not a recognized term in dental or medical guidelines. It appears in various forms in practice-management and smile-design discussions, with inconsistent meanings. If a clinician uses it, ask what they mean; it is not something you need to know to prepare for treatment.
“Stop your blood thinner before the dentist.” As discussed above, most routine work proceeds with anticoagulation continued and local bleeding control. Stopping on your own initiative is the risky move, not the safe one.
“Skip breakfast to be safe.” Fasting is required before sedation or general anesthesia, not before local anesthetic. For someone with diabetes, an unnecessary fast invites hypoglycemia in the chair.
“I’m allergic to the numbing agent.” A racing heart after an injection is far more often an epinephrine or anxiety response than an allergy, and the two have very different solutions.
“Everyone with a heart murmur needs antibiotics.” The American Heart Association narrowed this to specific highest-risk conditions years ago.
The common thread is that preparation works best as a conversation, not a set of rituals. Most of the rules people follow do less good than a single accurate medicine list.
Questions to ask your care team before restorative dental treatment
A good consultation leaves you knowing not just what will be done to the tooth but how your health fits around it. These questions tend to draw out the answers that matter.
- Which of my medicines are relevant to this procedure, and will you be contacting my doctor about any of them?
- Should I take everything as normal on the day, including my diabetes medicines, and should I eat beforehand?
- Do you need any recent blood results, such as an HbA1c or INR, before we book?
- Given my heart condition or joint replacement, is any preventive antibiotic recommended, and who makes that call?
- Which anesthetic will you use, and does it contain epinephrine? Is there an alternative if I have reacted before?
- If sedation is being considered, who will provide it and what is the fasting instruction?
- Is this tooth restorable in the long term, and what would you recommend if it is not?
- What are the alternatives to the treatment you are proposing, and what happens if I choose to wait?
- How much bleeding and discomfort should I expect afterward, and what would make you want to see me sooner?
- How many visits will this take, and how long will a temporary restoration be in place?
- Who do I call if something feels wrong out of hours?
Write the answers down or ask for them in the treatment summary. People remember roughly half of what is said in a medical consultation, and less when anxious. If any answer involves changing a prescribed medicine, ask explicitly whether your prescribing doctor has agreed; a good team will already have made that contact or will tell you exactly how it will happen.
None of these questions is a challenge to the dentist’s judgment. They are the raw material that lets the judgment be made well.
When to call your doctor or dentist after restorative dental treatment
Most recovery is uneventful, but a short list of red flags should prompt a same-day call to the dental practice, your doctor, or emergency services depending on severity.
- Bleeding that does not stop with firm pressure for a sustained period, or that soaks through gauze repeatedly, especially if you take an anticoagulant.
- Swelling that spreads into the face, neck or under the jaw, or that makes swallowing or breathing difficult. Difficulty breathing or swallowing is an emergency.
- Fever, feeling generally unwell, or a bad taste with pus around the treated tooth, which suggest infection.
- Pain that worsens after the first two or three days instead of easing, or that wakes you at night.
- Numbness that persists well beyond the expected few hours, particularly if it lasts into the next day.
- Signs of an allergic reaction after an injection or a new medicine: hives, facial or tongue swelling, wheeze or faintness. Call emergency services.
- Blood glucose readings well outside your usual range that you cannot correct with your normal plan, or repeated hypoglycemia after the appointment.
- Chest pain, palpitations that do not settle, or sudden weakness, facial droop or slurred speech at any point. These need emergency care regardless of the dental work.
Less urgent but still worth a call: a filling or temporary crown that comes out, a bite that feels high, sharp edges cutting the tongue, or sensitivity that is not improving after a few weeks.
When in doubt, call. Dental teams would far rather hear about a concern that turns out to be minor than see a preventable complication at the next scheduled visit. Any decision about medicines, further treatment or referral rests with the clinicians treating you; this list exists only so you know when to reach them.
Frequently asked questions
What is the 3-3-3 rule for dental care?
The 3-3-3 rule is an informal slogan meaning brush three times a day, for three minutes, within three minutes of eating. It is not a clinical guideline. Mainstream guidance recommends brushing twice daily with fluoride toothpaste for about two minutes and avoiding brushing immediately after acidic foods, when enamel is softened. Brushing more often does not add protection.
How painful is tooth restoration?
Restorative procedures are performed under local anesthesia, so during treatment most people feel pressure and vibration rather than pain; the injection is often the most uncomfortable moment. Afterward, tenderness for a few days and cold sensitivity for a few weeks are common. Pain that worsens after the first days, or swelling, is not expected and should be reported to the dental team.
When is a tooth not restorable?
A tooth is usually judged not restorable when too little sound structure remains above the gum to hold a crown, when a vertical root fracture is present, when decay extends deep below the bone level, or when advanced gum disease has left the tooth loose. In such cases extraction and replacement are discussed. The judgment is individual and worth asking your dentist to explain.
What is the 50-40-30 rule in dentistry?
There is no recognized clinical guideline called the 50-40-30 rule in dentistry. The phrase appears with inconsistent meanings in practice-management and smile-design discussions. It is not something patients need to understand to prepare for restorative treatment; if a clinician uses the term, simply ask what they mean by it in your case.
Which medications before dental work should I mention?
Mention every medicine, but speak up specifically about anticoagulants and antiplatelets, diabetes medicines, bone-modifying drugs for osteoporosis or cancer, steroids and immunosuppressants, heart and blood pressure medicines, and supplements such as fish oil or ginkgo. Include recent changes and any allergies with the exact reaction. Let the dentist filter what is relevant rather than leaving items off.
How does diabetes and dental treatment planning fit together?
Dentists usually ask how well your diabetes is controlled, often via a recent HbA1c, because high glucose slows healing and increases gum disease risk. Appointments are commonly scheduled in the morning, and you are generally told to eat and take medicines normally when only local anesthetic is used. Any adjustment for fasting before sedation is made by your diabetes team.
What dental anesthesia side effects should I report from past visits?
Report a racing heart, trembling, fainting, prolonged numbness, hives, swelling or breathing difficulty, and describe timing and duration. Most palpitations reflect epinephrine or anxiety rather than allergy, and an epinephrine-free anesthetic is often available. For sedation or general anesthesia, mention severe nausea, slow waking, airway difficulty, sleep apnea, or a family history of malignant hyperthermia.
Should I stop my blood thinner before a filling or root canal?
Not on your own. Current dental and cardiology guidance generally favors continuing anticoagulant and antiplatelet medicines for routine restorative work, because stopping raises stroke and clot risk while dental bleeding can usually be controlled in the chair. Your dentist may check a recent INR or coordinate timing with your prescribing doctor, who alone decides any change.
Do I need antibiotics before dental work if I have a heart murmur?
Usually not. The American Heart Association recommends preventive antibiotics before certain dental procedures only for people at highest risk of infective endocarditis, including those with prosthetic valves, previous endocarditis, specific congenital heart conditions, or transplant-related valve disease. A simple murmur alone is not on that list. Your cardiologist and dentist make the decision together.
How long does numbness last after restorative dental treatment?
The NHS describes numbness from a dental local anesthetic as wearing off over a few hours. Until it does, avoid hot drinks and chewing on the numb side to prevent burns or bites. Numbness lasting into the next day is unusual and should be reported to the dental practice, as it can indicate irritation of a nerve.
References
- NHS: Local anaesthesia
- NHS: Root canal treatment
- NIH National Institute of Dental and Craniofacial Research: Diabetes & Oral Health
- CDC: Diabetes and Oral Health
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What You Can and Cannot Eat with Braces: Safe Foods, Risky Foods and Practical Swaps
With braces, avoid foods that are hard, sticky, chewy or need biting into: whole apples, corn on the cob, popcorn, nuts, hard candy, caramel,…
How Bleeding Gums Are Treated at the Dentist: From Gum Measurements to Deep Cleaning
Dentists treat bleeding gums by first measuring the space between gum and tooth with a thin probe, then removing the plaque and hardened tartar…

Who May Benefit From Orofacial Myology? Children, Braces Patients and Mouth Breathers
Orofacial myofunctional therapy is most often considered for three groups: children with persistent thumb-sucking, tongue-thrust or open-mouth resting posture; people in or about to…

What Oral Health Therapy Changes Over Time: Gum Health, Breath and Follow-Up Visits
Oral health therapy results build gradually. Gum bleeding and tenderness usually settle within a few weeks of professional cleaning and better daily brushing, gum…
Teeth Whitening Myths: Enamel Damage, Baking Soda and Other Claims Dentists Correct
Most teeth whitening myths collapse under evidence. Dentist-supervised peroxide whitening does not dissolve or thin healthy enamel; it oxidizes stain molecules inside the tooth.…

Tooth Extraction Healing Timeline: The Socket From the First Day to the Fourth Week
After a tooth extraction, a blood clot forms in the socket within the first day, soft granulation tissue replaces it over the following week,…