

Preparing Your Child for Pediatric Plastic Surgery: Evaluations, Tests and Talking It Through

Key Takeaways
- Most pediatric plastic surgery is reconstructive, and the CDC estimates about 1 in 1,600 US babies is born with a cleft lip together with a cleft palate.
- Healthy children having minor procedures usually do not need routine blood tests; testing is ordered to answer a specific question from the history or exam.
- The NHS describes cleft lip repair usually at about 3 to 6 months and palate repair at about 6 to 12 months, illustrating that timing follows tissue growth, not a single best age.
- Deaths caused by general anesthesia are very rare, on the order of 1 per 100,000 anesthetics according to the NHS, while nausea and a sore throat are common short-term effects.
- Telling a preschooler a day or two ahead and a school-age child about a week ahead, in honest concrete language, is associated with better coping than surprise.
- Scar appearance depends mainly on skin type, wound tension, infection, and sun exposure, so protection and patience outweigh any over-the-counter product.
Preparing a child for plastic surgery usually means a consultation with the surgical team, a separate anesthesia assessment, and only the tests the child's health history calls for, since routine blood work is often unnecessary. Parents help most by explaining the plan in age-appropriate, honest language, following fasting instructions exactly, and asking the care team about timing, alternatives, and recovery.
The folder sits on the kitchen counter for a week before anyone opens it. Inside are consent forms, a fasting sheet, a map of the surgical wing, and a page titled “What to tell your child.” Upstairs, a seven-year-old is asleep with one ear folded under the pillow, unaware that the appointment her parents keep half-mentioning is about that ear.
Most families preparing a child for plastic surgery describe the same odd mix: relief that something can be done, and a low hum of worry about anesthesia, scars, and how to say the word “operation” without frightening anyone. The procedure itself may take an hour. The preparation stretches across weeks and involves far more conversation than cutting.
This guide walks through what the evaluations look for, which tests are genuinely needed, how anesthesia teams approach children, and how to talk it through with a toddler, a nine-year-old, or a teenager who has strong opinions of their own.
What does pediatric plastic surgery usually mean, and how much of it is cosmetic?
The phrase “plastic surgery” carries a lot of cultural baggage that has little to do with children’s hospitals. In pediatric practice, the overwhelming majority of procedures are reconstructive: surgery that restores the form or function of a part of the body affected by a congenital difference, an injury, or a tumor. The word “plastic” comes from the Greek for “to mold” and predates any notion of elective beauty work.
The list is broader than many parents expect. Cleft lip and cleft palate repair sits at the center of most pediatric plastic surgery programs. A cleft is a gap left when parts of the lip or the roof of the mouth do not fuse before birth; the CDC estimates that roughly 1 in 1,600 babies in the United States is born with a cleft lip together with a cleft palate, about 1 in 2,800 with a cleft lip alone, and about 1 in 1,700 with a cleft palate alone. Beyond clefts, surgeons treat prominent ears, extra or fused fingers (syndactyly, where two or more fingers are joined by skin or bone), large birthmarks, burns, scars that pull on joints, facial fractures from falls and sports, and skull-shape differences managed with craniofacial teams.
Purely cosmetic procedures in minors are a small slice and are approached cautiously. Ear-setback surgery, technically called otoplasty, is the one that most often straddles the line: it does not change hearing, yet its impact on a child who is being teased can be substantial. Teams generally treat these requests as they would any medical decision, weighing physical maturity, the child’s own wishes, and the realistic benefit against the risks of an anesthetic and an operation.
Knowing which category your child’s procedure belongs to matters for one practical reason: it shapes how the team talks about urgency, timing, and whether waiting is a reasonable option.
How preparing your child for plastic surgery works, step by step
Think of the pathway as three separate conversations that happen to lead to one morning in an operating room. Each has its own purpose, and understanding the sequence removes a surprising amount of anxiety.
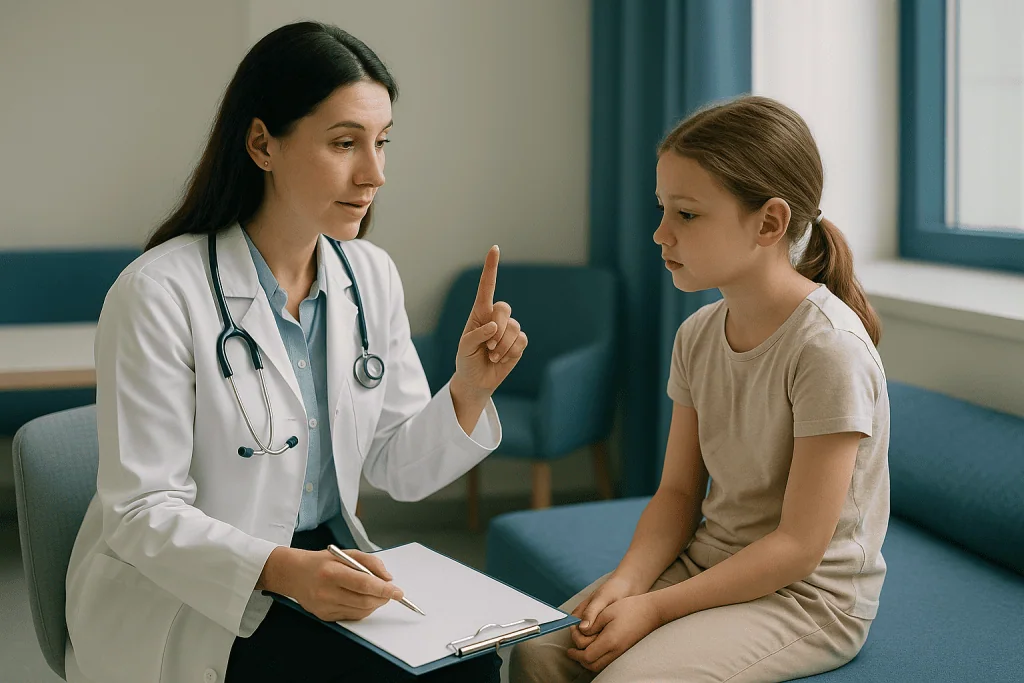
The first conversation is with the surgeon. A referral, usually from a pediatrician or a craniofacial or hand team, leads to a consultation where the surgeon examines the child, explains what the operation would involve, and discusses alternatives, which sometimes include doing nothing for now. Photographs are often taken for the medical record and for planning; these are protected health information, not marketing material, and you can ask how they are stored.
The second conversation is with the anesthesia team. An anesthesiologist is a physician who keeps a patient asleep, comfortable, and physiologically stable during surgery. For children, this assessment may happen at a pre-operative visit, by phone, or on the morning of surgery, depending on the child’s health and the complexity of the procedure. It is where fasting instructions, breathing history, and any previous reactions to anesthesia get discussed.
The third conversation is the one you have at home, repeatedly and in small doses, with your child. Many pediatric programs support this with a child life specialist, a professional trained to help children understand medical events through play, pictures, and rehearsal. Ask whether a tour, a video, or a practice session with a mask is available; these are common and often free-standing services.
Between those conversations sit the practical steps: consent forms, a check of vaccination and illness status in the days before, and a plan for who stays with the child afterward. Nothing on this list is rushed in a scheduled case. If your child has a cold or fever near the date, the team will decide whether to postpone, and a postponement for illness is a safety decision, not a setback.
What happens at the evaluation visit
The surgical consultation is longer than a typical clinic appointment because it has to do two jobs at once: assess the child and inform the family. Expect the surgeon to take a full history, including birth history, growth, feeding, breathing during sleep, previous operations, bleeding tendencies in the family, and allergies. For a child with a cleft, the team will also want to know about ear infections and speech, because the same anatomy affects both.
The examination is hands-on and unhurried. For a prominent ear, the surgeon assesses the cartilage’s firmness and the angle at which the ear sits away from the head. For a hand difference, they watch how the child uses the hand in play rather than only how it looks at rest. For a birthmark, they may measure it and note whether it has changed. Children are sometimes examined on a parent’s lap; a good team adapts to the child rather than the reverse.
Then comes the explanation. The surgeon should describe what would be done, what the incisions and scars would look like, what the expected recovery involves, and the main risks in plain language. Risks common to most pediatric plastic procedures include bleeding, infection, poor wound healing, asymmetry, a scar that thickens, and the possibility that a second operation is needed later as the child grows. Alternatives belong in this conversation too, whether that means observation, a splint or molding device, a non-surgical treatment, or a different operation.
Consent is not a signature; it is the outcome of this dialogue. In most jurisdictions a parent or guardian signs, but older children and teenagers are usually asked for their assent, meaning their agreement in their own words. Teams take seriously a teenager who says they do not want an elective procedure, and that is appropriate.
Bring a written list of questions. Most families leave having forgotten at least one, so ask how to reach the team afterward.
Which pre-operative tests does a child actually need?
Here is a point on which mainstream guidance has become steadily more conservative: healthy children scheduled for minor or intermediate surgery usually do not need routine blood tests, chest X-rays, or heart tracings. Pre-operative testing is ordered to answer a specific question raised by the history or examination, not as a ritual. A needle stick that changes nothing about the plan is a harm with no benefit, and pediatric anesthesia teams know it.

That said, testing is sometimes necessary, and knowing why helps you accept it. A child with a known heart condition may need an echocardiogram, an ultrasound picture of the heart. A child with a family history of unusual bleeding, or one facing a longer craniofacial operation where blood loss is expected, may need a blood count and clotting studies. Children on certain long-term medicines, those with kidney disease, or those with syndromes affecting the airway may need additional assessment. Sleep studies are sometimes requested for children with clefts or jaw differences, because obstructed breathing during sleep changes how anesthesia and recovery are managed.
Imaging depends entirely on the procedure. Hand differences may call for a plain X-ray to see the bones beneath fused fingers. Skull-shape surgery relies on a CT scan, a detailed three-dimensional X-ray, and teams use protocols designed to keep radiation as low as possible in children. Simple ear or lip procedures rarely need imaging at all.
Two practical checks matter more than any lab value. The first is a screen for recent illness: a runny nose may be trivial, but a chesty cough or fever in the days before surgery can increase breathing complications under anesthesia and often leads to postponement. The second is a review of every medicine and supplement the child takes, including herbal products and over-the-counter pain relievers, because some affect bleeding or interact with anesthetic drugs. Bring the containers, not just your memory.
If a test is ordered, ask what question it answers. If none is ordered, that is usually good news.
What is the best age for plastic surgery in children, and who is asked to wait?
Parents searching for the “best age” are really asking two questions: when is it safe, and when will it do the most good. The answer differs for every procedure because it depends on how the affected tissue grows and how much the child needs to participate in care afterward.
Cleft repair illustrates the principle. The NHS describes lip repair usually taking place when a baby is about 3 to 6 months old and palate repair usually between 6 and 12 months, timed to support feeding and the beginnings of speech while the child is small enough that scars mature well. Ear setback, by contrast, is typically deferred until the ear cartilage has grown close to its adult shape and the child can understand and tolerate the dressing afterward. Hand surgery for fused fingers is often done in the toddler years so that the fingers can develop independent movement.
| Procedure | Typical timing consideration | Common reasons to wait |
|---|---|---|
| Cleft lip repair | Infancy; NHS cites about 3 to 6 months | Prematurity, weight gain, heart or breathing issues |
| Cleft palate repair | Later infancy; NHS cites about 6 to 12 months | Airway concerns, other planned surgery |
| Fused fingers (syndactyly) | Toddler years, before fine motor patterns set | Complex bone involvement needing staged surgery |
| Prominent ears (otoplasty) | Once cartilage is near adult shape and the child can cooperate | Child does not want it; unrealistic expectations |
| Infant hemangioma (a benign blood-vessel birthmark) | Often observed first; many shrink on their own | Surgery reserved for residual tissue, ulceration, or function |
| Scar revision | After the scar has fully matured | Scar still changing; child still growing rapidly |
Who is asked to wait? Children with an active infection, poorly controlled asthma, or recent respiratory illness; children whose weight or nutrition is not yet where the team wants it; and children whose request is elective but whose own motivation is unclear. Waiting is not a refusal. It is often the plan that gives the best result later.
Preparing kids for anesthesia: what the anesthesia team will ask you
For many parents, the anesthetic worries them more than the operation. That fear deserves a straight answer. General anesthesia, a medicine-induced state of controlled unconsciousness, has become very safe for healthy children; the NHS notes that deaths caused by general anesthesia are very rare, on the order of 1 for every 100,000 anesthetics given, and Mayo Clinic describes serious complications as uncommon in people who are otherwise healthy. Common after-effects are unpleasant but short-lived: nausea, a sore throat from the breathing tube, shivering, and a spell of confusion or crying on waking that pediatric teams call emergence agitation.
The anesthesiologist will ask about snoring or pauses in breathing during sleep, asthma, recent colds, loose teeth, allergies, previous anesthetics and how the child reacted, and any family history of problems with anesthesia. Two inherited conditions in particular, malignant hyperthermia (a dangerous reaction to certain anesthetic agents) and pseudocholinesterase deficiency (slow breakdown of a muscle relaxant), run in families, so mention any relative who had an unexpected reaction.
Parents often ask about effects on the developing brain. The honest summary of current evidence, reflected in Mayo Clinic’s guidance, is that a single, relatively short anesthetic in a young child has not been shown to cause measurable developmental harm, while research continues into repeated or prolonged exposures in children under about three. If your child faces multiple staged operations, raise this directly; the team can explain how they weigh timing.
Practical preparation is simple. Follow fasting instructions to the minute. Tell the team about every medicine and supplement. Ask whether a pre-medicine, a calming drug given before the child goes to the operating room, is planned and what it will look like for your child; whether a parent can be present at the start; and whether the child will go to sleep with a mask or an intravenous line. Children who know which one to expect cope better. So do parents.
Preparing your child for plastic surgery by age: talking to a 3-year-old, a 9-year-old and a teen
Children read anxiety off their parents long before they understand a diagnosis, so the first person to prepare is you. Once you can say “operation” in a calm voice, the rest becomes easier.
Toddlers and preschoolers live in the present and think concretely. Tell a three-year-old a day or two beforehand, not weeks. Use simple, literal words: “The doctor is going to fix your ear while you have a special sleep, and Mommy will be there when you wake up.” Avoid phrases like “put you to sleep,” which some children associate with pets that never came home. Play works better than explanation; a toy medical kit and a stuffed animal who “goes first” let a small child rehearse without fear.
School-age children, including the nine-year-old whose parents most often ask this question, can handle more information and need it about a week ahead. They think in cause and effect and worry about specifics: Will it hurt? Will I wake up in the middle? Can I still play soccer? Answer each honestly. “You’ll have medicine so you don’t feel it, and the doctors watch you the whole time so you stay asleep until it’s finished.” Involve them in decisions they can control, such as which pajamas to bring or which parent walks them in. Give them one honest job, like remembering to tell the nurse about their loose tooth.
Teenagers need privacy, respect, and time with the team without a parent in the room. They may ask questions they will not ask in front of you, and they may have doubts about an elective procedure that they are afraid to voice. A teenager who says “I’m not sure” has given you valuable information. Let the team hear it too.
At every age, tell the truth about pain and about scars. Children forgive discomfort; they do not forgive being misled.
The night before and the morning of: fasting, medicines and what to pack
Fasting is the instruction families most often get slightly wrong, and it is the one that most often leads to a cancelled case. An empty stomach reduces the risk that stomach contents enter the lungs while a child is unconscious, a rare but serious complication called aspiration. The NHS describes the usual pattern for adults as stopping food about 6 hours before and clear fluids about 2 hours before an anesthetic; many pediatric anesthesia teams use shorter clear-fluid windows for children, and the instructions for breast milk and formula differ again. The only rule that matters is your own team’s written sheet. If the time seems odd or you are unsure whether a fruit juice with pulp counts as clear, call and ask.
Regular medicines are the second common question. Some are continued with a sip of water, some are held, and a few must be stopped days in advance because they affect bleeding. Never make that call yourself; the prescribing clinician or the anesthesia team decides, and the decision is written into the plan. The same applies to supplements and herbal products, several of which have effects on clotting or on how the liver processes anesthetic drugs.
Illness in the days before deserves a phone call, not a wait-and-see. A fever, a wet cough, wheezing, vomiting, or a new rash can all change the plan. A mild runny nose in an otherwise well child usually does not.
Packing is simple. Bring a comfort object, a change of clothes with a loose neck or front opening, a phone charger, insurance and identity documents, the medicine containers, and something to occupy waiting time. Leave jewelry and nail polish at home; polish can interfere with the finger clip that monitors oxygen. Remove contact lenses. If your child has a loose tooth, mention it again on arrival; it is a genuine safety point, not a triviality.
What actually happens on the day of surgery
Arrival is early, often well before the scheduled time, because a series of small checks has to happen in order. A nurse confirms identity, allergies, fasting times, and weight, which determines how anesthetic medicines are calculated. The surgeon visits, often marking the operative site with a pen while the child watches, and repeats the consent conversation in shortened form. The anesthesiologist introduces themselves if you have not already met, and this is a good moment for last questions.
Children may be given a calming pre-medicine, usually as a drink, to ease the separation. If so, expect your child to become drowsy, giggly, or uncoordinated over the following minutes; that is the intended effect. Many pediatric units allow one parent to accompany the child into the anesthetic room until the child is asleep, though policies vary, and some children do better without the extra emotion in the room. Ask in advance so no one is surprised at the door.
Going to sleep takes one of two routes. With a mask, the child breathes a sweet-smelling anesthetic gas and drifts off in a minute or two; the intravenous line goes in afterward. With an intravenous route, a numbing cream is often applied first and the medicine works within seconds. Once asleep, the child’s breathing, heart rhythm, blood pressure, oxygen level, and temperature are monitored continuously by a dedicated anesthesia team member who does nothing else.
The operation’s length varies from under an hour for a simple ear or hand procedure to many hours for major craniofacial work. Someone will update you if the time runs long.
Waking happens in a recovery area with one-to-one nursing. Children often cry, thrash, or say things they will not remember; this settles quickly. You will usually be called in once your child is stable enough to be comforted, which is often before they are fully awake.
Pediatric plastic surgery recovery: the first days and weeks
Recovery has a shape that most families recognize in hindsight: a rough first day, a visibly better second, and then a slow, uneven climb with occasional backward steps when a child overdoes it.
Pain is managed with a plan the team writes before you leave, combining scheduled pain relief with comfort measures such as cold packs, distraction, and rest. The prescribing clinician sets the medicines and the schedule; your job is to give them as written and to report if they are not enough. Children are notoriously poor at volunteering that they hurt, so watch behavior: a child who will not move a hand, refuses to eat, or wakes crying at night is telling you something.
Swelling and bruising peak around the second or third day after most facial procedures and then fade over a couple of weeks; this is a general clinical pattern rather than a promise, and your team will describe what to expect for your child’s operation. Dressings and splints protect the repair and should stay on until the team removes or changes them. A bulky head dressing after ear surgery, a cast after hand surgery, and arm restraints after cleft repair to stop fingers finding the mouth all look alarming and are all routine.
Feeding after mouth surgery follows a soft or liquid diet for a period the team specifies. Bathing, school, sports, and swimming each have their own return date; write them down at the follow-up visit rather than guessing.
Scars deserve a longer view. A new scar is red, firm, and slightly raised, and it matures over many months, sometimes longer in children whose skin is still growing. Sun protection on the healing area, gentle massage once the team clears it, and patience do more for the final result than any product. Children who are bothered by a scar’s appearance should have that concern heard; revision is sometimes possible once the scar has fully settled, and the team can say when.
Plastic surgery and children's mental health: what the evidence actually shows
Parents ask two opposite questions here. Will surgery help my child’s confidence? And could it harm their sense of self? Both deserve a careful answer, and the honest one is that the evidence is more limited than either the hopeful or the fearful narrative suggests.
What research on children with visible differences consistently shows is variability. Some children with a cleft, a large birthmark, or prominent ears are teased and withdraw; others are largely untroubled. The distress tracks more closely with peer reactions, family attitudes, and the child’s own coping style than with the size of the difference. That matters for expectations: an operation changes appearance, but a child’s wellbeing rests on a wider base of support. Teams increasingly include psychologists for exactly this reason, and a referral is not a sign that something is wrong.
The concerns about harm cluster around elective procedures in adolescence. Body dysmorphic disorder is a mental health condition in which a person is preoccupied with a perceived flaw that others barely notice; people with this condition are not helped by surgery and are often left more distressed by it. Screening for it is part of responsible practice when a teenager requests cosmetic surgery. A history of disordered eating, depression, or pressure from social media comparisons are also reasons for a team to slow down and involve mental health colleagues before scheduling anything.
None of this means surgery is bad for a child’s mental health. Reconstruction that improves speech, hand function, or the ability to close the eyes or lips carries obvious psychological weight. Ear setback for a child who is being mocked daily can remove a real stressor. What the evidence cautions against is expecting surgery alone to resolve unhappiness that has other roots. Ask the team what they expect the operation to change and what it will not touch. A clear answer to that question is a sign of a thoughtful program.
What people often get wrong about a child's plastic surgery
“Plastic surgery on children is vanity.” Most pediatric plastic procedures restore function: feeding, speech, grasp, eyelid closure, an airway. The minority that are primarily about appearance are approached with more caution, not less, than adult cosmetic surgery.
“Younger is always better because they won’t remember.” Memory is not the deciding factor. Tissue growth, the ability to cooperate with dressings and exercises, and the child’s own voice in the decision all shape timing. Some procedures are best done in infancy; others are deliberately deferred.
“One operation fixes it.” Children grow, and repaired tissue does not always grow at the same pace as the tissue around it. Staged surgery is common in cleft and craniofacial care, and a later revision is not a sign that the first operation failed.
“A good surgeon can guarantee the result.” No surgeon can, and one who promises a specific outcome should raise a question rather than settle one. Healing, scarring, and growth are partly outside anyone’s control.
“If I don’t tell my child, they won’t be scared.” Children who are surprised by a hospital cope worse than children who were prepared. Honest, age-matched information given in advance is one of the few interventions with consistent support in the pediatric literature.
“Scar creams and oils determine the result.” The strongest predictors of a scar’s appearance are the child’s skin type, the tension across the wound, infection, and sun exposure. No over-the-counter product has convincing evidence that it outperforms simple protection and time.
“Anesthesia is the dangerous part.” For a healthy child, general anesthesia is very safe, and the anesthesia team’s assessment is precisely how that safety is maintained. Fear of anesthesia should be discussed, not carried silently into the anesthetic room.
“A teenager who wants surgery should just have it.” A teenager’s request deserves respect and a proper evaluation, including of expectations and mental health. Respect sometimes looks like saying not yet.
Questions to ask your care team, including how to avoid a disappointing result
Families who search for how to avoid “botched” surgery are usually asking how to make a sound decision with incomplete information. The protective steps are unglamorous: confirm training, understand the plan, and insist on clear answers. The questions below are the ones seasoned clinicians say they wish every family asked.
About the team: Is the surgeon board certified in plastic surgery, and does their practice include children regularly? Will a pediatric anesthesiologist or a team experienced with children be involved? Who else, such as speech therapists, hand therapists, or psychologists, is part of my child’s care?
About the operation: What exactly will be done, and what will the scars look like at one year? What are the alternatives, including waiting? What are the most likely complications for this specific procedure, and how are they handled? How many stages might be needed as my child grows?
About anesthesia and safety: How will my child go to sleep, and can I be present? What is your policy if my child has a cold? How is pain managed afterward, and who do I call if it is not controlled?
About recovery: When can my child return to school, sports, swimming, and normal bathing? What does the dressing or splint look like, and how long does it stay on? What signs should send us back to the hospital?
About the decision itself: What do you expect this operation to change, and what will it not change? If my child is unsure, what happens? Is there anyone my child can speak to privately?
Write the answers down. A team that welcomes these questions, answers them without hedging, and is comfortable when you ask for a second opinion is showing you the culture of care your child will receive. A team that rushes past them is showing you something too.
When to call your doctor
Most children recover from plastic surgery without complications, and most of the phone calls teams receive are for reassurance. Call anyway. The nurses would rather hear from you about a small worry than see your child later with a large one.
Before surgery, contact the team if your child develops a fever, a wet or chesty cough, wheezing, vomiting or diarrhea, a new rash, or exposure to a contagious illness such as chickenpox in the days before the date. Call also if a scheduled medicine was missed or an extra one was taken, or if you realize fasting instructions were not followed. The case may still go ahead, but the team needs to know.
After surgery, seek same-day advice for a fever, pain that is not controlled by the plan you were given, increasing redness or warmth spreading from the wound, a foul smell or cloudy discharge, a dressing that becomes soaked with blood, or a child who refuses all fluids and is passing little urine. After cleft repair, watch for persistent bleeding from the mouth or nose. After hand surgery, call if fingers beyond the cast become pale, blue, cold, or numb, or if swelling makes the cast feel very tight. After ear surgery, sudden severe pain on one side can signal a collection of blood under the skin and needs prompt review.
Go to an emergency department or call emergency services immediately for difficulty breathing, noisy or labored breathing, a bluish tinge to the lips, a child who is very drowsy and hard to rouse, bleeding that does not slow with firm pressure, a seizure, or signs of a severe allergic reaction such as facial swelling, hives, and wheeze together.
Every one of these decisions, from postponing for a cold to reopening a dressing, belongs to the treating team. Your role is to notice early and call promptly. That partnership is what makes pediatric surgery as safe as it has become.
Frequently asked questions
How do I prepare a 9 year old for surgery?
Tell a nine-year-old about a week beforehand, using honest and concrete language about what will happen and why. Children this age worry about specifics such as pain and waking up mid-operation, so answer each question directly and explain that the anesthesia team watches them the whole time. Give them small choices, like which comfort item to bring, and ask the hospital whether a child life specialist, tour, or video is available for rehearsal.
What is the best age to get plastic surgery as a child?
There is no single best age; timing depends on the procedure and how the affected tissue grows. The NHS describes cleft lip repair usually at about 3 to 6 months and palate repair at about 6 to 12 months, while ear setback is generally deferred until the cartilage is near adult shape and the child can cooperate. Your surgical team weighs growth, function, safety, and the child’s own wishes before recommending a time.
How can families lower the risk of a bad plastic surgery result?
Confirm that the surgeon is board certified in plastic surgery and regularly treats children, that an anesthesia team experienced with pediatrics is involved, and that the plan, risks, alternatives, and expected scars have been explained clearly. Be wary of anyone promising a specific outcome. Follow pre-operative and wound-care instructions exactly, protect the scar from sun, and attend every follow-up so problems are caught early.
What are the negative effects of plastic surgery on a child's mental health?
Reconstructive surgery that improves function or removes a source of teasing is not associated with harm in most children. Concerns center on elective cosmetic procedures in teenagers who have body dysmorphic disorder, disordered eating, depression, or unrealistic expectations; in those situations surgery can deepen distress. Responsible teams screen for these issues and involve psychologists before scheduling, and they explain what an operation will and will not change.
Does my child need blood tests before plastic surgery?
Often not. Healthy children having minor or intermediate procedures usually do not need routine blood work, X-rays, or heart tracings. Tests are ordered when the history or examination raises a specific question, such as a bleeding tendency in the family, a heart condition, or a long operation with expected blood loss. Ask the team what question any ordered test answers; if none is ordered, that generally reflects a healthy child.
Is general anesthesia safe for children?
For healthy children, general anesthesia is very safe. The NHS notes deaths caused by anesthesia are very rare, around 1 per 100,000 anesthetics, and Mayo Clinic describes serious complications as uncommon. Common short-lived effects include nausea, a sore throat, and crying or confusion on waking. Current evidence has not shown measurable developmental harm from a single short anesthetic in young children, while research on repeated or prolonged exposure continues.
How long does my child have to fast before surgery?
Follow your own team’s written instructions exactly, because pediatric fasting rules differ from adult ones and vary by age and type of feed. The NHS describes the general adult pattern as no food for about 6 hours and clear fluids until about 2 hours before an anesthetic; many pediatric teams use shorter clear-fluid windows and separate rules for breast milk and formula. If you are unsure whether something counts as a clear fluid, call and ask.
What should I do if my child gets a cold before the operation?
Call the surgical or anesthesia team as soon as you notice symptoms. A mild runny nose in an otherwise well child often does not change the plan, but a fever, wet cough, wheezing, or vomiting can raise the risk of breathing complications under anesthesia and frequently leads to postponement. Delaying for illness is a safety decision made by the team, not a failure of preparation.
What does pediatric plastic surgery recovery usually look like?
Most families describe a rough first day, noticeable improvement by the second, and a gradual return over the following weeks. Swelling after facial procedures generally peaks around the second or third day before fading. Dressings, splints, or arm restraints protect the repair until the team removes them. Pain is managed with a written plan from the prescribing clinician, and return dates for school, sports, bathing, and swimming come from your follow-up visit.
Can my teenager refuse an elective procedure their parents want?
Teenagers are asked for their assent, meaning agreement in their own words, and teams take a reluctant teenager seriously. For an elective procedure such as ear setback, a young person who is unsure is usually asked to wait rather than proceed. Most programs offer adolescents time alone with the surgeon or a psychologist so they can express doubts privately, and that conversation is a normal part of good care.
References
- MedlinePlus – Plastic and Cosmetic Surgery
- NHS – General anaesthesia
- NHS – Cleft lip and palate
- CDC – About Cleft Lip and Cleft Palate
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Parents Can Support a Child in Intensive Care After Pediatric Cardiac Surgery
Parents in the PICU after a child's heart surgery help most by being a steady, familiar presence: talking and singing in a normal voice,…

Head Lice: What Works Now That Resistance Is Common
Head lice in the United States are now widely resistant to over-the-counter permethrin and pyrethrin products, so a failed first treatment usually reflects resistance…

Night Terrors in Toddlers: What They Are and Are Not
No. Night terrors in toddlers are not a sign of mental illness. They are a common parasomnia, a partial arousal from deep sleep in…

Pediatric Physical Therapy vs Occupational Therapy: Which Skills Does Each One Work On?
Pediatric physical therapy mainly works on how a child moves through space: strength, balance, posture, walking and other large-muscle skills. Pediatric occupational therapy works…

Going Home After Neonatal Sepsis Treatment: Discharge Criteria and Development Reviews
Babies usually go home after neonatal sepsis once the treating team is satisfied that the infection is controlled, the antibiotic course is complete or…

How Long Does Sensory Integration Therapy Take to Show Change? Realistic Family Timelines
Sensory integration therapy rarely shows change in the first few sessions. In the best-studied trial, children received about 30 one-hour sessions over 10 weeks…