

Swimmer’s Ear: Causes, Treatment and Prevention
Key Takeaways
- Swimmer's ear is a skin infection of the outer ear canal; pain that worsens when you pull the outer ear is the sign that separates it from a middle ear infection.
- The CDC estimates about 2.4 million US healthcare visits a year for swimmer's ear, most in summer, yet moisture from showers, earbuds and humid weather causes it in non-swimmers too.
- Randomized trials pooled in a Cochrane review show prescription antibiotic ear drops resolve most uncomplicated cases within 7–10 days, with pain easing in 48–72 hours.
- Oral antibiotics are not first-line for uncomplicated swimmer's ear; drops deliver far higher concentrations exactly where the infection sits.
- Hydrogen peroxide, garlic oil and ear candling have no trial evidence for infection, and candling has documented burns and eardrum perforations.
- Cotton swabs are the most common cause of the canal micro-tears that let bacteria in; drying ears by tilting and towel-patting is the prevention habit with the best mechanistic support.
Swimmer's ear (acute otitis externa) is an infection of the skin lining the outer ear canal, usually caused by bacteria that multiply when water, trapped moisture or scratches break down the canal's protective wax and acidity. It is treated with prescription antibiotic ear drops, pain relief and keeping the ear dry, and most cases settle within 7–10 days. Keeping ears dry and skipping cotton swabs is the main prevention.
Every June the same scene plays out on pool decks across the country: a child climbs out of the water, tilts their head like a confused puppy, and tugs at one ear. By bedtime that ear hurts to touch. As of June 2025, that moment has collided with a wave of viral videos recommending garlic oil, hydrogen peroxide rinses and even lit ear candles for post-swim ear pain, and searches for swimmer’s ear have jumped with the opening of outdoor pool season.
The condition itself is not new, and neither is the medicine. What is new is the volume of confident advice that gets the basics wrong. The CDC estimates swimmer’s ear drives roughly 2.4 million healthcare visits a year in the US, most of them in summer, and the vast majority respond well to treatment that has been studied in randomized trials.
This explainer separates what the evidence supports from what simply sounds plausible, and tells you plainly when an aching ear needs a clinician rather than a kitchen remedy.
What is swimmer's ear, and why does the ear canal get infected?
Swimmer’s ear is the everyday name for acute otitis externa, which means inflammation of the outer ear canal, the roughly one-inch tube that runs from the opening of the ear to the eardrum. It is a skin infection, not a deep ear infection. The eardrum and the middle ear behind it are usually untouched, which is why swimmer’s ear rarely causes fever or the deep, pressure-like ache of a childhood middle ear infection.
The canal is normally a hostile place for microbes. Its skin is thin, warm and lined with a coating of cerumen, the clinical term for earwax. Cerumen is mildly acidic, slightly water-repellent and loaded with enzymes that slow bacterial growth. Think of it as a weatherproof seal on a window frame. As long as the seal is intact and the canal dries between soakings, the bacteria that live there, including Pseudomonas aeruginosa and Staphylococcus aureus, stay in balance.
Trouble starts when that balance tips. Water that sits in the canal for hours softens the skin and washes away wax, raising the pH toward neutral. Bacteria that were merely visiting now have warm, damp, defenseless skin to colonize. Within a day or two the canal lining swells, weeps clear or cloudy fluid, and becomes exquisitely tender because the skin here is stretched over bone and cartilage with almost no cushioning underneath.
Mayo Clinic and MedlinePlus both describe this sequence as the central mechanism, and it explains two things parents often find puzzling: why swimmer’s ear can appear after a week of daily swimming rather than a single dip, and why it also shows up in people who never set foot in a pool but shower in hot climates, wear earbuds for hours or scratch their ears with cotton swabs.
What changed recently
The science of swimmer’s ear has not been overturned in 2025; what has shifted is how prominently public health bodies are pushing a few simple messages, and how loudly social media is contradicting them.

The CDC consolidated its swimmer’s ear advice into its Healthy Swimming hub, which it promotes each May during Healthy and Safe Swimming Week ahead of Memorial Day. Its headline figure, about 2.4 million US healthcare visits a year, comes from a CDC analysis of national visit data first published in 2011 and still cited in the current guidance. The emphasis has moved toward one practical habit: drying the ears thoroughly after every swim, including with a hair dryer on its lowest setting held at arm’s length.
On the clinical side, the US otolaryngology guideline on acute otitis externa, updated in 2014 and still the reference standard, made a point that remains underappreciated: oral antibiotics should not be the first treatment for uncomplicated swimmer’s ear. Topical ear drops deliver far higher concentrations of medicine exactly where the infection sits, with less risk of resistance and side effects. Mayo Clinic and the NHS both reflect this position in their current patient pages.
The newest development is not a trial but a trend. Over the past two summers, short-form videos have revived old folk remedies, often filmed by creators with no clinical training and watched millions of times. Several promote pouring warmed garlic oil or hydrogen peroxide into a painful ear, and ear candling has resurfaced despite long-standing warnings from the US Food and Drug Administration about burns and canal injuries. None of these methods appears in any mainstream guideline, and the sections below explain why the evidence does not support them.
What causes ear pain after swimming?
Ear pain after swimming has three common explanations, and only one of them is swimmer’s ear. Sorting them out early saves worry and unnecessary medicine.
The first is simple trapped water. A film of water held in the canal by a bend in its shape or by a plug of wax produces a muffled, full sensation and sometimes a dull ache. It usually resolves within a few hours as the water drains or evaporates, and the ear is not tender when touched.
The second is pressure change. Diving to the bottom of a deep pool, or repeated jumps, can strain the eardrum and the small tube that connects the middle ear to the throat. This feels like the discomfort of a plane landing and tends to settle quickly once pressure equalizes.
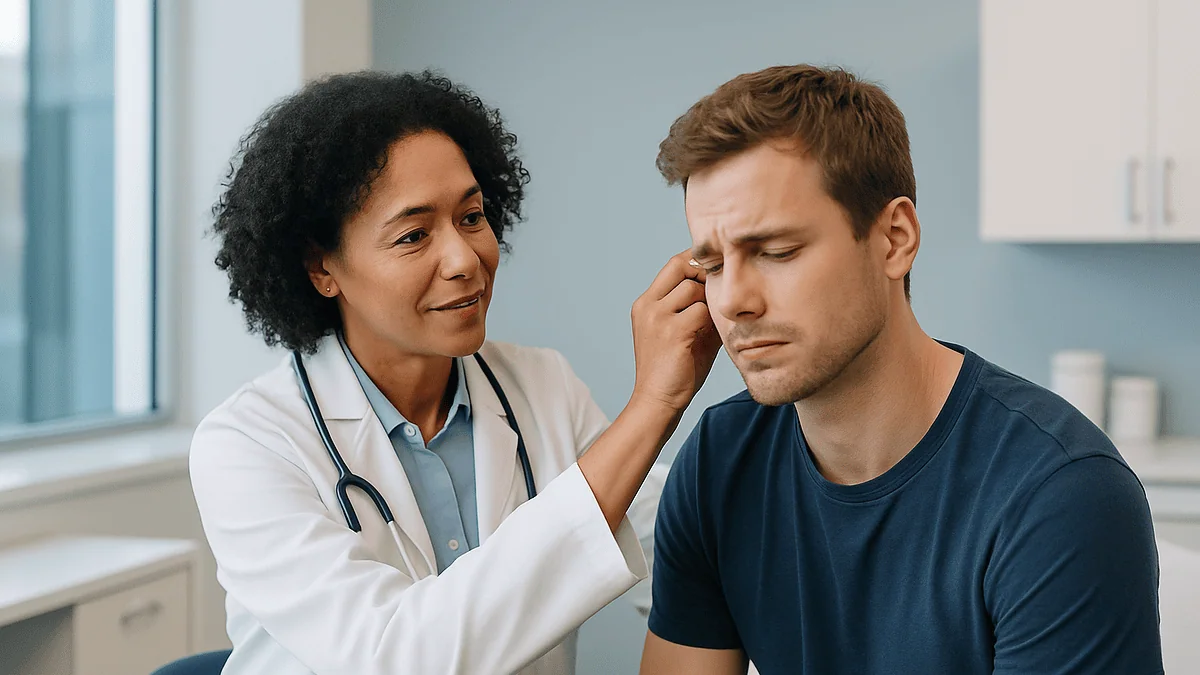
The third is infection of the canal skin, which is true swimmer’s ear. The distinguishing sign, noted consistently by Mayo Clinic, Cleveland Clinic and the NHS, is pain that worsens when you pull gently on the outer ear or press the small flap of cartilage in front of the canal, called the tragus. A middle ear infection does not hurt more when you tug the ear; swimmer’s ear almost always does.
Several factors raise the odds of that third scenario:
- Frequent or prolonged immersion, especially in warm water or water with higher bacterial counts such as lakes and poorly maintained hot tubs.
- Scratches from cotton swabs, fingernails, hairpins or in-ear headphones, which open the skin to bacteria.
- Skin conditions such as eczema or psoriasis that already affect the canal.
- Narrow ear canals, which drain slowly and are more common in children.
- Hairspray, dyes and other products that irritate the canal lining.
Chlorine itself is not the culprit. Properly treated pool water carries fewer bacteria than untreated water; the problem is the dampness it leaves behind, not the chemistry.
Swimmer's ear symptoms, from the first itch to a blocked canal
Swimmer’s ear symptoms tend to build over 24–48 hours in a fairly predictable order, and recognizing the early stage is useful because mild cases are the easiest to treat.

The first signal is usually itching deep in the canal, sometimes with a faint feeling of fullness. The outer ear may look slightly pink, and there may be a little clear, odorless drainage. At this stage many people assume they still have water in the ear. The clue that it is more than water is tenderness: touching or pulling the outer ear produces a sharp twinge.
Over the next day the pain intensifies, often out of proportion to how the ear looks from the outside. The canal skin swells, which narrows the passage and dulls hearing in that ear. Drainage may become thicker, yellowish or cloudy, and the surrounding skin can feel warm. Chewing or lying on that side hurts because the jaw joint sits directly in front of the canal.
In a severe case, the canal can swell shut. Pain radiates toward the face, neck or side of the head, the outer ear may look red and puffy, and lymph nodes in the neck can enlarge. Fever is uncommon in straightforward swimmer’s ear; when it appears, or when the redness spreads onto the skin of the face, the infection has moved beyond the canal and needs prompt medical assessment.
Two features deserve special mention. A foul smell from the ear, or drainage that looks like wet newspaper, suggests a fungal rather than bacterial cause, which responds to different drops. And a sudden sense that the ear has “popped” with a gush of fluid followed by relief of pressure can indicate a perforated eardrum, which changes what can safely be put into the ear. Both are reasons to have the ear examined rather than treated by guesswork.
Swimmer's ear vs middle ear infection vs water stuck in ear: how clinicians tell them apart
Three conditions share the phrase “my ear hurts after swimming,” and they are managed very differently. A clinician usually separates them in under a minute with a careful history and a look through an otoscope, the handheld lighted scope used to view the canal and eardrum. The pattern below summarizes what typically distinguishes them.
| Feature | Swimmer’s ear (otitis externa) | Middle ear infection (otitis media) | Water stuck in ear |
|---|---|---|---|
| Where the problem is | Skin of the outer ear canal | Space behind the eardrum | Canal, no infection |
| Pain when ear is pulled | Yes, often sharp | No | No |
| Typical trigger | Moisture, scratches, swimming | Cold or upper respiratory infection | Swimming, showering |
| Fever | Uncommon | Common in children | None |
| Drainage | Clear to cloudy, sometimes smelly | Only if eardrum ruptures | Clear water draining |
| Hearing | Muffled from swelling | Muffled from fluid behind drum | Muffled, clears as water leaves |
| Usual treatment | Prescription ear drops | Observation or oral antibiotics | Tilt, dry, wait |
Through the otoscope, swimmer’s ear shows a red, swollen canal, often with debris, while the eardrum, if visible, looks normal. In a middle ear infection the canal is healthy but the eardrum is red, bulging or dull. Trapped water shows a normal canal and drum.
Swabs for culture are not routine. Mayo Clinic notes they are reserved for infections that fail to improve on initial treatment, for people with diabetes or weakened immune systems, or when a fungal cause is suspected. Imaging is almost never needed unless a clinician is worried about spread into surrounding bone.
Is water stuck in ear dangerous, and how do you get it out safely?
Water stuck in ear is a nuisance far more often than a threat, but how you deal with it in the first hour decides whether it becomes swimmer’s ear. The goal is to let the water leave on its own and then dry the canal gently, without introducing anything that scratches the skin.
The CDC’s guidance is refreshingly low-tech. Tilt the head so the affected ear faces the floor and gently pull the outer ear in different directions to straighten the canal; gravity does most of the work. Hopping on one foot with the head tilted is a childhood classic that actually makes physiological sense, though lying on that side for a few minutes achieves the same thing with less risk of a fall. Pat the outer ear with the corner of a towel. If moisture lingers, a hair dryer on its lowest heat and speed, held at arm’s length and aimed near rather than into the ear, speeds evaporation.
What not to do matters more. Cotton swabs push wax deeper, strip the protective coating and leave micro-tears in the canal skin, which is exactly the opening bacteria need. Fingers, hairpins and tissue corners do the same. Mayo Clinic, Cleveland Clinic and the NHS are unanimous on this point.
Over-the-counter drying drops, typically a mix of alcohol and acetic acid, are designed to pull residual water from the canal and restore its acidity. They have a place for people who get swimmer’s ear repeatedly, but they should never be used if there is any chance of a perforated eardrum, ear tubes, or an already painful, inflamed ear, where alcohol can sting badly and worsen irritation. A pharmacist or clinician can advise whether they suit you.
If the plugged feeling persists beyond a day or two, is joined by pain or discharge, or hearing does not clear, the cause is probably no longer water. That is the moment to have the ear looked at.
How is swimmer's ear treated?
Treatment for swimmer’s ear rests on three pillars that every major source agrees on: clean the canal, treat the infection where it lives, and control pain while the skin heals.
Cleaning comes first. If the canal is full of debris or swollen shut, drops cannot reach the infected skin. A clinician may gently suction or wipe out wax and discharge, a step that is uncomfortable for a few seconds but often brings immediate relief. When swelling has narrowed the canal to a pinhole, a small sponge called an ear wick is inserted; it expands as drops are applied and carries medicine along the whole length of the canal. The wick usually falls out or is removed within a few days as the swelling settles.
The infection itself is treated with prescription ear drops. These typically contain an antibiotic active against the common canal bacteria, sometimes combined with a corticosteroid to calm inflammation and shorten the period of pain. Acidifying drops, which make the canal inhospitable to bacteria, are sometimes used for mild cases. If the clinician suspects a fungal infection, antifungal drops replace the antibiotic. Which product is chosen, and for how long, is a decision for the prescriber based on what the ear looks like and whether the eardrum is intact, because some older drop formulations should not be used if the drum is perforated.
Oral antibiotics are generally reserved for infections that have spread beyond the canal, for people with diabetes or weakened immunity, or when drops cannot be delivered. The NHS and Mayo Clinic both describe this as the exception rather than the rule.
Pain control is not an afterthought. Ordinary over-the-counter pain relievers are usually adequate; a clinician can advise on the right choice for your age and health. Most people feel noticeably better within 48–72 hours of starting drops, and the canal typically looks normal within 7–10 days. Keep the ear dry throughout, and finish the course even once the pain is gone.
Are ear drops supposed to drain out? Using drops so they actually work
A little drainage is normal; a lot usually means the drops never got in. The canal slopes gently upward from the eardrum to the opening, and swelling or debris can block the path, so technique decides whether the medicine reaches the infected skin or simply trickles down your cheek.
Mayo Clinic and the NHS describe a method that most people get right on the second try. Warm the bottle in your hand for a minute or two; cold drops hitting the eardrum can trigger a brief, unpleasant wave of dizziness. Lie down or tilt the head so the affected ear faces the ceiling. Pull the outer ear up and back in adults, or down and back in young children, to straighten the canal. Let the prescribed number of drops fall in without touching the bottle tip to the skin, then press the tragus a few times to pump the liquid inward. Stay in that position for several minutes before sitting up. If a wick is in place, the drops soak into it and little should escape.
When you do sit up, some excess will run out, often tinged with discharge. That is expected. What is not expected is the full volume pouring straight back out within seconds, which suggests the canal is blocked by swelling or wax; that is worth a call to the clinician rather than simply adding more drops.
Two cautions apply. Never use drops left over from a previous illness or someone else’s prescription, because the wrong formulation in an ear with a perforated eardrum can harm hearing. And if drops cause sharp, escalating pain, hearing loss or a rash around the ear, stop and seek advice; allergy to one of the ingredients, though uncommon, does occur. Any change in how or how long the drops are used should come from the person who prescribed them.
Home remedies for ear pain: what helps and what can harm
Home remedies for ear pain fall into two groups: the ones that make the wait for drops more bearable, and the ones that look like treatment but risk making things worse. The distinction is important, because the canal skin in swimmer’s ear is already damaged and anything poured into it reaches the eardrum.
What reasonably helps:
- A warm, not hot, compress held against the outer ear, which eases pain by relaxing surrounding muscles and improving blood flow.
- Over-the-counter pain relievers appropriate for your age and health, as advised by a pharmacist or clinician.
- Sleeping with the affected ear up, so gravity does not pool discharge against the eardrum.
- Keeping the ear completely dry: no swimming, and a soft cotton ball lightly coated with petroleum jelly placed at the ear opening during showers, removed immediately afterward.
- Leaving the ear alone. No scratching, no probing, no swabs.
What can harm:
- Hydrogen peroxide poured into a painful ear. It is marketed for softening wax in a healthy canal, but in inflamed skin it stings, delays healing and is dangerous if the eardrum is perforated.
- Warmed garlic, olive or other oils. There are no trials showing they treat infection, they coat the canal and interfere with examination and with prescribed drops, and heating oil for the ear carries a burn risk.
- Rubbing alcohol in an inflamed canal, which causes intense pain and further dries cracked skin.
- Ear candling, which the US Food and Drug Administration has warned causes burns, wax deposits and perforations and does nothing useful.
- Leftover antibiotic drops or anyone else’s prescription.
The honest summary is that no home remedy treats the infection. Swimmer’s ear beyond the mildest itch needs a look through an otoscope and, usually, prescription drops. Home measures buy comfort for a night, not a replacement for care.
What the evidence actually says about treating and preventing swimmer's ear
Evidence in medicine is not all equal. Randomized controlled trials, which assign people to treatments by chance and compare outcomes, sit at the top. Observational studies, which track what happens to people without assigning treatment, come next. Expert opinion and guideline consensus, while valuable, rank lowest. Here is how the main claims about swimmer’s ear stack up.
Topical antibiotic drops treat uncomplicated swimmer’s ear. Strong. Multiple randomized trials, pooled in a Cochrane systematic review available through PubMed, show topical treatment produces clinical resolution in most people within 7–10 days. No single antibiotic class clearly outperforms another, which is why clinicians choose based on eardrum status, cost-effectiveness and local practice rather than a presumed winner.
Adding a steroid to drops shortens pain. Moderate. Trials comparing antibiotic drops with and without a corticosteroid show a modest reduction in inflammation and faster symptom relief, though the effect size is small and not every trial agrees.
Oral antibiotics are unnecessary for uncomplicated cases. Moderate to strong by consensus, weaker by trial. The guideline position rests on pharmacology and observational data showing no added benefit and more side effects, rather than large head-to-head randomized trials.
Acidifying or alcohol-based drying drops prevent recurrence. Weak. The rationale is sound and small studies are supportive, but good randomized data in swimmers are sparse. Guidelines list them as an option, not a proven strategy.
Earplugs, swim caps and hair-dryer drying prevent swimmer’s ear. Expert opinion. These are recommended by the CDC and Mayo Clinic on mechanistic grounds and clinical experience; they have not been tested in rigorous trials, and some clinicians note that ill-fitting plugs can themselves irritate the canal.
Garlic oil, hydrogen peroxide, ear candling. No supporting evidence. No randomized or observational studies show benefit for infection; candling has documented harms.
Knowing the grade behind each claim helps you weigh a confident video against a quiet guideline, and the guideline usually wins.
Common myths about swimmer's ear, corrected
Viral advice thrives on half-truths. These are the claims circulating most widely this summer, and what the evidence says instead.
Myth: only swimmers get it. Any source of lingering moisture or skin damage qualifies. The NHS notes that hot, humid weather, frequent showering, hearing aids, earbuds and cotton swab use all cause otitis externa in people who never swim. The nickname describes the most common trigger, not the only one.
Myth: chlorine causes swimmer’s ear. Well-maintained chlorinated water contains fewer bacteria than lakes or rivers. The risk comes from moisture softening the canal skin, not from the disinfectant. If anything, the CDC identifies poorly maintained pools and hot tubs with inadequate disinfectant as the higher-risk settings.
Myth: a few drops of hydrogen peroxide will clear it. Peroxide loosens wax in a healthy canal. In an infected, inflamed canal it stings, slows healing and can injure the middle ear if the eardrum has a hole. No study supports it for infection.
Myth: garlic is a natural antibiotic, so garlic oil is a natural ear drop. Compounds in garlic kill bacteria in a test tube; that is a long way from treating infected skin in a living ear. There are no clinical trials of garlic oil for swimmer’s ear, oil obscures the eardrum during examination, and warming oil for the ear has caused burns.
Myth: ear candling draws out wax and infection. Studies measuring the residue left in candles show it is candle wax, not earwax, and candling produces no suction. The US Food and Drug Administration has documented burns and perforations from the practice.
Myth: once the pain stops, you can stop the drops. Pain usually eases in two to three days, well before the skin has healed. Stopping early is a common reason infections return. The prescribing clinician sets the course; follow it to the end.
Myth: swimmer’s ear is contagious. It is an infection of your own canal skin by bacteria already present there. You cannot catch it from another person in the pool.
How to prevent swimmer's ear: habits that hold up
Prevention of swimmer’s ear is mostly about denying bacteria the two things they need: standing water and broken skin. The habits below are the ones endorsed by the CDC, Mayo Clinic and Cleveland Clinic. They are low-effort, and for frequent swimmers they can turn a summer of recurring infections into a summer of none.
Dry every time. After swimming or bathing, tilt the head to each side and gently pull the outer ear to help water escape, then dry the outer ear with a towel corner. For a stubborn plugged feeling, a hair dryer on its coolest, lowest setting held about a foot away will finish the job in a minute.
Protect the canal’s natural seal. Earwax is doing a job. Avoid cotton swabs, fingernails and any object inserted into the canal. If wax genuinely builds up, a clinician or pharmacist can suggest safe softening methods; home digging is the single most common cause of the micro-abrasions that let bacteria in.
Consider a barrier. Soft silicone earplugs or a snug swim cap keep water out for people who get repeated infections. Fit matters: a plug that rubs or needs forcing in can scratch the canal and defeat the purpose.
Think about drying drops, with advice. Over-the-counter alcohol and acetic acid drops after swimming restore the canal’s acidity and evaporate residual water. They are suitable only for people with intact eardrums and no ear tubes, and a clinician should confirm they fit your history before you make them a habit.
Choose water wisely. Skip swimming in water flagged for high bacterial counts, and avoid hot tubs that look cloudy or smell strongly, both signs of poor disinfectant control.
Protect the skin from irritants. Place cotton balls at the ear openings while applying hairspray or dye, and keep earbuds clean and dry.
Managing underlying eczema or psoriasis of the canal with a clinician’s help also cuts recurrence, because inflamed skin is easier for bacteria to breach.
When swimmer's ear turns serious: complications to understand
Most swimmer’s ear is a nuisance that resolves in a week or two. A small minority of cases progress, and knowing the three main complications helps you recognize when a routine infection has stopped being routine.
Chronic otitis externa is inflammation that persists beyond three months or keeps coming back. It is more common in people with eczema, allergies to drop ingredients, or persistent fungal infection, and it is sometimes driven by the very remedies people use to relieve itching, such as repeated swabbing or over-the-counter creams. Management focuses on identifying the underlying irritant and restoring the canal skin, often with a specialist’s help.
Cellulitis occurs when the infection spreads from the canal into the surrounding skin of the outer ear, face or neck. The outer ear becomes red, swollen and hot, lymph nodes enlarge, and fever appears. At this point ear drops alone are insufficient and oral or occasionally intravenous antibiotics are required.
Malignant (necrotizing) otitis externa is the rare but dangerous form in which infection, almost always with Pseudomonas aeruginosa, invades the cartilage and bone at the base of the skull. The word “malignant” refers to its aggressive behavior, not to cancer. It occurs mainly in older adults with diabetes and in people with weakened immune systems, including those on chemotherapy or with HIV. Warning signs are pain that is severe and unrelenting, especially at night, pain that persists despite appropriate drops, and any new weakness of the facial muscles. Mayo Clinic and Cleveland Clinic both stress that this requires urgent specialist care, imaging and prolonged antibiotics.
Permanent hearing loss from uncomplicated swimmer’s ear is very rare. Temporary muffling from a swollen canal is expected and clears as the swelling resolves. If hearing does not return to normal within a couple of weeks after treatment, or if the infection involved a perforated eardrum, a follow-up examination and hearing check are sensible.
When to see a doctor
Mild itching with a plugged feeling after a swim can be watched for a day while you keep the ear dry. Beyond that, swimmer’s ear is a condition that benefits from being seen, because the drops that treat it require a prescription and an examination to confirm the eardrum is intact. Here is how to decide on timing.
Make an appointment within a day or two if:
- Ear pain lasts more than a day or worsens, especially if pulling the ear hurts.
- There is discharge of any kind from the canal.
- Hearing on that side is muffled and has not cleared within 24 hours of drying.
- Symptoms return within weeks of a treated episode.
- You have diabetes, a weakened immune system, ear tubes or a previously perforated eardrum, in which case even mild symptoms warrant an early look.
Seek urgent care the same day if:
- Pain is severe, keeps you awake, or does not respond to over-the-counter pain relievers.
- The outer ear or the skin of the face and neck becomes red, hot and swollen.
- You develop a fever alongside ear symptoms.
- Pain or hearing suddenly worsens while using prescribed drops, or a rash appears around the ear.
- Symptoms have not improved after three days of prescribed treatment.
Go to an emergency department or call for urgent help if:
- You notice weakness or drooping on one side of the face.
- You have a stiff neck, severe headache, confusion or dizziness with vomiting.
- Pain is extreme in someone who is elderly, has diabetes or is immunocompromised, as these are the settings in which necrotizing otitis externa occurs.
Every decision about which drops to use, how long to continue them, whether oral antibiotics are needed and when it is safe to swim again belongs to the clinician who has examined the ear. Bring a list of any products, including home remedies, that have gone into the canal; it changes what they look for and what they can safely prescribe.
Frequently asked questions
What causes ear pain after swimming?
Ear pain after swimming is most often trapped water, pressure changes from diving, or swimmer’s ear, an infection of the canal skin. Trapped water causes a muffled, full feeling that clears within hours. Pressure discomfort settles once the ear equalizes. Swimmer’s ear produces pain that worsens when the outer ear is pulled, often with itching and discharge, and it needs an examination because prescription drops are usually required.
What are some home remedies for ear pain that are actually safe?
Safe comfort measures include a warm compress against the outer ear, over-the-counter pain relievers suited to your age and health, sleeping with the sore ear facing up, and keeping the ear completely dry. Avoid pouring anything into the canal, including hydrogen peroxide, garlic oil or rubbing alcohol, and never use ear candles. These measures ease discomfort for a night; they do not treat the infection, which needs a clinician’s assessment.
Are ear drops supposed to drain out?
A small amount of excess running out when you sit up is normal and often carries discharge with it. If the full volume pours straight back out within seconds, the drops are probably not reaching the infected skin because the canal is swollen or blocked by debris. Warm the bottle, lie with the ear up, pull the outer ear to straighten the canal, press the tragus a few times and stay still for several minutes. Persistent run-out is worth reporting to the prescriber.
When should I see a doctor for water in ear?
Plain trapped water usually clears within a few hours with head tilting and gentle drying. See a clinician if the plugged feeling lasts more than a day, if pain develops, especially pain on pulling the ear, if there is any discharge, or if hearing does not return to normal. Seek care the same day for severe pain, fever, or redness spreading to the outer ear or face, and sooner if you have diabetes or a weakened immune system.
How long does swimmer's ear last?
With prescription drops, pain typically eases within 48–72 hours and the canal looks normal within 7–10 days. Untreated, mild cases sometimes settle on their own over one to two weeks, but many worsen and the canal can swell shut. The ear should stay dry until the clinician confirms it has healed. If there is no improvement after three days of treatment, the drops may not be reaching the skin or the cause may be fungal, both of which need re-examination.
Is swimmer's ear contagious?
No. Swimmer’s ear is an infection of your own ear canal skin by bacteria that already live there, most often Pseudomonas aeruginosa and Staphylococcus aureus. It is triggered by moisture and skin damage, not by exposure to another person. You cannot catch it from someone else in a pool, and a child with swimmer’s ear does not need to be kept away from others, though they should stay out of the water until the ear has healed.
Can you get swimmer's ear without swimming?
Yes, and many people do. Anything that keeps the canal damp or breaks its skin can trigger otitis externa: frequent showering, sweating in humid weather, hearing aids, long hours in earbuds, cotton swab use, scratching with fingernails, and skin conditions such as eczema or psoriasis. The nickname reflects the most common trigger, not the only one. Prevention for non-swimmers follows the same logic: dry the canal gently and keep objects out of it.
Can I swim with swimmer's ear?
Not until a clinician says the canal has healed. Swimming during treatment keeps the skin wet, washes out the medicine and can prolong the infection by days or weeks. During showers, protect the ear with a cotton ball lightly coated in petroleum jelly placed at the opening and removed afterward. Most people are cleared to return to the water once pain and discharge have resolved and the prescribed course of drops is complete.
Does hydrogen peroxide help swimmer's ear?
No. Hydrogen peroxide is intended for softening wax in a healthy canal; in an infected, inflamed canal it stings, dries cracked skin and delays healing. If the eardrum has a hole, which can happen in severe infections, peroxide can reach the middle ear and cause damage. No clinical study supports it as a treatment for swimmer’s ear. Prescription drops chosen after an otoscope examination remain the evidence-based approach.
How to prevent swimmer's ear in kids who swim every day?
Dry their ears after every swim by tilting the head to each side, gently pulling the outer ear and patting with a towel corner; a hair dryer on the coolest, lowest setting at arm’s length helps with stubborn moisture. Keep cotton swabs and fingers out of the canal. Well-fitted soft earplugs or a swim cap can help children with repeated infections. Ask a clinician before using over-the-counter drying drops, which are unsuitable for children with ear tubes or a perforated eardrum.
References
- MedlinePlus: Swimmer's ear (ear infection, outer ear)
- NHS: Otitis externa
- Cleveland Clinic: Swimmer's ear (otitis externa)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Eye Vitamins and Lutein: What the AREDS Trials Actually Showed
The AREDS trials showed that a specific antioxidant and zinc formula modestly slows progression in people who already have intermediate age-related macular degeneration, and…
Electric Toothbrushes, Water Flossers and Floss: What Dental Trials Show
Randomized trials pooled in a Cochrane review found that electric toothbrushes remove modestly more plaque and reduce gum inflammation slightly more than manual brushes,…

Receding Gums: Causes, Whether They Grow Back and the Treatments That Help
Receding gums happen when gum tissue pulls away from a tooth and exposes more of its root, most often because of gum disease, aggressive…
Earwax Removal: Safe Methods, the Cotton-Bud Problem and Why Ear Candling Is Dangerous
Earwax removal is rarely necessary because the ear canal cleans itself, but when wax blocks hearing or causes discomfort, the safest home approach is…