

The Hip Replacement Scar: Size, Placement and How It Fades
Key Takeaways
- Minimally invasive hip replacement scars run roughly 3 to 6 inches, while traditional approaches leave an 8-to-10-inch line, and incision size has no proven effect on long-term joint function.
- The scar's location follows the surgical approach: buttock/back of hip (posterior), outer hip (lateral), or front of the upper thigh (anterior).
- Scars keep maturing for 12 to 18 months, typically fading from raised red to a flat pale or faintly pigmented line, so don't judge the final result before month six.
- Silicone sheets or gel, scar massage after full wound closure, and strict sun protection for the first year are the scar-care measures with the best evidence; premium botanical scar creams largely lack it.
- A patch of numbness beside the scar is common, especially on the front-outer thigh after anterior surgery, and usually shrinks over 6 to 12 months without affecting hip function.
- Spreading redness, increasing drainage, wound opening, or a fever above 100.4°F (38°C) after hip replacement warrants a same-day call to your surgical team, because implant infections are treated most successfully when caught early.
A hip replacement scar is typically a single straight or gently curved line, roughly 3 to 6 inches long with minimally invasive techniques and 8 to 10 inches with a traditional approach. It sits on the front, side, or back of the hip depending on the surgical approach. Most scars fade from red to pale over 12 to 18 months, though some numbness nearby can persist.
At a community pool, you can often spot who has had a hip replaced. Not by a limp, many walk beautifully, but by a thin, silvery line along the outer hip or upper thigh, the kind of mark people stop noticing about a year in. More than 450,000 total hip replacements are performed in the United States each year, which means those lines are everywhere: on golfers, grandparents, and 52-year-old marathoners who wore out a joint early.
Yet before surgery, the scar looms large in patients’ minds. How long will it be? Will it show in shorts? Why does one neighbor have a faint 4-inch mark near the groin while another has a 10-inch curve across the buttock?
The honest answer involves surgical approach, skin biology, and time, and it is more reassuring than most people expect. Here is what the evidence actually shows about size, placement, and fading, along with the recovery questions people quietly type into search engines at 2 a.m.
What does a hip replacement scar actually look like?
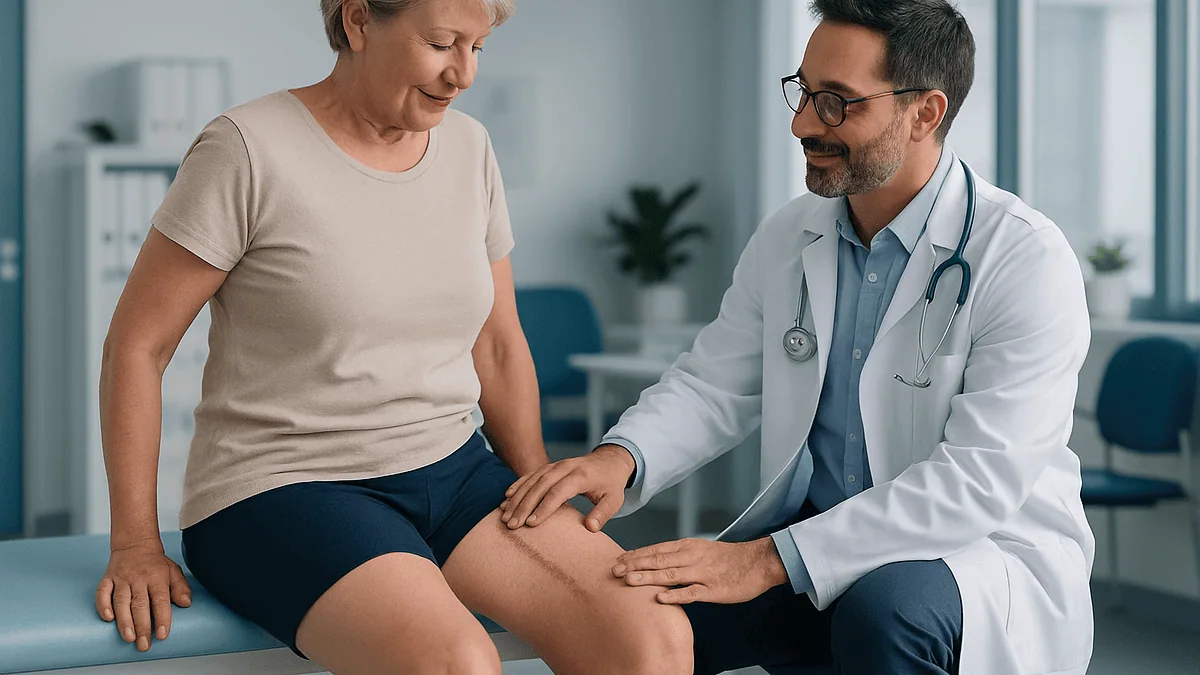
Picture a single line, not a web of marks. Total hip replacement is done through one incision, so the resulting scar is one straight or slightly curved line on the front, side, or back of the hip. In the early weeks it looks raised, pink to deep red, and slightly firm: the body floods a healing wound with tiny blood vessels and collagen, which gives fresh scars their color and stiffness.
Over months, that changes dramatically. The blood vessels recede, the collagen reorganizes, and the line flattens and lightens. A mature hip replacement scar is usually flat or barely raised, paler than the surrounding skin in lighter skin tones, and sometimes darker than surrounding skin in medium and deeper skin tones. Many patients describe theirs, a year on, as a faint pencil line.
Texture matters as much as color. Expect the area to feel firm and slightly tethered at first, because scar tissue binds the skin to deeper layers. Gentle movement, walking, and, once the wound is fully closed, scar massage encourage that tissue to soften. You may also notice small dots or short cross-marks near the main line early on; these come from staples or sutures and typically fade faster than the incision itself.
One more visual note worth setting expectations around: swelling. The hip and thigh often stay puffy for weeks after surgery, which can make the scar look wider and angrier than it will ultimately be. Judging your final scar at week three is like judging a cake mid-bake.
How big is the scar from a total hip replacement?
Size depends mostly on technique. A traditional total hip replacement uses an incision of roughly 8 to 10 inches (about 20 to 25 centimeters). Minimally invasive techniques, now common, work through incisions of roughly 3 to 6 inches (about 8 to 15 centimeters). Your build matters too: surgeons need enough exposure to place the implant precisely, and a larger or more muscular thigh may honestly require a longer incision.
| Technique | Typical incision length | Where the scar sits |
|---|---|---|
| Traditional (posterior or lateral) | 8–10 in (20–25 cm) | Back or side of the hip |
| Minimally invasive posterior | 3–6 in (8–15 cm) | Back of the hip, toward the buttock |
| Direct anterior | 3–5 in (8–13 cm) | Front of the upper thigh |
| Direct lateral | 4–6 in (10–15 cm) | Outer side of the hip |
Here is the part top-ranking articles tend to soft-pedal: incision length is a cosmetic detail, not a quality measure. Studies comparing approaches show that long-term function depends far more on accurate implant positioning than on skin incision size. A surgeon who is highly experienced with a longer incision is a better bet than an unfamiliar technique chosen for a smaller scar. Ask your surgeon which approach they perform most often: that answer matters more than inches.
Where will the scar be? Posterior, lateral, and anterior placement
The scar’s address on your body is determined by the surgical approach: the route the surgeon takes to reach the joint.
- Posterior approach: the most common technique worldwide. The incision curves along the back and side of the hip, partly over the upper buttock. In everyday clothing, and even in most swimsuits, this scar is largely hidden.
- Lateral approach: the incision runs vertically along the outer hip, over the bony prominence you can feel when lying on your side (the greater trochanter). Visible in a swimsuit with high-cut legs; covered by shorts.
- Anterior approach: the incision sits on the front of the upper thigh, angling slightly toward the groin. It is the most visible of the three in swimwear, though usually also the shortest.
There is a small irony here that patients notice after the fact: the anterior approach is often marketed around a discreet scar, yet its placement is the one most likely to peek out of a swimsuit, while the “big” posterior scar hides on the buttock. If scar visibility genuinely matters to you, and for some people it reasonably does, raise it during your surgical consultation. Surgeons can sometimes adjust incision placement slightly, for example orienting an anterior incision closer to a natural skin crease known as the bikini line, though the approach itself is chosen primarily for anatomical and surgical reasons, not cosmetic ones.
Does anterior hip replacement really mean a smaller, better scar?
Sometimes smaller, not automatically better. The direct anterior approach typically uses a 3-to-5-inch incision and spares major muscle from being cut, working instead between muscle planes. Early recovery, the first few weeks, is often somewhat faster, and studies suggest a modestly lower dislocation risk because the muscles at the back of the hip stay intact.
But the scar story has caveats the brochures skip. The anterior incision crosses skin that folds when you sit and flex your hip, and it lies near the path of the lateral femoral cutaneous nerve, which supplies feeling to the outer thigh. Irritation of that nerve is a recognized issue with this approach: some patients notice numbness or tingling on the front-outer thigh, which usually improves over months but occasionally lingers. Wound-healing problems along the groin crease can also be slightly more common in patients with a larger abdomen that overhangs the incision.
And by six months to a year, comparative studies consistently find that patients who had anterior, posterior, or lateral approaches function about the same. The joint doesn’t know which door the surgeon came through.
The evidence-first takeaway: choose the approach your surgeon does best and most often, in a volume that keeps their skills sharp. A slightly longer scar from a confident, practiced hand beats a shorter one from an approach the surgeon performs occasionally.
How the scar heals: a realistic timeline
Scar maturation runs on a slower clock than most people expect. The incision closes in weeks; the scar keeps changing for more than a year.
- Weeks 1–2: the wound edges seal. Staples or non-dissolving sutures, if used, typically come out 10 to 14 days after surgery. The line looks red, raised, and may be bruised around it. Mild drainage in the first few days can be normal; increasing drainage is not.
- Weeks 2–6: the surface is closed but fragile. Redness peaks, and the scar may feel itchy: a common and usually harmless part of healing, driven by histamine release and regrowing nerve endings.
- Months 2–6: collagen remodels. The scar begins to flatten and shift from red toward pink. Firmness and tightness ease, especially with movement and, if your care team approves, gentle scar massage.
- Months 6–18: the long fade. The line pales, softens, and settles into its final appearance. Dermatology sources generally describe full scar maturation as taking 12 to 18 months, sometimes longer.
Two practical implications follow. First, don’t panic about appearance in the first three months: you are looking at a construction site, not the finished building. Second, the window for influencing the final result stays open for many months, which is why sun protection and scar care are worth continuing well past the point the wound looks “done.”
What decides how well your scar fades?
Two scars from identical surgeries can look strikingly different a year later, and the reasons are mostly biological rather than surgical.
- Genetics and skin tone: people with medium to deep skin tones are more prone to hyperpigmentation (a scar darker than surrounding skin) and to keloids, raised scars that grow beyond the original incision. A personal or family history of keloids is worth mentioning before surgery, because closure technique and early scar management can be adjusted.
- Age: older skin, somewhat counterintuitively, often scars more faintly. Slower healing produces less exuberant collagen. Younger patients tend to form redder, thicker scars.
- Blood sugar and circulation: poorly controlled diabetes and peripheral vascular disease slow wound healing and raise infection risk, both of which worsen scarring. Getting blood sugar into range before elective surgery measurably improves wound outcomes.
- Smoking: nicotine constricts the small blood vessels that feed healing skin. Surgeons ask patients to stop smoking before joint replacement for good reason, smokers have higher rates of wound complications, and complications leave worse scars.
- Tension and movement: scars that heal under skin tension stretch and widen. This is one argument for following early activity guidance rather than testing your limits in week two.
- Sun exposure: ultraviolet light darkens immature scar tissue, sometimes permanently. A fresh scar tans faster and more stubbornly than normal skin.
You can’t change your genes, but blood sugar, smoking, sun, and tension are all within reach, and together they account for much of the difference between a faint line and a prominent one.
Caring for the incision in the first six weeks
Early wound care is unglamorous and enormously effective. The goal is simple: keep the incision clean, dry, and undisturbed while it seals.
Follow your surgical team’s specific instructions, closures vary (staples, sutures, surgical glue, adhesive strips), and each comes with slightly different rules. That said, mainstream guidance converges on a few principles. Keep the dressing on as directed and change it with clean hands. Showering is usually permitted once your team confirms the wound is sealed, often within about a week, but pat the area dry rather than rubbing. Skip baths, pools, and hot tubs until the incision is fully healed and your team clears you, typically several weeks, because soaking softens the wound and invites bacteria.
Resist the urge to help. Don’t apply lotions, ointments, or home remedies to an open or freshly closed incision unless your care team specifically recommends them. Don’t pick at scabs or peel adhesive strips early; they usually detach on their own within a couple of weeks. If staples are used, a clinician removes them: a quick, mildly pinchy process, not the ordeal people imagine.
Watch the wound daily. You are looking for stability: the same or less redness, the same or less drainage, edges staying together. Any trend in the wrong direction, spreading redness, new drainage, gaping, foul odor, belongs in the next section, and on the phone with your surgeon’s office.
Scar care after healing: what actually works
Once the wound is fully closed and your team gives the green light, three interventions have reasonable evidence behind them, and a fourth is mostly marketing.
Silicone sheets or gel are the best-supported over-the-counter option for reducing scar thickness and redness. Dermatology guidance generally recommends starting once the wound is healed and continuing for two to three months or longer, worn most of the day. The mechanism is thought to involve hydrating the scar surface and calming collagen overproduction.
Scar massagefirm, small circles along and across the line for a few minutes daily, helps soften the scar and free it from underlying tissue. The formal evidence is modest, but physical therapists widely use it after joint replacement, it costs nothing, and patients consistently report less tightness. Begin only after the wound is completely closed.
Sun protection is non-negotiable for at least the first year. Cover the scar with clothing or a broad-spectrum sunscreen whenever it will see daylight. UV exposure darkens immature scars, and that darkening can be permanent.
Now the honest part: expensive scar creams built around botanical extracts have weak and inconsistent evidence. Studies of onion-extract gels, for instance, have generally failed to show meaningful benefit over plain moisturizer. Moisturizing itself is fine and keeps the scar comfortable, just don’t pay premium prices for promises the data don’t support. If a scar becomes thick, raised, or itchy months in, a dermatologist has genuinely effective clinical options, and earlier treatment works better.
Why is the skin around my scar numb?
Because tiny nerves were unavoidably cut, and this is one of the most common, and least discussed, aftereffects of hip replacement.
Skin sensation travels through a fine network of superficial nerves, and any incision severs some of them. The result is a patch of numbness, tingling, or odd “woody” sensation next to the scar, most often on the side away from the midline. With the anterior approach, the nearby lateral femoral cutaneous nerve can be stretched or irritated, producing numbness or burning along the front-outer thigh: a pattern reported in a meaningful minority of anterior-approach patients in published series.
The good news comes in layers. First, this numbness is a sensory issue only; it does not affect the strength of your hip, the function of the implant, or your ability to walk. Second, superficial nerves slowly regrow or neighboring nerves take over, so the numb patch typically shrinks over 6 to 12 months. Some people notice zings or hypersensitivity during that regrowth phase: a strange but usually reassuring sign that nerves are reconnecting. Third, even when a small numb area is permanent, most patients report they stop noticing it within a year.
What deserves a call to your surgeon: numbness that spreads rather than shrinks, weakness in the leg or foot, or new numbness appearing weeks after surgery rather than immediately. Those patterns fall outside normal healing and warrant evaluation.
When to see a doctor about your scar or incision
Most incisions heal without drama, but infection after joint replacement is the complication worth respecting: it occurs in roughly 1 in 100 hip replacements, and catching it early makes an enormous difference. A metal and plastic implant cannot fight infection the way living tissue can, so surgeons treat warning signs seriously and so should you.
Contact your surgical team promptly if you notice any of the following:
- Redness that spreads outward from the incision rather than fading day by day
- Increasing pain at the wound after the first week, when pain should be steadily easing
- Drainage that increases, turns cloudy or foul-smelling, or reappears after stopping
- Wound edges separating or opening
- Fever above 100.4°F (38°C), or chills and feeling generally unwell
- A hot, swollen area around the scar
Two situations need emergency care rather than a phone call: signs of a blood clot, new calf pain or swelling in either leg, or of a clot traveling to the lungs, meaning sudden shortness of breath or chest pain. Blood clots are a known risk in the weeks after hip surgery, which is why your team prescribes prevention measures and early walking.
One quieter reason to check in: late changes. If a well-healed scar becomes newly red, tender, or draining months or years after surgery, that can signal a late infection around the implant. It’s uncommon, but it is never something to watch and wait on. When in doubt, call, surgical teams universally prefer a false alarm to a missed infection.
What is the hardest part of hip replacement recovery?
Ask patients rather than brochures and you hear surprisingly consistent answers, and the scar rarely makes the list.
Sleep tops it for many. Depending on your surgeon’s guidance, you may need to sleep on your back or with a pillow between your knees for several weeks, and side-sleepers find this genuinely miserable. Poor sleep then makes everything else, pain, mood, fatigue, harder.
The energy crash surprises people. Major surgery triggers an inflammatory response that leaves many patients wiped out for weeks, even as the hip itself improves. Needing an afternoon nap at week three is normal, not a setback.
Pacing is the psychological challenge. Recovery is nonlinear: a great Tuesday tempts you to overdo Wednesday, which produces a sore Thursday. Physical therapists spend as much time coaching restraint as effort. Most people walk with support within a day of surgery, drop the walker or crutches over two to six weeks, and reach the “I forget I had surgery” stage somewhere between three months and a year.
Dependence stings too. For the first weeks you may need help with socks, shoes, and low chairs. For people used to self-sufficiency, that is often harder than the pain.
Worth saying plainly: modern pain management means most patients describe post-surgical pain as very manageable and different in character from the grinding arthritis pain it replaced. Many report that relief within days, which is exactly why satisfaction rates with hip replacement run so high in long-term studies.
What can you never do again after a hip replacement?
Far less than the internet suggests, but a few honest limits exist.
The clearest one involves impact. Most surgeons advise against repetitive high-impact activities for life: distance running on pavement, competitive singles court sports, and sports with frequent jumping. The concern is mechanical, not fragile-patient caution, implant bearing surfaces wear over time, and repeated impact loading may accelerate that wear or loosen the implant’s fixation to bone. Modern implants routinely last 15 to 25 years; registry data show more than half of hip replacements still functioning at 25 years. Hammering them daily is the main way to shorten that.
What you absolutely can do, and are encouraged to: walking, hiking, swimming, cycling, golf, doubles racquet sports, dancing, strength training, and skiing for experienced skiers with surgeon approval. Regular activity strengthens the bone around the implant.
Early movement restrictions, often called hip precautions, depend on approach. Posterior-approach patients are traditionally told to avoid, for roughly 6 to 12 weeks, bending the hip past 90 degrees, crossing the legs, and twisting the leg inward, because those positions stress the repaired tissues while they heal. Many surgeons now relax these precautions earlier than in past decades, and some skip them entirely for certain patients; follow your own team’s guidance, not a forum’s.
After full healing, most people live without daily restrictions. They cross their legs, garden, and travel. The “never” list, honestly rendered, is short: don’t make repetitive high impact a lifestyle, and don’t ignore your specific surgeon’s early-recovery rules.
What can you never do after anterior hip replacement specifically?
The anterior approach flips the precaution script. Because the surgeon enters from the front and leaves the posterior muscles and capsule intact, the classic posterior precautions, no deep bending, no leg crossing, often don’t apply, or apply in reverse.
During early recovery, anterior-approach patients are typically cautioned against positions that stretch the front of the hip: extending the leg far behind the body, arching into a deep backward lunge, or rotating the leg outward forcefully. In practice this means avoiding certain yoga backbends, aggressive hip-flexor stretches, and lying flat on your stomach with the leg extended back during the first weeks. Your surgeon and physical therapist will tell you exactly which movements matter for your case and for how long, protocols genuinely vary, and some teams impose almost no formal precautions.
Permanently forbidden activities? The list matches any hip replacement: sustained high-impact loading is the main long-term concern, regardless of approach. The implant inside an anterior-approach patient is the same category of device as everyone else’s; the approach changed the doorway, not the hardware.
One anterior-specific point deserves repeating because it circles back to the scar: the numbness or tingling some patients feel along the front-outer thigh comes from the lateral femoral cutaneous nerve near the incision. It usually fades over months and doesn’t limit activity, but if it is your dominant symptom at follow-up visits, say so: your team can distinguish routine nerve irritation from something that needs attention.
Will the scar bother you long-term, and can anything be done if it does?
For most people, no. Surveys of joint replacement patients consistently show that pain relief and restored mobility dominate their assessment of the surgery; scar appearance barely registers a year out. The line fades, clothing covers most placements, and the psychological weight of a scar tends to shrink alongside its color.
But “most people” isn’t everyone, and it is fair to want a good cosmetic result. If your scar remains thick, raised, dark, itchy, or tight beyond the 12-to-18-month maturation window, you have real options. Dermatologists treat problematic surgical scars with approaches such as silicone therapy, corticosteroid-based injections for raised scars, laser treatments to reduce redness and thickness, and, rarely, surgical scar revision. Which option fits depends on the scar type: a keloid, a stretched wide scar, and a hyperpigmented flat scar are three different problems with three different answers. Earlier evaluation generally means simpler treatment.
A gentler point to close on: scars carry meaning, and you get to choose the frame. Plenty of patients come to see the line on their hip the way runners see a finisher’s medal, proof they traded years of grinding pain for stairs climbed without thinking, sleep without aching, and a walk that doesn’t announce itself. Twelve months after surgery, the average patient isn’t looking at the scar. They’re looking at the trail, the dance floor, or the grandchild they can finally chase. That is the honest picture, evidence, thin silver line, and all.
Frequently asked questions
What does the scar look like from a total hip replacement?
It is a single straight or gently curved line, typically 3 to 6 inches long with minimally invasive techniques or 8 to 10 inches with a traditional approach. Early on it appears red, raised, and firm; over 12 to 18 months it flattens and fades to a pale or faintly pigmented line. Placement depends on approach: the buttock area, the outer hip, or the front of the upper thigh.
How long does it take for a hip replacement scar to fade?
Expect 12 to 18 months for full maturation. The wound itself seals within about two weeks, redness peaks over the following month, and the color then shifts from red to pink to pale over many months. Some scars continue softening beyond 18 months. Sun protection during the first year matters, because ultraviolet light can darken an immature scar permanently.
What can you never do again after a hip replacement?
The main lifelong limit most surgeons set is repetitive high-impact activity, distance running on pavement, jumping sports, and competitive singles court sports, because impact may accelerate implant wear. Nearly everything else returns: walking, hiking, swimming, cycling, golf, dancing, and strength training are encouraged. Early movement precautions, such as avoiding deep hip bending after a posterior approach, are temporary and typically lift within weeks to a few months.
What can you never do after anterior hip replacement?
Long-term, the same single restriction as any hip replacement: avoid making repetitive high-impact exercise a lifestyle. Early on, anterior-approach patients are usually told to avoid positions that stretch the front of the hip, extending the leg far behind the body, deep backbends, or forceful outward rotation, for a few weeks. Classic posterior precautions like avoiding leg-crossing often don’t apply. Follow your own surgeon’s protocol, since guidance varies.
What is the hardest part of hip replacement recovery?
Patients most often cite disrupted sleep, unexpected fatigue, and the discipline of pacing rather than pain itself. Sleeping position restrictions frustrate side-sleepers, and the body’s inflammatory response to major surgery causes weeks of tiredness. Recovery is also nonlinear, good days tempt overexertion, which produces sore days. Most people walk with support within a day and shed walking aids over two to six weeks.
Is it normal for a hip replacement scar to be numb?
Yes, quite normal. The incision unavoidably cuts small skin nerves, leaving a numb or tingly patch beside the scar. After anterior surgery, numbness along the front-outer thigh can occur from irritation of the lateral femoral cutaneous nerve. The numb area usually shrinks over 6 to 12 months and never affects hip strength or implant function. Spreading numbness or leg weakness, however, should be reported to your surgeon.
Is an itchy hip replacement scar normal?
Usually, yes. Itching is a common feature of healing, driven by histamine release and regrowing nerve endings, and it often peaks between weeks two and six. Avoid scratching directly on the incision; a cool compress near the area can help. Itching accompanied by spreading redness, warmth, drainage, or fever is different: that pattern suggests possible infection and deserves a prompt call to your surgical team.
When can I put cream or silicone sheets on my hip replacement scar?
Only after the wound is fully closed and your surgical team confirms it, typically a few weeks after surgery. Applying products to an open or freshly closed incision raises infection risk. Once cleared, silicone sheets or gel used daily for two to three months have the best over-the-counter evidence for reducing scar thickness and redness, and gentle scar massage can ease tightness.
Why is my hip replacement scar so big compared to someone else's?
Surgical approach explains most of it: traditional incisions run 8 to 10 inches, minimally invasive ones 3 to 6 inches. Body build matters too, surgeons need adequate exposure to position the implant accurately, so a larger thigh may require a longer incision. Importantly, studies show incision length doesn’t predict long-term function. A longer scar from a precise, experienced surgeon is a good trade.
Can a hip replacement scar be fixed if it heals badly?
Yes, there are established options. If a scar remains thick, raised, dark, or painful beyond the 12-to-18-month maturation period, dermatologists can treat it with silicone therapy, injections for raised or keloid scars, laser treatments for redness and texture, or, rarely, surgical revision. The right choice depends on the scar type, and earlier evaluation generally means simpler treatment, so raise concerns at a follow-up visit rather than waiting years.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Is Pain Managed After Hand Surgery? Elevation, Splints and Safe Relief
Pain after hand surgery is usually managed with a combination of measures: keeping the hand raised above heart level to limit swelling, wearing the…

Glucosamine, Collagen and the Arthritis Diet: What Trials Show for Joint Pain
Glucosamine is a natural building block of cartilage sold as a supplement for osteoarthritis. Large randomized trials show it works no better than placebo…

Kinesiology Tape: What the Studies Show Behind the Colorful Strips
Kinesiology tape is a stretchy cotton strip applied over muscles and joints. Randomized trials and systematic reviews show it produces, at best, small and…
Pavlik Harness Warning Signs: Skin Redness, Swollen Feet and When to Call the Clinic
Mild pinkness under Pavlik harness straps that fades within about 30 minutes is common, but skin that stays red, weeps, cracks or smells needs…

Toe Shortening Surgery Recovery: Surgical Shoes, Swelling and When Shoes Fit Again
Toe shortening surgery recovery typically means a stiff-soled surgical shoe for several weeks, careful heel-weighted walking from the first days if the surgeon allows…

The McGill Big 3: The Back-Pain Exercises Spine Researchers Recommend
The McGill Big 3 is a set of three low-load core endurance exercises for people with low back pain: the modified curl up, the…