

Trigger Point Injections: How They Work and Who They Help
Key Takeaways
- A trigger point can refer pain far from the knot itself — a tight upper trapezius commonly sends pain up the neck and into the temple, mimicking a headache.
- Studies comparing injections with dry needling often find similar relief, which means the needle's mechanical disruption of the knot, not the medication, does most of the work.
- Relief typically lasts anywhere from several days to a few months, and stretching the treated muscle during that window is what converts short-term relief into lasting gain.
- Unlike steroid joint injections, steroid-free trigger point injections carry no strict yearly cap — but two or three failed injections is a signal to rethink the diagnosis, not schedule a fourth.
- Expect the treated muscle to feel like it hosted a hard workout for 24–48 hours; spreading redness, warmth, or fever afterward is not normal and warrants a same-day call.
- The rare serious risk is a partially collapsed lung when needling near the chest wall or deep shoulder — one concrete reason clinician experience and anatomy knowledge matter more than what's in the syringe.
Trigger point injections place a thin needle — often with a small amount of numbing medication — directly into a tight, tender knot of muscle to release it and calm the nerves feeding it. Evidence shows they can ease myofascial pain for days to months, though results vary widely, and they work best when paired with stretching, movement, and posture changes.
You know the spot. It sits just inside the shoulder blade, roughly where a backpack strap would dig in, and no amount of thumb-grinding against a doorframe makes it let go. Press it and the ache doesn’t stay put — it shoots up the neck, sometimes all the way to the temple. Massage helps for an afternoon. Then the knot is back, like it never left.
That stubborn, rope-like band of muscle has a clinical name — a myofascial trigger point — and a surprisingly direct treatment: a clinician finds the knot with their fingers and puts a needle in it.
It sounds almost too simple. And that’s exactly why it deserves an honest look. The procedure has been around for decades, the research is genuinely mixed in interesting ways, and the people it helps most are not always the people who ask for it.
What is a trigger point, exactly?
Run your fingers across a chronically tight trapezius and you may feel it: a taut band, like a guitar string under the skin, with one exquisitely tender nodule along its length. That nodule is a trigger point — a small patch of muscle fibers locked in contraction, refusing to relax even when the rest of the muscle is at rest.
The leading explanation, described in resources from the Mayo Clinic and the National Institutes of Health, goes something like this: overuse, injury, or sustained awkward posture keeps a cluster of fibers firing. Constant contraction squeezes the tiny blood vessels running through that patch, starving it of oxygen. The local chemistry turns acidic and inflammatory, which irritates nearby nerve endings, which keeps the fibers contracting. A loop forms, and the knot maintains itself.
Two features make trigger points clinically distinctive. First, referred pain: pressing a trigger point often reproduces pain somewhere else entirely. A knot in the upper trapezius can send pain behind the eye. One in the gluteal muscles can mimic sciatica. Second, the local twitch response — flick or needle the taut band and it visibly jumps, a brief involuntary contraction that clinicians use to confirm they’ve found the right spot.
Trigger points cluster in the neck, shoulders, and low back, but they show up almost anywhere skeletal muscle does. When they become persistent and start driving daily pain, the condition is called myofascial pain syndrome — and that is the diagnosis trigger point injections were designed for.
How do trigger point injections work?
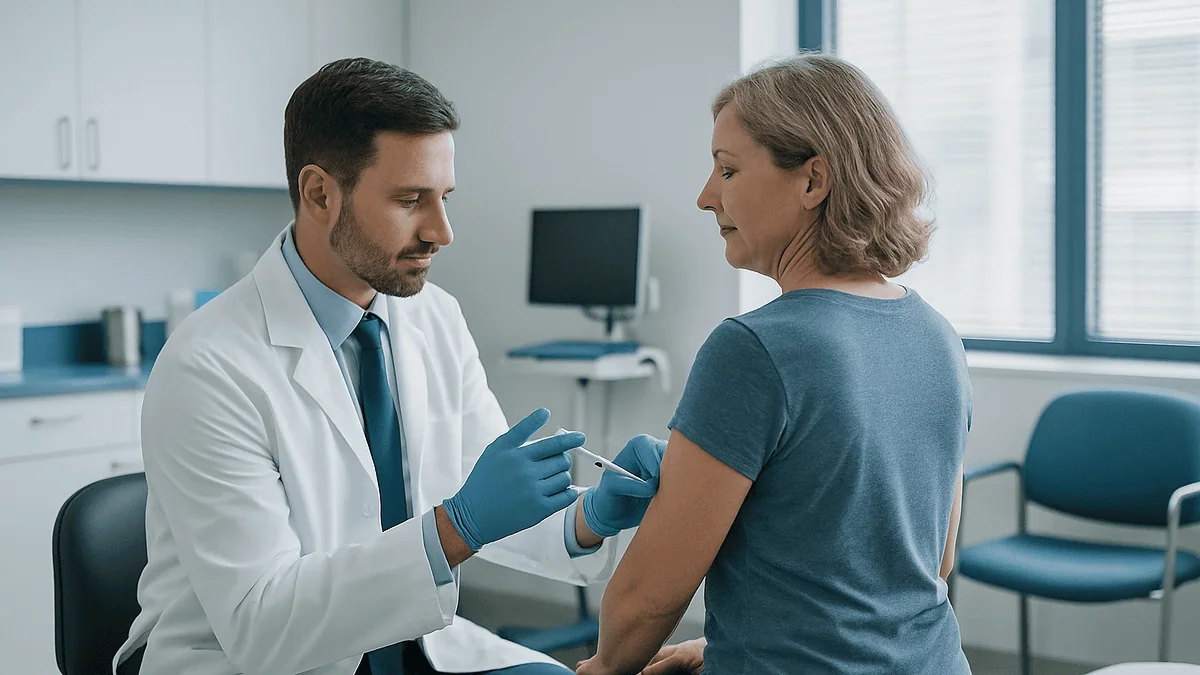
The procedure is disarmingly low-tech. A clinician locates the knot by feel, stabilizes it between two fingers, and passes a fine needle into it — usually several quick in-and-out passes, fanning through the taut band. Often a small volume of numbing medication goes in as well.
Why would that help? Researchers point to several overlapping mechanisms:
- Mechanical disruption. The needle physically breaks up the contracted fibers, like snipping a stuck zipper. Eliciting a local twitch response — that visible jump — is thought to signal that the loop has been interrupted, and studies associate the twitch with better relief.
- Chemical calming. A numbing agent quiets the irritated nerve endings inside the knot, giving the pain-spasm-pain cycle a chance to reset. It also makes the procedure and the day after considerably more comfortable.
- Washout. Injected fluid may dilute the inflammatory substances that have pooled in the oxygen-starved tissue.
- Improved blood flow. Once the fibers release, circulation returns, and the local chemistry can normalize.
Here is the part worth sitting with: a substantial body of research suggests the needle itself does much of the work. Studies comparing injections against dry needling — the identical technique with nothing in the syringe — often find similar pain relief. That doesn’t make the medication pointless; it mostly reduces soreness afterward. But it does tell you the treatment’s engine is mechanical, not pharmacological. That distinction shapes almost everything else in this article.
Do trigger point injections actually work?
The honest answer: yes for many people, modestly and temporarily, and the research has real limitations worth knowing about.
What the evidence supports fairly well: trigger point injections can reduce pain and improve range of motion in myofascial pain syndrome, particularly in the neck, shoulders, and low back. Relief commonly begins within a day or two — sometimes on the table — and lasts anywhere from several days to a few months. Clinical references from the Cleveland Clinic and the NIH-hosted StatPearls review both describe meaningful short-term benefit for appropriately selected patients.
What the evidence does not support: the idea of a one-and-done fix. Systematic reviews have struggled to show that any particular injected substance outperforms the needle alone, and trials are hard to blind — you know when you’ve been needled — which muddies the placebo question. Long-term outcomes depend heavily on what happens after the injection, not the injection itself.
A useful way to frame it: the injection opens a window. For a stretch of days or weeks, the muscle is looser and the pain quieter. People who use that window — stretching the muscle, correcting the workstation, rebuilding strength, fixing the sleep position that started the whole mess — tend to keep their gains. People who go straight back to the same desk, the same slouch, and the same twelve-hour laptop days tend to watch the knot re-form.
So the fair verdict is not “miracle” or “placebo.” It is: a legitimate, evidence-backed tool for short-term relief that earns its keep as part of a plan, rarely as the whole plan.
What's actually in the syringe?
People understandably want to know what’s being injected into their muscle. Without getting into specific medications — that conversation belongs with your own clinician — the options fall into a few well-defined categories.
- A local numbing medication. This is the most common choice. It temporarily quiets the nerve endings in the knot and, importantly, blunts the post-procedure soreness that otherwise follows needling.
- A numbing medication plus a steroid. Some clinicians add an anti-inflammatory steroid. Here the evidence is genuinely lukewarm: reviews have generally not shown that steroids add benefit for muscle trigger points, unlike their established role in inflamed joints and bursae. Steroids also carry their own local side effects, including thinning of skin and fat at the injection site with repeated use.
- Sterile saline. Salt water, essentially. It performs comparably to other solutions in some studies — another hint that the needle is the active ingredient.
- Nothing at all. Insert the needle without medication and you have dry needling, covered below.
Other injectable agents have been studied in specialty settings, mostly for stubborn cases, with mixed results — a reasonable question for a pain specialist rather than a reason to hold out on standard care.
The takeaway for a patient sitting on the exam table: the choice of solution matters less than the skill of the hands holding the syringe. Accurate palpation of the taut band, and reproducing your familiar pain before injecting, predict success far better than what’s in the barrel.
Trigger point injection vs. a steroid "cortisone" shot: what's the difference?
These two get conflated constantly, and the confusion is understandable — both involve a clinician, a syringe, and a sore body part. But they are different procedures aimed at different problems.
A steroid injection — what many people casually call a “cortisone shot” — delivers a potent anti-inflammatory into an inflamed structure: an arthritic knee joint, an irritated shoulder bursa, a cranky tendon sheath. The target is inflammation, the medication is the point, and because steroids can weaken tissue over time, clinicians typically limit how often one site is injected in a year.
A trigger point injection targets a contracted knot of muscle. The target is the knot itself, the needle does much of the work, and the injected solution — often just a numbing agent — plays a supporting role.
| Trigger point injection | Steroid joint/bursa injection | |
|---|---|---|
| Target | Taut band of contracted muscle | Inflamed joint, bursa, or tendon area |
| Main problem treated | Myofascial muscle pain | Inflammatory pain (e.g., arthritis, bursitis) |
| Active ingredient | Largely the needle; medication is supportive | The steroid medication itself |
| Typical relief window | Days to a few months | Weeks to several months |
| Repeat limits | Flexible if steroid-free; reassess if no benefit | Usually capped per site per year |
One practical consequence: if your pain is coming from a joint, a trigger point injection into nearby muscle will disappoint you — and vice versa. Getting the diagnosis right before anyone opens a needle package is half the battle.
How is this different from dry needling or acupuncture?
Three needle-based treatments, three different logics — though they overlap more than their practitioners sometimes admit.
Dry needling is the closest sibling. Same target (the trigger point), same goal (release the taut band, elicit the twitch), but no medication — often a thin filament needle rather than a syringe. In many states it’s performed by physical therapists as well as physicians. Head-to-head studies frequently show pain relief comparable to injections, with one consistent difference: more soreness in the day or two afterward, since there’s no numbing agent on board. If you’re already working with a physical therapist, dry needling folds neatly into a rehab program.
Acupuncture comes from an entirely different framework: needles placed at traditional points mapped centuries ago, not necessarily where the knot lives. Intriguingly, researchers have noted substantial geographic overlap between classic acupuncture points and common trigger point locations, which may explain why acupuncture sometimes helps muscle pain even though its theoretical model differs. Evidence for acupuncture in chronic pain is mixed but not dismissible; the NIH has funded considerable research on it.
Trigger point injections occupy the medical middle ground — physician-performed, medication-assisted, and the option most likely to be documented in a pain-management plan alongside imaging and diagnosis.
Which should you choose? Evidence doesn’t crown a clear winner for garden-variety myofascial pain. Access, cost, how your body handled previous needling, and who is already treating you are all legitimate deciding factors. The wrong answer is bouncing among all three without anyone addressing why the knots keep forming.
What happens during the appointment?
The whole visit often takes less time than the drive to it. Here is the typical sequence, so nothing surprises you.
First, the exam. The clinician presses along the muscle, hunting for the taut band and the tender nodule within it. A good practitioner will try to reproduce your pain — if pressing the spot lights up the familiar ache in your neck or temple, that’s confirmation they’ve found a culprit rather than a bystander. Expect this part to be briefly uncomfortable. It’s supposed to be; that’s the diagnostic signal.
Then, positioning and prep. You’ll sit or lie down — lying is preferred, since a small percentage of people feel lightheaded during needling — and the skin is cleaned with antiseptic. No sedation is needed.
The injection itself takes seconds per point. The clinician pinches the knot between two fingers to keep it from sliding away, inserts a fine needle, and moves it in small in-and-out passes through the band. You may feel a deep cramp or a sudden twitch — odd, but momentary, and generally a good sign. Medication, if used, goes in as the needle works. Afterward comes firm pressure for a minute or two to limit bruising, then a small bandage.
Several trigger points can be treated in one sitting. Most people walk out under their own steam, drive themselves home, and return to ordinary activities the same day, keeping strenuous use of the treated muscle off the schedule for a day or two.
Does it hurt, and what is recovery like?
Less than most people fear, more than nothing. The skin poke is minor — the needles are thin. The distinctive sensation comes when the needle finds the taut band: a deep, cramping ache, sometimes with that involuntary twitch, lasting a few seconds. Patients describe it as strange rather than sharp. If a numbing agent is used, the area often feels noticeably looser before you’ve put your coat back on.
Then comes the part worth planning around: post-injection soreness. For roughly 24 to 48 hours, the treated muscle typically feels like it hosted a hard workout — dull, bruise-like, tender to the touch. This is expected and not a sign anything went wrong.
What helps during that window:
- Ice for the first few hours if the site is tender; moist heat afterward if the muscle feels tight.
- Gentle, frequent stretching of the treated muscle — this is not optional comfort care, it’s part of the treatment. Stretching while the knot is released helps retrain the fibers to their full length.
- Normal daily movement. Bed rest works against you here; muscles that move recover their circulation faster.
- Skipping heavy lifting or intense training of that muscle group for a day or two.
By day three, most people are past the soreness and into whatever relief the injection is going to deliver. If instead the site becomes increasingly painful, red, warm, or you develop a fever, that’s not normal recovery — call the clinic promptly.
Who tends to benefit most from trigger point injections?
Not everyone with muscle pain is a good candidate, and the pattern of who responds well is fairly consistent across clinical experience and the literature.
The strongest candidates share a profile: a clear, palpable trigger point that reproduces their familiar pain when pressed; pain concentrated in one or a few muscles rather than everywhere; and a decent run of conservative care already behind them — stretching, physical therapy, heat, activity modification — that helped but didn’t finish the job. For these patients, an injection can break a cycle that hands and home exercises couldn’t.
Specific scenarios where the evidence and clinical practice line up well:
- Neck and upper-shoulder pain from trapezius and levator scapulae trigger points — the classic desk-worker pattern.
- Tension-type headaches traced to neck and shoulder knots that refer pain into the head.
- Low back and gluteal pain where a muscular trigger point mimics or aggravates other back problems.
- Myofascial pain flares that stall progress in physical therapy — the injection loosens the muscle enough for rehab to proceed.
A candid word about fibromyalgia: it’s a different condition. Fibromyalgia involves widespread pain and central nervous system sensitization, with tender points rather than discrete taut bands. Injections may help when a true trigger point coexists with fibromyalgia, but needling won’t treat the underlying condition, and some people with fibromyalgia find needling flares their symptoms. Expectations should be set accordingly — and the broader fibromyalgia treatment plan, not the syringe, remains the main event.
Who should not get trigger point injections?
The procedure is low-risk, but low-risk is not no-risk, and several situations call for delay, extra caution, or a different treatment entirely.
- Active infection at or near the site. Skin infection, cellulitis, or a systemic infection with fever means the needle waits. Introducing bacteria into deep tissue is the one complication everyone works hardest to avoid.
- Bleeding disorders or blood-thinning medication. Not an absolute barrier, but your clinician needs to know, because bruising and bleeding risk rises. Never stop a blood thinner on your own to get an injection.
- Allergy to local numbing medications. Rare, but real. Dry needling — no medication — is often the workaround.
- Pregnancy. Many clinicians proceed cautiously or defer elective injections; this is a case-by-case conversation, not a blanket rule.
- An unclear diagnosis. If nobody has actually confirmed a trigger point — if the “knot” hasn’t been palpated and your pain reproduced — injecting is premature. Muscle pain can mask joint disease, nerve compression, or, rarely, something more serious.
- Severe needle phobia or a history of fainting with procedures. Manageable (lying down helps enormously), but worth flagging in advance.
- Certain anatomic locations. Trigger points near the chest wall and upper shoulder sit close to the lung; experienced clinicians adjust technique and angle accordingly, and some prefer other treatments there.
None of these are reasons to feel excluded from pain care. They’re reasons the intake questions matter — answer them fully, even the ones that seem irrelevant.
What are the risks and side effects?
Compared with most procedures in a pain clinic, trigger point injections sit at the tame end of the spectrum. Still, informed consent means knowing the full list, not the brochure version.
Common and minor:
- Soreness at the site for one to two days — near-universal, and the reason gentle stretching is prescribed rather than rest.
- Bruising, especially in people on blood thinners or with fair skin.
- Temporary numbness or heaviness in the area if a numbing agent was used, fading within hours.
- Lightheadedness or fainting during the procedure — a vasovagal response to needling, not an allergy. Lying down for the injection largely prevents it.
Uncommon but worth knowing:
- Infection at the site — rare with sterile technique, but the reason spreading redness, warmth, or fever afterward warrants a same-day call.
- Bleeding into the muscle, producing a deeper, longer-lasting ache.
- Nerve irritation if a needle passes near a nerve — usually temporary tingling.
- Skin and fat thinning or a small dimple at the site, specifically when steroids are included and repeated.
Rare and serious: pneumothorax — a partially collapsed lung — when needling trigger points over the chest wall or deep shoulder. It is very uncommon in experienced hands, and it’s precisely why anatomy knowledge, not just palpation skill, matters in who performs your injection. Sudden shortness of breath or sharp chest pain after a chest-area injection is an emergency, not a wait-and-see.
Put in perspective: for most people, the realistic downside is two days of a sore muscle. The serious risks are rare, avoidable, and heavily technique-dependent.
How long does relief last — and how many injections will I need?
This is where honest expectation-setting earns its keep, because the range is wide. Some people get weeks or months of relief from a single session. Others feel great for four days and then watch the knot creep back. Clinical references describe typical relief spanning several days to a few months, and both ends of that range are normal.
Three factors reliably stretch the relief window:
- How long the trigger point existed. A knot that formed last month releases more durably than one that’s been entrenched for five years, complete with movement patterns built around it.
- Whether the cause was addressed. An injection can’t out-needle a monitor positioned eight inches too low or a shoulder bag carried on the same side for a decade.
- What you do in the first two weeks after. Stretching and progressive strengthening during the loosened window consolidates the gain; inactivity squanders it.
As for frequency: when injections are steroid-free, there’s no rigid annual cap the way there is for steroid joint injections. Clinicians commonly space sessions a few weeks apart and treat in a short series if the response is good. The more important rule runs the other direction — if two or three well-placed injections produce little or no relief, the answer is not a fourth injection. It’s a step back to reconsider the diagnosis. Pain that doesn’t respond to accurate trigger point treatment may not be trigger point pain, and continuing to needle it delays finding out what it actually is.
Why the needle is only half the treatment
The physicians who developed trigger point therapy in the mid-20th century paired every release technique with immediate stretching — the muscle was lengthened right after the knot let go. That instinct has held up. Modern practice treats the injection as the door-opener and rehabilitation as what walks through it.
What belongs alongside the injection, based on what the evidence and major clinical references consistently emphasize:
- Stretching the treated muscle daily, gently and often, especially in the first two weeks while it’s newly released.
- Strengthening once the pain settles. Weak, easily fatigued muscles form trigger points more readily; postural muscles in the neck and mid-back are the usual suspects.
- Ergonomic repair. Screen at eye level, elbows supported, phone out of the shoulder-to-ear crook. Trigger points in office workers are frequently a workstation problem wearing a medical costume.
- Sleep position and quality. Poor sleep lowers pain thresholds measurably, and a pillow that cranks the neck sideways for eight hours undoes daytime progress.
- Stress management. Sustained muscle tension from stress is a well-documented perpetuating factor — the clenched-jaw, hiked-shoulders posture that many of us hold without noticing.
You’ll also encounter advice about hydration and various supplements preventing trigger points. The candid version: evidence there is thin. Correcting a documented nutrient deficiency makes sense; chasing supplements without one does not, and it’s a conversation for your clinician, not the supplement aisle.
The pattern to internalize: injections relieve trigger points. Habits prevent them. Patients who get lasting results almost always changed something besides their pain level.
When should you see a doctor about muscle pain?
Most muscle knots are a nuisance, not a warning. But muscle pain is also a common disguise for problems that need different care, so certain signals should move you from self-massage to a medical appointment — some of them urgently.
Seek prompt medical care if muscle pain comes with:
- Fever, chills, or feeling generally unwell — muscle pain plus systemic symptoms needs evaluation.
- Numbness, tingling, or weakness in an arm or leg, which points toward nerve involvement rather than a simple knot.
- Loss of bowel or bladder control alongside back pain — an emergency, full stop.
- Pain following significant trauma, such as a fall or car accident.
- A limb that is swollen, red, and warm, particularly one calf — this needs same-day assessment to rule out a blood clot.
- Chest, jaw, or left-arm discomfort with exertion, sweating, or shortness of breath — treat as a possible heart problem and call emergency services.
Make a routine appointment if: the pain has persisted beyond a few weeks despite heat, stretching, and activity modification; it wakes you at night consistently; it’s accompanied by unexplained weight loss; or it keeps returning to the same spot no matter what you do. Persistent, recurring, localized muscle pain is precisely the scenario where a proper exam — and possibly a trigger point evaluation — pays off.
A pattern worth naming: many people wait years with a “bad shoulder” that turns out to be a treatable myofascial problem. Persistence, not severity, is often the better reason to get checked.
Frequently asked questions
Do trigger point injections actually work?
Yes, for many people with confirmed myofascial trigger points — but modestly and temporarily. Research supports short-term pain relief and improved range of motion, typically lasting days to a few months. The evidence is weaker on long-term benefit from injections alone; outcomes improve substantially when injections are paired with stretching, strengthening, and fixing whatever caused the knot, such as posture or workstation setup. Think of the injection as opening a window that rehabilitation then keeps open.
What drug is used for trigger point injections?
Most commonly a local numbing medication, sometimes combined with a steroid, and occasionally just sterile saline — or nothing at all, which is called dry needling. Interestingly, studies have generally not shown that any particular solution outperforms the needle itself; the numbing agent’s clearest benefit is reducing soreness afterward. The specific medication and amount are decisions for your clinician based on your health history, allergies, and the muscles being treated.
What is the difference between a cortisone shot and a trigger point injection?
They target different problems. A steroid injection — what many people call a “cortisone shot” — delivers anti-inflammatory medication into an inflamed joint, bursa, or tendon area, and the medication is the point of the procedure. A trigger point injection targets a contracted knot of muscle, where the needle’s mechanical disruption does much of the work and any medication plays a supporting role. Steroid injections are usually capped per site per year; steroid-free trigger point injections are not.
Who should not get trigger point injections?
People with an active infection at or near the site should wait, and those with bleeding disorders, on blood thinners, or with allergies to numbing medications need an individualized discussion first. Pregnancy usually prompts extra caution or deferral of elective injections. The procedure is also inappropriate when no actual trigger point has been confirmed by examination — muscle-like pain can mask joint, nerve, or other problems that need entirely different treatment.
How long do trigger point injections last?
Anywhere from several days to a few months, and both ends of that range are normal. Relief tends to last longer when the trigger point is relatively recent, when the underlying cause — posture, overuse, workstation setup — has been corrected, and when the treated muscle is stretched and strengthened during the weeks after the injection. If relief is consistently very brief across multiple sessions, that’s a cue to reassess the diagnosis rather than keep injecting.
How painful is a trigger point injection?
Briefly uncomfortable rather than severely painful. The skin poke is minor; the distinctive part is a deep cramping sensation, sometimes with an involuntary muscle twitch, lasting a few seconds when the needle reaches the knot — clinicians actually consider that twitch a good sign. Afterward, expect the muscle to feel sore, like a hard workout, for one to two days. Lying down during the procedure helps the minority of people prone to lightheadedness with needles.
How many trigger point injections can you get?
There’s no rigid limit when injections are steroid-free, unlike steroid joint injections, which are typically capped per site per year. Clinicians often space sessions a few weeks apart and may treat in a short series if you’re responding. The more meaningful boundary runs the other way: if two or three accurately placed injections produce little relief, the right move is re-evaluating the diagnosis, because pain that doesn’t respond may not be trigger point pain at all.
Can trigger point injections help tension headaches?
Sometimes, when the headache is being driven by trigger points in the neck and upper shoulders. Knots in the trapezius and nearby muscles commonly refer pain up into the head and behind the eye, mimicking or feeding tension-type headaches. If pressing those muscles reproduces your headache, treating them — with injections, dry needling, or hands-on therapy — can reduce headache frequency. Headaches with new or unusual features still deserve a full medical evaluation first.
Do trigger point injections work for fibromyalgia?
Not as a treatment for fibromyalgia itself. Fibromyalgia involves widespread pain and heightened central nervous system sensitivity, with tender points rather than the discrete taut bands injections target. When a true trigger point coexists with fibromyalgia, injecting it may relieve that specific spot — but it won’t address the underlying condition, and some people with fibromyalgia find needling temporarily flares symptoms. The broader fibromyalgia care plan remains the primary treatment.
What should I do after a trigger point injection?
Move normally, stretch gently and often, and skip strenuous use of the treated muscle for a day or two. Ice can ease early tenderness; moist heat helps if the muscle feels tight afterward. Soreness for 24–48 hours is expected. The first two weeks are the valuable window — daily stretching and gradually rebuilding strength during that period is what makes relief last. Call the clinic if you develop fever, spreading redness, warmth, or worsening pain at the site.
References
- Trigger Point Injection — Cleveland Clinic
- Trigger Point Injection — StatPearls, NCBI Bookshelf (NIH)
- Fibromyalgia — MedlinePlus
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What Sciatica Feels Like: Leg, Groin, Knee and Both Legs
Sciatica usually feels like a sharp, burning or electric pain that starts in the lower back or buttock and travels down the back of…

Steroid Injection Side Effects: What Is Normal and What Needs a Call
Mild soreness, a brief flare of pain lasting 24 to 72 hours, facial flushing, and a temporary rise in blood sugar are common and…
Cortisone Shots in the Knee: Relief, Limits and the Repeat-Injection Question
A cortisone shot in the knee delivers a corticosteroid directly into the joint to calm inflammation. Relief typically begins within a few days and…

How Long Does a Nerve Block Last? From Numbness to Full Sensation Returning
A nerve block for surgery usually lasts several hours to about a day, and sometimes longer, depending on the local anesthetic used, the nerve…
Cortisone Shots in the Shoulder: What to Expect and When They Make Sense
A cortisone shot in the shoulder is a corticosteroid injection that calms inflammation in a joint, bursa, or around a tendon. Relief usually begins…

Knee Gel Injections: Cost and Evidence for Hyaluronic Acid, Honestly
The price of hyaluronic acid knee injections varies widely with the product used, the number of injections in a course, imaging guidance, and country,…