

What a CT Scan Shows Before Zygomatic Implants: Cheekbone Volume, Sinus Anatomy and the Path

Key Takeaways
- A zygomatic implant anchors in the cheekbone rather than the jaw ridge, so the CT has to measure the zygoma's thickness along the exact angle the implant will travel.
- The maxillary sinus sits in the implant's path, and a clouded sinus, blocked drainage opening or large cyst on the scan is a common reason teams pause and refer to an ear, nose and throat specialist first.
- Cone beam CT gives relative grey values rather than calibrated Hounsfield units, so a report of "soft bone" is an impression, and a medical CT may be added when density really matters.
- Titanium is non-magnetic and poses no safety issue in a CT scanner; its only effect is streak artifact that can obscure thin bone next to an existing implant.
- Implant length and angle are chosen on the scan before surgery, which is the main practical reason freehand zygomatic placement without 3D imaging is not accepted practice.
- Published survival figures for zygomatic implants depend on definitions and follow-up length, so a number quoted without a source and timeframe should prompt a question, not reassurance.
A CT scan for zygomatic implants gives the surgical team a three-dimensional map of the upper jaw and cheekbones. It shows how much bone the zygoma can offer, where the maxillary sinus sits and how healthy it looks, and the safest route an implant can take from the mouth to the cheekbone while avoiding the eye socket, nerves and sinus lining.
The dentist turns the screen so you can see it, and there it is: your own skull, rotating slowly, with a blank stretch where the upper molars used to be. She points to a pale shadow above it and says the bone there is “too thin to hold anything.” Then she says the word you have been reading about late at night: zygomatic.
For many people with a severely resorbed upper jaw, this conversation ends with a referral for a CT scan for zygomatic implants, and a new set of questions. What exactly is the scanner looking for? Why the cheekbone? What is the sinus doing in a dental conversation at all?
The short version is that nobody drills toward a cheekbone on a hunch. The scan is the whole plan, measured in millimeters. This article walks through what it reveals, section by section, and what it cannot tell anyone.
Why would a dentist order a CT scan for zygomatic implants?
Ordinary dental X-rays are flat. A panoramic film squashes a curved jaw onto a single sheet, and a bitewing shows two or three teeth at a time. Neither can tell a surgeon how wide a bone is from cheek to tongue, because width is the one dimension a flat image discards.
Standard dental implants live in the alveolar ridge, the horseshoe of bone that once held tooth roots. When teeth are lost, that ridge shrinks; the body stops maintaining bone it no longer uses. In the upper jaw the problem is doubled, because the maxillary sinus, an air-filled cavity above the back teeth, tends to expand downward into the space the roots left behind. The result can be a shelf of bone thinner than a credit card between mouth and sinus.
Zygomatic implants solve this by skipping the ridge altogether and anchoring in the zygoma, the dense cheekbone beneath the eye. That changes the stakes. A standard implant drilled a few millimeters off course meets more jawbone. A zygomatic implant drilled off course can enter the orbit (the eye socket), the nasal cavity, the sinus or the soft tissue of the cheek.
So the question “why do dentists do CT scans” has a particularly sharp answer here. According to Mayo Clinic, implant planning routinely uses three-dimensional imaging to assess bone quantity and the position of nearby structures. For zygomatic cases the scan is not an optional extra; it is the only way to measure the cheekbone, chart the sinus and rehearse the implant’s path before anyone picks up a drill.
What a zygomatic implant actually is, and why the cheekbone matters
Picture a conventional implant as a screw the length of a tooth root, placed vertically into jawbone. Now picture a much longer screw that enters the mouth roughly where a molar sat, angles upward and outward, passes alongside or through the sinus, and bites into the cheekbone. That is a zygomatic implant.

Both kinds rely on the same biology. Osseointegration is the process by which living bone grows onto a titanium surface and locks it in place; Mayo Clinic describes this bonding as the foundation that lets an implant bear chewing forces. The difference is where that bonding happens. In a zygomatic case, most of the implant’s length travels through space that offers little support. The grip comes from the final stretch, embedded in the zygoma.
The zygoma earns its role for two reasons. It is dense cortical bone, the hard outer type, rather than the spongy cancellous bone that fills much of the jaw. And it sits in a predictable location, forming the lateral wall of the orbit and the prominence of the cheek. Surgeons describe the usable portion as a curved buttress; the implant tip needs to seat within that buttress with bone on all sides.
This is why “cheekbone volume” is not a vague phrase. The scan has to show how thick the buttress is at the planned entry point, how far the implant must travel to reach it, and whether the angle required to get there leaves enough margin from the eye above and the cheek skin outside. Every one of those is a measurement, and every measurement comes from the CT.
How a CT scan for zygomatic implants works, step by step
Computed tomography builds an image by firing a thin X-ray beam through the body from many angles and letting a computer reconstruct the result as cross-sections. The NHS compares the output to slices through a loaf, which can then be stacked back into a three-dimensional model.
For dental and facial work, most teams use cone beam CT (CBCT), a scanner that uses a cone-shaped beam and rotates once around the head while the patient sits or stands. The scan itself is brief; the NHS notes that CT scans generally take 10 to 20 minutes including positioning, and a dental cone beam acquisition is usually well inside that. You bite on a small rest or stabilize your chin, hold still, and the arm sweeps around you.
Here is what usually happens, in order:
- Metal objects such as earrings, glasses and removable dentures come out, because metal scatters X-rays and streaks the image.
- The technician positions your head so the Frankfort plane, an imaginary line from ear canal to the lower edge of the eye socket, sits level, which keeps anatomy comparable across scans.
- The scanner records a set of images; you may hear a soft hum.
- Software reconstructs the volume into axial, coronal and sagittal slices (horizontal, front-to-back and side-to-side planes) plus a rotating 3D model.
The planning work starts afterward. A surgeon or planning specialist scrolls through the slices, traces the sinus floor, measures the cheekbone and places a virtual implant of a chosen length and angle. Many teams then convert that plan into a physical surgical guide, a custom resin template that fits over the teeth or bone and directs the drill along the planned path. The scan, in other words, is less a photograph than a blueprint.
Cheekbone volume: what the scan measures in the zygoma
Open the coronal slices, the ones that look at the face head-on, and the zygoma appears as a bright, dense wedge at the outer edge of each cheek. Bright means dense: CT assigns every tiny cube of tissue a grey value that tracks how much X-ray it absorbs, so cortical bone glows white while air in the sinus reads black.
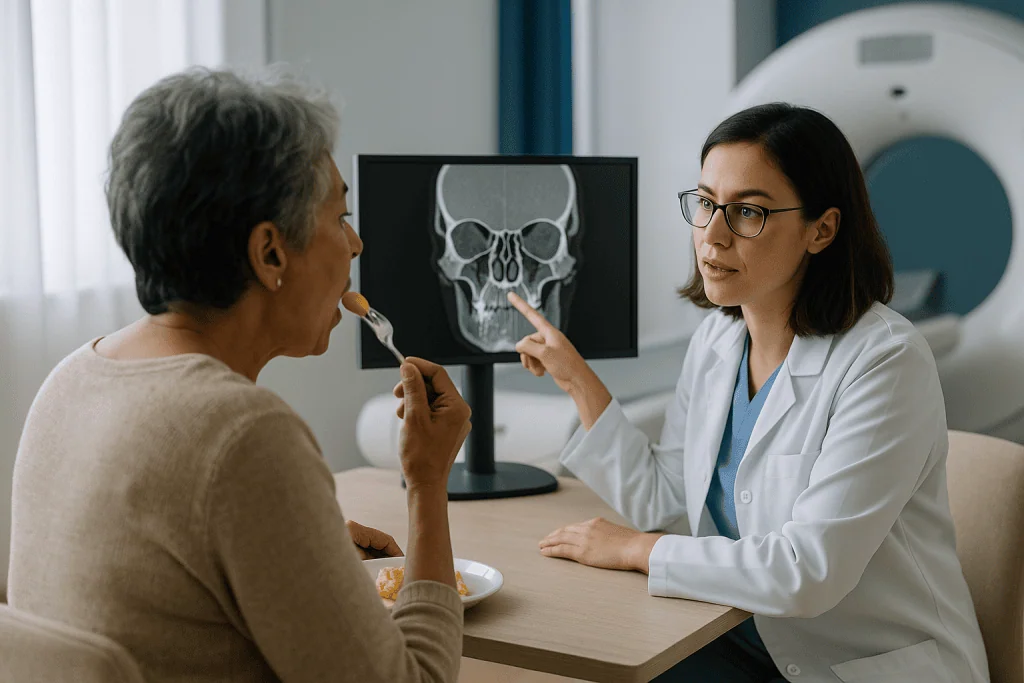
Three features of that wedge decide whether a zygomatic implant is feasible on a given side.
The first is thickness along the planned trajectory. The implant tip should be surrounded by bone, so the surgeon measures the zygoma where the implant would exit the sinus and enter the cheekbone. Thin, flaring cheekbones offer a shorter run of dense bone than broad ones; anatomy varies widely between individuals and even between the left and right side of the same face.
The second is bone quality. Older age, long-term tooth loss, osteoporosis and some medicines can reduce bone density, and the scan’s grey-scale values give an approximate reading. Cone beam scanners do not produce true calibrated Hounsfield units, the standardized density scale used on medical CT, so most clinicians treat these numbers as a relative guide rather than a precise score. If density is in doubt, a medical CT may be added.
The third is the relationship between the zygoma and the orbit. The eye socket’s floor and lateral wall are formed partly by the same bone. The scan lets the team confirm that the planned implant tip stays below and outside the orbital rim with a comfortable margin.
Put together, these readings answer a plain question: on this side of this face, is there enough good bone, in the right place, to hold a long implant for years of chewing? Sometimes the answer is yes on one side and no on the other, and the plan changes accordingly.
Sinus anatomy: what the maxillary sinus tells the surgeon
The maxillary sinus is the largest of the paranasal sinuses, a pyramid of air inside each cheek that drains into the nose. Its floor is often the ceiling of the upper back teeth, which is why sinus infections can mimic toothache and why zygomatic implants cannot avoid it.
MedlinePlus lists sinus CT among the standard ways to assess sinus disease, and the pre-implant scan does that job as a by-product. The surgeon looks for several things:
- Whether the sinus is clear and black (air) or clouded with grey (fluid, swollen lining or a polyp).
- How thick the mucosal lining is along the floor and lateral wall.
- Whether the ostium, the small drainage opening into the nose, appears open.
- Septa, which are bony partitions inside the sinus that can complicate drilling.
- How far the sinus has pneumatized, meaning expanded, into the former tooth-bearing bone.
The findings shape the technique. Where the sinus wall is concave and the bone outside it is thin, many surgeons route the implant along the outside of the sinus, in or against the lateral wall, so that less of the implant sits inside the air space. Where the wall is flatter and thicker, an intrasinus path, passing through the cavity, may be chosen. The scan is what makes that decision possible before the first incision.
Active sinus disease is a different matter. Chronic inflammation, blocked drainage or a large cyst are reasons many teams pause and refer to an ear, nose and throat specialist first. Placing a long implant through a sinus that is already struggling to drain can worsen sinusitis afterward, one of the better-known complications of this procedure. Seeing the problem on the CT in advance is far better than discovering it with a swollen cheek weeks later.
The path: how the planned route of the implant is drawn
If volume and sinus anatomy are the “where,” the path is the “how.” On the planning software, the surgeon places a virtual implant and adjusts three things until the geometry works: the entry point in the mouth, the exit point into the cheekbone and the angle connecting them.
The entry point matters for the final teeth. A zygomatic implant that emerges too far toward the palate produces a bridge that is bulky and hard to clean; one that emerges too far toward the cheek may not be covered by gum. Planners aim for the implant head to sit roughly under the future tooth position, which often means a trade-off with the bone available higher up.
The angle is constrained by what the implant must miss. Too steep and it threatens the orbit. Too shallow and it may leave the zygoma with only a few millimeters of grip, or exit through the cheek skin. Software lets the team rotate the model and view the planned implant from every direction, checking the gap to the orbital floor, the infraorbital nerve (which supplies feeling to the cheek and upper lip) and the outer cheek contour.
Length follows from everything else. Because the implant is measured on the scan from entry to tip, the team can select the length before surgery instead of estimating during it, which is one of the main practical reasons the CT is indispensable. The plan is then transferred to the patient by one of several methods:
- A printed surgical guide with sleeves that direct the drill.
- Real-time navigation, where a tracked drill is displayed on the CT during surgery.
- Freehand placement by an experienced surgeon using the CT as a reference.
Each has advocates and limits. Research on guided placement generally reports smaller deviations from the plan than freehand, but a guide can only be as accurate as the scan and the fit of the template. The surgeon’s judgment in the room remains the final check.
Cone beam CT for dental implants vs medical CT: which scan and why
Two kinds of scanner can produce the three-dimensional images a zygomatic plan needs, and patients are sometimes sent for both. Knowing why saves confusion.
| Feature | Cone beam CT (dental) | Medical multislice CT |
|---|---|---|
| Where it is done | Dental or oral surgery office | Hospital radiology department |
| Patient position | Sitting or standing, head stabilized | Lying on a table that moves through a ring |
| Field of view | Adjustable, often jaws and sinuses only | Whole head and face, or wider |
| Bone density readings | Relative grey values, not calibrated | Calibrated Hounsfield units |
| Soft tissue detail | Limited | Better, especially with contrast |
| Radiation dose | Generally lower for the same region | Higher, varies with protocol |
| Typical role | Routine implant planning and guides | Complex anatomy, prior facial surgery, sinus disease work-up |
Cone beam CT for dental implants is the workhorse. It images bone crisply, exposes a smaller area and integrates directly with the software used to design surgical guides. The NIH’s National Institute of Biomedical Imaging and Bioengineering notes that CT dose depends heavily on the body region and settings chosen, and dental cone beam protocols are designed to keep the exposed volume small.
Medical CT enters the picture when the question goes beyond bone shape. If the team suspects chronic sinus disease, needs reliable density values, or is dealing with a face altered by trauma, cancer surgery or a cleft, the hospital scanner offers a fuller view. A radiologist’s report also comes with it, which is useful when incidental findings appear in the sinuses or skull base.
Neither is “better” in the abstract. The right choice is the one that answers the specific question your surgeon is asking, and that decision belongs to the treating team.
Who zygomatic implants are usually for, and who is usually asked to wait
Zygomatic implants were developed for people whose upper jaw has lost so much bone that conventional implants cannot be placed, even with grafting, or for whom grafting has already failed. Typical candidates include those with long-standing complete upper tooth loss, those who have had part of the upper jaw removed for disease, and those who want to avoid the extended healing that bone grafting from the hip or skull involves.
The CT is what sorts candidates into categories. It may show that the back of the jaw is hopeless but the front retains enough bone for standard implants, which supports a “hybrid” plan mixing both types. It may show enough cheekbone for one zygomatic implant per side, or so little ridge that two per side are considered. Or it may show reasons to pause.
People commonly asked to wait or reconsider include those with:
- Active or chronic maxillary sinus infection, until it is assessed and treated.
- Uncontrolled diabetes, which Mayo Clinic lists among conditions that can impair healing around implants.
- Current heavy smoking, which raises the risk of implant failure and sinus complications.
- A history of radiotherapy to the jaws, which reduces blood supply to bone.
- Treatment with certain bone-modifying medicines used for osteoporosis or cancer, where the prescribing clinician and surgeon need to weigh the risk of poor jaw healing together.
- Cheekbones that the scan shows to be too thin or too shallow on the planned side.
Being asked to wait is not the same as being turned away. A sinus can be cleared, blood glucose can be brought into range, and a scan can be repeated. What the CT provides is an honest starting point, so that the conversation about timing is grounded in what the bone and sinuses actually look like rather than in hope or hurry.
Can you have a CT scan with a titanium implant, and is there metal in a tooth implant?
Yes to both, and the two questions are connected. Nearly all dental implants, zygomatic ones included, are made of titanium or a titanium alloy; a smaller number use zirconia, a ceramic. Titanium is used because bone bonds to its oxide surface, it resists corrosion in the mouth and it is non-magnetic.
That last property matters for imaging. A CT scan uses X-rays, not a magnetic field, so an existing titanium implant poses no safety problem at all; the NHS and Mayo Clinic list no implant-related restriction for CT. Even MRI, which does use a powerful magnet, is generally considered safe with titanium dental implants, although you should always tell the MRI staff what you have. Cardiac devices and some older surgical clips are a separate conversation, and the radiology team will ask about them.
What titanium does do on CT is scatter the beam. Around a dense metal object, the reconstruction produces bright and dark streaks known as artifact, which can hide the thin bone right next to the implant. Modern scanners include metal-artifact reduction software, and planners can usually work around a few existing implants, crowns or fillings. If you already have implants in the upper jaw, the team may simply position the scan or adjust the settings to limit the streaking.
After zygomatic implants are placed, a follow-up CT is sometimes taken to confirm position relative to the sinus and orbit. The implants themselves appear as bright white rods. They do not set off problems in the scanner; they just cast shadows that the radiologist knows to expect.
One practical note: removable dentures, especially those with metal frameworks, should come out before the scan unless your surgeon specifically asks you to wear a marked radiographic guide, a special denture containing small markers that help align the plan with your mouth.
What the days and weeks after the scan usually look like
The scan takes minutes. The thinking takes longer, and it helps to know that the quiet period afterward is active work rather than a queue.
In the first few days, the image data, stored in a universal format called DICOM, is loaded into planning software. The surgeon, and often a restorative dentist who will design the final teeth, review the slices together. Many teams also take a digital scan of the mouth and a facial photograph so that the planned implants can be checked against where the teeth should sit for speech and appearance, not just where the bone is.
Over the following weeks, several things may happen in parallel:
- If the CT raised a sinus concern, a referral to an ear, nose and throat specialist, possibly with a second scan.
- A planning consultation where the virtual implants are shown to you on screen and the trade-offs explained.
- Fabrication of a surgical guide, if one is to be used, which takes time to design, print and check against a model of your jaw.
- Medical clearance, blood tests or coordination with the clinician who manages any long-term condition.
Occasionally the plan calls for repeating the scan: if teeth are extracted in the interim, if the first scan was taken with a denture that did not fit, or if too much time passes and the bone may have changed. Bone remodels continually, and a scan older than a few months may not match what the surgeon finds.
After surgery itself, Mayo Clinic describes dental implant healing as a process that unfolds over months while osseointegration occurs, and zygomatic cases follow the same biology even when provisional teeth are fitted early. The imaging story continues too: periodic X-rays or a follow-up CT let the team confirm that the implant and the sinus are behaving as planned. None of these timelines is a promise; they are the ordinary shape of the process, and your team will give you the version that fits your case.
Radiation, safety, and what the CT scan cannot show
Any X-ray-based scan involves ionizing radiation, and it is reasonable to ask about it. The NHS and Mayo Clinic both describe the dose from a single CT as small in absolute terms and the long-term risk as very low, while advising that scans should be done only when the information is needed. A zygomatic implant plan clearly meets that bar; proceeding without one would expose you to a far more tangible surgical risk.
Dose depends on the equipment, the area scanned and the resolution requested. The National Institute of Biomedical Imaging and Bioengineering explains that newer scanners and tailored protocols can reduce exposure substantially, and dental cone beam machines are built to image a limited volume. Tell the team if you are or might be pregnant; the jaws are far from the abdomen and a lead apron is often used, but the conversation should happen before the scan, not after.
Equally worth knowing is what the scan cannot do.
- It cannot show how your bone will respond biologically. Density is a proxy for healing capacity, not a measurement of it.
- It cannot see gum thickness or quality well, which affects how the final bridge sits and how easy it is to clean.
- It cannot predict infection, smoking-related failure or how you will adapt to a full-arch prosthesis.
- Cone beam density values are not calibrated, so “soft bone” on the report is an impression, not a diagnosis.
And it occasionally shows things nobody was looking for: a retained root, a cyst in the jaw, a thickened sinus lining, a calcification in a neck artery at the edge of the field. Reputable practice is to have unexpected findings reviewed, sometimes by a radiologist, and to tell you about them. If something appears on your scan that you do not understand, ask for a plain explanation. The image is yours.
What people often get wrong about CT scans and zygomatic implants
Some beliefs travel from forum to forum and need correcting.
“The scan is just a formality; the surgeon decides in the operating room.” The opposite is closer to the truth. For zygomatic cases, the decisive measurements, cheekbone thickness, sinus condition and implant length, are made on the scan. Surgeons adjust during surgery, but they do not start without a plan derived from the CT.
“A panoramic X-ray shows the same thing.” A panoramic image cannot measure bone width or show the sinus walls in cross-section. It is useful for an overview and worthless for plotting a path to the cheekbone.
“If the scan says I have thin bone, implants are impossible.” Thin alveolar bone is precisely the situation zygomatic implants were designed for. What matters is the zygoma, and most people retain usable cheekbone even after decades without upper teeth. The scan tells you which category you are in; it does not close doors by itself.
“Titanium will set off the scanner or make it unsafe.” CT uses X-rays, not magnetism. Existing implants create streaks on the image, nothing more.
“Success rates on the internet apply to me.” Published reviews of zygomatic implants report high survival over several years of follow-up, but definitions differ, follow-up periods vary, and populations in those studies may not resemble you. Numbers quoted without a source, a timeframe and a definition of “success” are marketing, not evidence. Ask your team what their own outcomes are and how they define a complication.
“The scan will tell me how my new teeth will look.” Bone is only half the picture. The appearance of a full-arch bridge depends on lip support, gum display and tooth design, which come from the restorative plan, not the CT alone. Teams that combine the scan with facial photographs and a mouth scan are closing that gap, but it is still a design conversation, not a readout.
Questions to ask your care team about your CT scan
A planning consultation goes better when you arrive with specific questions. These are the ones that tend to produce the most useful answers.
- Can you show me my cheekbone on the scan and explain how much bone the implant tip will sit in?
- What does my maxillary sinus look like, and did you see any signs of inflammation or blocked drainage?
- Will the implant run inside the sinus or along its outer wall, and why did you choose that path for me?
- How many zygomatic implants are you planning per side, and are any conventional implants part of the plan?
- Are you using a printed surgical guide, navigation or freehand placement, and what is your reasoning?
- Did the scan show anything unexpected, in the sinuses or elsewhere, that should be checked?
- Is the scan recent enough, or will it need repeating before surgery?
- Which parts of my medical history or medicines could affect bone healing, and who will coordinate that?
- What complications specific to zygomatic implants should I know about, including sinus problems and changes in cheek sensation, and how would each be managed?
- What would make you stop and change the plan during surgery?
- How will you check the implant position afterward, and will that involve another scan?
- If the scan shows I am not a candidate on one side, what are the alternatives?
Notice that none of these asks for a guarantee. Good teams will answer with ranges, mechanisms and honest uncertainty. If an answer comes back as a single confident number with no source, a follow-up question is fair: “Where does that figure come from, and over how many years?”
It also helps to ask who will review the images. In many settings the oral surgeon reads the cone beam scan; in others a radiologist produces a formal report. Either can be appropriate, but you are entitled to know, and to request a copy of the images and report for your own records.
When to call your doctor
Most of this article concerns planning, but imaging and surgery both have moments when you should not wait for the next appointment.
After the scan itself, serious problems are rare because nothing invasive has happened. Contact the team if you were given a radiographic denture or marker to wear and it broke, or if you develop a new sinus or dental symptom before surgery, because it may change the plan.
If the scan reveals an unexpected finding and you were told it would be followed up, call if you have not heard back within the time the team suggested.
After zygomatic implant surgery, seek prompt care, through your surgeon or an emergency department if the practice is closed, for any of the following:
- Fever, spreading facial swelling, or swelling that worsens after the third or fourth day instead of easing.
- Pain or pressure in the cheek with thick, foul-smelling nasal discharge, which can signal sinus infection.
- Any change in vision, double vision, pain behind the eye, or swelling around the eye.
- Persistent numbness or tingling of the cheek, upper lip or side of the nose that is not improving.
- Bleeding that soaks through gauze repeatedly or returns after it had stopped.
- Air or fluid passing between your mouth and nose when drinking.
- A loose or mobile implant or provisional bridge.
- Difficulty breathing, chest pain or a fast heartbeat, which need emergency care regardless of the surgery.
Trust the pattern more than any single symptom: discomfort that follows the arc your team described, easing a little each day, is expected; anything that bucks that arc deserves a call. Keep the emergency contact number you were given somewhere you can find it at night, and do not adjust any prescribed medicine on your own; the clinician who prescribed it should make that decision with you.
Frequently asked questions
Why would a dentist do a CT scan before implants in the upper jaw?
Because flat X-rays cannot show bone width or the sinus in cross-section. A CT reveals how much bone remains between the mouth and the maxillary sinus, where nerves and the eye socket sit, and whether the cheekbone can hold a zygomatic implant. For a procedure that angles a long implant toward the orbit, three-dimensional planning is standard practice rather than an optional extra.
What does the CT scan show about cheekbone volume?
It shows how thick and dense the zygoma is at the point where the implant tip will seat, and how far that point lies from the entry in the mouth. The surgeon views coronal and sagittal slices to confirm bone surrounds the planned tip on all sides, with a safe margin from the orbital floor. Thin or steeply flaring cheekbones may change the plan on one or both sides.
How does sinus anatomy affect zygomatic implant planning?
The maxillary sinus lies directly in the implant’s path, so the scan is checked for a clear, air-filled cavity, a thin healthy lining and an open drainage opening. Its shape also decides whether the implant travels inside the sinus or along its outer wall. Signs of chronic infection, polyps or a large cyst usually lead to an ear, nose and throat assessment before any surgery is scheduled.
Is cone beam CT for dental implants the same as a hospital CT?
No. Cone beam CT is a compact scanner used in dental settings that images a limited volume at lower dose and integrates with guide-design software, but its density values are not calibrated. Hospital multislice CT gives calibrated Hounsfield units and better soft-tissue detail, which helps with sinus disease or complex anatomy. Surgeons choose based on the question they need answered, and sometimes use both.
Can you have a CT scan with a titanium implant already in place?
Yes. CT uses X-rays rather than a magnetic field, and titanium is non-magnetic in any case, so an existing implant poses no safety concern. It does create bright streaks, called artifact, that can hide thin bone nearby. Modern scanners use artifact-reduction software, and the team can adjust positioning or settings. Always tell imaging staff about any implants or devices before a scan of any kind.
Is there metal in a tooth implant?
Almost always. Most dental implants, including zygomatic ones, are made of titanium or a titanium alloy, chosen because bone bonds to its surface and it resists corrosion. A minority use zirconia, a ceramic. Titanium is non-magnetic, is not detected by typical security scanners and does not prevent CT or MRI, though you should still inform radiology staff about it before any imaging.
What is the zygomatic implants success rate?
Published systematic reviews report high implant survival over several years of follow-up, but the figures vary with how success is defined, how long patients were followed and what complications were counted. Sinus problems and soft-tissue issues occur more often than outright implant loss. Rather than relying on a single internet number, ask your surgical team for their own outcomes, their definition of success and the follow-up period behind it.
How long does the CT scan for zygomatic implants take?
The scan itself is brief. The NHS notes that CT appointments generally take around 10 to 20 minutes including positioning, and a dental cone beam acquisition is usually a single rotation lasting well under a minute. The longer part is afterward, when the images are reconstructed, measured and turned into a surgical plan, which can take days to weeks depending on whether a guide is fabricated.
What happens if the scan shows a problem with my sinus?
The usual step is a pause rather than a cancellation. Many surgeons refer to an ear, nose and throat specialist to assess and treat inflammation, blocked drainage or a cyst, sometimes with a second scan. Once the sinus is healthy, planning resumes. Placing a long implant through an already inflamed sinus raises the risk of sinusitis afterward, so clearing it first is standard practice.
Does a CT scan show how my new teeth will look?
Not on its own. The scan maps bone and sinuses, but the appearance of a full-arch bridge depends on lip support, how much gum shows when you smile and the design of the teeth. Many teams combine the CT with a digital scan of the mouth and facial photographs so the implants can be positioned under the planned teeth. Ask to see that combined plan, not just the bone.
References
- NHS: CT scan
- MedlinePlus: Sinus CT scan
- NIH National Institute of Biomedical Imaging and Bioengineering: Computed Tomography (CT)
- Cleveland Clinic: Dental Implants
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Preparing for All On 4: Imaging, Bite Records, Infection Control and What to Pause Beforehand
All on 4 preparation usually involves a medical and dental history review, a three-dimensional CBCT scan of the jaws, photographs and bite records that…

How Grinding and Erosion Lead to Full Mouth Reconstruction: Bite Collapse and Tooth Wear
Tooth wear bite collapse happens when years of grinding (bruxism) or acid erosion shorten the teeth enough that the jaws close too far, straining…

Who Is a Candidate for All On 6? Bone Volume, Bite Force and When Six Implants Are Advised
An all on 6 candidate is usually an adult missing most or all teeth in one jaw, with enough jawbone in the back of…
Why You Never Stop Blood Thinners Alone Before a Dental Bone Graft: What the Surgeon Checks
Stopping a blood thinner on your own before a dental bone graft is rarely advised. Most guidelines say routine dental surgery, including grafting, can…
Who Needs a Porcelain Crown? Cracked, Heavily Filled and Root-Treated Teeth Explained
A porcelain crown is usually considered when a tooth has lost too much sound structure for a filling to hold it together: a cracked…
Dental Crown Myths: Does a Crowned Tooth Stop Decaying and Never Need Care Again?
No. A dental crown covers the visible part of a tooth, but it cannot stop decay. The natural tooth structure beneath and around the…