

What a Renal Ultrasound Can Show: Stones, Cysts, Blockage and What Happens After the Report
Key Takeaways
- A renal ultrasound shows structure, such as kidney size, cysts, stones, and swelling from blocked drainage, but cannot measure kidney function, which comes from blood and urine tests.
- A simple cyst on ultrasound is round, black, thin-walled, and fluid-filled; such cysts are common with age and, according to the National Institute of Diabetes and Digestive and Kidney Diseases, rarely need treatment.
- Hydronephrosis, a kidney swollen with backed-up urine, is often clearly visible on ultrasound even when the stone or narrowing causing it is not, which is why a CT scan frequently follows.
- Ultrasound misses many small stones and stones in the mid-ureter, so being sent for CT after a normal scan when a stone is suspected is standard practice rather than a sign of a mistake.
- Kidneys that appear small, bright, or thin-walled on ultrasound suggest long-standing disease, but early chronic kidney disease frequently looks completely normal on the scan.
- Most ultrasound scans take 15 to 45 minutes according to the NHS, involve no radiation or dye, and results usually reach you via the referring clinician within days to weeks depending on urgency.
A renal ultrasound uses sound waves to picture the kidneys and often the bladder. It can show kidney size and shape, fluid-filled cysts, many kidney stones, swelling from blocked urine flow (hydronephrosis), solid masses that need further imaging, and structural changes seen with long-standing kidney disease. It cannot measure kidney function, so results are read alongside blood and urine tests by your treating team.
The sonographer dims the lights, warms the gel a little, and asks you to roll onto your side and hold your breath. On the screen, a gray, kidney-shaped shadow flickers into view. You have no idea what you are looking at, but you notice she pauses, clicks, measures, and moves on without a word. Then the appointment ends and you are left with a paper gown and a question you did not know how to ask.
Most people who search what does a renal ultrasound show are in that gap between the scan and the conversation with their doctor. Maybe a blood test flagged a kidney number, maybe there was blood in the urine, maybe the pain in one side of the back would not settle.
This explainer walks through what the pictures can and cannot tell, what the common findings mean in plain language, and what typically happens once the report lands on your clinician’s desk.
Why would a doctor do a renal ultrasound?
Clinicians reach for ultrasound first when they want a quick, safe look at the kidneys’ structure. There is no radiation and no injected dye, which is why it is often the opening move rather than a CT scan.
The triggers are usually one of a handful of situations. A routine blood test may show a raised creatinine or a lower estimated glomerular filtration rate (eGFR, a calculation of how well the kidneys filter waste), and the doctor wants to know whether the kidneys look shrunken, swollen, or normal. Blood in the urine, whether seen by eye or picked up on a dipstick, prompts a search for stones, cysts, or growths. Recurrent urinary infections, especially in children or in adults whose infections keep coming back, raise the question of a structural reason such as a blockage or a kidney that has not developed typically.
Pain is another common reason. A steady or colicky ache in the flank, the area between the lower ribs and the hip, can come from a stone stuck in the ureter (the tube from kidney to bladder), and ultrasound can show the swelling behind it. High blood pressure that is hard to control, a family history of polycystic kidney disease, difficulty emptying the bladder, or a planned kidney procedure are further reasons the test gets ordered.
Ultrasound is also the follow-up tool of choice. Once a simple cyst or a small stone is known, repeat scans over time can track whether anything has changed without adding radiation exposure. The National Institute of Diabetes and Digestive and Kidney Diseases describes ultrasound as a first-line urinary tract imaging test for exactly these reasons: it is painless, widely available, and safe in pregnancy and childhood.
None of these reasons means something is wrong. A referral is a question, not a verdict.
What does a renal ultrasound show, and what can it not see?
Think of the kidney as a bean-shaped organ roughly the size of a fist, with an outer layer called the cortex, an inner zone of pyramids called the medulla, and a central collecting area, the renal pelvis, where urine gathers before draining down the ureter. Ultrasound displays all of these as different shades of gray.

The scan measures each kidney’s length and the thickness of the cortex. It shows whether the two kidneys are similar in size, whether the outline is smooth or scarred, and whether the central drainage system is collapsed as it should be or stretched with urine. Fluid appears black; dense material such as stone appears bright white with a dark shadow behind it. Solid tissue that does not belong, such as a mass, shows up as a lump with a texture different from the surrounding kidney.
Doppler ultrasound, a mode that maps moving blood, can add information about blood flow into and out of the kidney, which matters in some causes of high blood pressure and after a kidney transplant.
What it cannot do is measure function. A kidney can look perfectly normal on ultrasound while filtering poorly, and a kidney can look scarred while still doing an adequate job. Function comes from blood tests and urine tests, not from pictures. Ultrasound also struggles with very small stones, stones hidden in the middle of the ureter behind bowel gas, and subtle differences inside solid masses. When those questions arise, the radiologist (the doctor who interprets medical images) will usually suggest CT or MRI as the next step.
So the honest answer to what a renal ultrasound shows is: anatomy, blockage, fluid, stone, and shape. Not chemistry.
How the scan actually works: sound, gel, and a full bladder
The transducer, the handheld wand the sonographer presses to your skin, sends out pulses of sound far above the range of human hearing. Those pulses bounce off tissue boundaries and return to the same wand, which times each echo and converts it into a dot of brightness on the screen. Thousands of dots a second become a moving picture. The gel is not medicine; it simply removes the air between wand and skin, because air scatters sound and ruins the image.
Preparation is usually light. Many departments ask you to drink water beforehand and arrive with a comfortably full bladder, since a fluid-filled bladder acts as a window for sound and lets the sonographer check how well it empties. Some ask you to avoid food for a few hours if the scan is combined with a look at the liver or gallbladder. Follow the instructions you were given rather than a general rule online, because departments differ.
During the scan you lie on your back, then on each side, sometimes on your front. You will be asked to take a deep breath and hold it so the kidneys drop below the ribs and stay still. The sonographer freezes images, measures, and labels. Silence during this part is normal and does not signal bad news; concentration looks the same whether the findings are boring or interesting.
The NHS notes that most ultrasound scans take between 15 and 45 minutes, and you can go home or back to work straight afterwards. There are no needles, no drugs, and no known harmful effects at diagnostic sound levels, which is why ultrasound is the standard imaging test during pregnancy.
The pictures then go to a radiologist, who writes the formal report your referring clinician will read with you.
Kidney stones on ultrasound: bright spots and their shadows
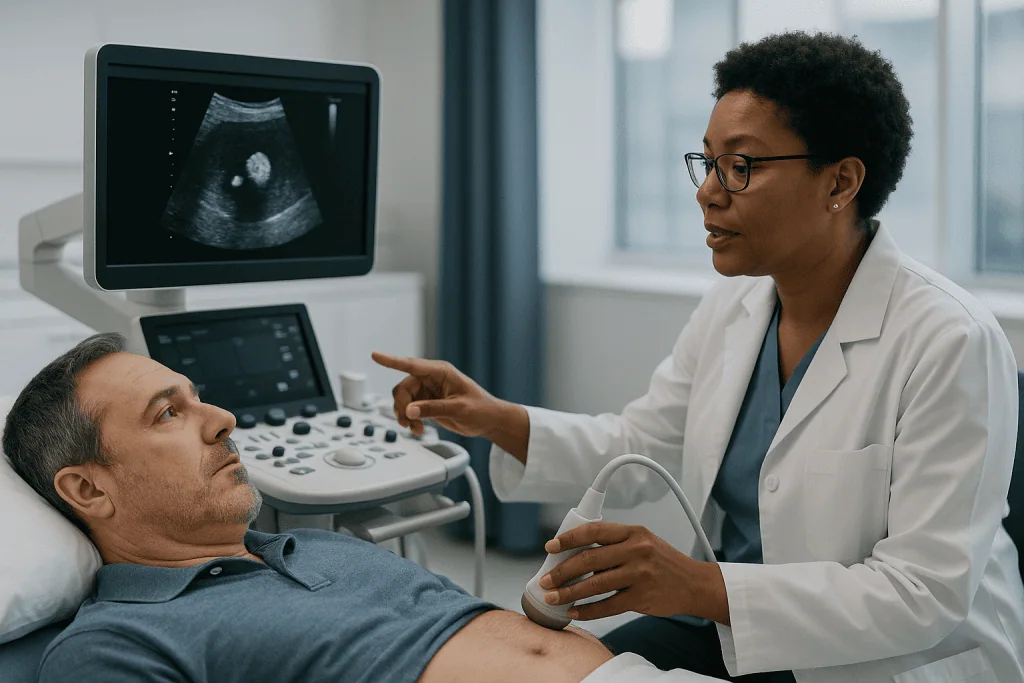
A kidney stone is a hard deposit of minerals and salts that crystallizes from urine. On the screen it looks like a small bright fleck with a dark stripe trailing behind it, the acoustic shadow, because sound cannot pass through stone. Sonographers hunt for that shadow deliberately; a bright spot without one may simply be a fold of tissue.
Stones are common. The National Institute of Diabetes and Digestive and Kidney Diseases estimates that about 11 percent of men and 6 percent of women in the United States have a kidney stone at some point in life. Many sit quietly in the kidney and are found by accident during a scan ordered for something else.
Ultrasound is good at spotting stones inside the kidney, particularly larger ones. It is less reliable for small stones and for stones that have already slipped into the ureter, where overlying bowel gas can hide them. In those cases the scan often finds the indirect clue instead: a swollen kidney upstream of the stone, or a jet of urine missing on the affected side when the bladder is examined with Doppler. When a stone is strongly suspected but not seen, a CT scan without contrast is the usual next test because it detects nearly all stone types regardless of size.
The report will typically state the stone’s size and location. Smaller stones frequently pass on their own with fluids and time, while larger ones or those causing blockage or infection may need a procedure. Which path applies is a decision for the urologist or referring clinician, weighing the stone’s size and position, your symptoms, kidney function, and any infection. The ultrasound supplies the map; it does not choose the route.
Kidney cysts: why 'simple' is the word you want to hear
A kidney cyst is a closed, fluid-filled sac that forms within or on the surface of the kidney. On ultrasound a simple cyst is one of the most recognizable images in medicine: a perfectly round, jet-black circle with a thin, smooth wall and a bright band of tissue directly behind it, because sound travels easily through clear fluid. No internal echoes, no thick walls, no solid parts.
Simple cysts are extraordinarily common and become more so with age. The National Institute of Diabetes and Digestive and Kidney Diseases notes that simple kidney cysts are found in a large share of adults by midlife and rarely cause symptoms or harm kidney function. Most are discovered incidentally and need no treatment. A report that describes a single simple cyst is, for most people, a footnote rather than a diagnosis.
The picture shifts when a cyst is complex. That word means the sac shows something a simple cyst should not: a thick or irregular wall, internal partitions, calcium in the wall, or a solid nodule. Complex cysts are not necessarily cancer; bleeding into a simple cyst or an old infection can produce the same look. But because ultrasound cannot always tell those apart, the radiologist will usually recommend CT or MRI with contrast to characterize it, or a repeat ultrasound after an interval to see whether it changes.
Many cysts in both kidneys, especially with enlarged kidneys and a family history, raise the question of polycystic kidney disease, an inherited condition in which cysts gradually replace working tissue. Here ultrasound is a screening tool, and the treating team may add genetic counseling and blood pressure and kidney-function monitoring.
Reports often use words like ‘benign-appearing’ or ‘no follow-up required.’ Ask your clinician to translate whichever phrase applies to yours.
Hydronephrosis on ultrasound: what a blocked kidney looks like
Hydronephrosis is the medical term for a kidney swollen with urine that cannot drain properly. Normally the renal pelvis and the branching calyces (the cup-shaped channels that collect urine from the kidney tissue) are collapsed and barely visible. When urine backs up, those spaces fill and appear as black, fluid-filled pockets fanning out from the center of the kidney, like the fingers of a dark glove.
Radiologists grade the swelling as mild, moderate, or severe based on how far it stretches and whether the kidney’s outer tissue is thinning. Mild dilation can be normal in a very full bladder or during pregnancy, when the growing uterus presses on the ureters. That is why the sonographer may ask you to empty your bladder and rescan.
The causes fall into two groups. Something blocking the pipe: a stone in the ureter, a narrowing at the junction where kidney meets ureter, an enlarged prostate compressing the bladder outlet, a tumor, or scar tissue. Or urine flowing the wrong way: vesicoureteral reflux, common in young children, in which urine washes back up from the bladder toward the kidney.
Ultrasound shows the swelling clearly but often cannot show the exact cause, particularly when the obstruction sits in the middle of the ureter. The report may therefore say ‘hydronephrosis, level of obstruction not visualized’ and suggest CT. One-sided hydronephrosis with a stone-type pain usually points to a stone; two-sided hydronephrosis more often points to a problem at the bladder or below.
Blockage matters because sustained pressure can damage the kidney and because a blocked, infected kidney is an emergency. This is one of the findings that can turn a routine scan into a same-day phone call, and it is one of the main reasons the test gets ordered urgently for flank pain with fever.
Does kidney disease show up on a renal ultrasound?
Partly, and this is where expectations most often mismatch reality. Chronic kidney disease (CKD) is defined by function, measured through blood tests for eGFR and urine tests for protein, not by how the kidneys look. The NHS notes that early CKD usually causes no symptoms and is detected through these tests. A person can have significant CKD with kidneys that look unremarkable on ultrasound, especially in the early stages or in diabetes, where the kidneys may even appear normal-sized or slightly large.
What ultrasound adds is context. Long-standing kidney disease tends to leave visible footprints: kidneys that are smaller than expected, an outer cortex that has thinned, tissue that appears brighter than the neighboring liver (radiologists call this increased echogenicity, meaning the tissue reflects more sound than it should), and a blurring of the normal contrast between cortex and medulla. Those changes suggest scarring that has been present for a long time and is unlikely to reverse.
Ultrasound is also used to rule out treatable structural causes of a falling eGFR. Hydronephrosis, for example, can lower kidney function and may improve once the blockage is relieved. Polycystic kidneys, a single kidney, or a kidney that has shrunk after an old infection all change how the treating team interprets the blood numbers.
The scan can flag problems with the arteries feeding the kidneys, which is one uncommon cause of hard-to-control blood pressure, though this often requires dedicated Doppler imaging or CT angiography to confirm.
In short, ultrasound does not diagnose or stage CKD on its own. It helps answer why the numbers might be off and whether anything mechanical can be fixed. The diagnosis, the stage, and the plan come from the whole picture assembled by your clinician.
Other common abnormal kidney ultrasound findings, explained
Beyond stones, cysts, and blockage, a handful of findings appear often enough to deserve plain-language translation.
Solid mass or lesion. A lump that is not fluid-filled. Some are benign tumors such as angiomyolipomas, which contain fat and have a characteristic bright appearance; others need further work-up because ultrasound cannot reliably distinguish benign from malignant solid growths. Expect a recommendation for CT or MRI with contrast. A recommendation for more imaging is standard practice, not a diagnosis of cancer.
Cortical scarring. A dent or notch in the kidney’s outline, often from an old infection or from childhood reflux. It signals past damage rather than current disease, though the team may check blood pressure and urine protein.
Duplex kidney. A kidney with two separate collecting systems and sometimes two ureters. It is a variation present from birth and usually harmless, though it can predispose to infection or reflux.
Horseshoe kidney, pelvic kidney, or single kidney. The kidneys may be fused at the bottom, sit lower in the pelvis than usual, or one may be absent. These are developmental variations that many people carry unknowingly for life.
Medullary nephrocalcinosis. Calcium deposits scattered through the inner pyramids, appearing as clusters of bright spots. It points to a metabolic cause the clinician may want to investigate with blood and urine chemistry.
Bladder findings. Because the bladder is usually included, the report may mention wall thickening, a stone in the bladder, incomplete emptying (measured as post-void residual), or, in men, an enlarged prostate pressing upward.
Perinephric fluid. Fluid around the kidney, which can follow injury, infection, or a leak of urine.
An ‘abnormal’ report is a list of observations. Which ones matter, and how much, depends on your symptoms, your blood work, and your history, all of which your clinician holds and the radiologist does not.
Who is usually offered a renal ultrasound, and who is asked to wait
Ultrasound is offered broadly because the barriers are so low. Pregnant women with flank pain or urinary infection receive it as the imaging of choice, since it avoids radiation entirely. Infants and children with a first febrile urinary tract infection, unexplained swelling, or an antenatal scan that showed dilated kidneys are routinely scanned. Adults with a new drop in eGFR, blood in the urine, suspected stones, recurrent infections, resistant hypertension, or a family history of polycystic kidney disease are typical referrals. People with a kidney transplant have regular ultrasounds to monitor blood flow and drainage.
Some people are asked to wait, and it helps to understand why. Someone with classic stone pain, no fever, and stable blood tests may be sent for a CT scan first, because CT finds ureteric stones that ultrasound often misses, and going straight to the definitive test avoids two appointments. A person with a very small simple cyst already documented may be told no follow-up is needed at all, because repeat imaging would not change anything.
Timing also matters for accuracy. A scan performed while the bladder is empty can underestimate bladder wall thickness and residual volume; a scan during an acute infection can show temporary swelling that resolves on its own. In those cases the team may deliberately schedule the ultrasound for a few weeks later so the picture reflects your baseline rather than a passing state.
Body habitus is an honest limitation too. Sound waves lose strength passing through thicker tissue, and in some people the kidneys, particularly the left one tucked under the ribs and behind bowel, are hard to see clearly. The report may read ‘limited visualization’ and suggest CT or MRI. That reflects physics, not effort or fault.
Who gets the test, and when, is a clinical judgment about which question needs answering first.
Renal ultrasound vs CT vs MRI: how the kidney tests compare
Patients often ask why they were sent for one test rather than another, or why a second scan is now being suggested. The tests are complementary rather than competing; each answers a different kind of question with a different trade-off. The table below summarizes the main distinctions as described by the National Institute of Diabetes and Digestive and Kidney Diseases and the NHS.
| Feature | Renal ultrasound | CT scan | MRI |
|---|---|---|---|
| How it makes images | High-frequency sound echoes | X-rays from many angles, reconstructed by computer | Strong magnet and radio waves |
| Radiation | None | Yes | None |
| Contrast dye | Not needed | Often used, except for stone protocols | Often used; a different agent from CT |
| Best at | Kidney size, cysts, hydronephrosis, larger stones, bladder emptying, blood flow with Doppler | Small and ureteric stones, characterizing solid masses, injuries | Characterizing complex cysts and masses, avoiding radiation and iodinated contrast |
| Main limits | Small stones, mid-ureter, operator and body-habitus dependent | Radiation; iodine contrast needs caution with low kidney function | Longer scan, noise, not suitable with some implants |
| Typical role | First-line and follow-up | Second-line or first for suspected stone | Problem-solving |
A recommendation for CT or MRI after ultrasound does not mean the ultrasound failed. It means the sound picture found something worth a sharper look or could not reach the area in question. Equally, the choice between CT and MRI depends on your kidney function, any allergies, whether you have metal implants, and what exactly needs clarifying. Those factors sit with your clinician and the radiologist, who together decide the next step.
Kidney ultrasound results explained: what the report's words mean
Radiology reports are written for the ordering clinician, in a shorthand that can read as ominous when it is not. A few phrases turn up repeatedly.
‘Unremarkable’ or ‘within normal limits.’ Good news, phrased flatly. Nothing abnormal was seen.
‘Normal size and echogenicity.’ The kidneys are the expected length and reflect sound the way healthy kidney tissue should.
‘Increased echogenicity’ or ‘echogenic kidneys.’ The tissue appears brighter than expected, a nonspecific sign often associated with long-standing kidney disease. On its own it is a pattern, not a diagnosis.
‘Preserved corticomedullary differentiation.’ The normal contrast between the outer and inner kidney is intact, which generally argues against advanced scarring.
‘Cortical thinning.’ The working outer layer is thinner than typical, suggesting chronic change.
‘No hydronephrosis.’ The drainage system is not swollen; no sign of blockage.
‘Echogenic focus with posterior acoustic shadowing.’ The classic description of a stone.
‘Anechoic, thin-walled, with posterior enhancement.’ The classic description of a simple cyst.
‘Incidental finding.’ Something noticed that was not the reason for the scan. Most incidental findings are benign.
‘Clinical correlation recommended.’ The radiologist is asking your clinician to interpret the image in light of your symptoms and tests, because pictures alone cannot settle it.
‘Limited study due to body habitus / bowel gas.’ Parts of the kidney could not be clearly seen, for physical reasons.
Two cautions. First, patient portals often release the report before your clinician has read it, so you may see these words without context. Second, radiologists describe everything they see, including trivia, because that is their job; the ordering clinician’s job is to decide what matters. Reading a report is not the same as receiving a result, and the conversation is where the meaning lives.
What happens after the report: the following days and weeks
Once the sonographer finishes, the images travel to a radiologist, who dictates a formal report. The NHS advises that although you may sometimes be told findings on the day, in most cases the report goes to the referring clinician and results are discussed with you a few days or weeks later, depending on urgency and how the appointment was arranged. Urgent findings, such as a blocked and infected kidney or a large mass, are typically phoned through the same day.
From there, the path branches. If the scan is normal and the original question was, say, a mildly reduced eGFR, your clinician may simply repeat blood and urine tests over time and address risk factors such as blood pressure and blood sugar, following CKD guidance. No further imaging may be needed.
If a simple cyst or a small, quiet stone was found, the common outcome is reassurance, sometimes with a repeat scan at an interval the team chooses. Many small stones are watched rather than treated, with advice on fluids and, where a stone is retrieved or passes, analysis of its type to guide prevention. Whether medicines are used to help a ureteric stone pass, or to lower the risk of new stones, is a prescribing decision that rests with your clinician.
A complex cyst or solid mass generally leads to CT or MRI within weeks, and possibly referral to a urologist. Hydronephrosis usually prompts a search for the cause, which may mean CT for a suspected stone, a bladder assessment for outflow problems, or a nuclear medicine scan to measure how each kidney drains.
Children with reflux or dilated kidneys may enter a monitoring pathway with repeat ultrasounds as they grow, since many childhood findings improve on their own.
Whatever the branch, the ultrasound is one input. The plan, its pace, and its priorities are set by the treating team with you.
What people often get wrong about kidney ultrasounds
‘A normal ultrasound means my kidneys are fine.’ A normal scan means the structure looks healthy. Function is measured by blood and urine tests, and early kidney disease frequently leaves no visible trace. Both pieces are needed.
‘The sonographer went quiet, so it must be bad.’ Sonographers concentrate, measure, and usually are not permitted to give results. Silence is protocol, not prognosis.
‘Any cyst is a tumor.’ Simple cysts are common, benign, and typically need no treatment. Only cysts with complex features warrant further imaging, and even most of those turn out not to be cancer.
‘Ultrasound catches every stone.’ It does not. Small stones and stones in the ureter are often invisible to sound, which is why CT remains the reference test when a stone is strongly suspected.
‘Being sent for a CT means the doctor thinks it is serious.’ More often it means the ultrasound raised a question it could not answer, or could not reach the area clearly. Further imaging is a routine step in the pathway.
‘Ultrasound uses radiation like an X-ray.’ It uses sound, not ionizing radiation, which is why it is the standard imaging in pregnancy and childhood.
‘An echogenic kidney is a diagnosis.’ Brightness is a nonspecific pattern seen in many chronic conditions and occasionally in normal kidneys. It is a clue that prompts questions, not an answer.
‘I can check my own kidney health from the report.’ Reports list observations without weighting them. Deciding which matter requires your history, examination, and laboratory results, which is the clinician’s role.
‘Drinking lots of water right before the scan will flush out a stone.’ Fluid helps the sonographer see the bladder; it does not dissolve or dislodge stones in the minutes before an appointment.
Correcting these ideas does not make findings less real. It makes the conversation afterwards more useful.
Questions to ask your care team about your kidney ultrasound
The appointment after a scan is short, and it is easy to leave with more uncertainty than you arrived with. A written list helps. These are the questions that tend to unlock the most useful answers.
- What was the specific question this ultrasound was ordered to answer, and did it answer it?
- Were both kidneys seen clearly, or was the view limited on either side?
- Are my kidneys a normal size and shape for my age and build?
- Was there any sign of blockage or swelling in the drainage system?
- If a stone was seen, where is it, how large is it, and is it likely to pass on its own or need a procedure?
- If a cyst was seen, is it simple or complex, and does it need any follow-up?
- Does anything on the scan help explain my blood or urine results?
- Do you recommend further imaging, and if so, why CT or MRI in my case?
- Is there anything on the report labeled incidental that we should track over time?
- How does this result change my plan, if at all?
- Should I repeat this ultrasound, and roughly when?
- Who will contact me with any results from further tests, and how?
Two further questions matter for people already living with kidney disease. First, does the appearance suggest the changes are long-standing, and does that alter how we monitor things? Second, is there anything mechanical, such as a blockage or a bladder that is not emptying, that could be improved and might help my kidney function?
Bring a copy of the report if you have one from a patient portal, and do not hesitate to ask for a phrase to be translated. Radiology language is precise but not written for patients; asking what a term means is a normal and welcome part of the consultation. If your clinician recommends watchful waiting, ask what specifically would prompt them to act sooner, so you know what to look for and when to call.
When to call your doctor: red-flag signs after a kidney ultrasound
The ultrasound itself carries no aftercare and no known side effects, so nothing about the scan should make you feel unwell. The signs that warrant a prompt call relate to the conditions the scan may have found or to changes in how you feel while awaiting results or follow-up.
Seek urgent medical care, the same day or through emergency services, if you have severe flank or abdominal pain together with fever, chills, or shaking, particularly if you know or suspect you have a stone or hydronephrosis. A blocked kidney that becomes infected is an emergency because infection trapped under pressure can spread rapidly into the bloodstream. The same urgency applies if you cannot pass urine at all, if you are vomiting and unable to keep fluids down, or if pain is so severe it cannot be controlled at home.
Contact your clinician promptly, within a day or two, if you see visible blood in your urine, notice new swelling of the ankles, legs, or around the eyes, produce far less urine than usual, or develop a burning, frequent, or urgent need to urinate alongside back pain. New or sharply rising blood pressure readings at home also deserve a call, as does any new shortness of breath, which can accompany fluid retention when kidney function drops.
If you were told to expect a call about results and it has not arrived within the timeframe given, chase it. Reports occasionally stall between departments, and a polite check is never a nuisance.
For people who received a finding that requires further imaging, a new symptom in the meantime is a reason to bring the follow-up forward rather than wait. Your treating team decides the pace, but they can only adjust it if they know what has changed. When in doubt about whether something counts, call; the people who ordered the scan would rather hear from you than not.
Frequently asked questions
Why would a doctor do a renal ultrasound?
Doctors order a renal ultrasound to look at the kidneys’ structure quickly and safely, usually after a blood test shows reduced kidney function, when there is blood in the urine, flank pain, recurrent urinary infections, hard-to-control blood pressure, or a family history of polycystic kidney disease. It is also used to follow known cysts or stones over time and to monitor transplanted kidneys, because it involves no radiation or injected dye.
What are the three warning signs of kidney disease?
There is no official trio, and the honest answer is that early chronic kidney disease usually has no symptoms at all; the NHS notes it is most often detected through routine blood and urine tests. Features that may appear as it progresses include swelling of the ankles or around the eyes, persistent tiredness, and changes in how often or how much you urinate. Any of these warrants a conversation with your clinician rather than self-diagnosis.
What are some common abnormal findings on a kidney ultrasound?
The most frequent abnormal kidney ultrasound findings are simple cysts, kidney stones, hydronephrosis (a kidney swollen from blocked drainage), and changes suggesting long-standing disease such as small, bright, or thin-walled kidneys. Less often the scan shows a solid mass, cortical scarring from past infection, developmental variations such as a duplex or horseshoe kidney, calcium deposits, or bladder findings like incomplete emptying. Most incidental findings turn out to be benign.
Does kidney disease show up on ultrasound?
Sometimes, but not reliably. Chronic kidney disease is defined by function measured through blood and urine tests, and kidneys can look normal on ultrasound in early disease. Long-standing damage tends to leave visible signs such as reduced size, increased brightness (echogenicity), and a thinned outer cortex. Ultrasound is mainly used to look for structural, treatable causes such as blockage or polycystic kidneys, not to diagnose or stage the disease itself.
What does hydronephrosis on ultrasound mean?
Hydronephrosis means the kidney’s drainage system is stretched with urine because flow is obstructed or urine is refluxing backward. On ultrasound it appears as black, fluid-filled pockets fanning out from the center of the kidney and is graded mild, moderate, or severe. Causes include stones, narrowings, an enlarged prostate, or reflux in children. Mild dilation can be normal with a very full bladder or in pregnancy, so the sonographer may rescan after you empty your bladder.
Can a renal ultrasound detect kidney stones?
Yes, particularly stones inside the kidney, which appear as bright spots with a dark shadow behind them. Ultrasound is less reliable for very small stones and for stones that have moved into the ureter, where bowel gas can hide them. In those cases the scan may show only the indirect sign of swelling upstream. When a stone is strongly suspected but not seen, a CT scan without contrast is usually the next test because it detects nearly all stones.
Do I need to fast or drink water before a kidney ultrasound?
Many departments ask you to drink water beforehand and arrive with a comfortably full bladder, because fluid improves the view and lets the sonographer check how well the bladder empties. Fasting is not usually required for the kidneys alone, though it may be requested if the liver or gallbladder is being examined at the same time. Follow the specific instructions from your department, as preparation varies between services.
How long does a renal ultrasound take and when do I get results?
The NHS notes that most ultrasound scans take between 15 and 45 minutes, and you can leave straight afterward. The images are read by a radiologist who writes a report for the referring clinician. You may occasionally be told findings on the day, but in most cases results are discussed with you a few days to weeks later depending on urgency. Urgent findings, such as a blocked and infected kidney, are usually phoned through the same day.
What does it mean if my kidney ultrasound results say echogenic kidneys?
Echogenic means the kidney tissue reflects more sound than expected and looks brighter than the neighboring liver on the screen. It is a nonspecific pattern often associated with long-standing kidney disease and scarring, but it can also appear in other conditions and occasionally in healthy kidneys. On its own it is not a diagnosis. Your clinician will interpret it alongside your blood and urine tests, blood pressure, and history to decide whether it changes anything.
Is a kidney ultrasound safe during pregnancy and for children?
Yes. Ultrasound uses sound waves rather than ionizing radiation and requires no injected dye, which is why it is the standard imaging test in pregnancy and the first-choice kidney imaging for infants and children. It is routinely used for pregnant women with flank pain or urinary infection, and for children after a first febrile urinary infection or when an antenatal scan showed dilated kidneys. No harmful effects at diagnostic levels have been established.
References
- Urinary Tract Imaging – National Institute of Diabetes and Digestive and Kidney Diseases (NIH)
- Ultrasound scan – NHS
- Kidney Stones: Definition & Facts – National Institute of Diabetes and Digestive and Kidney Diseases (NIH)
- Simple Kidney Cysts – National Institute of Diabetes and Digestive and Kidney Diseases (NIH)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Is It a Bladder Infection or a Kidney Infection? How Urinary Infections Are Told Apart
A bladder infection (cystitis) stays in the lower urinary tract and usually causes burning, urgency and lower-belly discomfort without fever. A kidney infection (pyelonephritis)…

Robotic vs Laparoscopic Urology for Kidney Surgery: How Surgeons Choose Between the Two
Robotic and laparoscopic kidney surgery are both keyhole techniques that use small incisions rather than one large cut. In laparoscopic surgery the surgeon holds…

What Is Monitored During Fluid Management: Weight, Urine Output, Pressure and Electrolytes
Fluid management is tracked with four linked measurements: daily body weight (a one-kilogram change usually reflects about one liter of fluid), urine output recorded…

Recovery After Minimally Invasive Urology: Same-Day Discharge, Catheters and Lifting Limits
Recovery after minimally invasive urology is usually measured in days to a few weeks, not months. Many scope procedures allow same-day discharge, catheters and…

Overactive Bladder Medicines: Dry Mouth, Constipation and the Side Effects to Report
Overactive bladder medicines fall into two main groups, and their side effects follow their mechanism. Anticholinergic drugs such as oxybutynin commonly cause dry mouth,…

Laser Lithotripsy Recovery Day by Day: Fragments, Stent Discomfort and the Follow-Up Scan
Laser lithotripsy recovery time is usually short in the sense that most people go home the same day and return to light routines within…