

What Age Is Right for Otoplasty? Ear Growth, Timing and Readiness in Children and Adults

Key Takeaways
- The outer ear reaches most of its adult size by around age five, which is why otoplasty is generally not offered before then.
- Non-surgical ear molding only works in the first weeks to months of life, while the cartilage is still soft from maternal hormones.
- There is no upper age limit for otoplasty in healthy adults; stiffer cartilage changes the technique, not the eligibility.
- Otoplasty usually takes one to two hours, is done as a day case, and children have a general anesthetic.
- Typical recovery includes about a week off school or work, four to six weeks away from swimming, and around twelve weeks away from contact sport.
- Ear tubes treat glue ear behind the eardrum and have nothing to do with otoplasty, which reshapes the outer ear only.
Otoplasty, surgery to reshape or set back prominent ears, is usually considered from about age five, when the outer ear has reached most of its adult size and cartilage is firm enough to hold a new shape. There is no upper age limit for healthy adults. Readiness, motivation and a surgeon's assessment matter more than a birthday, and newborn ear molding is a separate, non-surgical option in the first weeks of life.
The question usually arrives quietly. A parent watches a child tuck long hair over the ears before school photos, or hears a whispered nickname in the playground, and wonders whether to do something now or let time decide. A 34-year-old, tired of angling every selfie the same way, wonders whether she has somehow missed the moment.
Both are asking the same thing: what is the right otoplasty age? The honest answer is less about a number on a birthday cake and more about three things that happen at different speeds. Ear cartilage grows and stiffens on its own schedule. Children develop the ability to understand and want an operation on theirs. And adults, it turns out, are on no schedule at all.
This explainer walks through what the evidence actually says about ear growth, why the age of five appears in so many leaflets, what changes for teenagers and adults, and how to tell readiness from pressure.
What otoplasty is, and what it is not
Otoplasty is surgery that changes the shape, position or size of the outer ear. Most operations are done for ears that stick out more than usual, sometimes called prominent or protruding ears, and the aim is to bring them closer to the head or to recreate a fold that never fully formed. You may also hear it called ear correction surgery or ear pinning. Those are the same thing described in plainer words.
It helps to be clear about what the operation does not touch. Otoplasty works on the pinna, the visible cartilage-and-skin part of the ear, and does not involve the ear canal, the eardrum or the middle ear. Hearing is not the target and, in the ordinary course of things, is not changed by it. That distinction matters because prominent ears are a variation in shape, not a disease. A child with ears that stand out hears as well as any other child, and the reasons families consider surgery are about appearance, self-consciousness and how the child feels, not about function.
Prominent ears are common and usually run in families. The two anatomical features behind most cases are an underdeveloped antihelical fold, the curved ridge that gives the ear its characteristic C-shape, and an oversized conchal bowl, the cup-shaped hollow just outside the ear canal, which pushes the whole ear outward. Surgeons assess which of these is responsible because the technique is chosen to match, according to NHS and Mayo Clinic descriptions of the procedure.
Knowing this framing changes how the age question should be asked. Since the operation is elective and cosmetic, timing is not about urgency. It is about when the ear has finished most of its growth, when the person can take part in the decision, and when the recovery fits around school, work or sport without risk to the result.
How ear growth sets the otoplasty age window
Ears grow fast and then slow to a crawl. By the time a child starts school, the outer ear has reached most of its adult size; Mayo Clinic notes that otoplasty is usually considered once the ears have reached their full size, generally after age five. Width finishes first, length continues to creep for a few more years, and in later adulthood ears lengthen slightly as cartilage and skin lose elasticity. A pair of ears set back at six will, in other words, still be recognizably the same pair at sixty.

Cartilage stiffness follows a related curve. In a newborn, ear cartilage is soft and pliable, partly because of circulating maternal hormones in the first weeks of life. That softness is the reason non-surgical molding works in young infants and stops working a few months later, a point the NHS makes in its guidance on ear splinting for babies. By early childhood the cartilage is firm enough to hold stitches and keep a new shape, but not yet so rigid that it resists reshaping. Surgeons value that middle ground.
Operating before growth has largely finished carries a theoretical worry: a set-back ear might grow differently from its neighbor, or the correction might loosen as the framework enlarges. Operating after growth has finished removes that variable. Most surgical guidance therefore describes a starting point of around five years, not because something magical happens at that age, but because it is the point where the growth curve flattens enough for the result to be predictable.
Nothing about this window closes at the other end. Cartilage becomes stiffer and slightly more brittle with age, which changes how a surgeon handles it, but it does not stop being operable. The growth argument sets a floor for the otoplasty age. It does not set a ceiling.
Why age five comes up so often
Read three otoplasty leaflets and you will meet the number five three times. Mayo Clinic frames otoplasty as an option once the ears have reached full size, usually after age five. The NHS says ear correction surgery is generally not done before that age because the ears are still growing. The consistency is not coincidence, but it is worth understanding what the number does and does not stand for.
First, it marks the growth plateau described above. Second, it lines up with the start of formal schooling in many countries, which is when children begin comparing themselves to classmates and when teasing about appearance tends to start. Third, it is roughly the earliest age at which a child can be told what will happen, ask questions and give a form of agreement, even though the legal consent comes from parents.
What the number does not mean is that five is ideal for every child, or that waiting until seven or ten has been shown to produce a worse result. There is no strong evidence that operating at five rather than eight changes the cosmetic outcome. Surgical texts describe the years from about five to early adolescence as a broad, reasonable window rather than a target.
Nor does the number mean that a child who is content at five should be operated on to pre-empt future distress. Otoplasty is elective. Both Mayo Clinic and the NHS describe it as a decision made with the child, once the child is old enough to express a view. A quiet, unbothered six-year-old is not a candidate simply because a chart says the cartilage is ready.
So the honest reading of “age five” is this: it is the point after which the growth objection falls away and the conversation can genuinely begin. Whether that conversation ends in surgery, and when, depends on the child in front of the surgeon.
Is otoplasty safe for a 5-year-old child?
Parents ask this in two parts, even if they say it in one sentence. Is the operation itself safe, and is a general anesthetic safe for a child this young? Both deserve a plain answer.
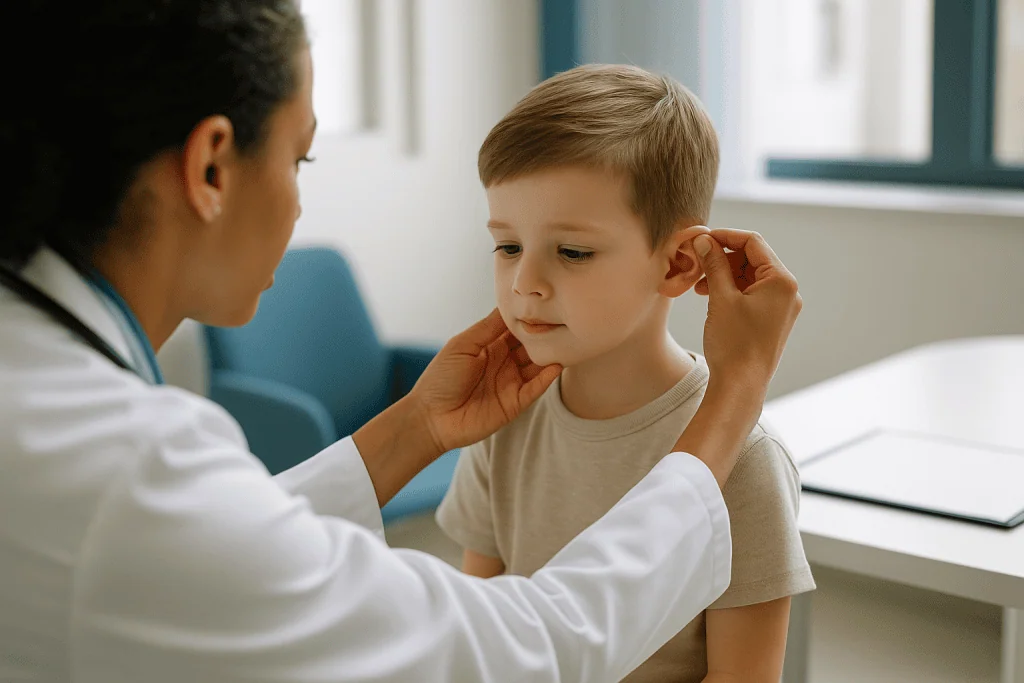
Otoplasty is a surface operation. It does not enter a body cavity, the incision is usually hidden behind the ear, and the tissues involved are skin and cartilage. The complications that can occur, described in the risk section further on, are mostly local: bleeding, infection, a stitch working its way to the surface, or a result that is uneven or that partly relapses. Serious harm is uncommon in the guidance published by the NHS and Mayo Clinic, though neither source, nor this article, can promise a particular outcome for any individual child.
General anesthesia is standard for children having otoplasty, since a young child cannot be expected to lie still for one to two hours under local anesthetic. Pediatric anesthesia is a routine, specialist-led part of children’s hospital care, with monitoring and drug choices adapted to small bodies. The anesthesiologist will ask about previous anesthetics, allergies, breathing problems, loose teeth and recent colds, and may postpone surgery if a child has a chest infection, because that raises airway risk. Asking about whether the team regularly anesthetizes children of this age is a fair and welcome question.
The remaining safety question is psychological. A five-year-old cannot consent in the legal sense, but can be prepared, involved and listened to. Children who have been told in age-appropriate language what will happen, who have seen the headband they will wear and who have some sense of why the operation is being done tend to cope better with the strange sensations afterward.
Safety, then, is not a single yes or no. It is a combination of a low-risk operation, a well-established anesthetic pathway, and a child who is emotionally ready. The treating team weighs all three before offering a date.
Who otoplasty is usually for, and who is usually asked to wait
Surgeons generally consider otoplasty for children and adults whose ears protrude noticeably or lack a defined fold, who are bothered by it, who are in good general health and, in the case of children, who have reached the age where the ear has largely finished growing. The person, or the child with parental support, should want the change for themselves rather than to satisfy someone else.
Several groups are usually asked to wait or are steered toward a different path:
- Children under about five, because the ear is still growing and the result is less predictable, as both the NHS and Mayo Clinic note.
- Children who are indifferent to their ears. Otoplasty is not a preventive operation, and a child who has not raised the subject is not a candidate on a parent’s worry alone.
- Anyone with a current ear infection or skin infection around the ear, until it has cleared.
- People with a known tendency to keloid or thick scarring, who need a frank discussion about the higher chance of a raised scar behind the ear.
- Adults whose expectations do not match what surgery can achieve, for example those hoping the operation will change their face or resolve unrelated distress.
- Anyone with a bleeding disorder or on medicines that affect clotting, who needs the prescribing clinician involved in planning before any decision is made about those medicines.
Teenagers occupy a middle ground. Cartilage is fully grown, motivation is usually strong and self-generated, and recovery fits into a school holiday. The main caution is making sure the wish is stable rather than a reaction to a single bad week.
None of these are absolute bars set by a checklist. They are the reasons a surgeon might suggest a later date, a second consultation or a conversation with a family doctor first. The decision belongs to the treating team together with the patient and family.
Ear molding for babies: the no-surgery window
There is one part of the otoplasty age story that runs in reverse. For a few weeks after birth, ear cartilage is soft enough to be reshaped without surgery, using small splints or molds taped to the ear. The NHS describes ear splinting as an option for babies, and notes that it works best when started early because the cartilage hardens as the child grows.
The mechanism is straightforward. Maternal estrogen circulating in the newborn keeps cartilage pliable, and that effect fades over the first months. A splint held against the rim and fold of the ear during this period encourages the cartilage to set in a more typical shape. Once the cartilage has firmed up, splinting no longer changes it, and surgery becomes the only route to a different shape later in life.
Practical details vary between services, but the pattern is similar: a soft splint or mold is fitted, checked at intervals and worn continuously for a few weeks, with the exact duration decided by the treating team. Parents are shown how to care for the skin beneath it and what to watch for, chiefly redness, irritation or a mold that has slipped.
Molding is not a guaranteed alternative to otoplasty, and the evidence base is smaller and less standardized than for surgery. Some ear shapes respond well; others, particularly a deep conchal bowl, respond less. A baby whose ears are noticed only at a few months of age has usually passed the window. For that child, the answer is not urgency but patience: nothing is lost by waiting until the surgical window opens at school age.
For expectant or new parents with a strong family history of prominent ears, the useful takeaway is simply to mention it at the newborn checks. Raising the question early keeps the non-surgical option open. Raising it later is not a failure; it just moves the conversation to a different chapter.
What actually happens during otoplasty
Most otoplasty operations take between one and two hours, according to the NHS, and are done as a day case. Children have a general anesthetic. Adults may have a general anesthetic or a local anesthetic with sedation, depending on the surgeon’s practice and the patient’s preference.
The surgeon makes an incision on the back of the ear, in the crease where the ear meets the head, so the scar sits out of sight. What happens next depends on the anatomy identified at consultation. If the antihelical fold is missing or weak, the surgeon may score the cartilage to weaken it, place permanent stitches to bend it into a fold, or both. If the conchal bowl is too deep and pushing the ear outward, a sliver of cartilage may be removed or the bowl may be stitched back toward the bone behind the ear. Often a small ellipse of skin is removed from the back of the ear to take up the slack. The incision is then closed with stitches, some of which may dissolve.
Both ears are usually treated in the same session even when one seems more prominent, because setting back one ear on its own can make the other look more noticeable, and because perfect symmetry is easier to approach when the surgeon works on both.
At the end of the operation a soft dressing or a bandage is placed around the head to protect the ears and hold them in their new position. After the first check, this is usually swapped for a headband, often a soft sports-style band, worn especially at night to stop the ears from folding forward during sleep.
There is no single “right” technique. Cartilage-sparing methods that rely on stitches and cartilage-cutting methods that reshape it each have supporters, and the NHS notes that the approach is tailored to the individual ear. What a patient should expect is that the surgeon can explain which method is planned and why it suits their anatomy.
Otoplasty for adults and teenagers: is there an upper age limit?
Adults sometimes arrive at consultation apologizing, as if they have shown up late. They have not. Otoplasty has no upper age limit for people in good general health, and many patients have the operation in their twenties, thirties or later, often after decades of arranging hairstyles around their ears. The Mayo Clinic describes the procedure as suitable for people of any age once the ears have finished growing.
What changes with age is texture. Adult cartilage is stiffer and slightly more brittle than a child’s, so surgeons may lean more on cartilage scoring or removal than on stitches alone, and the ear may feel firmer for longer afterward. Adult skin behind the ear is thinner and heals a little more slowly, and adults are more likely to have conditions such as high blood pressure or to take medicines that affect bleeding, all of which the team asks about beforehand.
The table below summarizes how timing considerations shift across life stages, drawing on NHS and Mayo Clinic guidance.
| Life stage | Cartilage | Usual approach | Main timing consideration |
|---|---|---|---|
| Newborn to a few months | Soft, pliable | Non-surgical molding or splinting | Window closes as cartilage firms in the first months |
| Under about 5 years | Firming, ear still growing | Usually asked to wait | Ear has not reached most of adult size |
| About 5 to 12 years | Firm, growth largely complete | Otoplasty under general anesthetic | Child’s own wish and understanding; school timing |
| Teenagers | Fully grown | Otoplasty, general or local with sedation | Stable motivation; fitting recovery around exams and sport |
| Adults | Stiffer, less elastic | Otoplasty, often local with sedation | General health, medicines affecting bleeding, scar tendency |
Teenagers deserve one specific note. Their wish is usually the most self-directed of any group, but surgeons often want to hear it expressed consistently over more than one visit before booking, because appearance concerns in adolescence can be intense and short-lived in equal measure.
Otoplasty recovery time: what the first days and weeks usually look like
Recovery from otoplasty is more about protecting the ears than about pain, though the first day or two can be uncomfortable. Ears feel tight, sore and sometimes numb, and the head bandage can be warm and itchy. Any medicine for discomfort, in children or adults, is chosen and directed by the treating team; this article does not give dosing.
Typical milestones, as described by the NHS, run roughly as follows:
- The head bandage stays on for the first several days and is removed or changed at a clinic check.
- A headband is then worn, mainly at night, for several weeks to stop the ears from being bent forward during sleep.
- Children usually need about a week off school; adults can often return to desk work in a similar time frame.
- Swimming is generally avoided for about four to six weeks.
- Contact sports and anything that could knock the ears are avoided for around twelve weeks.
These are ranges, not promises, and each surgeon adjusts them to the technique used and how the ears look at review. Bruising and swelling settle over the first two to three weeks, and the final shape becomes clear as swelling fades over the following months. Numbness around the ear is common and usually improves gradually, though a patch of altered sensation can persist.
A few practical points make the weeks easier. Sleeping on the back with the head slightly raised reduces throbbing. Loose-fitting tops that do not need to be pulled over the head protect the bandage. Hair can usually be washed once the surgeon says so, taking care to keep the incisions dry until they have closed. Children may need a note for school excusing them from physical education for the agreed period, and a quiet word with teachers about avoiding playground bumps helps.
Stitches behind the ear either dissolve or are removed at a follow-up visit. The scar sits in the crease and typically fades to a fine line, although scars behave differently in different people, a point covered under risks.
Is otoplasty risky?
Every operation carries risk, and otoplasty is no exception, though the risks are largely local and most are manageable. Both Mayo Clinic and the NHS list the following, and a surgeon should go through each of them at consultation:
- Bleeding or a collection of blood under the skin, called a hematoma, which may need draining.
- Infection of the skin or, rarely, the cartilage, which needs prompt treatment because cartilage infection can distort the ear.
- Scarring behind the ear. Most scars fade, but some people form thick or raised scars, and those with a known keloid tendency face a higher chance.
- Asymmetry, where the two ears end up slightly different in position or shape.
- Over-correction, where the ears sit too close to the head, or under-correction, where they remain more prominent than hoped.
- Recurrence, where an ear gradually drifts back toward its original position, particularly if stitches loosen or the headband is not worn as advised.
- Stitches working their way to the skin surface, which can cause irritation and may need removal.
- Altered sensation or numbness around the ear, usually temporary.
- Risks related to anesthesia, which the anesthesiologist discusses separately.
A small proportion of people have a second operation to adjust the result, but this article does not quote a revision percentage because published figures vary widely with technique and follow-up length, and no single guideline sets a definitive number.
Risk is also shaped by choices within the patient’s control. Following headband instructions, avoiding sport for the advised period, not smoking, and keeping the wound clean all reduce the chance of relapse or infection. Choosing a surgeon who regularly performs otoplasty and who is transparent about complications is the other half of the equation. The aim of this section is not to alarm but to make the consent conversation a real one, in which the person knows what they are agreeing to.
What people often get wrong about otoplasty age
Myths gather around cosmetic surgery, and the age question attracts more than its share. A few corrections, grounded in what the guidance actually says:
“If you miss childhood, it is too late.” Wrong. There is no upper age limit for otoplasty in healthy adults, and Mayo Clinic describes the operation as suitable once the ears have finished growing, whenever that person comes forward. Adult cartilage is handled differently, but it is entirely operable.
“Earlier is always better for the child.” Not supported. Operating before about five is discouraged because the ear is still growing, and there is no evidence that surgery at five gives a better cosmetic result than surgery at eight or ten. A child who is not troubled by their ears does not benefit from a pre-emptive operation.
“Taping a toddler’s ears will flatten them.” Only in early infancy does molding change cartilage, according to NHS guidance on ear splinting. Taping an older child’s ears does nothing to the cartilage and can irritate the skin.
“Otoplasty affects hearing.” The operation involves the outer ear only. The canal, eardrum and middle ear are untouched. It is not a hearing operation, and it is unrelated to ear tubes.
“The result is permanent no matter what.” Results are usually long-lasting, but partial relapse can occur, especially if the headband is abandoned early or the ear is knocked during healing. Aftercare influences durability.
“A celebrity had it, so it must be simple.” Speculation about whether any named public figure, including actors frequently mentioned online, has had otoplasty is exactly that: speculation. Hairstyles, camera angles and lighting change how ears appear, and no responsible source can confirm a private medical history. Celebrity ears tell you nothing about whether surgery is right for you or your child.
The thread running through these corrections is the same: the operation is elective, the window is wide, and the person’s own wish sits at the center.
Ear tubes and otoplasty are different operations
Because both involve children, ears and an anesthetic, families sometimes blur otoplasty with ear tubes. A common search asks whether four is too late for ear tubes. The two procedures have nothing to do with each other, and untangling them saves confusion at consultation.
Ear tubes, also called grommets or ventilation tubes, are tiny tubes placed through the eardrum to drain fluid from the middle ear and let air in. They treat glue ear, the build-up of sticky fluid behind the eardrum that can muffle hearing and affect speech and learning. The NHS explains that glue ear is very common in young children and often clears on its own, with tubes considered when fluid persists for months and is affecting hearing. The operation takes minutes, and the tubes usually fall out by themselves as the eardrum heals over the following months.
Four is not too late for ear tubes. They are placed whenever persistent glue ear is affecting a child, which can be at two, four, six or older. Some children need them more than once. The decision rests with an ear, nose and throat team after hearing tests and a period of watchful waiting, not with a birthday.
Otoplasty, by contrast, is about the shape of the outer ear and has no effect on middle-ear fluid or hearing. A child could, in theory, need both at different points in childhood, and they would be planned by different teams for different reasons.
Why does this matter for the otoplasty age question? Because parents sometimes assume that a child who has had tubes cannot later have otoplasty, or that ears which stick out are a sign of ear disease. Neither is true. Prominent ears are a variation in shape. Glue ear is a medical condition. Sorting them into their proper boxes lets each conversation happen on its own terms.
Questions to ask your care team
A good consultation leaves the patient or parent understanding the plan, the alternatives and the uncertainties. These questions help draw that out. Write the answers down; the details fade quickly once you leave the room.
- Which feature of the ear is causing the prominence, the fold, the bowl or both, and how does that shape the technique you are planning?
- Do you regularly perform otoplasty on patients of this age, and, for a child, does the anesthesia team routinely care for children this young?
- Would you recommend operating now, or would you prefer to wait, and what would change your view?
- What kind of anesthetic do you suggest and why?
- What does the bandage and headband routine look like, and for how long is the headband worn at night?
- How long should school, work, swimming and contact sport be avoided in your practice?
- What are the specific risks for this patient, given their skin type, scar history and general health?
- How often do you see partial relapse or asymmetry, and how do you handle a result that needs adjusting?
- Are there any medicines or supplements currently taken that need to be discussed with the prescribing clinician before surgery?
- For a child: how do you involve children in the decision, and what happens if the child changes their mind close to the date?
- Who do we contact, and how, if something worries us at night or over a weekend?
- When are the follow-up visits, and what will you be checking at each one?
It is reasonable to ask for time to think after the first consultation. Elective surgery rarely needs to be booked on the day, and a team that is comfortable with a pause is usually a team that has nothing to hide. For children in particular, a second visit some weeks later gives everyone a chance to confirm that the wish is steady and the questions have been answered.
When to call your doctor
Most people recover from otoplasty with soreness, swelling and some bruising that improve steadily over the first two weeks. Some signs, however, need prompt attention because they can point to bleeding, infection or a problem with the cartilage, all of which are far easier to manage early. Contact the surgical team, or seek urgent care if you cannot reach them, if any of the following occur:
- Bleeding that soaks through the dressing or does not stop with gentle pressure.
- Pain that is getting worse rather than better after the first couple of days, or pain on one side that is much stronger than the other.
- Rapidly increasing swelling or a tense, bulging area under the skin, which can indicate a hematoma.
- Spreading redness, warmth, pus or an unpleasant smell from the wound or from under the dressing.
- A fever, or a child who becomes unusually drowsy, floppy, or refuses fluids.
- Any part of the ear turning dusky, dark or pale, which needs same-day assessment.
- A stitch poking through the skin, or the ear suddenly springing back to its previous position after a knock.
- After a general anesthetic: persistent vomiting, difficulty breathing, or chest pain.
Numbness, itching under the bandage and mild asymmetry from swelling are common in the early weeks and are usually discussed at the routine check rather than by emergency call. When in doubt, ring. Surgical teams would far rather hear about a false alarm than see a delayed infection.
Everything in this article is general information drawn from mainstream medical guidance. It cannot replace an assessment by a surgeon and, for children, an anesthesia team. Whether to have otoplasty, at what age, by which technique and with what aftercare are decisions that sit with the treating team together with the patient and family.
Frequently asked questions
What is the best otoplasty age for a child?
Most surgeons consider otoplasty from about age five, once the ear has reached most of its adult size, but there is no single best age within childhood. The years from roughly five to early adolescence form a broad window. What matters more is that the child is bothered by their ears, understands what will happen and wants the operation for themselves, with parents and the surgical team agreeing on timing.
Is otoplasty safe for a 5-year-old child?
Otoplasty is a surface operation on skin and cartilage with mostly local risks, and general anesthesia for young children is a routine, specialist-led part of pediatric surgical care. Serious complications are uncommon according to NHS and Mayo Clinic guidance, though no outcome can be promised. Safety also depends on the child being emotionally ready and free of current infection. The anesthesia and surgical teams assess each child individually before offering a date.
Is otoplasty risky?
All surgery carries some risk. For otoplasty the main ones are bleeding or a blood collection under the skin, infection, thick or raised scarring behind the ear, uneven or over-corrected ears, partial relapse, stitches surfacing through the skin and temporary numbness. Anesthesia carries its own separate risks. Most are manageable if reported early, and following headband and sport restrictions reduces the chance of relapse.
Did Brad Pitt have an otoplasty?
There is no reliable medical source confirming whether any named celebrity has had otoplasty, and speculation about a private individual’s surgical history is not something a health publication can verify or should repeat. Hairstyles, camera angles, lighting and aging all change how ears appear in photographs. Whether a public figure has or has not had ear surgery has no bearing on whether it is appropriate for you or your child.
Is 4 years old too late to get ear tubes?
No. Ear tubes, or grommets, are placed to drain persistent fluid from the middle ear in glue ear and can be inserted at any age when fluid is affecting hearing, including four, six or older. They are unrelated to otoplasty, which reshapes the outer ear. The NHS notes glue ear often clears on its own, so an ear, nose and throat team usually watches and tests hearing before recommending tubes.
What is the ear pinning age for adults, and is there an upper limit?
Adults of any age in good general health can have otoplasty; there is no upper limit. Adult cartilage is stiffer and less elastic than a child’s, so surgeons may rely more on scoring or removing cartilage than on stitches alone, and healing behind the ear can be slower. Blood pressure, scar history and any medicines affecting bleeding are reviewed beforehand with the prescribing clinician.
How long is otoplasty recovery time?
According to NHS guidance, most people need about a week off school or work, wear a headband especially at night for several weeks, avoid swimming for around four to six weeks and avoid contact sports for about twelve weeks. Bruising and swelling settle over two to three weeks, and the final shape emerges as swelling fades over the following months. Individual surgeons adjust these ranges to the technique used.
Can ear molding for babies replace otoplasty later?
Sometimes. In the first weeks to months of life, ear cartilage is soft enough that a splint or mold can reshape it without surgery, as the NHS describes. Results depend on the ear shape; a weak fold often responds better than a deep conchal bowl. If molding is not started early enough or does not fully correct the ear, otoplasty remains an option once the child reaches about age five.
Will otoplasty change my hearing?
No. Otoplasty works on the pinna, the visible outer ear, and does not involve the ear canal, eardrum or middle ear. Hearing is not the aim of the operation and is not expected to change. Temporary numbness or a feeling of fullness while the ears are bandaged is common, but this relates to the skin and dressing, not to hearing function.
Does otoplasty for children need both ears to be done?
Usually both ears are treated in the same operation even if one seems more prominent, because setting back only one can make the other look more noticeable, and symmetry is easier to approach when both are adjusted together. If one ear is genuinely normal, a surgeon may operate on one side alone. The plan is decided at consultation based on measurements and the family’s wishes.
References
- NHS: Ear correction surgery, including ear pinning
- MedlinePlus: Ear surgery – cosmetic
- MedlinePlus: Plastic and Cosmetic Surgery
- NHS: Glue ear
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Cheek Augmentation Recovery: Swelling Stages, Sleeping Upright and When Contours Emerge
Cheek augmentation recovery follows a fairly predictable arc: swelling and bruising usually peak within the first two to three days, ease noticeably over two…
How Cheek Augmentation Surgery Is Done: Implant Placement Through the Mouth or Lower Eyelid
Cheek implant surgery places a shaped, solid implant over the cheekbone through a small incision either inside the mouth, above the upper gum, or…

When Is a Scar Ready for Scar Revision Surgery? Why Surgeons Wait for Scars to Mature
Most surgeons wait until a scar has fully matured before revising it, which commonly takes about 12 to 18 months and sometimes up to…

What Recovery From Nasal Reconstruction Involves: Congestion, Flap Care and Stage Intervals
Recovery from nasal reconstruction usually unfolds in stages rather than as one healing period. Expect heavy congestion for the first one to two weeks…

Can Buccal Fat Removal Be Reversed? Fat Grafting and Fillers After Over-Removal
Buccal fat removal cannot be truly reversed, because the removed fat pad does not grow back. What surgeons can do is rebuild lost cheek…

Do Surgical Dimples Look Natural? How Dimpleplasty Results Settle Over the First Months
Surgical dimples can look natural, but rarely in the first weeks. Dimpleplasty results usually begin as a fixed indentation that shows even when the…