

What an Echocardiogram Shows in Heart Failure: Ejection Fraction and Why It Guides Treatment

Key Takeaways
- A normal ejection fraction on echocardiogram is roughly 55 to 70 percent, which means a healthy heart leaves about a third of the blood in the ventricle after every beat.
- The widely used threshold for reduced ejection fraction is 40 percent or below, and 35 percent or below is the range where device discussions usually begin after optimized treatment.
- The normal range does not fall with age, so a 70-year-old should still have an ejection fraction in the fifties to sixties or higher.
- Heart failure with preserved ejection fraction is a real diagnosis: the ventricle squeezes normally but fills poorly, and the same scan detects it through filling pressures and atrial size.
- Readings from different days or laboratories can differ by several points without any true change in the heart, so trends over time matter more than single values.
- No supplement or quick fix raises ejection fraction; recovery, when it happens, follows treatment of the cause and months of guideline-directed therapy adjusted by the prescribing team.
An echocardiogram in heart failure measures ejection fraction, the percentage of blood the left ventricle pumps out with each beat. A normal range on echo is roughly 55 to 70 percent; 40 percent or lower is considered reduced. Because several heart failure treatments were studied in specific ejection fraction ranges, the number helps the care team decide which options apply, alongside symptoms and other findings.
The gel is cold, the room is dim, and the person holding the probe keeps asking you to roll a little further onto your left side and hold your breath. On the screen, a gray, flickering shape opens and closes like a fist. Nobody says much. Then, a week later, a letter or a portal message arrives with a single number in it, and suddenly that number seems to be the whole story of your heart.
People facing a new heart failure diagnosis often fixate on that figure before anyone has explained it. An ejection fraction echocardiogram is a routine test, but the result it produces is easy to misread: too low sounds like a countdown, and a normal-looking value can feel like a reprieve when it is not one.
This explainer walks through what the scan actually captures, what the ranges mean at different ages, why the number steers treatment choices, and where its limits are.
What does an ejection fraction echocardiogram actually measure?
Ejection fraction is a ratio, not a volume. It answers one question: of the blood sitting in the left ventricle at the end of filling, what share leaves with the next squeeze? The left ventricle is the heart’s main pumping chamber, the one that pushes blood out to the body. If it holds 100 milliliters when full and pushes out 60, the ejection fraction is 60 percent.
That framing matters because a healthy heart never empties completely. Even a strong ventricle keeps a reserve of blood behind after each contraction. The American Heart Association describes a normal ejection fraction as roughly 55 to 70 percent, which means a well-functioning heart routinely leaves about a third of its contents in the chamber. Anyone who expected 100 percent is measuring against the wrong yardstick.
An echocardiogram is an ultrasound of the heart: high-frequency sound waves bounce off moving tissue and are assembled into live images. The sonographer traces the inner edge of the left ventricle at its fullest and at its smallest, and software converts those outlines into estimated volumes. Subtract one from the other, divide by the full volume, and the percentage appears. Some laboratories also estimate the figure by eye, drawing on years of pattern recognition, and many report both.
Two things follow from this. First, ejection fraction describes the left ventricle’s squeeze and nothing else; the right side of the heart, the valves, and the ventricle’s ability to relax are separate questions the same scan can answer. Second, because the number depends on tracing edges on a moving image, it carries an inherent margin of uncertainty, a point worth returning to later.
How does the echocardiogram work, step by step?
The most common version is a transthoracic echocardiogram, meaning the probe rests on the outside of the chest. There is no radiation, no dye in a vein for a standard scan, and no fasting is usually required. The NHS notes that the whole appointment generally takes well under an hour.
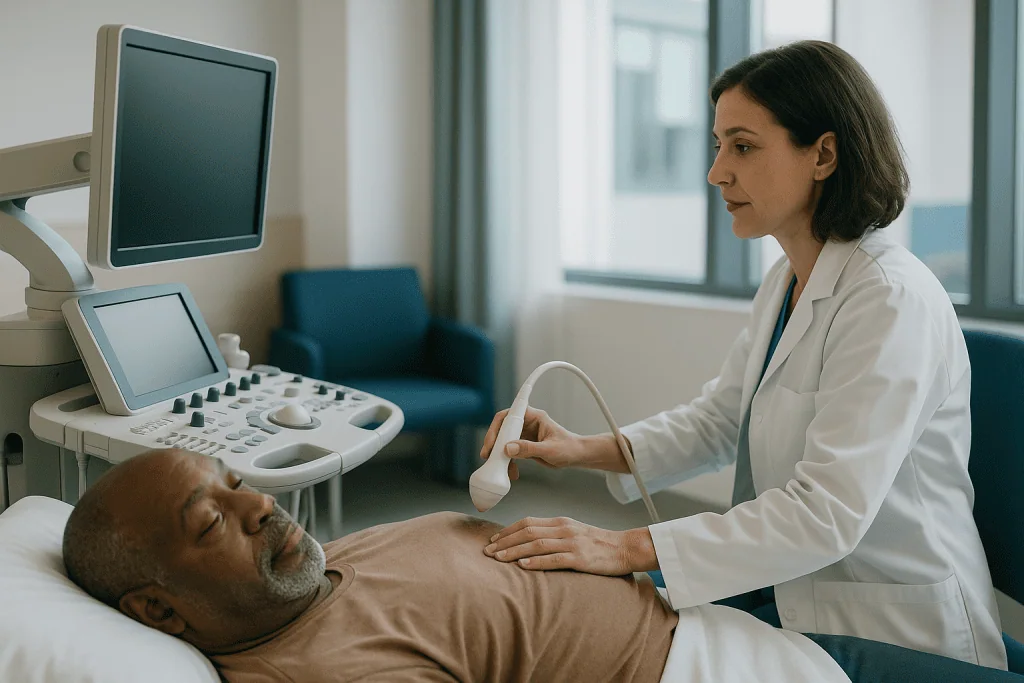
You undress to the waist, put on a gown, and lie on a couch, most often on your left side so the heart drops closer to the chest wall. Small sticky electrodes on the chest record the rhythm at the same time, which lets the machine time each image to the heartbeat. A water-based gel goes on the skin to help sound waves pass through, and then the sonographer moves a hand-held transducer across several standard windows: beside the breastbone, under the left breast, at the base of the throat, and just below the ribs.
Each window gives a different slice through the heart. One shows the left ventricle lengthwise; another cuts it in cross-section like a ring. Color overlays reveal the direction of blood flow, and a separate mode called Doppler measures its speed, which is how pressure differences across valves are estimated. You may be asked to breathe out and hold, because air in the lungs scatters ultrasound and blurs the picture.
If images are poor, sometimes because of body shape, lung disease, or a recent operation, a contrast agent can be injected into a vein to outline the chamber more clearly. When even that does not suffice, a transesophageal echocardiogram, with a small probe passed down the throat under sedation, gives a closer view. Most people never need either. MedlinePlus lists the standard scan as low risk, with mild pressure from the probe the most common complaint.
What is a normal ejection fraction range on an echo?
Guideline bodies and major clinical centers agree on the broad shape of the answer, though the exact boundaries shift by a few points depending on who is drawing them. The American Heart Association frames it this way: 55 to 70 percent is normal, 41 to 54 percent is mildly reduced or borderline, and 40 percent or below is reduced. Mayo Clinic gives a slightly wider normal band, starting around 50 percent. The overlap is what matters: somewhere in the low fifties the reading stops being reassuring on its own and starts prompting closer attention.
Notice what the numbers do not say. A value in the normal range does not rule out heart failure, and a value below it does not by itself mean a person feels unwell. Some people walk around with an ejection fraction in the thirties and climb stairs without complaint, at least for a time, because the body compensates: the heart enlarges, the pulse quickens, the kidneys hold fluid. Others feel breathless with a number that reads as normal. The figure describes the pump; the symptoms describe the whole system.
Very high readings are not automatically good news either. An ejection fraction above roughly 75 percent can point to a heart muscle that has thickened and stiffened, as in hypertrophic cardiomyopathy, where the chamber squeezes hard but fills poorly. The American Heart Association notes this pattern specifically. So the healthy zone is a plateau, not a summit.
Laboratories also differ in how they measure and round. If your report says 52 percent and a friend’s says 57, that gap may be noise rather than a meaningful difference in heart health. Your cardiologist reads the number against the images, the other measurements on the same scan, and how you are actually doing.
What is a worrisome ejection fraction?
The honest answer has two parts: the threshold clinicians use, and the reason it is only a starting point.

The widely used cutoff for reduced ejection fraction is 40 percent or below, the figure the American Heart Association highlights. Below that line, a person with symptoms is usually said to have heart failure with reduced ejection fraction, often shortened to HFrEF. Most of the large medication trials in heart failure recruited people in this range, which is why the number carries so much weight in treatment decisions.
A second line sits lower. The American Heart Association notes that an ejection fraction of 35 percent or below is associated with a higher risk of dangerous heart rhythms. That is the range where cardiologists begin discussing whether an implantable device that can correct a life-threatening rhythm might be appropriate, usually after a period of optimized medication and a repeat scan, because some hearts recover enough that the conversation changes.
Now the caveat. Worrisome is a clinical judgment, not a number alone. Two people can share a reading of 30 percent and have very different outlooks depending on the cause, how long the muscle has been weakened, whether the coronary arteries are open, how the kidneys are coping, and how much treatment has already been tried. An ejection fraction that has fallen from 60 to 45 in a year may concern a cardiologist more than one that has sat stably at 35 for a decade on good treatment.
Direction of travel, then, often tells more than the snapshot. Ask what your number was last time, whether the same laboratory and method were used, and what the team expects it to do over the coming months. Those three questions turn a frightening figure into a piece of information you can work with.
Does ejection fraction by age change what counts as normal for a 70-year-old?
People searching for a normal ejection fraction for a 70-year-old are usually hoping the bar is lower with age. It largely is not. The normal range cited by the American Heart Association and Mayo Clinic is not age-adjusted: a healthy left ventricle at 70 should still push out somewhere in the fifties to sixties or higher, much as it did at 40.
What does change with age is the way the heart fails when it fails. The heart muscle tends to thicken and stiffen over decades, especially in people with long-standing high blood pressure, diabetes, or excess weight. A stiff ventricle can still squeeze well, so the ejection fraction stays in the normal range, but it fills poorly under pressure. That pattern, heart failure with preserved ejection fraction, becomes progressively more common in older adults and is more frequent in women. The NHS describes it as one of the two main types of heart failure.
This is why an older person with breathlessness and swollen ankles should not be reassured purely by a normal-looking number. The echocardiogram has to be read for what the ventricle does when it relaxes, not only when it contracts. Sonographers measure this through Doppler patterns of blood flow across the mitral valve and the speed at which the heart wall moves during filling, alongside the size of the left atrium, which enlarges when filling pressures have been high for a long time.
The practical message for older readers is simple. Age is not a reason to accept a low ejection fraction as normal wear, and a normal ejection fraction is not a reason to dismiss symptoms. Both deserve the same careful reading of the full scan.
Why heart failure with preserved ejection fraction is still heart failure
Few results confuse people more than being told they have heart failure when their ejection fraction is normal. The words seem to contradict each other. They do not, once you separate the two jobs a ventricle has to do.
Squeezing is the job ejection fraction measures. Filling is the other half of every heartbeat, and a ventricle that has become thick or scarred cannot expand easily to accept blood from the lungs. Pressure builds up behind it, in the left atrium and then in the pulmonary veins. Fluid seeps into lung tissue. The person feels breathless on exertion, then lying flat, then at night, and their legs swell, even though the squeeze number looks fine. Mayo Clinic groups this under heart failure with preserved ejection fraction, defined by an ejection fraction of 50 percent or higher together with the signs and symptoms of heart failure.
Between the two lies a middle band, roughly 41 to 49 percent, that guideline bodies now call heart failure with mildly reduced ejection fraction. People in this range were historically excluded from many trials, and clinicians often treat them as sitting closer to the reduced group.
Why do the categories matter for treatment? Because the evidence does not spread evenly across them. Several medication classes with strong trial support in reduced ejection fraction showed weaker or no clear benefit when tested in people with preserved ejection fraction. Newer research, particularly with a class of drugs originally developed for diabetes, has shifted this picture, and guidelines have been updated accordingly. Managing blood pressure, fluid balance, atrial fibrillation, and weight carries particular weight in the preserved group. Your ejection fraction, in other words, tells the team which body of evidence applies to you.
How ejection fraction categories guide treatment: a summary table
The table below summarizes how clinicians commonly group ejection fraction readings and the kinds of decisions each group tends to prompt. The ranges follow the American Heart Association and Mayo Clinic; the treatment column describes categories of approach, not recommendations, and every choice rests with the prescribing team.
| Ejection fraction on echo | Common label | What it usually prompts |
|---|---|---|
| 55 to 70 percent | Normal squeeze | Attention turns to filling function, valves, chamber size, and rhythm if symptoms are present |
| 50 percent or higher with symptoms | Heart failure with preserved ejection fraction | Emphasis on blood pressure, fluid control, treating related conditions, and medication classes shown to help this group |
| 41 to 49 percent | Heart failure with mildly reduced ejection fraction | Often approached similarly to the reduced group; repeat imaging to see which way the number moves |
| 40 percent or lower | Heart failure with reduced ejection fraction | Guideline-directed medication classes with the largest evidence base; search for a reversible cause |
| 35 percent or lower after optimized treatment | Severely reduced | Discussion of implantable devices and, in selected cases, advanced therapies |
| Above roughly 75 percent | Hyperdynamic | Consideration of a thickened, stiff heart muscle or other causes |
A few things the table cannot capture. The same reading means something different in a person whose heart weakened after a heart attack than in someone whose ventricle enlarged from years of uncontrolled blood pressure or from a viral illness. Alcohol, some chemotherapy drugs, thyroid disease, and a persistently fast heart rhythm can each depress ejection fraction in ways that may partly recover once the cause is addressed. So the first question a cardiologist asks after seeing a low number is not which drug, but why.
Treat this as a map of the conversation you are likely to have, not a schedule of what you will receive.
What else does the echo show beyond ejection fraction?
If ejection fraction is the headline, the rest of the report is the article, and cardiologists read all of it. A typical echocardiogram in heart failure records a dozen or more separate findings, several of which change management as much as the pump number does.
Chamber size comes first. A left ventricle that has stretched wider than normal has been working against a problem for a while, and its enlargement is itself a marker that the team tracks over time. Wall thickness is measured in millimeters at set points; thick walls point toward long-standing high blood pressure, a genetic muscle disorder, or, rarely, deposits of abnormal protein in the heart. Regional wall motion is scored segment by segment, because a patch of muscle that does not move suggests a prior heart attack in the artery supplying it, which redirects the workup toward the coronary arteries.
Valves get their own examination. A leaking mitral valve is both a cause and a consequence of a failing ventricle, and its severity influences whether repair is discussed. A narrowed aortic valve can produce heart failure symptoms with a normal ejection fraction and is treatable in its own right.
Doppler measurements estimate the pressure in the pulmonary arteries and the pressure inside the left ventricle during filling, which is how heart failure with preserved ejection fraction is recognized. The right ventricle, often overlooked, is assessed for size and squeeze because a struggling right side changes both symptoms and prognosis. The sac around the heart is checked for fluid.
Many laboratories now add strain imaging, which tracks how much the muscle fibers shorten. It can pick up subtle weakness before the ejection fraction falls, and it is used increasingly in people receiving cancer treatments that can affect the heart. Mayo Clinic lists these features among the reasons echocardiography sits at the center of heart failure evaluation.
Who is usually offered an ejection fraction echocardiogram, and who is asked to wait?
Cardiologists request an ejection fraction echocardiogram when the answer will change what they do next. Mayo Clinic describes the test as a standard part of the initial evaluation when heart failure is suspected, typically after a history, an examination, a blood test for a hormone the stretched heart releases, and an electrocardiogram. A raised hormone level with breathlessness, swelling, or an abnormal tracing usually moves the echo up the list.
Several other situations bring people to the scanner. Someone recovering from a heart attack will often have one to see how much muscle was affected. People about to start, or already receiving, certain chemotherapy agents known to weaken the heart are scanned before and during treatment. A new murmur, unexplained palpitations, a family history of heart muscle disease, or an abnormal chest X-ray showing an enlarged heart shadow can each justify the test. People already diagnosed with heart failure are usually re-scanned after a period of adjusted treatment, or whenever their symptoms shift in a way that does not fit.
Who is asked to wait, or not scanned at all? Generally, people without symptoms and without a specific risk trigger. Guideline bodies do not recommend routine echocardiography as a screening test for the general population, because the chance of finding something that changes care is low and the chance of finding an incidental variation that causes worry is real. A stable person with a known ejection fraction and no change in symptoms is also not usually rescanned on a fixed calendar simply to check; the scan is repeated when there is a clinical question to answer.
None of this is a hard rule. If you believe you should have the test and have not been offered one, asking why is reasonable, and the answer should make sense to you.
How accurate is the number? Why two echoes can disagree
A percentage looks precise. The process that produces it is not, and understanding why spares a great deal of anxiety over small changes.
The standard method traces the inner edge of the left ventricle in two views at two moments of the cycle. Where exactly that edge sits is a judgment, and the ventricle is not a tidy shape; the software assumes a stack of discs to estimate volume from a two-dimensional slice. Image quality varies with body habitus, lung disease, and how the person breathes. Heart rate and blood pressure on the day shift the reading too, since a dehydrated or anxious heart with a fast pulse fills less and can look different from the same heart on a calm morning. Different sonographers, different machines, and different laboratories add their own variation.
The upshot, acknowledged by clinical centers including Cleveland Clinic, is that the same heart can produce readings several points apart on different days without anything having changed. A move from 48 to 44, or 60 to 56, may be measurement scatter. A move from 55 to 35 is not.
Cardiologists manage this in a few ways. They compare scans done at the same laboratory when possible. They weigh the visual impression alongside the traced figure. They look at whether other measurements moved in the same direction; if the ventricle also enlarged and the filling pressures rose, a drop in ejection fraction is more believable. Three-dimensional echo and contrast reduce, but do not remove, the variability. When a decision hinges on a threshold, such as whether a device is warranted, some teams confirm with cardiac magnetic resonance imaging, which measures volumes more reproducibly, though it is less available and not suitable for everyone.
Treat single-digit changes as questions to raise, not verdicts to absorb.
What is the fastest way to increase ejection fraction? How to improve ejection fraction honestly
This is among the most searched questions on the topic, and the truthful answer disappoints anyone hoping for a shortcut: there is no fast way, and the reliable ways are mostly the unglamorous ones your cardiologist has probably already described.
Start with the cause. If a weak ventricle is being driven by a persistently fast heart rhythm, blocked coronary arteries, heavy alcohol use, an overactive thyroid, or a medication that is harming the muscle, then addressing that problem can allow the ejection fraction to recover, sometimes substantially. This is why the workup after a low reading matters so much.
Next come the guideline-directed medication classes for reduced ejection fraction. Each works through a different mechanism: some blunt the stress hormones that make a struggling heart beat harder and enlarge further; some relax blood vessels and reduce the load the ventricle pushes against; some limit fluid retention and scarring; a newer class alters how the kidneys handle salt and sugar in ways that appear to protect the heart. In trials these classes, used together and adjusted over time by the prescribing team, were associated with improvements in ejection fraction over months rather than days, alongside fewer hospital admissions. Whether and how they apply to you is a decision for your clinician, and stopping or altering any of them without that conversation is unsafe.
Devices have a role for selected people. A pacemaker that resynchronizes the two ventricles can improve squeeze when the electrical timing is off. Supervised cardiac rehabilitation improves how far people can walk and how they feel, even when the number itself moves little.
Diet supplements marketed to raise ejection fraction lack convincing evidence. The NHS heart failure guidance points to salt awareness, appropriate activity, limiting alcohol, not smoking, and vaccinations as the everyday measures with support. Slow, steady, and boring is the honest recipe.
What the following weeks and months usually look like after the scan
The echocardiogram itself has no recovery period. You wipe off the gel, get dressed, and can drive home. Mild skin redness where the electrodes sat is about the only physical trace. The waiting is the harder part.
A cardiologist reviews the images and issues a report, which the requesting clinician then interprets alongside everything else. In many services this takes days to a couple of weeks, though a scan done during a hospital stay is often read the same day. If the ejection fraction is reduced, the next appointment usually covers three things: what might have caused it, which of the evidence-based treatment classes suit you, and what further tests will help. Further tests commonly include blood work for kidney and thyroid function, sometimes a coronary assessment, and occasionally cardiac magnetic resonance imaging for a closer look at the muscle.
Medication for reduced ejection fraction is typically introduced gradually. Clinicians start one class, watch blood pressure, kidney readings, and how you feel, then add or adjust. This staged approach is why the early months involve more appointments and blood tests than later ones. Mayo Clinic describes this monitoring as a routine part of heart failure care rather than a sign that something has gone wrong.
A repeat echocardiogram is generally arranged once treatment has been adjusted as far as is appropriate, commonly after a period of several months, so the team can see whether the ventricle has responded. That second scan often matters more than the first, because it separates hearts that are recovering from those that need the next tier of options discussed.
Symptoms and the number do not always move together. People frequently feel better before the ejection fraction changes, and some feel much the same even when it rises. Both patterns are recognized, and neither means the plan is failing.
What people often get wrong about ejection fraction
Some misunderstandings come up so often in clinic that they deserve to be named directly.
The first is that a low ejection fraction is a life expectancy. It is not. It is a measurement of one chamber’s squeeze at one moment, influenced by cause, treatment, and time. Plenty of people live for many years with readings in the thirties on well-managed therapy, and some see their number climb back toward normal. Prognosis is a conversation, not a percentage.
The second is that a normal ejection fraction means the heart is fine. As the sections above explain, heart failure with preserved ejection fraction is common, particularly in older adults and women, and it produces the same breathlessness and swelling with a reassuring-looking number. Symptoms plus a normal reading is a reason for the full scan to be read carefully, not a reason to stop looking.
The third is that the number should be 100 percent, or at least 90. A healthy heart deliberately keeps blood in reserve. The American Heart Association’s normal range tops out around 70 percent, and readings well above that can themselves signal a problem.
The fourth is that a change of a few points is real. Measurement variation between scans can account for small differences. Ask whether the same laboratory and method were used before drawing conclusions.
The fifth is that feeling better means treatment can stop. Several heart failure medication classes work by protecting the ventricle over the long term, and the benefit continues only while they are taken. Stopping because the symptoms have eased is a common and avoidable path back to hospital. Any change belongs in a conversation with the prescriber.
The last is that exercise is dangerous with a weak heart. Supervised, appropriately paced activity is a recognized part of heart failure care, not a threat to it.
Questions to ask your care team about your ejection fraction result
Consultations are short and the number tends to crowd out everything else. Arriving with a handful of specific questions makes the time count. These are the ones that tend to unlock the most useful answers.
- What exactly was my ejection fraction, and which method did the laboratory use to measure it?
- What was it on any previous scan, and was that done in the same place?
- What do you think is causing it, and which tests will help us find out?
- What did the rest of the echo show about my valves, chamber size, filling pressures, and right ventricle?
- Which category of heart failure does this put me in, and how does that shape the treatment options you are considering?
- What is each medication you are proposing meant to do, and what side effects should I report?
- When will you repeat the scan, and what would you hope to see?
- Which symptoms should prompt me to call, and which mean I should go to an emergency department?
- Is cardiac rehabilitation available to me, and how do I access it?
- How should I think about daily weight, salt, fluids, and alcohol in my situation?
Two further questions are worth asking even when they feel awkward. The first is about driving, work, and physical activity, because rules and advice vary with the diagnosis and it is better to hear them from the team than to guess. The second is about what happens if the ejection fraction does not improve: which options come next, and at what point they would be discussed. Knowing the shape of the road ahead, including the forks in it, tends to lower anxiety rather than raise it.
Write the answers down or bring someone who will. Ejection fraction is a number you will hear again, and the context you gather now makes every future reading easier to place.
When to call your doctor: red-flag signs in heart failure
An echocardiogram result, whatever it says, does not change the warning signs that need prompt attention. Heart failure can worsen gradually or abruptly, and knowing which is which keeps people out of avoidable emergencies.
Call emergency services, or have someone take you to an emergency department immediately, if you experience chest pain or pressure that does not settle within a few minutes, severe breathlessness at rest or breathlessness that is rapidly getting worse, fainting or near-fainting, a fast or irregular heartbeat accompanied by dizziness or breathlessness, coughing up pink or frothy sputum, or sudden confusion. The NHS and Mayo Clinic both list these as signs that need urgent assessment.
Contact your care team the same day, without waiting for the next scheduled appointment, if your breathlessness is worse than usual on ordinary activity, you need more pillows to sleep or wake at night gasping, your weight has climbed quickly over a few days, which usually reflects fluid rather than fat, your ankles, legs, or abdomen are noticeably more swollen, you feel unusually dizzy when standing, or you have developed a new cough that will not shift. Heart failure teams generally give a personal weight threshold for when to call; if you have not been given one, ask for it.
Also let the team know if you have been unable to take prescribed medication for any reason, including vomiting or a stomach illness, because fluid balance can shift quickly and the plan may need temporary adjustment under their guidance. Do not make that adjustment yourself.
Finally, if anything about your test result or plan does not make sense, that is itself a reason to call. Confusion about what a number means is common, and clearing it up is part of the team’s job, not an imposition on their time.
Frequently asked questions
What is a worrisome ejection fraction?
An ejection fraction of 40 percent or below is classed as reduced, and 35 percent or lower is linked to a higher risk of dangerous rhythms according to the American Heart Association. Whether a specific reading is worrisome depends on its cause, whether it is falling or stable, symptoms, and how much treatment has been tried, so the number is a prompt for discussion rather than a verdict.
What is a normal ejection fraction range on an echo?
Roughly 55 to 70 percent is normal on echocardiogram, with Mayo Clinic accepting a lower bound of about 50 percent. Values between 41 and 54 percent are considered mildly reduced or borderline. Readings above about 75 percent are not better; they can indicate a thickened, stiff heart muscle and are reviewed separately.
What is a normal ejection fraction for a 70 year old? Does ejection fraction by age matter?
The normal range is the same at 70 as at 40, roughly 55 to 70 percent. Age does not lower the bar. What changes with age is the type of heart failure people develop: older adults more often have preserved ejection fraction with a stiff ventricle that fills poorly, so a normal number with symptoms still needs a full reading of the scan.
What is the fastest way to increase ejection fraction?
There is no fast way. Ejection fraction may recover over months when a reversible cause such as a fast rhythm, blocked artery, alcohol, or thyroid disease is treated and when guideline-directed medication classes are adjusted by the care team. Supplements marketed for this purpose lack convincing evidence. Improvements, when they occur, typically appear on a repeat scan after several months rather than weeks.
How to improve ejection fraction without medication?
Lifestyle measures support the heart but rarely raise ejection fraction on their own. Limiting alcohol, not smoking, managing blood pressure and weight, staying active through supervised cardiac rehabilitation, and treating sleep apnea all help how people feel and reduce strain on the ventricle. For reduced ejection fraction, medication classes with trial evidence remain the main route to recovery, and decisions about them belong with the prescribing clinician.
Can you have heart failure with preserved ejection fraction?
Yes. Heart failure with preserved ejection fraction means the ventricle squeezes normally, with a reading of 50 percent or higher, but is stiff and fills poorly, producing breathlessness and swelling. It is common in older adults, especially women, and in people with long-standing high blood pressure or diabetes. The echocardiogram identifies it through filling pressures, wall thickness, and left atrial size rather than the pump number.
How long does an echocardiogram for heart failure take?
A standard transthoracic echocardiogram usually takes well under an hour, according to the NHS and MedlinePlus, and often around 30 to 45 minutes of scanning. There is no radiation and no recovery time. If images are unclear, a contrast injection may be added, and in some cases a transesophageal scan under sedation is arranged separately.
Why did my ejection fraction change between two echoes?
Small differences of a few points are often measurement variation rather than real change. Tracing the ventricle’s edge is a judgment, image quality varies, and heart rate and fluid status on the day shift the result. Cardiologists compare scans from the same laboratory when possible and look for other measurements moving in the same direction before concluding that the heart has genuinely changed.
Does a low ejection fraction always mean I need a defibrillator?
No. Discussion of an implantable defibrillator generally arises when ejection fraction remains 35 percent or below after a period of optimized medication, because some hearts improve enough that the picture changes. The decision also weighs the cause, other health conditions, symptoms, and personal preference. It is a shared decision with the cardiology team, not an automatic consequence of one scan.
Can ejection fraction go back to normal?
It can in some people, particularly when the weakness had a treatable cause or when guideline-directed therapy is well established over months. Cardiologists describe this as recovered or improved ejection fraction. Recovery does not usually mean treatment stops, because the protective effect of several medication classes depends on continuing them, and any change should be made only with the prescribing clinician.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Cardiac Ablation Recovery: The Overnight Stay and the First Two Weeks of Lighter Activity
Cardiac ablation recovery time is short for most people: home the same day or after one overnight stay, several hours lying flat while the…

Who Needs Heart Bypass Surgery Rather Than a Stent? What the Heart Team Weighs
Heart bypass surgery is usually offered when coronary blockages are too extensive, too complex, or too poorly placed for stents to treat well: typically…

How to Measure Blood Pressure at Home: The Technique Most People Get Wrong
To measure blood pressure at home, use a validated automatic upper-arm monitor with a cuff sized to your arm. Sit quietly for five minutes…

Who Is a Candidate for Percutaneous PFO or ASD Closure, and Who Is Better Served by Surgery?
Percutaneous PFO closure is usually considered for adults under about 60 who have had a stroke of unclear cause that a full workup links…

What an Echocardiogram Shows in Pericardial Effusion and How It Guides Treatment
An echocardiogram shows how much fluid surrounds the heart, where it sits, and whether it is pressing on the heart chambers. Measuring the fluid…

Managing Hypertension Day to Day: Salt, Weight, Exercise and a Reading Log Your Doctor Can Use
Living with hypertension means treating blood pressure as a number you manage rather than a label you carry. Guidelines point to four everyday levers:…