

What Does Hand Therapy Involve After Surgery and Why Does Timing Matter So Much?

Key Takeaways
- The joints that were not operated on are almost always part of the program from day one, because a stiff shoulder or finger after a wrist fracture is a common, avoidable complication.
- Release operations such as carpal tunnel decompression usually allow light hand use within days, while tendon and nerve repairs require weeks of protection before strengthening begins.
- Elevation above heart level in the first few days is the single most effective early measure against swelling, and a sling can defeat it by holding the hand at waist height.
- Splint angles are structural decisions that shift load away from a specific repair, so a home adjustment for comfort can silently remove that protection.
- Pins left protruding through the skin are removed in clinic once imaging shows healing, and the fuller motion program only begins after that visit.
- Escalating pain with shiny, discolored, sweaty and touch-sensitive skin can indicate complex regional pain syndrome, which responds better when recognized early.
Hand therapy after surgery is a supervised program of swelling control, protective splinting, graded movement, scar care and strengthening, usually led by an occupational or physical therapist working from the surgeon's protocol. Timing matters because tendons, joints and scar tissue respond to load within a narrow early window; starting too late often leaves stiffness, while starting too aggressively can harm the repair. The treating team sets the schedule.
The stitches are in, the bandage is bulky, and the hand on the pillow beside you feels like it belongs to someone else. You cannot open a jar, sign your name or brush your hair properly. The surgeon said the operation went well. Then came the sentence that catches most people off guard: therapy starts next week, and how the next six weeks go will matter as much as what happened in the operating room.
That is the part nobody films. Hand therapy after surgery is quiet, repetitive work with a splint, a tape measure and a therapist who counts the degrees your finger bends. It is also where much of the final result is decided, because a repaired tendon or a pinned bone is only half of a working hand.
This explainer walks through what those sessions involve, why the calendar is so unforgiving in hand rehabilitation, and what the first days, weeks and months usually look like.
What is hand therapy after surgery, and who provides it?
Hand therapy is rehabilitation focused on the fingers, hand, wrist and forearm, usually delivered by an occupational therapist or physical therapist who has trained specifically in upper-limb recovery. Some hold an additional certification in hand therapy; the credential signals extra experience with the anatomy, not a different kind of medicine.
The job has several parts. The therapist reads the operative report, learns exactly which structures were repaired or released, and translates the surgeon’s written protocol into a plan a person can follow at home. A protocol is simply the surgeon’s set of instructions about what the hand may do, and when. From there the work is practical: controlling swelling, making or adjusting a protective splint (a molded plastic or fabric support that holds joints in a chosen position), teaching gentle movement, managing the scar and, later, rebuilding grip and dexterity.
Why not just rest? Because the hand is unusually crowded. Twenty-seven bones, dozens of tendons and three major nerves share a space roughly the size of a wallet. When anything in that space is cut and sewn, the body’s healing response floods the area with fluid and lays down collagen, the protein scaffolding of scar. Left unguided, that scaffolding can glue tendons to their tunnels and stiffen small joints within weeks.
The surgeon decides what the hand is allowed to do; the therapist makes sure the hand actually does it, safely and at the right moment. Resources such as MedlinePlus describe this follow-up as an expected part of recovery after common procedures like carpal tunnel release, not an optional add-on.
How does hand therapy after surgery actually work?
Think of a repaired flexor tendon (the cord that bends a finger) as a thread running through a series of tight sleeves in the palm. After surgery, the body tries to heal the thread by gluing it to whatever it touches, including the sleeve. If the tendon never moves, that glue matures into firm adhesions, scar bands that tether one structure to another. The finger then bends only as far as the scar allows.

Controlled motion interrupts that process. Each gentle glide of the tendon through its sleeve tells the healing tissue where to stay flexible and where to stay strong. The same principle applies to joints. A finger joint held still in a swollen state loses the elasticity of its capsule, the fibrous envelope around the joint, and that loss is far easier to prevent than to reverse.
Swelling, or edema, is the other enemy. Fluid stretches skin, increases pressure inside tendon tunnels and makes every movement more painful, which in turn discourages movement. Elevation, light compression and active pumping of the fingers all push fluid back toward the heart. This is why the earliest instruction after most hand operations concerns positioning rather than exercise.
Scar care follows once the wound is closed. Massage and gentle stretching remodel the surface scar so it slides over the tissue beneath instead of dimpling into it. Desensitization, meaning graded exposure of a hypersensitive area to different textures, calms nerve endings that have become overly reactive.
Strength comes last, deliberately. Loading a repair before it can bear load is how repairs fail. The sequence, protect, move, remodel, then strengthen, is the logic behind nearly every hand protocol.
Why does timing matter so much in hand rehabilitation?
Healing runs on a schedule the patient cannot see. In the first days after surgery, inflammation dominates: the area is swollen, warm and fragile. Over the following weeks, cells lay down new collagen quickly and somewhat randomly. Only later does that collagen organize itself along lines of tension and gain strength. Each phase invites a different kind of therapy, and each closes a door behind it.
Move too early or too hard, and a tendon repair can gap or rupture, or a fracture fixed with pins can shift. Move too late, and the collagen has already set into adhesions and joint contractures, a fixed shortening that no amount of stretching fully undoes. The therapist’s calendar is an attempt to thread that needle: enough motion to keep tissues gliding, never enough force to disturb the repair.
Clinical guidance reflects this balance. Mayo Clinic notes that after a broken wrist, therapy typically begins once the cast or splint comes off, because immobilization itself causes stiffness that must then be worked out. MedlinePlus describes light use of the hand within days of carpal tunnel release, with heavier activity deferred for weeks. Neither timeline is arbitrary; both track the biology.
Nerve recovery has its own slow clock. A nerve that was compressed or repaired regrows at a pace measured in millimeters per day, so sensation may return over many months. Therapy during that period protects skin the person cannot fully feel and retrains the brain to interpret the new signals.
The practical lesson is that the appointment two weeks after surgery is not a formality. Missing it can mean arriving at week six with a hand that has quietly set in the wrong shape.
Who usually starts hand therapy early, and who is asked to wait?
Early referral, sometimes within the first week, is common after operations where stiffness is the main threat and the repair is stable enough to tolerate protected motion. Tendon repairs are the classic example: surgeons generally want the tendon gliding within a purpose-built splint that limits how far the wrist and fingers can move. Releases such as carpal tunnel decompression, where the nerve is freed rather than repaired, also tend to involve early gentle use, as MedlinePlus outlines.
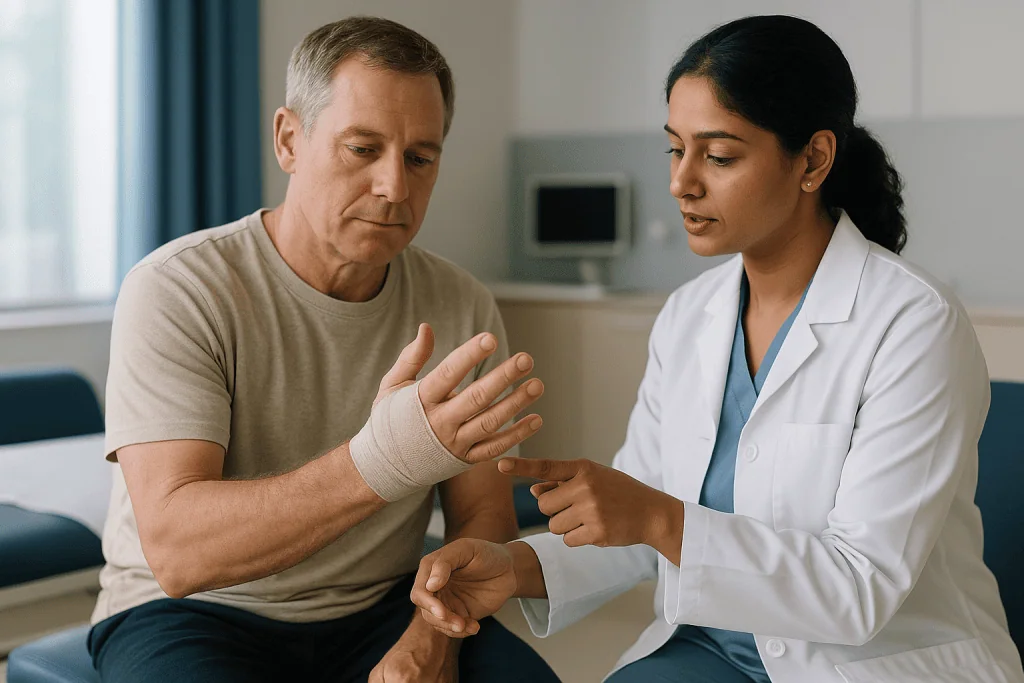
Fractures fixed with plates and screws often allow earlier motion than fractures held with pins or a cast, because rigid internal fixation protects the bone while joints are moved. The surgeon’s confidence in the fixation, judged in the operating room, usually determines the pace.
Some people are asked to wait. Fractures treated in a cast typically remain immobilized until imaging shows healing; NHS guidance places that at roughly six to eight weeks for many adult wrist fractures, though children heal faster and complex breaks slower. During that period, therapy may still address the free joints, such as shoulder, elbow and fingers, so they do not stiffen in sympathy.
Other reasons to delay include wound healing problems, infection risk, a repair that felt tenuous at surgery, or a person who cannot yet follow precise instructions because of pain or confusion. Skin grafts and nerve repairs often need a stretch of strict protection before motion begins.
Age alone rarely disqualifies anyone. Frailer patients may simply progress in smaller steps. The decision about start date rests entirely with the operating surgeon, who knows exactly what was sewn and how well it held.
Common hand and wrist surgeries and what therapy usually focuses on
Different operations ask different things of rehabilitation. The table below summarizes typical emphases described by mainstream sources such as MedlinePlus, Mayo Clinic and the NHS. It is orientation, not a schedule; individual protocols vary with the surgeon’s technique and the tissue found at surgery.
| Procedure | Main rehab goal | Usual early priority | Common later focus |
|---|---|---|---|
| Carpal tunnel release | Restore nerve gliding and grip without scar tenderness | Swelling control, gentle finger and wrist motion | Scar massage, gradual return to gripping tasks |
| Flexor tendon repair | Prevent adhesions while protecting the repair | Protective splint with guided tendon gliding | Progressive strengthening once healed |
| Distal radius (wrist) fracture | Regain wrist and forearm motion after immobilization | Keeping fingers, elbow and shoulder moving | Wrist range, weight-bearing tolerance, grip |
| Trigger finger release | Full smooth bending without catching | Early active finger movement | Scar softening, addressing residual stiffness |
| Dupuytren’s fasciectomy | Keep the straightened finger straight | Wound care, extension splinting as directed | Night splinting, stretching, grip return |
| Fracture with pins (K-wires) | Protect pins, prevent pin-site infection and stiffness | Pin-site care, motion of unpinned joints | Full motion program after pin removal |
Two patterns stand out. First, procedures that release something, such as a tight ligament or a catching tendon sheath, usually move earlier than procedures that repair something. Second, whatever the operation, the joints that were not operated on are almost always part of the program from the start, because a stiff shoulder after a wrist fracture is a well-recognized and avoidable complication.
What do the first days after hand surgery look like, and how long should you elevate your hand?
The first seventy-two hours are mostly about gravity. Fluid pools wherever the hand hangs, so the standard instruction is to keep the hand above the level of the heart as much as possible: propped on pillows in bed, resting on the opposite shoulder when sitting, never dangling by your side on a walk. MedlinePlus and Mayo Clinic both describe elevation as a central early measure for swelling and pain after hand and wrist procedures.
How long? Most guidance frames it as the first few days, tapering as swelling falls, rather than a fixed number of hours. A useful signal is the fingertips: if they look puffy or feel tight after the hand has been down for a while, it still needs elevating. Slings are used sparingly, because a hand strapped at waist level is a hand hanging below the heart.
Fingers that are free to move should move, early and often. Gentle fist-and-stretch cycles act as a pump, squeezing fluid out of the tissues. This is not strengthening; it is housekeeping.
Dressings usually stay dry and intact until the first clinic visit. Pain is expected and typically eases over the first week; the prescribing clinician chooses any medicine and its timeline, and therapy sessions are often scheduled around when relief is best. Stitches, where used, are commonly removed around one to two weeks after surgery, according to MedlinePlus guidance on carpal tunnel release.
Sleep can be awkward. Many people find a pillow under the forearm and another beside the body keeps the hand raised without the shoulder aching by morning.
What to expect after hand surgery with pins
Pins, often called K-wires, are thin metal rods pushed through the skin and bone to hold fracture fragments while they knit. Some are buried under the skin; many are left protruding, capped or bent, so they can be removed in clinic without a second operation. Seeing metal emerging from your own hand is unsettling, and it is worth knowing in advance what is normal.
The pin sites are small open wounds, so the first therapy priority is keeping them clean and dry as directed. A little clear or slightly blood-tinged fluid at the site can be expected early; increasing redness, thick discharge, warmth or a pin that suddenly feels loose are not, and should be reported promptly.
Movement is restricted around the pinned bone but usually encouraged everywhere else. If the pin crosses a joint, that joint stays still; the neighboring joints, the elbow and the shoulder generally keep moving from the start. The therapist will show which motions are safe and may fit a splint that shields the pins from knocks.
Pins typically come out once imaging shows enough healing, a point Mayo Clinic places some weeks after surgery, varying with the fracture and the person. Removal is quick and usually done in clinic. Only after that does the fuller motion program begin, which is why the weeks with pins can feel like a holding pattern.
Expect the pinned area to be stiff and weak immediately afterward. That is the moment therapy shifts gear, and the reason the appointment right after pin removal is one of the most important in the whole recovery.
What not to do after wrist surgery
Most complications in the first weeks come from ordinary life rather than dramatic accidents. A few rules recur across guidance from MedlinePlus, Mayo Clinic and the NHS, and they apply broadly whether the wrist was released, repaired or fixed.
- Do not lift, grip or push with the operated hand beyond what your protocol allows. Carrying a grocery bag or opening a stiff door loads structures that are not ready.
- Do not let the hand hang down for long stretches. Swelling returns fast, and with it pain and stiffness.
- Do not remove, loosen or reshape the splint on your own. Its angles are chosen to protect a specific repair; a comfortable adjustment can be an unsafe one.
- Do not get the wound or pin sites wet until cleared. Soaking softens skin and invites infection.
- Do not drive until the surgeon agrees and you can control the wheel and gear controls in an emergency, not merely on a quiet street.
- Do not skip the home program because the hand feels fine. Stiffness and adhesions form silently.
- Do not push through sharp or escalating pain. Discomfort during stretching is expected; pain that worsens after each session is a signal to stop and ask.
- Do not apply heat to a swollen hand in the early days unless told to; it tends to increase swelling.
Smoking deserves its own mention. It narrows small blood vessels and is associated with slower wound and bone healing, which is why surgical teams commonly raise it before and after operations. Anyone considering quitting should discuss support with their clinician rather than going it alone.
None of this means sitting motionless. The hand should be doing exactly what the protocol permits, every day, and nothing it forbids.
How long is hand therapy after surgery?
There is no single answer, and anyone who offers one has not read your operative report. The honest range runs from a couple of visits to many months, depending on what was operated on and how the tissue responds.
At the shorter end sit release procedures. MedlinePlus describes recovery from carpal tunnel release as light activity within days, return to many jobs within weeks, and full strength returning over a longer period; therapy for such cases may involve a handful of sessions focused on scar and grip. Trigger finger release often follows a similar pattern.
Fractures sit in the middle. NHS guidance gives about six to eight weeks for many adult wrist fractures to heal in a cast, and Mayo Clinic notes that regaining motion and strength afterward may take several more months. Formal therapy might span that whole stretch, with home exercise carrying on beyond it.
Tendon and nerve repairs are the long haul. Tendons need protection for weeks before strengthening can even start, and nerves regrow slowly, so therapy may continue in some form for many months while sensation and fine control return.
Frequency also changes over time. Early on, visits may be weekly or more, because splints need adjusting and the protocol shifts quickly. Later, appointments spread out and the emphasis moves to the home program. Discharge from therapy does not mean recovery is finished; it means the therapist trusts you to keep going without supervision.
A fair question to put to your team is not how long therapy lasts but what milestones would show it is working, and what would prompt them to change course.
What happens in a hand therapy session, and how do home exercises fit in?
A first appointment is largely measurement. The therapist inspects the wound, checks sensation and circulation, and records swelling by wrapping a tape around the hand or dipping it in a volumeter, a water-displacement device. A goniometer, a hinged ruler, measures how many degrees each joint bends and straightens. These baseline numbers matter because progress in hand therapy is often a few degrees a week, invisible to the eye but clear on paper.
Splint fitting frequently follows. Thermoplastic softens in warm water and is molded directly to the hand, then cooled to hold its shape. The therapist will show how to put it on, how tight the straps should be, and which activities require it.
The movement portion is specific. Rather than a generic list, exercises target the structures at risk: tendon gliding sequences after a tendon repair, wrist flexion and extension after a fracture, thumb web-space stretches after a release. Each is demonstrated, corrected and then written down, because the real work happens between visits.
Home exercise is the engine of recovery. Short sets performed several times a day generally beat one long effort, since tissue responds to frequent gentle reminders rather than occasional force. Doing them wrong, however, can be worse than not doing them, which is why therapists ask to watch you perform them at each visit.
Later sessions add scar massage, desensitization with textured fabrics, putty or graded grip tools, and practice with the actual tasks that matter to you, whether that is typing, buttoning a shirt or holding a chisel. The program bends toward your life, not the other way around.
Pain, swelling and stiffness after hand surgery: what is expected and what is not
Some discomfort is part of the deal. Surgery cuts skin and disturbs tissue, and the first week is usually the sorest. Stretching a stiff joint in therapy produces a pulling ache that eases within minutes of stopping. Swelling peaks early and then recedes over weeks, often lingering longest in the fingers and around scars. Morning stiffness that loosens with movement is common for months after a fracture.
The pattern to watch is direction. Pain and swelling that steadily improve, even with bad days, suggest normal healing. Pain that intensifies day by day, swelling that returns after having settled, or a hand that becomes shiny, discolored, sweaty and exquisitely sensitive to light touch are different signals.
That last cluster describes complex regional pain syndrome, or CRPS, an uncommon condition in which the nervous system amplifies pain out of proportion to the injury. Mayo Clinic notes that it can follow surgery or fracture, that it is more likely to improve when recognized and treated early, and that keeping the limb moving is part of management. Hand therapists are trained to spot the early picture and flag it to the surgeon.
Numbness is more nuanced. After a nerve release, tingling as sensation returns can be a positive sign. New numbness that was not present before surgery, or numbness that worsens, needs review because it can indicate pressure from swelling or a tight dressing.
Cold, pale or blue fingertips, or a dressing that feels tighter each hour, are circulation warnings and belong in the red-flag category below. When in doubt, describing the trend, better, same or worse, helps the team decide quickly.
What people often get wrong about hand therapy after surgery
Rest is the safest option. For the operated structure, protected rest may be right; for everything around it, immobility is the fastest route to stiffness. A wrist fracture treated with a cast but no attention to the fingers and shoulder can leave a person with three stiff joints instead of one.
Pain means damage. Stretching scar and stiff joints hurts in a specific, tolerable way that fades quickly. Learning the difference between that ache and a sharp, lingering or escalating pain is a skill the therapist teaches. Avoiding all discomfort usually means avoiding all progress.
More force means faster results. Tissue remodels in response to frequent gentle load, not occasional heroic effort. Overstretching provokes swelling and inflammation, which tightens things further. Slow and often beats hard and rarely.
Once the wound is healed, the job is done. Skin closes in weeks; tendons, bone and nerve mature over months. Many people stop exercising when the scar looks tidy, then wonder why grip never fully returned.
Therapy exercises are the same for every operation. Lists of generic finger movements circulate widely. Some are harmless after one procedure and risky after another. A tendon repair and a carpal tunnel release require nearly opposite approaches in the early weeks.
The surgeon fixed it, so the outcome is set. The operation creates the possibility of a working hand. The weeks afterward determine how much of that possibility is realized, which is why surgeons tend to be as insistent about therapy attendance as they are about the operation itself.
Splints are just for comfort. They are structural. Their angles are engineering decisions about which tissues bear load, and altering them without advice changes the protection they provide.
Questions to ask your care team before and after hand surgery
Good questions turn a passive recovery into a shared plan. These are ones therapists and surgeons say they welcome, because clear answers prevent the most common mistakes.
- Which exact structures were repaired, released or fixed, and which movements would put them at risk in the first weeks?
- When should my first therapy visit happen, and who arranges it?
- What may I do with this hand today: dress, type, drive, lift a kettle, hold a child?
- How should I wear the splint, for how many hours, and when may it come off for washing or exercise?
- What does normal swelling and pain look like at one week, three weeks and six weeks, and what would you want to hear about immediately?
- If I have pins, how do I care for the sites, and roughly when do you expect to remove them?
- How will we know therapy is working? What measurements will you track?
- What happens if motion plateaus: are there further steps, and when would you consider them?
- How long before I can return to my job or sport, and what modifications might bridge the gap?
- Is there anything about my health, such as smoking, diabetes or a previous stiff joint, that changes the plan?
- Who do I contact between appointments if something changes, and how quickly should I expect a reply?
Write the answers down, or ask someone to come with you. Post-operative visits are short, pain and medication blur memory, and the details, such as the splint angle or the exact day the protocol advances, are where recovery is won or lost.
One more question is worth asking of yourself: what tasks matter most to me? Telling the therapist that you need to play the piano or hold a steering wheel gives the program a target, and a target is what keeps most people doing their exercises on the days they would rather not.
When to call your doctor: red-flag signs after hand surgery
Most recoveries follow a steady, if slow, arc of improvement. A few developments should not wait for the next scheduled visit. Contact the surgical team, or seek urgent care if they cannot be reached, if you notice any of the following, which mainstream sources including MedlinePlus, Mayo Clinic and the NHS list as warning signs.
- Fingers that turn pale, blue, grey or cold, or that you cannot feel or move when you previously could. This can signal compromised circulation or pressure from swelling under a dressing or cast.
- A dressing, splint or cast that feels progressively tighter, or pain that is severe and not relieved by elevation and the prescribed measures.
- Spreading redness, warmth, thick or foul-smelling discharge, or a fever, which may indicate wound or pin-site infection.
- A pin that appears to have moved, bent or loosened, or new pain at a pin site.
- Bleeding that soaks through the dressing rather than spotting it.
- A sudden snap, pop or loss of the ability to bend or straighten a finger after a tendon repair, which can suggest the repair has given way.
- Increasing swelling, shiny skin, color changes, sweating and sensitivity to light touch out of proportion to the surgery, features Mayo Clinic associates with complex regional pain syndrome.
- Calf pain, chest pain or sudden breathlessness in the days after surgery, which are not hand symptoms but are emergencies in their own right.
Less dramatic changes still deserve a call: a stall in progress over a couple of weeks, a splint that rubs or has cracked, or exercises that consistently leave the hand more swollen the next day. Therapists would far rather adjust a plan early than discover a problem at the six-week visit.
Every decision about medicines, splints, return to activity and any further procedure sits with the treating team, who know the details of your operation. This article can help you ask better questions; it cannot replace their judgment.
Frequently asked questions
How long is hand therapy after surgery?
Anywhere from a few sessions to many months, depending on the operation. Release procedures like carpal tunnel decompression often need only brief therapy focused on scar and grip. Fractures may involve therapy through the six-to-eight-week healing window the NHS describes and for months afterward. Tendon and nerve repairs are the longest, because those tissues mature slowly. Your surgeon and therapist set the schedule.
What should you not do after wrist surgery?
Avoid lifting, gripping or pushing beyond your protocol, letting the hand hang down for long periods, altering or removing the splint without advice, getting the wound wet before clearance, driving before the surgeon agrees, and skipping home exercises because the hand feels fine. Sharp or worsening pain during activity is a signal to stop and ask, not to push through.
How long should I elevate my hand after surgery?
Most guidance frames elevation as a priority for the first few days, tapering as swelling settles, rather than a fixed number of hours. Keep the hand above heart level when resting, propped on pillows or against the opposite shoulder. If fingertips look puffy or feel tight after the hand has been down for a while, it still needs elevating. Your team will advise on your specific case.
What can I expect after hand surgery with pins?
Pins hold fracture pieces while they knit and often protrude through the skin under a dressing. Expect restricted movement around the pinned bone, encouraged movement everywhere else, and instructions on keeping pin sites clean and dry. Mild clear drainage early is common; increasing redness, discharge or a loose pin is not. Pins are removed in clinic once imaging shows healing, after which a fuller motion program begins.
Is it normal for hand therapy to hurt?
A pulling ache while stretching stiff joints or scar is expected and should fade within minutes of stopping. Pain that is sharp, lingers for hours, or leaves the hand more swollen the next day suggests the effort was too much. Report that pattern to your therapist so the program can be adjusted. Persistent, escalating pain with skin changes needs prompt medical review.
Why do I need therapy if the surgeon already fixed my hand?
Surgery repairs or releases a structure; it does not stop the body from forming scar and stiffness around it. In the crowded anatomy of the hand, healing tissue can glue tendons to their tunnels and shorten joint capsules within weeks. Guided motion, splinting and scar care steer that process. The operation creates the potential for a working hand; rehabilitation determines how much of it is realized.
Can I do hand exercises I found online instead of going to therapy?
Not safely without your team’s approval. Generic finger and wrist exercises can be harmless after one procedure and risky after another; a tendon repair and a carpal tunnel release call for nearly opposite approaches in the early weeks. Your therapist tailors movements to the structures actually operated on and checks your technique. Use online material only to supplement a plan your surgeon has agreed.
What is a hand therapist, and how is that different from a physical therapist?
A hand therapist is an occupational or physical therapist who has trained specifically in rehabilitation of the fingers, hand, wrist and forearm; some hold an additional certification. The skills overlap with general physical therapy but focus on splint fabrication, tendon and nerve protocols, fine motor retraining and scar management. The credential reflects extra experience with upper-limb anatomy rather than a different kind of care.
When can I drive after hand surgery?
Only when your surgeon agrees and you can grip the wheel, operate controls and react in an emergency without pain or a bulky splint interfering. The timing varies with the operation, the hand involved and whether you are taking medicines that affect alertness. Insurers may also have requirements. Ask the question directly at your follow-up visit rather than assuming a date.
What are the signs that something is wrong after hand surgery?
Cold, pale or blue fingers, new numbness, a dressing that feels tighter by the hour, spreading redness or discharge, fever, a loose or painful pin, a sudden snap and loss of finger movement after tendon repair, or escalating pain with shiny, sweaty, touch-sensitive skin. Any of these warrant a prompt call to the surgical team, or urgent care if they cannot be reached.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Is Arthritis Hereditary? (Osteoarthritis, Rheumatoid, Psoriatic)
Arthritis is partly hereditary, but no single type is passed down like eye color. Genes account for a meaningful share of risk in osteoarthritis,…

Why Dental Problems Are Treated Before Joint Replacement: Infection Risk and Implant Safety
Dental problems are usually treated before joint replacement because infected teeth and gums release bacteria into the bloodstream, and bacteria can settle on a…

Ankle Replacement Recovery: From Cast to Walking Boot to Full Weight-Bearing
Ankle replacement recovery time typically runs in stages: a cast or splint with no weight on the leg for the first few weeks, a…

Gout in the Knee: Yes It Happens, Here Is How It Looks
Yes, gout can affect the knee. The same uric acid crystals that usually settle in the big toe can collect inside the knee joint,…
Partial vs Total Knee Replacement: The Trade-offs Surgeons Actually Weigh
Partial knee replacement resurfaces only the damaged compartment of the knee, preserving healthy bone and both cruciate ligaments, which usually means a quicker recovery…

Swollen Knee and Fluid on the Knee: Causes and When to Worry
A swollen knee is usually not dangerous, but a few patterns are. Seek urgent care if the knee is hot, red, and very painful…