

What Does Retrograde Urethrography Show After a Pelvic or Straddle Injury?

Key Takeaways
- A retrograde urethrogram fills the urethra from its outer opening with X-ray contrast so a tear shows up as contrast escaping the tube, and a complete disruption as contrast that never reaches the bladder.
- Straddle falls crush the bulbar (anterior) urethra against the pubic bone, whereas pelvic fractures shear the membranous (posterior) urethra where it is anchored to the pelvic floor.
- Blood at the urethral opening, inability to urinate or a displaced prostate after trauma are the findings that prompt imaging before any blind catheter placement, because a catheter can turn a partial tear into a complete one.
- The single most consequential finding is whether the disruption is partial or complete, and sphincter spasm can imitate a complete block, which is why ambiguous films are often repeated or supplemented with a camera.
- A urethrogram examines the urethra; a cystogram examines the bladder, and after a pelvic fracture both are often needed because the two injuries can occur together.
- The test diagnoses but does not treat, and long-term follow-up for scar narrowing continues for months because a stricture can develop slowly after an apparently healed injury.
A retrograde urethrogram is an X-ray study in which contrast dye is gently instilled through the opening of the urethra so the whole tube shows up on the image. After a pelvic fracture or straddle injury, it shows whether the urethra is intact, bruised, partly torn or completely severed, where the damage sits, and whether contrast still reaches the bladder — information the trauma team uses before deciding how to drain the bladder.
A cyclist comes off the saddle and lands, hard, on the crossbar. A roofer falls two stories and arrives with a fractured pelvis. Different accidents, same quiet pause in the emergency bay: a nurse is about to place a bladder catheter, notices a bead of blood at the tip of the penis, and stops. Someone says the words retrograde urethrogram, and the patient — sore, frightened, needing to urinate and unable to — has no idea what that means.
It means, in short, that the team wants a picture before they push anything blind into a tube that may be torn. The urethra is only a few inches long, but the difference between a bruise, a partial tear and a complete disruption changes everything that happens next, from how the bladder is drained tonight to whether a repair operation is discussed in the months ahead.
This explainer walks through what the test involves, what the images can and cannot show, what it feels like, and which questions are worth asking while the dye is still on the film.
What is a retrograde urethrogram, in plain language?
The urethra is the tube that carries urine from the bladder out of the body. A retrograde urethrogram is an X-ray examination of that tube, taken while it is filled with contrast — a liquid that blocks X-rays and therefore appears bright white on the image. “Retrograde” simply means backwards: instead of following urine downstream from the bladder, the contrast is introduced at the outer opening and flows upstream toward the bladder, the opposite of the normal direction. MedlinePlus lists it as a standard test for suspected urethral injury and for narrowing of the urethra.
Think of a garden hose you suspect has split. You could turn on the tap and hope to spot a spray somewhere along the lawn, or you could fill the hose slowly from the nozzle end and watch for exactly where water escapes. The second approach is what a urethrogram does. Contrast that stays neatly inside a smooth-walled channel means the tube is intact. Contrast that spills into the surrounding tissue marks the tear. Contrast that stops dead and never reaches the bladder points to a complete break.
The examination is usually performed with fluoroscopy, a live X-ray that lets the radiologist watch the filling as it happens, though a series of plain films can also be used. It shows anatomy, not function: it tells the team what the channel looks like, not how well the bladder empties or whether nerves and blood supply are healthy. Those questions need other tests, which is why the urethrogram is best understood as the first, most urgent piece of a larger puzzle rather than the whole answer.
Why do pelvic and straddle injuries damage the urethra differently?
The male urethra is divided by clinicians into two regions, and the type of accident usually predicts which one is hurt. The anterior urethra runs through the penis and then widens into the bulbar segment, which sits low in the perineum, the area between the scrotum and the anus. The posterior urethra lies deeper: the short membranous segment passes through the muscular floor of the pelvis and the prostatic segment runs through the prostate to the bladder neck.

A straddle injury — a fall onto a bicycle frame, a fence rail, the edge of a bathtub — crushes the bulbar urethra upward against the underside of the pubic bone. The tube is pinched between a hard object outside and a hard bone inside, and it tears or bruises where it is trapped. Because the anterior urethra is close to the surface, blood often tracks into the skin of the perineum.
A pelvic fracture works by a different mechanism. The membranous urethra is anchored to the pelvic floor and the pubic bones; when those bones break and shift, the fixed segment is sheared while the more mobile prostate and bladder move away from it. MedlinePlus notes that trauma to the bladder or urethra most often accompanies pelvic fractures or straddle-type falls, and that the two injuries can coexist in the same patient.
The female urethra is shorter and more mobile, so it is injured far less often, usually only with severe pelvic disruption, and the same is true for girls. In children of either sex the anatomy is proportionally similar, and the same reasoning about mechanism applies, even though the test itself is adapted for smaller patients.
Blood at the tip and a full bladder: why the urethrogram comes before the catheter
Emergency teams live by a short rule: if there is a reason to suspect the urethra is torn, image it before you catheterize it. The reason is mechanical. A partially torn tube still has a bridge of tissue connecting the two ends. A catheter pushed blindly through that region can slip off the true channel, punch through the bridge and turn a partial tear into a complete one, or create a false passage in the surrounding tissue that later heals as scar.
So what makes a clinician suspicious? MedlinePlus describes the typical features of bladder and urethral trauma: blood at the urethral opening, blood in the urine, inability to pass urine, pain and swelling in the lower abdomen or perineum, and bruising over the injured area. On examination, a doctor may also find that the prostate feels displaced or cannot be reached in the usual position, a clue that it has been pulled away from the torn membranous urethra. None of these signs is proof of a tear, and none can be checked at home — they are prompts for the trauma team, not a self-assessment list.
The urgency is real but not frantic. Patients with pelvic fractures often have bleeding, other fractures and organ injuries that must be stabilized first. In that setting the urethrogram is fitted into the resuscitation sequence: it is quick, portable and can often be done on the trauma table. If the bladder is painfully full and the image cannot be obtained yet, the team may place a small drainage tube directly through the lower abdominal wall into the bladder, bypassing the urethra entirely, and image the urethra once the patient is stable.
How the retrograde urethrogram procedure actually happens, step by step
The test itself is mechanically simple, which is part of its value in an emergency. The patient lies on the X-ray table, ideally rolled slightly onto one side with the lower leg bent, so the urethra is not foreshortened and its full length is spread across the image. A first “scout” film is taken without contrast to record the bones, any foreign material and any pre-existing calcification.
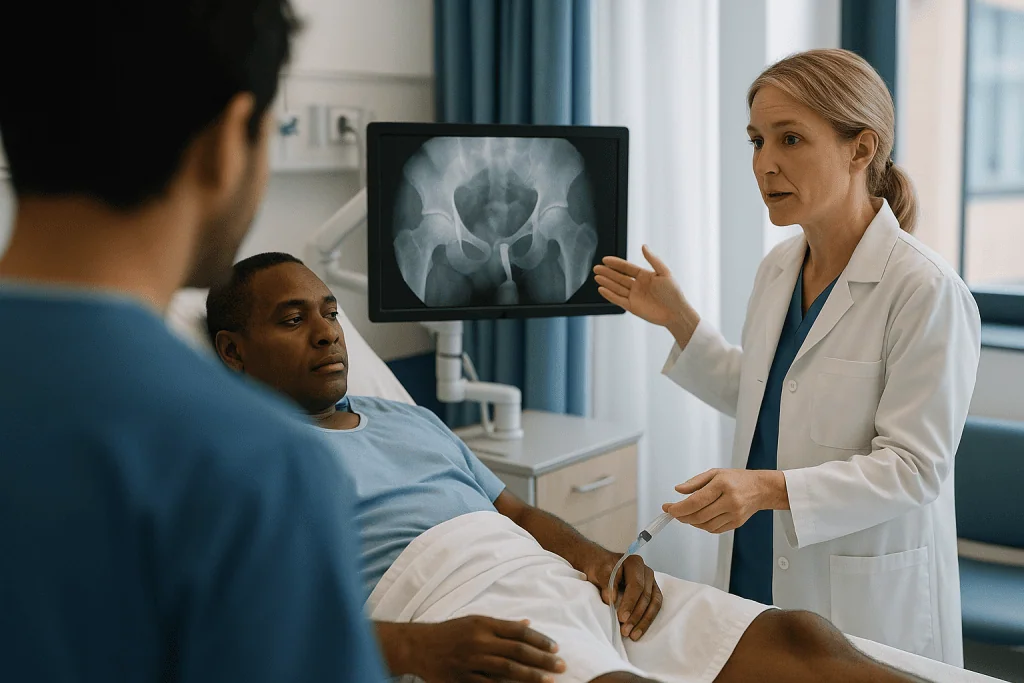
The area around the urethral opening is cleaned. A thin, soft catheter is placed just inside the opening, no more than a fingertip’s depth, and held in place either by gently inflating a tiny balloon within the first widened segment of the urethra or by a padded clamp. Some radiologists use a syringe with a cone-shaped tip pressed against the opening instead. Nothing is advanced deeper into the tube — the entire point is to avoid instrumenting the region that may be injured.
Water-soluble contrast is then injected slowly, by hand, while the radiologist watches on the fluoroscopy screen. Slow injection matters: it lets the contrast find its own way along the channel, shows the leading edge clearly and reduces the chance of forcing contrast into the veins around the urethra. Images are captured as the contrast advances, at the moment it reaches any narrowing or leak, and again when it enters the bladder or fails to.
From cleaning to final image, the study is typically a matter of minutes rather than hours, though the surrounding trauma care may take far longer. Children are usually examined with the same technique using smaller equipment, and a young child may be sedated so that the pictures are not blurred by movement — a decision the pediatric team makes case by case.
Is a retrograde urethrogram painful?
Most people describe pressure and an urgent need to urinate rather than sharp pain. MedlinePlus characterizes the experience as some discomfort when the catheter is placed and a sense of fullness as the contrast goes in. A lubricating gel, sometimes containing a local anesthetic, is commonly applied at the opening, and the catheter sits only in the first inch or so of the urethra, which is the least sensitive part to instrumentation.
That said, the honest answer depends on why you are having it. Someone having an elective urethrogram to check a suspected narrowing months after an injury usually finds the experience awkward and briefly uncomfortable, then forgettable. Someone lying on a trauma table with a fractured pelvis is already in significant pain from the fracture, the bruising and the distended bladder; the urethrogram itself rarely registers as the worst moment of that hour. Pain relief in that setting is directed by the trauma team according to the whole picture, and it is entirely reasonable to tell them if the injection is hurting so they can slow down or pause.
Two specific sensations are worth knowing about in advance. First, the contrast is at room temperature, and some people feel it as a cool trickle. Second, if the contrast reaches an area where the urethra is torn or inflamed, there can be a sting as it touches raw tissue — a useful signal to the radiologist, and one that fades within minutes as the contrast disperses.
Afterward, a mild burning with the first urination and a little pink tinge are common and expected, especially when there was already blood in the urine. Persistent or worsening symptoms are a different matter and are covered in the red-flag section below.
What the images show: reading urethral injury imaging
Radiologists and urologists describe post-traumatic urethrograms using a shared, descriptive language that grades the injury by how the contrast behaves. The table below summarizes the patterns most often reported.
| Pattern on the urethrogram | What it usually means | Why it matters for next steps |
|---|---|---|
| Smooth channel, contrast flows freely into the bladder, no leak | No injury or a contusion (bruise) without a tear | A urethral catheter can generally be considered by the team |
| Urethra appears stretched or elongated, no leak | Stretch injury without disruption | Often managed with cautious catheter drainage |
| Contrast leaks outside the tube and some still reaches the bladder | Partial disruption | Suggests a tissue bridge remains; drainage route chosen carefully |
| Contrast leaks outside the tube and none reaches the bladder | Complete disruption | Bladder usually drained through the abdominal wall; repair planned later |
| Leak at the bladder neck or the very top of the urethra | Combined injury involving bladder base or neck | Prompts bladder imaging and often earlier surgical involvement |
The location matters as much as the pattern. A leak in the bulbar segment after a straddle fall confirms an anterior injury; a leak at the level of the membranous urethra after a pelvic fracture confirms a posterior one, and the two heal and are repaired differently. Contrast that escapes into the veins around the urethra — appearing as fine white threads heading toward the pelvis — is a technique artifact from injecting too forcefully rather than a sign of injury, and an experienced reader will note it as such.
The distinction between partial and complete disruption is the single most consequential finding, and it can be genuinely difficult to make on one set of films. Muscle spasm at the sphincter can stop contrast from advancing even when the tube is intact, mimicking a complete tear. When the images are ambiguous, the team may repeat the study, add bladder imaging or use a flexible camera rather than commit to a diagnosis the pictures do not fully support.
Urethrogram vs cystogram: which test looks where
The two names are often spoken in the same breath, and patients understandably confuse them. A urethrogram fills the urethra from below and looks at the tube. A cystogram fills the bladder — through a catheter placed either along the urethra once it is known to be safe, or through the abdominal wall — and looks at the bladder itself for a rupture. Films are taken with the bladder full and again after it drains, because a small leak sometimes shows only on the emptied image.
After a pelvic fracture both organs are at risk, and MedlinePlus lists bladder rupture alongside urethral tears among the injuries these fractures cause. The sequence therefore runs: urethrogram first if the urethra is suspect; then, once a route into the bladder is established, a cystogram to check the bladder. In many trauma centers the bladder study is done on the CT scanner as a “CT cystogram,” which adds the ability to see the pelvic bones, the surrounding organs and whether leaked contrast lies inside or outside the abdominal lining — a distinction that shapes whether an operation is needed.
A third relative deserves a mention. A voiding cystourethrogram is an antegrade study: the bladder is filled and the patient is asked to urinate under fluoroscopy, so the contrast passes down the urethra in the normal direction. It is rarely used in the first hours after trauma, because it requires a bladder catheter and a patient able to void, but it becomes valuable later. The posterior urethra above a complete disruption cannot be seen from below; filling it from above, sometimes at the same sitting as a repeat retrograde study, lets the surgeon measure the gap between the two ends before planning repair.
Who is usually asked to have a retrograde urethrogram, and who is asked to wait
The test is generally reserved for people in whom a urethral injury is plausible on the basis of the accident and the examination. The classic candidates are men and boys with a pelvic fracture that involves the front of the pelvic ring, anyone with a straddle-type fall and perineal bruising, and any trauma patient with blood at the urethral opening, difficulty passing urine or a displaced prostate on examination. A penetrating wound to the perineum or lower abdomen that could have crossed the urethra also qualifies.
Outside the trauma setting, the same test is used months or years later to evaluate a suspected urethral stricture — a scar-narrowed segment that can follow a healed injury. Mayo Clinic and MedlinePlus both list the retrograde urethrogram among the standard studies for stricture, alongside urine flow measurement and a look with a flexible camera.
Who is asked to wait? First, anyone whose blood pressure is unstable or who is actively bleeding from the pelvis: resuscitation, control of bleeding and sometimes emergency pelvic stabilization come before any contrast study, and the bladder can be drained through the abdominal wall in the meantime. Second, people with a known severe allergy to iodinated contrast are discussed with the radiologist, though the risk from contrast placed into the urethra is generally considered lower than from contrast injected into a vein, because far less is absorbed. Third, someone with an active urinary infection scheduled for an elective study is often rescheduled, since pushing contrast up an infected tract can spread bacteria.
Women are imaged less often after pelvic fracture because urethral injury is less common, but a woman with blood at the urethral opening, vaginal bleeding from a pelvic fracture or inability to void is examined directly and may have the same imaging. The decision, in every case, rests with the treating team.
What should I avoid before a urethrogram, and how do you prepare?
In an emergency there is no preparation, and nothing you did or did not do beforehand affects the result. The team will ask what they need to know, and if you are able to speak the most useful things to volunteer are a history of contrast or iodine reactions, any blood-thinning medicines you take, and, for women of childbearing age, the possibility of pregnancy so the radiographer can shield and minimize exposure.
For a planned urethrogram — say, to assess a narrowing months after an injury — the list is short and mostly about information rather than restriction. MedlinePlus advises telling the provider about pregnancy, allergies and current medicines. Eating and drinking are usually unrestricted, because no sedation or intravenous contrast is involved; if a child is to be sedated, the pediatric team will give specific fasting instructions. You should not stop or alter any prescribed medicine, including blood thinners, on your own; the team will tell you if any change is needed and will make that decision themselves.
Things worth avoiding on the day are practical. Skip heavy creams or powders around the genital area, which interfere with cleaning. Empty your bladder shortly before the test if you are asked to; a full bladder is not needed for the retrograde study and can add to the discomfort. Wear loose clothing that is easy to remove from the waist down, and bring a list of previous urological procedures and surgeries, because prior instrumentation changes how the images are interpreted.
If you have an active urinary infection, fever or new burning on urination in the days before an elective study, call ahead. The department may prefer to treat the infection first and reschedule, since the test is not an emergency in that setting.
What the following days and weeks usually look like
The path after the film is read depends almost entirely on the pattern it shows. When the urethra is intact or merely bruised, a urethral catheter is commonly placed by the team — often by an experienced clinician, gently, sometimes over a guidewire — and left in place while the tissues settle. The catheter drains the bladder and acts as a stent, holding the bruised segment open as it heals.
When the urethrogram shows a partial disruption, practice varies. Some teams attempt a single careful catheter placement under direct vision; others prefer to avoid the injured segment altogether and drain the bladder through the abdominal wall with a suprapubic catheter. Either way, a repeat urethrogram is usual before any catheter is removed, injected alongside the tube — a “pericatheter” study — to confirm the leak has sealed.
A complete disruption is almost always managed initially with a suprapubic catheter. What happens next is one of the genuinely debated areas in urology. One approach is early realignment: within days, a catheter is passed across the gap using cameras from above and below, so that the two ends heal around it. The other is delayed repair: the suprapubic tube stays, the pelvis heals, and once bruising and scar have matured the urologist performs a urethroplasty, an operation that removes the scarred segment and rejoins the healthy ends. The timing of that operation is set by the surgical team according to the individual fracture and the surrounding injuries, not by a fixed calendar.
Whichever route is taken, MedlinePlus lists the same long-term issues to watch for: recurrent stricture, incontinence and erectile difficulty, the last two related more to the pelvic fracture itself and the nerves it damages than to the urethrogram or the repair. Follow-up imaging and flow tests continue long after the catheter is gone precisely because scar can narrow the channel slowly, over months, without early warning.
Risks, limits and alternatives: what a urethrogram can and can't tell you
The risks of the test itself are modest and worth setting out plainly. The urethra is briefly instrumented, so introducing bacteria and causing a urinary infection is possible, particularly if the tract is already injured. Contrast can enter the small veins around the urethra if injected forcefully; this is usually harmless but does expose the body to contrast, and it can blur the picture. Allergic reactions to contrast placed in the urethra are uncommon because little is absorbed, but they are not impossible, which is why allergy history is asked about. The radiation exposure is low and localized, and the radiographer shields the pelvis where the anatomy allows.
The limits are more important than the risks, and they are the reason a urethrogram is never the only test. It shows the channel but not the tissue around it, so bruising in the pelvic floor, injury to the erectile bodies and damage to nerves are invisible. It cannot reliably see above a complete disruption, since contrast never gets there. Sphincter spasm can imitate a block. A leak hidden by a large hematoma may be underestimated, and a small tear may be missed altogether if the contrast happens to flow past it.
The alternatives and complements fill those gaps. CT of the pelvis, usually already performed in major trauma, maps the bones, the bleeding and the bladder. Flexible cystoscopy — a slim camera passed along the urethra — lets the urologist see the lining directly and, if safe, guide a catheter into place. Ultrasound of the urethra, with the tube filled with saline instead of contrast, is used by some centers to measure the depth of scar around a stricture. MRI is reserved for complex reconstructions, where it can show the length of the gap and the position of the prostate before surgery. Which combination is used depends on the injury and on what is available in the moment.
What people often get wrong about retrograde urethrography
“The dye goes into my bloodstream.” It is meant to stay in the urethra. Only a small amount is absorbed unless the tube is torn or the injection is forceful, which is why contrast reactions are far less of a concern here than with an intravenous CT.
“If I can pass urine, my urethra can’t be torn.” A partial tear can leave a working channel, and some urine may pass through it. Being able to void is reassuring but not conclusive, which is why the team looks at the whole picture rather than one fact.
“The urethrogram fixes the problem.” It diagnoses; it does not treat. The catheter, the suprapubic tube and any later surgery are the treatment. Patients sometimes leave the X-ray suite expecting to feel better, and are disappointed when nothing has changed.
“Every pelvic fracture gets one.” Most pelvic fractures do not injure the urethra, and the test is chosen when the mechanism or the examination raises concern, not as a routine.
“It’s the same as a cystoscopy.” A cystoscopy passes a camera along the tube; a urethrogram passes only contrast. In a fresh injury the camera is often avoided precisely because it could worsen a partial tear.
“Women can’t injure the urethra.” They can, though far less often, and usually with severe pelvic disruption. The short female urethra is examined directly and imaged when there is concern.
“The catheter caused the injury.” In most cases the fracture or the fall did. The rule about imaging first exists to prevent a catheter from making an existing injury worse — a different thing from causing it.
“A normal film means nothing is wrong.” A normal urethrogram excludes a significant tear at that moment; it says nothing about the bladder, the pelvic nerves or the scar that may form later, all of which have their own follow-up.
Questions to ask your care team
Trauma moves quickly, and it is easy to leave the department with a catheter and no clear idea of what was found. These questions, asked when you or a family member has a moment with the team, help turn a set of films into a plan you understand.
- Did the urethrogram show a bruise, a partial tear or a complete disruption — and in which part of the urethra?
- Did the contrast reach the bladder? If not, is the team confident that this reflects a tear rather than spasm?
- Has the bladder itself been imaged, or is a cystogram still planned?
- How is my bladder being drained right now, and why was that route chosen over the alternative?
- Will a repeat urethrogram be done before the catheter comes out, and roughly what would you need to see on it?
- If the tear is complete, is the plan early realignment or delayed repair, and what factors in my case pushed you toward that choice?
- What symptoms after discharge would you want to hear about the same day?
- What is the long-term follow-up for narrowing, and how will you check for it — flow tests, imaging, a camera, or a combination?
- Could the pelvic fracture affect bladder control or sexual function, and who will follow those issues with me?
- Are any of my regular medicines affected by this injury or its treatment? (Do not change anything until the prescriber has answered.)
Write the answers down, or ask for them in the discharge letter. Injuries in this region are managed over months, sometimes by more than one specialist, and the person best placed to keep the story straight is often the patient.
When to call your doctor
After a urethrogram, a mild sting with the first urination and a faint pink tinge are expected, particularly when there was already blood in the urine from the injury. MedlinePlus and the NHS both note that visible blood in the urine should be assessed by a clinician, and after trauma that assessment is part of your ongoing care rather than an optional extra.
Contact the treating team the same day — or go to an emergency department — if you notice any of the following:
- Fever, shaking chills or feeling suddenly unwell, which can signal infection spreading from the urinary tract.
- Being unable to pass urine at all, or a catheter that stops draining despite drinking normally.
- Urine that becomes frankly red, passes clots, or grows darker rather than clearer over the hours after the test.
- New or rapidly increasing swelling or bruising of the perineum, scrotum, penis or lower abdomen.
- Severe or escalating pain in the pelvis or lower abdomen that is not controlled by the pain relief you were given.
- Any leaking of urine from the skin around a suprapubic tube site, or from a wound, that was not present before.
- Rash, facial swelling, wheeze or difficulty breathing, which can indicate a reaction to contrast and needs urgent care.
Weeks and months later, a different set of warning signs matters: a stream that becomes slower or thinner, straining to start, a feeling that the bladder never empties, or repeated urinary infections. Mayo Clinic lists these as the typical features of a developing urethral stricture. They are not emergencies, but they should prompt a call to the urology team rather than a wait for the next scheduled appointment — scar narrows gradually, and it is easier to manage when it is caught early. In every situation above, the treating team decides what happens next.
Frequently asked questions
Is a retrograde urethrogram painful?
Most people feel pressure and a strong urge to urinate rather than sharp pain. The catheter sits only in the first inch of the urethra, lubricating gel is used, and the test takes minutes. In a trauma setting the fracture and bruising usually hurt far more than the study itself. A brief sting can occur if contrast touches torn tissue, and mild burning with the first urination afterward is common and expected.
How is a retrograde urethrogram performed?
The patient lies slightly rolled to one side, the area is cleaned, and a thin catheter is placed just inside the urethral opening and held by a tiny balloon or clamp. Water-soluble contrast is injected slowly by hand while a radiologist watches on live X-ray, capturing images as the contrast advances, at any leak or narrowing, and when it reaches — or fails to reach — the bladder.
How much does a retrograde urethrogram cost?
We do not publish cost figures, because they vary widely with the setting, whether the test is part of emergency trauma care or an outpatient appointment, and how it is billed alongside other imaging. Your care team or the hospital’s patient services office can explain what applies to you. In an emergency the test is performed on clinical need, and the financial conversation happens afterward.
What should I avoid before a urethrogram?
For an elective study there are few restrictions: eating and drinking are usually allowed because no sedation or intravenous contrast is involved. Avoid creams or powders around the genital area, empty your bladder if asked, and tell the team about contrast allergies, pregnancy and every medicine you take. Do not stop any prescribed medicine, including blood thinners, unless the team tells you to. Call ahead if you have a urinary infection or fever.
What does contrast extravasation on a urethrogram mean?
Extravasation means contrast has escaped outside the urethra into the surrounding tissue, which is the direct sign of a tear. If some contrast still reaches the bladder, the tear is partial; if none does, the disruption is likely complete. Fine threads of contrast in nearby veins are a technique artifact from forceful injection rather than an injury, and an experienced reader distinguishes the two.
Why can't the team just place a catheter after a pelvic injury?
A partially torn urethra still has a bridge of tissue joining the two ends, and a catheter pushed blindly can slip off the channel, break that bridge or create a false passage that later scars. Imaging first tells the team whether a urethral catheter is safe or whether the bladder should be drained through the abdominal wall instead, avoiding the injured segment entirely.
What is the difference between a urethrogram and a cystogram?
A urethrogram fills the urethra from its outer opening and looks at the tube; a cystogram fills the bladder through a catheter and looks for a bladder rupture, often on a CT scanner. After a pelvic fracture both organs can be injured, so the urethrogram is usually done first and the cystogram follows once a safe route into the bladder is established.
Can women and children have a retrograde urethrogram?
Yes. Urethral injury is much less common in women and girls because the urethra is short and mobile, so the test is used less often, but it can be performed when a pelvic fracture raises concern. Children of either sex are examined with the same technique using smaller equipment, and young children may be sedated so movement does not blur the images; the pediatric team decides that individually.
Does a normal urethrogram mean nothing is wrong?
A normal study makes a significant urethral tear unlikely at that moment, but it says nothing about the bladder, the pelvic nerves, the erectile tissues or the scar that can form later. Someone with a pelvic fracture may still need bladder imaging and longer-term follow-up for bladder control and sexual function, which relate to the fracture rather than the urethra itself.
How much radiation does a urethrogram involve?
The exposure is low and confined to the pelvis, using brief bursts of fluoroscopy and a handful of stored images. Shielding is applied where the anatomy allows, and the radiographer keeps the imaging time as short as the study permits. Women who may be pregnant should tell the team beforehand so exposure can be minimized or an alternative approach considered; that decision rests with the clinicians.
References
- MedlinePlus — Retrograde urethrogram
- MedlinePlus — Traumatic injury of the bladder and urethra
- MedlinePlus — Urethral stricture
- NHS — Blood in urine
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Stress, Urge, Overflow or Mixed: How the Type of Urinary Incontinence Shapes Treatment
Urinary incontinence is grouped into four main types by what causes the leak: stress (pressure from coughing or lifting overwhelms the urethral seal), urge…
Phimosis vs Paraphimosis: Why One Is Managed Over Time and the Other Is Treated Urgently
Phimosis is a foreskin that cannot be pulled back over the head of the penis; it is normal in young boys and is usually…

Peritoneal Dialysis or Hemodialysis: Which Fits Your Life, Health and Home Setup?
For most people with kidney failure, peritoneal dialysis and hemodialysis are considered equally effective, so the choice usually rests on lifestyle, home setup and…
Why Do Bladder Stones Form? Retained Urine, Enlarged Prostate and What Treatment Fixes
Bladder stones usually form when the bladder does not empty fully, so leftover urine sits, concentrates and lets minerals crystallize. In adults the most…

What Happens in Testicular Torsion Surgery: Detorsion, Orchiopexy and Fixing Both Sides
Testicular torsion surgery is an emergency operation to untwist a spermatic cord that has cut off blood flow to a testicle. Under general anesthesia,…
How CT, Ultrasound and Urine Tests Shape a Kidney Stone Treatment Plan
A non-contrast CT scan is the most accurate single test for finding kidney stones and measuring their size and position, but it is not…