

What Happens in the Operating Room During Cataract Surgery, Minute by Minute
Key Takeaways
- The operative part of cataract surgery usually takes 30 to 45 minutes, and most people are awake with a numbed eye rather than under general anesthesia.
- The incision at the edge of the cornea is only a few millimeters wide and is angled to seal itself, so stitches are rarely needed.
- The lens's own transparent capsule is left in place to hold the new artificial lens, and haze in that capsule months or years later is treated with a brief laser procedure, not repeat surgery.
- Patients typically see bright, shifting light and colors during the operation, not instruments, because the microscope glare and dilated pupil wash out detail.
- The NHS estimates serious complications at around 1 in 50 cases and permanent sight loss at roughly 1 in 1,000, with most problems treatable.
- Vision often improves within days, but the eye continues settling for four to eight weeks, and a new glasses prescription usually waits until then.
During cataract surgery, a surgeon numbs the eye with drops or a small injection, makes an incision of a few millimeters at the edge of the cornea, opens the thin capsule holding the cloudy lens, breaks the lens up with ultrasound and suctions it out, then unfolds a clear artificial lens into the empty capsule. The procedure usually takes 30 to 45 minutes, most people stay awake, and the incision typically seals without stitches.
The pre-op nurse asks Margaret to tap the eye that is having surgery today. She points to her left, then hesitates, because for two years both eyes have looked at the world through a smear of petroleum jelly. Headlights bloom into starbursts. Her grandson’s face is a soft oval. She has read the leaflet twice, yet the one thing nobody has told her is what the next forty minutes will actually feel like from the inside.
That is the gap this article fills. Understanding what happens during cataract surgery, in the order it happens and roughly how long each step takes, turns an abstract operation into a sequence of small, knowable events. The evidence on this procedure is unusually deep because it is one of the most frequently performed operations in the world, so almost every question has a well-documented answer.
We will walk through it minute by minute, from the waiting-room drops to the plastic shield taped over your brow, and then through the weeks that follow.
What happens during cataract surgery, in one plain paragraph
A cataract is not a film that grows over the eye. It is the eye’s own lens, a clear disc about the size of a lentil that sits behind the colored iris, turning cloudy with age or injury. Surgery removes that cloudy lens and replaces it with a clear artificial one, called an intraocular lens or IOL. The Mayo Clinic describes the operation as typically taking an hour or less from the moment you enter the room, and the NHS puts the surgical part at 30 to 45 minutes; the difference is mostly set-up time.
The technique used in nearly all modern cases is phacoemulsification, which simply means using a vibrating ultrasound probe to break the lens into fragments small enough to suction through a tiny opening. Because the incision is only a few millimeters wide, it usually seals itself and needs no stitches, which is why the NHS describes the procedure as routine day surgery under local anesthetic. You are awake, the eye is numb, and you go home the same day.
What makes the operation elegant is that the surgeon leaves the lens’s own transparent wrapper, the capsule, in place. Think of the lens as an M&M: the surgeon opens a window in the front of the candy shell, removes the chocolate, and uses the remaining shell as a hammock for the new lens. That hammock is what holds the IOL centered for the rest of your life.
Everything in the sections that follow is a closer look at those three moves: open, remove, replace. The timings given are typical ranges from published patient guidance, not promises; your own surgeon may work faster or slower depending on how dense the cataract is and how your eye is built.
Before the operating room: drops, marking and the wait
The first hour belongs to the nursing team, and most of it happens in a chair, not on a table. According to MedlinePlus, you will usually have been told to skip food and drink for a set period beforehand if sedation is planned, and a nurse will check your name, date of birth and, crucially, which eye is being operated on. Expect an arrow or a dot to be drawn on your forehead or cheek above the correct eye. This marking is a universal safety step, not a sign of doubt.

Then come the drops. One set widens the pupil, because the surgeon needs the largest possible window to work through; a pupil that is normally three millimeters may open to seven or eight. The dilating drops take roughly 20 to 30 minutes to reach full effect, which is why you are asked to arrive well ahead of your slot. Another set begins numbing the surface of the eye. Some units also add a drop to reduce inflammation, as Cleveland Clinic notes in its overview of preparation. Your care team decides which drops you receive, and none of this involves you doing anything except tilting your head back.
Someone will confirm the power of the artificial lens chosen for you. That number came from measurements taken at an earlier visit, when a device bounced light or sound off the back of your eye to calculate its length and the curve of your cornea. The chosen lens is checked against your chart again in the room itself.
Finally, you are walked or wheeled into the operating room. It is cooler than you expect, brightly lit around the microscope and dim elsewhere, and there are usually four or five people: the surgeon, a scrub nurse, a circulating nurse, sometimes an anesthetist, and often a trainee.
Cataract surgery step by step: the first five minutes on the table
Minute zero. You lie flat, or nearly flat, on a narrow bed with a headrest shaped to cradle your skull. A pillow goes under your knees. If you have a bad back, say so now; the team can adjust the angle, and the position needs to be one you can hold still for half an hour.
Minute one. The anesthesia is confirmed. The NHS explains that cataract surgery is almost always done under local anesthetic, meaning the eye is numbed while you stay awake. There are two common routes. Topical anesthesia uses drops alone, sometimes with a numbing gel. The alternative is a small injection of anesthetic into the tissue beside or behind the eye, which also stops the eye muscles moving. Some patients are offered a mild sedative through a vein to take the edge off anxiety; it does not put you to sleep. General anesthesia is uncommon and reserved for people who cannot lie still, such as some children or adults with severe tremor or claustrophobia.
Minute two to three. The skin around the eye is cleaned with an antiseptic, usually an iodine-based solution that stings for a few seconds. A sterile drape is laid over your face with a window cut for the operating eye. Air is piped underneath so you can breathe comfortably, and the other eye is covered. This is the moment many people describe as the strangest, because your world shrinks to a small circle of light.
Minute four. A speculum, a small spring clip, is placed between the eyelids to hold them open. You cannot blink the operating eye, and you will not need to; the surface is kept wet with irrigation fluid throughout. The microscope light switches on, bright but not painful, and the surgeon asks you to look straight up at it.
Minute 5 to 8: the incision and the opening in the capsule
The surgeon now makes the main incision at the edge of the cornea, the clear dome at the front of the eye, where it meets the white. The blade is a fraction of the width of a fingernail, and the tunnel it creates is angled like a trapdoor so that internal pressure closes it from within once the instruments are withdrawn. Johns Hopkins Medicine describes this small-incision approach as the reason most patients need no sutures. A second, even smaller side port is often made about 90 degrees around for a supporting instrument.
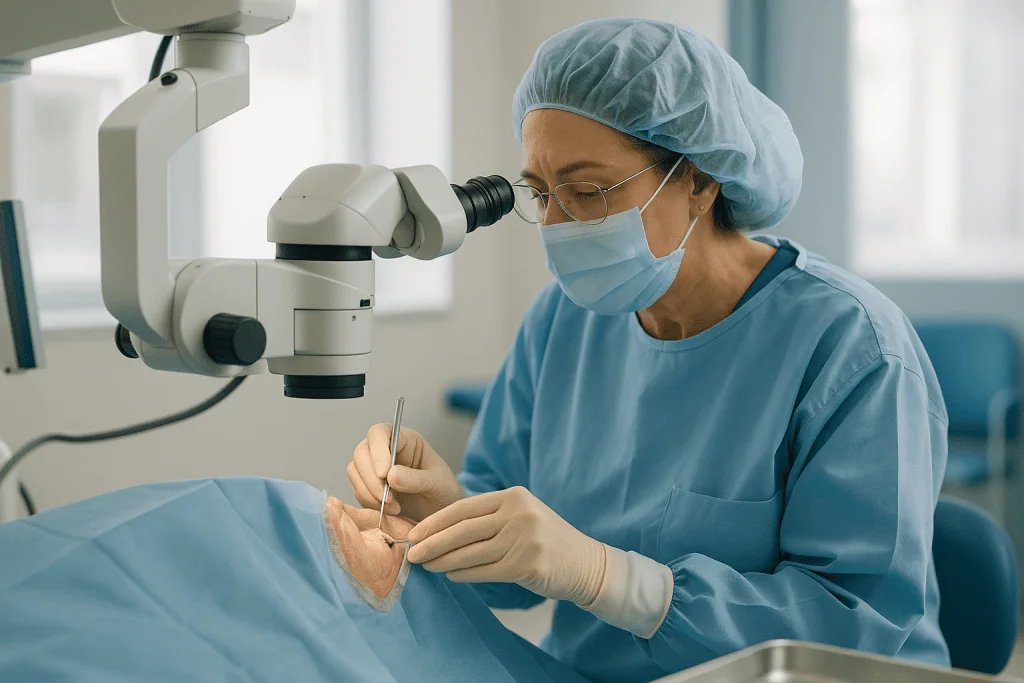
Next, a clear gel called viscoelastic is injected into the front chamber of the eye. Its job is to hold the space open and protect the delicate inner lining of the cornea from the instruments, much as packing foam protects a parcel. You may feel a faint sense of pressure here, but not pain.
Then comes the step surgeons consider the most technically important: the capsulorhexis. That word means tearing a controlled, circular opening in the front of the lens capsule, the cellophane-thin wrapper described earlier. Using fine forceps or a bent needle, the surgeon lifts a flap and guides it around in a circle roughly five millimeters across, about the size of a pencil eraser. A smooth, round edge is far stronger than a jagged one and will grip the new lens like a rubber band. In some units a femtosecond laser, a laser that fires in extremely short pulses, performs this circle and the initial incisions before the surgeon takes over; the NHS notes this is an option in some places, and it changes the sequence rather than the goal.
Finally, fluid is injected beneath the capsule edge to loosen the cloudy lens from its wrapper, a step called hydrodissection. The lens, which has been glued in place for decades, is now free to rotate.
Minute 8 to 15: breaking up and removing the cloudy lens
This is the phase that gives the operation its formal name. The phacoemulsification probe, a pen-sized handpiece with a hollow titanium tip, enters through the main incision. Its tip vibrates at ultrasonic frequency, tens of thousands of cycles per second, and that vibration turns the firm center of the lens, the nucleus, into an emulsion that the same tip suctions away. Irrigation fluid flows in continuously to replace what is removed, so the eye stays pressurized and its shape never collapses.
Surgeons rarely simply chew through the nucleus. Most divide it first. One common approach carves a deep groove across the lens, then cracks it into two halves, then into quarters, and removes each fragment in turn; the technique is often called divide and conquer. Another hooks the fragments apart with a second instrument in a method called chopping. Whichever is used, a soft cataract in a sixty-year-old may take three minutes; a dense, brown cataract in someone in their nineties can take twice that and needs more ultrasound energy, which is one reason the NHS gives a range rather than a single duration.
You will hear things. The machine chirps and changes pitch as the surgeon presses the foot pedal, and it beeps steadily as fluid flows. Many patients say the sound is more memorable than any sensation. You may notice a feeling of coolness from the irrigation, or a very light pushing, and the light in front of you may swirl.
Once the nucleus is gone, a gentler suction instrument removes the soft outer layer of the lens, the cortex, which clings to the inside of the capsule like the last of the yolk in an eggshell. The surgeon polishes the capsule, and what remains is a clear, empty bag ready for its new occupant.
Minute 15 to 20: placing the new lens
The intraocular lens arrives folded. Modern IOLs are made of soft acrylic or silicone and measure about six millimeters across the optic, the central disc that does the focusing, with two flexible arms called haptics that spring outward to hold it in place. Because the incision is smaller than the lens, the IOL is loaded into an injector that rolls it up like a tiny taco. The surgeon confirms the lens power against your chart aloud, a second check on the number calculated weeks earlier.
More viscoelastic goes in to reinflate the capsule. The injector tip passes through the incision, and the surgeon slowly advances a plunger. The lens unfurls inside the eye over a few seconds, the leading haptic sliding into the capsular bag first, and a fine hook then tucks the trailing haptic under the rim of the capsulorhexis. Watching this under the microscope is genuinely beautiful; from your side of the drape it registers as a shift in the light, sometimes a brief blur or a flash of color.
Which lens you receive was settled before today. A monofocal IOL, the standard option described by the National Eye Institute, focuses at one distance, usually far, and most people then use reading glasses. Multifocal and extended-depth-of-focus lenses split or stretch light to give a range of distances, at the cost of more nighttime halos for some people. Toric lenses correct astigmatism, an irregular corneal curve, and must be rotated to a precise axis, which the surgeon aligns now using marks placed earlier. None of these is universally better; the NEI is clear that the choice depends on your eyes, your habits and a conversation with your surgeon.
With the lens seated and centered, the surgeon suctions out the remaining viscoelastic. Leaving it behind can raise eye pressure overnight.
The last minutes: sealing, checking and the shield
The closing steps take three to five minutes. The surgeon injects a little fluid into the edges of the incision, swelling the corneal tissue so the tunnel presses shut. A dab of fluid on the surface is watched for leaks. If the wound does not seal cleanly, a single fine stitch may be placed; the NHS notes stitches are uncommon but occasionally needed. Many surgeons also place an antibiotic inside the eye at this point to lower infection risk; the drug class and whether it is used are decisions for the surgical team, not for this article.
The speculum comes out, the drape is peeled away, and you can blink again. A nurse tapes a clear plastic shield, or sometimes a pad, over the eye. The NHS advises wearing this at night for about a week to stop you rubbing the eye in your sleep.
| Phase | Typical timing | What you notice |
|---|---|---|
| Pre-op drops and checks | 30–60 minutes before | Blurring as the pupil widens |
| Positioning, anesthetic, drape | Minutes 0–5 | Cold antiseptic, a bright circle of light |
| Incision and capsule opening | Minutes 5–8 | Faint pressure, swirling light |
| Lens removal (phaco) | Minutes 8–15 | Machine sounds, coolness |
| Lens implant | Minutes 15–20 | Shift in light or color |
| Sealing and shield | Minutes 20–25 | Blinking returns |
Timings are typical ranges drawn from NHS and Mayo Clinic patient guidance and vary with cataract density and technique.
Recovery in the unit is short. You sit up, drink something, and a nurse reviews your drop schedule and warning signs. Most people leave within an hour, and MedlinePlus is explicit that you must not drive yourself home.
Is cataract surgery painful? What you actually feel
The honest answer is that pain is rare, but sensation is not. The NHS states that the procedure should not be painful because the eye is numbed, and this matches what most people report. What they do describe is a cluster of odd but tolerable feelings: a cool trickle of fluid, a sense of something pressing lightly, a dull ache behind the eye if an injection was used, and the peculiar awareness of not being able to blink.
Two moments account for most of the discomfort people remember. The first is the iodine antiseptic, which stings on the skin for a few seconds. The second is the injection, if you have one, which feels like a firm push and a brief sting around the eye socket. With topical drops alone there is no needle near the eye at all, though people with drops-only anesthesia are more likely to feel pressure during lens removal.
Anxiety amplifies every sensation, which is why sedation is offered in many units. It is worth saying that the sedative is light; you can answer questions and follow instructions. If something genuinely hurts during the operation, you should say so calmly. Surgeons can add more anesthetic through the side port within seconds, and they would rather pause than have you flinch. Do not raise your hand or move your head; speak.
Afterward, the eye typically feels gritty, itchy or watery, as though an eyelash is trapped, and it may ache mildly for a day or two. The Mayo Clinic notes that some discomfort for a couple of days is common and that it usually settles. Severe or worsening pain is different, and it belongs in the section on when to call your doctor.
What do you see during cataract surgery?
People fear they will watch a blade approach their eye. That does not happen, for two reasons. First, the microscope light is so bright, and the pupil so dilated, that the eye is flooded with glare; fine detail is lost the way it is when you glance at the sun. Second, the anesthetic and the removal of the lens itself change what the retina receives. The eye is still working, but what it reports is abstract.
What most people describe is light. A white or bluish glow that fills the field. As the surgeon works, that glow may swirl, dim, brighten or break into moving shapes, and the color often shifts, with pink, purple, gold or green appearing and vanishing. Some patients see faint shadows of instruments crossing the light, something like a hand passing in front of a lamp behind frosted glass. Others see nothing but brightness for the entire procedure. When the new lens goes in, a brief moment of surprising clarity is sometimes reported, then blur returns as fluid and gel fill the eye.
If you had an injection rather than drops, vision in that eye may be almost absent, because the nerve that carries sight can be temporarily quieted along with the nerves that control movement. This is expected and lifts over several hours.
You are asked to keep looking at the light, and this matters more than people realize. The eye follows the gaze, and a steady fixation gives the surgeon a stable target. If you feel an urge to look around, tell yourself the light is the whole job. Most people find that the abstract show of colors makes the time pass faster than expected; forty minutes rarely feels like forty minutes.
Who cataract surgery is usually for, and who is usually asked to wait
A cataract on its own is not a reason for surgery. The National Eye Institute frames the decision around function: the operation is offered when the cataract interferes with things you need or want to do, such as driving, reading, recognizing faces or managing stairs safely. Someone with a modest cataract who copes well with brighter lamps and an updated glasses prescription may reasonably be advised to wait, and waiting does not make the later operation riskier in most cases, though very dense cataracts require more ultrasound energy.
There is no age threshold. Cataracts most often affect people over 60, but they also occur in younger adults after injury, with diabetes, with long-term steroid use or with certain genetic conditions, and in infants, where surgery is more urgent because a cloudy lens can stop the visual pathway developing. Pediatric surgery follows a different pathway and is planned by specialist teams.
Some situations lead surgeons to pause. Active infection or inflammation on the eye surface is usually treated first. Uncontrolled blood pressure or blood sugar may prompt a delay so that healing is not compromised, a decision made jointly with your primary physician. People taking certain prostate or bladder medicines, alpha-blockers, are not asked to stop them, but the surgeon needs to know, because the drug class can make the iris floppy during surgery and the technique is adjusted accordingly. Blood thinners are usually continued for this operation, since bleeding risk is low, but again the surgeon and prescriber decide together.
Cataract surgery is also sometimes recommended when the cataract is not the main problem, for example to give a clear view of the retina for someone with diabetic eye disease, or to lower eye pressure in some forms of glaucoma. Each of those is a specialist judgment.
Cataract surgery recovery time: the following days and weeks
The first evening is blurry, watery and slightly disorienting, partly because the pupil is still dilated. Sleep with the shield on. By the next morning many people notice colors are brighter and edges sharper, though the eye may look red and feel scratchy. The NHS says most people can see well within a few days while the eye continues settling for four to six weeks; the Mayo Clinic gives complete healing at roughly eight weeks. Both are ranges, not deadlines.
You will be using drops, typically an anti-inflammatory and often an antibiotic, for several weeks. How often and for how long is set by your surgeon and printed on your discharge sheet; follow that sheet rather than anything you read here. Wash your hands before each drop and do not touch the bottle tip to the eye.
The NHS recovery guidance lists the practical rules most units share for the first week or two: no rubbing the eye, no swimming, no eye makeup, avoid getting soap or shampoo in the eye, avoid strenuous exercise and heavy lifting, and keep dust and wind out with sunglasses. Reading, screens and television are fine and do no harm, even if the eye tires quickly. Light housework and walking are encouraged.
Driving depends on meeting the legal vision standard, which for many people is possible within days but must be confirmed, ideally at your follow-up visit. A new glasses prescription usually waits until the eye has stabilized, often around the six-week mark, because the measurement drifts as swelling resolves. If your other eye still has a cataract, the imbalance between the two can be uncomfortable; the NHS notes the second eye is often scheduled some weeks after the first.
Risks, complications and alternatives in plain language
Cataract surgery has one of the best safety records of any operation, and it still carries risk. The NHS estimates the chance of a serious complication at around 1 in 50 and the risk of permanent sight loss at roughly 1 in 1,000, with most complications treatable by medicine or further surgery. Those figures are averages across all patients; your own risk depends on the health of your eye and your general condition, and your surgeon will discuss it before you sign consent.
The most common later problem is posterior capsule opacification, when the back wall of the capsule left in place turns hazy months or years afterward. Vision blurs again in a way that can feel like the cataract returning. It is not; the NEI explains it is treated in clinic with a brief laser procedure that opens a window in the haze. Other recognized complications include swelling of the cornea or retina, a temporary rise in eye pressure, a tear in the capsule during surgery that may require a different lens position, retinal detachment, and infection inside the eye, which is rare but serious. Dry eye symptoms are common for weeks and usually ease.
Alternatives are limited. No drop or medicine dissolves a cataract, and no diet or supplement has been shown to reverse one; the NIH Office of Dietary Supplements notes that antioxidant supplements have not been proven to treat existing cataracts. Non-surgical management means stronger lighting, magnifiers, updated glasses and anti-glare coatings, which can be entirely reasonable when the cataract is mild. The only other choice is timing: now, or later. That decision, including which lens type to implant, sits with you and your treating team after a discussion of your eyes and your daily life.
What people often get wrong about what happens during cataract surgery
The myths cluster around fear, and correcting them matters because unrealistic expectations are behind most of the disappointment people report afterward.
Myth: the eye is taken out of the socket. It is not, ever. The entire operation happens through an opening smaller than a grain of rice at the edge of the cornea, with the eye exactly where it always is.
Myth: you have to be put to sleep. Local anesthetic is the standard, as the NHS confirms, and being awake is safer for most older adults than general anesthesia.
Myth: lasers do the whole thing. Ultrasound removes the lens. A laser may assist with the incisions and capsule opening in some centers, and a different laser treats capsule haze later, but neither replaces the surgeon’s hands.
Myth: a cataract has to ripen before it can be removed. That was true decades ago with older techniques. Today a dense cataract is harder, not easier, to remove.
Myth: you will never need glasses again. The Mayo Clinic is direct that most people still use glasses at least some of the time, particularly for reading with a standard monofocal lens.
Myth: cataracts grow back. The lens is gone. Capsule haze can mimic recurrence and is treatable.
When people say they regret the operation, the reasons are rarely the surgery itself. They usually name a mismatch between the lens chosen and how they live, persistent halos or glare with premium lenses, dry eye that lingered longer than expected, a second eye left waiting so the two never matched, or simply not having been told that the first week would look blurry. Every one of those is a conversation to have before the day, which is why the next section exists.
Questions to ask your care team
The consultation before surgery is the moment you have the most influence over the outcome, because it is when the lens is chosen and expectations are set. Write your questions down; dilated eyes make reading difficult afterward.
- Which type of anesthesia are you planning for me, drops alone or an injection, and why?
- Will I be offered sedation, and does that change what I must do about eating beforehand?
- Which lens type do you recommend for my eyes, and what would I give up with each alternative?
- Do I have astigmatism, and if so how will it be handled?
- Do I have any features, such as a small pupil, weak lens supports or a very dense cataract, that make my operation more complex than average?
- Which of my regular medicines do you need to know about, and should any be paused or continued? (Do not change anything without the prescriber’s agreement.)
- What will my vision realistically be like on day one, at one week and at six weeks?
- Will I still need glasses, and for which tasks?
- When will my second eye be done, and how will I manage the imbalance in between?
- What exactly should I do about my drops, and what should I do if I miss one?
- Who do I call, at any hour, if something feels wrong, and what number do I use?
- When can I drive, work, exercise, and fly?
Bring someone with you if you can. Two sets of ears retain more, and that person may be the one driving you home and administering your drops on the first evening. If any answer is unclear, ask the surgeon to draw it. Eye surgeons tend to sketch well; they spend their days looking at cross-sections.
When to call your doctor after cataract surgery
Mild grittiness, watering, redness, light sensitivity and fluctuating blur are expected in the first week and usually improve day by day. A small number of symptoms are different in kind, and the NHS and Mayo Clinic both advise contacting your surgical team or emergency eye service promptly rather than waiting for a scheduled appointment if they appear.
- Pain that is severe, or that steadily worsens instead of easing, especially if pain relief you have been advised to use does not touch it.
- Vision that was improving and then gets noticeably worse, or a sudden loss of vision.
- Increasing redness of the eye, particularly with a discharge that is thick, yellow or green, or an eyelid that is swelling shut.
- A sudden shower of new floaters, flashes of light, or a dark curtain or shadow moving across part of your vision, which can signal a retinal tear or detachment.
- Nausea or vomiting with eye pain, which can accompany a sharp rise in eye pressure.
- Any blow or knock to the eye, however minor it seems, or a feeling that the wound is leaking.
Infection inside the eye, called endophthalmitis, is rare but progresses over hours, and the classic pattern is worsening pain, redness and blur within the first days. That combination should never wait until morning. Keep the emergency number you were given somewhere you can read it without glasses, on the fridge or in large type on your phone.
If you are unsure whether a symptom is normal, call anyway. Eye units field these calls every day and would far rather reassure ten people than miss one. Nothing in this article replaces the judgment of the team who operated on you; they know your eye, and every decision about your care belongs with them.
Frequently asked questions
How long does it take to recover from cataract surgery?
Most people see well within a few days, while the eye keeps settling for four to six weeks according to NHS guidance, and up to about eight weeks per the Mayo Clinic. Drops continue for several weeks, strenuous activity and swimming are usually restricted for a couple of weeks, and a final glasses prescription is measured once vision has stabilized. Your surgeon sets your own timeline.
How painful is a cataract operation?
Pain during the operation is uncommon because the eye is numbed with drops or an injection. People typically feel coolness, light pressure and the oddness of not blinking rather than pain. The antiseptic sting and, if used, the anesthetic injection are the moments most often remembered. Afterward the eye usually feels gritty or achy for a day or two; severe or worsening pain is a reason to call.
Can you see what is happening during cataract surgery?
Not in any detailed way. The microscope light and the widely dilated pupil flood the eye with glare, so most people perceive a bright glow that swirls, dims and changes color, sometimes with vague shadows of movement. If an injection anesthetic is used, vision in that eye may be almost absent for several hours. Nobody watches a blade approach; the eye cannot resolve that detail.
What are the top reasons patients regret cataract surgery?
Regret usually stems from expectations rather than the operation. Common themes are being surprised at still needing reading glasses, persistent halos or glare with multifocal lenses, dry eye that lingers, an unbalanced feeling while the second eye waits, and not being warned that the first week is blurry. Discussing lens choice and realistic day-one vision with your surgeon beforehand addresses most of these.
What is cataract surgery step by step?
The eye is numbed and cleaned, a drape and eyelid clip are placed, and a small incision is made at the corneal edge. A circular opening is torn in the front of the lens capsule, ultrasound breaks up the cloudy lens, fragments are suctioned out, and a folded artificial lens is injected into the empty capsule where it unfolds. The incision is sealed with fluid and a shield is applied.
Are you awake during cataract surgery?
Yes, in nearly all cases. Local anesthetic numbs the eye while you stay conscious, and a light sedative may be offered to ease anxiety without putting you to sleep. You are asked to look at the microscope light and keep still. General anesthesia is reserved for people who cannot lie still safely, such as young children or adults with severe tremor or claustrophobia.
What do you see during cataract surgery if you had an injection?
Often very little. An anesthetic injected beside or behind the eye can temporarily quiet the optic nerve along with the muscle nerves, so that eye may register only darkness or a dim glow for several hours. This is expected and wears off as the anesthetic clears. With drops-only anesthesia, people more often see shifting light and colors throughout.
How long does cataract surgery take from arrival to leaving?
Plan for two to three hours in the building. Dilating drops need 20 to 30 minutes to work, checks and consent take time, the operation itself typically runs 30 to 45 minutes per NHS guidance, and a short recovery period follows. Someone else must drive you home. Delays earlier in the day’s list can extend the wait, so bring something to listen to.
Does cataract surgery recovery time differ for the second eye?
The healing process is the same, but the experience often feels easier because you know what to expect and the two eyes finally match. The NHS notes the second eye is usually operated some weeks after the first, allowing the surgeon to check the first result and refine the lens calculation. Restrictions, drops and follow-up mirror the first operation.
Can a cataract come back after surgery?
No. The cloudy lens is removed entirely and cannot regrow. What can happen is posterior capsule opacification, a haze on the capsule left behind to support the new lens, which blurs vision months or years later and mimics a returning cataract. The National Eye Institute describes treatment as a quick laser procedure in clinic that opens a clear window in the haze.
References
- NHS: Cataract surgery, what happens
- NHS: Cataract surgery, recovery
- NHS: Cataract surgery, risks
- MedlinePlus: Cataract removal
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Injections, Laser or Surgery for Macular Diseases: How the Retina Team Picks a Path
Macular disease treatment depends on what is happening in the macula. Leaking new blood vessels and swelling are usually treated with repeated anti-VEGF eye…

How Tear Duct Irrigation and Imaging Confirm Where the Blockage Sits
A blocked tear duct test locates where tears stop draining rather than simply confirming that they overflow. An eye specialist usually starts with a…

Yellow Skin, Nausea and Blurry Hours After Eye Angiography: Expected Effects and Red Flags
After fluorescein eye angiography, a yellowish tint to the skin for a few hours, dark orange urine for about a day, brief nausea during…

Glasses, Contacts or Laser for Farsightedness: How the Decision Usually Unfolds
Farsightedness treatment options usually begin with glasses, which correct the focusing error with a convex lens and carry no medical risk. Contact lenses offer…
Massage, Probing, Stenting or DCR Surgery: How Blocked Tear Duct Treatment Is Chosen
Doctors choose blocked tear duct treatment by age, cause and where the blockage sits. In babies, most blockages open on their own, so gentle…

What the Pre-Laser Eye Tests Check: Corneal Thickness, Pressure and Prescription Stability
Tests before eye laser surgery measure how thick your cornea is, map its shape, check the pressure inside the eye, and confirm that your…