

What Ultrasound and OCT Show Before Retina Surgery and How the Images Shape the Plan
Key Takeaways
- OCT images the central retina in cross-section and shows whether the macula is on or off, which is the single finding that most shapes how urgently surgery is scheduled.
- B-scan ultrasound is chosen when blood, cataract or cloudy media block the view, because sound waves image through what light cannot.
- On ultrasound, a true retinal detachment stays anchored at the optic nerve and undulates, while a posterior vitreous detachment floats freely and does not insert there.
- A normal OCT does not exclude a peripheral tear, since most breaks begin at the retinal edge where OCT sees least; the dilated examination still matters.
- The position and number of retinal breaks on imaging help decide between laser, a gas bubble, a scleral buckle or vitrectomy, with the surgeon making the final call.
- A gas bubble left in the eye after surgery expands at altitude, so flying is unsafe until the surgeon confirms it has gone, which can take several weeks.
Before retina surgery, two imaging tests do most of the work. Optical coherence tomography (OCT) gives a cross-section of the retina, showing whether the central macula is lifted and how far fluid has spread. B-scan ultrasound maps the back of the eye when blood or cataract blocks the view. Together they help the surgical team judge urgency, choose between laser, gas, buckle or vitrectomy, and set expectations.
The waiting room is quiet except for the hum of a machine that looks like a pair of binoculars bolted to a desk. A man in his sixties sits with one eye dilated, trying to describe to his daughter what he saw that morning: a dark edge creeping up from the bottom of his vision, like a blind being drawn the wrong way. He is waiting for a retinal detachment scan, and he has already learned the word nobody wants to hear at an eye appointment.
What happens in the next hour is less mysterious than it feels. The technician will rest his chin on a bar and ask him to stare at a green dot. A few minutes later a probe coated in cool gel may be touched against his closed eyelid. Neither test hurts. Both produce pictures that a retina surgeon can read the way a builder reads a blueprint.
This article explains what those pictures show, why one test is sometimes chosen over the other, and how the findings steer the decisions about timing and technique that follow.
What a retinal detachment scan is actually looking for
The retina is the thin layer of light-sensing tissue lining the inside of the back of the eye, about as thick as a sheet of tissue paper. A retinal detachment happens when that layer peels away from the wall beneath it, which carries its blood supply. Deprived of oxygen and nutrients, the detached cells stop working, and if they stay lifted for long enough the loss can become permanent. That is why the NHS describes detachment as a medical emergency.
A retinal detachment scan, then, is not a single test but a set of questions the imaging must answer. Is the retina truly lifted, or is the patient describing something less serious, such as the jelly inside the eye shrinking away from the retina? If it is lifted, where is the break that let fluid underneath? How much of the retina is involved? Has the fluid reached the macula, the small central zone responsible for reading and recognizing faces? And is there anything else in the way, such as bleeding, that changes the plan?
Two tools answer most of these questions. Optical coherence tomography, or OCT, uses light waves to produce a cross-section of the retina with detail measured in thousandths of a millimeter. B-scan ultrasound uses sound waves to build a two-dimensional map of the whole back of the eye, even when the view through the pupil is blocked. The Mayo Clinic notes that ultrasound is the test reached for when bleeding inside the eye makes it hard to see the retina directly.
Neither test replaces the examiner. A dilated examination with a bright light and a magnifying lens remains the foundation. The scans add precision to what the clinician already suspects, and they create a record the surgical team can measure against after treatment.
Can a regular eye doctor tell if your retina is detached?
Often, yes. An optometrist or general ophthalmologist who dilates the pupil and examines the back of the eye can usually see a detached retina directly. It looks pale, wrinkled and slightly out of focus compared with the smooth orange surface around it, and it may ripple when the eye moves. The Mayo Clinic describes this dilated examination as the first step in diagnosis, with ultrasound added when the view is unclear.

The harder question is not whether a detachment is present but what kind it is and what caused it. Small retinal tears at the far edge of the retina can hide behind the iris and need a specialized lens or gentle pressure on the eyelid to bring them into view. A shallow detachment may be almost invisible without imaging. Fluid under the macula can be impossible to judge by eye alone, yet it is one of the most important facts for planning.
This is where referral matters. A community eye examiner who finds a tear or detachment will typically arrange same-day or next-day assessment with a retina specialist, who has access to OCT, wide-field ultrasound and the surgical options that follow. The NHS advises that anyone with sudden flashes, a shower of floaters or a shadow across their vision should seek urgent advice rather than waiting for a routine appointment.
What a regular eye doctor cannot do is decide the surgical plan. That sits with the retina team, and it depends on details that only the scans reliably provide: the exact location and number of breaks, the height of the detachment, the state of the vitreous jelly, and whether scar tissue has started to form on the retinal surface.
How an OCT scan for retinal detachment works, in plain language
Optical coherence tomography is often compared to ultrasound that uses light instead of sound. The machine sends a beam of near-infrared light into the eye and measures the tiny delays as that light bounces back from each layer of the retina. Software stacks those reflections into a cross-sectional image, so the retina appears as a series of colored or grayscale bands, each representing a different layer of cells.
For the patient, the experience is undramatic. You sit at the machine, rest your chin and forehead against supports, and look at a fixation target while the scanner sweeps across the back of the eye. Nothing touches the eye. The light is not bright enough to be uncomfortable. The Cleveland Clinic lists OCT among the standard tools used to assess the retina in suspected detachment.
What the surgeon sees is a profile of the retina in section. In a healthy eye, the layers lie flat against the pigment layer beneath, like floorboards on joists. In a detachment, a dark gap of fluid appears between the retina and that base. OCT shows how high the retina is lifted, how far the fluid extends, and whether the photoreceptors, the cells that actually detect light, have begun to lose their orderly structure.
OCT has limits. It images the central retina beautifully but struggles at the far periphery, where most tears begin. It needs a reasonably clear path for light, so dense cataract or blood in the vitreous degrades the picture. Very high, bullous detachments can rise beyond the depth the scanner captures. For those situations, the team turns to ultrasound.
How a B-scan ultrasound of the eye works when the view is blocked
B-scan ultrasound sends high-frequency sound waves into the eye and listens for the echoes. Dense structures such as the eye wall reflect strongly and appear bright; clear fluid such as the vitreous gel reflects almost nothing and appears dark. The result is a two-dimensional slice of the whole globe, from the lens at the front to the optic nerve at the back.
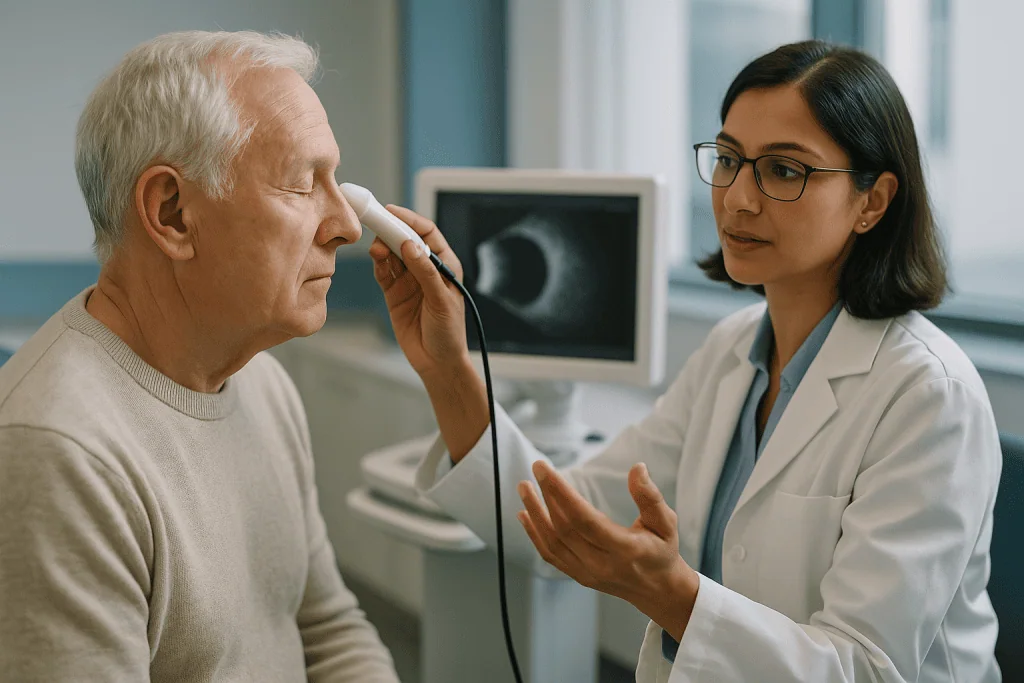
The test is done with the eyes closed. A small probe about the size of a marker pen is coated in gel and rested gently on the eyelid, then angled in several directions while you are asked to look up, down, left and right. Moving the eye matters because a detached retina behaves differently from other things that can float inside the eye. It tends to stay anchored at the optic nerve and at the front edge of the retina, so it undulates rather than drifts freely.
The Mayo Clinic explains that ultrasound is used specifically when bleeding has occurred in the eye and the retina cannot be seen directly. The same logic applies to a dense cataract, a cloudy cornea, or an eye too painful or swollen to examine.
Ultrasound also measures. The team can estimate how high the retina is lifted, how much of the circumference is involved, and whether the detachment is open and mobile or stiff and funnel-shaped from scar tissue. It can show a shrunken vitreous pulling on the retina, a lump beneath the retina that suggests a different diagnosis entirely, or thickening of the eye wall that points toward inflammation rather than a tear.
Resolution is the trade-off. Ultrasound cannot see the individual layers that OCT reveals, so the two tests are complementary rather than competing.
Retinal detachment vs PVD vs choroidal detachment on the scan
Three conditions produce similar symptoms and can look alike to an anxious patient, yet they call for very different responses. Imaging separates them.
Posterior vitreous detachment, or PVD, is the vitreous gel shrinking and pulling away from the retina with age. It causes flashes and floaters but, on its own, does not threaten sight. On B-scan it appears as a faint, mobile membrane floating in the vitreous, not attached at the optic nerve, that swirls freely when the eye moves. The National Eye Institute notes that PVD can occasionally tear the retina as it pulls away, which is why new floaters still deserve an examination.
A rhegmatogenous retinal detachment (the common type, caused by a break) appears as a brighter, thicker membrane that inserts into the optic nerve head and moves in a slower, wave-like way. On OCT it shows as a clear gap between the retina and the pigment layer.
Choroidal detachment involves the vascular layer beneath the retina lifting off the eye wall, usually after surgery, trauma or very low eye pressure. On ultrasound it appears as a smooth, dome-shaped, thick echo that does not reach the optic nerve and hardly moves.
| Finding | Posterior vitreous detachment | Retinal detachment | Choroidal detachment |
|---|---|---|---|
| Attachment to optic nerve | No | Yes | No |
| Mobility on eye movement | Free, swirling | Undulating, tethered | Minimal |
| Thickness on B-scan | Thin, faint | Thicker, bright | Thick, dome-shaped |
| OCT appearance | Gel lifting off flat retina | Fluid gap beneath retina | Elevation of layers beneath the retina |
| Usual urgency | Monitor, re-examine | Urgent repair | Treat the cause |
These distinctions change everything downstream, from whether surgery is needed at all to which operation is chosen.
Who is usually scanned urgently, and who is asked to wait and watch
Not everyone who hears the word detachment ends up in an operating room. The scans help sort people into pathways.
Urgent imaging and same-day specialist review are the norm for anyone with a sudden shadow or curtain in the field of vision, a sudden burst of many new floaters, flashes that persist, or a drop in vision that cannot be explained by something simpler. The NHS is explicit that these symptoms need urgent advice because the chance of protecting sight is better when treatment is not delayed.
People at higher background risk are also examined promptly when symptoms appear. The Mayo Clinic lists several risk factors: being very short-sighted, having had cataract or other eye surgery, a previous detachment in the other eye, a family history, eye injury, and certain thinning conditions of the peripheral retina.
Who is asked to wait? People whose scans show an uncomplicated PVD with no tear, no hemorrhage and no retinal elevation are commonly given safety advice and a follow-up appointment rather than treatment. The vitreous can continue to pull for several weeks after it first separates, so a repeat examination lets the team catch a late tear. Someone with a small, flat, asymptomatic area of peripheral thinning found on a routine examination may also be observed rather than treated, depending on the specialist’s judgment.
There is a third group: people whose detachment has clearly been present for months, perhaps with a visible line of pigment marking where fluid has sat for a long time. Here the imaging may suggest that urgent surgery offers less than careful planning does. The treating team weighs these factors individually; the scan informs the decision but does not make it.
How the images shape the surgical plan: laser, gas, buckle or vitrectomy
Once the scans confirm a break or a detachment, the surgeon is choosing among a small number of approaches. The Mayo Clinic describes four: laser or freezing treatment for a tear that has not yet detached, pneumatic retinopexy, scleral buckle, and vitrectomy. Imaging drives the choice.
A tear with no fluid underneath can often be sealed from outside with laser burns or a freezing probe, creating a ring of scar that welds the retina down. OCT confirming a flat retina around the break is what makes this the preferred option.
Pneumatic retinopexy means injecting a small gas bubble into the eye so it floats up and presses the retina back against the wall, after which the tear is sealed. It suits a single break or a cluster of breaks in the upper part of the retina, because the bubble rises. Ultrasound and examination that map the break to the upper clock positions, with no breaks below, point toward this option.
A scleral buckle is a silicone band stitched to the outside of the eye wall, indenting it so the wall meets the detached retina. It is often favored in younger eyes with an intact natural lens and breaks that are hard to reach from inside. Ultrasound showing a mobile, open detachment without heavy scarring supports this route.
Vitrectomy removes the vitreous gel through tiny ports, relieves traction, flattens the retina from inside, and fills the eye with gas or oil. Imaging that shows multiple or giant breaks, blood in the vitreous, scar membranes on the retinal surface, or a stiff funnel-shaped detachment tilts the decision this way. Which option is right is a judgment for the surgeon, who combines the pictures with the patient’s age, lens status and other health.
What the macula on OCT tells the team about timing
One line on the OCT report carries more weight than almost any other: macula on or macula off. The macula is the central few millimeters of the retina responsible for sharp, detailed vision. If the detachment has not yet reached it, the team speaks of a macula-on detachment, and the clock is running fast.
The National Eye Institute stresses that detachment should be treated quickly to protect vision. In practice, a macula-on detachment with fluid advancing toward the center is treated as among the most time-sensitive situations in eye surgery, because reattaching the retina before the macula lifts gives the best chance of preserving the central vision the patient already has.
OCT changes the conversation when the macula is already off. The scan shows how high the central retina is lifted and whether the fine architecture of the photoreceptor layer is still intact or has started to disorganize. It may reveal cystic spaces within the detached retina, a sign that fluid has been present for some time. These details help the surgeon counsel the patient honestly about what reattachment can and cannot restore. Reattaching the retina is the goal of surgery; how much detail returns to central vision depends on how long the macula was off and how much the cells recovered, which no scan can promise in advance.
OCT also shapes the hours before surgery. A patient with a macula-on detachment may be asked to rest with the head positioned so that gravity keeps the fluid away from the center. The scan tells the team which direction that is.
After surgery, the same scan becomes a yardstick. Repeat OCT shows whether the retina has settled flat, whether a thin film of fluid lingers under the center, and whether scar tissue is forming on the surface.
How long does a retina scan take, and what the appointment feels like
People often expect a retinal detachment scan to be lengthy or uncomfortable. The imaging itself is neither. The Mayo Clinic describes the diagnostic process as an eye examination with dilating drops, followed by ultrasound if the view is obscured; neither step involves needles or anesthesia beyond a numbing drop if the probe is placed directly on the eye.
What makes the visit feel long is everything around the pictures. Dilating drops need time to open the pupil, so there is a wait. Vision stays blurred and light-sensitive for some hours afterward, which is why the Mayo Clinic advises bringing someone to drive you home. You may be examined by a technician, then a doctor, then a specialist, each looking for something slightly different.
The OCT sits in the middle of this. You rest your chin on the machine, fix your gaze on a target, and hold still while the scanner passes. Blinking between scans is fine. If your central vision is too poor to see the target, the operator can guide you or use an external fixation light for the other eye.
B-scan ultrasound comes next if needed. You lie back or sit with eyes closed while gel-coated probe moves over the lid. The operator will ask you to look in different directions with your eyes shut, which feels odd but is painless. Expect the gel to be cool and slightly messy.
You may also have a wide-field photograph of the retina, a pressure check and a vision test with a letter chart. Ask the team at the start how many stations are planned, so the wait between them is less unsettling.
Is it worth getting a retinal scan if you have no symptoms?
This question comes up constantly, often prompted by an optometrist offering an OCT as an add-on to a routine eye test. The honest answer depends on who is asking.
For a healthy adult with no symptoms and no risk factors, there is no guideline from major health bodies recommending routine OCT or ultrasound to screen for retinal detachment. Detachment is uncommon in the general population, and the most reliable early warning remains symptoms: flashes, a burst of floaters, or a shadow. The MedlinePlus summary emphasizes recognizing these symptoms and seeking care fast, rather than periodic imaging.
For people at higher risk, the calculation shifts. The Mayo Clinic lists high myopia, previous cataract surgery, a detachment in the fellow eye, family history and prior eye trauma as factors that raise the odds. In these groups a dilated peripheral examination, sometimes with imaging, at regular intervals is often advised by the treating ophthalmologist, both to document any areas of thinning and to make later comparison easier. The specialist, not the scan, decides what interval makes sense.
There is also a case for a baseline OCT in people who already have another retinal condition, such as diabetic eye disease or age-related macular degeneration, because the central retina is monitored anyway and detachment would be easier to spot against a known reference.
What a routine scan cannot do is substitute for acting on symptoms. A normal OCT last year offers no reassurance about a shadow that appeared this morning. If you are offered a scan without symptoms, a reasonable response is to ask what specifically it would look for in your case, and what would change if it found something.
What the following days and weeks usually look like
The path after a retinal detachment scan branches depending on what the images showed.
If the scan shows PVD without a tear, the next weeks are mostly about vigilance. Floaters tend to settle or become less noticeable over time, and the team usually schedules a repeat dilated check because late tears can occur while the vitreous is still separating. The National Eye Institute advises returning promptly if new symptoms appear in that window.
If a tear was lasered or frozen, expect a mildly sore, light-sensitive eye for a day or two, then a review to confirm the seal has formed. The scar takes time to mature, so the surgeon may ask you to avoid strenuous activity until that check.
After surgery with a gas bubble, the first week is defined by positioning. You may be asked to keep your head in a specific posture for much of the day so the bubble presses on the right spot. Vision through gas is very blurred, and you will see the bubble as a dark, wobbling line that gradually shrinks. The NHS notes that you must not fly or travel to high altitude while gas remains in the eye, because the bubble expands under lower pressure; the gas can take several weeks to disappear. Your surgeon will tell you when it has gone.
After a scleral buckle, the eye is often more sore and red than after gas, and glasses may need updating later because the buckle slightly changes the eye’s length. After vitrectomy with oil, a second operation to remove the oil is usually planned months later.
Across all pathways, follow-up OCT and examination track whether the retina stays flat. Vision recovery is gradual and uneven; the team will describe what is typical for your situation rather than a fixed schedule.
What people often get wrong about retinal detachment scans
Myth: a clear OCT means the retina is fine. OCT sees the center superbly and the far periphery poorly, yet most tears start at the edge. A normal central scan does not exclude a peripheral break. That is why the dilated examination, with the examiner looking around the edges, remains essential.
Myth: ultrasound is the older, less accurate test. Ultrasound has lower resolution than OCT, but it does something OCT cannot: it images through blood, cataract and cloudy media. The Mayo Clinic describes it as the standard choice precisely in those situations. The two tests answer different questions.
Myth: floaters mean detachment. Most new floaters come from PVD, a normal age-related change that the National Eye Institute describes as common. Only a minority of PVDs tear the retina. Floaters still warrant an examination, but the scan is more likely to reassure than alarm.
Myth: once the scan is done, surgery is inevitable. A tear without detachment is often sealed with laser in the clinic. A PVD is watched. A chronic, stable, shallow detachment in a part of the retina that does not affect central vision is sometimes observed. Imaging opens options rather than closing them.
Myth: the scan predicts how well you will see afterward. OCT can show whether the macula is on or off and whether its structure looks preserved, which shapes expectations. It cannot forecast an individual’s final vision. Anyone promising a specific outcome from a scan is overstating what the picture shows.
Myth: eye pressure checks or routine photos catch detachment. Pressure measures fluid inside the eye, not retinal position. Standard retinal photographs capture the center. Neither replaces a dilated peripheral examination when symptoms appear.
Questions to ask your care team about the scan and the plan
A retinal detachment appointment moves quickly, and it is easy to leave with pictures you do not understand. These questions help you keep up with the team.
- Is my retina detached, torn, or is this a vitreous detachment only? Which test showed that?
- If detached, is the macula on or off? What does that mean for how soon you want to operate?
- Where are the breaks, and how many? Does their position rule any treatment in or out?
- Did the ultrasound show any bleeding, scar tissue or anything else that changes the approach?
- Which procedure are you recommending for me, and what about my scans led you there rather than the alternatives?
- What are the main risks of this approach for someone with my eye, and what are the risks of waiting?
- Will I have a gas bubble? If so, what head position do you need, for how long, and when will it be safe to fly or go to altitude?
- What should the next few days look like, and what would make you want to see me sooner?
- How will you check that the retina has stayed attached, and will I have repeat OCT?
- Is my other eye at higher risk, and should it be examined or imaged?
- Can I have a copy or printout of my scan for my records?
The Cleveland Clinic encourages patients to understand that treatment choice depends on the type and extent of detachment, which is exactly what these questions draw out. Writing the answers down, or having a companion do it while your eyes are dilated, is worth the small effort. Decisions about timing and technique rest with the treating surgeon, but you will carry out the positioning and the follow-up, and that works better when the reasoning is clear.
When to call your doctor: red-flag signs before and after surgery
Retinal detachment is one of the few eye problems where hours can matter. The NHS advises seeking urgent advice the same day for any of the following, whether you have had a scan before or not.
Before any diagnosis, call urgently if you notice a sudden increase in floaters, especially a shower of many small dark specks; flashes of light that keep coming, often in the edge of vision; a shadow, curtain or dark edge moving across part of your sight; sudden blurring or distortion of central vision; or any sudden loss of vision in one eye. These are the warning signs most often described, and they mirror the list given by MedlinePlus. Painlessness is not reassurance; detachment usually does not hurt.
After a scan that showed PVD only, the same symptoms returning or worsening mean the vitreous may have torn the retina since you were seen. Do not wait for the scheduled follow-up.
After laser, gas, buckle or vitrectomy, contact the surgical team promptly for: vision that is getting worse rather than slowly better; a new shadow or curtain, which may mean the retina has lifted again; increasing pain not controlled by what you were advised; a red, swollen or discharging eye; nausea or vomiting with eye pain, which can signal high pressure; or any new flashes or floaters. The Mayo Clinic notes that some people need more than one procedure, so a change after surgery is a reason to be seen, not a sign of failure to be endured quietly.
If you have a gas bubble and must travel urgently, call before any flight or mountain journey. If you cannot reach the eye team, an emergency department can examine you and contact the on-call ophthalmologist. Every decision about re-imaging or re-operating belongs to the treating team; your job is to make the call early.
Frequently asked questions
What are the 5 warning signs of a detached retina?
The five signs most often described are a sudden shower of new floaters, repeated flashes of light in the edge of vision, a shadow or curtain spreading across part of your sight, sudden blurring or distortion of central vision, and sudden loss of vision in one eye. Detachment is usually painless, so the absence of pain is not reassuring. Any of these warrants same-day urgent eye assessment rather than waiting for a routine appointment.
Is it worth getting a retinal scan if I have no symptoms?
For a healthy adult with no symptoms and no risk factors, major health bodies do not recommend routine imaging to screen for retinal detachment, because symptoms remain the most reliable early warning. People who are very short-sighted, have had cataract surgery, a detachment in the other eye or a family history may be offered periodic dilated examination, sometimes with imaging, at intervals set by their ophthalmologist.
How long does a retina scan take?
The imaging itself is brief and painless; OCT involves resting your chin on a machine while a scanner sweeps the retina, and B-scan ultrasound involves a gel-coated probe on the closed eyelid. The appointment feels longer because dilating drops need time to work and vision stays blurred for some hours afterward. Bring someone to drive you home, and ask the team at the outset how many steps are planned.
Can a regular eye doctor tell if your retina is detached?
Usually yes; an optometrist or general ophthalmologist who dilates the pupil can often see a detached retina directly. What they may not be able to determine is the exact location and number of breaks, whether the macula is involved, or whether scar tissue is present. Those details come from OCT, ultrasound and a specialist examination, so a community eye doctor who suspects detachment will arrange urgent referral to a retina team.
What does an OCT scan for retinal detachment actually show?
OCT produces a cross-section of the retina using light waves, showing the individual layers in fine detail. In a detachment it reveals a gap of fluid between the retina and the pigment layer beneath, how high the retina is lifted, whether fluid has reached the macula, and whether the light-sensing cells still look structurally intact. After surgery, repeat OCT confirms whether the retina has settled flat.
When is an eye ultrasound used for the retina instead of OCT?
Ultrasound is used when the view through the pupil is blocked, most often by bleeding inside the eye, a dense cataract or a cloudy cornea. Sound waves pass through these obstacles where light cannot. It also captures the whole globe, including the far periphery and very high detachments that OCT cannot reach. The two tests are complementary: OCT for fine central detail, ultrasound for the overall map.
How does a B-scan ultrasound of the eye tell detachment from a vitreous detachment?
The examiner watches how the membrane behaves when you move your eyes. A detached retina stays anchored at the optic nerve, appears relatively thick and bright, and moves in a slow wave. A posterior vitreous detachment is thinner, fainter, does not insert at the optic nerve, and swirls freely. Choroidal detachment, a third possibility, appears as a thick smooth dome that barely moves and does not reach the nerve.
Does the scan decide which retinal surgery I will have?
The scan informs the decision but does not make it. The surgeon combines the imaging, which shows the number and position of breaks, the extent of detachment, the state of the vitreous and any scar tissue, with your age, whether you still have your natural lens, and your general health. Laser alone, a gas bubble, a scleral buckle or vitrectomy may each be appropriate in different situations, and the choice rests with the treating team.
Why does the macula being on or off matter so much?
The macula is the central zone of the retina responsible for detailed vision. If the detachment has not yet reached it, surgery is treated as highly time-sensitive, because reattaching before the macula lifts gives the best chance of preserving the central sight you already have. If the macula is already off, OCT helps the surgeon judge how its structure looks and counsel you about what reattachment may and may not restore.
Can I fly after a retinal detachment scan or surgery?
After a scan alone there is no imaging-related restriction, though you should not travel with untreated symptoms. After surgery with a gas bubble, flying and travel to high altitude are unsafe until the gas has fully gone, because the bubble expands under lower cabin pressure and can raise eye pressure dangerously. Health services note this can take several weeks; your surgeon will confirm when the bubble has disappeared.
References
- NHS: Detached retina (retinal detachment)
- National Eye Institute (NIH): Retinal detachment
- MedlinePlus: Retinal detachment
- Cleveland Clinic: Retinal detachment
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
How a Custom Prosthetic Eye Is Made and Fitted: Impressions, Color Matching and Final Checks
A custom prosthetic eye is usually made by an ocularist over several visits, typically starting around six to eight weeks after eye removal surgery…

How a Vitrectomy Is Performed: Tiny Ports, Removing the Gel and Repairing the Retina
A vitrectomy is performed through three tiny ports in the white of the eye, usually under local anesthesia with sedation. The surgeon inserts a…

Questions to Ask Before Laser Treatment for Farsightedness (and What the Answers Mean)
Before laser treatment for farsightedness, ask your care team which procedure they propose and why, how high and how stable your prescription is, how…

How Eye Muscle Surgery for Strabismus Works: Loosening, Tightening and Adjustable Sutures
Strabismus surgery realigns the eyes by repositioning one or more of the six small muscles attached to the outside of each eyeball. A surgeon…

How Laser Treatment Corrects Myopia: Flattening the Cornea to Refocus Distant Objects
Laser treatment corrects myopia by reshaping the cornea, the clear front window of the eye. In a nearsighted eye, light focuses in front of…

Is Super LASIK Only for Complex Prescriptions? Who Actually Benefits From Custom Treatment
No. Custom or wavefront-guided LASIK, often marketed as Super LASIK, is not reserved for complex prescriptions. It uses a detailed optical map of each…