

When Is Radioiodine Treatment Chosen for an Overactive Thyroid Over Tablets or Surgery?
Key Takeaways
- Radioiodine is most often chosen when Graves' disease relapses after a 12–18 month course of antithyroid tablets, when a toxic nodule or multinodular goiter is the cause, or when the tablets cause a serious reaction.
- Iodine-131 emits short-range beta radiation that travels only a millimeter or two, so the thyroid takes the damage while nearby tissue is largely spared.
- According to Mayo Clinic, symptoms usually subside within several months of radioiodine, and most people who have the treatment eventually develop an underactive thyroid managed with daily hormone replacement.
- Radioiodine is never given in pregnancy or during breastfeeding, and the NHS advises women to avoid conceiving for at least 6 months and men for at least 4 months after treatment.
- Radioiodine can worsen thyroid eye disease, so people with active moderate to severe eye involvement are usually steered toward tablets or surgery, and smokers are urged to stop.
- Surgery remains a mainstream choice when a goiter is large enough to compress the airway or gullet, when a nodule looks suspicious, or when both tablets and radioiodine are unsuitable.
Radioiodine is usually chosen for an overactive thyroid when antithyroid tablets have not kept the condition controlled, when hyperthyroidism returns after a course of tablets, when a toxic nodule or multinodular goiter is the cause, or when someone cannot take the tablets safely. It is generally avoided in pregnancy, breastfeeding and active moderate to severe thyroid eye disease; the treating team weighs each case individually.
She had come in expecting a prescription refill. Instead, the endocrinologist slid a sheet across the desk with three columns on it: tablets, radioiodine, surgery. Eighteen months of medicine had settled her racing heart and the tremor in her hands, and then, four months after the last tablet, the old restlessness crept back. Now she was being asked to choose, or at least to help choose.
That conversation happens in thyroid clinics every week, and the radioactive iodine vs antithyroid medication question sits at the center of it. Each option quiets the same overactive gland by a different route: one by blocking hormone production for a while, one by shrinking the tissue that makes it, one by removing the gland altogether.
None of the three is universally better. What matters is why the thyroid is overactive, what else is going on in a person’s life and body, and what they are willing to trade for the prospect of not thinking about their thyroid every day.
Radioactive iodine vs antithyroid medication vs surgery: what are the three paths?
Hyperthyroidism means the thyroid gland, the butterfly-shaped organ at the base of the neck, is releasing more thyroid hormone than the body needs. That excess speeds up nearly everything: heart rate, digestion, heat production, the turnover of bone. Left unmanaged it strains the heart and thins the skeleton, which is why the condition is treated rather than simply watched.
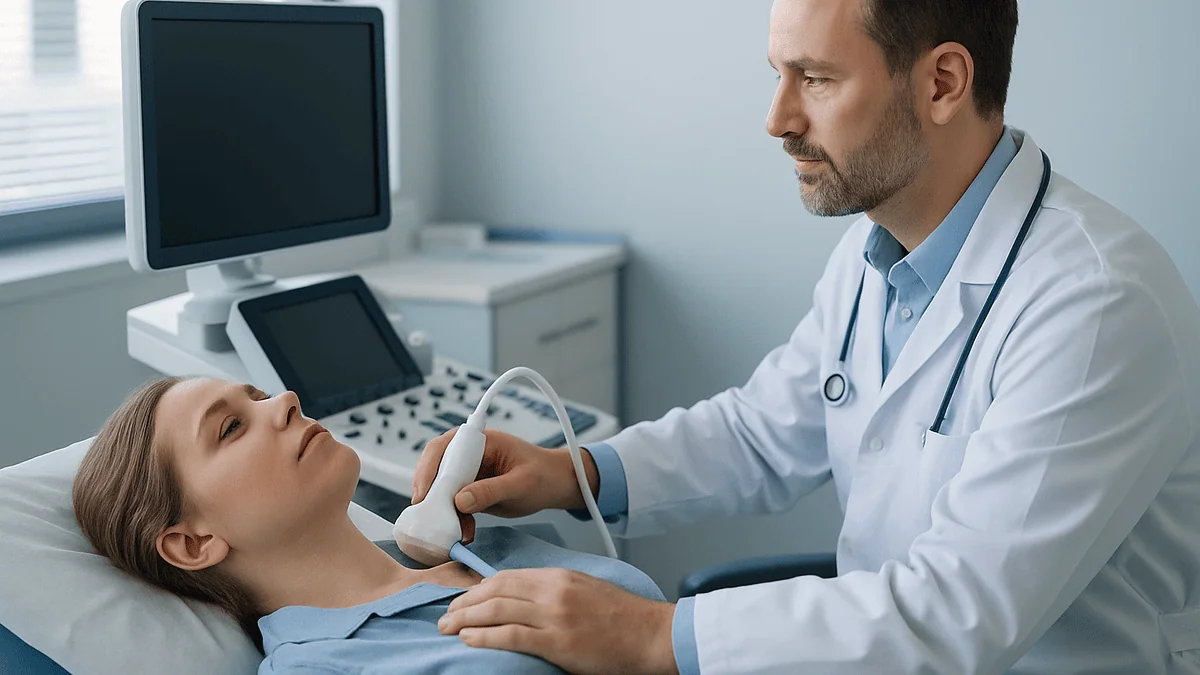
Three established treatments exist, and mainstream sources such as the NHS and Mayo Clinic describe them in the same terms. Antithyroid medicines, a class of drugs called thionamides, slow the gland’s hormone factory without changing the gland itself. Radioiodine, taken by mouth as a capsule or liquid, is absorbed by thyroid cells and damages them from within so they make less hormone over the following weeks and months. Surgery, called thyroidectomy, removes all or most of the gland.
The three differ in reversibility. Tablets can be stopped and their effect fades; radioiodine and surgery are permanent. They also differ in speed: tablets begin to ease symptoms within weeks, radioiodine takes months to reach its full effect, and surgery works immediately once the gland is out.
Specialists tend to frame the choice around three questions. What is driving the overactivity: Graves’ disease, an autoimmune condition where antibodies switch the gland on, or one or more nodules that have become autonomous? Is there any reason a particular option is unsafe for this person right now? And what does the patient want, given that each route has consequences they will live with for years?
The rest of this article walks through those questions one at a time, beginning with what radioiodine actually does inside the body.
How does radioiodine treatment actually work?
The thyroid is the only tissue in the body that actively pulls iodine out of the bloodstream, because iodine is a building block of thyroid hormone. Radioiodine treatment borrows that habit. A radioactive form of iodine, usually iodine-131, is swallowed and travels to the gland, where the cells absorb it just as they would iodine from food.

Once inside, the isotope emits short-range beta radiation that travels only a millimeter or two through tissue. That short reach is the point: the radiation damages the thyroid cells that took it up while sparing the structures beside them. Over the following weeks those cells stop dividing and slowly lose the ability to make hormone. The gland often shrinks noticeably.
Because the effect builds gradually, most people notice little on the day itself. According to Mayo Clinic, symptoms usually subside within several months of treatment, and the NHS notes that most people need only one treatment, although a second can be given if the first does not bring hormone levels down enough.
Overactive tissue tends to take up more iodine than quiet tissue. In a toxic nodule, the nodule soaks up the isotope while the surrounding, suppressed gland takes up very little. That is one reason radioiodine is often favored for nodular disease: the treatment finds its target.
The same principle is used, at higher activity, to treat some thyroid cancers after surgery, which is why the therapy sits within nuclear medicine and cancer services in many hospitals. The preparation, precautions and follow-up for benign hyperthyroidism are simpler, but the underlying idea is identical: let the thyroid’s own appetite for iodine deliver the treatment.
What do antithyroid tablets do, and how long is a typical course?
Thionamides, the antithyroid drug class that includes carbimazole, methimazole and propylthiouracil, work by blocking an enzyme the thyroid uses to attach iodine to hormone precursors. Hormone production slows within days; because circulating thyroid hormone lingers, symptoms typically begin to ease over the following weeks. Mayo Clinic describes improvement usually beginning within several weeks to months.
For Graves’ disease, the NHS and Mayo Clinic both describe a standard course lasting roughly 12–18 months, after which the medicine is withdrawn to see whether the immune system has quietened. Some people stay in remission. Many do not: hyperthyroidism returns, sometimes within months, sometimes years later. It is that relapse that most often triggers the conversation about permanent options.
Tablets are frequently used in another role too: as a bridge. Someone heading for surgery is usually brought to normal hormone levels first, because operating on a thyroid in overdrive carries a higher risk of a dangerous surge in hormone during or after the procedure. People with severe symptoms may also take tablets for a period before radioiodine so that the gradual effect of the isotope does not leave them unwell for months.
Two clinical patterns matter for the choice. First, long-term or lifelong antithyroid medicine is an option some specialists now offer, particularly for people who prefer to avoid permanent treatment and whose disease is easily controlled on a low maintenance regimen. Second, because the drugs affect the whole body, they carry their own uncommon but serious risks, especially a sharp fall in white blood cells known as agranulocytosis, which the NHS notes occurs rarely, and liver injury. A person who has reacted badly to one thionamide is generally steered toward radioiodine or surgery rather than another tablet in the same class. Any change to a prescription is a matter for the prescriber.
Antithyroid drugs vs surgery: when is a thyroidectomy chosen instead?
Surgery is the least common of the three routes for benign hyperthyroidism, but there are situations in which it is the clearest answer. The gland may be so large that it presses on the windpipe or gullet, causing breathlessness lying flat or difficulty swallowing; radioiodine shrinks a goiter only partially and slowly, whereas removal relieves pressure at once. A nodule may look suspicious on ultrasound or biopsy, and an operation both treats the overactivity and answers the question of what the lump is.

Surgery is also chosen when radioiodine is unsuitable and tablets have failed or are not tolerated. Pregnancy is the classic example: radioiodine is never given during pregnancy, and if tablets cannot control the condition, an operation, usually planned for the middle trimester, is the fallback. Active moderate to severe thyroid eye disease is another, since radioiodine can worsen it, as the NHS cautions.
Some people simply want the fastest, most definite resolution and are willing to accept an operation and a scar to get it. Mayo Clinic lists thyroidectomy as an option for those who cannot take antithyroid medicine and do not want radioiodine.
The trade-offs are specific to the neck’s anatomy. The nerves that move the vocal cords run just behind the gland, and the four tiny parathyroid glands that regulate calcium sit on its back surface. Injury to either is uncommon in experienced hands but can be permanent, leaving a hoarse voice or a need for lifelong calcium and vitamin D supplements. General anesthesia carries its own small risks.
After a total thyroidectomy, thyroid hormone replacement is not a possibility but a certainty. That predictability is, for some, a feature rather than a drawback: there is no waiting to see whether and when the gland will fail.
Who is radioiodine usually for, and who is usually asked to wait?
Guideline-level sources converge on a recognizable profile of the person for whom radioiodine is a first-line or early choice. Someone whose Graves’ disease relapsed after a full course of tablets. Someone with a toxic multinodular goiter or a single toxic nodule, where the NHS notes radioiodine is often used because nodular disease rarely goes into remission on medicine alone. Someone who developed a serious reaction to a thionamide. Someone older, or with heart disease, for whom the cardiac strain of repeated relapses is a real hazard and a permanent solution is attractive. And someone who, having heard the options, prefers a single treatment to years of tablets and blood tests.
Equally well defined are the people asked to wait or to choose differently:
- Anyone who is pregnant or breastfeeding. Radioiodine crosses the placenta and enters breast milk, and it would destroy the baby’s developing thyroid. A pregnancy test is routine immediately before treatment.
- Anyone planning a pregnancy soon. The NHS advises women to avoid becoming pregnant for at least 6 months after treatment and men to avoid fathering a child for at least 4 months.
- People with active moderate to severe thyroid eye disease, discussed in its own section below.
- People who cannot follow radiation precautions for practical reasons, such as sole carers of very young children with no one to help for the required days.
- People with a very large goiter causing compression, or a nodule with worrying features, where surgery answers more questions.
Children and adolescents are a separate conversation. Tablets are generally tried first, and definitive treatment is discussed with pediatric endocrinologists who weigh long-term considerations that differ from adult practice.
None of these categories is absolute. A specialist will sometimes recommend radioiodine to someone with mild eye disease under steroid cover, or tablets to an older person with a nodule. The lists describe the usual starting point, not the ending.
Radioactive iodine vs antithyroid medication: risks and trade-offs side by side
A single table cannot capture every nuance, but it does make the shape of the decision visible. The entries below reflect descriptions in the NHS, Mayo Clinic and NIDDK patient resources rather than any single trial.
| Feature | Antithyroid tablets | Radioiodine | Surgery |
|---|---|---|---|
| How it controls hormone | Blocks hormone synthesis while taken | Damages thyroid cells so they make less hormone | Removes the gland |
| Speed of effect | Weeks | Months to full effect | Immediate |
| Reversible? | Yes | No | No |
| Chance the problem returns | Relapse common after stopping (Graves’) | Low; second treatment sometimes needed | Very low after total removal |
| Lifelong thyroid hormone likely? | No, unless overtreated | Yes for most people eventually (Mayo Clinic) | Yes after total thyroidectomy |
| Main serious risks | Agranulocytosis (rare), liver injury, rash | Worsening of eye disease, transient neck soreness, hypothyroidism | Voice nerve injury, low calcium, anesthesia, scar |
| Pregnancy | Usable with specialist oversight | Not given; delay conception afterward | Possible in mid-pregnancy if essential |
| Special precautions | Blood tests, awareness of infection signs | Radiation safety for days to weeks | Hospital stay, wound care |
Read across the rows and a pattern emerges. Tablets buy time and preserve options at the price of uncertainty. Radioiodine trades a period of radiation precautions and a probable future of hormone replacement for a good chance of settling the problem with one outpatient visit. Surgery offers the most certainty and the most invasive route to it.
The row that people underestimate is the fourth one. Roughly speaking, the more definitive the treatment, the more likely the outcome is an underactive rather than a normal thyroid. Whether that counts as a drawback depends on how a person feels about a daily replacement tablet versus the alternative of unpredictable relapses.
How long does radioactive iodine take to work, and what do the first weeks look like?
The treatment visit itself is brief and undramatic. A nuclear medicine team confirms identity, checks a pregnancy test where relevant, reviews the precautions, and hands over a capsule or a small drink. Most people are home within an hour or two. There is no anesthetic, no needle beyond a possible blood test, and nothing to feel as the isotope goes down.
The days that follow are mostly about keeping distance from others, covered in the next section. Physically, a minority notice a mildly sore or swollen neck as the gland reacts, or a metallic taste and dry mouth from iodine taken up by the salivary glands. These usually pass within days. Rarely, the damaged gland leaks stored hormone, producing a temporary flare of symptoms such as palpitations in the first couple of weeks; anyone with heart disease is often kept on medicine through this window for that reason.
Then comes the waiting. Mayo Clinic describes symptoms usually subsiding within several months. Blood tests for thyroid hormone and thyroid stimulating hormone are typically checked every few weeks at first, then at longer intervals, to track the gland’s decline. Some people cross from overactive to normal to underactive within a couple of months; others take considerably longer; a few need a second treatment.
The moment hormone levels drop below normal, replacement thyroid hormone is usually started so the person never spends long feeling sluggish, cold and low. This handover, from too much hormone to just enough, is where good follow-up matters most. People who drift for weeks without a test can feel genuinely unwell, and the fatigue is easy to blame on stress or age rather than a thyroid that has finally quietened.
By six months most people know how the story is going to end, and by a year the picture is usually settled.
Radioactive iodine precautions after treatment: what do you actually have to do?
The isotope leaves the body two ways: it decays, with a physical half-life of about eight days, and it is excreted, mainly in urine, over the first few days. During that period a treated person is a weak source of radiation to those around them and their bodily fluids contain traces of iodine-131. The precautions exist to keep other people’s exposure trivially small, not because the patient is in danger.
Exactly how long each precaution lasts depends on the amount given and local regulations, and the nuclear medicine team issues written instructions tailored to the individual. The NHS describes the general shape: avoid prolonged close contact with other people for a few days, and keep away from young children and pregnant women for longer, sometimes up to several weeks, because their tissues are more sensitive.
In practice that usually means a few adjustments to ordinary life:
- Sleeping alone for a defined number of nights and keeping an arm’s length from others when sitting together.
- Avoiding cuddling babies or small children, and arranging for someone else to do close care if possible.
- Staying away from crowded places such as cinemas and public transport for the first days where feasible, and informing the team if travel is unavoidable.
- Flushing the toilet twice, sitting to urinate, washing hands thoroughly and rinsing the basin, since urine carries most of the excreted iodine.
- Using separate cutlery and towels for a short period and drinking plenty of fluids to speed excretion.
Work is often possible after a few days, depending on how close one sits to colleagues; a person who works with children or pregnant women is usually asked to stay away longer. Airport radiation detectors can pick up residual activity for weeks, so many teams provide a card explaining the treatment for anyone who must fly.
Most people describe the precautions as tedious rather than hard. Planning them before the treatment day, including childcare, is the single practical step that makes the fortnight afterward go smoothly.
Hypothyroidism after radioactive iodine: is it a side effect or the goal?
This is the point most often misunderstood, so it deserves a plain statement. In modern practice, an underactive thyroid after radioiodine is largely expected, and for Graves’ disease many specialists deliberately aim for it. Mayo Clinic notes that most people who have the treatment eventually develop hypothyroidism.
The reasoning is about certainty. Give enough radioiodine to bring hormone levels to exactly normal and a proportion of people relapse, because the remaining tissue is still under autoimmune stimulation. Give enough to quiet the gland fully and the overactivity is very unlikely to return. What replaces it, hypothyroidism, is straightforward to manage with a daily tablet of thyroid hormone, which is chemically identical to what the gland made and adjusted using periodic blood tests.
For a toxic nodule the picture is different. The normal tissue around the nodule has been suppressed and takes up little iodine, so it often recovers once the nodule is knocked out. A higher proportion of people end with a normal, not underactive, gland.
Timing varies widely. Hypothyroidism can appear within a couple of months or emerge years later, which is why follow-up blood tests continue long after the immediate recovery period, typically at least annually for life. Symptoms of an underactive gland, fatigue, feeling cold, weight gain, constipation and low mood, creep in slowly and are easy to misattribute; a scheduled test catches the change before it becomes miserable.
Once on replacement hormone, most people feel entirely well, and the regimen rarely changes. Pregnancy is the notable exception, because hormone needs rise early in gestation and doses are reviewed by the prescriber. Anyone who has had radioiodine and later plans a pregnancy should say so at their first appointment.
Seen this way, hypothyroidism after radioiodine is less a complication than the intended landing place, with the cost being a lifelong tablet and a lifelong blood test.
Why does thyroid eye disease change the decision?
Graves’ disease is not confined to the thyroid. In a proportion of people the same antibodies inflame the tissue behind the eyes, causing grittiness, swelling, redness, double vision and, in the classic case, a staring or bulging appearance. This is thyroid eye disease, also called Graves’ orbitopathy.
Radioiodine has a specific, well-documented downside here: it can trigger or worsen the eye inflammation. The mechanism is thought to be a surge of thyroid antigens released as the gland is damaged, which briefly stokes the autoimmune response. The NHS advises that radioiodine is not usually recommended for people with moderate to severe eye disease.
How specialists handle it depends on severity. Someone with no eye involvement can generally proceed. Someone with mild, inactive eye disease is often treated with radioiodine under a short course of corticosteroids, a class of anti-inflammatory medicine, to blunt any flare; the prescriber decides whether and how. Someone with active, moderate or severe disease is usually steered toward tablets or surgery, at least until the eyes have settled, and is seen jointly with an ophthalmologist.
Two modifiable factors matter regardless of treatment. Smoking substantially increases the risk of eye disease developing or worsening, and stopping is the single most useful thing a person with Graves’ disease can do for their eyes. Uncontrolled hypothyroidism after treatment also aggravates orbitopathy, which is another reason for close blood test follow-up in the months after radioiodine.
The eye question is a good example of why the choice is never made from a flowchart alone. A person whose thyroid history points cleanly toward radioiodine may be sent down a different route because of what an ophthalmologist sees at the slit lamp. Ask directly whether your eyes have been assessed before a decision is made.
Pregnancy, breastfeeding and fertility: how do family plans shape the choice?
Few factors move the decision as decisively as reproductive plans. Radioiodine is never given in pregnancy because it crosses the placenta and would ablate the fetal thyroid, which begins concentrating iodine around the end of the first trimester. It is also never given during breastfeeding, since the isotope concentrates in breast milk; feeding must be fully stopped, not paused, before treatment.
After treatment the NHS advises avoiding conception for at least 6 months for women and at least 4 months for men. The reason for the delay is twofold: to allow residual radiation to clear the body and to give time for thyroid hormone levels to stabilize on replacement before a pregnancy places extra demand on them. Radioiodine at the activities used for hyperthyroidism has not been shown to reduce fertility or to increase birth defects in pregnancies conceived after the recommended interval, which is why the waiting period rather than permanent avoidance is the advice.
For someone actively trying to conceive or already pregnant, antithyroid tablets are the mainstay, managed by a specialist because the choice of thionamide and the target hormone levels differ in pregnancy. Surgery is reserved for cases where tablets cannot be used and is usually timed for the second trimester.
There is a longer-term argument that sometimes tips the balance the other way. A woman in her twenties with relapsing Graves’ disease who wants children in a few years may prefer to have radioiodine now, settle onto stable replacement hormone, and enter pregnancy with a predictable thyroid rather than an active autoimmune condition that could flare. Whether that reasoning applies is an individual conversation, but it is worth raising.
Men are asked about fatherhood plans too, and both partners should hear the same advice from the team so the household can plan together.
What people often get wrong about radioiodine and thyroid tablets
Some misunderstandings surface so regularly in clinic that they are worth naming directly.
“Radioactive treatment must be dangerous to me.” The radiation from iodine-131 is delivered almost entirely to the thyroid, and radioiodine has been used for hyperthyroidism for decades. Mainstream sources describe it as safe and well established. The precautions are designed to protect other people, especially children and pregnant women, not because the patient is at risk.
“I’ll lose my hair or feel sick like chemotherapy.” Radioiodine is not chemotherapy and does not cause hair loss or the nausea associated with it. Temporary neck tenderness or a dry mouth are the usual, mild complaints.
“Tablets are the gentle option, so they must be the safest.” Thionamides are safe for most people, but they carry rare serious risks of their own, notably a sudden drop in infection-fighting white blood cells. A fever or sore throat on antithyroid medicine needs a same-day blood test. Gentle in effect does not mean free of hazard.
“If radioiodine makes my thyroid underactive, the treatment failed.” As explained above, hypothyroidism is the expected and often intended outcome for Graves’ disease, exchanged for a much lower chance of the overactivity returning.
“I can eat whatever I like beforehand.” Teams commonly ask people to avoid iodine-rich items such as seaweed, iodized salt in large amounts, and certain supplements for a period before treatment, and to disclose any recent CT scan with iodine contrast, because excess dietary iodine competes with the isotope and can blunt its effect. Follow the specific instructions given.
“Surgery is old-fashioned and nobody does it now.” For a large compressive goiter, a suspicious nodule, or severe eye disease, thyroidectomy remains a mainstream, guideline-endorsed choice.
Clearing these up early makes the actual decision, which is hard enough, considerably cleaner.
Questions to ask your care team before deciding
A good consultation leaves a person able to explain to a friend why one option fits them better than the others. These questions tend to draw out the information needed to get there.
- What is causing my overactive thyroid: Graves’ disease, a single nodule or several? How does that change which treatment you would lean toward?
- If I take tablets, how long would the course be, and what would we do if the condition comes back afterward?
- Have my eyes been assessed for thyroid eye disease, and does the result affect whether radioiodine is advisable?
- If I choose radioiodine, how likely am I to need a second treatment, and how would I know?
- What is the chance I will end up needing thyroid hormone replacement with each option, and how soon might that happen?
- Exactly which radiation precautions would apply to me, for how many days, and how do they fit with my children, my work or a partner who is pregnant?
- How would each option affect plans for pregnancy or breastfeeding in the next year or two?
- What symptoms after treatment should prompt me to call you urgently rather than wait for my next appointment?
- How often will I need blood tests in the first year, and who arranges them?
- Is there any reason surgery would be a better answer for me, such as the size of the gland or the appearance of a nodule?
- If I feel unwell during the waiting period after radioiodine, what is the plan?
It helps to bring someone along, write the answers down, and ask for a copy of the clinic letter. Decisions about permanent treatment rarely need to be made in the room; asking for a week to think is entirely reasonable, and most teams expect it.
The best question of all may be the simplest: “If you were in my position, with my results and my life, what would you want to know before choosing?”
When to call your doctor: red-flag signs at every stage
Whichever route is chosen, a few situations need prompt medical attention rather than a note for the next routine visit.
On antithyroid tablets, contact the prescribing team the same day, and stop no medicine without their advice, if you develop a fever, a severe sore throat, mouth ulcers or any sign of infection; these can signal a dangerous fall in white blood cells and need an urgent blood count. Yellowing of the skin or eyes, dark urine, pale stools, persistent nausea or severe abdominal pain may indicate liver injury and also need same-day assessment. A widespread itchy rash should be reported promptly.
After radioiodine, seek urgent care for a rapid or irregular heartbeat, chest pain, breathlessness, high fever, confusion or agitation, particularly in the first few weeks, as these can indicate a surge of thyroid hormone from the treated gland. A neck that becomes markedly swollen, hot or makes swallowing or breathing difficult needs assessment the same day. New or worsening eye symptoms, especially double vision, pain on eye movement or any change in sight, should be reported quickly. In the months afterward, worsening fatigue, feeling cold, slowed thinking or unexplained weight gain suggest the gland has become underactive and a blood test is due sooner than planned.
After surgery, call urgently for tingling around the mouth or in the fingers, muscle cramps or spasms, which point to low calcium; for wound swelling that increases rapidly or bleeding; for difficulty breathing; or for a voice that is hoarse or weak beyond the first days.
At any stage, call emergency services for severe chest pain, fainting, severe breathing difficulty, or a combination of very high temperature, racing heart and confusion, which can represent thyroid storm, a rare, life-threatening escalation of hyperthyroidism.
None of these lists replaces the specific instructions from the treating team, who know the individual’s situation and remain responsible for every decision about treatment.
Frequently asked questions
How long does radioactive iodine take to work for hyperthyroidism?
The effect builds gradually over weeks to months rather than days. Mayo Clinic describes symptoms usually subsiding within several months of treatment. Blood tests are checked every few weeks at first to track the gland’s decline, and some people continue antithyroid tablets for a period so they are not left symptomatic while waiting. A small proportion need a second treatment if hormone levels have not fallen enough after several months.
What are the radioactive iodine precautions after treatment, and how long do they last?
Precautions protect other people from small amounts of radiation while the isotope decays and is excreted in urine. Typical advice includes keeping distance from others for a few days, avoiding close contact with young children and pregnant women for longer, sleeping alone, flushing twice and washing hands carefully. The exact duration depends on the amount given and local rules; the nuclear medicine team provides individual written instructions.
Is hypothyroidism after radioactive iodine inevitable?
Not inevitable, but very common, and for Graves’ disease it is often the intended outcome because a fully quieted gland is far less likely to become overactive again. Mayo Clinic notes most people eventually develop an underactive thyroid after the treatment. It is managed with a daily replacement tablet adjusted by blood tests. People treated for a single toxic nodule more often keep normal thyroid function.
Antithyroid drugs vs surgery: which is safer?
Each carries different risks rather than one being uniformly safer. Antithyroid tablets are safe for most people but have rare serious effects, notably a sudden fall in white blood cells and liver injury. Surgery carries risks of anesthesia, injury to the voice nerves and low calcium from parathyroid damage, and guarantees lifelong hormone replacement after total removal. The right balance depends on the cause, gland size and the individual’s health.
Can I have radioiodine if I have Graves' eye disease?
It depends on how active and severe the eye disease is. Radioiodine can worsen thyroid eye disease, and the NHS advises it is not usually recommended for moderate to severe cases. People with mild or inactive eye involvement are sometimes treated with radioiodine alongside a short course of corticosteroids decided by the prescriber. An eye assessment, ideally with an ophthalmologist, should happen before the decision.
Does radioactive iodine cause cancer or affect fertility?
At the activities used for benign hyperthyroidism, radioiodine has been used for decades and mainstream sources describe it as safe. Studies have not shown reduced fertility or increased birth defects in pregnancies conceived after the recommended waiting period, which the NHS gives as at least 6 months for women and 4 months for men. The radiation is concentrated in the thyroid, which is why long-term follow-up focuses on thyroid function.
Why did my doctor put me on tablets before radioiodine?
Usually to bring hormone levels down first so that the months-long wait for radioiodine to take full effect does not leave you unwell, and to reduce the risk of a temporary hormone surge as the gland is damaged. This is especially common in older people and anyone with heart disease. Tablets are typically paused for a short period around the treatment day on the team’s instructions so they do not blunt iodine uptake.
Is radioiodine treatment painful, and do I need to stay in hospital?
For hyperthyroidism it is an outpatient procedure with no anesthetic and nothing to feel as the capsule or liquid is swallowed. Most people go home the same day and follow radiation precautions at home. Some notice a mildly sore neck, a metallic taste or a dry mouth for a few days. Higher-activity radioiodine used after thyroid cancer surgery sometimes involves a short hospital stay, which is a separate pathway.
What happens if antithyroid tablets stop working or my hyperthyroidism comes back?
Relapse after a completed course of tablets is common in Graves’ disease, and it is the most frequent reason radioiodine or surgery is proposed. Options include a further period on tablets, long-term low-maintenance medicine for people who prefer it, or a permanent treatment. Which is suggested depends on age, gland size, eye disease, pregnancy plans and personal preference, and the decision rests with the treating specialist.
Will I need blood tests for life after radioiodine or surgery?
Yes, in almost all cases. After radioiodine, tests are frequent in the first year to catch the shift from overactive to underactive, then typically at least annually because hypothyroidism can emerge years later. After total thyroidectomy, replacement hormone is adjusted using periodic tests. Anyone planning a pregnancy should tell their team early, since hormone requirements change in the first trimester.
References
- NHS: Overactive thyroid (hyperthyroidism) – Treatment
- NIH NIDDK: Hyperthyroidism (Overactive Thyroid)
- NIH NIDDK: Graves' Disease
- MedlinePlus: Hyperthyroidism
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Why Surgeons Remove a Margin of Healthy Skin in Wide Local Excision for Melanoma
Surgeons remove a rim of healthy-looking skin around a melanoma, usually between 0.5 and 2 centimeters wide depending on how thick the tumor is,…

What Happens During a Lutetium-177 PSMA Therapy Session: Infusion, Fluids and Monitoring
A lutetium-177 PSMA treatment session is an outpatient visit of several hours in which a radioactive medicine is given through an intravenous line, usually…

Exercise, Weight and Bone Strength During Hormone Therapy: A Practical Routine
Exercise during hormone therapy for cancer is generally encouraged because these treatments lower estrogen or testosterone, which speeds bone loss, muscle loss and fat…
When Is Mohs Surgery Chosen Over Standard Excision for Skin Cancer? How Surgeons Decide
Surgeons usually choose Mohs surgery over standard excision when a basal cell or squamous cell skin cancer sits in a cosmetically or functionally sensitive…

When Do Scans Show a Response After CyberKnife? Why Follow-Up Imaging Takes Patience
Scans after CyberKnife, a form of stereotactic radiosurgery, usually change slowly. Cancerous tumors often begin to shrink over a few months, while benign tumors…

Inside a Proton Therapy Session: Positioning, Image Checks and the Minutes the Beam Is On
A proton therapy session is usually an outpatient visit of about 15 to 45 minutes, and most of that time goes to positioning you…