

When Pink Eye Needs an Eye Doctor Rather Than Time: How Conjunctivitis Care Is Decided
Key Takeaways
- Simple conjunctivitis irritates the conjunctiva but spares the cornea, so pain, blurred vision or light sensitivity point to a different, more urgent diagnosis.
- Viral pink eye typically runs 7 to 14 days and can take up to three weeks to clear; antibiotics do not shorten it, according to the CDC.
- Mild bacterial conjunctivitis often improves within 2 to 5 days without treatment, which is why prescriptions are reserved for heavier or higher-risk cases.
- Any red eye in a newborn under one month, or in a contact lens wearer, is assessed the same day because corneal damage can develop within days.
- Infectious pink eye remains contagious while discharge persists, and adenovirus can survive on surfaces for days, so fresh towels and clean hands matter more than any drop.
- The NHS threshold for review is symptoms not improving after two weeks, but worsening at any point moves that timeline forward.
Most pink eye is viral or allergic and settles on its own within one to two weeks, so time and hygiene are usually enough. It needs a doctor when there is eye pain, light sensitivity, blurred vision that does not clear with blinking, a newborn is affected, contact lenses are worn, symptoms follow an injury, or things are not improving after several days.
The text arrives at 7:40 in the morning, a photo of one puffy, cherry-red eye and three words: “School or doctor?” The parent sending it has already googled, found eight conflicting answers, and is now standing in the kitchen with a child who feels perfectly fine apart from the crusted lashes.
That small domestic standoff is the whole question of when pink eye needs a doctor. Conjunctivitis is one of the most common reasons people walk into a clinic, and one of the most common reasons they are told, kindly, that they did not need to. Yet a minority of red eyes are not conjunctivitis at all, and a handful of true conjunctivitis cases can scar the cornea if left to “time.”
Clinicians sort these cases with a short list of signals rather than a glance at the color. This article walks through that list, what the exam actually checks, and why patience is the right medicine for most people but the wrong one for a few.
What is actually happening when an eye turns pink
The conjunctiva is the thin, transparent membrane that lines the inside of the eyelids and covers the white of the eye. It is laced with tiny blood vessels you normally cannot see. When the membrane is irritated or infected, those vessels widen and fill, and the white of the eye takes on its pink or red cast. The name conjunctivitis simply means inflammation of that membrane.
Three things usually drive the inflammation. A virus, most often an adenovirus (the same family that causes many colds), is the single most frequent cause in adults, according to the CDC. Bacteria, including Staphylococcus and Streptococcus species and, in young children, Haemophilus, are the next group. Allergens such as pollen or pet dander trigger the third, through histamine release rather than infection. A fourth, smaller group comes from irritants: chlorine, smoke, a stray eyelash, a splash of shampoo.
Whatever the trigger, the membrane responds in similar ways. It leaks fluid, which is why the lids swell. Goblet cells in the conjunctiva produce more mucus, which dries overnight into the familiar crust. Nerve endings fire, producing the gritty, sand-in-the-eye feeling. Tear production rises as the eye tries to flush the surface.
What the conjunctiva does not do, on its own, is affect sight. The cornea, the clear dome over the colored iris, sits in front of the pupil and does the focusing. Simple conjunctivitis leaves the cornea alone. That distinction matters more than anything else in this article: a red eye that also sees poorly, or hurts deeply, is signaling that something beyond the conjunctiva is involved, and that is where the calculation changes from waiting to examining.
How can you tell if pink eye is viral or bacterial?
Honestly, often you cannot, and neither can a clinician with certainty from across the room. Studies summarized by the Mayo Clinic and CDC describe patterns rather than rules, and the patterns overlap. Still, the patterns are worth knowing because they shape how urgently a case is reviewed.

Viral conjunctivitis tends to arrive with company. A runny nose, sore throat or cough in the days before, or a household member with a cold, points toward adenovirus. The discharge is usually watery or thin and stringy. It often starts in one eye and travels to the other within a few days. The small lymph node in front of the ear may be tender, a detail clinicians check for because it is uncommon in bacterial cases.
Bacterial conjunctivitis more often produces thick yellow or green discharge that returns within minutes of wiping, and lids that are glued shut on waking rather than lightly crusted. It can affect one eye only, and in young children it sometimes accompanies an ear infection, a pairing the CDC specifically notes.
Allergic conjunctivitis almost always hits both eyes at once, and the dominant complaint is itching rather than grit. Sneezing and an itchy nose usually come along.
The catch is that watery discharge can be bacterial, thick discharge can be viral, and cultures, when taken, show that even experienced examiners misjudge a meaningful share of cases. This is why most guidance, including the NHS’s, does not hinge the first few days of care on getting the label right. It hinges on whether warning signs are present and whether the eye is improving on its own.
Viral, bacterial, allergic and irritant pink eye at a glance
The table below pulls together the typical features described by the CDC, Mayo Clinic and NHS. Read it as a set of tendencies, not a diagnostic test; the final sorting belongs to whoever examines the eye.
| Feature | Viral | Bacterial | Allergic | Irritant |
|---|---|---|---|---|
| Usual cause | Adenovirus and other cold viruses | Staphylococcus, Streptococcus, Haemophilus | Pollen, dust, dander | Chlorine, smoke, foreign body |
| Discharge | Watery, sometimes stringy | Thick, yellow or green, recurs quickly | Watery, often with mucus strands | Watery |
| Eyes affected | One, then often both | One or both | Both together | Whichever was exposed |
| Main sensation | Grit, burning | Grit, lids stuck on waking | Itching | Stinging |
| Company | Cold symptoms, tender node by ear | Sometimes ear infection in children | Sneezing, itchy nose | Known exposure |
| Contagious | Yes, highly | Yes | No | No |
| Typical course (CDC) | 7–14 days, up to 2–3 weeks | Often eases in 2–5 days untreated, may last 2 weeks | As long as exposure continues | Hours to a day or two after removal |
Two things stand out. First, only the infectious types spread, which is why the “stay home” question depends on the probable cause rather than on redness alone. Second, every column has a self-limiting course; none of these, in an otherwise healthy adult with no warning signs, routinely requires urgent treatment to protect sight. The urgency comes from the exceptions, which the next sections lay out.
When pink eye needs a doctor: the signals that change the plan
Eye specialists are trained to separate “red eye” into the harmless majority and the dangerous few using a handful of questions. The same questions decide when pink eye needs a doctor rather than a week of warm compresses.

Pain is the first. Conjunctivitis is uncomfortable, scratchy, sometimes burning. It is not painful in the deep, aching way that keeps someone awake or makes them squint. Real pain suggests the cornea or the structures inside the eye are inflamed, as in keratitis (infection of the cornea), iritis (inflammation inside the front of the eye) or acute glaucoma (a sudden pressure rise). Each of those is examined promptly.
Vision is the second. Blur that clears after blinking away discharge is expected. Blur that persists once the surface is clean is not, and the Mayo Clinic lists it among reasons to seek care.
Light sensitivity, called photophobia, is the third. Mild bother in bright sun is common with conjunctivitis; needing to keep the eye closed indoors is not.
Then come the context clues. A newborn with a red eye is always assessed the same day, because some infections acquired during birth can damage the cornea within days. Anyone who wears contact lenses is assessed because lens-related corneal infections can mimic conjunctivitis early. A red eye after an injury, a chemical splash or a possible foreign body is examined, not waited out. People whose immune systems are weakened, whether from medicines or illness, have a lower threshold too.
Finally, there is trajectory. The NHS advises contacting a clinician if symptoms have not started improving after two weeks, or sooner if they worsen rather than plateau.
Who is usually seen promptly, and who is usually asked to wait
Triage for a red eye is unusually consistent across guidelines, which is reassuring when a phone line or front desk gives an answer that sounds dismissive. “Wait a few days” is often the evidence-based response, not a brush-off.
Seen the same day, in most pathways: newborns in their first month; anyone with eye pain, reduced vision or marked light sensitivity; contact lens wearers with a red eye; people with a recent injury or chemical exposure; anyone with a red eye alongside a severe headache, nausea or a haloed view of lights, which can accompany acute glaucoma; and people whose redness is intense and localized with a visible bulge or a very swollen, hot, tender lid, because infection can track into the tissues around the eye.
Seen within a few days: children and adults whose symptoms are not easing after roughly a week, those with very heavy discharge that returns constantly, people who are immunocompromised, and anyone whose condition is interfering with daily life or work in a way that needs a certificate or a plan.
Usually asked to wait, with self-care: otherwise healthy people with mild to moderate redness, watery or modestly crusty discharge, grittiness without true pain, normal vision once the eye is wiped, and no lens wear. The NHS explicitly notes that most people in this group do not need to see a GP, and a pharmacist can advise on comfort measures.
The group that is asked to wait is far larger than the group that is not. What keeps the system safe is that the waiting comes with instructions: which changes would move someone from the second list to the first, and how quickly to act if they appear.
What happens at the eye doctor's exam
People sometimes avoid the appointment because they imagine instruments touching the eye. For conjunctivitis the exam is almost entirely visual and takes a few minutes.
History comes first and does most of the work: when it started, one eye or two, the nature of the discharge, any cold or allergy symptoms, lens wear, injuries, recent travel or swimming, and whether anyone at home has the same thing. The clinician checks vision on a chart, because a normal reading in each eye quietly rules out several of the serious alternatives.
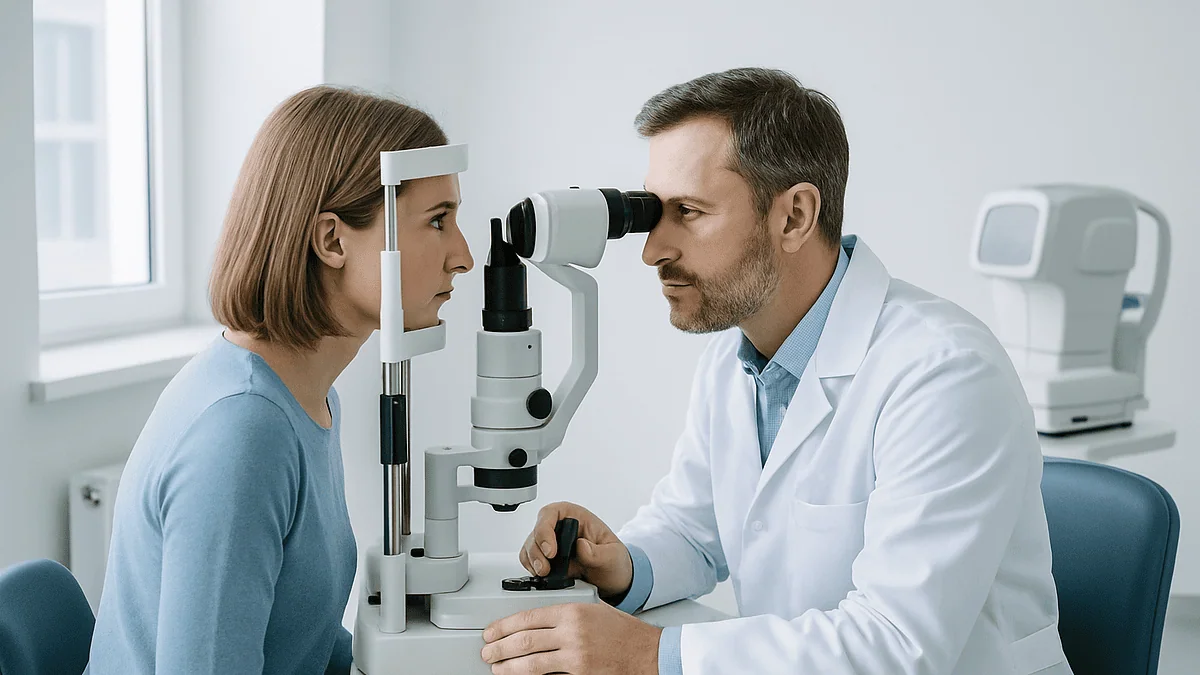
Next is inspection, often with a slit lamp, a bright microscope on a stand that lets the examiner look at the surface of the eye under magnification. The lower lid is gently pulled down and the upper lid may be flipped to look for follicles (small bumps typical of viral infection), papillae (a cobblestone texture typical of allergy) or a hidden foreign body. The pupil’s response to light is checked.
A drop of fluorescein, a harmless orange dye that glows under blue light, may be placed on the eye. It pools in any scratch or ulcer on the cornea, turning a suspected simple conjunctivitis into a corneal problem in seconds. The clinician may also feel for the small lymph node in front of the ear.
Swabs for culture are the exception rather than the rule. The CDC and Mayo Clinic describe them as reserved for severe cases, newborns, people who are not improving, or when a sexually transmitted infection is suspected. Rapid adenovirus tests exist but are not routine. Most of the time the decision rests on the pattern seen, not on a laboratory result.
How long does pink eye last? What the following days usually look like
The days after a diagnosis follow a reasonably predictable arc, and knowing it helps people judge whether they are on track.
Viral conjunctivitis typically worsens for the first three to five days before it improves. The second eye often joins in during that window, which feels like a setback but is expected. The CDC puts the usual course at 7 to 14 days, with some cases taking two to three weeks to clear fully. Watery discharge and redness fade gradually; a faint grittiness can linger a few days after the eye looks normal. In a minority of adenovirus cases, small inflammatory spots form on the cornea and leave the eye slightly hazy or glare-sensitive for weeks, a complication that is monitored rather than ignored.
Bacterial conjunctivitis, per the CDC, often improves without treatment within 2 to 5 days and may take up to two weeks to resolve completely. When antibiotic drops are prescribed, the thick discharge usually thins within a couple of days; if nothing changes after that, the diagnosis is revisited.
Allergic conjunctivitis has no fixed course. It persists as long as the allergen is around and eases within hours to a day or two when exposure stops, which is why a sudden improvement after leaving a house with a cat is itself a clue.
The pattern clinicians watch for is direction. Symptoms that plateau for a few days are tolerable. Symptoms that climb steadily past day five, or that improve and then sharply rebound, change the plan. Those typical windows come from population averages; an individual’s timeline may be shorter or longer without anything being wrong.
What clears conjunctivitis quickly? An honest answer
This is the search almost everyone makes at midnight, and the honest reply is that very little speeds up the common forms. Viral conjunctivitis has no antiviral treatment in routine use; the CDC states plainly that antibiotics do not help it. The immune system clears adenovirus on its own schedule, and the measures that follow make the wait more comfortable rather than shorter.
A clean, cool or lukewarm compress over closed eyes eases swelling and loosens crust. Lubricating eye drops, sometimes called artificial tears and sold without prescription, dilute irritants and relieve grittiness. Wiping from the inner corner outward with a fresh cotton pad for each eye prevents reseeding the other eye. Taking contact lenses out and leaving them out until the eye has been clear for a day, and discarding the pair and case that were in use, is standard advice.
Allergic conjunctivitis does respond quickly to two things: removing the allergen and, where a clinician agrees, antihistamine drops, which block the histamine that causes itching. Cold compresses work well here too.
Bacterial conjunctivitis is the only common type where a prescribed medicine may shorten the course, and even then the margin is modest. The NHS and CDC describe antibiotic drops as something that can shorten the illness and reduce spread in bacterial cases, while noting that mild cases often resolve without them.
Things that do not clear conjunctivitis and may harm the eye: leftover drops from a previous illness, drops borrowed from someone else, home remedies such as breast milk or tea bags applied to the eye, and redness-relieving drops used daily, which can rebound and mask worsening. The quickest route is usually the most boring one.
How the medicines work, when they are used at all
When a clinician does prescribe for conjunctivitis, it is for a reason tied to the probable cause, and the choice, duration and any adjustment belong to that clinician. What follows explains mechanisms and typical expectations so the conversation makes sense.
Topical antibiotics, given as drops or an ointment, kill or stop the growth of bacteria on the surface of the eye. They do nothing to viruses or allergens. Guidance from the Mayo Clinic and CDC reserves them for cases that are likely bacterial, especially when discharge is heavy, when the person is immunocompromised, when a contact lens is involved, or when a specific bacterium such as gonococcus or chlamydia is suspected. People commonly notice thinner discharge within a few days when the diagnosis is right. The full course is generally finished even if the eye looks clear earlier, to reduce relapse and resistance.
Antihistamine and mast-cell stabilizer drops are used for allergic conjunctivitis. Antihistamines block histamine already released; mast-cell stabilizers reduce future release. The first act within minutes, the second build over days.
Lubricants, the artificial tears mentioned earlier, have no active drug; they simply replace and thicken the tear film to protect the surface and wash away debris.
Steroid drops reduce inflammation powerfully but can worsen certain infections, raise eye pressure and thin the cornea with misuse. They are prescribed by eye specialists in specific situations such as adenoviral corneal spots or severe allergic disease, and are never a first step for an unexamined red eye.
Oral antibiotics enter the picture for newborn infections, for chlamydial or gonococcal conjunctivitis in adults, and for infections spreading into the tissues around the eye. Each of those is a clinician’s call after examination.
Pink eye symptoms in babies and newborns: a different pathway
A red or sticky eye in the first four weeks of life is handled differently from pink eye at any other age, and the reason is the cornea. Newborn conjunctivitis, known as ophthalmia neonatorum, can be caused by bacteria the baby met during birth, and two of them, gonococcus and chlamydia, can damage the cornea quickly if untreated. MedlinePlus and the CDC both describe this as a condition that needs same-day assessment.
Timing offers clues that the clinician will ask about. The CDC notes that chemical irritation from protective drops given soon after birth typically appears within the first day or two and clears on its own. Gonococcal conjunctivitis usually shows up 2 to 5 days after birth, with marked lid swelling and heavy pus. Chlamydial conjunctivitis tends to appear 5 to 14 days after birth with a watery discharge that becomes thicker. Other bacteria and viruses can appear across the first month.
Parents most often notice swollen lids, redness of the white of the eye, and discharge that may be watery, yellow or green. A baby who keeps one eye shut, or whose lids are puffy enough to be hard to open, is examined without waiting.
The pathway in clinic is gentle: the eye is inspected, swabs are taken for culture because the cause matters for treatment, and the baby’s general health is checked, since the same bacteria can affect other parts of the body. Treatment, when needed, is chosen by the pediatric team and may involve drops, ointment or medicine given by mouth or injection. The parents are usually offered testing too, so the infection is not passed back.
Much milder, and far more common, is a watery or mildly sticky eye without redness in an infant, often from a tear duct that has not fully opened. That is also worth a check, but it is a different condition, and the pediatrician will tell the two apart.
Contact lens wearers: why a red eye is never just pink eye
Someone who sleeps in lenses, swims in them, or stretches a two-week pair into a fourth week is in a separate category the moment one eye turns red. The reason is microbial keratitis, an infection of the cornea itself. Lenses reduce oxygen to the cornea and give bacteria, and occasionally a water-borne amoeba, a surface to cling to. Early keratitis looks a great deal like conjunctivitis: redness, watering, a scratchy feeling. The difference emerges over hours as pain deepens, light becomes intolerable and vision clouds.
Because that early window is where treatment protects sight, every mainstream guideline, including the Mayo Clinic’s, advises lens wearers with a red eye to remove the lens and be seen promptly rather than watching and waiting. At the exam, the fluorescein dye test described earlier shows whether the cornea is intact. If it is, and the picture is simple conjunctivitis, the advice is to stay out of lenses until the eye has been free of symptoms for at least a day, and to discard the lenses and case in use when symptoms began.
If the cornea is involved, treatment is more intensive and is managed by an eye specialist, often with frequent follow-up in the first days.
The practical lesson is prevention as much as triage. Hands washed and dried before touching lenses, no tap water on lenses or cases, no sleeping or swimming in lenses unless the lens is specifically approved for it, and replacing the case every few months each lower the risk. Keeping a current pair of spectacles means a red eye never forces a choice between seeing and resting the eye.
Is pink eye contagious, and how do you stop it spreading?
Viral and bacterial conjunctivitis are contagious; allergic and irritant forms are not. The infectious types spread through direct contact with eye secretions, through hands that have touched them, and via shared towels, pillows, eye makeup and, in the case of adenovirus, through the respiratory droplets of the accompanying cold. Adenovirus is hardy and can survive on surfaces for days, which is why outbreaks move through classrooms and offices so efficiently.
The CDC’s guidance is that a person is generally contagious for as long as they have symptoms, particularly tearing and discharge. For bacterial cases on antibiotics, contagiousness falls substantially after about 24 hours of treatment, a figure many schools use for return policies.
Simple habits break the chain. Hands washed with soap for 20 seconds after touching the eyes or face. A fresh towel and pillowcase for the affected person, washed in hot water. No sharing of eye drops, cosmetics or lens solutions. Discarding any eye makeup used while the eye was infected. Avoiding rubbing the eye, which both spreads the infection and increases inflammation. Swimming pools are best avoided until the eye is clear, both for the swimmer and for others.
On school and work attendance, policies vary by setting and local health departments, and there is no single national rule. The CDC notes that children with mild conjunctivitis and no systemic symptoms often do not need exclusion if they can practice good hygiene, but that individual schools may still require time away. A clinician’s note is sometimes requested; the conversation about returning is one to have with both the care team and the school.
What people often get wrong about pink eye
The myths around conjunctivitis are durable precisely because the condition is so common. A few are worth dismantling.
“Pink eye always needs antibiotics.” Most cases are viral, and antibiotics do not act on viruses. The CDC is explicit that antibiotic drops will not help viral conjunctivitis and that mild bacterial cases often resolve without them. Unnecessary antibiotics add side effects, cost, and resistance without shortening the illness.
“If it’s not getting better in two days, something is wrong.” Viral conjunctivitis typically peaks around day three to five, and the second eye often joins in. Lack of improvement at 48 hours is normal; worsening pain or vision is not. The distinction is between slow and sinister.
“Green discharge means bacteria.” Color is an unreliable guide. Thick, constantly recurring discharge leans bacterial, but viral infections can produce yellowish mucus, and heavy allergic mucus can look alarming.
“A red eye is just pink eye.” The overwhelming majority are, but keratitis, iritis, acute glaucoma, scleritis and a foreign body all present with redness. The features that separate them are pain, vision change and light sensitivity, which simple conjunctivitis does not cause.
“Redness-relief drops treat it.” Vasoconstrictor drops shrink blood vessels cosmetically. They treat nothing, can rebound with regular use, and may hide a worsening eye.
“Home remedies are harmless.” Applying breast milk, tea bags, honey or urine to an eye introduces bacteria to an already inflamed surface. None has evidence of benefit.
“Once it’s cleared, it can’t come back.” Reinfection from a contaminated lens case, mascara or pillowcase is common enough that replacing these is standard advice.
Questions to ask your care team
A pink eye appointment is brief, and people often leave with a prescription but without the context that makes it useful. These questions tend to surface the information that matters.
- Which type of conjunctivitis do you think this is, and how confident are you? If it is uncertain, what would make you change your mind?
- Did you check the cornea, and was it clear? Knowing the dye test was normal is reassuring when symptoms drag on.
- What should I expect over the next few days, and roughly when should I be improving?
- Which specific changes mean I should come back or go to urgent care, and how quickly?
- If medicine has been prescribed, what is it meant to do, how long is the full course, and what should I do if a dose is missed or the eye seems no different after a few days?
- Is it safe for me to drive, read or use screens, and will the medicine blur my vision for a while after each use?
- When can I go back to work or school, and when can my child? Do you need to provide a note?
- When can I wear contact lenses again, and should I throw away the pair and case I was using?
- How can I avoid passing this to the rest of the household?
- Is there any reason to test for a sexually transmitted infection in my case, or in my baby’s?
- If this is allergic, what is the likely trigger and are there ways to reduce exposure?
Writing down the answers, especially the return-if list and the expected timeline, turns a two-minute consultation into a plan. Clinicians generally welcome these questions; they are the same ones they would want answered for themselves.
When to call your doctor
Most pink eye can be managed at home with hygiene, compresses and patience. These signs mean the eye should be seen promptly, the same day where possible, because they point to something beyond the conjunctiva or to a type of conjunctivitis that can threaten the cornea.
- Eye pain that is deep or aching rather than gritty, or pain severe enough to keep the eye closed.
- Blurred or reduced vision that does not clear after blinking away discharge.
- Marked sensitivity to light, especially indoors.
- A red eye in a baby under one month old, whatever the amount of discharge.
- A red eye in anyone who wears contact lenses.
- Redness following an injury, a chemical splash, or a suspected foreign body in the eye.
- Intense redness in one spot with a visible bulge, or an eyelid that is very swollen, hot and tender, particularly with fever.
- Severe headache with nausea, or halos around lights, alongside a red eye.
- Symptoms in someone with a weakened immune system or recent eye surgery.
- Very heavy pus that returns within minutes of wiping, especially with a possible sexually transmitted exposure.
- No improvement after about a week, or worsening at any point rather than a slow plateau.
- Symptoms persisting beyond two weeks, the threshold the NHS uses for review.
If vision drops suddenly, pain becomes severe, or a child becomes drowsy or very unwell with a red eye, emergency care is appropriate rather than a routine appointment.
Any decision about examination, testing or treatment rests with the clinician who sees the eye. This list is a guide to when that conversation should happen quickly, not a substitute for it.
Frequently asked questions
What are the symptoms of an eye infection compared with simple pink eye?
Simple conjunctivitis causes redness, watering, discharge, crusting and a gritty feeling, with normal vision once the eye is wiped. An infection reaching the cornea or deeper tissues adds deep aching pain, blurred vision that does not clear, strong light sensitivity, and sometimes a hot swollen lid or fever. Those additional features, not the shade of red, are what prompt a prompt examination.
What clears conjunctivitis quickly?
Nothing reliably speeds up viral conjunctivitis, which clears on its own over one to two weeks. Cool compresses, lubricating drops and strict hand hygiene relieve symptoms and limit spread. Allergic conjunctivitis improves fast once the allergen is removed, and antihistamine drops may help where a clinician agrees. Antibiotic drops can modestly shorten bacterial cases, but only a clinician can judge whether they are appropriate.
What is conjunctivitis in babies and what are its symptoms?
Conjunctivitis in a newborn, called ophthalmia neonatorum, is inflammation of the eye’s lining in the first month of life, sometimes caused by bacteria acquired during birth. Signs are red whites of the eyes, puffy lids and watery or thick yellow discharge. Because certain bacteria can damage the cornea within days, a newborn with a red or sticky eye is examined the same day rather than observed at home.
How can you tell if pink eye is viral or bacterial at home?
You can only estimate. Viral pink eye usually brings watery discharge, often follows a cold, and spreads from one eye to the other. Bacterial pink eye more often produces thick yellow-green discharge that recurs quickly and glues the lids shut on waking. The overlap is large, so guidance focuses on warning signs and whether the eye is improving rather than on getting the label right at home.
How long does pink eye last if left alone?
The CDC describes viral conjunctivitis as usually lasting 7 to 14 days, sometimes two to three weeks, and mild bacterial conjunctivitis as often improving within 2 to 5 days with full resolution inside two weeks. Allergic conjunctivitis lasts as long as exposure continues. These are typical ranges from population data, not promises for an individual eye.
Is pink eye contagious, and for how long?
Viral and bacterial pink eye are contagious; allergic and irritant types are not. The CDC advises that a person can spread the infection for as long as symptoms, especially tearing and discharge, are present. For bacterial cases treated with antibiotics, contagiousness drops considerably after about 24 hours of treatment. Clean hands, separate towels and no shared eye products limit spread.
Can I go to work or send my child to school with pink eye?
It depends on the probable cause and the setting’s policy. Allergic pink eye is not contagious and needs no time away. For infectious types, the CDC notes that children with mild symptoms who can practice good hygiene often do not require exclusion, though many schools and workplaces set their own rules, sometimes asking for 24 hours of antibiotic treatment or a clinician’s note.
Should I see an eye doctor or my regular doctor for pink eye?
For a typical case, a primary care clinician, pediatrician or pharmacist is well placed to advise, and the NHS notes most people do not need a GP at all. An eye specialist becomes the right stop when there is pain, vision change, light sensitivity, contact lens wear, an injury, a newborn is affected, or symptoms fail to improve, because those cases may need a slit-lamp examination of the cornea.
Why did my doctor not prescribe antibiotic drops for pink eye?
Most likely because the case looked viral or allergic, and antibiotics act only on bacteria. The CDC and Mayo Clinic both describe antibiotics as unhelpful for viral conjunctivitis and unnecessary for many mild bacterial cases, which improve on their own. Withholding them avoids side effects and resistance. If discharge becomes heavy or symptoms worsen, the decision is usually revisited at follow-up.
Can pink eye damage my vision permanently?
Simple conjunctivitis very rarely does. Risk arises when the cornea is involved, as in contact lens related keratitis, severe adenoviral infection with corneal spots, or untreated gonococcal or chlamydial infection, especially in newborns. These are exactly the situations where same-day assessment is advised. Pain, persistent blur and strong light sensitivity are the signals that the cornea may be affected.
References
- CDC: About Pink Eye (Conjunctivitis)
- CDC: Pink Eye in Newborns
- NHS: Conjunctivitis
- MedlinePlus: Neonatal conjunctivitis
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Keratoconus Treatment Ladder: Lenses, Cross-Linking, Rings and When Transplant Is Discussed
Keratoconus treatment options form a ladder rather than a single choice. Glasses and soft lenses help early; rigid gas-permeable, hybrid or scleral lenses restore…

Can a Contact Lens Get Lost Behind Your Eye? Contact Lens Myths, Corrected
No. A contact lens cannot travel behind your eye. The conjunctiva, the thin membrane lining the inside of the eyelids, folds back onto the…

Recovering From Myopia Laser Surgery: Screens, Makeup, Swimming and the Follow-Up Calendar
Myopia laser surgery recovery is usually quick for daily life and slow for fine detail. Patient guides describe most people returning to work and…

How IntraLase Creates the LASIK Flap and What That Means for Your Eye
An IntraLase femtosecond flap is the thin, hinged layer of cornea that a femtosecond laser, rather than a mechanical blade, creates during LASIK. The…

When Is Glaucoma Surgery Needed? What Pushes Care Beyond Drops and Laser
Glaucoma surgery is usually needed when eye pressure stays above the target the treating team has set despite well-used drops and laser treatment, when…
Daily Disposable vs Monthly Contact Lenses: How Your Eye Doctor Helps You Choose
Daily disposable and monthly contact lenses correct vision the same way; they differ in how long each lens is worn before it is discarded.…