

Which Tests Assess the Reproductive System? Pelvic Ultrasound, Hormone Panels and Beyond

Key Takeaways
- Around 84 in 100 couples conceive within a year of regular unprotected sex, which is why testing is usually offered after 12 months, or after about 6 months when the woman is 35 or older.
- A transvaginal pelvic ultrasound shows the uterus, ovaries and antral follicle count but cannot tell whether the fallopian tubes are open; that requires an HSG or a saline ultrasound test.
- Early-cycle FSH, LH and estradiol are drawn on days 2–5 of bleeding, progesterone about a week before the expected period, and AMH on any day, so the cycle day changes what a normal result looks like.
- Semen analysis is repeated after several weeks when abnormal because sperm take two to three months to develop and counts vary with fever, heat and the interval since last ejaculation.
- Chlamydia screening is a fertility test in its own right, since the infection can scar the fallopian tubes without causing symptoms.
- Infertility affects an estimated 1 in 6 people of reproductive age worldwide, and causes are found in men, in women, in both, or remain unexplained with similar frequency.
Reproductive system tests usually begin with a history and physical exam, then move to targeted checks: a semen analysis for men, blood tests that measure hormones such as FSH, LH, progesterone and AMH for women, and a pelvic ultrasound to look at the uterus and ovaries. Tests of the fallopian tubes, infection screening, genetic tests and, less often, laparoscopy or hysteroscopy may follow, chosen by the treating team.
The envelope from the lab sits on the kitchen table for two days before anyone opens it. Inside is a single page of hormone results, a column of numbers next to reference ranges, and a note to book a follow-up. Nothing on the page explains what the numbers mean for the question that actually matters: is something wrong, and what happens next?
People arrive at reproductive system tests from very different directions. One couple has been trying to conceive for fourteen months. A man in his forties has noticed a heaviness on one side of the scrotum. A woman in her twenties has periods so irregular she has stopped tracking them. All three will hear phrases like pelvic ultrasound, hormone panel and semen analysis, often in the same appointment.
This guide walks through what each test involves, why clinicians order them in a particular sequence, what the results can and cannot tell you, and where the evidence is honest about its limits.
What actually happens during reproductive system tests?
Most reproductive assessments start not with a machine but with a conversation. A clinician asks about menstrual patterns, past pregnancies, surgeries, infections, medicines, smoking, alcohol and how long a couple has been trying to conceive. That history steers everything that follows, because the tests are chosen to answer specific questions rather than run as a fixed battery.
A physical examination usually comes next. For women this may include a pelvic exam, where the clinician checks the size and position of the uterus and looks for tenderness or masses. For men it includes examining the testicles and the veins around them, since an enlarged vein cluster called a varicocele (a swollen network of veins in the scrotum) is one of the more common findings in male infertility, according to Mayo Clinic.
Then come the laboratory and imaging steps, typically in this order:
- Blood tests timed to the menstrual cycle, measuring hormones that reflect ovulation and ovarian reserve (the number of eggs remaining in the ovaries).
- A semen analysis, which counts sperm and checks their movement and shape.
- A pelvic ultrasound, which uses sound waves to build a picture of the uterus, ovaries and surrounding tissue.
- Infection screening, most often for chlamydia and gonorrhea.
Only if these leave a question unanswered does the team move to tests of the fallopian tubes, genetic analysis, or a look inside the pelvis with a camera. The NHS describes this stepwise approach in its guidance on infertility diagnosis, and it matters for a practical reason: each step carries a little more time, discomfort or risk than the one before, so the simplest checks are done first.
Who is usually offered reproductive system tests, and who is asked to wait?
Waiting can feel like being ignored, yet the timing rules exist because conception is slow even when everything is working. NHS figures show that around 84 in every 100 couples who have regular unprotected sex will conceive within a year, and most of the rest will do so in the second year (NHS). Testing too early risks labelling a normal wait as a problem.

So the usual threshold for a fertility workup is 12 months of trying without success. That window shortens to about 6 months when the woman is aged roughly 35 or older, because ovarian reserve declines more steeply in the late thirties, a point made by both the NHS and Mayo Clinic.
Some people are offered tests without waiting at all. Clinicians tend to move faster when there is a known reason to suspect a problem: very irregular or absent periods, a history of pelvic infection or endometriosis, previous surgery on the ovaries or testicles, undescended testicles in childhood, or a diagnosis of a condition known to affect fertility, such as polycystic ovary syndrome (PCOS, a hormonal condition that disrupts ovulation).
Reproductive tests are not only for people trying to conceive. Pelvic ultrasound and hormone panels are also used to investigate heavy or painful periods, pelvic pain, early or delayed puberty, symptoms of menopause and testicular lumps. The same scan or blood draw answers a different question depending on why it was ordered.
Who is asked to wait? Mainly couples under 35 who have been trying for less than a year with no warning signs. That advice can be frustrating, but it reflects what the data show about normal time to pregnancy, not a judgment about the individual.
Female reproductive system tests: what a first workup includes
The first round of female reproductive system tests is designed to answer three questions. Is ovulation happening? Are the ovaries and uterus structurally normal? Is there an infection or blockage that could interfere with conception?
Ovulation is the release of an egg from the ovary, usually about two weeks before the next period. The most common way to confirm it is a blood test for progesterone, a hormone the ovary makes after the egg is released. The NHS notes this is often taken around day 21 of a typical cycle, timed differently if cycles are longer or irregular (NHS). A low result on one occasion does not settle the matter; timing is easy to miss, and the test may be repeated.
A second set of hormones is measured early in the cycle, usually within the first few days of bleeding. These include follicle-stimulating hormone (FSH), which prompts the ovaries to mature an egg, and luteinizing hormone (LH), which triggers its release. Thyroid hormone and prolactin (a hormone that, when high, can suppress ovulation) are often added, since disorders of either can quietly stop periods.
Infection screening is routine and frequently overlooked by patients as a fertility test. Chlamydia is a common bacterial infection that can scar the fallopian tubes without causing symptoms, so a urine sample or swab is usually part of the initial workup (NHS).
The imaging step is a pelvic ultrasound, covered in the next section. Together, these first-line tests can be completed within one or two menstrual cycles, and they identify the cause, or rule out the common ones, in a large share of cases before anything more invasive is considered.
Pelvic ultrasound for fertility: what the scan can and cannot see
A pelvic ultrasound is a painless imaging test that uses high-frequency sound waves to create pictures of the uterus, ovaries, cervix and bladder. No radiation is involved, which is one reason it is the first imaging test in nearly every reproductive workup (MedlinePlus).
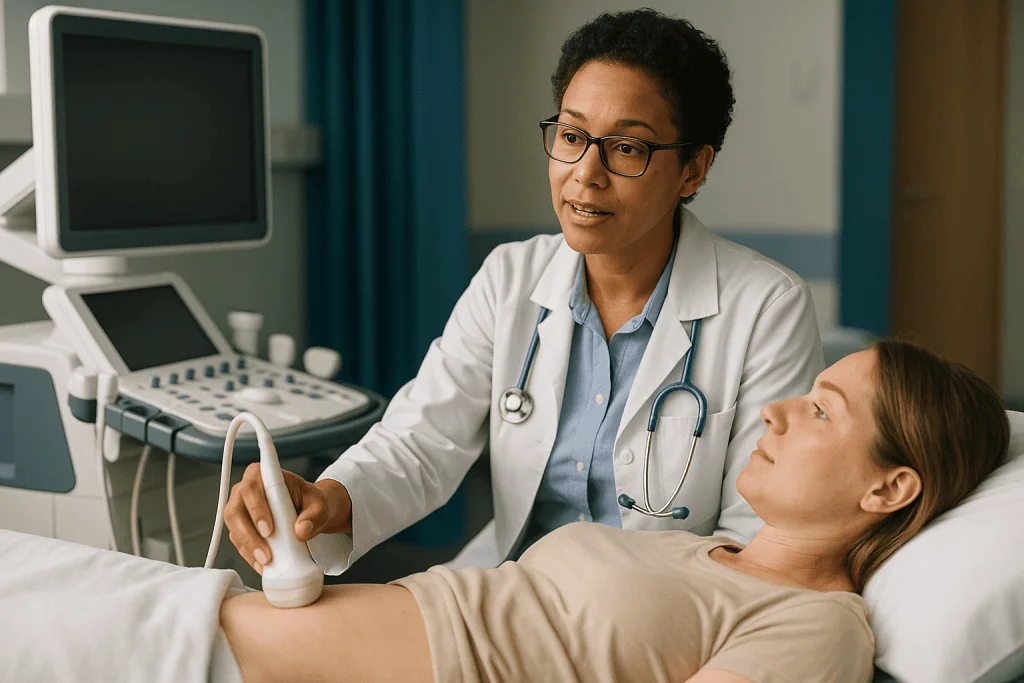
There are two ways to do it. In a transabdominal scan, gel is applied to the lower abdomen and a handheld probe is moved across the skin, often with a full bladder to push the bowel out of the way. In a transvaginal scan, a slim, covered probe is placed a short distance into the vagina. The transvaginal approach sits closer to the ovaries and gives sharper detail, so it is preferred for fertility questions. Most people describe it as a feeling of pressure rather than pain, and it usually takes 15–30 minutes (MedlinePlus).
What the scan shows well:
- The size and shape of the uterus, and growths such as fibroids (non-cancerous muscle tumors of the uterine wall) or polyps.
- The thickness of the uterine lining, which changes across the cycle.
- Ovarian cysts, and the pattern of many small follicles that can accompany PCOS.
- A count of small follicles early in the cycle, called the antral follicle count, used as one marker of ovarian reserve.
What it cannot reliably show: whether the fallopian tubes are open, since normal tubes are too thin to see; endometriosis outside the ovaries; and the quality of eggs, which no imaging test can assess. A normal ultrasound is reassuring about structure, but it does not by itself confirm fertility. Clinicians combine it with hormone results and, where needed, a tubal test.
Fertility hormone blood test: what each hormone tells the team
Hormone results are the part patients most often try to interpret alone, and the part most easily misread. Each hormone answers a narrow question, and the timing of the blood draw changes what a normal value looks like.
FSH is released by the pituitary gland at the base of the brain to stimulate follicles, the fluid-filled sacs that hold eggs. When ovarian reserve falls, the pituitary works harder and FSH rises. A raised early-cycle FSH can suggest reduced reserve, but the level swings from month to month, so a single result carries limited weight (MedlinePlus).
LH surges just before ovulation. Measured early in the cycle alongside FSH, an altered ratio between the two can point toward PCOS.
Estradiol is the main form of estrogen. A high early-cycle estradiol can mask a raised FSH, which is why the two are read together.
Anti-Müllerian hormone (AMH) is produced by small follicles and is relatively stable across the cycle, so it can be drawn on any day. It reflects the number of remaining eggs, not their quality, and it does not predict whether a person will conceive naturally, a distinction Mayo Clinic makes in its overview of ovarian reserve testing.
Progesterone, measured in the second half of the cycle, confirms that ovulation occurred.
Prolactin and thyroid-stimulating hormone (TSH) are checked because abnormalities in either can suppress ovulation and are treatable causes that are easy to miss.
For men, a hormone panel usually includes testosterone, FSH and LH, ordered when semen analysis is abnormal or when there are signs of low testosterone. In every case the pattern across several values, not any single number, guides the interpretation.
Are my fallopian tubes open? HSG and other tubal tests
The fallopian tubes are two narrow channels, each roughly the width of a strand of spaghetti, that carry the egg from the ovary toward the uterus. Fertilization happens inside them. If a tube is blocked by scarring from infection, endometriosis or previous surgery, egg and sperm cannot meet. Because ultrasound cannot see inside a normal tube, a separate test is needed.
The most common is a hysterosalpingogram, or HSG. A thin tube is passed through the cervix, a small amount of contrast dye is injected into the uterus, and X-ray images track the dye as it fills the uterine cavity and spills out of the ends of the tubes. Free spill on both sides means the tubes are open. The test also outlines the shape of the uterine cavity and can reveal polyps, fibroids pressing into the cavity or scar tissue. It is scheduled after a period ends and before ovulation, to avoid the possibility of an early pregnancy (Mayo Clinic).
People often ask about pain. Cramping during the dye injection is common and usually settles within minutes to a few hours; a small number of people find it quite uncomfortable. Light spotting afterward is normal. Infection is a rare complication, and clinicians typically screen for chlamydia before the procedure for this reason.
An alternative uses ultrasound instead of X-ray. Saline or a foam contrast is introduced into the uterus while a transvaginal scan watches it pass through the tubes. It avoids radiation and can be done in the same room as a routine ultrasound.
When the tubes need to be seen directly, or endometriosis is strongly suspected, laparoscopy may be offered. This is keyhole surgery under general anesthetic in which a camera inspects the pelvis and dye is flushed through the tubes. It is reserved for cases where less invasive tests have not answered the question, since it carries the risks of any surgery.
Male fertility tests: why semen analysis comes first
Fertility difficulties are shared roughly equally between partners, yet men are still sometimes tested last or not at all. The evidence argues the opposite order. A semen analysis is quick, non-invasive and identifies or excludes a male factor before a woman undergoes anything more involved.
The test requires a semen sample, usually produced by masturbation into a sterile container at the laboratory or brought in within a set time window. Clinicians generally ask for 2–7 days without ejaculation beforehand, because a shorter or longer gap can distort the count (Mayo Clinic).
The laboratory measures several things (MedlinePlus):
- Volume of the sample.
- Sperm concentration, the number of sperm per milliliter, and total count.
- Motility, the percentage of sperm that are moving and how purposefully they swim.
- Morphology, the proportion with a normal head, midpiece and tail shape.
- Signs of infection, such as white blood cells, and the acidity of the fluid.
A single result is a snapshot. Sperm take about two to three months to develop, and counts vary with illness, fever, heat exposure and stress, so an abnormal first result is almost always repeated after several weeks before conclusions are drawn (Mayo Clinic).
If the count is low or absent, further tests follow: hormone levels (testosterone, FSH, LH), a scrotal ultrasound to look for varicocele or blockage, genetic testing for chromosomal causes, and in selected cases a testicular biopsy to see whether sperm are being produced but not reaching the semen. Each of these is chosen by the team according to what the first analysis showed.
What are the parts of the male reproductive system, and which tests look at each?
Search engines see a steady stream of questions about the components of the male reproductive system, sometimes phrased as a numbered list. Anatomy textbooks count the parts differently, but the working structures are consistent, and each has a test that examines it.
The testicles (testes) produce sperm and testosterone. They are examined by hand, imaged by scrotal ultrasound, and their hormone output is checked by blood test. The epididymis is a coiled tube on the back of each testicle where sperm mature; swelling or blockage here shows up on ultrasound. The vas deferens carries sperm toward the urethra and is the tube cut in a vasectomy; its absence on one or both sides can be a clue to a genetic cause, which is why genetic tests are sometimes ordered when semen contains no sperm.
The seminal vesicles and prostate add most of the fluid in semen. Low semen volume or altered acidity on analysis can point toward a problem in these glands, and a transrectal ultrasound can image them directly. The urethra is the channel through the penis that carries both urine and semen; infection testing usually involves a urine sample or swab from here.
Above all of this sits the hypothalamus and pituitary in the brain, which send FSH and LH to the testicles. When testosterone is low, the pattern of FSH and LH tells the team whether the problem lies in the testicles themselves or in the signals reaching them (Mayo Clinic).
Thinking of the system as a supply chain helps. Sperm are manufactured, matured, transported and mixed with fluid before delivery. A test at each stage narrows down where the chain is interrupted.
Reproductive system tests compared: timing, discomfort and what each shows
Seeing the tests side by side makes the sequence easier to follow. Timing refers to when in the menstrual cycle the test is usually done; discomfort is described in the terms patients and clinical sources most commonly use.
| Test | Usual timing | What it shows | Typical experience |
|---|---|---|---|
| Early-cycle hormones (FSH, LH, estradiol) | Days 2–5 of bleeding | Ovarian reserve signals, PCOS pattern | Standard blood draw |
| AMH | Any day | Estimate of remaining egg number | Standard blood draw |
| Progesterone | About 7 days before expected period | Whether ovulation occurred | Standard blood draw |
| Transvaginal pelvic ultrasound | Often early cycle for follicle count | Uterus, ovaries, fibroids, cysts, follicle count | Pressure, 15–30 minutes, no radiation |
| Chlamydia and gonorrhea screen | Any time | Infections that can scar tubes | Urine sample or swab |
| Semen analysis | After 2–7 days without ejaculation | Sperm count, movement, shape | Sample production; often repeated |
| HSG | After period, before ovulation | Whether tubes are open, uterine cavity shape | Cramping during dye, brief X-ray exposure |
| Laparoscopy | Scheduled surgery | Direct view of pelvis, endometriosis, tubal patency | General anesthetic, keyhole incisions, recovery days |
Timing details draw on the NHS and Mayo Clinic overviews of fertility testing. The pattern in the table is the point: tests at the top are cheap in time and discomfort and are done in nearly everyone; those at the bottom are reserved for specific unanswered questions. A team that skips straight to laparoscopy without the earlier steps would be departing from standard practice.
What the following days and weeks usually look like
A reproductive workup rarely happens in one visit. Because several tests are tied to the menstrual cycle, the full picture typically takes one to two cycles to assemble, and longer if a semen analysis has to be repeated.
After blood tests there is nothing to recover from, and results usually return within days. Hormone results are often released to a patient portal before the clinician has reviewed them, which is when the numbers-without-context problem arises. A value flagged as high or low against a laboratory range may be entirely expected for the day of the cycle on which it was drawn.
Following a transvaginal ultrasound, most people return to normal activity immediately. Occasional light spotting can occur after a transvaginal probe.
After an HSG, cramping generally fades within hours, and spotting for a day or two is common. A small amount of dye leaking out is normal. Because the procedure involves instruments passing through the cervix, clinicians give specific advice about signs of infection to watch for in the following days (Mayo Clinic).
Laparoscopy is the exception in this list. It involves general anesthetic and small incisions, so people are usually advised to rest for a few days, expect shoulder-tip pain from the gas used to inflate the abdomen, and avoid strenuous activity until the team clears them. Recovery timelines vary with what was found and whether anything was treated during the same operation, and the surgical team gives individual guidance.
The results conversation is often the hardest week to wait for. It helps to know in advance that the most common outcome of a complete workup is one of three things: a specific treatable finding, a combination of smaller factors, or no clear cause identified, a situation the NIH describes as unexplained infertility. Each has its own pathway, and the treating team will lay out the options.
What common diseases of the reproductive system can these tests help find?
People searching for lists of reproductive conditions are usually trying to make sense of a symptom or a result. Rather than a self-diagnosis checklist, it is more useful to know which tests detect which conditions, since that explains why a clinician chose a particular test.
Polycystic ovary syndrome is suggested by hormone patterns plus an ultrasound showing many small follicles, alongside the clinical picture. Endometriosis, where tissue resembling the uterine lining grows outside the uterus, may show as ovarian cysts on ultrasound but is often only confirmed at laparoscopy. Uterine fibroids and polyps are usually visible on ultrasound and outlined further by HSG. Pelvic inflammatory disease, an infection of the upper reproductive tract most often caused by chlamydia or gonorrhea, is detected by swabs and can leave tubal scarring that HSG reveals later.
Premature ovarian insufficiency, where the ovaries stop working before age 40, shows as a raised FSH and low AMH on repeated testing. Thyroid disorders and high prolactin are found on blood tests and can disrupt ovulation in women and sperm production in men. Varicocele is felt on examination and confirmed by scrotal ultrasound. Obstruction of the sperm ducts is suspected when semen has no sperm but hormones are normal. Genetic conditions, such as Klinefelter syndrome in men or certain chromosomal variants in either partner, are identified by blood karyotyping when semen analysis or the history points that way. Sexually transmitted infections more broadly are screened by urine and blood tests.
This list is not exhaustive, and none of these conditions can be diagnosed from symptoms alone. The overlap between them is exactly why clinicians run a structured set of tests rather than guessing from the story. The NIH and WHO both stress that infertility frequently has more than one contributing cause.
What people often get wrong about reproductive system tests
Several beliefs recur so often in clinic that they are worth correcting directly.
A normal ultrasound means everything is fine. It means the uterus and ovaries look structurally normal on that day. It says nothing about tubal patency, egg quality, ovulation or the male partner. A workup is a set of complementary tests, not a single pass or fail.
AMH tells me how fertile I am. AMH estimates the number of remaining eggs. It does not measure their quality, and studies have not shown it predicts natural conception in women without a fertility problem (Mayo Clinic). It is most useful for planning treatments that involve stimulating the ovaries.
One bad semen result is a verdict. Counts fluctuate with fever, heat, stress and the interval since last ejaculation. Clinicians repeat the test precisely because one sample can mislead (Mayo Clinic).
Fertility problems are mostly a female issue. The WHO notes that infertility affects an estimated 1 in 6 people of reproductive age worldwide and that causes are found in men, in women, in both, or in neither with similar frequency. Testing both partners from the start is standard.
If nothing is found, nothing is wrong. Unexplained infertility is a recognized outcome, not a failure of the tests. It means current methods have not identified a cause, and it has its own treatment pathways.
Hormone results can be read against the printed range. Laboratory ranges are not adjusted for cycle day. A value outside the range may be normal for when it was drawn, and a value inside the range may still be informative in context. The interpretation belongs with the clinician who ordered the test.
Questions to ask your care team
The results appointment goes better when the questions are ready. These are the ones that tend to move a conversation from numbers to decisions.
- Which specific question was each test ordered to answer, and did it answer it?
- Were any results borderline rather than clearly abnormal, and will they be repeated?
- On which day of my cycle was each blood test drawn, and does that change how the results are read?
- Has my partner been tested, and are our results being considered together?
- Do I need a test of the fallopian tubes, and if so, which type do you recommend for me and why?
- What did the ultrasound show about follicle count and the uterine lining, and how does that fit with the hormone results?
- If the semen analysis was abnormal, what are the next tests, and what would each one tell us?
- Are there any findings that need treatment regardless of fertility plans, such as a thyroid problem or an infection?
- What would you expect to find at laparoscopy that earlier tests could not, and what are the risks of the procedure in my case?
- If no cause is identified, what does that mean for the options you would suggest?
- What lifestyle factors in my history are most likely to matter, based on what the tests showed?
- How long should we expect the rest of the workup to take, and what is the plan if results change?
Writing down the answers, or asking whether the plan can be summarized in the clinic letter, prevents the common experience of leaving with reassurance but no clear memory of what comes next. If a term is used that was not explained, asking for a one-sentence definition is reasonable and expected.
When to call your doctor
Most reproductive tests are low-risk, and most symptoms that prompt them are not emergencies. Some situations do need prompt attention, either during a workup or at any other time.
Seek urgent care, or contact the team the same day, for:
- Severe or worsening pelvic or abdominal pain, especially with fever, after an HSG, hysteroscopy or laparoscopy, which can signal infection or bleeding.
- Heavy vaginal bleeding that soaks through a pad an hour for more than two hours, or bleeding with dizziness or fainting.
- Sudden, severe pain in one testicle, particularly with swelling, nausea or vomiting, which can indicate testicular torsion, a twisting of the blood supply that requires emergency treatment.
- A positive pregnancy test alongside sharp one-sided pelvic pain, shoulder-tip pain or bleeding, since these can indicate an ectopic pregnancy outside the uterus.
- Fever, foul-smelling discharge or pain on urination in the days after any procedure through the cervix.
- Redness, spreading warmth or discharge at laparoscopy incision sites, or shortness of breath and calf pain after surgery.
Make a routine appointment, without waiting for the next scheduled test, for a new lump in the testicle or breast, bleeding between periods or after sex, periods that have stopped for three months or more without pregnancy, or pain that is affecting daily life. The NHS also advises seeing a clinician sooner than the standard one-year wait if there is any known reason to suspect a fertility problem.
None of these signs confirms a particular diagnosis. They are reasons to be assessed promptly so that the treating team can decide what, if anything, needs to happen next.
Frequently asked questions
How do I know if I have reproductive system issues?
You cannot confirm a reproductive problem from symptoms alone; a clinician needs a history, examination and targeted tests. Common reasons people are referred include not conceiving after 12 months of trying, very irregular or absent periods, pelvic pain, a testicular lump or a history of pelvic infection. If any of these apply, booking an appointment is the appropriate step rather than waiting or self-testing.
What are the most common female reproductive system tests?
The standard first round includes blood tests for FSH, LH, estradiol, AMH, progesterone, prolactin and thyroid hormone, a transvaginal pelvic ultrasound, and screening for chlamydia and gonorrhea. If those leave questions, a hysterosalpingogram checks whether the fallopian tubes are open. Hysteroscopy and laparoscopy, which look inside the uterus and pelvis with a camera, are reserved for specific unanswered questions.
What does a pelvic ultrasound for fertility show?
It shows the size and shape of the uterus, the thickness of its lining, fibroids, polyps, ovarian cysts and the number of small follicles in the ovaries, which is one marker of ovarian reserve. It does not show whether the tubes are open, whether eggs are of good quality, or endometriosis outside the ovaries. It uses sound waves, not radiation, and usually takes 15–30 minutes.
What is included in a fertility hormone blood test?
For women, usually FSH, LH and estradiol drawn early in the cycle, AMH on any day, progesterone in the second half of the cycle, plus prolactin and thyroid-stimulating hormone. For men, testosterone, FSH and LH are measured when semen analysis is abnormal or low testosterone is suspected. The cycle day matters, so results should be interpreted by the clinician who ordered them rather than against the printed range.
Which male fertility tests come first?
Semen analysis comes first because it is non-invasive and identifies or excludes a male factor quickly. It measures volume, sperm concentration, movement and shape after 2–7 days without ejaculation. An abnormal result is repeated after several weeks. Further tests such as hormone levels, scrotal ultrasound, genetic testing or, rarely, testicular biopsy follow only if the analysis points that way.
What are 10 common diseases of the reproductive system?
Conditions frequently identified during reproductive testing include polycystic ovary syndrome, endometriosis, uterine fibroids, uterine polyps, pelvic inflammatory disease, premature ovarian insufficiency, thyroid-related ovulation problems, varicocele, obstruction of the sperm ducts and sexually transmitted infections such as chlamydia. Genetic conditions and high prolactin are also on the list. None can be diagnosed from symptoms alone; each is confirmed by specific tests.
What is the 12 male reproductive system?
This search usually refers to the parts of the male reproductive system, which textbooks number differently. The main structures are the testicles, epididymis, vas deferens, seminal vesicles, prostate, urethra and penis, controlled by hormone signals from the hypothalamus and pituitary in the brain. Each part has a corresponding test: physical exam and ultrasound for the testicles, semen analysis for the glands and ducts, and blood tests for the hormone signals.
Does an HSG hurt, and is the radiation a concern?
Most people feel cramping during the few minutes when dye is injected, similar to strong period pain, and it usually settles within hours. A minority find it very uncomfortable, and the team can discuss pain relief options in advance. The X-ray exposure is brief and low. The test is scheduled after a period and before ovulation to avoid the possibility of an early pregnancy.
How long does a full reproductive workup take?
Typically one to two menstrual cycles, because several blood tests are tied to specific cycle days and the ultrasound is often timed to the early cycle. A repeat semen analysis adds several weeks. If tubal testing or laparoscopy is needed, the timeline extends further. Individual scheduling varies, and the treating team can outline the expected sequence at the first visit.
What happens if all my reproductive system tests are normal?
It means the current standard tests have not identified a cause, a situation clinicians call unexplained infertility. It is a recognized outcome, not a failure of the workup, and it has its own treatment pathways that the team will discuss. Normal results also rule out several conditions that would have needed separate treatment, which is useful information in itself.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Male Fertility Test: What a Semen Analysis Measures and What the Numbers Mean
A male fertility test usually begins with a semen analysis, a laboratory test that measures semen volume, sperm concentration, total sperm count, motility (movement),…

PCOS Belly: Why Insulin Resistance Shapes Fat Distribution, and What Helps
PCOS belly is the informal name for abdominal fat that builds up in polycystic ovary syndrome, largely because insulin resistance and higher androgen levels…

Postpartum Hair Loss: Why It Happens, When It Peaks and When It Is Something Else
Postpartum hair loss is a temporary shedding, called telogen effluvium, that usually begins two to four months after delivery, peaks around month three to…
Preparing Your Body and Calendar for IVF: Ovarian Reserve Tests, Screening and Timing
Preparing for IVF usually starts two to three months before a cycle. Your team checks ovarian reserve with an AMH blood test and an…

When Does Trying Become Infertility? How Long to Wait Before an Evaluation and Who Goes Sooner
Most guidelines define infertility as not conceiving after 12 months of regular, unprotected sex, and that is the usual point to request an evaluation.…