

Which Tests Diagnose Asbestosis? Chest CT, Spirometry and the Role of Your Exposure History

Key Takeaways
- No blood test can confirm asbestos exposure; the diagnosis rests on a documented history of heavy exposure combined with imaging and lung function findings.
- High-resolution chest CT detects early fibrosis that a plain chest X-ray misses, and is usually performed with some images taken face down to separate scarring from gravity effects.
- Spirometry in asbestosis typically shows a restrictive pattern, with reduced forced vital capacity, and gas transfer (DLCO) often falls before other measurements change.
- Pleural plaques on a scan indicate past exposure and are not the same as asbestosis, which specifically means scarring within the lung tissue.
- Symptoms usually appear 10 to 40 years after exposure, so the condition is most often diagnosed in people who left the relevant trade decades earlier.
- Lung biopsy is rarely needed when the exposure history is clear and the CT pattern is typical, because it adds risk without adding certainty.
Asbestosis is diagnosed by combining three things: a documented history of significant asbestos exposure, usually decades earlier; imaging that shows lung scarring, with high-resolution chest CT being more sensitive than a plain X-ray; and lung function tests such as spirometry and gas transfer that reveal stiff, less efficient lungs. There is no single blood test. Lung biopsy is rarely needed, and the diagnosis always rests with a specialist team.
A retired pipefitter sits across from a respiratory physician with a folder on his knee. In it are the names of two shipyards, a boiler room, and the brand of lagging he used to cut with a handsaw. He has been short of breath on the stairs for about a year, and his wife has noticed a dry cough that never quite goes. The question he came to ask is simple: is this asbestosis, and what tests will tell us?
The honest answer surprises many people. The most important piece of evidence is already in that folder. Imaging and breathing tests confirm and measure the damage, but they cannot on their own say what caused it. Asbestosis diagnosis tests only make sense when they are read alongside a careful account of where you worked, for how long, and how dusty it was.
This explainer walks through each step, from the first conversation to the scan, so that you know what to expect and what each result can and cannot tell you.
What actually happens in the lungs when asbestos fibers cause scarring
Asbestos is not one mineral but a group of six naturally occurring silicate fibers that split into strands far thinner than a human hair. Those strands are the problem. Breathed in, the longest and thinnest ones travel past the mucus and tiny hairs that clear ordinary dust and lodge deep in the air sacs, the alveoli, where oxygen passes into the blood.
The immune system treats each fiber as an invader. Scavenger cells called macrophages try to swallow them, fail because the fibers are too long, and release inflammatory chemicals as they die. Over years, that smoldering inflammation lays down scar tissue around the fiber, a process doctors call fibrosis. Scar tissue is stiff and does not exchange gas. As more of the lung becomes scarred, it loses its elasticity, so each breath takes more effort and delivers less oxygen.
Two features of this process shape how the condition is diagnosed. First, it is slow. The Mayo Clinic notes that symptoms usually appear 10 to 40 years after exposure, because scarring accumulates gradually and the lungs have enormous reserve. Second, it is dose related. Asbestosis, as distinct from other asbestos-related conditions, is generally seen in people with heavy or prolonged exposure, typically in trades such as insulation work, shipbuilding, boiler making, construction and asbestos mining. A brief, incidental contact with intact asbestos material does not normally produce this kind of scarring.
Understanding the mechanism also explains why the scarring has a recognizable pattern on scans. Fibers settle under gravity and along airflow, so the earliest changes cluster in the lower, outer parts of both lungs and often sit alongside thickening of the pleura, the thin membrane that wraps each lung. Radiologists look for exactly that distribution when they read the images described below.
Why your exposure history is the first of the asbestosis diagnosis tests
Scans show scarring. Spirometry measures stiffness. Neither can see an asbestos fiber. Many other diseases scar the lungs in a similar way, so the thing that turns a general picture of fibrosis into a diagnosis of asbestosis is a credible history of exposure. Clinicians treat that history as a test in its own right, and they take it seriously.

Expect detailed questions. Which jobs did you hold, and in which decades? Did you cut, drill, sand or strip material, or simply work in a building that contained it? Were respirators used, and how consistently? How many years did the exposure last? Did you handle a family member’s dusty work clothes? The NHS describes this kind of occupational interview as a core part of the assessment, alongside the physical examination and imaging.
Write it down before the appointment. Dates do not need to be exact, but the sequence of jobs and the tasks you performed help enormously. Old pay records, union documents or a colleague’s recollection can fill gaps. If you are unsure whether a material contained asbestos, say so; the clinician can often judge from the trade and era.
The physical examination follows the conversation. The doctor listens to the bases of your lungs for fine, crackling sounds at the end of a breath in, often compared to the sound of Velcro being pulled apart. Mayo Clinic lists these crackles and finger clubbing, a widening and rounding of the fingertips seen in some chronic lung conditions, among the signs doctors check for. Neither finding is specific to asbestosis, but together with the history they raise or lower the likelihood before any imaging is ordered.
Asbestosis chest X-ray: what it shows and what it misses
A plain chest X-ray is usually the first image taken, partly because it is quick and widely available and partly because it is the tool used in many occupational screening programs. On an X-ray, established asbestosis appears as small, irregular shadows in the lower lung fields, giving the normally dark lung a hazy, net-like texture. Thickened or calcified pleura along the chest wall and diaphragm often appears alongside it.
Occupational physicians frequently grade these films using the International Labour Organization (ILO) classification, a standardized scoring system in which the reader compares the patient’s film against reference images and assigns a profusion score for how dense the small shadows are. Readers trained in this method are sometimes called B readers, a certification run by the National Institute for Occupational Safety and Health (NIOSH) within the CDC. The system was designed to make readings consistent between hospitals and over time, which matters when surveillance films are compared year after year.
The X-ray has a real weakness, though. The Mayo Clinic notes that chest X-ray changes may not be visible in the early stages, and that CT is better at detecting the condition before it shows on a plain film. In practice, a normal X-ray in a person with heavy exposure and new breathlessness does not rule anything out. It simply moves the question to the next test.
The reverse is also true. An X-ray showing pleural plaques alone, without the small irregular shadows in the lung tissue, points to past exposure rather than to asbestosis. That distinction is one of the most common sources of confusion for patients, and it is worth asking the reporting doctor to spell out exactly which structures are affected.
High-resolution chest CT: the imaging test that carries the most weight
High-resolution computed tomography, or HRCT, is a CT scan that takes very thin slices through the chest, roughly a millimeter thick, so that fine detail in the lung tissue becomes visible. It is the imaging test that most specialist teams rely on when asbestosis is suspected, because it can show early scarring that an X-ray cannot resolve.
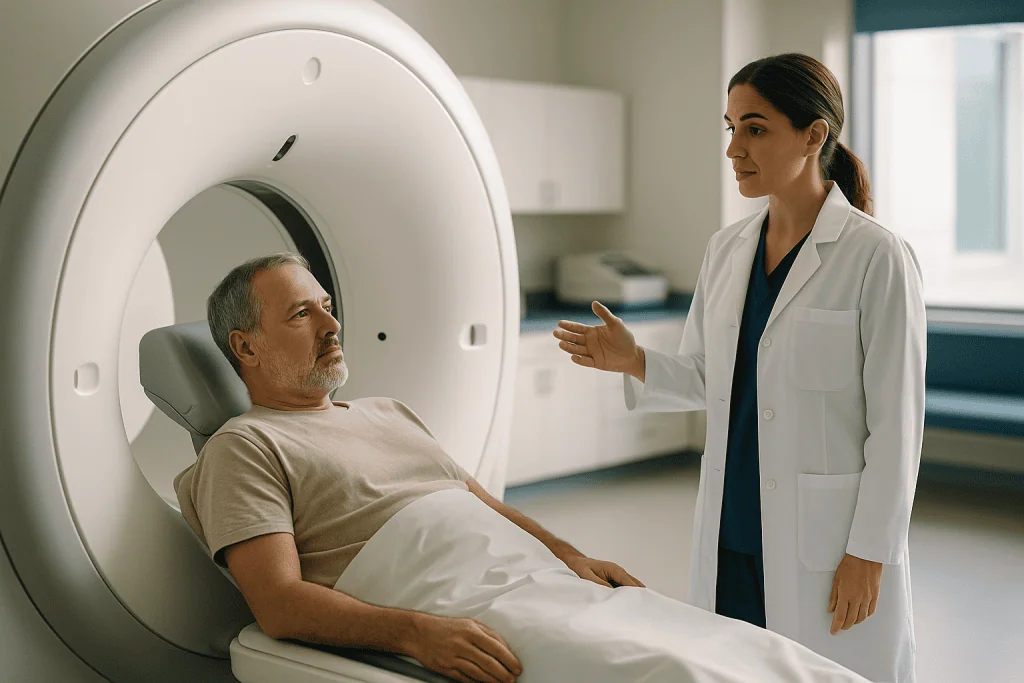
The radiologist is looking for a specific pattern. Early changes include short lines running from the lung surface inward, called subpleural curvilinear lines, and small dots that represent scarring around the smallest airways. As the disease advances, these coalesce into reticulation, a mesh of fine lines, and in later stages into honeycombing, which is a cluster of small air-filled cysts with thick walls that marks irreversibly destroyed lung. The changes are usually symmetrical, worst in the lower lobes, and accompanied by pleural thickening or plaques.
Technique matters. Scans are typically done with you lying face down for at least some images, because in the usual face-up position the lowest part of the lung sags under its own weight and can look hazy even in healthy people. Turning you over separates genuine scarring from that gravity effect. Some protocols also include images taken after a full breath out to assess small-airway trapping.
HRCT is not perfect. A small group of people with proven asbestosis have scans that look normal, and other causes of fibrosis can produce similar appearances. Radiation exposure is also higher than for a plain film, which is one reason it is not used for routine screening of symptom-free workers. The Cleveland Clinic lists CT alongside X-ray and lung function tests as the standard components of the workup, and in most pathways the HRCT result, read together with the exposure history, is what allows the team to commit to a diagnosis.
Spirometry and lung function tests: measuring how stiff the lungs have become
Imaging shows where the scarring is. Lung function testing shows what it is doing to your breathing. Spirometry is the simplest of these tests: you breathe out as hard and fast as you can through a mouthpiece connected to a machine that measures the volume and speed of air leaving your lungs.
Two numbers matter most. Forced vital capacity, or FVC, is the total amount of air you can blow out after a full breath in. Forced expiratory volume in one second, FEV1, is the amount you expel in the first second. Scarred lungs are small and stiff, so FVC falls, while the airways themselves are relatively open, so FEV1 falls in proportion. Doctors call this a restrictive pattern, and it is the opposite of what is seen in asthma or emphysema, where air gets out slowly but total volume is preserved or even increased. Many people with asbestosis who also smoked show a mixed picture.
A second test, called gas transfer or diffusing capacity (DLCO), measures how easily a tracer gas crosses from the air sacs into the blood. Because fibrosis thickens the barrier between air and blood, DLCO is often reduced before spirometry changes become obvious. Full lung volume measurements in a sealed booth, body plethysmography, confirm the restriction by measuring the total air the lungs can hold.
Results are expressed as a percentage of what is predicted for someone of your age, sex, height and ancestry, which is why a single number is never read in isolation. The NHS and Mayo Clinic both describe lung function tests as part of the standard assessment, and specialist teams repeat them at intervals because the trend over time, not any single visit, is what shows whether the disease is stable or progressing.
Is there an asbestos exposure test? Blood tests, sputum and when biopsy is considered
People often ask for a blood test that proves they were exposed. None exists for routine clinical use. Asbestos fibers do not circulate in the bloodstream, and the proteins the body releases in response are not specific enough to confirm or exclude the diagnosis. Blood tests are still ordered during the workup, but their purpose is to rule out other causes of lung fibrosis, such as autoimmune conditions like rheumatoid arthritis or scleroderma, and to check general health before any treatment decisions.
Fibers can occasionally be detected directly. Under a microscope, an asbestos fiber coated by the body’s iron-rich protein looks like a tiny golden dumbbell and is called an asbestos body or ferruginous body. These can sometimes be found in sputum or in fluid washed out of the lungs during a bronchoscopy, a procedure in which a thin flexible camera is passed through the nose or mouth into the airways. Finding them confirms exposure but does not by itself diagnose asbestosis, and not finding them does not exclude it, because the technique misses many fibers and some exposed people clear them.
Lung biopsy, the removal of a small piece of tissue for examination, is the only way to see fibrosis and fibers together. It is rarely needed. Guidance from the Mayo Clinic and the NHS reserves it for situations where the imaging pattern is unusual, the exposure history is uncertain, or a different diagnosis such as cancer needs to be excluded. Biopsy carries risks of bleeding, infection and air leak, and when the history is clear and the HRCT pattern is typical, most teams judge that the extra certainty is not worth the risk.
If you are offered any of these procedures, ask what specific question the team hopes it will answer. A good answer should change the plan, not merely add a result to the file.
Asbestosis diagnosis tests compared: what each one can and cannot tell you
Each test answers a different question, and the diagnosis is built from their combination rather than from any single result. The table below summarizes what the main investigations contribute, based on descriptions in NHS, Mayo Clinic and Cleveland Clinic patient resources.
| Test | What it involves | What it can show | Main limitation |
|---|---|---|---|
| Exposure history and examination | Detailed occupational interview; listening to the chest; checking fingers | Likelihood of asbestos as the cause; crackles and clubbing | Depends on memory and records; findings are not specific |
| Chest X-ray | Standing against a plate for a few seconds | Established scarring, pleural plaques, thickening | Often normal in early disease |
| High-resolution CT | Lying on a scanner table, often face down for part of the scan | Early fibrosis, its pattern and distribution, honeycombing | Higher radiation dose; patterns overlap with other fibrotic diseases |
| Spirometry and lung volumes | Forced breathing into a mouthpiece; sitting in a sealed booth | Restrictive pattern; how much capacity is lost | Cannot identify the cause; affected by smoking and other conditions |
| Gas transfer (DLCO) | Single breath of tracer gas held briefly | Reduced oxygen transfer, sometimes before other tests change | Also reduced in emphysema and anemia |
| Blood tests | Standard venous sample | Exclusion of autoimmune or other causes | No test confirms asbestos exposure |
| Bronchoscopy or biopsy | Camera into the airways; tissue sample under sedation or anesthesia | Asbestos bodies; fibrosis under the microscope | Invasive; rarely needed when history and CT agree |
Reading the table from top to bottom also roughly follows the order in which tests are done. The history and examination come first because they decide whether imaging is warranted at all. Imaging comes next because it is non-invasive. Lung function testing is usually arranged alongside or soon after imaging, and the invasive tests sit at the end as options the team may never need to use.
Who is usually tested for asbestosis, and who is usually asked to wait
Not everyone who has ever been near asbestos needs a scan. Clinicians weigh two things: how substantial the exposure was and whether there are symptoms or signs to explain. People with years of heavy occupational exposure who have developed breathlessness on exertion, a persistent dry cough, crackles on examination or clubbing are usually investigated promptly with imaging and lung function tests. The same applies to those whose chest X-ray, taken for another reason, has shown changes that could be fibrosis.
A second group is enrolled in surveillance rather than diagnosis. In several countries, workers with documented exposure are offered periodic medical reviews through occupational health programs. The CDC’s NIOSH describes medical surveillance for asbestos-exposed workers that includes a questionnaire, examination, spirometry and, in some programs, chest X-ray at set intervals. The aim is to catch change early, not to confirm disease in people who feel well.
Then there are people who are usually asked to wait, or reassured rather than scanned. Someone who lived in a house with intact asbestos cement roofing, or who worked briefly in an office building where asbestos was later found, has had a very different level of exposure from an insulation worker. Mayo Clinic notes that most people with asbestosis acquired it through prolonged work with the material. For low-level exposure without symptoms, a CT scan carries radiation risk and a real chance of finding incidental changes that cause anxiety without improving health. In that situation, many clinicians recommend recording the exposure in the medical notes, staying alert to new symptoms, and not smoking, rather than ordering imaging.
Children and younger adults exposed through a parent’s work clothes fall between these groups and are assessed individually. Whichever group you are in, the decision about whether and when to test rests with the clinician who has your full history in front of them, and it is reasonable to ask them to explain their reasoning.
Asbestosis vs mesothelioma and other look-alikes: how doctors tell them apart
Asbestos causes several distinct conditions, and the testing pathway is partly about telling them apart. Pleural plaques are patches of thickened, sometimes calcified pleura. They are the most common asbestos-related finding, usually cause no symptoms, and are a marker of exposure rather than a disease of the lung tissue. Diffuse pleural thickening is more extensive and can restrict breathing. Benign asbestos pleural effusion is fluid between the lung and chest wall. None of these is asbestosis, which specifically means fibrosis within the lung tissue itself.
Mesothelioma is a cancer of the pleura or, less often, the lining of the abdomen. It is strongly linked to asbestos but can follow much lower exposures than asbestosis. On imaging it tends to produce irregular, lumpy pleural thickening and fluid, and its diagnosis requires tissue, so a suspicion of mesothelioma changes the plan toward biopsy in a way that a typical asbestosis picture does not. The NHS lists mesothelioma, lung cancer and pleural disease among the conditions people with asbestosis are at increased risk of developing, which is why follow-up imaging looks for new masses as well as progression of scarring.
The hardest distinction is from idiopathic pulmonary fibrosis, or IPF, a scarring disease of unknown cause that produces a very similar lower-lobe pattern on HRCT. Two clues favor asbestosis: the presence of pleural plaques, which are rare in IPF, and a convincing exposure history. Where the history is weak, teams increasingly discuss the case at a multidisciplinary meeting with radiologists and sometimes pathologists before settling on a label, because the distinction affects the treatment options discussed later.
Other fibrotic conditions, including those linked to autoimmune disease, certain medicines and other mineral dusts such as silica, are excluded through the history, blood tests and imaging pattern. That is why the workup can feel broader than the single question you came in with.
What are the stages of asbestosis? Why there is no formal staging system
Searches for asbestosis stages are common, and the honest answer is that asbestosis does not have a numbered staging system of the kind used for cancers. Doctors describe severity instead, drawing on three sources: how extensive the changes are on imaging, how much lung function has been lost, and how limited a person is day to day.
On imaging, the earliest changes are the subtle subpleural lines and dots described earlier, visible on HRCT but not on X-ray. Moderate disease shows clear reticulation through the lower lobes, often with pleural thickening, and begins to appear on plain films. Advanced disease shows honeycombing, volume loss and distortion of the airways. On X-ray, the ILO profusion score provides a graded scale that occupational physicians sometimes use as a shorthand for this progression.
Lung function adds numbers to the picture. FVC and DLCO are reported as percentages of predicted, and specialists broadly describe impairment as mild, moderate or severe according to how far those figures have fallen. These thresholds are used in interstitial lung disease generally rather than being specific to asbestosis, and your clinician can explain where your own results sit.
Symptoms often map loosely onto these findings but not always. Some people with striking scans walk briskly without complaint; others with modest changes feel breathless, usually because another condition such as emphysema or heart disease is adding to the load. For this reason, teams avoid giving a single stage and instead monitor trends. The Mayo Clinic describes asbestosis as a condition that can continue to progress slowly even after exposure has stopped, which is why the direction of travel over repeated tests tells you more than any one-time label.
What the weeks after testing usually look like
The pathway from first appointment to a settled diagnosis is rarely a single visit. A typical sequence begins with the occupational history and examination in a general or respiratory clinic, followed by a chest X-ray and spirometry, which can often be done the same day. If those raise suspicion, a high-resolution CT and full lung function tests including gas transfer are booked. Waiting times for these vary widely between health systems and are not something any article can promise.
Once the images and breathing tests are back, many respiratory teams review them together before meeting you again. In cases where the picture is clear, the diagnosis is explained at that follow-up and a monitoring plan is agreed. Where the pattern is atypical, the team may request a multidisciplinary discussion, repeat imaging after an interval, or, rarely, propose bronchoscopy or biopsy. Each of those steps adds weeks rather than days.
After the diagnosis, follow-up settles into a rhythm. The NHS describes regular monitoring with repeated lung function tests and, where appropriate, imaging, so that any progression or complication is picked up early. Many clinics also arrange a six-minute walk test, in which your oxygen levels are measured while you walk along a corridor, to see whether oxygen falls on exertion.
Practical conversations happen in this period too. In the United States and the United Kingdom, asbestosis is a recognized occupational disease, and clinicians can usually point you toward the official processes for recording it and for any benefits you may be entitled to; this article does not cover that process. Expect also to be asked about smoking status at every visit, about vaccinations against influenza, pneumococcus and COVID-19, and about whether a pulmonary rehabilitation program would suit you. These are the elements that most reliably influence how you feel, and they begin as soon as the diagnosis is made.
Can asbestosis be treated, and is it a terminal illness?
These two questions sit behind almost every diagnostic appointment, so it is fair to address them directly even though decisions about care belong to your team.
Asbestosis can be managed, but existing scar tissue cannot be reversed. Both the NHS and Mayo Clinic state plainly that no treatment removes the fibrosis or undoes the damage already done. What treatment can do is ease symptoms, protect the remaining lung, and address the other conditions that commonly travel alongside. Stopping smoking is the single intervention with the clearest effect, because smoking and asbestos together multiply the risk of lung cancer far beyond either alone. Pulmonary rehabilitation, a supervised program of exercise and education, helps many people do more with the lung capacity they have. Supplemental oxygen is offered when blood oxygen falls below defined levels at rest or on exertion. Vaccinations reduce the chance of infections that stiff lungs tolerate poorly. In a small number of people with severe disease, lung transplantation is discussed. Antifibrotic medicines, drugs that slow the laying down of scar, are approved for some other fibrotic lung diseases; whether they help in asbestosis is not established, and any discussion of them belongs with a specialist.
On the question of whether asbestosis is terminal, the evidence does not support a single answer. The condition is chronic and can progress, and the NHS notes it is associated with a shortened life expectancy in some people, particularly those with extensive disease or complications. Yet many people live for years, even decades, with stable or slowly changing lung function, and the leading risks to life are often the related cancers rather than the fibrosis itself. Your own outlook depends on how much scarring is present, how fast it is changing, your smoking history and your other health conditions. The team that has seen your scans and function tests is the only source that can discuss this honestly with you.
What people often get wrong about asbestosis tests
Several beliefs come up again and again in clinic, and correcting them saves worry.
The first is that a normal chest X-ray means no asbestos damage. It does not. Plain films miss early fibrosis, which is why clinicians move to HRCT when the history and symptoms warrant it. The reverse error is equally common: people see the word “pleural plaques” on a report and assume they have asbestosis. Plaques indicate exposure and are usually harmless; asbestosis means scarring in the lung tissue, and the two are reported separately.
A second myth is that a blood or urine test can confirm exposure. No such test exists for routine use. Companies that advertise exposure testing kits are not offering anything that specialist teams rely on, and the blood tests you will have in clinic are there to exclude other diagnoses.
Third, many people believe that because their exposure ended years ago, nothing can be happening now. Asbestosis typically becomes apparent decades after exposure, which is why older adults who have long since left the trade are the usual patients, and why the NHS advises reporting breathlessness to a doctor even when the exposure is distant.
Fourth is the idea that a biopsy is needed for a proper diagnosis. In most cases it is not. When the exposure is well documented and the HRCT pattern is typical, the diagnosis is made without tissue, and biopsy adds risk without adding certainty.
Finally, some assume that an asbestosis diagnosis is the same as a cancer diagnosis. It is not. The conditions are distinct, though people with asbestosis carry a higher lifetime risk of lung cancer and mesothelioma, which is precisely why ongoing surveillance, and not smoking, matter so much after diagnosis.
Questions to ask your care team about asbestosis testing
A diagnostic workup goes better when you understand each step, and clinicians generally welcome specific questions. Consider taking a written list to your appointments. Useful ones include:
- Based on my work history, how significant do you consider my exposure, and does it fit the pattern usually seen in asbestosis?
- Which tests are you ordering, and what specific question is each one meant to answer?
- Will my CT be done with images taken face down, and is it a high-resolution protocol?
- Does my X-ray or scan show pleural plaques, lung tissue scarring, or both? Can you show me on the image?
- What do my spirometry and gas transfer results mean as percentages of predicted, and how will you track them over time?
- Are there other conditions you are considering, such as idiopathic pulmonary fibrosis, and what would change your mind?
- Is a bronchoscopy or biopsy being considered, and if so, how would the result alter my care?
- How often should I have follow-up imaging and lung function tests, and what would prompt an earlier review?
- Would pulmonary rehabilitation, oxygen assessment or vaccination be appropriate for me, and who arranges them?
- Should my family members who may have been exposed through my work clothes be assessed?
- How do I ensure this is recorded as an occupational disease, and where can I get reliable information about that process?
You are entitled to a clear explanation of each result in plain language and to copies of your reports. If anything remains unclear after the appointment, asking for a written summary or a follow-up call is a reasonable request, and many teams provide a named contact for exactly that purpose.
When to call your doctor
Most of the asbestosis pathway moves at a measured pace, but some situations need prompt attention. Contact your doctor without delay, or use emergency services where appropriate, if you notice any of the following.
- Sudden or rapidly worsening breathlessness, especially if it comes on over hours or a few days rather than months. This can signal a chest infection, a collapsed lung, fluid around the lung or a blood clot, all of which stiff lungs tolerate poorly.
- Chest pain that is sharp, one-sided or worse on breathing in, or any new, persistent chest or shoulder pain.
- Coughing up blood, even a small amount.
- Blue or gray tinge to the lips or fingertips, confusion, or drowsiness, which can indicate falling oxygen levels.
- Fever with a productive cough, or a cough that changes character and does not settle.
- Unexplained weight loss, loss of appetite, night sweats or a new hoarse voice lasting more than a couple of weeks.
- New swelling of the ankles or legs, which can reflect strain on the right side of the heart from long-standing lung disease.
- Any new symptom that worries you, particularly if you have a history of heavy asbestos exposure and have not yet been assessed.
The NHS advises anyone who has been exposed to asbestos in the past and develops breathlessness or a persistent cough to see a doctor, even if the exposure was decades ago. For people already diagnosed, the Mayo Clinic emphasizes regular follow-up so that complications are caught early. If you are waiting for tests and your symptoms change meaningfully in the meantime, tell the clinic; the timetable can usually be adjusted. Every decision about further investigation and treatment belongs with the team looking after you, but you should never feel you have to wait for a scheduled appointment to report a red-flag sign.
Frequently asked questions
Are there any tests for asbestosis?
Yes, though no single test gives the answer on its own. Doctors combine a detailed occupational exposure history, a physical examination listening for fine crackles, a chest X-ray, a high-resolution CT scan and lung function tests including spirometry and gas transfer. Blood tests are used to exclude other causes of scarring. Bronchoscopy or lung biopsy is reserved for unusual cases where the history and imaging do not agree.
Can asbestosis be treated?
Asbestosis can be managed but the existing scarring cannot be reversed. Treatment focuses on easing symptoms and protecting remaining lung function through stopping smoking, pulmonary rehabilitation, vaccinations and, where oxygen levels fall, supplemental oxygen. Lung transplantation is considered for a small number of people with severe disease. Whether antifibrotic medicines help in asbestosis is not established, and all treatment decisions rest with the respiratory team.
Is asbestosis a terminal illness?
Not in a fixed sense. Asbestosis is a chronic, sometimes progressive condition that can shorten life in people with extensive disease or complications, but many people live for years with stable or slowly changing lung function. The greater risks are often the related cancers, lung cancer and mesothelioma, rather than the fibrosis itself. Your individual outlook depends on scan findings, lung function trends, smoking history and other health conditions, which only your team can assess.
What are the different stages of asbestosis?
There is no formal numbered staging system. Severity is described using three sources: the extent of changes on imaging, from subtle lines on CT through reticulation to honeycombing; lung function results, often labelled mild, moderate or severe according to how far forced vital capacity and gas transfer have fallen; and how limited you are day to day. Doctors monitor the trend over repeated tests rather than assigning a single stage.
Does a chest X-ray show asbestosis?
Often, but not reliably in early disease. Established asbestosis appears as small irregular shadows in the lower lungs, frequently with pleural thickening or plaques. In the early stages these changes may not be visible on a plain film, which is why a high-resolution CT scan is ordered when exposure history and symptoms raise suspicion. A normal X-ray in someone with heavy exposure and new breathlessness does not exclude the condition.
Is there an asbestos exposure test using blood or urine?
No. There is no blood or urine test in routine clinical use that confirms or rules out asbestos exposure. Fibers do not circulate in blood, and the body’s response markers are not specific enough. Asbestos bodies can sometimes be seen in sputum or fluid washed from the lungs during bronchoscopy, which confirms exposure but not disease. Clinic blood tests are used to exclude other causes of lung scarring.
What is the difference between asbestosis and mesothelioma?
Asbestosis is scarring of the lung tissue itself, caused by heavy, prolonged asbestos exposure and diagnosed mainly through history, CT and lung function tests. Mesothelioma is a cancer of the lining around the lung or abdomen, can follow lower exposures, and requires a tissue sample for diagnosis. People with asbestosis have an increased risk of mesothelioma and lung cancer, which is one reason for ongoing surveillance after diagnosis.
How long after asbestos exposure do symptoms appear?
Usually decades. The Mayo Clinic notes that signs and symptoms typically appear 10 to 40 years after initial exposure, because scar tissue accumulates slowly and the lungs have considerable reserve. This long latency is why most people diagnosed with asbestosis are older adults who left the relevant trade long ago, and why clinicians ask about jobs from early in your working life.
What does spirometry show in asbestosis?
Spirometry in asbestosis typically shows a restrictive pattern: the total air you can force out, called forced vital capacity, is reduced because the lungs are stiff and small, while the proportion exhaled in the first second remains normal or high. People who also smoked may show a mixed pattern. Gas transfer, measured separately, is often reduced early because thickened scar tissue slows oxygen crossing into the blood.
Do I need a lung biopsy to diagnose asbestosis?
Usually not. When there is a well-documented history of substantial exposure and the high-resolution CT shows the typical lower-lobe scarring with pleural changes, specialists make the diagnosis without tissue. Biopsy carries risks of bleeding, infection and air leak, so it is reserved for cases where the imaging pattern is unusual, the exposure history is uncertain, or another condition such as cancer needs to be excluded.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Pulmonary Edema Is Treated in the Emergency Room: Oxygen, Diuretics and Monitoring
Pulmonary edema emergency treatment focuses on getting oxygen into the blood and fluid out of the lungs quickly. Emergency teams typically sit the person…

Questions to Ask at Your Asthma Review: Triggers, Inhaler Technique and Follow-Up
At an asthma review, the most useful questions to ask cover three areas: which triggers are driving your symptoms and how to reduce exposure,…

Can You Fly With Emphysema? Altitude, In-Flight Oxygen and Planning Long Trips
Many people with emphysema can fly, but it depends on how much oxygen your blood carries at rest and how stable your lungs have…

Living With Bronchiectasis: Exercise, Travel and Fitting Airway Clearance Into Your Day
Living with bronchiectasis usually centers on a daily airway clearance routine, regular physical activity, and prompt attention to flare-ups. Most people can exercise and…

Flying After a Pneumothorax: Why Doctors Ask You to Wait and How Clearance Works
Flying after a pneumothorax is usually delayed until a follow-up chest X-ray confirms the lung has fully re-expanded, then for a further waiting period…

When Does a Chronic Cough Need a Pulmonologist? How Lung Disease Evaluation Is Organized
A cough that has lasted eight weeks or more in an adult, or that comes with breathlessness, coughing up blood, unexplained weight loss, or…