

Which Tests Guide Cystic Fibrosis Care? Sweat Test, Genetic Testing and Sputum Cultures

Key Takeaways
- A sweat chloride result of 60 mmol/L or more is consistent with cystic fibrosis, below 30 makes it unlikely, and 30 to 59 is genuinely uncertain and needs genetic testing and specialist review.
- Newborn screening uses a blood-spot IRT measurement and is deliberately sensitive, so most screen-positive babies turn out not to have CF once the sweat test is done.
- Infants usually need to be about two weeks old and over roughly 2 kilograms before a sweat test can reliably collect enough sweat.
- A targeted CFTR panel can miss rare variants, especially outside the ancestry it was designed for, so a negative carrier result lowers risk without eliminating it.
- Knowing both CFTR variants matters for adults as well as children, because eligibility for CFTR modulator medicines is decided by the specific variants on the genetic report.
- Sputum cultures taken at routine visits, not only during illness, are how teams detect new organisms such as Pseudomonas early, when eradication is most realistic.
Cystic fibrosis care relies on three kinds of tests. The sweat chloride test measures how much salt is in sweat and remains the main diagnostic test. Genetic testing looks for disease-causing variants in the CFTR gene, confirms the diagnosis, identifies carriers and helps guide treatment choices. Sputum cultures then track which bacteria live in the lungs so the care team can adjust management over time.
The envelope from the state newborn screening program is thin, and the letter inside uses a phrase no parent is ready for: “screen positive.” A nurse calls the next morning. She is calm, she says the word “follow-up” more than once, and she asks whether you can bring the baby in for something called a sweat test. You hang up and realize you do not know what a sweat test is, or why a tiny blood spot taken in the hospital nursery could lead here.
That moment, or a version of it, happens thousands of times a year. Sometimes the person being tested is a newborn. Sometimes it is a teenager with stubborn sinus infections, or an adult with unexplained infertility, or a couple planning a pregnancy who want to know their carrier status. The questions are strikingly similar: what does the cystic fibrosis sweat test and genetic testing pathway actually involve, how reliable is each step, and what happens once the answers arrive?
This article walks through the whole sequence, from the first screening result to the sputum cultures that guide care for life, and is honest about where the evidence is firm and where it still leaves gaps.
What is the cystic fibrosis sweat test and genetic testing pathway?
Cystic fibrosis (CF) is an inherited condition in which a faulty protein, called CFTR, fails to move chloride and water properly across the surfaces of the lungs, pancreas, gut and sweat glands. The result is thick, sticky mucus in the airways and digestive system, and unusually salty sweat. That saltiness is not a side detail. It is the basis of the oldest and still most trusted diagnostic test.
The pathway usually unfolds in a fixed order. A screening step raises the possibility of CF; in the United States that is the newborn blood-spot screen, which every state now runs, according to the NIH’s National Heart, Lung, and Blood Institute. A sweat chloride test then confirms or rules out the diagnosis by measuring salt in sweat collected from the skin. Genetic testing of the CFTR gene adds a second layer: it identifies the specific variants a person carries, which matters for family planning and, increasingly, for choosing treatment. Once CF is confirmed, sputum cultures become a routine part of every clinic visit, tracking which bacteria have settled in the airways.
Each test answers a different question. The sweat test answers “does the CFTR protein work?” Genetic testing answers “which change in the gene is responsible?” Sputum cultures answer “what is growing in the lungs right now?” None of them replaces the others, and the order matters less than the fact that a specialist team interprets all three together.
What follows takes each in turn, with the detail that a thin letter and a kind nurse rarely have time to give.
How does the sweat test actually work?
A sweat test is a measurement of chloride, one half of ordinary table salt, in sweat that has been deliberately stimulated on a small patch of skin, usually the forearm or, in small infants, the thigh.
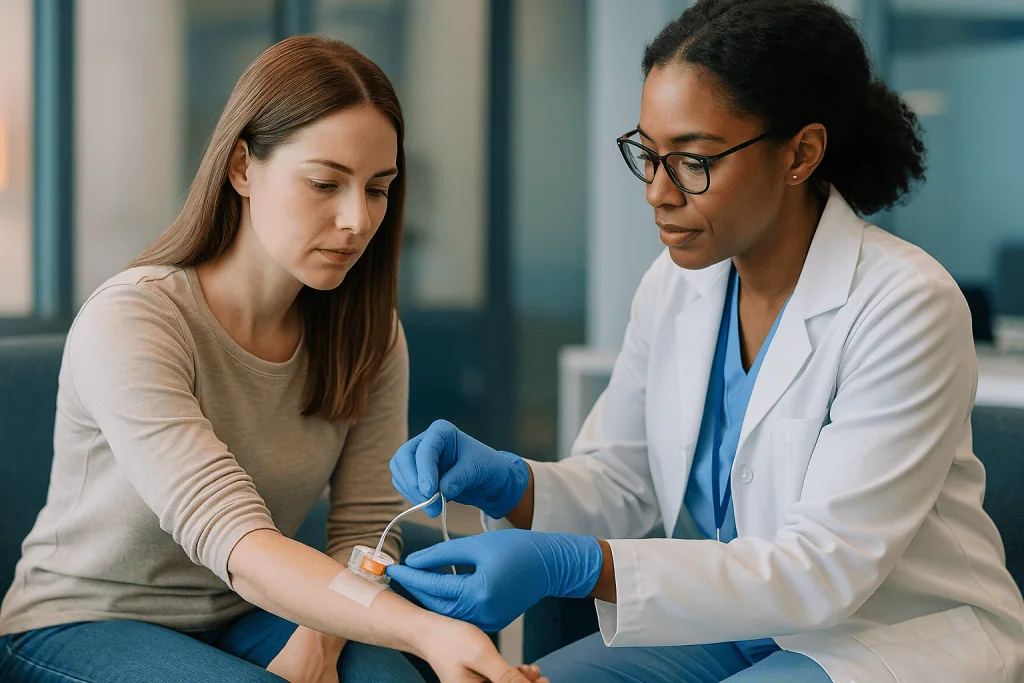
The process has three parts. First, a technician applies a medication called pilocarpine to the skin and passes a very mild electric current through it for a few minutes. Pilocarpine makes the sweat glands in that spot work harder; the current simply carries the drug into the skin. Most people describe the sensation as a tingling or light warmth. Second, the stimulated area is cleaned and covered with a collection device, either a filter paper disc and a sealed plastic sheet or a small plastic coil that draws sweat along a tube. Sweat is gathered over roughly half an hour. Third, the laboratory weighs or measures the sample and analyzes its chloride content.
Why chloride? In healthy sweat glands, the CFTR protein pulls chloride back out of sweat before it reaches the skin, so the final fluid is fairly dilute. When CFTR is absent or broken, that reabsorption fails and chloride stays in the sweat. The test is therefore reading the function of the protein directly, which is why it detects CF regardless of which of the many gene variants is responsible.
The whole visit typically lasts about an hour, MedlinePlus notes, with no needles and no sedation. Laboratories follow strict minimum sample sizes; if a baby does not sweat enough, the result is reported as “insufficient quantity” rather than guessed at, and the test is repeated another day. A result that looks positive is normally confirmed on a second occasion before anyone is told they have CF.
How do you interpret sweat chloride test results?
Sweat chloride is reported in millimoles per liter (mmol/L), and the interpretation bands come from the Cystic Fibrosis Foundation’s consensus diagnostic guidelines, published in the Journal of Pediatrics and indexed on PubMed.
| Sweat chloride (mmol/L) | What it usually means | Typical next step |
|---|---|---|
| Below 30 | CF unlikely at any age | Usually no further testing unless symptoms are strong |
| 30 to 59 | Intermediate, CF possible | CFTR gene analysis, repeat sweat test, specialist review |
| 60 or above | Consistent with CF | Confirm on a second sample, genetic testing, referral to a CF center |
Two points deserve emphasis. The first is that the lower cutoff of 30 mmol/L applies to everyone, including infants; earlier guidance used a higher threshold for older people, and that has been retired. The second is that the intermediate band is genuinely uncertain, not a soft positive. Some people in that range turn out to have CF with milder variants, some have a related condition called CFTR-related disorder, and some have nothing wrong at all. Resolving the question takes genetic testing and clinical judgment, and it may take months.
A few situations can nudge results in either direction. Dehydration, malnutrition and certain rare hormonal or skin conditions can raise sweat chloride without CF being present. A sample that is too small, or skin that has been contaminated with salty fluid, can also distort the number. On the other side, a small proportion of people with proven CF have sweat chloride below 60, which is exactly why a normal result in someone with a convincing story does not close the case.
If you receive a number, ask the team which band it falls into and whether a repeat is planned. Those two questions tell you most of what the result means.
Who is usually tested, and who is asked to wait?
A sweat test is requested in four broad situations: a positive newborn screen, a sibling or other close relative with CF, symptoms that fit the condition, or a genetic result that needs clinical confirmation. Adults are tested more often than people assume, typically after chronic sinusitis, recurrent chest infections, pancreatitis or male infertility prompts a closer look.

Not everyone can be tested straight away. The consensus guidelines advise that infants should be at least about two weeks old and weigh more than roughly 2 kilograms before a sweat test is attempted, because very young or very small babies often do not produce enough sweat and insufficient samples are common. Premature infants may need to wait longer. If a newborn screen is positive, the clinic will generally aim to have the test done within the first month of life so that, if CF is confirmed, nutritional support can start early.
Other reasons the test may be postponed:
- Dehydration from vomiting, diarrhea or a feverish illness, which can alter sweat chemistry.
- Widespread eczema or a rash over the collection site, which interferes with sweat collection.
- Recent use of corticosteroid medicines or certain hormone treatments, which the laboratory may ask about because they can affect results.
- A baby who is unwell enough to need oxygen or intensive care, where the test can wait until they are stable.
None of these is a reason to skip testing; they are reasons to time it well. A delayed test done properly is worth far more than an early test that has to be repeated.
Genetic testing has fewer timing constraints. It can be done on a blood sample, a cheek swab, or even the original newborn screening blood spot, at any age. Carrier screening is commonly offered before or early in pregnancy, which is when it is most useful for planning.
What happens on the day of a sweat test, especially for a child?
Preparation is light. The clinic will usually ask you to avoid creams and lotions on the arms and legs the day before, keep the person well hydrated, and bring a feed or snack. Normal eating and drinking are fine; there is no fasting.
On arrival, a technician explains the steps and checks that the skin is clean and intact. The stimulation phase with pilocarpine and the mild current lasts around five minutes. Children sometimes dislike the straps or the strangeness more than the sensation, so a familiar toy, a feed or a phone with a favorite show helps more than reassurance alone. Infants can be held throughout.
The collection phase is the long part. The sealed collector sits on the skin for about 30 minutes while the person stays warm; some clinics wrap the limb or ask for an extra layer of clothing, because warmth encourages sweating. Walking around the room, feeding or reading are all fine. Many centers collect from both arms at once to reduce the chance of an insufficient sample.
After collection the skin may look a little red where the electrodes sat. This fades within a few hours. Serious skin injury is rare with modern, properly maintained equipment.
Results from a laboratory that runs the test regularly often come back the same day or within a few days, though this varies and the clinic should tell you what to expect. One practical tip: ask in advance whether the result will be given by phone, portal or at a follow-up appointment, and who will be available to explain it. The number itself is less important than hearing what it means from someone who can answer your questions on the spot.
Does genetic testing include cystic fibrosis? Understanding the CFTR gene mutation test
The honest answer is: sometimes, and you should check. “Genetic testing” covers very different products, and not all of them look at the CFTR gene.
A CFTR gene mutation test, in its diagnostic form, reads through the gene itself to find changes that stop the protein working. The CFTR gene is large, and MedlinePlus Genetics describes well over a thousand variants that have been identified in it, though only a fraction are confirmed to cause disease. Laboratories handle this in tiers. A targeted panel checks for the most common disease-causing variants in a population; in people of European ancestry the variant called F508del dominates, but the common set differs by ancestry, and a panel designed around one population can miss variants in another. Full gene sequencing reads the entire coding region and catches rare variants a panel would miss. A further step looks for larger deletions or duplications that sequencing alone can overlook.
Where CF appears on broader tests:
- Expanded carrier screening panels offered in pregnancy planning almost always include CFTR, because it is among the most common serious recessive conditions.
- Newborn screening in all US states includes an initial blood test for CF and, in many states, a second-tier CFTR variant check on the same blood spot.
- Consumer ancestry-style tests may report a small number of CFTR variants, but these are not diagnostic and typically cover far fewer variants than a clinical panel.
- Whole-exome or whole-genome sequencing ordered for another reason will contain CFTR data, but the laboratory may not analyze or report it unless asked.
If a relative has CF, tell the laboratory which variants they carry. Testing specifically for a known family variant is more reliable than hoping a general panel happens to include it.
Cystic fibrosis carrier screening: what a result can and cannot tell you
Being a carrier means having one working copy of the CFTR gene and one altered copy. Carriers do not have cystic fibrosis and, in nearly all cases, have no symptoms. The NHS estimates that about 1 in 25 people of white European ancestry carries a CF variant, a figure that is lower in other ancestry groups but nowhere near zero.
The arithmetic of inheritance is simple and worth stating plainly. If both parents are carriers, each pregnancy has a 1 in 4 chance of a child with CF, a 2 in 4 chance of a carrier child, and a 1 in 4 chance of a child with two working copies, as MedlinePlus Genetics explains. If only one parent is a carrier, a child cannot inherit CF but may be a carrier.
What carrier screening cannot do is deliver certainty. A negative panel reduces the chance of being a carrier; it does not eliminate it, because the panel only looks for the variants it was built to detect. Laboratories report this as a “residual risk,” and a genetic counselor can translate it into terms that make sense for your ancestry and family history. A negative result from a 23-variant panel means something quite different from a negative full-sequence result.
Results can also land in a gray zone. A “variant of uncertain significance” is a change in the gene whose effect is not yet known. It is not a diagnosis and not a reassurance; it is a question that may be answered as databases grow. Some variants cause CF only when paired with specific other variants, and some cause milder, organ-limited problems rather than classic disease.
Carrier results have implications for siblings and extended family, who may wish to be tested themselves. Sharing results is a personal decision, and counseling can help with the conversation.
Newborn screening for cystic fibrosis: how the blood-spot test leads to a diagnosis
Newborn screening is not a diagnostic test. It is a net cast wide on purpose, designed to catch almost every baby with CF at the cost of flagging many who do not have it.
The first step measures a substance called immunoreactive trypsinogen (IRT) in the dried blood spot taken from the baby’s heel in the first days of life. IRT is a pancreatic enzyme precursor; in babies with CF, thickened secretions block the pancreas and IRT leaks into the blood at higher levels. Elevated IRT is also seen in some healthy babies, premature infants and babies stressed at birth, which is why a high IRT alone proves nothing.
States then use one of two strategies, according to the NIH’s National Heart, Lung, and Blood Institute. Some repeat the IRT on a second blood spot. Many run a CFTR variant panel on the original spot if IRT is high. A baby is reported as “screen positive” if IRT is high and one or more variants are found, or in some programs if IRT is very high even without a variant.
From there the sweat test takes over. A screen-positive baby who then has a sweat chloride below 30 mmol/L is very unlikely to have CF, and may simply be a carrier of the one variant found. A baby with two disease-causing variants or a sweat chloride of 60 mmol/L or more is diagnosed with CF and referred to a specialist center.
Some babies end up in a third category, with a positive screen but inconclusive sweat and genetic results. The guidelines call this CFTR-related metabolic syndrome, or CRMS. Most of these children stay well, but they are followed in clinic and may be retested over time because a small number later meet criteria for CF.
Screening also misses a small number of babies, so symptoms that fit CF should still be investigated even with a normal newborn screen.
Cystic fibrosis sweat test and genetic testing: how the two fit together
People often ask which test is “better.” The question misunderstands the pair. They measure different things, fail in different ways and are strongest in combination. The table below sets them side by side.
| Feature | Sweat chloride test | CFTR genetic testing |
|---|---|---|
| What it measures | Whether the CFTR protein works, via salt in sweat | Which changes exist in the CFTR gene |
| Sample | Sweat collected from stimulated skin | Blood, cheek swab or newborn blood spot |
| Earliest age | About two weeks, with adequate weight | Any age, including before birth |
| Main strength | Detects CF regardless of which variant is responsible | Identifies carriers, explains inheritance, guides variant-specific therapy |
| Main limit | Intermediate results need further work-up; sample can be insufficient | Panels miss rare variants; some variants have uncertain meaning |
| Typical turnaround | Hours to days | Days to weeks depending on depth |
In practice the consensus guidelines allow a diagnosis to be made when there is clinical evidence of CF plus either a sweat chloride of 60 mmol/L or higher, or two CF-causing CFTR variants. Where one test is clear and the other is not, the clear one usually carries the day, but the uncertain one is not ignored; it is revisited.
A few examples make the logic concrete. A child with sweat chloride of 85 mmol/L and only one variant found on a standard panel has CF; the second variant is simply rarer than the panel covers, and full sequencing will usually find it. An adult with sweat chloride of 42 mmol/L and two variants of uncertain significance does not yet have a diagnosis; they have a question that needs specialist follow-up and perhaps more specialized tests of CFTR function.
The pairing also protects against the rare laboratory error. Two independent methods pointing the same way give far more confidence than either alone.
Why sputum cultures matter in ongoing cystic fibrosis care
Once CF is diagnosed, the testing shifts from “what is this?” to “what is happening now?” and sputum cultures are the workhorse of that phase.
A sputum culture is a laboratory test in which mucus coughed up from the lungs is spread on growth media to see which bacteria and fungi are present. Thick CF mucus is an unusually hospitable environment for certain organisms, and the ones that settle in change over a lifetime. Mayo Clinic describes cultures as a routine part of monitoring, and the organisms of greatest interest include Staphylococcus aureus, Pseudomonas aeruginosa, the Burkholderia cepacia complex, and non-tuberculous mycobacteria, along with fungi such as Aspergillus.
Why does the team care which bug it is? Several reasons:
- Some organisms, once established, are very difficult to clear, so early detection prompts a decision about whether to attempt eradication while that is still realistic.
- Antibiotic choices depend on the organism and its sensitivity pattern, which the laboratory reports alongside the culture.
- Certain organisms are associated with faster lung function decline and with infection-control rules in clinics, including separation of patients who carry them.
- A new organism, or a jump in the amount grown, can signal an exacerbation before symptoms are obvious.
Cultures are typically collected at each routine visit, and CF centers generally see patients several times a year, so a person with CF builds up a long microbiological history. Young children who cannot cough up sputum have a throat swab taken instead, sometimes with a cough prompted first. Bronchoscopy, where a thin camera samples fluid from deep in the lungs, is reserved for specific situations.
Standard bacterial results usually come back within a few days. Mycobacterial cultures grow slowly and can take several weeks, which is why the team may ask you to be patient about one specific result while acting on the others.
What else does the care team monitor after diagnosis?
Cystic fibrosis affects more than the lungs, and the monitoring program reflects that. Alongside sputum cultures, a typical annual review at a CF center covers several systems, as described by Mayo Clinic and the NHLBI.
Lung function. Spirometry, a breathing test into a tube connected to a measuring device, tracks how much air the lungs can move and how fast. The number most watched is FEV1, the volume exhaled in the first second of a hard breath out. Trends over years matter more than any single reading. Infants and young children who cannot do spirometry may have other lung function tests, and chest imaging with X-ray or low-dose CT is used at intervals to look for structural change.
Digestion and growth. Most people with CF have a pancreas that does not release enough digestive enzymes. A stool test for fecal elastase shows whether the pancreas is working, and weight, height and body mass are tracked closely because nutrition and lung health are tightly linked. Blood tests check fat-soluble vitamins, which are absorbed poorly when fat digestion fails.
Blood sugar. CF-related diabetes is a distinct form of diabetes caused by damage to the insulin-producing pancreas, and routine screening with an oral glucose tolerance test is part of standard care from later childhood onward.
Liver, bones and other organs. Liver blood tests and sometimes ultrasound, bone density scans in adolescence and adulthood, and hearing checks for those who receive certain intravenous antibiotics are all common.
None of these is dramatic on its own. Together they form the early-warning system that lets a team act before a problem becomes an emergency, which is the entire point of structured CF care.
What do the days and weeks after testing usually look like?
The timeline depends on which door you came through, but the broad shape is similar.
After a positive newborn screen. Programs aim for the sweat test to be completed in the first few weeks of life, and the consensus guidelines encourage diagnosis by about one month of age where possible, so that feeding support, enzyme replacement where needed and salt advice can start early. If the sweat test is positive, the family is usually seen at a CF center within days, meets the team (physician, nurse specialist, dietitian, physiotherapist, social worker) and begins a schedule of visits that is frequent in the first year. Genetic results, if not already available from the screen, follow over the next couple of weeks.
After an intermediate result. This is the slower and more frustrating path. A repeat sweat test may be scheduled a few weeks later, full CFTR sequencing is sent, and the family may be asked to watch for specific signs in the meantime. Some clinics use additional specialized tests of CFTR function. A clear answer can take months, and in some cases the label remains “possible CF” with regular review.
After adult diagnosis. Adults diagnosed later in life often have milder variants and may have spent years with unexplained symptoms. The first weeks typically involve a full baseline assessment: spirometry, imaging, sputum cultures, pancreatic function and nutritional review, plus a conversation about whether their specific variants make them eligible for CFTR modulator therapy, a class of medicines discussed below.
After carrier screening. If you are a carrier, the next step is usually testing your partner. If both carry a variant, genetic counseling covers the options, which include prenatal diagnostic testing and preimplantation testing for those using IVF. These are personal decisions, and good counseling presents them without steering.
Can cystic fibrosis be treated, and how does genotype guide that?
Cystic fibrosis cannot yet be made to go away, and anyone who tells you otherwise is selling something. What has changed, dramatically, is how well it can be managed, and genetic testing now sits at the center of that.
Treatment has two layers. The first is the long-standing foundation: airway clearance physiotherapy to move mucus, inhaled medicines that thin secretions or open airways, antibiotics guided by sputum cultures, pancreatic enzyme replacement with meals, high-calorie nutrition with vitamin supplements, and vaccination. These do not touch the underlying protein defect; they manage its consequences, and they remain essential.
The second layer is newer. CFTR modulators are a class of oral medicines that act on the faulty CFTR protein itself. Depending on the type, they help misfolded protein reach the cell surface, hold the chloride channel open longer, or both. Their effect depends entirely on which variants a person carries, because different variants break the protein in different ways. This is the most practical reason to have a complete genotype: eligibility for modulator therapy is determined by the specific variants on a person’s genetic report, as both Mayo Clinic and the NHS explain. A person whose second variant was never identified may be missing information that affects their options.
Modulators are not suitable for every genotype, they require monitoring of liver function and other parameters, and they are prescribed and adjusted only by CF specialists. Whether, when and how to start is a decision for the treating team, informed by the genetic result, lung function, age and other health factors. Gene-based therapies that aim to supply a working copy of the gene are in research but are not standard care.
The realistic message is that CF has become a condition to manage over a lifetime rather than a short childhood illness, and the testing described here is what makes that management precise.
What people often get wrong about cystic fibrosis testing
Misunderstandings about CF testing cause real harm, from delayed diagnoses to needless panic. Here are the ones that come up most.
“A normal newborn screen means my child cannot have CF.” Screening catches the great majority of cases but not all. A child with recurrent chest infections, poor weight gain despite a good appetite, or persistently greasy stools deserves a sweat test regardless of the screen result.
“A positive newborn screen means my baby has CF.” Most screen-positive babies do not. Many are healthy carriers of a single variant, and some had a high IRT for reasons unrelated to CF. The sweat test exists precisely to sort this out.
“Salty-tasting skin is enough to diagnose it.” Parents have noticed salty kisses for generations, and it is a genuine clue, but it is neither sensitive nor specific enough to replace a laboratory measurement.
“A negative carrier panel means I am definitely not a carrier.” It lowers the chance, sometimes substantially, but residual risk remains, and the size of that risk depends on the panel and your ancestry.
“Genetic testing is only useful for babies and pregnancies.” For adults with CF, knowing both variants can determine eligibility for modulator therapy, which makes a complete genotype one of the most consequential pieces of information in their record.
“Sputum cultures are only needed when someone is sick.” Routine cultures in well people are how teams spot new organisms early, when eradication is most realistic.
“A sweat test is painful or risky.” It involves a mild tingling and about an hour of waiting. Serious complications are rare with modern equipment.
Each of these myths has a kernel of truth wrapped around a wrong conclusion, which is what makes them stubborn. The antidote is asking the team what a result means for you specifically.
Questions to ask your care team about sweat tests, genetic testing and cultures
Clinic appointments are short and the vocabulary is unfamiliar. A written list helps. These are the questions that tend to unlock the most useful answers.
About the sweat test
- What was the exact chloride value, and which interpretation band does it fall into?
- Was the sample size adequate, and will the test be repeated?
- Were both arms collected, and did the two results agree?
About genetic testing
- Was this a targeted panel or full gene sequencing, and how many variants did it cover?
- Have both disease-causing variants been identified, and if not, what further testing is planned?
- Are any of the reported variants classed as uncertain significance, and will they be re-reviewed as databases update?
- Do my specific variants affect eligibility for any current treatment class?
- Which relatives might benefit from knowing this result, and can you help me tell them?
About sputum cultures and monitoring
- Which organisms have grown in my cultures over time, and has anything new appeared?
- How often will cultures, spirometry and imaging be repeated?
- What results would prompt a change in my management, and how will you contact me?
About the bigger picture
- Who is my main point of contact between visits?
- Is there a genetic counselor available, and how do I book?
- What signs at home should make me call before the next scheduled appointment?
You are entitled to copies of your laboratory reports, including the full genetic report with variant names. Keep them. They are worth more than any summary letter, particularly if you move or change centers.
When to call your doctor
Testing is a process that unfolds over weeks, but some situations should not wait for the next scheduled appointment. Contact your CF team or primary care clinician promptly if any of the following occurs, whether a diagnosis is confirmed or still being worked out.
Call the same day
- An infant who is feeding poorly, vomiting repeatedly, unusually drowsy or not producing wet diapers, which can signal dehydration or salt loss.
- A sudden increase in cough, sputum volume or a change in sputum color, especially with fever or breathlessness.
- Blood in the sputum beyond small streaks.
- Severe or persistent abdominal pain, a swollen abdomen, or no bowel movement in a baby in the first day or two of life, since bowel blockage is a known early complication of CF.
- Unexpected weight loss or a child who has stopped gaining weight.
Call emergency services
- Severe difficulty breathing, blue or gray lips, or chest pain that comes on suddenly, which can indicate a collapsed lung.
- Coughing up a large amount of blood.
- Collapse, confusion or signs of severe dehydration in hot weather or during illness, as people with CF lose more salt in sweat.
Call within a few days
- You have received a result and no one has explained it.
- A planned repeat test or referral has not been scheduled.
- A relative has been diagnosed and you want to understand your own testing options.
Every decision about further testing, treatment and timing belongs to the treating team, who know the full picture. The aim of this article is to make you a better-informed partner in those conversations, not to replace them.
Frequently asked questions
Does genetic testing include cystic fibrosis?
Not automatically. Clinical carrier screening panels and newborn screening programs almost always include the CFTR gene, but consumer ancestry tests usually check only a handful of variants and are not diagnostic. Broad sequencing tests contain CFTR data yet may not report it unless requested. If you want CF covered, ask the laboratory directly which test and how many variants it includes.
How do you interpret sweat chloride test results?
Results are read in three bands set by consensus guidelines. Below 30 mmol/L makes CF unlikely, 60 mmol/L or above is consistent with CF, and 30 to 59 is intermediate and needs further work-up including CFTR gene analysis. A positive result is normally repeated for confirmation, and an insufficient sample is reported as such rather than interpreted.
Can cystic fibrosis be treated or controlled?
Yes, although it cannot yet be made to disappear. Management combines airway clearance, inhaled therapies, culture-guided antibiotics, enzyme replacement and nutrition, and for people with eligible variants a class of medicines called CFTR modulators that act on the faulty protein. Treatment choices depend on genotype, age and lung function and are made by the specialist team.
What are the common symptoms that lead to cystic fibrosis testing?
Clinicians commonly request testing when someone has recurrent chest or sinus infections, a persistent cough with thick sputum, poor weight gain despite a good appetite, greasy or bulky stools, very salty skin, or unexplained male infertility. These features overlap with many other conditions, so they prompt a sweat test and genetic analysis rather than a diagnosis on their own.
What does cystic fibrosis carrier screening tell a couple?
It shows whether each partner carries a CFTR variant. If both do, each pregnancy carries a 1 in 4 chance of a child with CF. A negative result lowers but does not remove the chance of being a carrier, because panels only detect the variants they include. A genetic counselor can explain the residual risk for your ancestry and family history.
How does newborn screening for cystic fibrosis work?
A heel-prick blood spot taken in the first days of life is tested for immunoreactive trypsinogen, a pancreatic marker that is raised in most babies with CF. If it is high, many states run a CFTR variant check on the same spot. A screen-positive result leads to a sweat test, which is the step that confirms or rules out the diagnosis.
What is a CFTR gene mutation test and when is it needed?
It is a laboratory analysis of the CFTR gene to find changes that stop the protein working, using a targeted panel, full sequencing, or testing for deletions. It is needed to confirm a diagnosis, resolve an intermediate sweat test, identify carriers, test relatives of someone with CF, and determine whether a person’s variants make them eligible for variant-specific treatments.
Why are sputum cultures repeated so often in cystic fibrosis care?
Because the bacteria in CF lungs change over time, and catching a new organism early matters. Routine cultures at each clinic visit reveal organisms such as Staphylococcus aureus or Pseudomonas aeruginosa, along with their antibiotic sensitivities, before symptoms escalate. Young children who cannot produce sputum have a throat swab instead. Mycobacterial cultures can take several weeks to report.
Can an adult be diagnosed with cystic fibrosis for the first time?
Yes. Adults with milder CFTR variants may reach their twenties or beyond before chronic sinusitis, pancreatitis, repeated chest infections or infertility prompt testing. The same sweat test thresholds apply, and genetic testing often finds variants not covered by older screening panels. Diagnosis in adulthood opens access to structured CF care and, for some genotypes, modulator therapy.
What happens if the sweat test result is in the intermediate range?
An intermediate result of 30 to 59 mmol/L is a question rather than an answer. The team usually repeats the sweat test, sends full CFTR gene sequencing, and reviews symptoms and other tests. Some people are diagnosed with CF, some with a CFTR-related disorder, and some are followed over time without a definite label. This process can take months.
References
- MedlinePlus Genetics: Cystic Fibrosis
- NIH National Heart, Lung, and Blood Institute: Cystic Fibrosis Diagnosis
- NHS: Cystic Fibrosis
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Lung Abscess on a CT Scan: What the Images Show and How Sputum Cultures Guide Antibiotics
On a CT scan, a lung abscess usually appears as a rounded, thick-walled cavity inside the lung, often with an air-fluid level where pus…

After Pleural Effusion Drainage: Normal Soreness vs the Breathing Changes That Need Urgent Care
After thoracentesis, most people notice easier breathing within hours, along with a dull ache or pinching at the needle site that fades over one…

Pulmonary Edema: How the Heart, Lung or Kidney Cause Dictates the Treatment Plan
Pulmonary edema is fluid leaking into the lungs' air sacs. The most common cause is a heart that cannot pump or relax properly, which…

Traveling With Cystic Fibrosis: Flights, Therapy Equipment and Planning Care Away From Home
Most people with cystic fibrosis can travel, including by air, when their lung disease is stable and the trip is planned with their CF…

Who Benefits Most From a Structured Smoking Cessation Program? What Doctors Consider
A structured smoking cessation program tends to help most when nicotine dependence is strong, earlier quit attempts have not lasted, or a health condition…

The First 24 Hours After a Bronchoscopy: Sore Throat, Swallowing Checks and Driving Rules
After a bronchoscopy, most people spend one to several hours in a recovery area while sedation wears off, then go home the same day…