

Who Actually Needs Hemorrhoid Surgery? When Office Procedures Are No Longer Enough

Key Takeaways
- Hemorrhoidal cushions are normal anatomy that help the anal canal seal, so surgeons remove only diseased tissue and never aim to take it all out.
- Surgery is generally discussed for grade III disease that office procedures cannot control, most grade IV disease, mixed internal and external hemorrhoids, and painful clots seen within about 72 hours.
- Rubber band ligation makes the hemorrhoid fall off within about a week, but it treats internal tissue only and cannot address skin tags or external hemorrhoids.
- Excisional hemorrhoidectomy is the most complete treatment but has the hardest recovery, with MedlinePlus citing around two to three weeks before most people feel recovered.
- Stapled hemorrhoidopexy and artery ligation hurt less than excision but carry a higher chance that hemorrhoids return, according to the Mayo Clinic and NHS.
- Difficulty passing urine is a recognized complication after hemorrhoidectomy, which is why patients are not discharged until they have urinated.
Hemorrhoid surgery is usually reserved for people whose symptoms persist despite fiber, fluids and office procedures such as rubber band ligation, or who have large grade III or grade IV hemorrhoids that prolapse and cannot be pushed back, mixed internal and external disease, or a painful clotted external hemorrhoid seen within about 72 hours. Most hemorrhoids never reach that point, and the decision always rests with the treating team.
The man in the waiting room has done everything right. He eats oatmeal with ground flaxseed every morning, keeps a water bottle on his desk, and has sat through two rounds of rubber band ligation in a specialist’s office. He still finds blood on the tissue most weeks, and something still slips out when he strains. Now his doctor has used the word that makes most people flinch: surgery.
His question is the one that brings people to this article. Who needs hemorrhoid surgery, and who is simply being offered it too early? The honest answer is more reassuring than many search results suggest. Surgery sits at the far end of a long ladder, and most people step off well before the top.
Nearly three in four adults will have hemorrhoids at some point, according to the Mayo Clinic, yet only a small fraction ever reach an operating room. What separates them is not how much the hemorrhoids hurt on a bad week, but how they behave over months, and whether every gentler option has genuinely been tried.
What hemorrhoids actually are, and why removing them is not the goal
Here is a fact that reframes the whole conversation: everyone has hemorrhoids. They are normal cushions of blood vessels, connective tissue and smooth muscle that sit inside the anal canal and help it close completely. A hemorrhoid, in the medical sense, is simply one of those cushions that has become swollen, stretched or displaced enough to cause symptoms.
Doctors sort them by location. Internal hemorrhoids lie above a line in the anal canal called the dentate line, where the lining has almost no pain nerves, which is why they typically bleed painlessly rather than hurt. External hemorrhoids sit below that line under skin rich in nerve endings, so when one swells or develops a clot, it can be exquisitely tender. Many people have both, which surgeons call mixed disease.
The National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) estimates that about one in twenty Americans has symptomatic hemorrhoids, and roughly half of adults over 50 have had them. The triggers are familiar: straining with constipation, long sessions on the toilet, pregnancy, heavy lifting, chronic diarrhea and simply getting older as supporting tissue loosens.
This anatomy explains why no surgeon aims to remove all hemorrhoidal tissue. The cushions contribute to continence, especially for gas and liquid stool. Operations target only the diseased, prolapsing portions and deliberately leave healthy tissue and bridges of skin between wounds. Knowing that changes the question from “should these be taken out” to “is the problem tissue causing enough trouble, for long enough, that it is worth a wound in a sensitive place.”
That framing also explains why the first prescription for almost everyone is fiber, fluids and changing toilet habits. Softer stools and shorter sits reduce the pressure that stretched the cushions in the first place, and for a large share of people, that alone is enough.
How do you know if hemorrhoids need surgery? The grading system doctors use
Surgeons rarely decide based on how a hemorrhoid looks on a single day. They look at behavior over time, which is captured in a four-step grading scale for internal hemorrhoids described by the Cleveland Clinic and others. The grade matters because it predicts which treatments are likely to work.
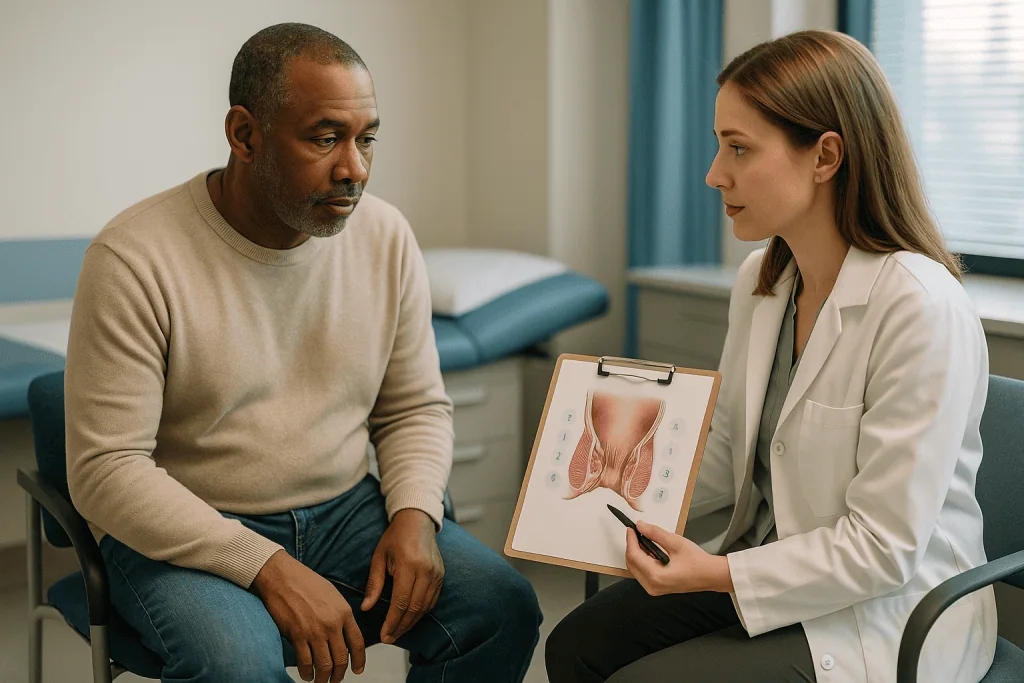
| Grade | What happens | Where treatment usually starts |
|---|---|---|
| I | Bleeds, but never prolapses (slips out) | Fiber, fluids, habits; sometimes office procedures |
| II | Prolapses with straining, goes back on its own | Office procedures such as banding |
| III | Prolapses and must be pushed back by hand | Banding often tried; surgery considered if it fails or disease is bulky |
| IV | Stays prolapsed and cannot be pushed back | Surgery is usually discussed |
External hemorrhoids are not graded this way. They become surgical candidates mainly when a clot forms inside one (thrombosis) or when large skin tags interfere with hygiene and comfort.
Before any grade is assigned, something more important happens: the doctor confirms that hemorrhoids are actually the cause. Rectal bleeding is also a symptom of anal fissures, inflammatory bowel disease, polyps and colorectal cancer. The Mayo Clinic notes that clinicians may recommend a sigmoidoscopy or colonoscopy when bleeding occurs with other risk factors, when symptoms suggest another digestive condition, or when the person is of an age at which colon cancer screening is due. No surgeon should operate on an assumed diagnosis, and no reader should assume blood is “just hemorrhoids” without an examination.
Only after the cause is confirmed and the grade is known does the real question, who needs hemorrhoid surgery, come into focus. For most people with grade I or II disease, the answer is nobody, at least not yet.
What office procedures do, and where they stop working
The middle rungs of the treatment ladder are procedures done in a clinic room without general anesthesia. They all work on the same principle: shrink or fix the internal hemorrhoid by cutting off its blood supply or scarring it to the underlying wall, using the fact that the tissue above the dentate line barely registers pain.
Rubber band ligation is the workhorse. A small band is placed around the base of the internal hemorrhoid, the tissue loses its blood supply and withers, and according to the Mayo Clinic the banded hemorrhoid typically falls off within about a week. Bleeding can occur two to four days afterward as the tissue separates, and the procedure can feel uncomfortable, though it rarely requires time off work.
Sclerotherapy injects a chemical solution that scars and shrinks the hemorrhoid. Infrared coagulation uses heat to achieve a similar effect. The NHS also describes electrotherapy as an option for smaller hemorrhoids. These methods tend to be gentler than banding and, in the Mayo Clinic’s assessment, somewhat less likely to control symptoms long term.
So where do they stop working? Office procedures have three predictable limits. First, they only treat internal tissue; they cannot address a bulky external component or skin tags. Second, they struggle with grade IV disease, where the cushion no longer slides back inside to be banded safely. Third, they are a numbers game: each session treats one or two hemorrhoids, and some people need repeat rounds over months, only to see symptoms return.
This is the point where the man in the waiting room found himself. Two rounds of banding, continued bleeding, persistent prolapse. Not a failure on his part, and not a failure of the procedure. Simply a signal that his disease had outgrown what a clinic room can offer, and that the next conversation belonged to a surgeon.
Who needs hemorrhoid surgery, and who is usually asked to wait
Strip away the fear and the forum posts, and the surgical candidates fall into a handful of recognizable groups described consistently by the Mayo Clinic, NIDDK and the NHS.

- People whose symptoms persist after a fair trial of conservative care and office procedures.
- People with grade III hemorrhoids that are too large or numerous to band effectively, and most people with grade IV disease.
- People with mixed internal and external disease, where only an operation can treat both.
- People with a painful thrombosed external hemorrhoid seen early, typically within about 72 hours of the clot forming.
- Less commonly, people with ongoing bleeding significant enough to cause anemia despite other treatment.
Who is usually asked to wait? Pregnant women, for one. Hemorrhoids are common in pregnancy and, as the Mayo Clinic notes, often improve after delivery, so surgery is deferred unless there is a pressing problem. People with grade I or II disease who have not yet changed fiber intake or toilet habits are almost always sent home with a plan rather than a surgical date. Anyone with rectal bleeding whose cause has not been confirmed waits for an examination, and sometimes a colonoscopy, before any procedure.
Some people are not asked to wait so much as to prepare. Those taking blood-thinning medicines need a plan agreed with the prescribing clinician, because the operation site bleeds easily. People with inflammatory bowel disease, immune suppression or poorly controlled diabetes carry higher wound-healing risk and may be steered toward less invasive options or closer follow-up.
Underlying all of this is a principle worth holding onto: hemorrhoid surgery is elective in almost every case. The disease is benign. The decision is about quality of life, measured against a genuinely uncomfortable recovery, and it belongs to the patient and the treating team together.
Why don't doctors like to remove hemorrhoids?
Patients notice the reluctance. They describe a specialist who nods sympathetically and then recommends more fiber, another round of banding, another three months. It can feel like being brushed off. The reluctance is real, but it has reasons, and they are worth hearing.
The first is anatomy. As the Cleveland Clinic and others explain, hemorrhoidal cushions are normal structures that help the anal canal seal. Removing too much tissue, or removing it carelessly, risks a degree of leakage that is far harder to live with than the original bleeding.
The second is pain. A hemorrhoidectomy leaves wounds in skin packed with nerve endings, in a place that must still open several times a day. The Mayo Clinic is blunt that most people have some pain after the procedure. Doctors who have watched patients through those first two weeks are understandably slow to recommend it for symptoms that fiber might settle.
The third is that conservative treatment genuinely works for a large share of people. NIDDK’s guidance is that procedures are generally considered only when home treatment has not helped. Skipping that step means operating on people who never needed it.
The fourth is the risk of scarring. Removing tissue around the full circumference of the anal canal can lead to narrowing, called stenosis, which is why surgeons leave bridges of intact skin between excision sites and limit how many cushions they remove in one sitting.
None of this means doctors refuse to operate. It means the bar is deliberately set at a point where the recovery is clearly worth it. If you have cleared that bar, a good surgeon will say so plainly. If you have not, the recommendation to wait is not dismissal. It is the evidence talking.
What actually happens during a hemorrhoidectomy
A hemorrhoidectomy is the operation in which swollen hemorrhoidal tissue is cut away. The Mayo Clinic calls it the most effective and complete way to treat severe or recurring hemorrhoids, and it is the procedure most people picture when they say “hemorrhoid surgery.”
The day usually begins in a day-surgery unit. MedlinePlus describes it as a procedure done under general anesthesia, where you are asleep, or spinal anesthesia, where you are numb from the waist down, sometimes with a local anesthetic added around the anus to ease the first hours afterward. Which approach is used depends on your health, your surgeon’s preference and your own wishes, and the anesthesia team will discuss it with you beforehand.
Once you are anesthetized and positioned, the surgeon gently opens the anal canal with a small instrument to see the hemorrhoids clearly. Each diseased cushion is lifted, its blood supply is tied off at the base, and the excess tissue is removed with a scalpel, scissors or an energy device that cuts and seals at the same time. The surgeon deliberately leaves strips of normal skin and lining between the wounds so the canal can heal without narrowing.
What happens to the wounds depends on technique. In a closed hemorrhoidectomy, the edges are stitched together with dissolving sutures. In an open hemorrhoidectomy, the wounds are left to heal from the base upward, which takes longer but is sometimes preferred when infection risk is a concern. Neither approach is universally better, and surgeons often choose based on the size and position of each hemorrhoid.
Finally, a dressing may be placed, you are woken, and recovery staff monitor you until you have passed urine and your pain is controlled. The Mayo Clinic notes that temporary difficulty emptying the bladder is a known issue after this operation, which is why that step is never skipped before discharge.
Hemorrhoidectomy vs rubber band ligation and the other surgical options
Cutting the tissue out is not the only operating-room option, and the comparison people search for, hemorrhoidectomy vs rubber band ligation, is really a comparison across a spectrum of invasiveness. Two alternatives appear in the NHS and Mayo Clinic treatment guidance.
Stapled hemorrhoidopexy, sometimes called stapling, does not remove the hemorrhoids. A circular stapling device removes a ring of lining above them and pulls the prolapsed tissue back into its normal position, reducing its blood supply in the process. Because the work happens above the dentate line, the Mayo Clinic notes it generally involves less pain and an earlier return to normal activity than hemorrhoidectomy, but carries a greater risk of recurrence and of rectal prolapse, and has been associated with rare but serious complications.
Hemorrhoidal artery ligation, described by the NHS, uses a small ultrasound probe to locate the arteries feeding each hemorrhoid, which are then tied off with stitches. Prolapsed tissue can be hitched up at the same time. No tissue is cut away, so pain is typically lower, though the NHS notes recurrence appears somewhat more likely than after excision.
| Option | What is done | Typical setting | Main trade-off |
|---|---|---|---|
| Rubber band ligation | Band starves internal hemorrhoid | Office, no anesthesia | Internal grades I–III only; may need repeat |
| Hemorrhoidectomy | Diseased tissue excised | Operating room, day case | Most complete; most painful recovery |
| Stapled hemorrhoidopexy | Prolapse repositioned, blood supply reduced | Operating room | Less pain; higher recurrence |
| Artery ligation | Feeding arteries stitched closed | Operating room | Less pain; recurrence more likely than excision |
Which is right depends on grade, external component, bleeding history and personal priorities. Someone who values the lowest chance of ever coming back may accept the harder recovery of excision; someone who cannot take two weeks away from a physical job may lean the other way. That is a conversation, not a formula.
How long does hemorrhoid surgery take, and will I go home the same day?
Two of the most searched questions about this operation have short answers. The procedure itself is brief, and most people do not stay overnight.
Operating time is measured in minutes rather than hours. A hemorrhoidectomy for one or two hemorrhoids is often finished well within an hour of the first incision, and stapled or artery-ligation procedures are similarly quick. Exact timing varies with the number of hemorrhoids treated, the technique, and whether the surgeon also removes skin tags, so treat any specific figure you read online as an estimate, not a commitment. Your surgeon can give you a realistic range for your own anatomy.
What takes longer is everything around the operation. Expect to arrive an hour or two early for checks and anesthesia preparation, and to spend time afterward in a recovery area until you are awake, comfortable, and able to pass urine. MedlinePlus describes hemorrhoid surgery as a procedure after which most people go home the same day, which matches NHS guidance that it is usually performed as a day case. An overnight stay is reserved for people with other health conditions, poorly controlled pain or urinary retention.
Because of the anesthesia, you will need someone to take you home and ideally stay with you that first night. You will leave with instructions about sitz baths (sitting in a few inches of warm water), stool softeners or fiber supplements to keep bowel movements soft, pain management as prescribed by your team, and a follow-up appointment.
The gap between how long surgery takes and how long recovery takes is where expectations go wrong. An operation that fits inside a lunch hour leads to a recovery measured in weeks. The next section is about that reality.
Hemorrhoid surgery recovery time: how bad is it, and what do the first weeks look like?
People ask “how bad is hemorrhoid surgery recovery?” because they have heard it is bad. The truthful answer is that the first week after an excisional hemorrhoidectomy is one of the harder recoveries for a day-case operation, and that it gets steadily better from there.
MedlinePlus gives a typical recovery of around two to three weeks, and the NHS describes full recovery taking a few weeks. Within that window, a rough pattern repeats across most patients.
Days one to three are the most uncomfortable. Pain is constant at a low level and spikes with sitting, standing and especially with the first bowel movement, which many people dread more than the surgery. Keeping stools soft with fiber, fluids and any softener your team recommends is the single most useful thing you can do. Warm sitz baths several times a day, particularly after bowel movements, relax the muscle and keep the wounds clean. Some spotting of blood on the dressing or tissue is expected.
Days four to seven bring the first real improvement. Pain becomes intermittent rather than constant. Many people manage short walks and light desk work from home. Difficulty urinating, if it occurred, has usually settled.
Week two is when most people return to office-based work, though sitting for long stretches remains tiring. Wounds may weep a little as they heal, and a small amount of bleeding with bowel movements can continue.
Weeks three and four see wounds closing and the sharp pain fading to soreness. Heavy lifting and strenuous exercise are usually cleared around this point, subject to your surgeon’s review. Full healing of the lining, and the disappearance of the last tenderness, can take a few more weeks beyond that.
Recovery after stapling or artery ligation is usually quicker and less painful, which is precisely why those options exist. Your team will tailor the timeline to the procedure you actually had.
What can go wrong: risks explained without alarm
Every operation carries risk, and this one deserves an honest list, because the location makes a few complications more likely than people expect. None of this is a reason to panic. It is the information you need to recognize a problem early and to weigh the decision properly.
Bleeding is the most common. A little is normal; the concern is heavier bleeding, which can happen in the first day or two, or again around a week later when a scab separates. Infection is uncommon given how well the area is supplied with blood, but it does occur, and it tends to announce itself with worsening pain, fever and discharge.
Urinary retention, meaning difficulty emptying the bladder, is specifically flagged by the Mayo Clinic as a complication of hemorrhoidectomy. Pain and spinal anesthesia both contribute. It usually passes, though occasionally a temporary catheter is needed, and the Mayo Clinic notes it can lead to urinary tract infections.
Fecal impaction, where fear of pain leads to holding stool until it becomes hard and stuck, is a preventable complication that stool softeners and fiber are designed to avoid. Narrowing of the anal canal from scar tissue, called stenosis, is a later risk, which is why surgeons leave skin bridges intact.
Changes in control of gas or liquid stool are the complication people fear most. MedlinePlus lists incontinence among possible risks; it is uncommon with careful technique, and most reported cases are minor and improve, but it is a reason surgeons do not remove more tissue than necessary.
Finally, hemorrhoids can come back, particularly after stapling or artery ligation, as the Mayo Clinic and NHS both note, and especially if constipation and straining return. Surgery treats the tissue; habits protect the result.
Thrombosed external hemorrhoids: why timing changes the answer
There is one situation where the usual ladder is set aside and surgery can move to the front of the line, and it is worth understanding on its own because it is sudden, alarming and often misdiagnosed by the person experiencing it.
A thrombosed external hemorrhoid is an external hemorrhoid in which a blood clot has formed. It appears over hours as a firm, bluish, intensely painful lump at the edge of the anus. The pain is out of all proportion to the size, because the overlying skin is packed with nerves and the clot stretches it tight. People often fear an abscess or something worse; a quick examination settles the question.
Here the clock matters. The Mayo Clinic advises that removing the clot, through a small incision done under local anesthetic, can provide prompt relief and is most effective when performed within 72 hours of the clot forming. After that window, the body has usually begun to dissolve the clot on its own, and the pain starts to ease without intervention. Cutting at that stage adds a wound without adding much benefit, so the recommendation often shifts to warm baths, soft stools and patience.
Two points follow. First, if you develop a sudden painful lump, seeing a clinician promptly, rather than waiting a week, widens your options. Second, the procedure for a thrombosed hemorrhoid is far smaller than a full hemorrhoidectomy. It is often done in an office or emergency setting, takes minutes, and recovers in days rather than weeks.
Occasionally a thrombosed hemorrhoid is the first sign of a wider problem, with prolapsing internal tissue behind it. In that case the acute pain is dealt with first, and the longer conversation about who needs hemorrhoid surgery happens later, once everything has calmed down and the full picture can be assessed.
What people often get wrong about hemorrhoid surgery
The myths around this operation are stubborn, partly because the subject is embarrassing enough that people rely on hearsay rather than asking. A few corrections, grounded in what the sources actually say.
“If it bleeds, it needs surgery.” Bleeding is the defining symptom of grade I hemorrhoids, the mildest grade, and most bleeding settles with fiber, fluids and shorter toilet sits. Bleeding does need examination to confirm the cause, but it is not, on its own, a surgical indication.
“Surgery removes all my hemorrhoids so they can never come back.” Surgeons remove diseased tissue and leave healthy cushions in place for continence. Remaining tissue can enlarge later, especially if constipation returns, which is why both the Mayo Clinic and the NHS mention recurrence as a real possibility.
“Office banding is just a cheaper version of surgery.” They treat different problems. Banding handles internal tissue of grades I to III; it cannot address external hemorrhoids, skin tags or grade IV prolapse. Choosing between them is a question of anatomy, not thrift.
“Creams can shrink hemorrhoids permanently.” Over-the-counter preparations containing mild steroids or local anesthetics ease itching and soreness in the short term. The Mayo Clinic cautions against using steroid-containing products for more than a week without medical advice because they can thin skin. They do not change the structure of a prolapsing hemorrhoid.
“Recovery is a few days.” That is true for banding or a small clot removal. For excisional hemorrhoidectomy, MedlinePlus puts typical recovery at around two to three weeks.
“Doctors refuse surgery to save money.” The reluctance is clinical: pain, continence, scarring and the fact that most people improve without it. When the criteria are met, surgery is recommended.
Questions to ask your care team before agreeing to hemorrhoid surgery
A good surgical consultation is a two-way conversation, and the quality of the decision often depends on the quality of the questions. Take this list with you, and do not be shy about asking for answers in plain language.
- What grade are my hemorrhoids, and do I have an external component or skin tags as well?
- Has the cause of my bleeding been confirmed, and do I need a colonoscopy or sigmoidoscopy before any procedure?
- Have I genuinely exhausted conservative treatment and office procedures, or is there another step worth trying first?
- Which operation are you recommending, excision, stapling or artery ligation, and why that one for my anatomy?
- Will the wounds be closed with stitches or left open, and how does that affect my healing?
- What kind of anesthesia will I have, and what are my options?
- What should I expect in the first 72 hours, and what pain plan will I go home with?
- How do I keep my first bowel movement manageable, and what should I do if I cannot pass urine?
- When can I return to desk work, driving, exercise and heavy lifting?
- What are the chances these come back, and what habits most protect the result?
- Which symptoms after surgery should prompt a phone call, and which should send me to an emergency department?
- If I take blood thinners or have diabetes, inflammatory bowel disease or an immune condition, how does that change the plan?
Notice that several of these questions are really about whether surgery is needed at all. Surgeons respect that line of inquiry. If the answers leave you unsure, asking for time to think, or for a second opinion from another colorectal specialist, is entirely reasonable for an elective operation on a benign condition. The decision should feel like yours, made with the team, not handed to you.
When to call your doctor
Most of this article has argued for patience: fiber first, procedures second, surgery last. Patience has limits, and there are moments, both before and after treatment, when the right move is to pick up the phone the same day.
Before any treatment, seek medical care promptly if you have rectal bleeding that is heavy, that is dark or mixed into the stool rather than bright red on the surface, or that comes with unexplained weight loss, a change in bowel habit lasting more than a few weeks, dizziness or faintness. The NHS and Mayo Clinic are clear that bleeding should not be assumed to be hemorrhoids without an examination, especially if you are over 40 or have a family history of bowel cancer. A sudden, intensely painful lump at the anus also deserves a same-day appointment, because clot removal is most useful within about 72 hours.
After surgery, call your care team without delay if you notice any of the following:
- Bleeding that soaks through a dressing or pad, passes clots, or does not slow with rest.
- Inability to pass urine for several hours despite drinking normally.
- Fever, chills, or pain that worsens after day three instead of easing.
- Foul-smelling discharge, spreading redness, or a hot swollen area near the wounds.
- No bowel movement for several days despite softeners, or a sense of hard stool stuck that you cannot pass.
- Severe pain not controlled by the plan you were sent home with.
Go to an emergency department or call emergency services if bleeding is heavy and continuous, if you feel faint or your heart is racing, or if you develop severe abdominal pain or vomiting. These are rare, but they are the situations where waiting until morning is the wrong choice. Your surgical team would far rather hear from you about a false alarm than meet a real one late.
Frequently asked questions
How do you know if hemorrhoids need surgery?
Surgery is usually considered when symptoms persist despite fiber, fluids, habit changes and office procedures such as banding, or when hemorrhoids are grade III or IV, prolapse and cannot be pushed back, include a large external component, or when a painful clot has formed within the last 72 hours. The decision also requires that other causes of bleeding have been ruled out by examination.
How bad is hemorrhoid surgery recovery?
Recovery after excisional hemorrhoidectomy is genuinely uncomfortable for the first several days, with pain peaking around bowel movements, then easing steadily. MedlinePlus describes typical recovery as about two to three weeks. Soft stools, warm sitz baths and a pain plan from your team make the biggest difference. Stapling and artery ligation usually recover faster and with less pain.
How long does hemorrhoid surgery take?
The operation itself is usually completed in well under an hour, though exact time depends on how many hemorrhoids are treated and the technique used. Preparation and recovery room time add several hours to the day. MedlinePlus and the NHS both describe it as typically a day-case procedure, with most people going home the same day once pain is controlled and they have passed urine.
Why don't doctors like to remove hemorrhoids?
Because hemorrhoidal cushions are normal tissue that contributes to continence, the recovery from excision is painful, scarring can narrow the anal canal, and most people improve with conservative treatment. Doctors set a deliberately high bar so that surgery is offered only when its benefits clearly outweigh a difficult few weeks. When that bar is met, they do recommend it.
What is the usual grade 4 hemorrhoids treatment?
Grade IV hemorrhoids stay prolapsed and cannot be pushed back, which makes office banding impractical and often unsafe. Surgery is usually discussed, most commonly excisional hemorrhoidectomy, sometimes stapled hemorrhoidopexy depending on anatomy and bleeding history. Fiber and stool softening still matter before and after any operation, and the treating team decides the approach after examination.
When is hemorrhoid surgery necessary rather than optional?
Hemorrhoid surgery is almost always elective, because the condition is benign. It becomes strongly advised rather than merely optional when prolapse cannot be reduced, bleeding is causing anemia, a thrombosed external hemorrhoid is seen early, or symptoms seriously affect daily life after every gentler option has failed. Even then, the final choice rests with the patient and treating team.
Hemorrhoidectomy vs rubber band ligation: which is better?
They suit different situations. Banding is an office procedure for internal grades I to III, quick with minimal downtime, but it may need repeating and cannot treat external hemorrhoids. Hemorrhoidectomy is more complete and addresses mixed disease and grade IV prolapse, at the cost of a longer, more painful recovery. Your surgeon matches the method to your anatomy and history.
Can hemorrhoids come back after surgery?
Yes. Surgeons leave healthy cushions in place, and remaining tissue can enlarge again, especially if constipation and straining return. The Mayo Clinic and NHS note recurrence is more likely after stapled hemorrhoidopexy or artery ligation than after excision. Long-term fiber intake, adequate fluids and limiting time on the toilet protect the result more than anything else.
Should I have hemorrhoid surgery during pregnancy?
Usually not. Hemorrhoids are common in pregnancy because of pressure from the growing uterus and hormonal changes, and the Mayo Clinic notes they often improve after delivery. Treatment during pregnancy focuses on fiber, fluids, warm baths and products your obstetric team approves. Surgery is deferred unless there is a pressing problem, and that judgment belongs to the care team.
What are the red-flag signs after hemorrhoid surgery?
Call your team the same day for bleeding that soaks a pad or passes clots, inability to urinate for several hours, fever or chills, pain that worsens after day three, foul discharge or spreading redness, or inability to pass stool despite softeners. Seek emergency care for heavy continuous bleeding, faintness or a racing heart.
References
- MedlinePlus: Hemorrhoid surgery
- NHS: Piles (haemorrhoids)
- NIDDK (NIH): Treatment of hemorrhoids
- Cleveland Clinic: Hemorrhoids
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Do Surgeons Choose Between Robotic, Laparoscopic and Open Hernia Repair?
Surgeons choose between robotic, laparoscopic and open hernia repair based on the hernia's location and size, whether it is a first repair or a…

What Does Progress Look Like in Fecal Incontinence Treatment? Biofeedback and Follow-Up
Biofeedback can help some adults with fecal incontinence, especially when weakened or poorly coordinated pelvic floor muscles or reduced rectal sensation are part of…
Minimally Invasive Surgery Recovery: Why Small Cuts Still Need a Gradual Return to Activity
Minimally invasive surgery recovery time is usually shorter than after open surgery, yet it is still measured in weeks. NHS guidance suggests many people…

Fever, Wound Redness or Bowel Trouble After Appendectomy: What to Watch and When to Call
A mild temperature in the first day or two after appendectomy is common and usually reflects the body's inflammatory response to surgery. A fever…

Fever, Wound Redness or Bowel Trouble After Appendectomy: What to Watch and When to Call
A mild temperature in the first 24 to 48 hours after appendectomy is common and usually reflects the body's response to surgery, not infection.…

What Are the Warning Signs of a Bile Leak After Gallbladder Surgery? A Rare Risk Explained
A bile leak after gallbladder surgery is an uncommon complication in which bile escapes from the sealed duct stump or a bile duct into…