

Before Thyroidectomy: Ultrasound, Biopsy, Voice Checks and Medicines to Pause
Key Takeaways
- Ultrasound grading, often with the TI-RADS system, decides which thyroid nodules are biopsied, and most nodules turn out to be benign.
- Biopsy results are reported in Bethesda categories from non-diagnostic to malignant, and an indeterminate category may lead to repeat sampling, molecular testing or lobe removal rather than a definite answer.
- The recurrent laryngeal nerve controls each vocal cord and lies directly behind the thyroid, which is why many surgeons check cord movement with a scope before operating.
- An overactive thyroid is brought into the normal range with antithyroid medicine, which can take one to two months to work, before surgery is scheduled.
- Blood thinners, anti-inflammatory painkillers and supplements such as fish oil, ginkgo and high-dose vitamin E are the items most often paused, always on the prescriber's timetable.
- Temporary low calcium from stunned parathyroid glands is common after total thyroidectomy, and tingling around the lips or fingertips is its earliest sign.
Thyroidectomy preparation usually includes a neck ultrasound, a needle biopsy if a nodule looks suspicious, blood tests for thyroid hormone and calcium, and often a look at the vocal cords. Your surgical team will tell you which medicines to pause, typically blood thinners, some supplements and certain diabetes drugs, and which to continue. Never stop a prescribed medicine without their instruction.
Somewhere between the endocrinologist’s office and the car park, the word lands: surgery. The nodule that showed up on a scan for something else, or the overactive gland that has kept your heart racing for a year, now has a date attached to it. Most people spend the drive home thinking less about the operation itself and more about the scaffolding around it. What will they scan? Will someone put a camera down my throat? Do I really have to stop the tablets I take every morning?
Thyroidectomy preparation is, in truth, a sequence of small, sensible steps that answer questions the surgeon needs settled before an incision is made. Each one has a reason. The ultrasound maps the gland. The biopsy sorts a nodule into a category the team can act on. The voice check protects a nerve that runs a few millimeters from the operating field.
This explainer walks through that sequence in the order it usually happens, then follows you home through the first days and weeks, with the evidence stated plainly and the decisions left where they belong: with your treating team.
What thyroidectomy preparation actually involves, and what happens in the operating room
A thyroidectomy is an operation to remove part or all of the thyroid, the butterfly-shaped gland at the front of the neck that makes hormones controlling how fast the body burns energy. Surgeons speak of a lobectomy or hemithyroidectomy when one side is removed and a total thyroidectomy when the whole gland comes out. Which one you are offered depends on what the ultrasound and biopsy show and on how the gland is behaving.
The operation itself is done under general anesthesia through a small horizontal cut low on the neck, usually placed along a natural skin crease. The surgeon lifts thin muscles aside, identifies the gland, and then works carefully around two structures that matter more than the thyroid itself: the recurrent laryngeal nerves, which move the vocal cords, and the four parathyroid glands, rice-grain-sized glands behind the thyroid that regulate blood calcium. Mayo Clinic describes the procedure as typically taking one to two hours, though complex or large glands can take longer.
Preparation, then, is everything that lets the surgeon do that work safely. In broad strokes it covers four areas: imaging to map the gland and any lymph nodes; tissue sampling to classify a nodule; blood tests to check hormone levels, calcium and vitamin D; and a review of every medicine and supplement you take. A voice assessment is added when there is any reason to think a vocal cord might already be weak.
None of these steps is unique to one hospital or one country. They appear in the same order in guidance from the NHS, Mayo Clinic and Cleveland Clinic because they answer the same universal questions. What is in the neck? What is it doing? What could complicate removing it?
Who is usually offered thyroidectomy, and who is usually asked to wait
Thyroid surgery is offered for a fairly short list of reasons. The NHS lists surgery as the main treatment for most thyroid cancers. Beyond cancer, surgeons operate for nodules whose biopsy is suspicious or indeterminate, for large goiters that press on the windpipe or food pipe and cause swallowing or breathing symptoms, and for an overactive thyroid, most often Graves disease or a toxic nodule, when medicines or radioactive iodine are unsuitable or have not controlled the condition. Some people with hyperthyroidism choose surgery because they want a definitive treatment or because they plan a pregnancy soon and want to avoid radioactive iodine.
Equally important is who is asked to wait. Someone whose thyroid is still overactive is almost always asked to hold off until hormone levels are brought into the normal range with medicine, because operating on a gland in full overdrive raises the risk of a dangerous surge of thyroid hormone during or after surgery, sometimes called thyroid storm. A person with an uncontrolled heart rhythm, poorly controlled blood pressure or a recent chest infection may also be scheduled later once those are addressed.
Pregnancy changes the calculus too. When surgery cannot safely be delayed until after birth, teams generally aim for the second trimester, and the decision sits with the obstetric and surgical teams together.
Small, benign-appearing nodules with reassuring biopsies are often not operated on at all. Guideline-based care increasingly favors monitoring these with repeat ultrasound rather than removing them, which is one reason the biopsy result matters so much: it is frequently the step that decides whether surgery is needed rather than simply how it will be done.
Why the ultrasound comes first, and what the surgeon is looking for
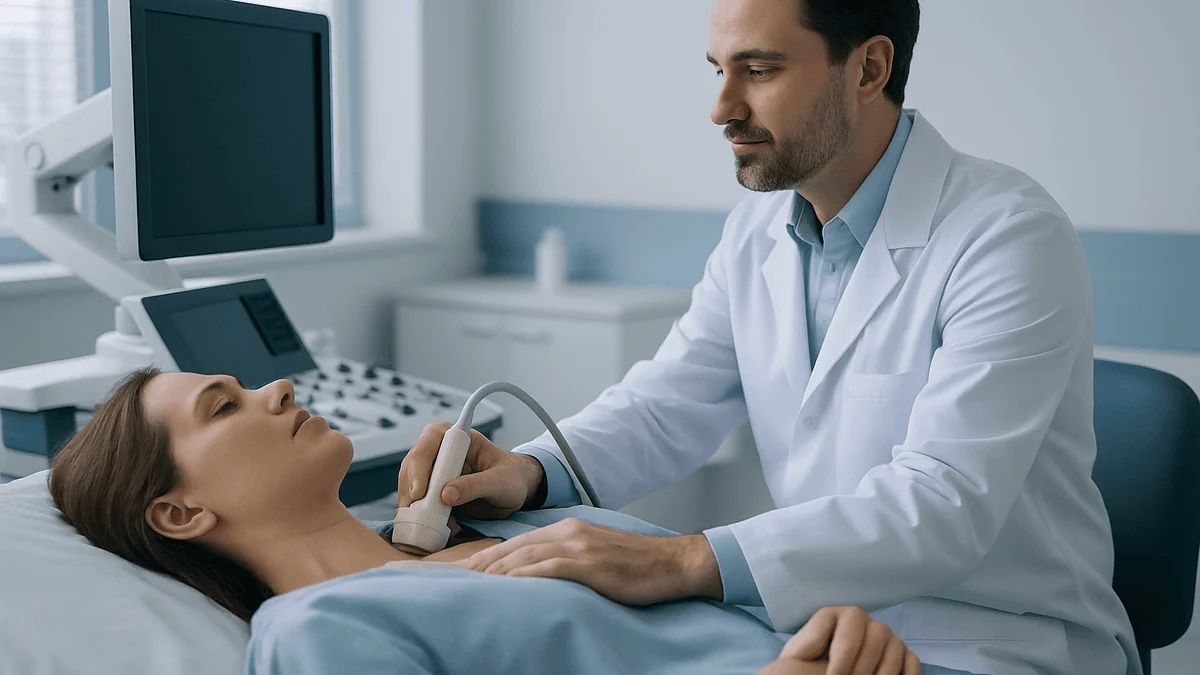
Ultrasound uses sound waves to build a live picture of the gland; no radiation, no needles, and typically twenty to thirty minutes on a couch with gel on your neck. It is the workhorse of thyroidectomy preparation because it answers several questions at once. How large is the gland? Is a nodule solid, fluid-filled or mixed? Does it have features that raise concern, such as irregular edges, tiny bright calcium specks, a shape that is taller than it is wide, or a very dark appearance on the screen? Are any lymph nodes along the side of the neck enlarged or abnormal?
Radiologists commonly score these features using a structured system, often abbreviated TI-RADS, that grades nodules from very low to high suspicion. The grade, together with the nodule’s size, determines whether a biopsy is recommended. The threshold is not the same for every grade: a low-suspicion nodule may only be sampled if it is large, while a high-suspicion nodule is sampled at a smaller size.
For the surgeon, the ultrasound is also a map. Knowing before the operation that a nodule sits at the back of the gland near the nerve, or that a lymph node in the central neck looks suspicious, changes how the operation is planned and how the consent conversation is framed. A pre-operative neck ultrasound that carefully assesses lymph nodes is a standard recommendation in thyroid cancer guidance for exactly this reason.
What the scan cannot do is tell you definitively whether a nodule is cancer. It estimates probability. Cleveland Clinic and Mayo Clinic both note that the large majority of thyroid nodules are benign, and the ultrasound’s job is to pick out the minority that deserve a needle.
What thyroid biopsy results really tell you before surgery
A fine-needle aspiration, usually shortened to FNA, is a biopsy in which a very thin needle is passed into the nodule under ultrasound guidance to draw out a few cells for a pathologist to examine. It is done awake, often with a little local anesthetic, and takes minutes. Most people describe pressure rather than pain. A small bruise afterward is common; anything more than that is unusual.
The pathologist reports the result using a standardized scale, most commonly the Bethesda system, which places the sample in one of six categories. In plain terms these run from non-diagnostic (not enough cells to judge), through benign, to two indeterminate categories where the cells look atypical but not clearly cancerous, then suspicious for malignancy, and finally malignant.
Understanding your category matters because it shapes the surgical plan:
- A benign result often means monitoring rather than surgery, unless the nodule is causing pressure symptoms.
- An indeterminate result is the gray zone. Options may include repeating the biopsy, molecular testing of the cells, or removing the affected lobe so the whole nodule can be examined.
- A suspicious or malignant result usually points toward surgery, with the extent decided by the size of the tumor and the ultrasound findings in the lymph nodes.
Two honest caveats. First, a non-diagnostic sample is not a bad sign; it simply means the needle did not capture enough cells, and repeating it is routine. Second, an indeterminate category cannot be resolved by more worry. The uncertainty is real, and the team will explain what the evidence supports for that specific category rather than promising a clean answer. The final diagnosis, when surgery is done, comes from examining the removed tissue itself.
Voice checks before thyroidectomy: why the surgeon looks at your vocal cords
The recurrent laryngeal nerve on each side runs directly behind the thyroid lobe and controls the vocal cord on that side. Injury to one nerve typically leaves a hoarse, breathy voice; injury to both, which is rare, can affect breathing. Because the nerve is the structure most at risk during the operation, knowing how the cords are moving beforehand is a basic part of thyroidectomy preparation.
The simplest check is a conversation. The surgeon listens to your voice and asks whether it has changed, whether you tire when talking, or whether liquids make you cough. Many teams go a step further with laryngoscopy, in which a slim flexible camera is passed through the nose, or a small angled mirror is used at the back of the mouth, to watch the cords move while you say a long vowel. It is brief and mildly uncomfortable rather than painful.
Guidelines generally recommend a formal look at the cords when there is any voice change, when a person has had previous neck or chest surgery, or when the ultrasound raises concern about a cancer growing beyond the gland. Some surgeons check everyone, reasoning that a cord can already be weak without the person noticing, and that finding this out afterward makes it impossible to know whether surgery caused it.
During the operation itself, many surgeons use a monitoring system in which the breathing tube carries sensors that signal when the nerve is being stimulated. The evidence on whether monitoring lowers permanent injury rates is mixed; it is best described as a tool that helps identify the nerve rather than a guarantee. Mayo Clinic notes that temporary hoarseness or a weak voice after surgery is common and usually resolves, while permanent change is uncommon. Your surgeon can share their own approach.
Getting hormone levels steady when the thyroid is overactive
If your thyroidectomy is being done for an overactive gland, the single most important preparatory step happens weeks before the operation, not the night before. An overactive thyroid pushes the heart rate up, raises blood pressure, and leaves the body in a state where the stress of surgery could trigger a sudden, severe worsening. Bringing hormone levels into the normal range first makes anesthesia safer and the operation calmer.
Two classes of medicine do most of this work. Antithyroid drugs, the thionamide class, act inside the gland to block the enzyme that builds thyroid hormone. They take time to show their effect because the gland already holds a store of made hormone that must be used up; the NHS notes that it can take one to two months for symptoms to settle on these medicines, with blood tests guiding adjustments along the way. Beta blockers act elsewhere: they blunt the effects of excess hormone on the heart and nervous system, slowing the pulse and easing tremor within hours to days, without changing hormone production.
Some surgical teams add a short course of an iodine solution in the final days before a Graves disease operation. The mechanism is that a large iodine load temporarily reduces hormone release and blood flow through the gland, which some surgeons feel makes the operation less bloody. This is a specialist decision with specific timing, and it is only ever started on the surgeon’s or endocrinologist’s instruction.
What this means for you is practical: keep every pre-operative blood test appointment, take the medicines exactly as prescribed, and expect the date to move if levels are not yet where the team wants them. A postponed operation for this reason is not a setback; it is the plan working.
Which medicines to pause before thyroidectomy, and which to keep taking
Nearly everyone facing surgery asks the same question: what do I stop? The honest answer is that the list is built for you by the anesthesia and surgical team, based on the specific drugs you take and how long each stays active in the body. The table below explains why certain classes come up so often; it is a guide to the conversation, not a set of instructions.
| Medicine class | Why it matters before neck surgery | Typical approach |
|---|---|---|
| Anticoagulants (blood thinners) and antiplatelet drugs | Bleeding into the tight space of the neck can compress the airway; these drugs slow clotting | Often paused for a period set by the prescriber, sometimes with a bridging plan; never stopped on your own |
| Non-steroidal anti-inflammatory painkillers | Reduce platelet function and can increase surgical bleeding | Frequently paused in the days before; acetaminophen is often the suggested alternative |
| Diabetes medicines, including insulin | Fasting before anesthesia changes blood sugar; some tablets carry specific perioperative cautions | Adjusted by the prescriber for the fasting period |
| Antithyroid drugs and beta blockers | Keep hormone effects controlled through the operation | Usually continued, often including the morning of surgery, on the team’s instruction |
| Levothyroxine (thyroid hormone replacement) | Long-acting; missing a dose does not destabilize levels quickly | Usually continued or restarted after surgery as directed |
| Blood pressure and heart medicines | Stopping abruptly can cause rebound problems | Most are continued; the anesthesia team advises on the morning dose |
Two points deserve emphasis. Blood thinners are the class where an unplanned stop or an unplanned continuation can each cause harm; the prescriber weighs your clot risk against the surgeon’s bleeding concern. And everything you swallow, including over-the-counter cold remedies and sleep aids, belongs on the list you bring to the pre-assessment appointment, because several contain ingredients from the rows above.
Supplements, herbal products and iodine: the quiet bleeding risk
People are usually diligent about prescription medicines and surprisingly casual about the bottles in the kitchen cupboard. Yet several common supplements affect clotting or interact with anesthesia, and anesthesia teams routinely ask about them for that reason.
Fish oil and high-dose vitamin E both reduce platelet stickiness. Ginkgo, garlic extracts and ginger supplements have been associated with increased bleeding in case reports. St John’s wort changes how the liver processes many drugs, including some used during anesthesia. None of these is a reason for alarm; they are simply things to disclose so the team can decide whether to pause them and when. Most pre-assessment services suggest stopping non-essential supplements in the week or two before an operation, but the timing should come from your team rather than from a general rule.
Iodine deserves its own mention because it sits at the heart of thyroid function. The gland needs iodine to make hormone, which is why a sudden large intake, from kelp or seaweed supplements, iodine-containing multivitamins or some cough remedies, can push an already overactive gland further or interfere with tests and treatments planned around the operation. The NIH Office of Dietary Supplements notes that kelp supplements in particular can contain iodine amounts far above daily needs and vary widely between products. If radioactive iodine treatment is a possibility after surgery for thyroid cancer, the team may later ask you to follow a short low-iodine diet, and taking iodine supplements in the run-up would work directly against that.
Calcium and vitamin D are a special case. Because the parathyroid glands can be bruised during surgery, some teams check vitamin D levels before the operation and correct a deficiency first. Whether you should take or pause these is a question for the team, not the label.
Fasting, anesthesia and the night before surgery
The pre-assessment appointment, usually a week or two before the operation, is where the practical details get pinned down. A nurse or anesthetist reviews your medical history, checks blood pressure and weight, arranges any final blood tests and, for some people, an electrocardiogram. This is the moment to hand over your complete medicine and supplement list and to mention anything you might think irrelevant: loose teeth, sleep apnea, a previous reaction to anesthesia, a tendency to bruise easily.
Fasting instructions follow a familiar pattern. Solid food is stopped several hours before anesthesia, commonly from the night before for a morning operation, while clear fluids are often allowed until closer to the time. The exact cut-offs are set by the anesthesia team and printed on your admission letter; follow those rather than a friend’s memory of their own surgery, because an operation may be delayed if the stomach is not empty enough.
You will typically be asked to shower with ordinary soap, avoid lotions on the neck and chest, remove jewelry and nail polish, and leave valuables at home. Many people find it helpful to arrange a few things in advance:
- A responsible adult to take you home and stay the first night, since you cannot drive after a general anesthetic.
- Loose, front-opening tops that do not need to be pulled over the head and neck.
- A couple of extra pillows for the first nights at home.
- Any regular medicines the team has told you to continue, in their original packaging.
Smoking deserves a frank word. Stopping even a few weeks before surgery improves wound healing and lowers chest complications, and it makes anesthesia safer. Your team can point you to support; this is one of the few preparation steps entirely within your control.
Is it a big deal to have your thyroid removed?
People ask this question with two very different anxieties behind it. One is about the operation; the other is about life without the gland. Both deserve a straight answer.
As an operation, thyroidectomy is common, well studied and generally low risk in experienced hands. It is still major surgery under general anesthesia, and the neck is an unforgiving space. The complications that surgeons watch for are specific. Bleeding into the neck in the first hours can compress the airway, which is why you are observed closely and why MedlinePlus lists swelling and difficulty breathing among the reasons to seek urgent help. Injury to the laryngeal nerve can change the voice, usually temporarily. Damage to or removal of the parathyroid glands can drop blood calcium, causing tingling around the lips and fingers and, if untreated, muscle cramps. Infection and anesthetic reactions are possible with any operation. Your surgeon should give you their own figures for these events, because rates vary with the extent of surgery and the reason for it, and guideline documents caution against quoting a single universal percentage.
Life afterward depends on how much gland is removed. After a total thyroidectomy, the body can no longer make thyroid hormone, so a daily replacement tablet becomes lifelong; the NHS describes this plainly for people treated for thyroid cancer. After removal of one lobe, many people keep making enough hormone from the remaining half, though some will need replacement and everyone needs blood tests to find out.
So is it a big deal? It is a significant operation with a short recovery for most people and, for many, a permanent daily tablet. It is not, for the great majority, life-limiting. Both halves of that sentence are true, and a good consent conversation covers both.
The first 48 hours: calcium checks, voice, swelling and sleeping sitting up
You wake in a recovery area with a dressing across the lower neck and, in some cases, a thin drain tube that is removed before you go home. The throat feels sore from the breathing tube; swallowing is uncomfortable rather than dangerous. MedlinePlus notes that many people stay in hospital overnight, with some going home the same day and others staying a second night depending on the extent of surgery and how calcium levels behave.
Calcium is the number the nurses watch. After a total thyroidectomy the parathyroid glands may be stunned even when they have been carefully preserved, and blood calcium can dip in the first day or two. You may have blood tests at set intervals and be asked to report tingling around the mouth or in the fingertips, the earliest sign of a low level. If it falls, the team treats it, often with calcium tablets and sometimes active vitamin D, and then tapers as the glands recover. This is common and usually temporary; permanent low calcium is much less frequent.
Your voice may be hoarse, quieter or tire easily. Most of this settles over days to weeks as swelling around the nerve resolves. A small amount of bruising and a firm, swollen feeling above the scar is expected.
On the question everyone asks: sleeping sitting up. There is no rule that you must, and no study that fixes a number of nights. Many surgeons suggest keeping the head raised on two or three pillows, or in a reclining chair, for the first few nights because it eases swelling and makes swallowing and breathing feel more comfortable. Once the swelling is settling and you can lie flat without a sense of pressure, you can return to your normal position. Follow the specific advice on your discharge sheet, because instructions vary between surgeons.
Thyroidectomy recovery time: how many days should you rest after thyroid surgery?
Recovery from thyroid surgery is quicker than most people expect and slower in one or two specific ways than they hope. The broad pattern is consistent across mainstream guidance. MedlinePlus describes most people returning to normal activities within a few weeks, with the first several days spent taking things gently. Mayo Clinic gives a similar outline, with everyday activities resuming over one to two weeks and full recovery of energy taking a little longer.
A typical, non-binding sequence looks like this:
- Days 1–3: rest at home, short walks around the house, soft or normal food as comfort allows, pain controlled with the medicines the team has suggested. Neck movement is encouraged; stiffness comes from holding still, not from moving.
- Days 4–7: longer walks, light household tasks, showering with the wound covered or uncovered as directed. Many people with desk-based work start thinking about returning toward the end of this window.
- Weeks 2–3: most routine activities resume. Heavy lifting, straining and vigorous exercise are commonly held back for roughly two to three weeks to protect the wound; the exact advice is on your discharge instructions.
- Weeks 4–6: the scar begins to soften and fade, though it continues to mature for a year or more. Follow-up blood tests check hormone and calcium levels and guide any adjustment to replacement therapy.
What tends to lag is energy, particularly after total thyroidectomy while hormone replacement is being fine-tuned. Tiredness in the first weeks is normal; tiredness that deepens over months is a reason to ask for a blood test rather than to push through.
Driving is usually reasonable once you can turn your head comfortably to check mirrors and are no longer taking sedating painkillers, typically a week or so for many people, but check with your team and, where relevant, your insurer.
What to eat after thyroidectomy, from the first week to a year on
The internet is full of restrictive post-thyroidectomy diets. The evidence supports very few of them.
In the first days, comfort guides the menu. A sore throat from the breathing tube and a swollen neck make soft, cool or lukewarm foods easier: yogurt, soup, soft eggs, well-cooked pasta, smoothies. Very hot drinks and sharp-edged foods like crusty bread or crisps may sting. There is no medical reason to avoid protein or dairy; the wound needs both to heal. Most people are back to their usual diet within a week.
If your surgery was for thyroid cancer and radioactive iodine treatment is planned afterward, your team may ask you to follow a low-iodine diet for a short, defined period before that treatment. The logic is simple: starving the body of dietary iodine makes any remaining thyroid cells take up the radioactive iodine more avidly. This is temporary and specific; it is not a lifelong rule, and it is not needed at all if radioactive iodine is not part of your plan.
The question many people search, what not to eat a year after thyroidectomy, has a reassuring answer. For most people there are no forbidden foods. What matters at a year, and forever after if you take thyroid hormone replacement, is how you take the tablet. Levothyroxine is absorbed in the gut, and its absorption is reduced by calcium and iron supplements, some antacids, soy products and coffee taken at the same time. Prescribers therefore usually advise taking it on an empty stomach and separating it from those items; the specific gap is something your pharmacist or prescriber will set. Consistency matters more than perfection, because blood tests are interpreted against your routine.
Weight can shift after thyroid surgery while hormone levels settle. That is a reason for a blood test, not a diet.
What people often get wrong about how to prepare for thyroidectomy
Some myths about thyroidectomy preparation are harmless. A few are not.
“I should stop all my medicines to be safe.” This is the most dangerous misconception. Stopping a blood thinner, a heart medicine or an antithyroid drug without instruction can cause a stroke, a rhythm problem or a hormone surge. The team gives you a written list of what to pause and what to continue; the safe move is to follow it and to phone if anything is unclear.
“A benign biopsy means the nodule is definitely benign.” A benign result is reassuring and carries a low false-negative rate, but no test is perfect. It is why nodules are often followed with a repeat ultrasound rather than dismissed, and why growth or new symptoms should prompt a fresh look.
“They will cut my throat and I will never sing again.” Temporary voice change is common; permanent change is uncommon. The pre-operative voice check and careful surgical technique exist precisely to protect the nerve, and most people are talking normally within weeks.
“Removing the thyroid means I will gain weight no matter what.” Weight changes can happen while hormone replacement is being adjusted, but a properly dosed replacement restores a normal metabolic rate. Persistent change is a signal to recheck levels, not an inevitability.
“I need a special healing diet or supplement stack.” No supplement has been shown to speed thyroid wound healing, and several increase bleeding risk. Ordinary balanced food does the job.
“I must sleep bolt upright for weeks.” A few nights with the head raised is a comfort measure, not a medical requirement, and there is no evidence that lying flat once swelling has settled causes harm.
The thread running through all of these is the same: the written instructions from your own team outrank general advice, including this article.
Questions to ask your care team before thyroid surgery
A consent conversation is a two-way exchange, and surgeons generally welcome specific questions; they tend to lead to better-informed decisions and calmer recoveries. Write yours down beforehand, and consider bringing someone to listen with you.
About the plan itself:
- Are you removing one lobe or the whole gland, and what would make you change that decision during the operation?
- What did my ultrasound and biopsy show, and which Bethesda category was my nodule?
- Will you check my vocal cords before surgery, and do you use nerve monitoring?
- Will lymph nodes be removed, and if so, which ones and why?
About medicines and preparation:
- Which of my medicines and supplements should I pause, when, and when do I restart them?
- Who is coordinating the pause of my blood thinner with my cardiologist or primary care doctor?
- Do I need my vitamin D or calcium checked or corrected before the operation?
- What are my exact fasting times?
About risks and afterward:
- What are your own rates of temporary and permanent voice change and low calcium for this type of operation?
- How long do you expect me to stay in hospital, and what would extend that?
- How will my calcium be monitored, and what symptoms should I report immediately?
- Will I need thyroid hormone replacement, and who manages the blood tests and adjustments?
- When can I drive, return to work, exercise and lift my children or grandchildren?
- If this is for cancer, what happens after the pathology result, and is radioactive iodine or further treatment a possibility?
You are entitled to clear answers in plain language. If an answer is uncertain, a good team will say so and explain what the evidence does and does not show.
When to call your doctor
Most recoveries are uneventful, but a few problems after thyroid surgery need prompt attention because of where the operation is. Your discharge sheet will list local contact numbers; keep it by the phone.
Seek emergency help immediately, by calling emergency services or going to the nearest emergency department, if you notice any of the following, which MedlinePlus and Cleveland Clinic list as urgent:
- Rapid swelling of the neck, a feeling of tightness or pressure, or difficulty breathing or swallowing. Bleeding into the neck can compress the airway and is treated as an emergency.
- Sudden noisy or labored breathing, or a voice that becomes very weak along with breathing difficulty.
- Severe muscle cramps, spasms of the hands or feet, or twitching of the face, which can signal a sharp drop in calcium.
- Chest pain, or a racing, irregular heartbeat with sweating, fever and confusion, which after surgery for an overactive gland could indicate a hormone surge.
Call your surgical team or doctor the same day, without waiting for a scheduled appointment, if you have:
- Tingling or numbness around the mouth or in the fingers or toes, especially if it is spreading or not improving with any calcium the team has prescribed.
- A fever, or increasing redness, warmth, pus or a foul smell at the wound.
- A wound that opens, or bleeding that does not stop with gentle pressure.
- Pain that is worsening rather than easing after the first few days.
- Hoarseness that is not beginning to improve after a few weeks, or liquids that repeatedly make you cough.
Contact your doctor at the next available appointment for deepening tiredness, feeling unusually cold or hot, unexplained weight change or low mood in the weeks and months after surgery, since these can reflect hormone replacement that needs adjusting. None of these lists replaces the specific instructions from your own team, and when in doubt, calling is always the right choice.
Frequently asked questions
How long do I have to sleep sitting up after a thyroidectomy?
There is no fixed requirement, and no study sets a number of nights. Many surgeons suggest keeping your head raised on two or three pillows for the first few nights because it eases neck swelling and makes swallowing more comfortable. Once the swelling is settling and lying flat no longer feels tight, you can return to your usual position. Follow the specific advice on your discharge instructions.
What should I not eat one year after thyroidectomy?
For most people there are no forbidden foods a year after thyroid surgery. What matters, if you take thyroid hormone replacement, is timing: calcium and iron supplements, some antacids, soy products and coffee can reduce absorption when taken at the same moment as the tablet. Your prescriber or pharmacist will advise on separating them. A short low-iodine diet is only relevant if radioactive iodine treatment is planned.
Is it a big deal to have your thyroid removed?
It is a significant operation under general anesthesia, with specific risks to the voice nerves and the calcium-regulating parathyroid glands, but it is also common, well studied and followed by a short recovery for most people. After total removal you will need a daily thyroid hormone tablet for life; after removal of one lobe, many people do not. Your surgeon should explain their own complication rates.
How many days should I rest after thyroid surgery?
Most people take things gently for the first several days and return to routine activities within one to two weeks, according to MedlinePlus and Mayo Clinic guidance, with heavy lifting and vigorous exercise commonly held back for roughly two to three weeks. Desk-based work is often possible toward the end of the first week. Energy can lag longer while hormone levels settle, so pace yourself and follow your team’s timeline.
How do I prepare for a thyroidectomy in the weeks beforehand?
Attend every appointment, including the ultrasound, any biopsy, blood tests and the pre-assessment visit. Bring a complete list of prescription medicines, over-the-counter products and supplements so the team can decide what to pause. If your thyroid is overactive, take antithyroid medicine as prescribed so levels are steady in time. Stop smoking if you can, arrange someone to take you home, and write down your questions.
Which medications are usually stopped before thyroid surgery?
Blood thinners and antiplatelet drugs, non-steroidal anti-inflammatory painkillers, and supplements that affect clotting such as fish oil, ginkgo and high-dose vitamin E are the items most often paused, while diabetes medicines are adjusted for fasting. Antithyroid drugs, beta blockers and most heart and blood pressure medicines are usually continued. The exact plan comes from your prescriber and anesthesia team; never stop anything without their instruction.
What does an indeterminate thyroid biopsy result mean?
It means the cells look atypical but the pathologist cannot say with confidence whether the nodule is benign or cancerous. Under the Bethesda system this covers two categories. Options usually include repeating the biopsy, sending the cells for molecular testing, or removing the affected lobe so the whole nodule can be examined. Your team will explain which approach the evidence supports for your category.
Why does the surgeon want to look at my vocal cords before thyroid surgery?
The nerves that move the vocal cords run directly behind the thyroid and are the structures most at risk during the operation. Checking cord movement beforehand, usually with a thin flexible scope through the nose, establishes a baseline and can reveal a cord that is already weak without your noticing. This is especially recommended if your voice has changed or you have had previous neck surgery.
Why is calcium checked after a total thyroidectomy?
The four parathyroid glands sit behind the thyroid and control blood calcium. Even when carefully preserved they can be stunned by surgery, causing calcium to dip in the first day or two. Nurses monitor blood levels and ask you to report tingling around the mouth or fingertips, the earliest sign. If levels fall, the team treats and then tapers as the glands recover; permanent low calcium is much less common.
What is the typical thyroidectomy recovery time before I can drive and exercise?
Many people can drive after about a week, once they can turn their head comfortably to check mirrors and are no longer taking sedating painkillers, though you should confirm with your team and insurer. Light walking is encouraged from the first days, while heavy lifting and vigorous exercise are commonly held back for two to three weeks to protect the wound. Full energy may take a few weeks longer.
References
- MedlinePlus: Thyroid gland removal
- MedlinePlus: Thyroid gland removal – discharge
- Cleveland Clinic: Thyroidectomy
- NHS: Thyroid cancer – Treatment
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

After a Longevity Program Visit: Sleep, Stress and Exercise Plans and When Reassessment Is Due
A longevity program follow up usually turns the first visit's measurements into three written plans: a sleep target of at least seven hours a…
Robotic Thyroidectomy Through the Armpit: What Does the Robot Change vs a Neck Incision?
A robotic transaxillary thyroidectomy removes the thyroid through an incision hidden in the armpit, using a surgeon-controlled robot to reach the neck beneath the…

Long-Term Care in Androgen Insensitivity Syndrome: Bone Health, Hormones and Support
Long-term care in androgen insensitivity syndrome (AIS) means lifelong follow-up with an endocrinologist and a wider team: monitoring bone density, using hormone replacement after…
Graves Disease in Pregnancy and When Planning a Family: How Treatment Is Adapted
Graves disease in pregnancy is usually managed with antithyroid medicines rather than radioactive iodine, which is not used in pregnancy. Guidelines generally favor propylthiouracil…

Robotic Thyroidectomy Recovery: Armpit Soreness, Shoulder Movement and Overhead Limits
After a robotic thyroidectomy done through the armpit, most people go home within a day, return to desk work within roughly one to two…
Minimally Invasive or Four-Gland Exploration Parathyroidectomy: How Is the Approach Chosen?
Surgeons choose between a minimally invasive (focused) parathyroidectomy and a four-gland exploration mainly on whether preoperative imaging clearly points to a single overactive gland.…