

Bronchitis Treatment When You Smoke: Why Quitting Is Part of the Plan

Key Takeaways
- Chronic bronchitis is defined by a mucus-producing cough on most days for at least three months in each of two consecutive years, not by how the cough sounds.
- Acute bronchitis is almost always viral, and CDC guidance is that antibiotics do not help it in otherwise healthy people, including smokers.
- Cigarette smoke slows or stops the cilia that sweep mucus out of the airways, which is why smokers clear infections more slowly and relapse more often.
- The WHO attributes over 70% of COPD cases in high-income countries to tobacco smoking, and chronic bronchitis is one of the two conditions grouped under COPD.
- Cilia regrow and airway inflammation subsides after quitting, but lung function already lost to emphysema is not regained; quitting protects what remains.
- Spirometry, a few minutes of blowing into a device, is how chronic bronchitis and COPD are confirmed, and a persistent cough with a significant smoking history is the usual reason to offer it.
Bronchitis treatment for smokers follows the same core steps as for anyone: rest, fluids, easing the cough, and antibiotics only when a bacterial infection is likely. The difference is that continued smoking keeps the airway lining inflamed, so recovery is slower and repeat episodes are more likely. Clinicians therefore treat quitting smoking as part of the treatment itself, and decide the rest based on whether the bronchitis is acute or chronic.
The cough usually announces itself at night. You sit up, reach for water, and notice the rattle has been there for two weeks now, maybe three. You have smoked for years and you already know what the doctor is going to say, which is partly why the appointment keeps sliding down the to-do list.
That hesitation is worth naming, because bronchitis treatment for smokers is not a lecture with a prescription attached. It is a practical plan built around one awkward fact: the thing that soothes the airway and the thing that irritates it are in a daily tug of war, and the medicines only pull on one side of the rope.
This explainer walks through what is happening inside your bronchial tubes, how clinicians decide between watchful waiting and active treatment, what the following weeks usually look like, and what the evidence actually shows about lungs recovering once the smoke stops.
Why bronchitis treatment for smokers starts with a different conversation
Bronchitis is inflammation of the bronchi, the branching tubes that carry air from the windpipe into the lungs. In someone who does not smoke, that inflammation usually has a single cause, most often a virus, and it settles once the infection passes. In someone who smokes, there are two irritants at work at the same time: the infection and the smoke.
That second irritant changes the clinical picture in three ways. First, the lining of the airway is already thicker and more mucus-heavy before the infection arrives, so symptoms tend to be louder. Second, the tiny hair-like structures called cilia, which sweep mucus and debris upward and out, are slowed or paralyzed by smoke, so the airway clears itself less efficiently. Third, each new episode raises the question of whether this is still an acute illness or the early stage of chronic bronchitis, a long-term condition defined by a productive cough lasting at least three months in each of two consecutive years, according to MedlinePlus.
So when a clinician asks about your smoking before asking about your cough, it is not moralizing. The answer determines which category you are likely in, how long recovery may take, and whether lung function testing belongs in the plan. It also explains why quitting is written into the treatment rather than added as an afterthought: it is the only step that addresses the irritant that will still be there once the virus has gone.
The rest of this article treats those two threads, the infection and the smoke, as a single problem, because that is how your care team will see it.
What is actually happening inside an irritated airway
Picture the inside of a bronchial tube as a corridor lined with a thin, moving carpet of mucus. Beneath that carpet sit millions of cilia, beating in coordinated waves roughly a dozen times per second, pushing the carpet upward toward the throat where it is swallowed or coughed out. Dust, pollen, bacteria and viral particles get trapped in the mucus and ride the carpet out. This is the mucociliary escalator, and it is the lung’s first line of housekeeping.
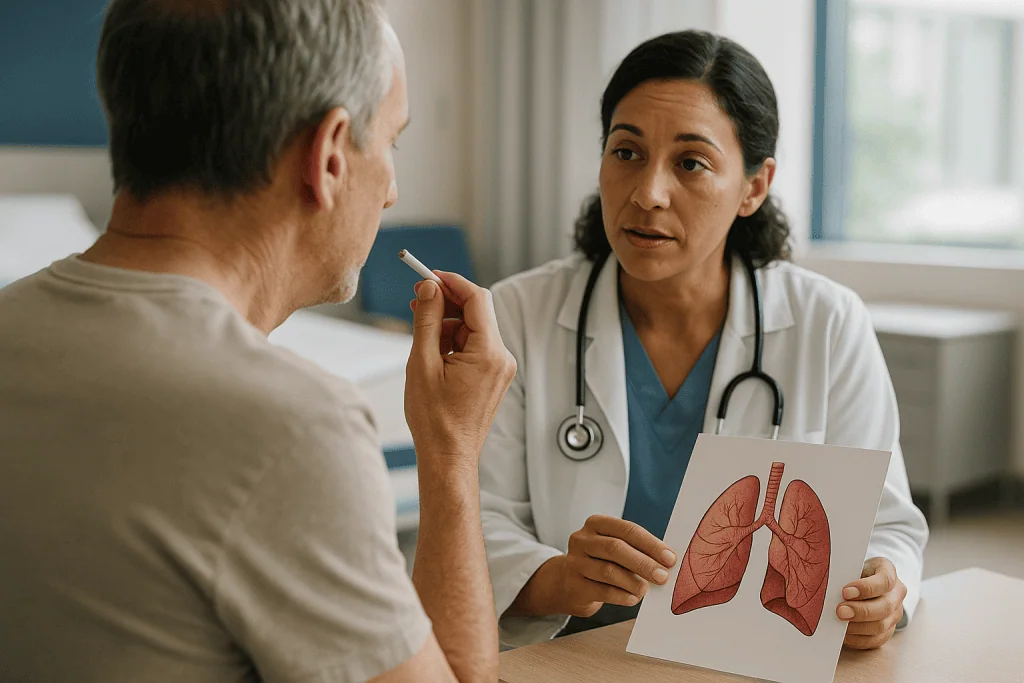
When a virus infects the cells lining the corridor, the body responds with inflammation. Blood vessels widen, immune cells arrive, the lining swells, and the mucus glands produce more secretions than usual. The corridor narrows and fills. The cough reflex, triggered by nerve endings in the irritated lining, becomes the backup system for clearing what the cilia cannot.
Cigarette smoke interferes at every stage. It slows or stops ciliary beating, so the escalator stalls. It causes the mucus glands to enlarge over time and produce thicker secretions. It damages the surface cells, which makes them easier for viruses and bacteria to colonize. And it keeps a low level of inflammation going even between infections, which is why many long-term smokers describe a morning cough that they have stopped noticing.
Bronchitis treatment works on this picture from two directions. Fluids and humidified air thin the mucus so the stalled escalator has less to move. Inhaled bronchodilators, medicines that relax the muscle around the airway, widen the corridor when wheeze or breathlessness is present. Antibiotics act only if bacteria are contributing, which in acute bronchitis they usually are not. Stopping smoke exposure is the one measure that lets the cilia begin to move again, and no medicine does that job for them.
Smokers cough vs bronchitis: how clinicians tell them apart
Many people who smoke live with a habitual cough and only book an appointment when something changes. Sorting out what has changed is the first task at the visit, and it is a matter of pattern rather than a single test.
The everyday smoker’s cough is typically worst in the morning, produces a modest amount of clear or pale mucus, and has been present in roughly the same form for months or years. It reflects the chronic irritation described above. Acute bronchitis layered on top usually arrives with a cold-like illness: sore throat, congestion, tiredness, sometimes a mild fever, then a cough that becomes the dominant symptom and lingers after the rest has cleared. The NHS notes that most acute bronchitis improves within about three weeks, though the cough itself can outlast the other symptoms.
Chronic bronchitis is a diagnosis of duration. MedlinePlus defines it as a mucus-producing cough on most days for at least three months a year, in two consecutive years, once other causes have been excluded. It is one of the two conditions grouped under chronic obstructive pulmonary disease, or COPD, the other being emphysema, which is damage to the air sacs themselves.
| Feature | Habitual smoker’s cough | Acute bronchitis | Chronic bronchitis |
|---|---|---|---|
| Usual trigger | Ongoing smoke irritation | Viral infection, occasionally bacterial | Long-term irritant exposure, most often smoking |
| Typical course | Stable for months or years | Improves within about 3 weeks (NHS) | Present 3+ months a year for 2+ years (MedlinePlus) |
| Usual assessment | History, examination | History, examination; imaging if pneumonia suspected | History plus spirometry (a breathing test) |
| Role of quitting | Primary measure | Speeds airway recovery | Core of long-term management |
The table simplifies, and real patients often sit between columns. That is exactly why the clinician’s questions about timing matter more than any single symptom.
Does smokers bronchitis go away on its own?
The honest answer depends on which kind you mean, and the distinction is not academic.

Acute bronchitis in a smoker usually does resolve, because the underlying viral infection runs its course regardless of what anyone does. The Mayo Clinic describes a cough that can persist for several weeks after the infection itself has cleared, and in smokers that tail tends to be longer, since the airway lining is starting from a more irritated baseline and clearing itself less efficiently. So yes, an individual episode generally goes away. It just takes its time, and a person who keeps smoking through it is asking a stalled escalator to carry a heavier load.
Chronic bronchitis is a different matter. By definition it has already lasted years, and the structural changes behind it, enlarged mucus glands and a thickened airway wall, do not reverse on their own while the irritant continues. The NHLBI, part of the NIH, is direct on this point: COPD, which includes chronic bronchitis, has no reversal, but it can be treated, and stopping smoking is the single most effective step in slowing its progression. That is a management goal, not a promise of disappearance.
What people often notice after quitting is that the daily cough changes character over the following weeks and months, sometimes getting temporarily more productive as cilia recover and begin moving accumulated mucus, then gradually easing. That pattern is described in mainstream quit-smoking guidance and is not a sign of harm. It is also not universal, and its timing varies widely between people.
The practical takeaway: an acute episode will likely settle whether or not you quit, but each episode you have while smoking makes the chronic form more likely. The question is less whether this cough will go away and more which category the next one falls into.
What clears up bronchitis fast, and what only feels like it does
Search engines are full of promises here, so it is worth being precise about what the evidence supports.
Nothing reliably shortens a viral bronchitis. The infection has a natural duration, and the treatments that help work by making that duration more comfortable and by preventing complications, not by compressing it. The NHS and Mayo Clinic both emphasize rest, plenty of fluids and, where appropriate, over-the-counter measures for fever or discomfort, with any choice of medicine discussed with a pharmacist or clinician.
Fluids matter more than they sound. Thin mucus moves; thick mucus sits. Warm drinks, steam from a shower and a humidifier in a dry bedroom all work on the same mechanical principle. Honey in warm water is a traditional cough soother with modest supporting evidence for adults and older children, though it is not suitable for infants under one year.
Cough suppressants are a mixed picture. A productive cough is doing useful work, and suppressing it entirely can leave mucus in place. Clinicians often reserve suppressants for a dry, sleep-wrecking cough at night, and this is a decision to make with them rather than at the pharmacy shelf.
Antibiotics are the biggest source of false speed. The CDC’s guidance is that acute bronchitis is almost always viral and antibiotics do not help it; they add side effects and drive resistance. When someone feels better a few days into a course, it is usually the infection resolving on its own schedule.
The one intervention with a direct mechanical effect on recovery is removing smoke from the airway. It does not shorten the virus, but it lets the cilia restart, which is the body’s own fast-clearing system. If there is a shortcut, that is the closest thing to it.
Who is usually treated actively, and who is asked to wait and watch
Bronchitis care is a triage exercise, and understanding where you sit on it explains why one person leaves with advice and another leaves with a prescription and a follow-up date.
Watchful waiting is the usual approach for an otherwise healthy adult, including a smoker, with a cough of less than three weeks, no high or persistent fever, normal breathing at rest, and a clear chest on examination. The clinician’s reasoning is that a viral illness will resolve, that antibiotics carry more harm than benefit in this group according to CDC guidance, and that a return visit is easy to arrange if the picture changes. Smoking does not by itself move someone out of this group, though it does earn a firmer conversation about the next steps.
Active treatment is more likely when any of the following applies: the person already has a diagnosis of COPD or chronic bronchitis, where an episode is called an exacerbation and may be treated with a short course of oral corticosteroids, medicines that dampen inflammation, sometimes alongside an antibiotic when mucus changes color or volume; there are signs pointing toward pneumonia, such as focal crackles on examination or a high fever, in which case a chest X-ray and antibiotics may follow; the person has heart failure, diabetes, a weakened immune system or is elderly; or breathing is measurably affected, with wheeze or low oxygen readings, which may prompt an inhaled bronchodilator.
Spirometry, the breathing test that measures how much and how fast air can be blown out, is not part of acute care but is often suggested to smokers with repeated episodes or a persistent cough, because it is how chronic bronchitis and COPD are confirmed. Being asked to book one is not an alarm; it is the clinician gathering the information needed to plan properly. Which group you belong to, and what follows, is always the treating clinician’s call.
Medicines your care team may discuss, by class and how they work
This section describes mechanisms and typical roles so the conversation with your prescriber makes more sense. It is not a menu, and nothing here should prompt starting, stopping or changing anything on your own.
Bronchodilators. These inhaled medicines relax the smooth muscle wrapped around the airways, widening them. Short-acting versions work within minutes and are used for wheeze or breathlessness during an acute episode. Long-acting versions, taken regularly, are a mainstay of chronic bronchitis and COPD management according to NHLBI guidance. They ease the work of breathing; they do not treat the infection or the inflammation itself.
Corticosteroids. Inhaled corticosteroids reduce airway inflammation over weeks and are generally reserved for people with established COPD who have frequent flare-ups. Oral corticosteroids, taken briefly during an exacerbation, act faster and more broadly. Neither has a routine role in uncomplicated acute bronchitis in someone without underlying lung disease.
Antibiotics. These kill or slow bacteria and have no effect on viruses. Their place in bronchitis is narrow: exacerbations of chronic bronchitis with features suggesting bacterial involvement, or suspected pneumonia. The CDC is explicit that acute bronchitis in otherwise healthy people does not warrant them.
Mucolytics. These thin mucus chemically. Evidence for benefit is modest and mainly in people with chronic bronchitis and frequent flare-ups.
Smoking-cessation medicines. Nicotine replacement products supply nicotine without smoke so withdrawal is manageable while the behavior is unlearned. Two prescription-only medicines act on brain receptors involved in craving and reward. Both categories have consistent trial evidence for improving quit rates when combined with behavioral support, and both are decisions for the prescribing clinician, who will weigh other conditions and medicines.
Notice that the last category is listed with the others on purpose. In bronchitis treatment for smokers, it belongs in the same conversation.
Chronic bronchitis from smoking and the COPD question
At some point in a pattern of repeated bronchitis, a clinician will raise COPD. The term frightens people, so it helps to know what it does and does not mean.
COPD is an umbrella label for long-term airflow limitation that is not fully reversible. It covers chronic bronchitis, where the problem is inflamed, mucus-clogged airways, and emphysema, where the air sacs at the ends of those airways have lost their elastic walls. Many people have elements of both. The WHO reports that COPD is the third leading cause of death worldwide and that in high-income countries tobacco smoking accounts for over 70% of cases, with the remainder linked to indoor and outdoor air pollution, occupational dust and fumes, and rarer genetic causes.
The diagnosis rests on spirometry. A person blows as hard and as long as they can into a device, which records the total volume exhaled and the amount expelled in the first second. A reduced ratio between those two numbers, persisting after a bronchodilator, is the defining finding. Symptoms and history support the diagnosis but cannot make it alone, which is why a clinician who suspects chronic bronchitis will want the test rather than relying on how the cough sounds.
Receiving a COPD diagnosis changes the treatment framework from episode-by-episode to long-term management. The NHLBI describes the goals as relieving symptoms, slowing progression, preventing and treating exacerbations, and maintaining the ability to stay active. Stopping smoking is listed first because it is the only intervention shown to change the trajectory of lung function decline. Regular inhaled medicines, vaccination against influenza and pneumococcal disease, and pulmonary rehabilitation, a structured program of exercise and education, are the other pillars.
Staging, medication choices and monitoring intervals are individualized, and they sit with the treating team.
What are the first signs of lung damage from smoking, and how are they assessed?
People ask this hoping for a clear early warning. The uncomfortable truth is that the earliest damage is silent, and by the time symptoms appear, some airflow limitation is often already present. That is precisely why clinicians lean on testing rather than on how a person feels.
The changes that precede symptoms are microscopic: slowed cilia, enlarged mucus glands, thickening of the small airway walls, and low-grade inflammation. None of these can be felt. What people eventually notice is a shift in things they had normalized. A morning cough that becomes an all-day cough. Mucus that changes from occasional to daily. Breathlessness on a staircase that used to be effortless, often attributed to age or fitness. A chest infection each winter that takes longer to clear than the one before.
None of these is diagnostic on its own, and this is not a checklist to score yourself against. The pattern that matters to a clinician is change over time in someone with a significant smoking history, which is usually described in pack-years: the number of packs smoked per day multiplied by the number of years. A history of ten or more pack-years with a persistent cough is a common threshold for offering spirometry, though thresholds vary between guidelines.
The assessment itself is straightforward. Spirometry takes a few minutes. A pulse oximeter clipped to a fingertip estimates blood oxygen. A chest X-ray or CT scan may be arranged if the history or examination suggests something beyond bronchitis. Blood tests are occasionally used to look for the rare inherited enzyme deficiency that causes emphysema in young people or non-smokers.
Finding early change is not bad news in the way people fear. It is the point at which quitting produces the largest measurable difference, because the lung function that has not yet been lost is the lung function that can be protected.
What the next days and weeks usually look like
Timelines here are typical ranges drawn from mainstream guidance, not schedules, and smokers frequently sit at the longer end of each.
| Phase | What is common | What helps |
|---|---|---|
| Days 1–3 | Cold-like symptoms, sore throat, tiredness; cough begins and may be dry | Rest, fluids, warm drinks, avoiding smoke |
| Days 3–10 | Cough becomes the main symptom, often productive; chest may feel sore from coughing | Humidified air, continued fluids; medical review if fever persists or breathing worsens |
| Weeks 2–3 | Other symptoms resolve; cough eases for most (NHS: usually improves within about 3 weeks) | Patience; follow-up if no improvement |
| Weeks 3–8 | Lingering cough in some, longer in smokers (Mayo Clinic: cough may last several weeks) | Review if cough passes 3–4 weeks or changes character |
For someone who quits smoking during the illness, the recovery of the airway follows its own overlapping timeline. Within days, carbon monoxide levels in the blood normalize and oxygen delivery improves. Over the following weeks to months, cilia regrow and resume beating, which is when some people notice their cough temporarily loosen and produce more mucus. Mainstream quit-smoking guidance from the CDC describes coughing and shortness of breath decreasing over the first one to twelve months. These are population patterns, not individual guarantees.
For someone with chronic bronchitis or COPD having an exacerbation, the picture is different. Flare-ups often take longer to settle, a short medication course may be involved, and a follow-up appointment within a couple of weeks is common practice so the team can confirm recovery and review the long-term plan.
Two signals should move anyone off this table and back to the clinician: a cough that has not begun to improve by three weeks, or one that gets worse after initially getting better. Both are covered in the red-flag section below.
Can lungs heal after bronchitis if you stop smoking?
The word people reach for is healing, and it deserves a careful answer because the lung recovers unevenly: some parts remarkably, others not at all.
The airway lining recovers well. The cells damaged by an acute infection are replaced within weeks. Cilia that were slowed or destroyed by smoke regrow once exposure stops; this is a documented, repeatable finding and the reason the mucociliary escalator restarts in former smokers. Mucus gland enlargement reduces partially over months. Inflammation subsides. Someone who quits after years of smoking but before airflow limitation has developed can expect the airway to function close to normally over time.
The air sacs do not recover. Once the elastic walls of the alveoli have broken down, as in emphysema, they are not rebuilt. Lung function that has been lost to COPD is not regained, which is why the NHLBI frames COPD as manageable rather than reversible.
What quitting does change, even late, is the rate of further loss. Everyone loses a little lung function each year with age. Smokers with COPD lose it faster. Former smokers, across many long-term studies summarized in WHO and NIH guidance, return toward the slower age-related rate of decline. That is why clinicians say quitting is worthwhile at any stage: it does not restore what is gone, but it protects what remains, and what remains is often enough for a long, active life.
There is also a practical short-term benefit that matters for bronchitis specifically. Former smokers have fewer chest infections and recover from them faster, because the airway is clearing itself again. Fewer episodes means fewer chances for an acute problem to become a chronic one.
So: can lungs heal after bronchitis? The airway, largely yes. Established structural damage, no. The direction of travel, always.
Quitting support that the evidence actually backs
If quitting is part of bronchitis treatment for smokers, then the methods with the strongest evidence deserve the same plain description as the inhalers.
Behavioral support means structured help from a trained person, whether face to face, by phone or through a digital program. It covers identifying triggers, planning for cravings, and follow-up contact. On its own it improves quit rates modestly. Combined with medication, it roughly doubles the chance of success compared with willpower alone, a finding consistent across the systematic reviews that inform NHS and CDC guidance.
Nicotine replacement delivers nicotine without combustion products through patches, gum, lozenges, sprays or inhalators. The principle is to separate the chemical dependence from the ritual, treat the first with a steady supply, and unlearn the second. Products are often combined, a long-acting patch with a short-acting form for breakthrough cravings, but combinations and durations are for a pharmacist or clinician to advise.
Two prescription medicines act on the brain rather than replacing nicotine. One partially stimulates nicotine receptors while blocking cigarette nicotine from binding, reducing both craving and reward. The other affects neurotransmitters involved in mood and craving. Both have consistent trial evidence, both have side-effect profiles and interactions the prescriber will weigh, and neither is a decision to make from an article.
Electronic cigarettes are an area where evidence is still developing. Some national bodies, including the NHS, describe them as a less harmful option for adults who would otherwise continue smoking, while others, including the CDC, emphasize that they are not approved cessation products and that long-term effects are unknown. Presenting either view as settled would be inaccurate.
The strongest single predictor of success is not the method chosen but making a supported, planned attempt. Relapse is common and is treated as information, not failure. Many people quit for good on a later try.
What people often get wrong about bronchitis and smoking
Several beliefs circulate widely enough to shape how people behave during an episode, and most of them steer the wrong way.
“If it were serious, antibiotics would fix it.” Acute bronchitis is nearly always viral, and the CDC is unambiguous that antibiotics do not help it. Feeling better a few days into a course is the virus resolving on schedule. The seriousness of a chest illness is judged by breathing, oxygen and fever, not by whether a pill was prescribed.
“Cutting down is nearly as good as quitting.” Reducing cigarettes lowers exposure to some toxins, but the airway inflammation and ciliary paralysis that drive bronchitis persist with continued smoking at any level. Guidance from the WHO and NHS consistently identifies complete cessation as the intervention that changes the course of chronic bronchitis.
“Coughing more after quitting means it made things worse.” A temporarily looser, more productive cough in the weeks after stopping is a recognized pattern as cilia recover and begin moving accumulated mucus. It usually settles. A cough that worsens with fever, breathlessness or blood is a different matter and needs review.
“Bronchitis is just a bad cold.” An acute episode often follows a cold, but the inflammation sits lower, in the bronchi, and in smokers each episode adds to the cumulative picture that can become chronic bronchitis.
“Chronic bronchitis and emphysema are the same thing.” They are grouped under COPD but describe different damage: clogged, inflamed airways in one; destroyed air sacs in the other. The distinction affects treatment.
“Damage is done, so quitting is pointless.” This is the most consequential myth. Lost lung function is not regained, but the rate of further loss slows toward normal after quitting at any age, and infection frequency falls. The evidence base for late benefit is among the most robust in respiratory medicine.
Questions to ask your care team
A good appointment is a two-way exchange, and smokers sometimes hold back questions because they anticipate judgment. These are the ones worth asking anyway, roughly in the order they tend to come up.
- Is this acute bronchitis, an exacerbation of something chronic, or are you not sure yet? What would help you tell?
- Do I need a chest X-ray or a breathing test, and if not now, what would prompt one?
- Why are you recommending, or not recommending, an antibiotic in my case?
- If you are prescribing an inhaler, what is it doing, how will I know it is working, and when should I stop needing it?
- How long would you expect this cough to last for someone with my smoking history, and at what point should I come back?
- What specific signs should make me seek urgent care rather than wait for a routine appointment?
- Given my pack-years, do you think I already have some airflow limitation? Would you want to check?
- What quitting support is available through this practice, and which options fit with my other medicines and conditions?
- Is there a nurse, pharmacist or cessation adviser I can follow up with between doctor visits?
- Should I be vaccinated against influenza and pneumococcal disease this year, given my lungs?
- If I do quit and my cough changes, how do I tell recovery from a new problem?
Write the answers down or ask for them in the after-visit summary. Bronchitis treatment for smokers often spans several conversations, and the plan is easier to follow when the reasoning behind it is on paper. If a question is deferred, ask when it will be revisited. The decisions rest with your treating team, but the questions are yours to ask.
When to call your doctor
Most bronchitis is managed at home with a single visit or none. The following signs mean the picture may have moved beyond simple bronchitis and warrant prompt contact with a clinician, or emergency services where breathing is severely affected.
- Breathlessness at rest, difficulty speaking in full sentences, or lips or fingertips turning bluish or gray.
- Chest pain, particularly if it is sharp, worsens with breathing, or spreads to the arm, jaw or back.
- Fever above 100.4°F (38°C) that lasts more than three days, or any fever with shaking chills and rapid breathing.
- Coughing up blood, or mucus that is rust-colored, frankly bloody, or suddenly foul-smelling.
- A cough that has not started to improve after three weeks, or one that improves and then clearly worsens again.
- Confusion, drowsiness, or a heart rate that feels unusually fast or irregular.
- New swelling of the ankles or legs alongside breathlessness, which can point to the heart rather than the lungs.
- Unexplained weight loss, night sweats or persistent hoarseness accompanying a long-standing cough in a smoker.
People with a known diagnosis of COPD, heart failure, diabetes or a weakened immune system should have a lower threshold for calling, and many will have been given a written action plan describing exactly when to do so. Follow that plan over general advice.
Two further situations deserve a call even without drama. The first is a smoker whose everyday cough has changed in character over weeks, becoming more frequent, more productive or associated with new breathlessness on exertion, because that pattern is how chronic bronchitis is usually first recognized. The second is anyone who has decided to quit and wants help doing it: that is a medical conversation, not a confession, and clinicians consider it one of the most valuable calls they receive.
When in doubt, call. A clinician would rather assess ten people who turned out to be fine than miss one who was not.
Frequently asked questions
Does smokers bronchitis go away?
An acute episode of bronchitis usually resolves on its own even in a smoker, because the underlying viral infection runs its course, though the cough often lingers for several weeks. Chronic bronchitis, defined by a productive cough lasting at least three months a year for two consecutive years, does not go away while smoking continues. It can be managed, and stopping smoking is the step most likely to slow its progression.
What clears up bronchitis fast?
Nothing reliably shortens a viral bronchitis; treatments make the illness more comfortable and prevent complications. Fluids, warm drinks, humidified air and rest help thin mucus so the airway can clear it. Antibiotics do not speed recovery from acute bronchitis according to CDC guidance. Removing smoke from the airway is the one measure that directly helps the lung’s own clearing system, the cilia, restart their work.
What are the first signs of lung damage from smoking?
The earliest damage from smoking is silent and microscopic, which is why clinicians rely on a breathing test called spirometry rather than symptoms alone. Changes people eventually notice tend to be gradual: a morning cough that spreads through the day, more frequent mucus, breathlessness on stairs that used to be easy, and chest infections that take longer to clear. These patterns warrant assessment rather than self-diagnosis.
Can your lungs heal from bronchitis?
The airway lining recovers well after bronchitis, and cilia damaged by smoke regrow over weeks to months once exposure stops. Structural damage to the air sacs, as in emphysema, does not reverse, and lung function already lost to COPD is not regained. Quitting smoking at any stage slows the rate of further decline toward the normal age-related pace and reduces how often chest infections occur.
Do smokers need antibiotics for bronchitis?
Usually not. Acute bronchitis is almost always viral, and antibiotics have no effect on viruses; the CDC advises against them for otherwise healthy people regardless of smoking status. Antibiotics may be considered when someone with established chronic bronchitis or COPD has a flare-up with signs of bacterial involvement, or when pneumonia is suspected. That judgment rests with the examining clinician, not with how severe the cough feels.
Why does my cough get worse after I quit smoking?
A temporarily looser, more productive cough in the first weeks after quitting is a recognized pattern. As cilia recover and resume beating, they begin moving mucus that had accumulated while they were paralyzed by smoke. This usually settles over weeks to months. A worsening cough accompanied by fever, breathlessness, chest pain or blood is not part of that pattern and should be reviewed by a clinician promptly.
How is chronic bronchitis from smoking diagnosed?
Chronic bronchitis is diagnosed from the history, a productive cough on most days for at least three months in two consecutive years, combined with spirometry. Spirometry measures how much air you can exhale and how quickly, and a persistently reduced ratio after a bronchodilator confirms the airflow limitation that defines COPD. Chest imaging and oxygen measurement may be added. Symptoms alone cannot make the diagnosis.
Is it too late to quit if I already have chronic bronchitis?
No. Lung function already lost is not regained, but every major guideline identifies stopping smoking as the single most effective intervention for slowing further decline in COPD, at any age and any stage. Former smokers also have fewer and shorter chest infections. Clinicians consider a late quit attempt one of the most worthwhile steps a person with chronic bronchitis can take, and support is available through primary care.
What is the difference between smokers cough and bronchitis?
A habitual smoker’s cough is stable over months or years, usually worst in the morning with modest clear or pale mucus, and reflects ongoing irritation. Acute bronchitis arrives with a cold-like illness and a cough that becomes the dominant symptom before settling within about three weeks. Chronic bronchitis is the long-term form, diagnosed by duration and spirometry. Clinicians distinguish them mainly by asking how the pattern has changed.
Should I use an inhaler for bronchitis if I smoke?
Inhaled bronchodilators relax the muscle around the airways and may be offered when wheeze or breathlessness accompanies bronchitis, or as regular treatment in chronic bronchitis and COPD. They do not treat the infection itself and are not routinely needed in uncomplicated acute bronchitis. Whether an inhaler is appropriate, which type, and for how long are decisions for the prescribing clinician after examining you.
References
- Chronic Bronchitis (MedlinePlus)
- Bronchitis (NHS)
- Chronic obstructive pulmonary disease (COPD) fact sheet (WHO)
- COPD (NIH National Heart, Lung, and Blood Institute)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Preparing for a Pulmonology Consultation: Scans, Breathing Tests and Records to Bring
To prepare for a pulmonology appointment, gather your actual chest X-ray and CT images (not only the written reports), any previous spirometry or lung…

What Does Daily Cystic Fibrosis Treatment Involve? Airway Clearance, Inhalers and Nutrition
Daily cystic fibrosis treatment usually combines airway clearance to loosen and cough out thick mucus, inhaled medicines that open the airways, thin secretions or…

Is It Bacterial or Viral Pneumonia? How the Cause Changes Your Treatment Plan
Bacterial and viral pneumonia are treated differently because the cause decides which medicines can help. Bacterial pneumonia is usually treated with antibiotics chosen by…

Lung Abscess After Aspiration: Why Swallowing Problems Matter in Your Treatment Plan
A lung abscess after aspiration is a pus-filled cavity that forms when food, saliva or stomach contents slip into the lungs and infection destroys…

Does Every Pleural Effusion Need Draining? When Doctors Treat the Cause Instead
No. Most pleural effusions are treated by addressing what caused them, such as heart failure, pneumonia or low protein, and the fluid clears as…

Recovering From a Mediastinoscopy: Neck Soreness, Wound Care and When to Resume Lifting
Most people go home the same day or the morning after a mediastinoscopy and feel close to normal within a few days. Neck soreness…