

Does SMR Help Snoring and Nasal Obstruction? What Results Submucous Resection Can Bring

Key Takeaways
- SMR (submucous resection) is an operation on the nasal septum or turbinates that treats nasal obstruction; it is not, by itself, an operation on the throat where most snoring is generated.
- Nasal blockage contributes to snoring mainly by forcing mouth breathing, which drops the jaw and narrows the space behind the tongue, so people whose snoring worsens with congestion are the most likely to benefit.
- Systematic reviews consistently find that nasal surgery alone produces small and inconsistent changes in sleep apnea severity, so a sleep study usually comes before SMR when apnea is suspected.
- The clearest role of nasal surgery in sleep medicine is as an enabler: an open nose makes CPAP and mandibular advancement devices easier to tolerate.
- The Mayo Clinic advises that nasal tissues stabilize over 3 to 6 months after septal surgery, which is the realistic point to judge the effect on snoring rather than the first few weeks.
- Classic resection removes more cartilage than modern cartilage-preserving septoplasty, and the gentler approach carries a lower risk of septal perforation and changes to nasal shape.
SMR (submucous resection) straightens a deviated nasal septum or reduces swollen turbinates to improve airflow through the nose. It reliably treats nasal obstruction, but its effect on snoring is less predictable: most snoring is generated in the throat, so SMR helps most when a blocked nose is forcing mouth breathing. It is not a stand-alone treatment for sleep apnea, and an ENT assessment decides whether it is suitable.
The spare room has a name in some households. Nobody chose it; it just became the place one partner retreats to at two in the morning, pillow under one arm, after the snoring reached a pitch that no earplug could soften. Then, at a routine appointment, an ear, nose and throat specialist mentions a deviated septum and an operation called SMR, and a very specific hope takes hold: fix the nose, fix the noise, reclaim the bed.
It is a reasonable hope, and sometimes it is rewarded. Yet the question does SMR help snoring has a more layered answer than most clinic leaflets admit, because the nose and the snore are neighbors rather than the same problem. This explainer walks through what submucous resection actually does, what the evidence supports, where it tends to disappoint, and what the first weeks afterward usually look like.
Every decision described here belongs to you and your treating team. Our aim is simply to make that conversation sharper.
Does SMR help snoring? The honest short version
Start with the distinction that matters most. Nasal obstruction is a plumbing problem: air struggles to get in. Snoring is an acoustics problem: soft tissue in the throat, usually the soft palate, uvula, tongue base or side walls of the pharynx, vibrates as air rushes past. SMR (submucous resection) works on the plumbing. Whether it quiets the acoustics depends on how much the blocked nose was contributing in the first place.
A severely deviated septum (the wall of cartilage and bone dividing the two nostrils, bent far enough to narrow one or both passages) can push someone toward mouth breathing at night. Mouth breathing drops the jaw, pulls the tongue back and lets the throat collapse more easily, which is why nasal congestion is listed among recognized contributors to snoring by the NHS and the Mayo Clinic. Restore nasal airflow and that chain of events can loosen.
What the evidence does not show is that nasal surgery alone switches snoring off in most people. Studies of nasal procedures report consistent improvement in nasal breathing and in how people rate their sleep quality, while objective measures of snoring and breathing pauses change far less reliably. In plain terms: expect to breathe better, hope to snore less, and do not plan a celebration around silence.
Ear, nose and throat specialists therefore tend to frame SMR as a treatment for nasal obstruction that may improve snoring, rather than a snoring operation. If a clinician has suggested it to you, the most useful question to ask is which problem they are primarily aiming to solve. The answer shapes everything that follows, from realistic expectations to how success will be judged afterward.
What is submucous resection, and how is it different from septoplasty?
The term causes real confusion, partly because it is used for two different operations. The classic SMR is submucous resection of the septum: the surgeon lifts the mucosa (the moist lining of the nose) away from the septum, removes the deviated portions of cartilage and bone from underneath, and lays the lining back down. The septum stays in place as a lining-covered partition, minus the bent sections.
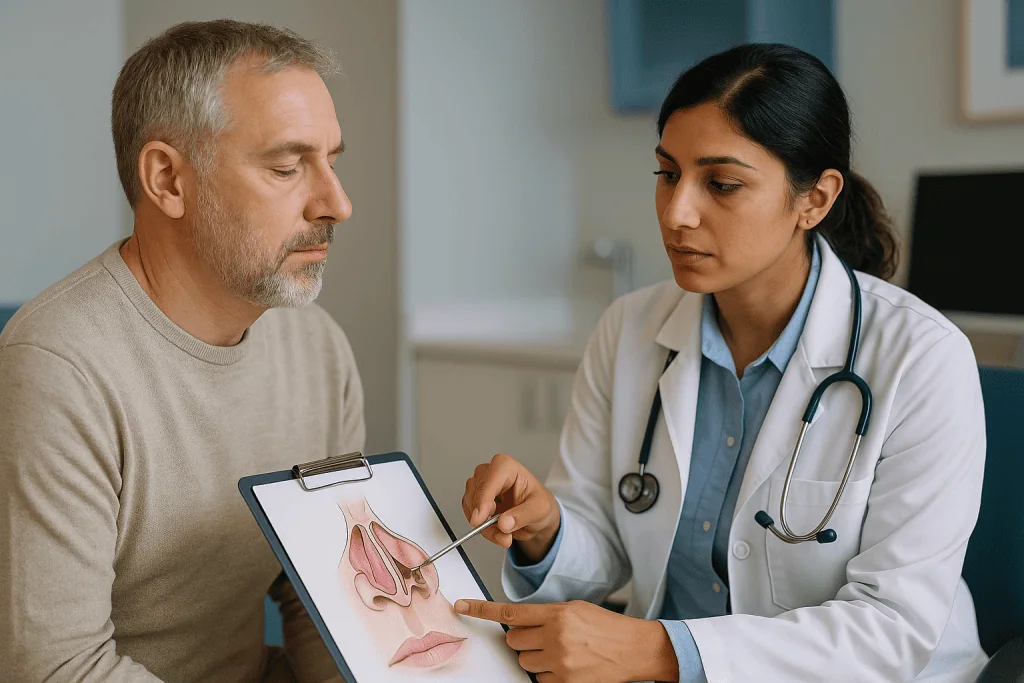
Septoplasty is the more modern, tissue-preserving relative. Instead of removing large sections, the surgeon reshapes, repositions or trims only what is needed and keeps most of the cartilage framework. The Mayo Clinic describes septoplasty as straightening the septum by trimming, repositioning and replacing cartilage or bone. In many hospitals, “SMR” on a consent form now means an operation closer to septoplasty, and surgeons choose between the two according to how the septum is deformed.
The second use of the term is submucous resection of the inferior turbinates. Turbinates are shelf-like structures on the side wall of each nasal passage that warm and humidify air; when they swell chronically, from allergy or long-standing rhinitis, they can block the nose as effectively as a deviated septum. Turbinate SMR removes tissue beneath the lining to shrink them while sparing the surface that does the humidifying work.
Why does the distinction matter for snoring? Because the right operation depends on where the blockage sits. A straight septum with swollen turbinates will not improve with septal surgery, and vice versa. Many patients have both problems and have both addressed in one session. Clinicians use an endoscope (a thin camera passed into the nose) and sometimes a CT scan to map this before anything is planned, and a careful map is a better predictor of a good outcome than any single technique.
Why a blocked nose makes some people snore
Picture the upper airway as a length of soft hose connected to a rigid pipe. The nose is the rigid pipe; the throat is the hose. If the pipe is partly obstructed, the chest has to pull harder to draw the same volume of air, which creates stronger negative pressure inside the hose downstream. Negative pressure in a collapsible tube does exactly what you would expect: it sucks the walls inward. The soft palate flutters, the tongue base drifts back, and the sound of snoring is produced.
Nasal obstruction feeds this in a second way. When the nose will not deliver enough air, people open their mouths during sleep. Mouth breathing rotates the lower jaw backward and downward, narrowing the space behind the tongue. The Mayo Clinic lists noisy breathing during sleep and a preference for sleeping on a particular side among the signs of a deviated septum, and the NHS counts a blocked nose, alongside weight, alcohol and sleeping position, among the things that make snoring more likely.
There is also a reflex component that is less obvious. Receptors in the nasal lining appear to help regulate breathing rhythm and muscle tone in the upper airway; bypassing the nose removes that input. Evidence here is less settled than the mechanical story, but it is one reason some people notice their sleep feels lighter when their nose is blocked by a cold even before any snoring begins.
All of this explains why fixing the nose can help, and also why it often is not enough. If the hose would collapse anyway because of its own shape, muscle tone or surrounding tissue, clearing the pipe improves the pressure situation without removing the underlying tendency. The nose is a contributor, sometimes a major one, rarely the whole story.
What actually happens during the operation
SMR is typically performed under general anesthesia, although some surgeons offer local anesthesia with sedation for straightforward cases, according to MedlinePlus and the Mayo Clinic. The operation takes place entirely inside the nostrils, so there are no external cuts and no change to the outward shape of the nose unless a combined procedure has been planned.
The surgeon makes a small incision in the lining on one side of the septum, lifts the mucosa off the cartilage and bone, and either removes the deviated segments or reshapes them, depending on whether the plan is a classic resection or a septoplasty. Where turbinates are being reduced, tissue is removed or shrunk from beneath their surface using instruments, a microdebrider or an energy device; the technique varies between surgeons and is a reasonable thing to ask about.
At the end, the lining is laid back and held with dissolvable stitches. Many surgeons place thin silicone splints inside the nose for a few days to keep the septum stable while it heals; some use soft packing instead, and some use neither. The Mayo Clinic notes that splints or packing, when used, are usually removed within days to about a week.
Most people go home the same day. The first sensation on waking is usually a very blocked nose, which can feel disheartening for an operation meant to relieve blockage; this is swelling and dried blood, not failure. Breathing through the nose commonly improves as swelling settles over the following weeks, and the Mayo Clinic advises that nasal tissues continue to settle for 3 to 6 months, occasionally longer. The surgeon’s notes will record exactly what was done, and it is worth asking for a plain-language summary, because that record becomes useful if snoring persists and the next step needs planning.
Who SMR is usually for, and who is usually asked to wait
The clearest candidates are adults with a documented structural blockage, a septal deviation or turbinate enlargement seen on examination, whose symptoms match that finding: persistent nasal obstruction, often worse on one side, recurrent sinus infections linked to poor drainage, or difficulty tolerating a CPAP mask because air cannot pass through the nose. Snoring that improves noticeably whenever the nose happens to be clearer, for example after a course of nasal steroid spray, is a helpful clue that the nose is contributing.
Clinicians usually ask people to try non-surgical measures first. For turbinate swelling driven by allergy, intranasal corticosteroid sprays and antihistamines reduce inflammation over weeks, and the response, or lack of it, tells the surgeon something useful. A septum cannot be straightened with medication, but even here a trial of sprays helps separate structural blockage from swelling before anyone commits to an operation. Decisions about starting or stopping any of these medicines rest with the prescribing clinician.
Who tends to wait or be steered elsewhere?
- Children and teenagers, because the septum is still growing; surgeons generally defer unless obstruction is severe.
- People whose snoring comes with witnessed breathing pauses, gasping or heavy daytime sleepiness, who need a sleep study first because obstructive sleep apnea changes the treatment plan.
- Anyone with active sinus infection, uncontrolled allergy or recent nasal trauma, where swelling would confuse the picture.
- Smokers and people with poorly controlled diabetes or bleeding disorders, where healing and bleeding risk are higher; these are addressed before surgery, not ignored.
None of these are permanent barriers. They are reasons to sequence care sensibly, and the treating team will weigh them against how much the obstruction is affecting daily life.
Deviated septum snoring: does straightening the septum stop the noise?
Here is where honesty earns its keep. Surgeons have studied this question for decades, and the pattern across the literature is remarkably consistent: people breathe better through the nose after septal surgery, they frequently report that their sleep feels more restful, and bed partners often say the snoring is softer or less frequent. Those are real, meaningful outcomes.
What is harder to find is reliable evidence that septal surgery alone eliminates snoring, or that objective recordings of snoring sound change as much as the subjective reports suggest. Part of this is measurement: snoring is notoriously variable night to night, and the partner’s perception shifts as their own sleep improves. Part of it is anatomy. In many people with a deviated septum, the vibrating tissue is the soft palate, and the palate does not change shape because the septum did.
Who tends to do well? Broadly, people whose snoring is tied to a blocked nose: those who snore more during hay fever season or head colds, who notice they wake with a dry mouth from breathing through it, or whose snoring eased during a trial of nasal sprays. People who snore just as loudly with a perfectly clear nose are less likely to notice a difference from nasal surgery alone, and an experienced ENT will often say so before the operation rather than after.
The practical takeaway is to treat SMR as one component in a layered approach. A straight septum improves the odds that other measures, such as side sleeping, weight management, an oral appliance or CPAP, will work comfortably. It also removes a variable, which makes any residual snoring easier to diagnose. For some, that is enough; for others, it is step one.
Nasal surgery and sleep apnea: what the evidence actually shows
Obstructive sleep apnea (OSA) is the condition in which the throat repeatedly closes during sleep, causing pauses in breathing, drops in oxygen and fragmented rest. The NHS describes the warning signs as loud snoring, gasping, snorting or choking noises, frequent waking and feeling very tired during the day. It is not simply loud snoring, and it carries health consequences that snoring alone does not.
The evidence on nasal surgery for OSA points in one direction. Operations on the septum and turbinates improve nasal breathing and tend to improve daytime sleepiness scores and quality of life, but they produce small and inconsistent changes in the apnea-hypopnea index, the count of breathing events per hour used to grade severity. Systematic reviews repeatedly conclude that nasal surgery alone should not be relied on to treat OSA.
Where it earns a clear place is as an enabler. CPAP (continuous positive airway pressure, a mask that splints the airway open with gently pressurized air) is the standard treatment for moderate and severe OSA according to the NHS, and it depends on air passing through the nose. People with a blocked nose often struggle with the mask, need higher pressures, or abandon treatment. Clearing the nasal passage can make CPAP tolerable and sometimes allows lower pressures. The same logic applies to mandibular advancement devices, the mouthguard-like appliances that hold the lower jaw forward; they work best when the nose is open enough for the lips to stay closed.
This is why a sleep study usually comes before, not after, nasal surgery in anyone with apnea symptoms. If OSA is present, the plan will generally pair SMR with a definitive airway treatment rather than offer it as a substitute. If the study shows simple snoring without apnea, the stakes are lower and the decision becomes more about comfort and quality of life.
SMR, septoplasty, turbinate reduction and the alternatives at a glance
Patients frequently ask how the options line up against one another. The table below summarizes what each is designed to do and what it does not do, drawing on descriptions from the NHS, Mayo Clinic and Cleveland Clinic. It is a map, not a recommendation; the right combination depends on individual findings.
| Option | What it targets | Typical effect on snoring | What it does not do |
|---|---|---|---|
| SMR of the septum / septoplasty | Bent cartilage and bone narrowing the nasal passage | May reduce snoring when nasal blockage drives mouth breathing | Does not change the throat; not a treatment for OSA on its own |
| Turbinate reduction | Chronically swollen turbinates, often from rhinitis | Similar: helps if congestion is the driver | Does not treat allergy itself; swelling can return |
| Nasal steroid sprays | Inflammatory swelling of the lining | Modest, for congestion-related snoring; weeks to take effect | Cannot straighten a septum |
| Side sleeping and weight management | Tongue position and tissue around the airway | First-line for simple snoring per NHS | Requires sustained effort; no effect on a structural nasal block |
| Mandibular advancement device | Collapse behind the tongue | Established option for snoring and mild OSA | Needs good dental health and an open nose to work comfortably |
| CPAP | Airway collapse at any level | Standard treatment for moderate to severe OSA | Depends on nasal airflow; blocked nose reduces tolerance |
| Palate or throat surgery | Vibrating or collapsing soft tissue in the pharynx | Variable; considered after other options | Does not help nasal obstruction |
Two patterns stand out. Nasal procedures sit on the left of the airway, throat procedures and devices on the right, and most durable results come from matching the intervention to where the problem lives. Second, the nose operations are the ones most likely to make the other treatments work better, which is the strongest argument for them in someone who both snores and cannot breathe through the nose.
SMR nose surgery recovery: what the first days and weeks usually look like
The first 48 hours are about swelling, oozing and sleeping propped up. Expect a blocked nose, mild bloody discharge onto a gauze pad under the nostrils, a dull headache and some tooth or upper-lip numbness; MedlinePlus and the Mayo Clinic describe all of these as normal. Pain is usually moderate and managed with medicines the surgical team prescribes, and the team will advise which over-the-counter products to avoid because of bleeding risk.
Splints, if used, come out at a clinic visit within the first week, and most people notice an immediate sense of relief when they do. Return to desk work or study typically happens within about a week, per MedlinePlus, although fatigue can linger. Surgeons generally ask people to avoid nose blowing, strenuous exercise, heavy lifting and bending for several weeks, to sneeze with the mouth open, and to use saline rinses to keep crusts soft. The Cleveland Clinic and Mayo Clinic both describe these restrictions as lasting a few weeks, with the exact timing set by the operating surgeon.
Weeks two to six are when nasal breathing starts to feel genuinely better as internal swelling recedes. This is also when people first form an opinion about snoring, and the honest advice is to withhold judgment: the lining is still swollen, and residual congestion can mask the eventual result. Bed partners sometimes report an early improvement simply because mouth breathing has stopped.
The Mayo Clinic notes that nasal tissues are relatively stable by 3 to 6 months and may continue shifting for up to a year. That is the realistic point at which to assess the snoring outcome and decide, with the care team, whether anything further is needed. If a sleep study was done beforehand, repeating it after full healing gives an objective comparison.
What are the risks of submucous resection?
SMR is a routine operation with a long safety record, and most people recover without incident. Routine is not the same as risk-free, and a candid list helps decisions more than reassurance does.
- Bleeding. Minor oozing for a few days is expected; heavier bleeding that needs packing or a return to hospital is uncommon but recognized by MedlinePlus and the Mayo Clinic.
- Infection. Unusual inside the nose, but possible; it presents as worsening pain, fever or foul discharge.
- Septal perforation. A hole through the septum where the lining on both sides fails to heal. It can cause whistling, crusting or nosebleeds, and is more of a concern with the classic resection than with cartilage-sparing septoplasty, which is one reason surgeons now remove less.
- Persistent or recurrent obstruction. Scar tissue, residual deviation or turbinate regrowth can leave the nose blocked, occasionally requiring revision.
- Change in nasal shape. Removing too much supporting cartilage can, rarely, cause the bridge to sag or the tip to drop; preserving structure guards against this.
- Altered sense of smell or numbness. Usually temporary, occasionally lasting.
- Empty nose sensation. After aggressive turbinate removal, a small number of people feel paradoxically blocked despite wide passages. Conservative, lining-sparing techniques reduce this risk.
- Anesthetic risks. Low for healthy adults; discussed individually by the anesthesia team.
Then there is the risk that is not a complication at all: the operation goes perfectly, the nose breathes beautifully, and the snoring carries on because it was coming from the throat. It is worth naming this openly during consent, because disappointment is lower when expectations were accurate. Ask the surgeon how they would judge the operation a success, and make sure you agree on that definition before the day.
Septoplasty for snoring compared with the non-surgical options
Before any operation, the NHS recommends a set of self-help steps for snoring that are unglamorous and surprisingly effective for many: lose weight if overweight, sleep on your side, avoid alcohol in the hours before bed, stop smoking, and treat nasal congestion. Alcohol relaxes throat muscles, extra tissue around the neck narrows the airway, and lying on the back lets the tongue fall backward; each of these acts on the throat, where most snoring originates.
Positional therapy deserves a specific mention. Simple approaches, from a pillow arrangement to a wearable that vibrates when you roll onto your back, help the subset of people whose snoring is markedly worse supine. It costs nothing to test with a partner’s observations over a week or two.
Mandibular advancement devices hold the lower jaw forward during sleep and are a recognized option for snoring and mild sleep apnea, according to the NHS. A custom-fitted device from a dentist with sleep training generally fits better than a boil-and-bite product, and people with loose teeth, gum disease or jaw joint problems may be advised against them.
Where does septoplasty fit? It is the right tool when the examination shows a structural block and the symptoms match. It is the wrong tool for snoring with a clear nose. For the many people in between, the sensible sequence is often: treat congestion medically, adopt the lifestyle measures, get a sleep study if apnea is suspected, and then consider SMR either to relieve obstruction in its own right or to make a device or CPAP workable. This sequencing is not caution for its own sake; it is how clinicians avoid operating on the wrong problem.
What people often get wrong about SMR and snoring
“Can snoring be stopped completely?” Not reliably, and not by any single treatment. Snoring sits on a spectrum, varies with weight, alcohol, sleep position and head colds, and can return years after a successful intervention. The realistic goal is to reduce it enough that both people sleep, and to rule out or treat sleep apnea. Anyone promising total silence is selling something.
“Does Vicks vapor rub help stop snoring?” Menthol and camphor create a cooling sensation that makes the nose feel more open, but they do not measurably widen the airway, and there is no good evidence they reduce snoring. For congestion-related snoring, saline rinses and clinician-advised nasal sprays have a stronger rationale. Vapor rubs should never be put inside the nostrils.
“Can air purifiers help with snoring?” Indirectly, perhaps, for people whose congestion is driven by indoor allergens such as dust mite or pet dander; fewer triggers can mean less turbinate swelling. There is no evidence that a purifier affects snoring in someone without allergic rhinitis.
“What is the best sound to block snoring?” This is a question about the partner’s sleep, not the snorer’s airway. Steady broadband noise, such as a fan or white-noise app, masks the irregular peaks of snoring better than music, and earplugs rated for sleep add a further layer. Masking is a coping strategy, not a treatment, and it should not postpone an assessment if apnea signs are present.
“Loud snoring means severe apnea.” Volume correlates poorly with breathing pauses. Quiet snorers can have significant OSA; thunderous ones can have none. Only a sleep study tells the difference.
“Once the septum is fixed, the job is done.” For nasal obstruction, often yes. For snoring, the nose is one stop on a longer route, and the best results come when the care team plans the whole journey.
Questions to ask your care team before agreeing to SMR
A good consultation is a two-way exchange, and surgeons generally welcome specific questions because they signal realistic expectations. These are the ones that tend to change decisions.
- What exactly did you find on examination, and is the blockage from the septum, the turbinates, or both?
- Is the primary goal of this operation to relieve my nasal obstruction, to reduce snoring, or to make another treatment such as CPAP workable?
- Based on my examination, how likely is it that my snoring is coming from the nose rather than the throat?
- Should I have a sleep study first? If apnea is found, how would that change the plan?
- Will you be doing a classic submucous resection, a cartilage-preserving septoplasty, or a turbinate procedure, and why that choice for me?
- Will you use splints or packing, and when would they come out?
- What non-surgical measures should I try or continue beforehand, and for how long?
- Which of my current medicines or supplements need to be reviewed before surgery?
- What would make you consider the operation a success, and when would we judge that?
- If the snoring persists after full healing, what would the next step be?
- What symptoms after surgery should prompt me to call rather than wait for follow-up?
Take notes, or bring someone who will. It also helps to keep a simple snoring diary for a couple of weeks before the appointment: which nights were worse, what preceded them, whether a blocked nose coincided. Patterns that are obvious on paper are easy to miss from memory, and they give the surgeon evidence to work with rather than an impression. The decision at the end of this conversation belongs with you and the team, informed by what the examination and any sleep study show.
When to call your doctor
Two sets of warning signs matter here: those before any surgery that point to sleep apnea, and those after SMR that indicate a complication.
Before surgery, arrange an assessment promptly if snoring comes with: witnessed pauses in breathing, gasping or choking during sleep, waking repeatedly through the night, severe daytime sleepiness, especially if it affects driving, morning headaches, or high blood pressure that is difficult to control. The NHS lists these as features of sleep apnea, which needs its own diagnosis and treatment rather than a nasal operation alone. Falling asleep at the wheel or in conversation warrants urgent attention.
After surgery, contact the surgical team or seek emergency care the same day for:
- Bleeding that soaks through dressings repeatedly, runs steadily down the throat, or does not slow with firm pressure and sitting upright.
- Fever, increasing facial pain, spreading redness or foul-smelling discharge, which may signal infection.
- Severe headache with a stiff neck, confusion or vision change.
- Clear, watery fluid dripping from one nostril that worsens when leaning forward, which can rarely indicate a leak of cerebrospinal fluid.
- Breathing difficulty, chest pain, calf swelling or fainting.
- A splint that has shifted and cannot be left comfortably in place.
Less urgent but still worth a call: a nose that remains completely blocked beyond the timeframe the surgeon described, a whistling sound on breathing, persistent numbness of the front teeth, or any visible change in the shape of the nose. None of these should be managed by waiting for the routine follow-up if they are worrying you. The team that operated holds the full picture, and a quick phone call is almost always the right first step.
Frequently asked questions
Does SMR help snoring if my septum is only slightly deviated?
Usually not much. Minor deviations are extremely common and often cause no obstruction at all, so straightening them rarely changes airflow enough to affect snoring. Surgeons generally reserve SMR for deviations that visibly narrow the passage and match the symptoms. If your nose feels clear, the snoring is far more likely to originate in the throat, and other measures will be more useful.
Is septoplasty for snoring the same as SMR?
They are close relatives. Classic SMR removes the deviated cartilage and bone from under the nasal lining; septoplasty reshapes and repositions while preserving most of the framework. Many surgeons use the terms loosely, and the actual technique is tailored to how the septum is bent. Ask which approach is planned for you and why, since the more conservative version carries lower risk of perforation.
Can deviated septum snoring go away without surgery?
Sometimes, if the obstruction is mostly swelling rather than structure. Nasal steroid sprays, allergy control, saline rinses and side sleeping can reduce congestion enough to restore nasal breathing in some people. A bent septum itself does not straighten with medication, but a trial of these measures helps clarify how much of the problem is structural before anyone considers an operation.
Will nasal surgery treat my sleep apnea?
On its own, usually not. Studies show nasal surgery improves nasal breathing and daytime sleepiness scores but produces only small, inconsistent changes in the number of breathing pauses per hour. Its main value in sleep apnea is making CPAP or an oral appliance tolerable. Anyone with apnea symptoms should have a sleep study before deciding on SMR so the full plan can be made together.
How long is SMR nose surgery recovery?
Most people return to desk work within about a week, according to MedlinePlus, while splints, if used, come out within days. Strenuous activity and nose blowing are restricted for several weeks. The Mayo Clinic notes that nasal tissues continue settling for 3 to 6 months, so judgments about breathing and snoring are best made after that, not during the swollen early phase.
Does Vicks vapor rub help stop snoring?
There is no good evidence that it does. Menthol creates a cooling sensation that makes the nose feel clearer without measurably widening the airway, and it has no effect on the throat tissues that vibrate during snoring. It should never be applied inside the nostrils. If congestion is driving your snoring, saline rinses and clinician-advised sprays have a stronger rationale.
Can air purifiers help with snoring?
Only indirectly, and only for some people. If indoor allergens such as dust mites or pet dander trigger nasal swelling, reducing them may ease congestion and the mouth breathing that follows. In someone without allergic rhinitis, a purifier has no plausible effect on snoring. It is a reasonable comfort measure, not a treatment, and it should not delay assessment if apnea signs are present.
Can snoring be stopped completely?
Not reliably by any single treatment. Snoring varies with weight, alcohol, sleep position, colds and age, and it can return after a good result. The realistic aim is to reduce it enough that both partners sleep well and to identify or treat sleep apnea if present. Combining nasal treatment, lifestyle changes and, where needed, a device gives the best chance of a lasting improvement.
What is the best sound to block snoring for a partner?
Steady broadband sound such as a fan or white-noise app masks snoring better than music because it covers the irregular peaks rather than competing with them. Sleep-rated earplugs add further protection. Masking helps the listener cope but does nothing for the snorer’s airway, so it should sit alongside, not instead of, a medical assessment if gasping or breathing pauses are noticed.
What happens if I still snore after SMR?
It usually means the main source was the throat rather than the nose, which the operation was never designed to change. The good news is that an open nose makes other options, including side-sleeping strategies, mandibular advancement devices and CPAP, easier to use. Your care team may suggest a sleep study after full healing to pinpoint where the airway narrows and plan the next step.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Long Does Adenoid Surgery Recovery Take in Children? Discomfort, Bad Breath and Swimming
Most children recover from adenoid surgery within about one to two weeks, with the first few days being the most uncomfortable. A sore throat,…

Does Septoplasty Improve Breathing? Realistic Results and How Long Full Benefit Takes
Septoplasty straightens a crooked nasal septum, and for people whose blockage comes mainly from that deviation, breathing through the nose usually improves once swelling…

Why Does Untreated Sleep Apnea Strain the Heart, and How Does Treatment Aim to Reduce Risk?
Untreated sleep apnea strains the heart because each pause in breathing drops blood oxygen, triggers a stress-hormone surge and spikes blood pressure, many times…

Preparing for SMR: Blood Thinners, Smoking and Fasting Before Submucous Resection
Preparing for submucous resection usually means three things in the weeks before surgery: telling your team about every blood thinner, painkiller and supplement you…

CPAP or ENT Surgery for Sleep Apnea: How Do Specialists Decide Which Path Fits Your Airway?
Specialists usually offer CPAP first for moderate or severe obstructive sleep apnea because it supports every level of the airway at once and carries…

Cochlear Implant Evaluation: What Do the Hearing Tests, Speech Assessment and Imaging Decide?
A cochlear implant evaluation combines three strands of evidence. Hearing tests measure how much sound the inner ear still detects; speech assessment, done with…