

How Aesthetic Dentistry Is Planned: Smile Assessment, Imaging and Treating Decay First

Key Takeaways
- Cosmetic materials bond to healthy enamel, so active decay and gum disease are treated and stabilized before whitening, bonding or veneers are planned.
- Bitewing X-rays are the main way decay between teeth is found, and periapical films show root infection and bone support that determine whether a tooth can carry a veneer.
- Early enamel decay that has not broken the surface can be halted and often reversed with fluoride and habit change, preserving enamel for later bonding.
- Veneers require irreversible enamel removal, which is why dentists usually offer whitening, orthodontics or bonding first when they can achieve the same goal.
- No major guideline publishes a 3-3-3 rule; mainstream advice is twice-daily brushing with fluoride toothpaste, daily cleaning between teeth and fewer sugar exposures.
- Recall intervals after cosmetic work are set by individual risk, from about three months to two years under NHS guidance, because gum inflammation at margins shortens the life of restorations.
Aesthetic dentistry treatment planning follows a fixed order: first a full smile assessment of the teeth, gums, bite and facial proportions; then imaging such as X-rays, photographs and digital scans; then treatment of any active decay or gum disease before cosmetic steps such as whitening, bonding or veneers are considered. Disease control comes first because cosmetic work placed over untreated problems tends to fail early. Your dentist decides the sequence with you.
She had already chosen the shade. Sitting in the chair with a phone full of screenshots, she wanted to talk about veneers on the front six teeth and nothing else. The dentist listened, then gently turned the monitor toward her: two small shadows between the molars on the X-ray, and a gumline that bled when touched. The veneer conversation would happen, but not today.
That small redirect is the heart of aesthetic dentistry treatment planning. Cosmetic results that last are built the way a house is built, foundations before paint. The foundation in dentistry is healthy enamel, calm gums and a bite that spreads force evenly. The paint is the shade, the shape, the edge that catches the light in a photograph.
This article walks through how a careful dentist plans a smile: what the assessment looks for, which images are taken and why, and the reasons decay and gum disease are treated before any cosmetic step begins.
What does aesthetic dentistry treatment planning actually involve?
Planning is a series of decisions made in a deliberate order, not a single appointment. A dentist first gathers information: a medical and dental history, an examination of every tooth and the gums, a look at how the upper and lower teeth meet (the bite, or occlusion), and a set of images. Only then does the conversation turn to what the person wants their smile to look like.
The reason for that order is practical. Cosmetic materials such as porcelain and composite resin (a tooth-colored plastic filled with glass particles) bond to enamel. They do not bond well to softened, decayed tooth structure, and they cannot stop a cavity that is already growing underneath. Mayo Clinic describes cavities as permanently damaged areas that develop into holes; once a hole is present the only route is to remove the decay and restore the tooth. A veneer placed over that hole would be a lid on a problem, not a solution.
So planning moves in stages. Urgent pain or infection is dealt with first. Active disease, meaning decay and gum inflammation, is treated and stabilized. The bite is checked, because a heavy or uneven bite can chip porcelain. Then the cosmetic proposal is designed, often with a preview, and finally a maintenance schedule is agreed.
What people commonly ask at this point is whether the disease-control stage is a way of delaying what they came for. It is not. It is the part of the plan most likely to decide how long the cosmetic result survives. A dentist who insists on it is protecting the investment of time and tooth structure the person is about to make.
Why decay is treated before any cosmetic work
Tooth decay, or dental caries, is the breakdown of enamel and the softer dentine beneath it by acids that bacteria produce from sugars. The National Institute of Dental and Craniofacial Research explains that the process is a tug of war: minerals are lost when acid attacks and regained when saliva and fluoride repair the surface. In its earliest stage, a white spot on the enamel, decay can be halted and even reversed. Once the surface breaks, it cannot.

That distinction matters for planning in two ways. A very early lesion may be managed with fluoride and improved cleaning rather than a filling, which preserves enamel for later bonding. A cavity that has broken through needs a restoration first, and the dentist has to decide whether the tooth will then be strong enough to carry a veneer or should be protected by a crown instead.
Placing cosmetic material over active decay creates three predictable problems. The decay continues under the restoration, often unseen because the porcelain or composite hides it. The bond fails as the tooth beneath softens, so the veneer or filling debonds or chips. And the eventual repair is larger and more expensive in tooth structure than the original cavity would have been, sometimes ending in a root canal treatment, which is the removal of the infected pulp from inside the tooth.
There is also a bacterial argument. A mouth with several active cavities is a mouth with a high load of acid-producing bacteria. Treating the cavities and changing the habits that fed them lowers that load before new margins, the edges where restoration meets tooth, are introduced. Margins are where new decay most often starts, so they should be placed into a mouth that is already under control.
The smile assessment: what the dentist is looking at
A smile design assessment sounds like a beauty consultation, and in part it is. But most of it is measurement. The dentist looks at the face at rest and during speech and smiling, noting how much tooth and gum shows, whether the midline of the upper front teeth sits close to the midline of the face, and whether the edges of the upper teeth follow the curve of the lower lip.
Then the assessment narrows to the teeth themselves. Width-to-length proportions of the front teeth, the symmetry of the two central incisors, the way each tooth steps back slightly toward the corners of the mouth, and the height of the gum on each tooth are all recorded. Small asymmetries that a person has never noticed often turn out to be the thing bothering them when they say a smile looks “off.”
Color is assessed under neutral light with a shade guide, because the same tooth looks different under bathroom bulbs and daylight. Existing restorations are mapped, since old fillings and crowns will not whiten and may need replacing to match a new shade.
Alongside the aesthetics runs a health check that is not optional. Each tooth is probed for soft spots. The gums are measured with a fine probe to detect pockets, the spaces that deepen when gum disease is present. Bleeding on probing is recorded, because inflamed gums cannot be trusted to sit still against a new veneer margin; as they heal they shrink, exposing an edge.
Finally, the dentist asks what the person actually dislikes. Photographs the patient brings are useful here, not as a target to copy but as a way of learning whether the concern is color, shape, alignment or gum display. Those are different problems with different, often simpler, solutions.
Imaging in cosmetic dentistry: X-rays, photographs and digital scans
Imaging answers questions the eye cannot. MedlinePlus lists several types of dental X-ray, each with a distinct job. Bitewing X-rays show the crowns of upper and lower back teeth together and are the main way decay between teeth is found; those contact areas are invisible to direct inspection. Periapical X-rays show a whole tooth from crown to root tip and reveal infection at the root, bone loss and the size of the pulp chamber. Panoramic X-rays capture the entire jaw in one image and are used to see wisdom teeth, jaw joints and larger patterns of bone loss.
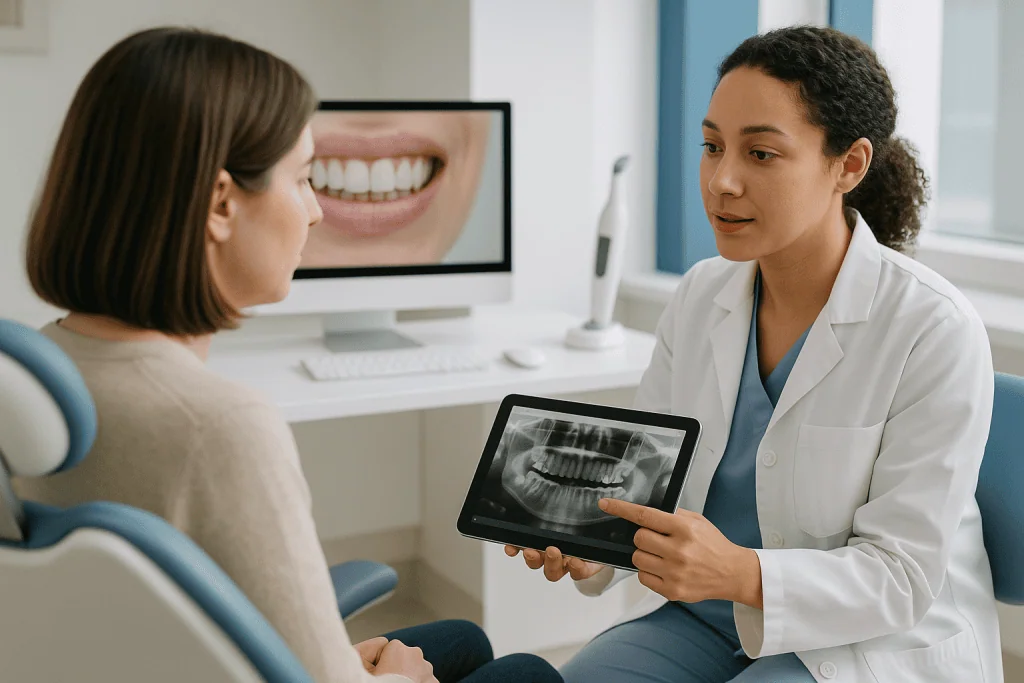
Why do dental X-rays before veneers matter so much? Because a veneer preparation removes a thin layer of enamel from the front of a tooth. If that tooth has a large pulp, an old root filling of uncertain quality or a cavity on its hidden side, the dentist needs to know before drilling. The X-ray also shows how much bone supports each tooth, which affects whether the gum position will stay stable.
MedlinePlus notes that the radiation dose from dental X-rays is low and that patients who are pregnant should tell their dentist, who will weigh whether the image is needed now. Frequency is individualized to decay risk rather than fixed to a calendar.
Photographs and digital scans complete the picture. Standardized clinical photographs record the smile from several angles and become the reference for design. An intraoral scanner, a small wand that builds a three-dimensional model of the teeth, replaces the tray of impression material for many cases and lets the dentist design a proposed smile on screen. That design can be printed and tried in the mouth as a temporary mock-up, so the person sees and feels the change before any enamel is touched.
What are the 5 phases of dental treatment planning?
The phases of dental treatment planning taught in dental schools are a framework rather than a rule from any guideline body, but they explain the order dentists follow. The common five-phase version runs as follows.
- Systemic phase. Medical conditions and medicines that affect dental care are reviewed, such as diabetes, blood-thinning treatment or a history of radiotherapy to the jaw. Any needed liaison with the person’s physician happens here.
- Acute or urgent phase. Pain, swelling, a broken tooth or an infection is treated first, before anything else is planned.
- Disease-control phase. Active decay is removed and restored, gum disease is treated with professional cleaning below the gumline, hopeless teeth are removed, and the causes of disease, usually diet and cleaning habits, are addressed. Progress is reassessed before moving on.
- Definitive phase. This is where aesthetic dentistry lives: orthodontics, whitening, bonding, veneers, crowns, implants and gum reshaping. It is planned as a whole, because moving a tooth may remove the need to veneer it, and whitening first changes the shade the veneers must match.
- Maintenance phase. Recall intervals, hygiene visits, night guards where the bite demands them, and a plan for repair when materials wear.
Four-phase versions merge the first two. The numbering matters less than the principle: each phase is completed and checked before the next begins, and the definitive phase is never used to hide problems that belong in the disease-control phase.
For the person in the chair, the framework offers a useful question to ask at any visit: which phase are we in, and what has to be true before we move to the next one? A clear answer is a sign of a well-organized plan.
What procedures are included in aesthetic dentistry?
Aesthetic, or cosmetic, dentistry covers any treatment whose main purpose is appearance, though most of these procedures also have a functional role. The list below runs roughly from least to most invasive, which is also the order a conservative dentist tends to consider them.
| Procedure | What it changes | Enamel removed | Typical planning caveat |
|---|---|---|---|
| Whitening | Color only | None | Does not lighten fillings or crowns; not permanent |
| Orthodontics / clear aligners | Position, spacing, bite | None | Slowest option; may remove the need for veneers |
| Composite bonding | Small chips, gaps, shape | Little or none | Stains and wears sooner than porcelain; repairable |
| Gum contouring | Gum height and symmetry | None (gum tissue) | Bone level on X-ray limits how much can be reshaped |
| Porcelain veneers | Color, shape, minor alignment | Thin front layer | Irreversible; needs healthy enamel and calm gums |
| Crowns | Whole visible tooth | All surfaces | Reserved for weakened or heavily filled teeth |
| Implants | Replaces a missing tooth | None (surgical) | Requires adequate bone and controlled gum disease |
Cleveland Clinic describes veneers as thin shells bonded to the front of teeth to change color, shape or minor alignment, and notes that the procedure is not reversible because enamel is removed. That single fact shapes a great deal of planning: anything that achieves the goal without removing enamel is usually offered first.
Two things are often missing from cosmetic wish lists and belong on them. Tooth-colored fillings that replace failing old restorations are both health treatment and aesthetic improvement. And a night guard, a custom plastic cover worn during sleep, protects expensive porcelain from grinding forces that would otherwise chip it.
Who is aesthetic dentistry usually for, and who is asked to wait?
The typical candidate is an adult whose teeth and gums are healthy or have been brought back to health, who has a specific concern, and whose expectations match what the materials can do. Age by itself is rarely a barrier. What the dentist assesses is the state of the mouth and the stability of the person’s habits.
Several groups are commonly asked to wait, and the reasons are protective rather than dismissive.
- Active decay or gum disease. As described above, cosmetic work is postponed until disease is controlled and the person has shown that cleaning and diet changes are holding.
- Uncontrolled grinding or clenching. Heavy bite forces break porcelain. The bite is stabilized, and a guard planned, before veneers or crowns are placed.
- Teenagers and young adults with teeth still erupting. Gum levels keep changing into the early twenties; veneers placed too early can end up with visible edges. Whitening and orthodontics are usually the options discussed.
- Pregnancy. Elective cosmetic treatment is generally deferred; urgent care is not. MedlinePlus advises telling the dentist about pregnancy before X-rays are taken so the need can be weighed.
- Recent or planned orthodontics. Cosmetic shaping is designed after teeth have settled in their final positions.
- Expectations that materials cannot meet. A request for a shade whiter than natural enamel, or for veneers to fix a bite problem, calls for an honest conversation rather than a start date.
Medical conditions matter too. Poorly controlled diabetes slows gum healing. Some medicines cause dry mouth, which raises decay risk around new margins. A history of bisphosphonate therapy or jaw radiotherapy changes how surgery such as implants is planned. None of these automatically rules treatment out; each changes the sequence, and the decision sits with the treating team in consultation with the person’s physician.
Gum health and the bite: the two things that decide how long results last
Ask a dentist what most often shortens the life of cosmetic work and the answer is rarely the porcelain. It is the gum around it and the forces on it.
Gum disease begins as gingivitis, inflammation of the gum edge that bleeds when brushed. Left alone it can progress to periodontitis, where the bone supporting the tooth is lost and the gum recedes. Recession exposes root surface that is darker than enamel and cannot be whitened; around a veneer it reveals a dark line at the margin that no amount of polishing hides. For that reason gum measurements are repeated after treatment and again before final cosmetic impressions. Only when bleeding has stopped and pocket depths are stable is the gum position considered trustworthy enough to design against.
The bite is the second silent factor. When the jaws close, force should spread across many teeth. If a few front teeth take the load, or if the lower jaw slides against the upper during grinding, thin porcelain edges chip. Part of the assessment is watching the teeth slide against each other and noting wear facets, the flat shiny patches that betray grinding. A dentist may adjust high spots, plan slightly thicker material in load-bearing areas, or provide a night guard. Sometimes the honest recommendation is orthodontics to correct the bite before anything is bonded.
These two factors also explain why maintenance is written into the plan. NHS guidance sets check-up intervals according to individual risk, from as little as three months to as long as two years for people with very healthy mouths. Someone with new veneers and a history of gum disease sits toward the shorter end, because catching inflammation early protects margins that took months to plan.
How long does aesthetic dentistry treatment planning take?
There is no guideline that fixes a duration, and any single number would be a guess. What can be described is the shape of the timeline and what governs each part.
The assessment itself usually takes one or two visits: examination, gum measurements, X-rays, photographs and a scan, then a separate conversation once the dentist has studied the images and drawn up options. Spacing these apart is deliberate; a plan made at the first meeting is a plan made without time to look properly.
Disease control sets the pace of everything that follows. A single small filling adds one visit. Several cavities, a root canal treatment or gum therapy can add weeks, because gums need time to heal after cleaning below the gumline before they can be reassessed. Where early decay is being managed with fluoride and habit change rather than drilling, the dentist will want to see at a follow-up that the lesions have stopped progressing before bonding anything nearby.
Orthodontics, if it is part of the plan, is the longest component and is measured in months rather than weeks. Whitening comes after orthodontics and before veneers or bonding, so that the new restorations are matched to the final shade; most dentists allow the whitened color to settle for a couple of weeks before shade matching.
The definitive cosmetic work is often the shortest stretch: a preview mock-up visit, a preparation visit, temporary restorations while the laboratory works, and a fitting visit. Then maintenance begins, with recall intervals set by risk as NHS guidance describes.
Someone who arrives with a healthy mouth may move through all of this quickly. Someone with untreated decay will not, and a dentist who compresses the disease-control stage to hit a deadline is trading durability for speed.
What the following weeks usually look like once treatment begins
The early weeks of a cosmetic dentistry treatment plan are mostly about the unglamorous stages, and it helps to know that in advance.
After fillings, mild sensitivity to cold for a few days is common as the tooth settles; a bite that feels high should be reported, because a filling left proud can cause pain and chipping. After gum treatment, gums may feel tender and teeth may look slightly longer as swelling resolves, which is the tissue returning to a healthy contour rather than a complication. Bleeding on brushing should fall week by week; if it does not, the dentist will look for spots being missed or a pocket that needs further attention.
Whitening typically brings a window of temporary sensitivity during treatment. Its results are not permanent, and the dentist will discuss how diet and habits affect how long the shade holds; no fixed figure applies to everyone.
During the veneer or crown stage, temporary restorations are worn while the laboratory works. They are made of acrylic, feel slightly bulky, and can come loose with sticky foods, so the instructions about diet and cleaning around them matter. After final fitting, the bite is checked and adjusted, speech may feel different for a few days as the tongue learns the new edges, and a night guard is fitted where planned.
The first review after cosmetic work is usually within a few weeks. The dentist checks margins, gum response and the bite, and takes photographs to compare with the plan. From there, recall shifts to the maintenance interval set for that person’s risk.
The pattern throughout is the same: each step is checked before the next. A well-run plan feels slower than expected at the start and faster at the end, because the foundation work was done properly.
Risks, alternatives and the principle of least invasion
Every aesthetic procedure carries risks that belong in the planning conversation, stated plainly.
Whitening can cause temporary tooth and gum sensitivity and will not change the color of existing restorations. Bonding can chip, stain and need periodic repolishing or replacement. Veneers require irreversible enamel removal; Cleveland Clinic notes that they can chip or debond, that sensitivity may follow preparation, and that once placed they will eventually need replacing rather than removing. Crowns remove more tooth structure and carry a small risk that the pulp inside reacts and later needs root canal treatment. Gum surgery carries bleeding and infection risks and can produce uneven healing. Implants are surgical, with risks that include infection, nerve irritation and failure to integrate with bone, and they depend on stable gum health.
Alternatives exist for almost every goal. Discolored teeth can be whitened rather than veneered. Crowded teeth can be aligned rather than disguised. A single dark tooth that has had a root canal can sometimes be whitened from the inside. Small gaps can be closed with bonding rather than porcelain. The alternative that is often forgotten is doing nothing cosmetic at all after disease control, and living with a healthy, functional smile; for some people the improvement in gum color and clean margins after treatment is enough.
The organizing idea is least invasion first. Enamel does not grow back, and each step up the ladder closes doors below it. A dentist working this way will often propose a sequence that starts with the reversible options and pauses to reassess before anything irreversible is done. The person is free to stop at any rung.
None of this means the more invasive options are wrong. It means they should be chosen, with the risks understood, rather than arrived at because a simpler path was never offered.
What people often get wrong about planning a new smile
“Veneers will fix the cavities too.” They will not. A veneer covers the front surface only; decay between teeth or under the gum continues, and Mayo Clinic is clear that established cavities need the decay removed and the tooth restored.
“There is a 3-3-3 rule for teeth I should follow first.” People search for this constantly, and the honest answer is that no major guideline body publishes a 3-3-3 rule. The phrase circulates informally with different meanings, most often brushing three times a day for three minutes and waiting a period after eating before brushing. Mainstream guidance from the NHS is simpler: brush twice a day with fluoride toothpaste, clean between the teeth daily, and cut down on how often sugar is eaten. Frequency of sugar matters more than quantity because each exposure starts a fresh acid attack.
“Whitening damages enamel.” Professionally supervised whitening on healthy teeth is not shown to cause lasting enamel damage; sensitivity during treatment is common and temporary. Whitening over untreated decay or exposed roots, however, can be painful, which is another reason disease control comes first.
“The whitest shade is the best shade.” Natural enamel has translucency and slight warmth; a flat, very white shade can look like a denture in photographs. Shade is chosen against the whites of the eyes and skin tone.
“Bleeding gums are normal.” Bleeding on brushing is a sign of inflammation, not vigor. It has to resolve before margins are placed near the gum.
“Once it is done, it is done.” Every cosmetic material wears, stains or fails eventually. Planning includes maintenance and a realistic conversation about repair, which is why the recall interval is part of the plan and not an afterthought.
Questions to ask your care team before a smile design assessment
A good plan survives questions. These are the ones that tend to surface the reasoning behind a proposal, and a dentist who welcomes them is usually one who has thought the plan through.
- Which phase of treatment planning are we in now, and what must be true before we move to the next?
- Which X-rays or scans have been taken, what did they show, and is anything on them being treated before cosmetic work starts?
- Do I have any active decay or gum disease, and how will we know it is under control?
- What is the least invasive option that would address what bothers me, and why might you recommend something more?
- Which steps are reversible, and which remove enamel permanently?
- Can I see a mock-up or trial version in my mouth before any tooth is prepared?
- How will my bite be checked, and do you think I need a night guard?
- What could go wrong with each option, and what would the repair involve?
- Will any existing fillings or crowns need replacing to match a new shade?
- How often will I need to be seen afterward, and what will you be checking for?
- If I stop after the disease-control stage and do nothing cosmetic, what does my mouth look like?
Bring the photographs that shaped your idea of the goal, but be ready to hear that the feature you admire in them may be produced by a different treatment from the one you had in mind. Ask the team to point to the specific thing in your own photographs that they propose to change; a plan that can be described in those concrete terms is usually a plan that has been genuinely individualized. Write the answers down. The plan belongs to you and the treating team together, and understanding it is part of consenting to it.
When to call your doctor or dentist
Most of the sensations that follow dental treatment are mild and settle within days. Some are not, and they need a call rather than a wait. Contact your dentist, or seek urgent medical care if a dental service is not available, for any of the following.
- Facial or gum swelling that is spreading, especially toward the eye or under the jaw, or swelling with fever, which can indicate a dental infection that is tracking into surrounding tissue.
- Difficulty swallowing or breathing, or being unable to open the mouth fully; these are emergency signs.
- Severe, throbbing tooth pain that wakes you or is not controlled with the measures your dentist advised.
- Bleeding from the gums or a surgical site that does not stop with firm pressure.
- Numbness of the lip, chin or tongue that persists beyond the expected duration of local anesthetic.
- A veneer, crown or temporary restoration that has come loose or broken, or a filling that feels sharp; a loose piece can be swallowed or inhaled and an exposed tooth is vulnerable to decay.
- Sensitivity to hot or cold that is getting worse rather than better after two weeks, or pain when biting on a treated tooth, which can signal a high spot or a crack.
- A bad taste, pus or a small bump on the gum near a treated tooth, which can indicate an abscess.
Before treatment begins, tell the team about any medical change: a new diagnosis, a new medicine, pregnancy, or an upcoming surgery. These can change the sequence of the plan, and the treating team will coordinate with your physician where needed.
Between visits, the everyday warning signs are simpler. Gums that keep bleeding, a sweet or cold sensitivity that appears in a new place, or a rough edge the tongue keeps finding are all reasons to be seen sooner than the scheduled recall. Every decision about what to do next rests with your dentist and, where relevant, your doctor.
Frequently asked questions
What is the 3-3-3 rule for dental care?
There is no 3-3-3 rule in guidance from the NHS, CDC or other major health bodies; the phrase is an informal mnemonic with several versions, most often brushing three times a day for three minutes. Evidence-based advice is simpler: brush twice daily with fluoride toothpaste, clean between teeth every day, and reduce how often sugary foods and drinks are consumed, because each exposure triggers a fresh acid attack on enamel.
What are the 5 phases of dental treatment planning?
The five phases commonly taught are systemic (reviewing medical conditions and medicines), acute (treating pain or infection), disease control (treating decay and gum disease and addressing their causes), definitive (restorative and aesthetic work such as orthodontics, whitening, veneers or implants) and maintenance (recall visits and protection such as night guards). Each phase is checked before the next begins, and cosmetic work sits in the definitive phase.
What procedures are included in aesthetic dentistry?
Aesthetic dentistry includes whitening, composite bonding, porcelain veneers, tooth-colored fillings and crowns, orthodontics including clear aligners, gum contouring and implants to replace missing teeth. Most have a functional role as well as a cosmetic one. Dentists typically consider them from least to most invasive, since options such as whitening and orthodontics remove no enamel, while veneers and crowns involve permanent tooth preparation.
Why do I need dental X-rays before veneers?
X-rays reveal what the eye cannot: decay between teeth, infection at the root tip, the size of the nerve chamber and how much bone supports each tooth. A veneer preparation removes enamel, so the dentist needs to know the tooth beneath is sound. MedlinePlus notes that dental X-ray radiation is low and that pregnant patients should tell their dentist so the need can be weighed.
Can a dentist put veneers over cavities?
No. Veneers cover only the front surface and bond to enamel, not to decayed tooth structure. Mayo Clinic explains that an established cavity must have the decay removed and the tooth restored. Decay left under a veneer continues to grow unseen, weakens the bond and often ends in a larger repair, so fillings come first and the dentist then decides whether a veneer or a crown is the right cover.
Does gum disease need treating before cosmetic dentistry?
Yes, in almost every case. Inflamed gums bleed, swell and then shrink as they heal, which can expose the edge of a new veneer or crown and leave a dark line. Gum measurements are repeated after treatment to confirm pockets are stable and bleeding has stopped before final impressions are taken. Controlled gum health also protects implants, which depend on stable bone and tissue.
How is a cosmetic dentistry treatment plan sequenced?
Urgent problems are treated first, then active decay and gum disease, then the bite is stabilized. Orthodontics comes before any reshaping, whitening comes before veneers or bonding so new materials match the final shade, and a preview mock-up is often tried before enamel is removed. Maintenance intervals are agreed at the end. The order protects durability and keeps reversible options available for as long as possible.
Is teeth whitening permanent?
No. Whitening lightens natural enamel but the effect fades over time, and how quickly depends on diet, smoking and oral hygiene rather than a fixed figure. It does not change the color of existing fillings, crowns or veneers, which may need replacing to match. Temporary sensitivity during treatment is common. Whitening over untreated decay or exposed roots can be painful, which is one reason disease is treated first.
Who should wait before having cosmetic dental work?
People with active decay or gum disease, uncontrolled grinding, teeth still erupting, planned or ongoing orthodontics, or pregnancy are usually asked to wait, and elective treatment is deferred until the mouth is stable. Medical conditions such as poorly controlled diabetes or a history of jaw radiotherapy change the sequence rather than rule treatment out. The treating dentist, with the person’s physician where needed, makes that call.
How often will I need check-ups after aesthetic dental treatment?
It depends on individual risk. NHS guidance sets check-up intervals from around three months for people at higher risk of decay or gum disease to two years for those with very healthy mouths. Someone with new veneers and a history of gum problems usually sits toward the shorter interval, because catching inflammation at restoration margins early is the main way to protect the work.
References
- MedlinePlus: Dental X-rays
- Cleveland Clinic: Dental Veneers
- NHS: Tooth decay
- NIH National Institute of Dental and Craniofacial Research: Tooth Decay
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Tooth Decay Treatment Visit: Numbing, Removing Damaged Tissue and Restoring the Tooth
A cavity treatment procedure usually has three steps: the dentist numbs the area with a local anesthetic, removes the softened, decayed part of the…

How a Smile Makeover Is Planned: Photographs, Digital Impressions and Smile Design
A smile makeover is planned in stages: a dental health examination first, then a set of standardized photographs, a digital scan of the teeth,…

Gum Recession Treatment Results: How Grafted Gum Matures and What It Can and Cannot Restore
Gum graft results develop in stages: the graft attaches over the first one to two weeks, swelling and a pale or reddish look settle…
How to Read a Smile Makeover Plan: Questions About Each Step and Temporary Teeth
A smile makeover treatment plan is a written, sequenced document that lists each proposed procedure, the order it will happen in, what temporary teeth…
What Happens During a Root Canal? Cleaning, Shaping and Sealing the Canals Step by Step
A root canal procedure treats infection or inflammation inside a tooth by removing the soft tissue in its center, cleaning and shaping the narrow…

When Aesthetic Dentistry Makes Sense and When Gum Health Has to Come First
Cosmetic dentistry usually makes sense once your gums are healthy and stable, any decay or infection has been treated, and a specific feature of…