

How Do You Prepare a Child for Pediatric Surgery? Age-Appropriate Words, Fasting and Comfort

Key Takeaways
- A child’s sense of time sets the schedule: toddlers cope best with a short explanation the day before or morning of, while school-age children usually need about a week and teens should hear as soon as the decision is made.
- Avoid “put to sleep,” “cut” and “shot”; describe anesthesia as sleepy medicine the doctor switches off, and be honest that some soreness afterward is normal and treatable.
- Clear fluids, breast milk, formula and solid food are fasted for different lengths because they leave the stomach at different speeds; the NHS cites about six hours for food and about two hours for clear fluids, with your unit’s written instructions taking precedence.
- Crying at the mask and confused, thrashing wakefulness (emergence agitation) are common in young children and usually settle within minutes to half an hour as the anesthetic wears off.
- A fever, wet cough or wheeze in the days before surgery frequently leads to postponement because inflamed airways react badly to anesthetic gases and breathing tubes.
- Clinginess, sleep disruption and a return to bedwetting after a hospital stay are a recognized, temporary stress response that fades over days to a few weeks in most children.
To prepare a child for surgery, match honest, simple explanations to their age, follow the fasting instructions the anesthesia team gives you exactly, and plan comfort ahead: a familiar toy, a calm parent nearby, and a clear picture of how the day will unfold. Toddlers need only a short heads-up; older children and teens do better with more notice and room to ask questions. Your care team confirms every detail.
The appointment letter has been on the fridge for a week, and tonight, mid-bath, your six-year-old finally asks the question you have been rehearsing an answer to: “Will they cut me open while I’m awake?” You have a clinician’s leaflet, a vague memory of your own tonsillectomy, and no idea whether the truth will help or terrify.
Working out how to prepare a child for surgery is less about finding magic words than about timing, honesty pitched to a child’s age, and getting the practical pieces right so the morning itself is uneventful. Fasting is where families most often stumble, comfort is where they have more influence than they think, and the words they choose can either shrink a hospital corridor or make it loom.
What follows is the sequence pediatric anesthesia and surgical teams walk families through, in plain language, so the bath-time questions have grounded answers.
What actually happens on the day of a child's operation
Most children’s operations follow a rhythm that looks the same whether the procedure takes twenty minutes or three hours. You arrive, usually early, and a nurse records your child’s weight, temperature and heart rate, asks about allergies and recent illness, and fastens an identity band around a wrist or ankle. Your child changes into a gown, though many units let favorite pajama bottoms or socks stay on.
Two conversations follow. The surgeon confirms what will be done and marks the site if the operation is on one side of the body. The anesthesiologist, the doctor who keeps your child asleep, comfortable and monitored throughout, asks about past anesthetics, loose teeth, snoring and the exact time your child last ate or drank. This is the moment to raise anything you have been turning over at home.
When the operating room is ready, your child walks, rides in a wagon or is carried down. Depending on local policy and the child’s age, one parent may come as far as the anesthetic room and stay until the medicine takes effect. During the operation you wait in a designated area; a nurse typically updates you if it runs longer than expected. Afterward your child moves to a recovery unit, where staff watch breathing, pain and comfort until they are awake enough for you to join them. For many minor day-case procedures, children go home the same day once they have taken fluids, passed the nurses’ checks and are reasonably comfortable, a pattern the NHS describes in its overview of general anesthesia.
Knowing this sequence lets you narrate it in advance, “first the band, then the doctor chat, then the sleepy medicine, then I’ll be there when you wake up”, which is the backbone of how children make sense of an unfamiliar day.
How to prepare a child for surgery by age: what to say and when
The single most useful principle is that a child’s sense of time sets the schedule. Telling a two-year-old about an operation next week creates a fortnight of dread for a mind that cannot hold “next week”; telling a fourteen-year-old the night before feels like a betrayal. Child life specialists, hospital staff trained to help children cope with medical experiences, generally stagger the conversation by developmental stage, and MedlinePlus offers age-specific guides that follow the same logic.
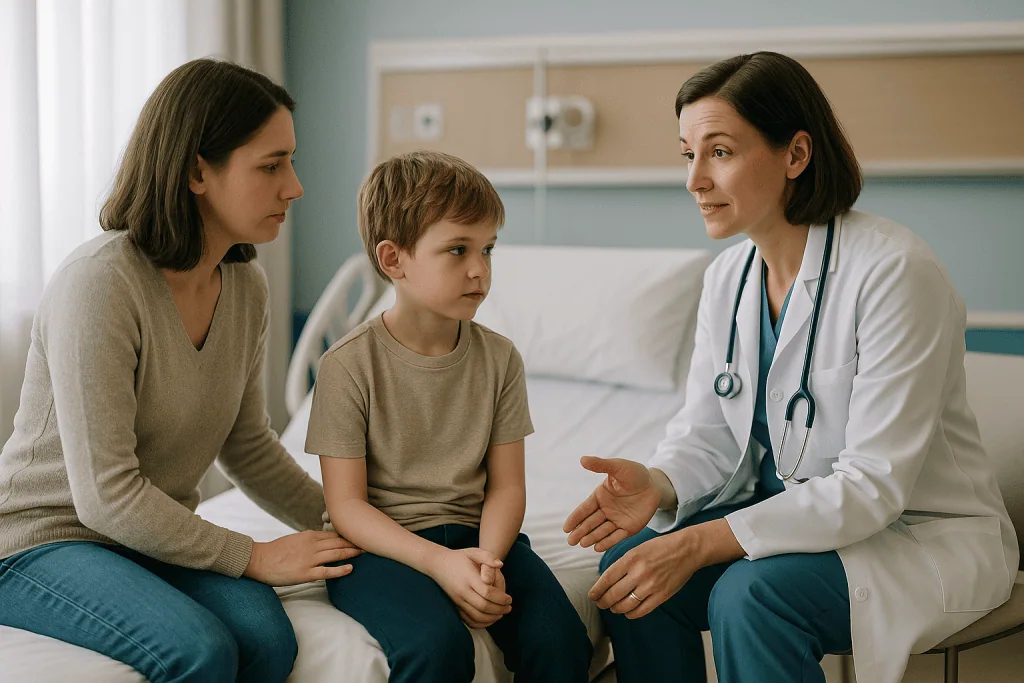
Babies under a year need no explanation. What they need is a parent whose routine, voice and touch stay steady, and a plan for feeding around fasting so hunger is not the loudest thing in the room.
Toddlers and young preschoolers do best with a brief, concrete explanation close to the day, often the evening before or the morning of. Older preschoolers can handle a few days’ notice, ideally paired with play: a doctor kit, a doll who gets a “band-aid,” a picture book about hospitals.
School-age children usually benefit from roughly a week to absorb the news, ask questions in installments and rehearse the sequence. They are old enough to worry about specifics, waking up mid-operation, needles, missing a birthday party, and old enough to be reassured by facts.
Adolescents deserve the information as soon as the decision is made, and a seat at the table. Privacy, body image and control matter intensely at this age; being asked what they would like to know, and who they want in the room, respects that.
Whatever the age, keep the message short the first time and let the child set the pace of follow-up questions. Repetition without pressure beats a single long briefing.
Explaining surgery to a child: words that help and words that frighten
Children hear language literally, and a few common phrases backfire. “The doctor will put you to sleep” is the sentence many families have used about a family pet; “a little cut” invites imagining a knife; “you’ll get a shot” lands as an act of violence. None of these are lies, but each hands a child a frightening picture to fill in alone.
Swap them for plain, accurate images. Anesthesia becomes “a special sleepy medicine that makes you fall into a deep sleep where you can’t feel anything, and the doctor wakes you up when they’re finished.” The incision becomes “a small opening the doctor makes so they can fix the part inside, then closes up carefully.” A needle becomes “a small poke that feels like a pinch,” and if a numbing cream is planned, say so: it is a local anesthetic that quiets the nerves in that patch of skin so the poke feels dull.
Honesty about discomfort matters more than parents expect. Promising “it won’t hurt at all” costs you credibility the moment it does. “Afterward some parts may feel sore, and the nurses have medicine to help, and I’ll be there” is both true and steadying.
Three more habits help:
- Name the reason simply. “Your tummy has been hurting because of this part, and the doctor is going to help it” tells a child the operation is for them, not to them.
- Separate the operation from behavior. Children under about eight often assume illness is punishment; say plainly that nothing they did caused this.
- Trade “be brave” for “it’s okay to feel nervous; we’ll do it together.” Permission to feel scared reduces the need to hide fear.
Then stop talking and listen. What a child asks next tells you exactly which picture in their head needs correcting.
Toddler surgery preparation: keep it short, close and concrete
Toddlers present a particular puzzle. They are old enough to be frightened by strangers, masks and separation, yet too young to be reassured by explanations about tomorrow. MedlinePlus’s guide to preparing toddlers for procedures suggests keeping the explanation very short and giving it shortly before the event, because a toddler’s anxiety rises with waiting time rather than with information.

What a toddler can grasp is sequence and sensation. “We’re going to the hospital. A nurse will look at you. You’ll have a special mask with sleepy medicine, and when you wake up Mommy or Daddy will be right there.” Say it the same way each time; sameness is comfort at this age.
Play does the rest. A toy doctor kit lets a toddler give teddy a check-up, put a mask on a doll and take it off again. That rehearsal, run many times on the living-room floor, is how the child learns that the mask comes off and the doll is fine.
Separation is the flashpoint. Ask in advance whether a parent can accompany your child into the anesthetic room; policies vary, and knowing the answer prevents a bargaining scene at the doors. If you cannot go in, a familiar object in the child’s hands, a blanket that smells of home, a beloved stuffed animal, travels where you cannot.
Expect regression. A toilet-trained toddler may want diapers for a few days; a child who slept through the night may wake crying. Johns Hopkins lists such behavior changes as a common, temporary response to hospitalization at this age. Meeting them with patience rather than correction shortens them.
Bring a bottle or sippy cup, a change of clothes for both of you, and the stroller. Toddlers who have fasted and then been woken from anesthesia are rarely at their most cooperative.
Fasting before surgery for kids: why the empty stomach matters
Fasting is the instruction families most often misjudge, and the one anesthesiologists are least able to bend. Under general anesthesia the reflexes that normally close off the airway relax. If the stomach holds food or milk, contents can travel back up and enter the lungs: a rare event called aspiration that can cause serious pneumonia. An empty stomach is the protection.
The other side of the ledger is that a long fast makes children thirsty, irritable and, in small bodies, at risk of low blood sugar and dehydration. Modern guidance therefore distinguishes sharply between what is in the stomach. Clear fluids leave quickly; breast milk takes longer; formula and solid food longer still. The NHS notes that adults and children are usually asked not to eat for about six hours before a general anesthetic, while clear fluids may often be taken until about two hours beforehand. Some pediatric anesthesia services allow clear fluids even closer to the operation; your unit’s written instructions override any general table.
| What the child had | Typical minimum gap before anesthesia | Why the difference |
|---|---|---|
| Clear fluids (water, diluted juice without pulp) | About 1–2 hours, per local policy | Pass through the stomach quickly |
| Breast milk | Roughly 4 hours in most protocols | Digests faster than formula |
| Infant formula, milk | Roughly 6 hours | Proteins and fats slow emptying |
| Solid food, sweets, chewing gum | About 6 hours (longer for fatty meals) | Slowest to clear |
Two practical notes. Write the last eating and drinking times on your phone; you will be asked, and “around breakfast” is not an answer the team can use. And if your child sneaks a biscuit, tell the nurse immediately rather than hoping it does not matter. A delayed operation is inconvenient; a hidden snack is a safety problem.
Child anesthesia: what to expect from the mask to waking up
Parents often fear anesthesia more than the operation. Understanding the mechanics helps. General anesthesia is a medically controlled state of deep unconsciousness in which the child cannot feel, remember or move. In young children it is usually begun with a scented mask delivering anesthetic gas: the child breathes, counts or blows into the mask like a balloon, and drifts off within a minute or two. Once asleep, a thin plastic tube (a cannula) goes into a vein so medicines and fluids can be given painlessly. Older children and teens may prefer the cannula first, often after a numbing cream or spray dulls the skin.
Some children receive a pre-medication: a sedative given by mouth beforehand to ease separation anxiety. Whether one is used, and which class, is the anesthesiologist’s judgment based on the child’s age, temperament and medical history.
Throughout, monitors track heart rhythm, oxygen level, blood pressure, breathing and temperature, and the anesthesiologist stays at the child’s side. Mayo Clinic’s overview of general anesthesia describes serious complications as uncommon in otherwise healthy people, with the risk depending more on the child’s underlying health and the operation than on the anesthetic itself.
Waking is where surprises happen. Many young children emerge confused, crying or thrashing for a short period, a phenomenon called emergence agitation. It is distressing to watch and usually settles within minutes to half an hour as the medicines wear off. Nausea, a sore throat from a breathing tube, shivering and sleepiness through the rest of the day are common and expected.
On the question of anesthesia and the developing brain: large studies have not shown lasting learning problems after a single, relatively short anesthetic in a healthy child. Uncertainty remains around repeated or prolonged exposures in very young children, which is one reason surgical timing is a conversation, not a default.
Who is usually ready for surgery, and who is asked to wait
Planned children’s surgery is scheduled for a child who is as well as they can be on the day. That sounds obvious until a cold arrives the weekend before, and the family is unsure whether to cancel.
A child with a fever, a wet cough, wheeze or a chest infection is frequently postponed. Anesthetic gases and breathing tubes irritate airways that are already inflamed, and a child recovering from a respiratory infection can react with spasm of the airway or drops in oxygen during or after the anesthetic. A mild runny nose without fever is often judged acceptable, particularly for short procedures, but that call belongs to the anesthesiologist on the morning, so phone the unit rather than deciding at home.
Other reasons a team may pause include a skin infection near the operation site, vomiting or diarrhea in the previous day or two, a recent live vaccine in some centres, or, the commonest, a broken fast. Occasionally a very loose tooth needs a plan so it cannot be dislodged during airway care; mention it.
Children with asthma, sleep apnea, congenital heart conditions, epilepsy, diabetes, prematurity or neuromuscular conditions are not excluded, but they are usually seen earlier in a pre-assessment clinic so the anesthetic plan can be tailored. Some may be scheduled first on the list, kept overnight for observation, or moved to a centre with a pediatric intensive care unit. Medicines the child already takes are reviewed one by one; the team will tell you which to give on the morning and which to hold. Do not stop or adjust anything on your own initiative.
Emergencies, appendicitis, a fracture that must be set, follow different rules, because waiting carries its own risk. Even then, the same fasting and airway principles shape how the anesthesiologist proceeds.
Comfort strategies that genuinely reduce a child's distress
Comfort is not decoration; children who arrive calmer tend to need less rescue sedation, settle faster in recovery and carry fewer bad memories forward. Fortunately, most of what works is simple.
Start with objects. A comfort item that goes into the operating room and comes back out teaches, wordlessly, that things return. Label it. Familiar pajamas, if permitted, keep the child’s own smell close. A tablet loaded with a favorite show or a pair of headphones with a known playlist gives the mind somewhere else to be during waiting, and many anesthetic rooms will let a child watch right up to the mask.
Then people. Ask about parental presence at induction and in recovery. Where it is allowed, your job is to be a calm anchor, not a commentator: a hand on the chest, a familiar song hummed low. Where a child life specialist is available, book them; they are experts in medical play, distraction and coaching, and they speak the child’s language better than most doctors do.
Distraction outperforms reassurance in the moment. Blowing bubbles, counting ceiling tiles, “I spy,” a search-and-find book or a running conversation about the weekend all give the brain a competing task. Repeated “it’s okay, it’s okay” tends to signal that something is not.
Give the child a job. Choosing the mask flavor, holding the oxygen tubing, deciding which arm gets the cream, pressing the button that raises the bed, small choices restore a sense of control that hospitals strip away.
Finally, plan the after. A promised treat once eating is allowed, a favorite film for recovery day, a sibling waiting with a card: anticipation of something good is a comfort strategy children understand instinctively.
Why your own calm is part of how to prepare a child for surgery
Children read faces before they read leaflets. A parent whose voice tightens on the word “anesthetic,” who checks the clock every ninety seconds or who cries in the corridor, is telling the child that something dangerous is happening, however carefully the words have been chosen. Parental anxiety is one of the more consistent predictors of a child’s distress during medical procedures, which is why teams pay attention to it.
This is not an instruction to feel nothing. It is an argument for getting your own questions answered before the day, so the fear is not still fresh in the waiting room. Write the questions down. Ring the pre-assessment nurse. Ask what the mask smells like, who calls you when it is over, what emergence agitation looks like so it does not blindside you. Anesthesiologists and surgical nurses would far rather spend ten minutes on the phone with a prepared parent than manage a panicked one in the anesthetic room.
Decide in advance which adult goes in, if one can. Ideally that is the person who is steadier in medical settings, not necessarily the primary caregiver, and not both parents negotiating at the door. The other parent’s role, looking after siblings, fetching coffee, holding the car keys, is just as real.
Take care of the body too. Eat breakfast yourself, out of sight if your child is fasting. Bring a book. Recovery units are often cold; bring a sweater. You may be sitting for hours, and a hungry, shivering parent is not at their most reassuring.
If your own fear is out of proportion, a past bad anesthetic, a family loss, say so to the team. They can put more support around you, and around your child.
The night before and the morning of: a practical checklist
The evening before is for logistics, so the morning can be about your child. A bath or shower the night before, with attention to the operation area if the team asked for it, reduces the number of things to do at dawn. Remove nail polish and any jewelry, including earrings; the clip that measures oxygen sits on a fingertip and reads poorly through polish, and metal must not be worn during surgery. Trim nails if you can, children scratch at dressings.
Set out loose, front-opening clothes for afterward, a spare set in case of vomiting, and the comfort item, labeled. Charge the tablet. Pack:
- The hospital letter, insurance or health-service details, and a list of every medicine, supplement and allergy, with the time of the last dose.
- Formula or expressed milk for infants, and any special-diet items for the trip home.
- Snacks for you, and a drink your child likes for when eating is allowed again.
- A phone charger, a book, and coins or a card for parking.
Confirm the fasting times against the written instructions and set alarms rather than relying on memory: one for the last solid meal, one for the last drink. Explain to older siblings why the fridge is off limits for one person. Arrange childcare for siblings; hospitals are dull for a well child and stressful for the parent watching two.
On the morning, give only the medicines the team told you to give, with the small sip of water they specified. Dress your child in something easy to change. Leave home earlier than seems necessary; parking and check-in absorb time, and a rushed arrival undoes a week of careful preparation.
Bring your phone, keep it charged and keep it on. The recovery nurse will call it.
What the following days and weeks usually look like
Recovery has two layers: the body and the behavior. Parents expect the first and are often unsettled by the second.
Physically, the first day is dominated by the anesthetic wearing off. Sleepiness, unsteadiness, a sore throat and some nausea are common, and the NHS advises that anyone who has had a general anesthetic be supervised for the rest of the day. Eating restarts gently, sips, then bland food, and a child who vomits once and then keeps fluids down is following a normal script.
Pain is usually greatest in the first two or three days and then eases. The team will tell you which pain relievers to give, in what pattern and for how long; the two most often used in children are a simple analgesic and an anti-inflammatory, given in a schedule the prescriber sets. Give them as instructed rather than waiting for tears, and report pain that seems out of keeping with what you were told to expect. Wound care, bathing rules and activity limits vary by operation, so ask for them in writing.
Behaviorally, Johns Hopkins and other pediatric centres describe a cluster of changes that follow many hospital stays: clinginess, sleep disruption, nightmares, tantrums, new fears of strangers or of the dark, and a return to thumb-sucking or bedwetting. These typically fade over days to a few weeks. They are a child processing a strange experience, not evidence of harm. Routine, extra cuddles, medical play with the toy kit, and letting the child retell the story in their own words all help.
Return to nursery or school is usually guided by comfort and the surgeon’s advice on activity. A follow-up appointment or phone check is common; put it in the calendar before you leave the unit.
What people often get wrong about preparing a child for surgery
“If I don’t mention it, they won’t worry.” Children notice whispered phone calls, empty fridges and unfamiliar early alarms. A child who arrives at hospital with no explanation experiences ambush, and ambush is remembered. Age-appropriate honesty is consistently associated with less distress, not more.
“A sip of juice won’t matter.” Clear fluids and milk are treated differently precisely because they empty at different speeds, and juice with pulp or a splash of milk counts as more than clear. Anesthesiologists cancel operations over this daily. The rule is not fussiness; it is airway protection.
“Crying when the mask goes on means something went wrong.” Many preschoolers cry at induction and many wake crying. Neither predicts a bad outcome. What matters is that the team expected it and you did too.
“They’re too young to remember, so preparation is pointless.” Toddlers may not store a narrative memory, but they form emotional associations with white coats, masks and separation that can shape later medical visits. Comfort and predictability at this age are an investment in the next appointment.
“Behavior changes afterward mean the anesthetic damaged them.” Clinginess and disturbed sleep after a hospital stay are a well-described stress response that resolves in most children within weeks. Persistent or worsening changes deserve a conversation with your pediatrician, but the common pattern is temporary.
“Bribing with a treat is cheating.” A promised reward for afterward is not a bribe; it is an anchor to the near future, and it works because children reason concretely. What to avoid is making the reward conditional on not crying: that punishes an honest emotion.
“I should stop their regular medicines to be safe.” Never adjust prescribed medicines on your own before an operation. Some are continued through the morning; some are held; the team decides which.
Questions to ask your care team before the day
A ten-minute conversation before the operation prevents most morning-of confusion. Bring this list, add your own, and write the answers down; you will not remember them under pressure.
- What exactly will be done, and why now rather than later? Are there non-surgical options, and what happens if we wait?
- What are the specific risks of this operation and this anesthetic for my child, given their medical history?
- What are the fasting times for solids, milk, breast milk and clear fluids, written down, and what counts as a clear fluid?
- Which of my child’s regular medicines should be given on the morning, and which held?
- Will my child have a mask or a cannula first? Will numbing cream be used? Might a pre-medication be offered?
- Can a parent be present at induction and in recovery? If only one, when will the other be called?
- How long is the operation expected to take, and who will update me if it runs over?
- What will my child look and feel like when they wake, and what should I not be alarmed by?
- What is the pain plan for the first three days, and who do I call if it is not working?
- What are the wound care, bathing and activity rules, and when can my child return to school or sport?
- Which symptoms mean I should phone, and which mean I should go straight to emergency care?
- Is a child life specialist or pre-operative visit available so my child can see the ward beforehand?
- If my child develops a cold, who do I call and by when?
You are also entitled to ask the surgeon how often they perform this operation in children of your child’s age, and to request a second opinion if you are uncertain. Good teams welcome the question. The decision to proceed, and how, sits with them and with you together.
When to call your doctor after your child's surgery
Most children recover from planned surgery without incident, and most of what you will see, drowsiness, a single vomit, grumpiness, a dressing that looks untidy, is expected. Some signs are not, and the unit should have given you a number that is answered around the clock. Use it without embarrassment.
Phone the surgical team or your pediatrician the same day if your child has:
- A fever that develops or climbs after the first day, or a temperature the discharge instructions told you to report.
- Increasing redness, warmth, swelling, pus or a bad smell at the wound, or a wound that is opening.
- Bleeding that soaks through the dressing or does not stop with gentle pressure.
- Repeated vomiting so that fluids will not stay down, or far fewer wet diapers or trips to the toilet than usual.
- Pain that is worsening rather than easing, or that the prescribed pain relief does not touch.
- A new rash, hives or facial swelling, which can signal a reaction to a medicine.
- Unusual sleepiness, confusion or difficulty rousing beyond the first evening.
Call emergency services or go to the nearest emergency department immediately if your child has difficulty breathing, noisy or labored breathing, blue or gray lips or face, is limp or unresponsive, has a seizure, or has severe bleeding. These are red flags in any child and are not to be watched and waited on at home.
Trust your instinct. Parents are reliable detectors of “not right” in their own child, and clinicians know it. If something worries you and it is not on this list, the call is still the correct response. The team would rather reassure you a dozen times than miss the one call that mattered.
Frequently asked questions
How far in advance should I tell my child about their operation?
It depends on age. Toddlers do best with a short explanation the evening before or on the morning; older preschoolers can handle a few days’ notice, especially with medical play; school-age children usually benefit from about a week; adolescents should be told as soon as the decision is made and involved in planning. Keep the first conversation brief and let follow-up questions arrive in their own time.
What are the fasting rules before surgery for kids?
Most children are asked to stop solid food, formula and milk about six hours before a general anesthetic, breast milk somewhat later, and clear fluids until roughly one to two hours before, depending on local policy. The gaps differ because these leave the stomach at different speeds. Always follow the written times your anesthesia team gives you, and tell the nurse immediately if your child eats or drinks by mistake.
Can I stay with my child while the anesthesia is given?
Often, yes, but policies vary between hospitals and by the child’s age and medical situation. Many pediatric units allow one parent into the anesthetic room until the child is asleep, and most call parents into recovery as the child wakes. Ask at pre-assessment so you know the answer before the day, and decide in advance which adult will go in.
What is toddler surgery preparation supposed to look like at home?
Keep it short, concrete and repeated. Use a toy doctor kit so your toddler can put a mask on a doll and take it off, say the same simple sequence each time, and choose a comfort object that will travel into the operating room and come back. Prepare for regression afterward, disrupted sleep, clinginess, wanting diapers, and meet it with patience rather than correction.
Is it safe for a child to have a general anesthetic?
For an otherwise healthy child, serious complications from general anesthesia are uncommon, and the risk relates more to the child’s underlying health and the type of operation than to the anesthetic itself. Anesthesiologists monitor breathing, heart rhythm, oxygen and temperature continuously. Your child’s specific risks depend on their history, which is exactly what the pre-assessment conversation is for.
What should I expect in child anesthesia recovery?
Expect drowsiness, possibly a brief period of crying or confusion as the medicines wear off, a sore throat if a breathing tube was used, and sometimes nausea. Young children often wake agitated for a short time before settling. Staff watch breathing and comfort until your child is alert enough for you to join them, then until they have taken fluids and are comfortable enough to go home or to the ward.
My child has a cold, will the operation be cancelled?
Possibly. A fever, wet cough or wheeze often leads to postponement because inflamed airways react poorly to anesthetic gases and breathing tubes, whereas a mild runny nose without fever may be acceptable for a short procedure. The decision rests with the anesthesiologist. Phone the unit as soon as symptoms appear rather than deciding at home or waiting until arrival.
How do I explain surgery to a child without frightening them?
Use plain, literal images: sleepy medicine that the doctor switches off, a small opening the doctor closes carefully, a poke that feels like a pinch. Avoid “put to sleep,” “cut” and “shot.” Say the operation is to help them, that nothing they did caused it, and that some soreness afterward is normal and the nurses have medicine for it. Then listen for what they ask next.
Why is my child acting differently after coming home from surgery?
Clinginess, nightmares, tantrums, new fears and a return to bedwetting or thumb-sucking are a well-described, temporary stress response to hospitalization and anesthesia. In most children they fade over days to a few weeks with routine, reassurance and medical play. Contact your pediatrician if changes persist beyond that, worsen, or are accompanied by physical symptoms.
Should I stop my child's regular medicines before surgery?
No, not on your own. Some medicines are continued right through the morning of surgery, some are held, and the pattern depends on the medicine and the operation. The anesthesia team reviews each one at pre-assessment and tells you what to give, with what sip of water, and when. Bring a complete list, including supplements and inhalers, and follow their instructions exactly.
References
- NHS – General anaesthesia
- MedlinePlus – Toddler test or procedure preparation
- MedlinePlus – School-age test or procedure preparation
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Do Babies Start Walking? Milestones and Normal Ranges
Most babies take their first independent steps around 12 months, and about half are walking by their first birthday. The normal range is wide:…

How Do Seizure Diaries and Sleep Routines Support Pediatric Epilepsy Treatment Day to Day?
A seizure diary for a child records when each seizure happens, how long it lasts, what it looks like and what came before it,…

How Long Viral Croup Usually Lasts: Why Nights Feel Worse and When the Bark Fades
Viral croup usually runs its course in about three to seven days. The barking cough and noisy breathing tend to be worst on the…
What Does Recovery After Pediatric Cardiac Surgery Look Like? Intensive Care, Ward and Home
Recovery after child heart surgery usually moves through three stages: a monitored intensive care phase of roughly 2 to 4 days after open-heart procedures,…

Is Kawasaki Disease Contagious? Myths About Causes, Spread and Who Gets It, Corrected
No. Kawasaki disease is not contagious. It is an inflammatory illness of the blood vessels, most common in children under five, and it does…

When Toddlers Stop Napping, and How to Handle the Transition
Most children stop napping somewhere between ages 3 and 5, although a small number give up daytime sleep closer to age 2 and some…