

How Is Pneumonia Diagnosed? Chest X-Ray, Blood Tests and Oxygen Readings Explained

Key Takeaways
- A chest X-ray is the standard confirming test for pneumonia, but it can appear normal in the first hours of illness, so clinicians sometimes treat on examination findings and repeat imaging.
- Pulse oximetry, the fingertip sensor reading, is one of the most objective severity measures in pneumonia; the Cleveland Clinic cites a typical healthy range of 95 to 100 percent, but your own baseline matters.
- Blood tests such as white cell count and C-reactive protein gauge inflammation and organ strain rather than confirming pneumonia by themselves.
- Sputum and blood cultures take one to three days to grow organisms and are often negative, which is why treatment usually begins before the germ is named.
- The NHS describes typical recovery in stages, with fever settling within about a week, cough and breathlessness easing by roughly six weeks, and full energy returning over up to six months for some people.
- Older adults may present with confusion, weakness or a fall rather than fever and cough, so a low threshold for assessment is appropriate in that group.
Pneumonia is diagnosed by combining a clinician's examination with tests. A doctor listens to the lungs for crackles, checks temperature, breathing rate and pulse, and measures blood oxygen with a fingertip sensor. A chest X-ray usually confirms infection in the lung tissue, while blood tests gauge inflammation and severity. Sputum, swab or urine tests may identify the germ, and a CT scan is reserved for unclear cases.
The cough has been hanging around for eight days. It started as a cold, then something changed: climbing the stairs to the bedroom now takes a pause on the landing, the chills come in waves, and each deep breath catches on the right side like a stitch. The person sitting in the waiting room is turning one question over and over: is this just a bad chest infection, or is it pneumonia, and how would anyone actually know?
That question deserves a straight answer, because the process is more layered than a single scan. Understanding how pneumonia is diagnosed helps you follow what happens in the exam room, know why a nurse clips a sensor to your finger before anyone mentions an X-ray, and recognize which results genuinely change the plan.
What follows is the whole pathway, from the stethoscope to the lab, explained by medical evidence rather than by what a relative swears happened to a friend of a friend.
How is pneumonia diagnosed? What clinicians are actually looking for
Pneumonia is an infection that inflames the small air sacs of the lungs, called alveoli, and fills them with fluid or pus. Diagnosis rests on two linked questions. Is there infection in the lung tissue itself, rather than only in the airways above it? And if there is, how sick is this person right now?
The first question separates pneumonia from a chest cold or acute bronchitis, which irritate the breathing tubes but leave the air sacs largely clear. The second question decides where care happens, because a young, otherwise healthy adult with a patch of infection and normal oxygen is in a very different position from an older person who is confused, breathing fast and running low on oxygen.
Clinicians build the answer in layers. A history of symptoms and their pace comes first. Examination follows: temperature, pulse, breathing rate, blood pressure, oxygen saturation, and careful listening over both lungs. Imaging, usually a plain chest X-ray, adds a picture of the tissue. Blood tests measure the body’s inflammatory response and check how organs such as the kidneys are coping. Where it matters, samples of sputum, blood or urine try to name the organism responsible.
No single element settles the matter alone. The Mayo Clinic describes the diagnosis as a judgment that pulls together medical history, physical findings and tests, and that framing is worth holding onto. A clear X-ray does not always rule pneumonia out early in the illness, and an abnormal blood count does not by itself rule it in. Doctors weigh the whole pattern, then match the intensity of testing to the risk they see in front of them.
How do doctors tell if you have pneumonia during the physical exam?
Before any machine is involved, a great deal is learned from a chair and a stethoscope. The clinician wants to know when the illness began, whether a cold seemed to improve then worsened, whether the cough brings up discolored phlegm, and whether breathing has become painful or fast. Recent travel, contact with sick people, smoking, and long-term conditions such as heart failure, diabetes or COPD (chronic obstructive pulmonary disease, a narrowing of the airways) all shift the odds.
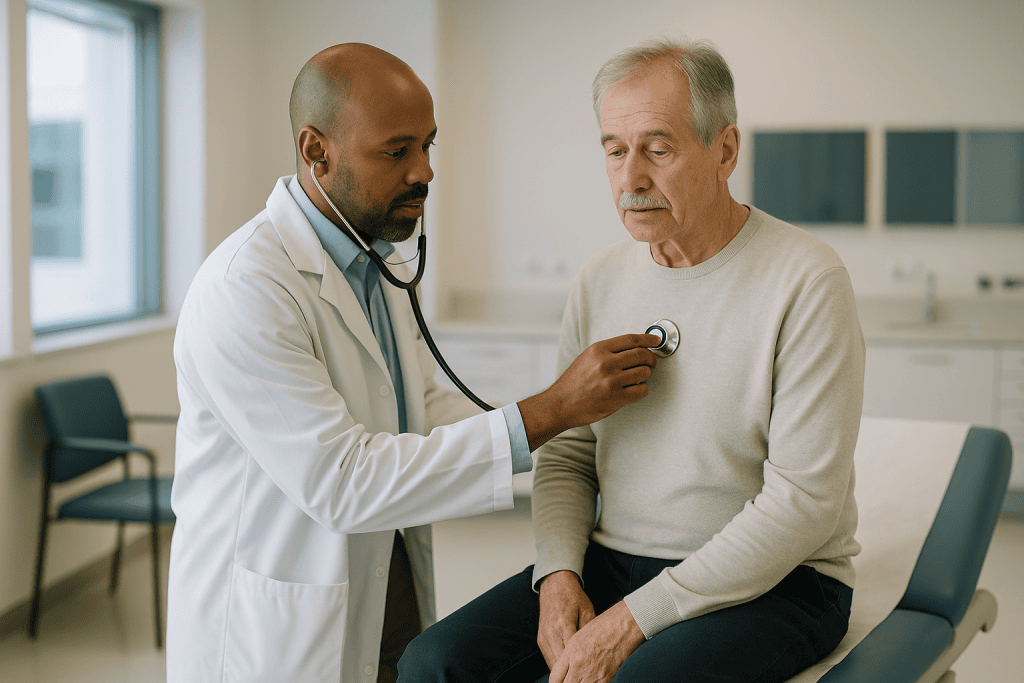
The vital signs come next, and they carry more weight than most people expect. A rapid breathing rate, a fast heart rate, a high or unusually low temperature, and low blood pressure are among the findings clinicians use to grade severity. New confusion in an older adult is treated as an important warning rather than a side note.
Then the stethoscope. Healthy lungs make a soft, breezy sound as air moves in and out. When air sacs are filled with fluid, the clinician may hear crackles, a fine popping or velcro-like sound as collapsed sacs snap open, usually concentrated over one area. Breath sounds can also be quieter than normal over a consolidated zone, or the voice may transmit unusually clearly through it. Tapping the chest wall may produce a duller note over dense, fluid-filled tissue.
These findings are suggestive rather than conclusive. Crackles appear in other conditions, including heart failure, and some people with proven pneumonia sound almost normal. That is precisely why the exam rarely stands alone. It tells the clinician where to look and how urgently, and it is the reason a chest X-ray is usually ordered when the story and the sounds point toward the air sacs rather than the airways.
Pneumonia chest X-ray results: what the picture shows and what it misses
The chest X-ray remains the workhorse test. It takes a few minutes, uses a small dose of radiation, and gives a two-dimensional shadow picture of the lungs, heart and ribs. Healthy lung tissue is mostly air, so it appears dark. Infected, fluid-filled tissue blocks more of the beam and shows up as a pale, cloudy area that radiologists call consolidation or an infiltrate. Either word simply means a region of lung that should be full of air is full of something else.
Doctors read the film for three things. The pattern of shadowing can hint at the cause: a dense patch confined to one lobe is classic for bacterial infection, while patchy or streaky changes across both lungs are more typical of viral or so-called atypical organisms. The extent matters, because involvement of several lobes signals a heavier illness. The X-ray also reveals complications such as a pleural effusion, a collection of fluid between the lung and the chest wall, which may need its own attention.
The test has real limits, and honesty about them prevents confusion. Early in the illness, before fluid has accumulated, the film can look clear even when infection is under way, so a clinician who strongly suspects pneumonia may treat and repeat the imaging. People who are dehydrated or have existing lung scarring can be harder to read. The X-ray also cannot name the germ; it shows the damage, not the culprit.
Shadows linger after recovery. The Mayo Clinic notes that clinicians may order a follow-up X-ray to confirm the infection has cleared, and the NHS advises this at roughly six weeks for people at higher risk of complications, including smokers and those over 50, mainly to ensure nothing else is hiding behind the original shadow.
Blood tests for pneumonia: what each result tells the care team
Blood tests do not diagnose pneumonia on their own, but they answer questions the X-ray cannot. Think of them as a readout of how hard the body is fighting and how well its systems are holding up.

A complete blood count measures the cells circulating in the blood. A raised white blood cell count is the classic signature of bacterial infection, because these cells multiply to attack invaders; a very low count is also concerning, as it can mean the marrow is overwhelmed. The Cleveland Clinic lists this count among the standard tests when pneumonia is suspected.
C-reactive protein, usually shortened to CRP, is a protein the liver releases within hours of inflammation beginning. High levels support the presence of a significant infection and can be rechecked over days to see whether treatment is working. Procalcitonin is a related marker that tends to rise more with bacterial than viral infection; clinicians sometimes use it to help judge whether antibiotics are likely to be useful, though guidance treats it as a supporting clue rather than a deciding vote.
Kidney and liver function tests, electrolytes and blood glucose reveal whether the infection is stressing other organs, which directly influences whether someone is safe to recover at home. In sicker patients, an arterial blood gas, drawn from an artery rather than a vein, gives a precise measure of oxygen and carbon dioxide levels and the blood’s acidity.
Blood cultures are different in purpose. A sample is incubated to see whether bacteria grow, which identifies the organism when infection has spilled into the bloodstream. The Mayo Clinic notes they are mostly reserved for people ill enough to be admitted, since results take a day or more and are often negative in milder cases.
What an oxygen reading really means when pneumonia is suspected
The small clip that glows red on your fingertip is a pulse oximeter. It shines light through the nail bed and measures how much of that light is absorbed by oxygen-carrying hemoglobin, then reports the result as an oxygen saturation percentage, often written SpO2. The Cleveland Clinic gives a typical range for healthy adults of 95 to 100 percent.
Why does this matter so much in pneumonia? Fluid-filled air sacs cannot pass oxygen into the blood efficiently. As more of the lung is affected, saturation falls, and that drop is one of the most objective signals of severity a clinician has. It often comes before a person feels obviously breathless, which is why the reading is taken before anyone reaches for an X-ray form.
Clinicians interpret the number in context. Someone with long-standing COPD may live comfortably at a saturation that would alarm a doctor in a previously healthy 30-year-old. Cold hands, nail polish, poor circulation and movement all degrade the signal, and there is evidence that readings can be less accurate in people with darker skin, so a borderline result is usually confirmed by repeat measurement or by an arterial blood gas.
A low reading changes the plan in concrete ways. It is a core reason for hospital admission, because supplemental oxygen can be delivered and monitored there. It also prompts closer observation of breathing rate and effort, since the two tend to deteriorate together.
For people recovering at home, a clinician may suggest a home oximeter and set individual thresholds for when to call. Those thresholds are personal, based on your baseline and your condition, and should come from your own care team rather than from a general article.
Sputum, swabs and urine tests: identifying the germ behind pneumonia
Knowing that the lung is infected is one thing; knowing what is infecting it is another. A range of samples can point to the organism, and the choice depends on how ill the person is and what the team suspects.
A sputum sample is phlegm coughed up from deep in the chest, ideally first thing in the morning. In the lab it is examined under a microscope and cultured to see which bacteria grow. The Mayo Clinic lists this among routine tests, while acknowledging its practical weaknesses: many people cannot produce a good sample, saliva contaminates it easily, and results take a day or two. When it works, it can confirm a specific bacterium and show which antibiotics it responds to.
Nose and throat swabs are analyzed with molecular tests that detect the genetic material of viruses such as influenza, respiratory syncytial virus and the virus that causes COVID-19, as well as some bacteria that cause atypical pneumonia. Results can return within hours, and a positive viral result may steer the team away from unnecessary antibiotics.
Urine tests may sound out of place, but two important bacteria, the pneumococcus and Legionella, shed fragments that can be detected in urine quickly. These are typically used in people sick enough to be admitted, where speed matters.
In severe or puzzling cases, a bronchoscopy may be considered. A thin flexible tube is passed through the nose or mouth into the airways so that fluid can be washed into a small area and collected directly, avoiding contamination from the mouth. The Mayo Clinic reserves this for people who are not improving as expected.
Many pneumonias are never matched to a named organism, and that is normal. Treatment often begins before results return, then is adjusted once they do.
When is a CT scan or lung ultrasound used to diagnose pneumonia?
A plain X-ray answers most questions, but not all of them. A CT scan, short for computed tomography, takes a rapid series of X-ray images from many angles and assembles them into detailed cross-sections of the chest. It picks up small or subtle areas of consolidation that a flat film can hide behind the heart or diaphragm, and it distinguishes infection from other causes of shadowing, such as a blood clot in the lung, a collapsed segment or a tumor.
The Mayo Clinic describes CT as the next step when pneumonia is not clearing as expected, when the person is severely ill, or when the X-ray is ambiguous. It is also valuable in people with existing lung disease whose baseline films already look abnormal, and in those whose immune systems are suppressed, where infections can behave in unusual ways. The trade-off is a higher radiation dose and, for some scans, an injected contrast dye that requires a kidney check first.
Lung ultrasound has grown in use, particularly in emergency departments and intensive care units. A handheld probe is pressed against the chest wall, and consolidated lung, pleural fluid and certain patterns of inflammation produce recognizable images at the bedside within minutes. There is no radiation, which makes it attractive for children and pregnant patients, and it can be repeated as often as needed to track change. Its accuracy depends heavily on the skill of the operator, so it usually supplements rather than replaces conventional imaging.
If a pleural effusion is large, a sample of the fluid may be drawn through a fine needle under ultrasound guidance and sent for analysis, both to relieve breathlessness and to check whether the fluid itself is infected, which changes management.
Who gets the full diagnostic workup, and who is asked to wait and watch
Testing is not one-size-fits-all, and understanding why can spare frustration on both sides of the desk. Clinicians match the depth of investigation to the likelihood of pneumonia and to the consequences of missing it.
A previously healthy adult with a few days of cough, a mild fever and normal vital signs, whose chest sounds clear, most often has a viral respiratory infection or acute bronchitis. Guidance from bodies such as the NHS supports managing these without imaging or blood tests, with clear instructions to return if things change. Ordering an X-ray for every cough would expose many people to radiation and expense for very little gain, and it would not change their care.
The threshold drops sharply for people at higher risk of serious illness. The CDC identifies adults aged 65 and older, children under five, and people with chronic heart, lung, liver or kidney disease, diabetes, weakened immunity, or a history of smoking as more likely to develop severe pneumonia. In these groups, a lower oxygen reading, a raised breathing rate or a single focal area of crackles usually earns imaging and blood work promptly.
Severity scoring helps decide the setting. Clinicians combine findings such as confusion, breathing rate, blood pressure and age into structured scores; a low score supports home care with a follow-up plan, while a higher score points toward admission and the broader panel of cultures, urine tests and possibly CT described earlier.
Being asked to wait is not the same as being dismissed. It reflects a judgment that the current picture does not need imaging, paired with an explicit safety net. If you are sent home to watch and wait, make sure you leave knowing exactly which changes should bring you back.
Pneumonia diagnostic tests compared at a glance
Seeing the tests side by side makes the logic of the pathway clearer. Each answers a different question, and none is expected to do the whole job.
| Test | What it measures | Main question it answers | Typical turnaround | Key limitation |
|---|---|---|---|---|
| Physical exam and vital signs | Breath sounds, temperature, pulse, breathing rate, blood pressure | Does this look like lung infection, and how sick is the person? | Minutes | Findings overlap with other conditions |
| Pulse oximetry | Blood oxygen saturation | Is oxygen exchange compromised? | Seconds | Affected by circulation, movement, skin tone |
| Chest X-ray | Shadowing in lung tissue, fluid around the lung | Is there consolidation, and how extensive? | Minutes to an hour | Can look normal very early; cannot name the germ |
| Complete blood count, CRP | White cells, inflammatory proteins | How strong is the inflammatory response? | Hours | Non-specific; raised in many illnesses |
| Sputum or blood culture | Bacterial growth | Which organism, and which antibiotics does it respond to? | One to three days | Often negative or contaminated |
| Viral swab (molecular) | Viral genetic material | Is a virus such as influenza or SARS-CoV-2 responsible? | Hours | Does not exclude a bacterial co-infection |
| Urine antigen tests | Bacterial fragments | Is pneumococcus or Legionella involved? | Hours | Limited to two organisms |
| CT scan | Detailed cross-sectional images | What is really causing an unclear or persistent shadow? | Under an hour | Higher radiation; contrast may be needed |
The turnaround column explains a common frustration: treatment usually starts before every result is back. Cultures need time for organisms to grow, so clinicians begin with the most likely cause and refine once the lab reports. Turnaround times here are typical ranges described by the Mayo Clinic and Cleveland Clinic; your own results may take longer depending on the laboratory and the time of day.
Early warning signs of pneumonia versus a cold or bronchitis
People searching for the early warning signs of pneumonia usually want to know one thing: when does a chest infection stop being something to ride out and start being something to get checked? The honest answer is that no list of symptoms can diagnose pneumonia at home, because the same features appear in milder illnesses. What the pattern can do is tell you when an examination is worth having.
Clinicians pay attention to trajectory. A cold that seemed to be improving and then turns, with a new fever, a deeper and more productive cough, or breathlessness that was not there before, is a classic story for a bacterial pneumonia following a viral infection. Pain on one side of the chest that sharpens with each breath suggests the inflammation has reached the lining of the lung, which colds and simple bronchitis rarely do.
The character of the breathing is another clue. Breathlessness at rest or with light activity, a breathing rate that feels fast even when sitting still, or a sense of not being able to fill the lungs all point beyond the airways. The NHS also highlights that older adults may present differently: confusion, unusual drowsiness or a fall can be the leading feature, with cough and fever surprisingly muted.
Bronchitis, by contrast, tends to bring a persistent cough with only mild systemic illness and normal oxygen readings. It is often viral and settles on its own, though the cough can linger for weeks.
The takeaway is not to memorize symptoms but to notice change and speed. A chest illness that is getting worse rather than better after several days, or that affects breathing, warrants a clinician’s assessment, where the exam and, if needed, an X-ray can settle the question properly.
What the days and weeks after a pneumonia diagnosis usually look like
Once the diagnosis is made, the picture changes from detective work to monitoring. What happens next depends on where care is delivered, but the rhythm is broadly similar.
For people managed at home, most bacterial pneumonias are treated with antibiotics chosen by the prescribing clinician according to the likely organism, local resistance patterns and individual factors such as allergies and kidney function. Viral pneumonias are managed with rest, fluids and, where relevant, antiviral medicines decided on by the treating team. The Mayo Clinic notes that people generally begin to feel better within a few days of starting appropriate treatment, though fatigue commonly outlasts the fever. A review visit or phone check within a few days is typical, and it is the moment to report anything that has not improved.
In hospital, the first days revolve around oxygen support, fluids and repeated vital signs, with blood tests rechecked to see whether inflammation markers are falling. As results from cultures and urine tests arrive, treatment may be narrowed. Discharge usually follows once oxygen levels are stable on room air, or on a home oxygen plan, and the person can eat, drink and move about safely.
Recovery is slower than most people expect. The NHS describes a typical course in which fever has usually settled within about a week, chest pain and phlegm have reduced by around four weeks, cough and breathlessness have eased by about six weeks, and most symptoms have resolved by three months, with full energy returning over roughly six months for some people. Those are typical ranges from population guidance, not a promise, and older adults or those with other conditions may take longer.
A follow-up chest X-ray, as discussed earlier, is arranged for selected higher-risk groups to confirm the shadow has cleared.
Can pneumonia go away on its own? What the evidence supports
This is one of the most common questions people type into a search engine, usually while deciding whether to book an appointment. The candid answer has two parts.
Some pneumonias do resolve without specific treatment. Many viral pneumonias, particularly in otherwise healthy adults, are managed with supportive care alone because antibiotics have no effect on viruses and effective antivirals exist for only a handful of them. The body’s immune response clears the infection over one to several weeks, and the role of medical care is to monitor oxygen and watch for complications. Mild, so-called walking pneumonia caused by atypical bacteria can also be relatively self-limiting in younger people, though clinicians often still treat it to shorten the illness and reduce spread.
Bacterial pneumonia is a different matter. Left untreated, it can progress to a lung abscess, an infected collection of fluid around the lung, or sepsis, the body’s dangerous overreaction to infection that can cause organ failure. The CDC notes that pneumonia remains a leading cause of hospitalization and death from infection in the United States, with risk concentrated in older adults, young children and people with chronic illness. Antibiotics, when a bacterial cause is likely, substantially change that course.
The practical problem is that you cannot reliably tell at home which kind you have. Viral and bacterial pneumonia produce overlapping symptoms, and the tests that separate them are the ones described in this article. That is why the question is better reframed: not whether pneumonia can resolve without help, but whether this particular illness is safe to watch. A clinician with a stethoscope, an oximeter and access to an X-ray can answer that in a way no online article can. If you are unsure, the assessment is worth having.
What people often get wrong about how pneumonia is diagnosed
Misunderstandings about diagnosis cause real problems, from unnecessary worry to delayed care. A few deserve correcting.
The first is that a normal chest X-ray rules pneumonia out. Early in the illness, before fluid has built up, the film can be clear despite genuine infection. Clinicians who see a convincing story and examination may treat on clinical grounds and repeat the imaging, and the Mayo Clinic recognizes CT as the next step when a plain film is inconclusive.
The second is the reverse: that a shadow on the X-ray must mean pneumonia. Fluid from heart failure, a blood clot in the lung, scarring from old infection and certain tumors can all produce pale areas. The picture is read alongside symptoms, blood tests and history, and a lingering shadow after recovery is one reason follow-up imaging is offered to higher-risk groups.
Third, many people believe green or yellow phlegm proves a bacterial infection that needs antibiotics. Color reflects the presence of white blood cells and is common in viral illness too. Clinicians use the whole picture, and increasingly inflammatory markers, to decide whether antibiotics are likely to help.
Fourth, the idea that you cannot have pneumonia without a high fever. Older adults and people with weakened immunity often run little or no temperature; confusion, weakness and fast breathing may be the only signs, as the NHS highlights.
Fifth, that a home oximeter reading in the normal range means everything is fine. Saturation can hold up until a fair portion of the lung is involved, and the device is a supplement to clinical judgment, not a replacement for it.
Finally, some assume a normal stethoscope exam settles the question. Sound travels poorly through certain areas of the chest, and deep-seated infection can be silent. When the story is convincing, imaging is what settles it.
Questions to ask your care team about your pneumonia diagnosis
Consultations move quickly, and it is easy to leave with a diagnosis but without the understanding you wanted. Writing down a few questions beforehand helps you use the time well and keeps decisions where they belong, with the clinicians who know your case.
- What in my examination or tests points to pneumonia, and how confident are you in the diagnosis right now?
- Do you think the likely cause is bacterial, viral or uncertain, and does that change the treatment you are recommending?
- Which tests are still pending, when will results be back, and how will I hear about them?
- What was my oxygen reading today, and is there a level at which you would want me to seek care urgently?
- Are there any other conditions you are still considering, and what would prompt a CT scan or further tests?
- Why is home care, or hospital admission, the right setting for me specifically?
- What does a typical recovery look like for someone with my health background, and at what point would slow progress worry you?
- Will I need a follow-up chest X-ray, and if so, roughly when?
- Should my regular medicines continue unchanged while I am being treated?
- Am I likely to be contagious, and for how long should I limit contact with others, especially older or vulnerable people?
- Are there vaccinations you would recommend once I have recovered, to lower my risk of another episode?
You are entitled to answers in plain language, and to ask for a written summary of what was found and what happens next. If a family member usually helps with your care, having them present or on speakerphone means the plan is heard twice. Bring a list of your medicines and allergies; kidney function, existing prescriptions and past reactions all shape which treatments are appropriate, and your prescribing clinician will weigh those factors in a way no general guidance can.
When to call your doctor: red-flag signs during and after a pneumonia diagnosis
Most people with pneumonia recover steadily once treatment starts. The purpose of this section is to make sure the minority who deteriorate are seen quickly, because pneumonia can worsen over hours rather than days.
Seek urgent care, or call emergency services, if you or someone you are looking after develops any of the following, drawn from guidance published by the NHS and Mayo Clinic:
- Severe difficulty breathing, breathing that is very fast, or struggling to speak in full sentences
- Lips, face or fingertips turning blue or gray, or a home oxygen reading below the threshold your clinician set for you
- Chest pain that is severe, persistent, or accompanied by coughing up blood
- New confusion, unusual drowsiness, difficulty waking, or fainting
- Cold, clammy or mottled skin, very little urine, or a rapid heartbeat with dizziness, which can signal sepsis
- A high temperature that does not respond to simple measures, or a temperature that is unusually low
- In a child: grunting or flaring nostrils with each breath, the skin pulling in between the ribs, refusal to drink, or becoming floppy or unresponsive
Contact your doctor promptly, without waiting for the next scheduled review, if symptoms have not begun to improve after a few days of treatment, if a fever returns after settling, if breathlessness is worsening rather than easing, or if you develop new symptoms such as a swollen, painful leg or sudden sharp chest pain, which can point to a blood clot.
People at higher risk, including adults over 65, young children, pregnant women and anyone with chronic heart, lung or kidney disease, diabetes or a weakened immune system, should have a lower threshold for calling. The same applies if you live alone and cannot easily be checked on.
When in doubt, call. Clinicians would far rather reassure you over the phone than see a preventable deterioration arrive by ambulance. Every decision about tests, treatment and where care happens rests with your treating team, and they can only make good decisions if they know what is changing.
Frequently asked questions
How do doctors tell if you have pneumonia?
Doctors combine your symptom history, a physical examination and tests. They listen for crackles over the lungs, check temperature, pulse, breathing rate and oxygen saturation, and usually order a chest X-ray to look for consolidation, the pale shadow of fluid-filled air sacs. Blood tests measure inflammation and organ function, and sputum, swab or urine tests may identify the organism. No single finding settles it; the overall pattern does.
Can pneumonia go away on its own without antibiotics?
Sometimes, particularly with viral pneumonia in otherwise healthy adults, where antibiotics have no effect and the immune system clears the infection with supportive care. Bacterial pneumonia, by contrast, can progress to abscess, infected fluid around the lung or sepsis if untreated. Because the two cannot be reliably distinguished at home, a clinical assessment is the safe way to decide whether watching and waiting is appropriate for you.
What are the early warning signs of pneumonia that should prompt a doctor's visit?
Clinicians look for a chest illness that worsens rather than improves after several days, especially a cold that seems to recover and then brings new fever, deeper cough and breathlessness. Chest pain that sharpens with each breath, rapid breathing at rest, and in older adults new confusion or unusual drowsiness are also concerning. These features do not diagnose pneumonia, but they justify an examination and, if needed, an X-ray.
What do pneumonia chest X-ray results look like?
Infected lung tissue appears as a pale, cloudy area called consolidation or an infiltrate, because fluid blocks more of the X-ray beam than air does. A dense patch in one lobe is classic for bacterial infection, while patchy changes in both lungs suggest viral or atypical causes. The film also shows fluid around the lung. It cannot identify the germ, and early in the illness it can look normal.
Which blood tests for pneumonia are usually done and why?
A complete blood count checks white cell levels, which rise with bacterial infection. C-reactive protein and sometimes procalcitonin measure the intensity of inflammation and help clinicians judge whether antibiotics are likely to help. Kidney and liver tests, electrolytes and glucose show how other organs are coping, which influences whether home care is safe. Blood cultures, which try to grow bacteria from the bloodstream, are mainly used in people admitted to hospital.
What oxygen level is concerning with pneumonia?
Healthy adults typically read between 95 and 100 percent on a pulse oximeter, according to the Cleveland Clinic. Lower readings indicate that fluid-filled air sacs are struggling to pass oxygen into the blood and are a key reason for hospital admission. The right threshold for you depends on your baseline and any lung disease, so ask your clinician for a personal number rather than relying on a general figure.
How long does it take to get pneumonia test results?
The exam and oxygen reading are immediate, and a chest X-ray is usually read within minutes to an hour. Routine blood tests return within hours. Molecular viral swabs typically report the same day. Sputum and blood cultures need one to three days for organisms to grow, according to descriptions from the Mayo Clinic, which is why treatment often begins before every result is available and is adjusted afterward.
How can I prevent pneumonia when I already have a cough?
You cannot guarantee prevention, but you can lower the odds of a cold or bronchitis progressing. Rest, stay well hydrated, avoid smoke exposure, and wash hands often to limit new infections. Staying up to date with influenza, COVID-19 and pneumococcal vaccines, as the CDC recommends for eligible groups, reduces the risk of the most common causes. If your cough is worsening after several days or breathing changes, seek an assessment rather than waiting.
Why did my doctor order a CT scan instead of just an X-ray?
A CT scan gives detailed cross-sectional images that reveal small or hidden areas of infection and separate pneumonia from look-alikes such as a blood clot, collapsed lung segment or tumor. The Mayo Clinic describes it as the next step when a plain X-ray is unclear, when pneumonia is not improving as expected, or when someone is severely ill or has existing lung disease that complicates the ordinary film.
Will I need a follow-up chest X-ray after pneumonia?
Not everyone does. The NHS advises a follow-up X-ray at around six weeks for people at higher risk of complications, such as smokers and adults over 50, mainly to confirm the shadow has cleared and that nothing else was hidden behind it. Shadows can lag well behind symptom recovery, so a persistent change on an early repeat film is not by itself alarming. Your clinician will decide based on your risk.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Can Bronchitis Turn Into Pneumonia? Complications Doctors Watch For During Treatment
Bronchitis does not usually turn into pneumonia, but the same infection can spread from the large breathing tubes into the air sacs, and a…