

How Long Does VNS Recovery Take? Incision Healing and the First Programming Visit

Key Takeaways
- VNS surgery involves two small incisions in the neck and chest, no opening of the skull, and typically a same-day or one-night hospital stay.
- The incisions generally heal over about two weeks, while the device is usually left switched off until a programming visit two to four weeks after surgery.
- Early hoarseness usually comes from swelling or the breathing tube; hoarseness that later follows the stimulation cycle is the device working, not nerve injury.
- Mayo Clinic reports that VNS rarely stops seizures completely, that responders typically see a 20 to 40 percent reduction, and that benefit can take months to two years to appear.
- Each magnet swipe delivers a preset extra burst, so a swipe cannot exceed the programmed limit, but frequent swiping adds stimulation time and more throat and voice side effects.
- The left vagus nerve is chosen because the right one sends more branches to the heart's pacemaker region, and the nerve is wrapped, never cut, during the procedure.
VNS recovery time is usually short compared with brain surgery. The operation typically takes one to two hours, most people go home the same day or after one night, and the neck and chest incisions generally heal over about two weeks. Soreness and a hoarse voice usually ease within days to weeks. The device is normally switched on at a programming visit two to four weeks after surgery, then adjusted gradually over months.
The morning after surgery, the bathroom mirror tells a modest story: a small dressing tucked into a crease on the left side of the neck, another just below the collarbone, and a voice that sounds as if it belongs to someone recovering from a cold. On the kitchen counter sits a folder with a follow-up appointment circled, the one where a neurologist will hold a wand over the chest and turn the device on for the first time.
People researching VNS recovery time tend to want two answers that no leaflet quite gives together: how long the body needs to heal, and how long before the treatment does anything. Those are different clocks. The first runs in days and weeks. The second runs in months and sometimes years.
This explainer follows both, from the operating room to the first programming visit and the slow adjustment period that follows, with the evidence laid out as it stands rather than as anyone wishes it were.
What actually happens during VNS surgery?
Vagus nerve stimulation, or VNS, is a treatment in which a small implanted device sends mild, timed electrical pulses to the vagus nerve in the neck. The vagus nerve is a long nerve running from the brainstem through the neck into the chest and abdomen, carrying signals in both directions between body and brain. Pulses delivered to it travel upward and appear to alter electrical activity in brain regions involved in seizures and mood, although the precise mechanism is still being studied.
The operation is not brain surgery. Nothing is opened in the skull. Under general anesthesia, the surgeon makes two incisions: one in a natural crease on the left side of the neck, and one below the left collarbone. Through the neck incision, a thin wire called a lead is wrapped around the left vagus nerve using soft, coiled electrodes. The left side is chosen because the right vagus nerve sends more branches to the heart’s natural pacemaker region. The lead is then passed under the skin to the chest incision, where it connects to a flat pulse generator, roughly the size of a large coin, that sits in a small pocket beneath the skin and fat.
Once the connection has been tested, both incisions are closed with dissolvable stitches, skin glue, or adhesive strips and covered with light dressings. Mayo Clinic describes the procedure as typically taking around one to two hours, with many people going home the same day and others staying one night for observation. The generator is usually left switched off at this point. Turning it on happens at a separate visit, once the tissue around the electrodes has settled, which is why the early part of VNS recovery time is about healing rather than treatment.
VNS recovery time at a glance: a typical timeline
Every surgical team writes its own instructions, and the ranges below are typical rather than promised. They come from patient information published by Mayo Clinic, Cleveland Clinic, and Johns Hopkins Medicine, and they describe what most adults experience after an uncomplicated implant.

| Stage | Typical window | What usually happens |
|---|---|---|
| Surgery | About 1–2 hours | General anesthesia; two incisions; generator left off |
| Hospital stay | Same day to one night | Observation, pain control, first walk, discharge teaching |
| Early soreness | First few days | Tenderness at chest pocket and neck; sore throat; hoarseness |
| Incision healing | Roughly 2 weeks | Skin edges seal; strips or glue lift off; bruising fades |
| First programming visit | About 2–4 weeks after surgery | Device switched on at a low setting; sensations checked |
| Adjustment period | Weeks to months | Settings raised gradually at follow-up visits |
| Judging benefit | Months, sometimes up to 2 years | Seizure diaries reviewed; medicines continue |
Two features of this table deserve emphasis. First, the physical recovery is compressed into the top half; by the time the incisions have healed, the treatment has barely begun. Second, the bottom rows stretch far longer than most people expect. Mayo Clinic notes that it can take months, and in some cases a year or two, before any effect on seizures becomes clear. Holding both halves of the timeline in mind is the single most useful thing a person can do in the first month, because it stops a quiet, uneventful device from feeling like a failed one.
How painful is VNS surgery? What the first 48 hours usually feel like
Honest answer: it is sore, but most people describe it as far less painful than they feared. The chest incision tends to bother people more than the neck one, because the surgeon creates a small pocket for the generator, and the muscle and skin around it protest when you reach, twist, or roll over in bed. The neck incision often feels more like a stiff pull than a sharp pain, especially when turning the head.
A scratchy or sore throat is common in the first day or two and has two sources. One is the breathing tube used during general anesthesia. The other is gentle handling of the tissue around the vagus nerve, which lies close to the structures that move the vocal cords. Mayo Clinic lists hoarseness and voice change among the expected effects after implantation, and in the immediate postoperative period these are usually tied to swelling rather than to stimulation, since the device is still off.
Pain relief is typically a short course of medicine arranged by the surgical team before discharge, sometimes over-the-counter options alone, sometimes a brief prescription. This article does not discuss specific medicines or amounts; the plan belongs to the prescribing clinician and depends on the person’s other medicines, including their seizure medicines. What matters more than any tablet is the practical side: keeping the arm on the operated side from lifting anything heavy, sleeping slightly propped up if the neck feels tight, and applying a wrapped cold pack for short spells if the team allows it.
Bruising around the chest pocket can look dramatic on day two or three and then fade over the following week. A small firm ridge along either scar is normal healing tissue and softens over months.
VNS incision healing: caring for the neck and chest wounds
Both incisions are closed wounds, meaning the skin edges have been brought together with stitches, glue, or strips. MedlinePlus advice on closed surgical wounds applies well here: keep the area clean and dry, follow the surgeon’s specific timing for the first shower, avoid soaking in a bath, pool, or hot tub until cleared, and resist the urge to peel at glue or strips, which usually loosen and fall away on their own within about one to two weeks.
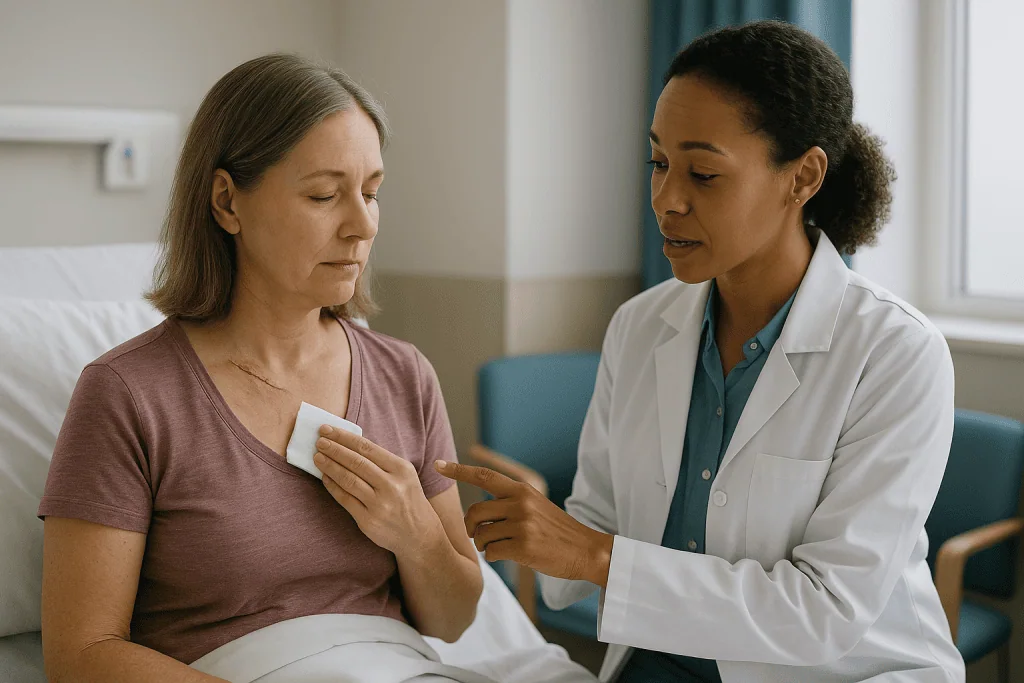
Showering is generally permitted after the initial dressing period the team specifies. Let water run over the incisions rather than scrubbing them, pat dry with a clean towel, and leave them open to the air unless told otherwise. Lotions, ointments, and powders are best avoided on the wound line until the skin has sealed, again unless your team recommends a particular product.
What normal healing looks like:
- Mild redness confined to a thin border along the incision, fading week by week.
- A little clear or faintly pink fluid on the dressing in the first day or two.
- Itching as the skin knits, which is annoying but expected.
- Numbness or tingling in the skin around the chest pocket, sometimes lasting months, as small skin nerves recover.
What is not part of normal healing is covered in the section on when to call your doctor: spreading redness, warmth, thick or foul-smelling discharge, a wound that opens, or fever. Infection around an implant is uncommon but taken seriously, because the device itself can become involved.
Scars mature slowly. The neck scar often settles into the skin crease and becomes hard to spot; the chest scar sits under most clothing. Sun protection on healing scars during the first year helps them fade evenly. Some people notice the outline of the generator under thin skin; that is expected and not a sign of a problem.
What the first two weeks of VNS surgery recovery usually look like
The first two weeks are quieter than most people expect. There is no device to manage, no magnet to learn yet, and no change in seizure medicines. The job is to heal.
Days one to three: fatigue from anesthesia, soreness that peaks and then begins to ease, short walks around the house, and gentle attention to the dressings. Sleeping can be awkward; a pillow under the operated arm takes pressure off the chest pocket. Talking may feel tiring if the voice is hoarse, and that is a reasonable excuse to let others do more of it.
Days four to seven: most people are moving comfortably indoors, showering, and reducing pain relief. The main restriction is mechanical. Surgical teams generally ask people to avoid heavy lifting, vigorous overhead reaching, and forceful twisting of the neck while the lead settles into position along the nerve and the tissue around the generator firms up. Your team will give a specific limit and a specific duration; follow theirs rather than a general figure.
Week two: bruising fades, strips or glue lift, and many people with desk-based work return, sometimes with reduced hours. Physically demanding jobs wait longer. Driving is a separate question, because it depends on seizure control and local licensing rules rather than on the wound, and the neurologist rather than the surgeon usually advises on it.
Johns Hopkins Medicine and Cleveland Clinic both describe the postoperative phase as brief, with the longer commitment being the series of programming visits that follow. Treat the two weeks as the calm before that work begins: eat normally, walk daily, protect the incisions, and keep the seizure diary going, because the neurologist will want a clear baseline from before the device is turned on.
The first programming visit: why the device stays off at first
Programming means adjusting the settings of the implanted generator from outside the body. The neurologist or nurse holds a small wand connected to a tablet or programmer over the chest, reads the device, and changes its parameters wirelessly through the skin. Nothing pierces the skin, and the visit is painless apart from the sensations of stimulation itself.
The generator is usually left off for the first weeks after implantation. Mayo Clinic and Cleveland Clinic both describe the first activation as happening around two to four weeks after surgery. The pause serves two purposes. It lets swelling around the electrodes settle so that the nerve receives a consistent signal, and it lets the person recover from the operation before adding a new set of sensations to interpret. Some programs switch the device on at a very low level in the operating room; most wait.
At the visit, the clinician starts at a low setting and watches how you respond. VNS works in cycles: a short burst of stimulation, then a longer rest, repeated around the clock. During each burst many people feel a tickle or tightness in the throat, a slight vibration, or a change in voice, which is why bringing someone who knows your normal voice can be surprisingly useful. Between bursts, most people feel nothing.
Settings are then raised gradually at follow-up visits spaced weeks apart, a process Johns Hopkins Medicine describes as continuing over several months. The pace is set by tolerance, not by a fixed schedule; a persistent cough or breathlessness slows things down. You will also be shown how to use the handheld magnet and given written instructions for it, which the next sections cover. Ask for a card or note listing your current settings and the date of your next adjustment.
How long does it take for the vagus nerve to heal, and can a VNS damage it?
Two of the most searched worries about VNS deserve a direct answer. The vagus nerve is not cut during the operation. The electrodes are soft helical coils that wrap loosely around it, and the surgeon works to keep the nerve’s own blood supply intact. What the nerve experiences is handling and mild swelling, and that irritation typically settles over the same weeks that the incisions heal, which is one reason the device is left off at first.
Can the nerve be damaged? Rarely, yes. Mayo Clinic lists vocal cord paralysis among the uncommon surgical risks, and it can occur if the nerve branch that moves the left vocal cord is stretched or injured. Most postoperative hoarseness is temporary and traceable to swelling or to the breathing tube; hoarseness that persists for many weeks after surgery, or difficulty swallowing that does not improve, is a reason to be reassessed, sometimes with a look at the vocal cords by an ear, nose and throat specialist. Nerve tissue that has been bruised rather than severed recovers slowly, over weeks to months, and the outcome is judged over that longer window.
Once the device is on, the stimulation itself is designed to fall within limits the nerve tolerates. Side effects during stimulation, such as voice change, cough, or throat tingling, reflect the nerve doing exactly what it is asked to do rather than being harmed, and they usually lessen as the body adapts or as settings are adjusted. Long-term studies summarized by Cleveland Clinic and the National Institute of Neurological Disorders and Stroke have not shown progressive nerve injury from chronic stimulation in the general population of users. The more realistic long-term concerns are mechanical: a lead that fractures after years of neck movement, or a generator battery that runs down, both of which are addressed with revision surgery rather than being signs of nerve damage.
Who is VNS usually for, and who is usually asked to wait?
VNS is most often offered to people with drug-resistant epilepsy, meaning seizures that continue despite adequate trials of at least two appropriate anti-seizure medicines. The NHS describes it as an option when medicines have not controlled seizures and when surgery to remove the seizure focus is not possible or has not helped. In the United States it is approved for focal epilepsy in adults and children aged four and older, according to Mayo Clinic. Cleveland Clinic notes that it is also approved for treatment-resistant depression and, in a different form, for rehabilitation of arm function after stroke; those uses have their own selection criteria and are not covered in detail here.
Who tends to be asked to wait or to consider something else:
- People whose seizures come from a single, clearly identified area that could be removed surgically, since resective surgery has a better-established chance of stopping seizures and is generally evaluated first.
- Anyone with an active infection, particularly skin infection near the planned incisions, until it has cleared.
- People with certain heart rhythm problems, significant lung disease, or untreated obstructive sleep apnea, which Mayo Clinic flags as needing careful review because stimulation can affect breathing during sleep.
- Those who cannot attend the series of programming visits the treatment requires; without them the device offers little.
- People who need frequent MRI scans of the neck or chest, where imaging compatibility must be confirmed with the specific device beforehand.
Pregnancy, planned or possible, is a discussion point rather than an automatic exclusion. Candidacy is decided by an epilepsy team, usually after video EEG monitoring, imaging, and a review of every medicine tried. If a team recommends waiting, the reason is worth asking about, because it is often a step toward a treatment with a stronger chance of helping.
How long before VNS starts to help seizures? Setting realistic expectations
This is where the two clocks of VNS recovery time diverge most sharply. Incisions heal in weeks. Benefit, if it comes, arrives slowly and is measured in a seizure diary rather than felt in the moment.
Mayo Clinic summarizes the evidence this way: VNS rarely stops seizures altogether, most people who respond see seizure frequency fall by roughly 20 to 40 percent, and it can take months, and in some cases a year or two, for the effect to become clear. Cleveland Clinic makes a similar point and adds that improvement often continues to build over time rather than plateauing after the first year. These figures come from observational follow-up rather than from the short randomized trials that first tested the device, and individual results range widely, from no change to substantial reduction.
Several practical consequences follow. Seizure medicines are continued; VNS is added to them, not swapped for them, and any later change to medicines is a decision for the prescribing neurologist based on months of diary data. Seizure severity and recovery time after a seizure are worth recording alongside frequency, because some people report shorter or milder events before they notice fewer of them. Mood, alertness, and sleep are worth noting too, since some people describe changes in these areas, though the evidence for them is less consistent than for seizure frequency.
What this means for the first year: judge nothing in month one, review the diary honestly at each programming visit, and agree with the team in advance how long a fair trial should last before deciding whether the device is helping. A quiet device that has not yet changed anything is not a broken device. A person who expects a switch to flip is set up for disappointment; a person who expects a slow dial is set up to notice real change when it arrives.
Can you overuse a VNS magnet?
The handheld magnet that comes with the device does two things. Swiped briefly across the generator, it triggers an extra burst of stimulation on top of the automatic cycle, which some people use at the start of an aura, a warning sensation before a seizure, or which a companion uses when they see a seizure beginning. Held steadily over the generator, it pauses stimulation for as long as it stays there, which is useful during public speaking, singing, or eating if the on-cycle causes coughing.
Can it be overused? The magnet is not addictive and each swipe delivers a preset extra burst decided by the neurologist, so a single swipe cannot exceed the programmed limit. Repeated swiping in a short period does add up to more stimulation time, and the most likely result is more of the on-cycle side effects: hoarseness, throat tightness, cough, or brief shortness of breath. Cleveland Clinic and Johns Hopkins Medicine describe magnet use as a supplement to, not a replacement for, the automatic settings, and most teams give a written guide on how often to swipe. Follow that guide rather than a general rule.
Two things are worth telling the team promptly. If you find yourself swiping many times a day because seizures seem to be breaking through, that is information the neurologist needs, since it may prompt a change in settings or a look at other causes. If swiping seems to do nothing at all, the device may need checking.
Some newer generators also detect a sharp rise in heart rate, which often accompanies certain seizures, and deliver an automatic extra burst without the magnet. The clinician will explain whether your device has this feature. Keep the magnet away from credit cards, phones, hearing aids, and anyone with a pacemaker, and store a spare where family can find it.
What people often get wrong about VNS recovery time
Misunderstandings about this treatment cluster around a few themes, and each one can make the recovery feel worse than it is.
“It is brain surgery.” It is not. Both incisions are in the neck and chest, no part of the skull is opened, and the hospital stay is usually a day or less. The recovery resembles that from a pacemaker implant more than from a craniotomy.
“The device works as soon as it is implanted.” In most programs it is switched off for two to four weeks, then raised gradually. Even after activation, Mayo Clinic notes that benefit can take months to a year or two to become clear. Feeling no different in the first month is the expected experience.
“Hoarseness means the nerve is damaged.” Early hoarseness is usually swelling or the breathing tube. Later, hoarseness that comes and goes in step with the stimulation cycle is the device working, not injuring. Persistent hoarseness that does not follow the cycle is the version worth reporting.
“I can stop my seizure medicines now.” VNS is an add-on. Any change to medicines is a decision for the prescribing neurologist, made after months of diary data, never on the day of surgery or activation.
“I can never have an MRI again.” Imaging is possible under specific conditions that depend on the exact device and lead. It requires planning with the imaging team, not avoidance.
“A visible generator outline means something has gone wrong.” In slimmer people the coin-shaped device is often visible under the skin. Redness, warmth, or the skin thinning over it are the signs that matter, not the outline itself.
“If it has not helped by six months, it never will.” The published follow-up suggests otherwise for a meaningful share of people, which is why teams ask for patience before drawing conclusions.
Risks, alternatives, and living with the device long term
Surgical risks are those of any small implant operation: infection at either incision, bleeding or bruising, pain, scarring, and the rare nerve injury discussed earlier. Mayo Clinic also lists difficulty swallowing and, uncommonly, vocal cord paralysis. Anesthesia carries its own small risks, which the anesthesiologist reviews beforehand.
Side effects of stimulation are different in character. They occur during the on-phase of each cycle and include voice change or hoarseness, throat tingling or tightness, cough, headache, shortness of breath, and occasionally trouble sleeping. Mayo Clinic and Cleveland Clinic both describe these as generally mild and as tending to fade over time or with adjustment of settings. People with sleep apnea need particular review, because stimulation can affect breathing during sleep.
Alternatives depend on the type of epilepsy. They include further trials of anti-seizure medicines, surgery to remove or disconnect the seizure focus where one can be found, other forms of neurostimulation that place electrodes inside the skull, and dietary therapies such as the ketogenic diet, which the NHS lists among options for some children. None of these is universally better; the epilepsy team weighs them against the individual’s seizure type, imaging, and priorities.
Living with the device involves a few permanent habits. The generator battery lasts several years, with the exact life depending on settings; when it runs low, the generator alone is replaced through the chest incision in a shorter operation, usually leaving the lead in place. Tell every clinician, dentist, and imaging department that you have an implant. Carry the identification card. Ask before any procedure that uses strong magnets, diathermy, or electrical cautery. Airport security scanners are generally passable with the card shown; strong industrial magnets and some theft-detection gates can briefly trigger or pause the device, so walk through them rather than lingering.
Questions to ask your care team
A good consultation before or after VNS surgery leaves you with specific answers rather than general reassurance. These questions are worth bringing on paper, because the moments after a surgeon or neurologist finishes speaking are when they tend to vanish from memory.
Before surgery:
- Why is VNS being recommended for me rather than surgery to remove the seizure focus or a different form of stimulation?
- Will I go home the same day, and who should be with me for the first night?
- Which of my current medicines, including seizure medicines, do I take on the morning of surgery, and who confirms that?
- Will the device be switched on in the operating room or at a later visit?
About the first weeks:
- When may I shower, and how should I care for the glue or strips on the incisions?
- What exactly should I not lift or do with my neck, and for how long?
- When is my first programming visit, how long will it take, and should I bring someone?
- Which changes in my voice, swallowing, or breathing do you want to hear about between visits, and how do I reach the team?
About the longer term:
- How often will settings be adjusted, and how many months will we allow before judging whether the device is helping?
- How should I record seizures, magnet use, and side effects so the diary is useful to you?
- Is my specific device and lead compatible with MRI, and what does the imaging team need to know in advance?
- Roughly how long is the battery expected to last at typical settings, and how will we know it is running low?
Write the answers next to the questions. A folder that holds the settings card, the diary, and these notes becomes the most useful object in the house over the coming year.
When to call your doctor: red-flag signs after VNS surgery
Most of VNS recovery is uneventful, which makes the exceptions easier to recognize. Contact the surgical or neurology team the same day, or seek emergency care if severe, for any of the following.
At the incisions:
- Redness spreading outward from the wound, increasing warmth, or swelling that grows rather than shrinks after the first few days.
- Thick, cloudy, or foul-smelling discharge, or a wound edge that separates.
- Fever or chills in the days after surgery.
- The skin over the generator becoming thin, shiny, or breaking down, at any point in the years after implantation.
Voice, swallowing, and breathing:
- Hoarseness or a weak voice that persists for weeks without improving, or that does not follow the on-off rhythm of the stimulation cycle.
- Difficulty swallowing, choking on liquids, or food sticking.
- Shortness of breath at rest, or new or worsening breathing pauses noticed during sleep by a partner.
Device-related:
- A painful shock or sudden intense stimulation, especially after a fall or blow to the neck or chest.
- Stimulation that becomes constant rather than cyclical, or that stops entirely and does not respond to the magnet.
- A generator that appears to have moved or flipped in its pocket.
Seizure-related:
- Any seizure lasting longer than five minutes, or repeated seizures without full recovery between them, which is a medical emergency regardless of the device.
- A clear increase in seizure frequency or severity compared with the diary baseline.
Hoarseness on the day of surgery, mild soreness that eases each day, faint pink fluid on the first dressing, and itching along the scar are expected and do not need a call. When unsure, call anyway; teams that implant these devices would far rather hear about a false alarm than miss an infection near an implant. Every decision about wound care, settings, and medicines rests with the treating team.
Frequently asked questions
How painful is VNS surgery compared with other operations?
Most people describe VNS surgery as sore rather than severely painful, closer to a pacemaker implant than to brain surgery. The chest pocket where the generator sits tends to ache more than the neck incision, especially when reaching or rolling over. A sore throat and hoarse voice are common in the first days. Pain relief is arranged by the surgical team, and soreness usually eases steadily over the first week.
How long does VNS surgery recovery take before I can return to work?
Many people with desk-based jobs return within about two weeks, once the incisions have sealed and soreness has settled, while physically demanding work waits longer. The limiting factor is usually the restriction on heavy lifting and forceful neck movement while the lead settles, which your surgical team will define. Driving depends on seizure control and local licensing rules rather than on the wound itself.
What does the first programming visit involve?
At the first programming visit, usually two to four weeks after surgery according to Mayo Clinic and Cleveland Clinic, the neurologist holds a wand over the generator and switches it on at a low setting. You will feel a tickle or tightness in the throat and perhaps a voice change during each burst. Settings are then raised gradually over several follow-up visits, and you are taught how to use the magnet.
How long does it take for the vagus nerve to heal after VNS implantation?
The nerve is not cut during VNS surgery; it is wrapped with soft electrodes. Irritation and swelling from handling typically settle over the same few weeks the incisions take to heal, which is why the device is left off at first. If a nerve branch has been bruised, recovery is slower, over weeks to months, and persistent hoarseness or swallowing trouble should be reassessed by the team.
Can a VNS damage the vagus nerve permanently?
Permanent injury is uncommon. Mayo Clinic lists vocal cord paralysis among the rare surgical risks, arising if the nerve branch to the left vocal cord is stretched during the operation. Ongoing stimulation itself is set within limits the nerve tolerates, and long-term follow-up has not shown progressive nerve injury in general use. Side effects such as cough or voice change during stimulation reflect the nerve responding, not being harmed.
Can you overuse a VNS magnet?
A single swipe cannot exceed the extra burst your neurologist has programmed, so the magnet is not dangerous in that sense. Repeated swiping in a short time does add more stimulation and can bring on more hoarseness, throat tightness, or cough. Follow the written guidance your team gives on frequency, and tell them if you are swiping many times a day, because that pattern is useful information about seizure control.
How should I care for VNS incision healing at home?
Keep both incisions clean and dry, shower only when your surgeon allows, let water run over them rather than scrubbing, and pat dry. Do not soak in baths or pools until cleared, and leave glue or adhesive strips to fall off on their own, usually within one to two weeks. Mild redness along the line, slight itching, and skin numbness near the chest pocket are normal; spreading redness, discharge, or fever are not.
Why is the device left switched off after surgery?
The pause lets swelling around the electrodes settle so the nerve receives a steady, predictable signal, and it gives you time to recover from the operation before learning to interpret the new sensations of stimulation. Most programs wait two to four weeks, though some activate a very low setting in the operating room. Either way, benefit is judged over months, so the short delay does not cost you meaningful treatment time.
How long does it take for VNS to reduce seizures?
Mayo Clinic notes that it can take months, and sometimes a year or two, for any effect on seizures to become clear, and Cleveland Clinic observes that improvement often keeps building over time. VNS rarely stops seizures entirely; people who respond typically see frequency fall by roughly 20 to 40 percent. Seizure medicines continue throughout, and any change to them is a decision for the prescribing neurologist based on diary data.
Can I have an MRI with a VNS device?
Often yes, but only under specific conditions that depend on the exact generator and lead you have, and only after the imaging team has confirmed compatibility and planned the scan accordingly. Some body regions and scanner types are permitted and others are not. Always tell every imaging department about your implant, carry the identification card, and ask your neurology team to confirm the details before any scan is booked.
References
- Cleveland Clinic: Vagus Nerve Stimulation (VNS)
- NHS: Epilepsy, treatment
- NIH NINDS: Epilepsy and Seizures
- MedlinePlus: Surgical wound care, closed
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
What Does a Swallowing Study Show? Endoscopy and Imaging Tests Used in Dysphagia Care
A swallowing study for dysphagia records what happens to food and liquid as you swallow, most often with a moving X-ray (videofluoroscopy) or a…

Is Cerebral Palsy Care Different for Teens and Adults? Rehabilitation Goals as Needs Change
Yes. Cerebral palsy care for adults shifts away from the growth- and milestone-focused therapy of childhood toward protecting existing function, managing pain, spasticity and…

How Long Until Narcolepsy Treatment Settles? Follow-Up Visits and Adjustments Explained
Narcolepsy treatment usually settles in stages rather than all at once. Wake-promoting medicines are often noticeable within days, while medicines for cataplexy and night-time…

Epilepsy Myths Neurologists Still Hear: Flashing Lights, Tongue Swallowing and Driving
Most epilepsy myths do not survive contact with the evidence. Flashing lights trigger seizures in only a small minority of people with epilepsy, roughly…

What Happens in a Cognitive Assessment? Memory Tests, Imaging and Blood Work Explained
A cognitive assessment usually begins with a conversation about what has changed, a review of medicines and mood, and a short pencil-and-paper or verbal…

What Do Lumbar Puncture, Imaging and Blood Tests Show in Neuroinfectious Disease Care?
In neuroinfectious disease care, a lumbar puncture samples cerebrospinal fluid, the clear liquid around the brain and spinal cord, so laboratories can count cells,…