

How to Measure Blood Pressure at Home: The Technique Most People Get Wrong
Key Takeaways
- A cuff that's too small for your arm can inflate a systolic reading by 10 to 20 points, making cuff sizing the single most consequential equipment decision.
- Every inch your arm sits below heart level adds roughly 2 points to the reading, so an arm resting in your lap can overstate blood pressure by up to 10 points.
- A full bladder can raise systolic readings by 10 to 15 points, emptying it beforehand is the easiest accuracy fix in the entire protocol.
- Properly taken home readings run about 5 points lower than office readings, so a home average of 135/85 is roughly equivalent to 140/90 measured in a clinic.
- The standard baseline protocol is two readings one minute apart, morning and evening, for seven days, with the first day's readings discarded before averaging.
- A reading above 180/120 that persists after five quiet minutes warrants same-day contact with a clinician, and emergency care immediately if chest pain, breathlessness, or vision or speech changes accompany it.
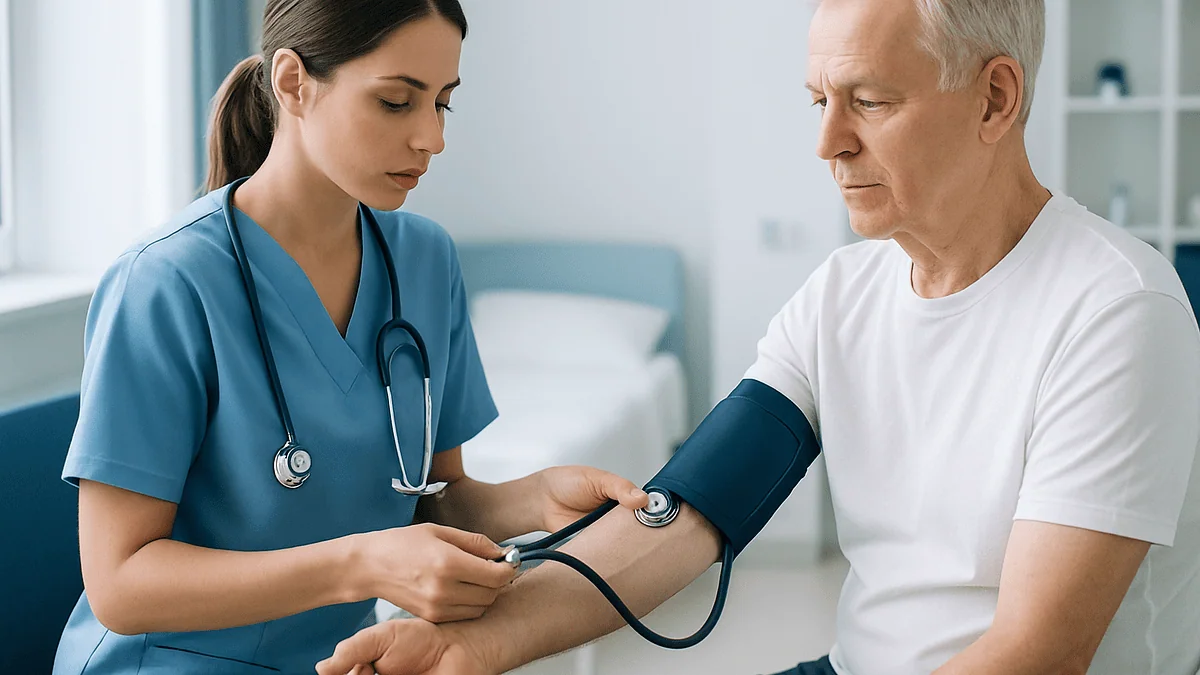
To measure blood pressure at home, use a validated automatic upper-arm monitor with a cuff sized to your arm. Sit quietly for five minutes with your back supported, feet flat, and legs uncrossed. Rest your bare arm on a table at heart level, stay silent, take two readings one minute apart in the morning and evening, and record the average over several days.
Picture the scene: you’re on the couch, coffee in one hand, phone in the other, arm dangling toward the floor while the cuff hums away. The monitor beeps, the number looks alarming, and suddenly the evening has a different mood. Here’s the twist: that reading was probably wrong before the cuff even inflated.
Home monitors themselves are remarkably good. Automated devices that pass independent validation testing perform close to clinical equipment. What fails, again and again, is everything around the device: the crossed legs, the sweater sleeve bunched under the cuff, the conversation mid-reading, the arm resting in a lap instead of on a table.
Each of those details sounds trivial. Stack three or four together and you can shift a reading by 20 points or more, enough to make healthy numbers look worrisome or hide a real problem. The technique is learnable in an afternoon. Here is how to get it right.
Why measure blood pressure at home at all?
A reading in a clinic captures one moment on one day, often a stressful one. Research summarized by the American Heart Association suggests that a meaningful share of people with elevated office readings have what’s called white-coat hypertension/">hypertension: numbers that climb in medical settings and settle at home. The reverse pattern, masked hypertension, is sneakier, readings that look fine in the exam room but run high in daily life, where the real cardiovascular wear and tear happens.
Home monitoring solves both problems by trading a single snapshot for an album. An average built from a week of morning and evening readings tells you and your clinician far more about your true baseline than any solo measurement can. Studies have consistently found that out-of-office averages track more closely with long-term cardiovascular risk than isolated clinic values.
There’s a practical benefit, too. If your clinician adjusts your treatment plan, home readings show whether the change is working across real days, workdays, weekends, good nights of sleep and bad ones. And people who monitor at home tend to stay more engaged with their own care, which matters for a condition that produces no symptoms for years.
One caveat worth stating plainly: home monitoring supports medical care; it doesn’t replace it. The numbers you collect are raw material for a conversation with a professional, not a diagnosis you hand yourself.
What kind of monitor should you buy?
Choose an automatic monitor with a cuff that wraps around your upper arm. That’s the configuration used in the major studies that established what home readings mean, and it’s what the American Heart Association and Mayo Clinic recommend for most people.
Wrist and fingertip devices are tempting, smaller, cheaper, easier to slip on. They’re also far more sensitive to position. A wrist held a few inches too high or too low, or bent slightly, can throw the number off substantially, because the measurement depends on the sensor sitting exactly at heart level. Unless a clinician has specifically recommended a wrist device (sometimes appropriate when an upper-arm cuff won’t fit), stick with the arm.
Beyond the basic format, look for:
- Independent validation, several medical organizations maintain public listings of devices that have passed standardized accuracy testing; check that your model appears on one before buying.
- Multiple cuff sizes available, so you can match the cuff to your arm rather than the reverse.
- Memory that stores readings with date and time, which makes your log more reliable than pen-and-paper recall.
Skip features that add cost without accuracy: you don’t need an app to get trustworthy numbers, though some people find automatic syncing helps them stay consistent. Once a year, bring your monitor to an appointment and compare it against the office measurement. Devices drift, and a quick side-by-side check catches it.
Does cuff size really matter that much?
More than almost anything else, yes. The cuff works by squeezing your arm until blood flow briefly stops, then listening as flow returns. A cuff that’s too small for the arm has to squeeze disproportionately hard, and the monitor reads that extra effort as higher blood pressure. Research published in cardiology literature has found that using a standard cuff on an arm that needs a larger one can overestimate systolic pressure by amounts approaching 20 points, enough to move someone from a normal category into apparent hypertension on paper alone.
A too-large cuff errs in the other direction, underestimating pressure, though usually by a smaller margin.
Getting it right takes two minutes and a soft tape measure:
- Find the midpoint of your upper arm, halfway between shoulder and elbow.
- Wrap the tape around that point, snug but not compressing, and note the circumference in centimeters.
- Compare that number to the size range printed on the cuff itself or in the device manual. Most manufacturers sell small, standard, and large cuffs for the same monitor.
If your arm circumference sits at the edge of a range, size up rather than down: the error from a slightly large cuff is generally smaller. And if the cuff that came in the box doesn’t match your measurement, replace the cuff, not the whole monitor. Most brands sell them separately.
The 30 minutes before: what to avoid
Blood pressure is a live signal, not a fixed trait. It responds to what you drank, whether you smoked, how recently you climbed the stairs, even whether you need the bathroom. The half hour before a reading determines whether you’re measuring your baseline or measuring your morning.
In the 30 minutes beforehand, skip:
- Caffeine, coffee, strong tea, and energy drinks can nudge pressure upward temporarily.
- Nicotine in any form, which constricts blood vessels and raises readings for a stretch afterward.
- Exercise, including brisk housework or a fast walk up from the parking garage.
- Heavy meals, which shift blood flow and can move the numbers in either direction.
Then handle the one people forget: use the bathroom. A full bladder activates the sympathetic nervous system, and Cleveland Clinic and other sources note it can raise systolic readings by roughly 10 to 15 points. It’s one of the largest single errors on this list, and the easiest to fix.
Finally, sit down and do nothing for five full minutes. Not scrolling, not sorting mail, resting. This step feels excessive and gets skipped constantly, but pressure genuinely takes several minutes to settle after any activity, even walking across the room to fetch the monitor. Set a timer if patience isn’t your gift. Five quiet minutes is the cheapest accuracy upgrade available.
How to sit: the position most people get wrong
Watch how measurements happen in real kitchens and living rooms: perched on a stool, slumped into a soft couch, legs tucked underneath, chatting with a spouse. Every one of those choices moves the number.
The correct setup looks almost formal:
- A chair with a firm back, dining chair, not recliner or couch. Lean back so your spine is supported. Sitting unsupported forces postural muscles to work, which can add 5 to 10 points to a systolic reading.
- Both feet flat on the floor. If your feet dangle, rest them on a book or step.
- Legs uncrossed. Crossing at the knee compresses vessels and can raise systolic pressure by several points, small individually, meaningful when combined with other errors.
- Arm resting on a table, positioned so the cuff sits at heart level (more on that shortly).
Then comes the discipline nobody warns you about: silence and stillness for the entire reading. Talking during a measurement, or even actively listening to someone else talk, can raise the reading by around 10 points. The nervous system treats conversation as mild activity, and the numbers follow. Turn the television down, set the phone face-down, and let the 30-odd seconds pass quietly.
It feels ceremonial. That’s fine. The ceremony is the method.
Where exactly should the cuff go, and why bare skin?
Cuff placement has three rules, and each one earns its keep.
First: bare arm. Not a rolled-up sleeve, not a thin shirt, skin. Fabric under the cuff muffles and distorts the signal the monitor listens for, and a sleeve rolled tight above the cuff acts like a tourniquet, restricting flow before the measurement even starts. Clinical guidance notes that measuring over clothing can shift readings unpredictably, sometimes by a wide margin. If it’s chilly, drape a sweater over your shoulders and leave the measurement arm free.
Second: position. The bottom edge of the cuff should sit about an inch, two to three centimeters, above the crease of your elbow. Most cuffs have an artery marker, a small arrow or line, that should point down the middle of the inner arm, roughly in line with your ring finger. That marker aligns the sensor with the brachial artery, the vessel the device actually measures.
Third: snugness. The cuff should be firm enough that you can slide two fingertips underneath, but no more. Too loose, and it has to over-inflate to compensate, inflating the reading along with itself. Too tight, and you’ve pre-compressed the artery.
Take ten extra seconds to check all three before pressing start. A perfectly executed reading with a badly placed cuff is still a bad reading.
Arm at heart level: the small detail that moves the numbers most
Here’s the piece of physics that explains a surprising share of home-reading errors: blood has weight. When your arm hangs below your heart, the cuff measures your blood pressure plus the pressure of the column of blood between your heart and the cuff. Every inch below heart level adds roughly 2 points to the reading. An arm resting in your lap or hanging at your side can inflate a systolic value by as much as 10 points, purely from gravity, with your actual blood pressure unchanged.
Hold the arm above heart level and the error flips: readings come in falsely low.
Heart level means the middle of the cuff sits at the height of the midpoint of your breastbone, roughly where a shirt’s third button falls. For most people seated at a standard table, resting the forearm flat on the tabletop lands the cuff close to the right height. If your table runs low or you’re tall, prop the arm on a folded towel or a firm cushion until the cuff aligns with mid-chest.
Two related details finish the job. Let the table carry the arm’s full weight: a muscle actively holding position raises pressure on its own, so the arm should feel heavy and lazy. And turn the palm gently upward, which relaxes the forearm and presents the inner arm, where the artery marker belongs.
Gravity doesn’t negotiate. Position the arm correctly and one of the biggest error sources disappears entirely.
Step-by-step: the full technique from start to finish
With the principles covered, here’s the complete sequence in order. After a week it becomes automatic.
- 1. For 30 minutes beforehand: no caffeine, nicotine, exercise, or heavy meals. Empty your bladder.
- 2. Sit in a firm-backed chair at a table. Back supported, feet flat, legs uncrossed.
- 3. Rest quietly for five minutes. No phone, no conversation.
- 4. Wrap the cuff on a bare arm, an inch above the elbow crease, artery marker on the inner arm, snug enough for two fingertips.
- 5. Rest the arm on the table so the cuff sits at mid-chest height, palm up, muscles slack.
- 6. Press start. Stay silent and still until the cuff fully deflates.
- 7. Note the reading, wait one minute, and take a second measurement without moving from position.
- 8. Record both readings with the date and time, or confirm the device stored them.
Why two readings? First measurements often run a few points high; the artery and your nervous system settle with the second pass. Some clinicians suggest a third reading if the first two differ by more than a few points, then averaging the final two.
The whole ritual takes under ten minutes, most of it quiet sitting. Pair it with something you already do daily, after brushing your teeth, before the evening news, and consistency takes care of itself.
How many readings do I need, and at what times of day?
Blood pressure follows a daily rhythm, typically lower overnight, climbing in the morning, drifting through the afternoon. A single daily reading, taken whenever you remember, samples that curve at random. Structured timing fixes it.
The widely recommended protocol, endorsed in guidance from the American Heart Association and echoed by Mayo Clinic, looks like this:
- Measure twice a day: once in the morning, before breakfast, before any medications your clinician has prescribed, and before your morning coffee, and once in the evening, roughly before dinner or bed.
- Take two readings each session, one minute apart.
- Continue for seven consecutive days when establishing a baseline or checking a change in your care plan.
- When calculating your average, many clinicians discard the first day entirely, those readings tend to run high while the routine is still novel, and average the remaining days.
That produces roughly 24 usable readings, which is enough to smooth out the day-to-day noise that makes single measurements misleading.
Between these structured weeks, most people with stable readings don’t need daily monitoring: a few sessions a week, or whatever cadence your clinician suggests, usually suffices. Resist the urge to measure repeatedly throughout the day, especially when anxious. Pressure rises with anxiety, the elevated number feeds the anxiety, and the loop generates alarming data that reflects the loop itself rather than your health.
Why are my home readings different from the doctor's office?
They’re supposed to be, at least a little. Home readings taken correctly tend to run about 5 points lower than office readings, partly because home is calmer, partly because the structured protocol removes errors that creep into busy clinic visits.
Thresholds account for this. Where an office reading of 140/90 has traditionally flagged hypertension, the equivalent home average is around 135/85. Current American Heart Association categories, which apply to properly measured readings, define normal as below 120/80, elevated as 120–129 with a bottom number under 80, stage 1 hypertension as 130–139 or 80–89, and stage 2 as 140 or higher, or 90 or higher. A reading above 180/120 belongs in its own urgent category, covered later in this article.
What matters is the pattern, not the vocabulary. If your home average consistently sits well below your office numbers, that gap is exactly the kind of information home monitoring exists to reveal, bring the log to your appointment and let your clinician interpret it. If home and office agree, you’ve confirmed the office picture is real.
One thing home numbers should never do is prompt you to change your own treatment. Adjusting or skipping prescribed medication based on a good week of readings is a common and genuinely risky mistake; pressure often looks controlled precisely because the treatment is working. Every change goes through your clinician.
Common mistakes, and how much each one changes your reading
Individually, these errors sound minor. The trouble is that they stack: a full bladder, a dangling arm, and a mid-reading conversation can together push a genuinely normal blood pressure into apparently dangerous territory. Estimates below reflect ranges cited in clinical guidance and measurement research; individual effects vary.
| Mistake | Typical effect on systolic reading |
|---|---|
| Cuff too small for the arm | Up to 10–20 points higher |
| Cuff over clothing | Unpredictable; can shift readings substantially in either direction |
| Full bladder | Around 10–15 points higher |
| Arm unsupported or below heart level | Up to 10 points higher (about 2 points per inch below heart) |
| Talking or actively listening during the reading | Up to 10 points higher |
| Back unsupported | Around 5–10 points higher |
| Legs crossed at the knee | Roughly 2–8 points higher |
| No 5-minute rest beforehand | Variable; often 5–10 points higher |
| Caffeine or nicotine within 30 minutes | Temporary rise, varies by person |
Notice that nearly every error pushes readings upward. That asymmetry means sloppy technique usually makes blood pressure look worse than it is, which sounds harmless until it leads to unnecessary worry, extra appointments, or treatment decisions built on distorted data. The fix costs nothing: the same reading, taken the careful way, is the real one.
Which arm should you use, and what if the two arms differ?
The first time you set up home monitoring, measure both arms. Sit properly, take two readings on one arm, rest a few minutes, then repeat on the other. Small differences between arms are completely normal: a gap of a few points reflects ordinary anatomy.
From then on, use the arm with the higher reading, every time. That sounds counterintuitive, why choose the worse number?, but the higher-reading arm reflects the pressure your arteries actually experience, and consistency matters more than comfort. Switching arms between sessions injects noise into your log and makes trends harder to read.
Pay attention if the gap between arms is large. A persistent difference of more than 10 points in the top number, confirmed across several careful sessions, is worth mentioning at your next appointment. Research summarized by Harvard Health and others has linked larger between-arm differences to a higher likelihood of vascular narrowing, so it’s a data point your clinician will want, not a cause for panic, but not something to shrug off either.
A few practical notes: if you’ve had lymph node surgery, a dialysis access site, or an injury affecting one arm, ask your care team which arm to use before starting. And note your chosen arm in your log, so that anyone reviewing your numbers later knows the readings are comparable to one another.
How to keep a log your clinician can actually use
A stack of readings only becomes useful when someone can interpret it, and interpretation depends on honest, complete records. That starts with the hardest rule: write down every reading, including the ones you don’t like. Logs edited to show only good days, and people do this more than they admit, are worse than no log, because they tell a false story with confident-looking data.
For each session, capture:
- Date and time
- Both numbers, plus pulse if your device reports it
- Which arm you used
- Anything unusual, poor sleep, illness, a stressful morning, a skipped rest period
Most modern monitors store readings automatically, and many export averages you can print or show on your phone. If you prefer paper, a simple notebook grid works; several health organizations, including the American Heart Association, offer printable tracking sheets.
When you bring the log to an appointment, bring the monitor too, at least once a year. Your clinician can run an office measurement alongside your device and confirm the two agree: a quick calibration check that catches drifting sensors and worn cuffs.
One last habit worth building: look at weekly averages, not individual readings. A single elevated evening after a hard day means little. A seven-day average that has climbed since last month means something. Training your eye on the average is how you extract signal from the noise, and how you avoid riding the emotional rollercoaster of daily fluctuation.
When should you see a doctor about your readings?
Home monitoring works best with clear lines about when to escalate. Here they are.
Seek emergency care immediately if a reading exceeds 180/120 and you have any of these symptoms: chest pain, shortness of breath, sudden severe headache, weakness or numbness, changes in vision, or difficulty speaking. Don’t wait to recheck, call emergency services. These symptoms alongside a very high reading can signal a hypertensive emergency requiring immediate treatment.
If a reading exceeds 180/120 without symptoms, sit quietly for five minutes and measure again. If the second reading is still above that line, contact your clinician promptly: the same day. Guidance from the American Heart Association treats confirmed readings at this level as urgent even when you feel fine.
Schedule a routine appointment if your home average over a week runs at or above roughly 135/85 and you haven’t been diagnosed with high blood pressure, or if your average has climbed noticeably despite an existing care plan. Bring the full log.
Also worth a call: readings that are consistently much lower than usual, especially with dizziness, lightheadedness, or fainting; a persistent between-arm difference above 10 points; or numbers that swing wildly session to session despite careful technique, which sometimes points to a device problem or an irregular heart rhythm your monitor may flag.
High blood pressure typically causes no symptoms at all until it has done damage, which is precisely why the quiet, unglamorous habit of accurate home measurement earns its place in your week.
Frequently asked questions
What time of day should I measure my blood pressure at home?
Measure twice daily: in the morning before breakfast, coffee, and any prescribed medications, and again in the evening before dinner or bed. Blood pressure follows a daily rhythm, so consistent timing makes your readings comparable to one another. Take two readings one minute apart at each session and record both. Random, whenever-you-remember measurements sample that daily curve at unpredictable points and produce a noisier, less useful record.
Which arm should I use for home blood pressure readings?
Use the arm that gives the higher reading, and use it consistently. The first time you monitor, measure both arms during separate rested sessions to find out which that is. Small differences between arms are normal, but a persistent gap of more than 10 points in the top number is worth mentioning to your clinician. If you’ve had lymph node surgery or have a dialysis access site, ask your care team which arm to use first.
Are wrist blood pressure monitors accurate?
They can be, but they’re much harder to use correctly than upper-arm monitors. Wrist devices are extremely sensitive to position: the sensor must sit exactly at heart level with the wrist straight, and small deviations produce large errors. Major organizations including the American Heart Association recommend automatic upper-arm cuff monitors for most people. A wrist device is reasonable mainly when an upper-arm cuff won’t fit, and ideally with a clinician’s guidance.
Why is my blood pressure lower at home than at the doctor's office?
A modest gap is expected and even built into the thresholds, home readings typically run about 5 points lower than office readings. Clinical settings raise many people’s pressure, a pattern called the white-coat effect. That’s one reason home monitoring exists: a week of properly taken home readings often reflects your true baseline better than a single office measurement. Bring your log to appointments so your clinician can compare the two pictures directly.
How often should I check my blood pressure at home?
When establishing a baseline or after a change in your care plan, follow the structured protocol: two readings, twice a day, for seven days. Between those focused weeks, most people with stable numbers need only occasional sessions: a few per week or whatever cadence their clinician suggests. Avoid measuring many times a day, especially when anxious; anxiety raises pressure, and repeated checking of elevated numbers tends to feed a stressful and misleading loop.
Should I measure my blood pressure when I feel stressed or unwell?
Generally no, unless you have symptoms that need urgent evaluation. Readings taken during acute stress, pain, or illness will be elevated and don’t reflect your baseline, so they add noise to your log rather than information. The exception is serious symptoms, chest pain, breathlessness, sudden severe headache, vision or speech changes, where the priority is emergency care, not measurement. For routine monitoring, stick to your scheduled, rested morning and evening sessions.
What is a normal blood pressure reading at home?
For properly taken home readings, an average below 120/80 is considered normal, and a home average of about 135/85 or higher corresponds roughly to the traditional office threshold of 140/90. American Heart Association categories define elevated pressure as 120–129 systolic with a diastolic under 80, stage 1 hypertension as 130–139 or 80–89, and stage 2 as 140 or higher or 90 or higher. Your clinician interprets your average in the context of your overall health.
Why do two readings taken minutes apart give different numbers?
Because blood pressure genuinely fluctuates moment to moment, with breathing, posture shifts, and nervous system activity. Differences of a few points between back-to-back readings are completely normal, and first readings often run slightly high before the artery and your body settle. That’s why the standard protocol takes two readings one minute apart and why averages across days matter far more than any single number. Large, erratic swings despite careful technique are worth mentioning to your clinician.
Do home blood pressure monitors need to be calibrated?
They should be checked, yes. Once a year, bring your monitor to a medical appointment and compare its reading against the office measurement taken moments apart. Sensors drift over time and cuffs wear out, and this simple side-by-side check catches problems early. Also confirm before buying that your model appears on an independent validation listing, since validation testing verifies the device met standardized accuracy criteria in the first place.
Is one high blood pressure reading a reason to worry?
Usually not. A single elevated reading can reflect stress, caffeine, a full bladder, poor positioning, or ordinary fluctuation, which is why diagnosis never rests on one number. Sit quietly for five minutes and measure again, then watch your weekly average. The important exception: a reading above 180/120 that persists on recheck warrants same-day contact with a clinician, and emergency care immediately if it comes with chest pain, breathlessness, weakness, or vision or speech changes.
References
- MedlinePlus: Blood Pressure Monitoring at Home
- NHS: High Blood Pressure (Hypertension)
- CDC: About High Blood Pressure
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What an Echocardiogram Shows in Heart Failure: Ejection Fraction and Why It Guides Treatment
An echocardiogram in heart failure measures ejection fraction, the percentage of blood the left ventricle pumps out with each beat. A normal range on…

Cardiac Ablation Recovery: The Overnight Stay and the First Two Weeks of Lighter Activity
Cardiac ablation recovery time is short for most people: home the same day or after one overnight stay, several hours lying flat while the…

Who Needs Heart Bypass Surgery Rather Than a Stent? What the Heart Team Weighs
Heart bypass surgery is usually offered when coronary blockages are too extensive, too complex, or too poorly placed for stents to treat well: typically…

Who Is a Candidate for Percutaneous PFO or ASD Closure, and Who Is Better Served by Surgery?
Percutaneous PFO closure is usually considered for adults under about 60 who have had a stroke of unclear cause that a full workup links…

What an Echocardiogram Shows in Pericardial Effusion and How It Guides Treatment
An echocardiogram shows how much fluid surrounds the heart, where it sits, and whether it is pressing on the heart chambers. Measuring the fluid…

Managing Hypertension Day to Day: Salt, Weight, Exercise and a Reading Log Your Doctor Can Use
Living with hypertension means treating blood pressure as a number you manage rather than a label you carry. Guidelines point to four everyday levers:…