

Kinesiology Tape: What the Studies Show Behind the Colorful Strips

Key Takeaways
- In sham-controlled trials, kinesiology tape typically reduces pain by less than the 1.5 to 2 points on a 0 to 10 scale that patients can reliably feel.
- A 2021 Cochrane review of roughly two dozen shoulder trials rated the evidence for kinesiology tape as low to very low certainty and could not show it beat sham tape or exercise alone.
- Randomized trials in chronic low back pain found that tape applied with the recommended stretch performed no better than flat, unstretched tape after four weeks.
- Trials measuring ankle circumference after sprains found no consistent reduction in swelling, undermining the lymphatic drainage claim.
- Dozens of small studies in healthy volunteers show no meaningful change in grip strength, quadriceps torque, jump height or sprint time with tape.
- The color of kinesiology tape is cosmetic only; manufacturers use the same fabric and adhesive across their ranges.
Kinesiology tape is a stretchy cotton strip applied over muscles and joints. Randomized trials and systematic reviews show it produces, at best, small and short-lived reductions in pain, often no greater than sham tape, and no consistent improvement in strength, swelling or injury prevention. It is generally safe for most people and can be a reasonable low-risk add-on to exercise-based rehabilitation, but it does not replace that rehabilitation.
Scroll through any highlights reel from this summer’s outdoor season and you will spot it: a sprinter’s thigh striped in teal, a volleyball player’s shoulder fanned out in pink, a weekend runner filming a “knee pain hack” that involves nothing more than four strips of adhesive. As of September 2026, searches for kinesiology tape have surged again, pushed by short-form videos promising that the right pattern can switch off pain, drain a bruise overnight or make a hamstring fire harder.
The tape itself has barely changed since it went mainstream at the 2008 Olympics. What has changed is the volume of the claims and, quietly, the volume of studies testing them. Physiotherapy journals have now published well over a hundred randomized trials, plus several systematic reviews and a Cochrane review, on the colorful strips.
The picture that emerges is neither the miracle the videos sell nor the fraud the skeptics assume. It is smaller, more specific and, for anyone with a sore knee or shoulder, genuinely useful to understand.
What is kinesiology tape, and how is it different from athletic tape?
Kinesiology tape is a thin, elastic cotton strip with an acrylic adhesive, designed to stretch lengthwise by roughly 40 to 60 percent of its resting length and then recoil like skin. That elasticity is the whole point. Traditional athletic tape is rigid; a trainer wraps an ankle with it precisely because it does not give, holding the joint in a safer range for the length of a game. Kinesiology tape does the opposite. It is applied in single strips or fans over a muscle or around a joint, often with the tape or the body part under tension, and it is meant to move with you.
The method dates to the 1970s, when a Japanese chiropractor began using elastic tape to try to influence muscle and skin rather than immobilize joints. It stayed a niche clinical tool until the 2008 Beijing Olympics, when bright strips on the shoulders of beach volleyball players turned it into a consumer product almost overnight.
The kinesiology tape vs athletic tape distinction matters when you read the research. Studies of rigid taping and bracing for ankle instability form a separate literature with a longer track record and somewhat firmer support. When this article says “tape,” it means the elastic kind, and the claims under scrutiny are the ones printed on its packaging: less pain, better muscle activation, faster recovery, reduced swelling and a lower injury risk.
One practical difference is wear time. Rigid tape comes off within hours because it restricts circulation and loses tension. Elastic tape is water-resistant and typically stays on for several days, which is why you now see it in swimming pools and open-plan offices as often as on playing fields.
What changed recently
Nothing in the tape itself has changed; what has shifted is how much scrutiny it receives. Three dated milestones frame the current picture.

In 2012, a meta-analysis in the journal Sports Medicine: a meta-analysis pools the results of multiple studies into one statistical estimate, reviewed the trials then available on kinesiology tape for treating and preventing sports injuries. The authors found little quality evidence to support its use over other elastic taping and described any benefits as small and possibly not clinically meaningful.
In 2014, a systematic review in the Journal of Physiotherapy went further. After examining randomized trials across several musculoskeletal conditions, the authors concluded that current evidence did not support use of the technique in clinical practice, noting that where tape beat a comparison, the margin was usually too small for a patient to feel.
In 2021, a Cochrane review, Cochrane reviews are independent, methodically rigorous summaries of trials, examined the tape for rotator cuff disease of the shoulder. It rated the certainty of evidence as low to very low and could not say whether tape was better than sham taping or than exercise alone.
Since then, the trickle of small trials has continued, mostly from physiotherapy departments, and mostly with the same shape: a few dozen participants, follow-up measured in weeks, and a modest short-term difference that shrinks or disappears against a sham comparison. As of September 2026, none of the major orthopedic or sports medicine guidance we reviewed recommends kinesiology tape as a stand-alone treatment. That absence, rather than any new discovery, is the real story behind the viral clips.
What the evidence actually says: grading the studies
Medical evidence comes in tiers, and the tier matters more than the headline. A randomized controlled trial assigns people to treatment or comparison by chance, which is the fairest way to test whether something works. A systematic review gathers every trial on a question and weighs their quality together. Observational data simply watches what happens to people who choose a treatment, and expert opinion is exactly that.
For kinesiology tape, the good news is that most of the evidence is randomized. The bad news is that the trials are small, typically 20 to 60 participants, and short, usually following people for days or a few weeks. Small, short trials tend to exaggerate benefits and miss harms.
The comparison arm is the other weak point. When tape is compared with doing nothing, it often looks helpful. When it is compared with sham tape, tape applied loosely, in the wrong place or without stretch, the advantage usually narrows to a point or two on a 0 to 10 pain scale, or vanishes. Researchers generally consider a change of about 1.5 to 2 points on that scale the smallest difference a patient can actually feel; most tape studies land below it.
Blinding is also imperfect. Participants can see the tape, and the clinician applying it always knows which version they are using. Expectation alone can lower reported pain, and the studies cannot fully separate that effect from the tape.
Graded honestly, then: there is moderate-quality evidence that the tape does not meaningfully reduce swelling, improve strength or prevent injury; low to very low certainty evidence of a small, short-term pain benefit in some conditions; and no high-quality evidence that it outperforms a well-designed sham.
Does kinesiology tape work, and how could a strip of cotton change pain?
Ask a devoted user “does kinesiology tape work?” and the answer arrives with a mechanism attached. The most common explanation is that the recoiling tape gently lifts the skin, creating space beneath it that improves blood and lymphatic flow and takes pressure off pain receptors. It is a tidy story. It is also largely untested in humans; the handful of imaging studies that have looked for that lift found inconsistent or trivial changes in the tissue beneath the tape.
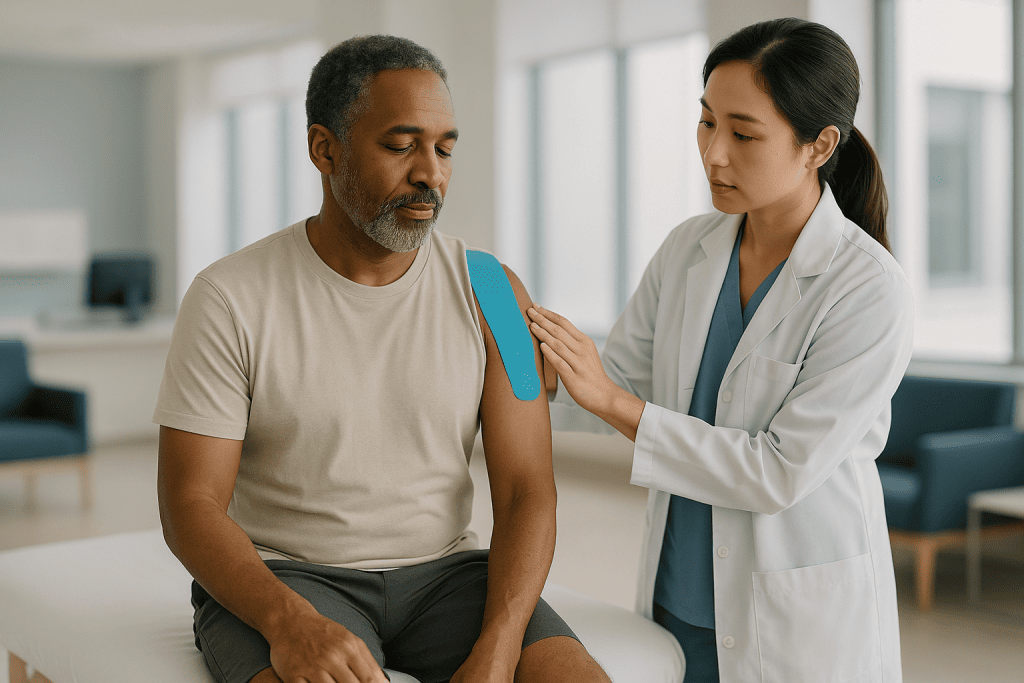
A second explanation is proprioception: the body’s sense of where its joints are in space. The theory holds that tape tugging on skin gives the nervous system a constant stream of information, sharpening joint awareness and encouraging better movement. Some laboratory studies do show altered muscle activation on electromyography, a test that records the electrical activity of muscles, but the changes are small and do not reliably translate into measurable strength or performance gains.
A third mechanism is the pain gate. Stimulating touch fibers in the skin can partly dampen pain signals traveling along slower nerves; rubbing a bumped shin works on the same principle. This is plausible and probably contributes to whatever immediate relief people feel, but it applies to any snug fabric or firm touch, not to the tape specifically.
Finally there is placebo, which is not the same as “nothing.” A bright, deliberately applied strip, placed by a confident clinician, sets a strong expectation of relief. Trials that use sham tape are essentially measuring how much of the effect survives once expectation is matched. The recurring finding is: not much.
None of this makes the tape useless. It does mean the honest answer is “it can make some people feel a little better for a little while, mostly through the skin and the mind rather than the muscle.”
Kinesiology tape for knee pain: what the trials found
The knee is where the tape is most often searched and most often tested. Two conditions dominate: patellofemoral pain, an aching around or behind the kneecap common in runners and young athletes, and knee osteoarthritis, the wear-and-tear thinning of joint cartilage that typically arrives in middle age and later.
For patellofemoral pain, several small randomized trials compared kinesiology tape for knee pain against sham tape, rigid patellar taping or exercise alone. A few reported slightly lower pain in the first days after application. Most found no difference from sham once the follow-up stretched to two to four weeks, and none showed that tape improved the outcome of a supervised strengthening program, which remains the treatment with the strongest support for this condition.
Knee osteoarthritis trials tell a similar story with a small twist. Some studies found modest short-term improvements in pain and in functional tests such as rising from a chair or climbing stairs, particularly when tape was combined with exercise. Systematic reviews of these trials rate the evidence as low quality because of small numbers, inconsistent taping techniques and the absence of long-term follow-up. Whatever the tape adds appears to fade within weeks.
What the trials do not show deserves equal weight. There is no convincing evidence that tape changes how the kneecap tracks, slows cartilage loss, reduces effusion, the fluid buildup that makes a knee feel tight, or lets people return to sport sooner.
For a reader with a nagging knee, a fair summary is this: tape may take the edge off for a run or a workday, and it is unlikely to hurt. The exercises a physiotherapist prescribes for the hips and thighs are what change the trajectory.
Shoulder pain and the rotator cuff: the most rigorous review so far
The rotator cuff is the group of four muscles and tendons that hold the ball of the shoulder in its shallow socket and power overhead movement. Rotator cuff disease, a spectrum from tendon irritation to partial tears, is the leading cause of shoulder pain in adults, and it is the one condition for which kinesiology tape has been examined by a Cochrane review.
The 2021 review pooled roughly two dozen randomized trials with about a thousand participants. Its questions were direct: does tape beat sham tape, does it beat doing nothing, and does it add anything to exercise or other physiotherapy?
Its answers were carefully hedged, and the hedging is the finding. The authors judged the certainty of the evidence low to very low across every comparison. Against sham taping, they could not tell whether tape improved pain, function or range of motion. Against exercise alone, adding tape may make little or no difference. A few trials suggested slightly better pain scores at one to two weeks, but the effects were small and inconsistent across studies.
Why such uncertainty after so many trials? The trials were small, used different taping patterns and tensions, measured different outcomes and rarely followed people beyond a month. Several had a high risk of bias, meaning the way they were run could have tilted results toward the tape.
The practical reading for someone with a painful shoulder: tape is unlikely to cause harm and may feel supportive during the day, but it has not been shown to change the course of rotator cuff disease. Progressive strengthening of the cuff and shoulder-blade muscles remains the evidence-backed core of management, and any taping decision belongs in a conversation with the treating clinician.
Low back pain: does adding tape to exercise help?
Chronic low back painpain lasting more than 12 weeks, is the condition most likely to send someone hunting for something, anything, that helps. Tape is cheap, painless and visible, so it is no surprise that clinics began applying two long strips along the spine and testing the results.
The research here is among the better designed in the field. A group in Brazil ran a series of randomized trials in the 2010s specifically built to control for expectation. One compared tape applied with the recommended stretch and skin convolutions against tape applied flat, with no stretch, in the same position. After four weeks, pain and disability scores were essentially the same in both groups. A later trial added tape to a standard exercise program and compared it with the exercise program alone; the tape added nothing measurable to pain or function at the end of treatment or at follow-up.
Smaller trials elsewhere have reported short-term pain reductions of about one point on a 0 to 10 scale compared with no treatment, and some show brief improvements in how far people can bend. These findings are real but modest, and they do not clear the threshold most researchers use for a difference a patient would notice.
Guidance from health services on low back pain emphasizes staying active, continuing normal activities as far as possible, and using exercise and, where appropriate, manual therapy or psychological approaches. Tape does not appear in those recommendations.
If wearing tape helps someone feel confident enough to move, walk and return to their exercise routine, that confidence has value. The tape is the nudge, though, not the treatment.
Ankle sprains, swelling and the lymphatic drainage claim
The most dramatic videos show a bruised ankle striped in a fan pattern one evening and, supposedly, half-cleared by morning. The explanation offered is lymphatic drainage: the lymphatic system is the network of vessels that carries excess fluid and waste from tissues back toward the bloodstream, and the tape is said to lift the skin and open channels for that fluid to flow.
Tested formally, the claim does not hold up well. Randomized trials in people with acute ankle sprains have generally found no meaningful difference in ankle circumference or swelling between taped and untaped groups, or between kinesiology tape and simple compression. Studies in post-surgical swelling and in lymphedema after cancer treatment have produced mixed results, with any benefit small and not clearly superior to standard compression garments or manual lymphatic drainage delivered by trained therapists.
Bruises fade on their own over one to two weeks as the body reabsorbs blood under the skin. A photo taken 12 hours apart will look different regardless of what is stuck to the ankle, and lighting does the rest.
Injury prevention is the other ankle claim. Rigid taping and lace-up braces have observational and some trial support for reducing repeat sprains in people with unstable ankles. Elastic kinesiology tape does not restrict the joint enough to offer that mechanical protection, and the trials that have looked found no reduction in sprain rates. Its supporters argue it works through proprioception instead, but studies measuring balance and joint position sense in taped ankles show inconsistent and small effects.
For a fresh sprain, the evidence-supported basics remain protection, gentle early movement as pain allows, compression, elevation and a graded return to activity. Tape can sit alongside those; it cannot stand in for them.
Kinesiology tape evidence at a glance
The table below summarizes what randomized trials and systematic reviews have found for the uses people most often search. “Evidence strength” follows the usual hierarchy: how many trials exist, how large they are, how well they controlled for expectation, and how consistent the results are.
| Use | Typical comparison in trials | What trials tend to find | Evidence strength |
|---|---|---|---|
| Knee pain (patellofemoral, osteoarthritis) | Sham tape, exercise alone | Small short-term pain relief in some trials; no added benefit to exercise at follow-up | Low |
| Shoulder / rotator cuff disease | Sham tape, exercise, no treatment | Uncertain whether better than sham; may add little or nothing to exercise | Low to very low (Cochrane 2021) |
| Chronic low back pain | Flat sham tape, exercise alone | No meaningful difference from sham; nothing added to exercise | Low to moderate (fairly consistent null results) |
| Acute ankle sprain swelling | Compression, no tape | No consistent reduction in swelling or circumference | Low |
| Injury prevention | No tape, rigid tape or brace | No reduction in injury rates shown | Low; rigid tape and braces have better support |
| Muscle strength and performance | Sham tape, no tape | No consistent gain in strength, jump height or endurance | Moderate (many small trials, consistent null) |
| Lymphedema and post-surgical swelling | Compression, manual drainage | Mixed; not clearly better than standard care | Very low |
Two patterns stand out. First, the more carefully a trial controls for expectation, the smaller the effect. Second, the results are most consistent where the outcome is objective, a tape measure around an ankle, a force plate under a jumping athlete, and least consistent where the outcome is how someone says they feel. That gap is exactly what you would expect from a treatment that works largely on perception and touch rather than on tissue.
Common myths about kinesiology tape
The viral claims cluster around a few ideas worth correcting plainly.
“The color matters.” It does not. Manufacturers use the same fabric and adhesive across their color ranges; the pigment is cosmetic. Some early proponents assigned colors to warming or cooling effects, but no trial has ever compared colors, and there is no physiological reason the dye would change anything. Choose the color you like.
“It speeds healing.” Tissue healing runs on biology: inflammation, repair and remodeling over days to months. No trial has shown that tape shortens that timeline, closes a tendon tear faster or regrows cartilage. What people often notice is reduced pain, which is not the same as faster repair and can tempt someone back into activity before the tissue is ready.
“It lifts the skin to drain swelling.” As covered earlier, imaging studies do not consistently show that lift, and swelling trials do not show the drainage.
“It makes muscles stronger or fire better.” Dozens of small trials in healthy volunteers have measured grip strength, quadriceps torque, jump height and sprint times with and without tape. The pooled picture is no meaningful change. Where individual studies show a difference, it is usually within measurement error.
“If athletes use it, it must work.” Elite athletes also wear lucky socks. Their choices reflect routine, sponsorship, comfort and superstition alongside evidence, and their medical teams generally treat tape as a comfort measure layered onto rigorous rehabilitation.
“It can replace physiotherapy.” This is the myth with real cost. Every well-designed trial that added tape to exercise found the exercise did the work. Skipping the exercise to rely on the strip trades an effective treatment for an ineffective one.
How long to wear kinesiology tape, and how to use it safely
Because the tape is a consumer product rather than a medicine, the practical questions are about skin, not dosing. “How long to wear kinesiology tape” is the most common of them.
Most manufacturers state that a well-applied strip stays put for three to five days, through showers and sweat. That is an upper limit, not a target. The adhesive is designed to be gentle, but skin varies, and the longer any adhesive sits, the more moisture, friction and bacteria build up beneath it. Many physiotherapists suggest removing it sooner, and certainly at the first sign of itching, burning, redness that spreads beyond the tape edge, or blistering.
A few habits reduce trouble:
- Apply to clean, dry, lotion-free skin; oils prevent adhesion and trap moisture.
- Trim dense body hair rather than shaving immediately before, since fresh razor abrasions are prone to irritation under adhesive.
- Round the tape corners with scissors so edges do not catch on clothing and peel.
- Never apply over broken skin, a rash, a healing wound or a recent surgical incision unless a clinician has said so.
- Remove slowly in the direction of hair growth, pressing the skin down as you go, ideally after softening the adhesive with baby oil or in a warm shower. Ripping it off quickly is how skin tears happen.
If you plan to use tape repeatedly, a small patch test on the forearm for 24 hours is sensible, particularly if you have reacted to bandage adhesives before.
Application technique, where to anchor, how much stretch to use, whether to fan the strips, varies enormously between tutorials, and the trials have not established that any one pattern outperforms another. A physiotherapist or athletic trainer can show you a method that suits your anatomy and avoids common mistakes such as over-stretching the tape, which is the most frequent cause of blisters.
Who should be cautious about kinesiology tape
Serious harm from elastic tape is rare, and the most common problem is a red, itchy rectangle that fades within a few days of removal. Still, some people should pause before applying it, or check with their clinician first.
Fragile skin tops the list. Older adults, people on long-term corticosteroids, and anyone whose skin bruises or tears easily are at real risk of skin tears when tape is removed. The adhesive bond can be stronger than the skin’s own layers.
Adhesive allergy is next. Acrylic adhesives cause contact dermatitis: an itchy, sometimes blistering rash from direct skin contact with an irritant or allergen, in a small percentage of people. A history of reacting to bandages, medical tape or wound dressings is a warning sign.
People with diabetes and reduced sensation in the feet or legs may not feel a blister or pressure sore forming under tape, and skin that has poor circulation heals slowly. The same caution applies to anyone with peripheral arterial disease.
Active infection, cellulitis, or a suspected blood clot in a limb are reasons to leave the area untaped and seek care rather than cover it. Tape over an unexplained swollen, warm calf can delay recognition of a deep vein thrombosis, a clot in a deep leg vein that needs urgent assessment.
Because the tape is marketed for lymphatic drainage, some people with lymphedema after cancer treatment try it. That group should discuss it with their oncology or lymphedema team first; skin integrity is especially important in a limb with impaired lymph flow, where a small tear can become a significant infection.
Children and pregnant women are not known to be at particular risk from the tape itself, but the same skin rules apply, and any persistent musculoskeletal pain in a child deserves assessment rather than taping.
When to see a doctor
Tape is at its best as a comfort measure for a strain or a familiar ache that is already being managed. It becomes a problem when it masks a symptom that needs a diagnosis. Arrange prompt medical assessment rather than reaching for the roll if you notice any of the following.
- You cannot bear weight on a leg or take four steps after an injury, or a joint looks visibly deformed or out of place.
- You heard a pop or snap at the time of injury, or a joint gives way or locks.
- Numbness, tingling, weakness or a cold, pale limb below the painful area.
- Pain that wakes you at night, is constant regardless of position, or is worsening over days rather than easing.
- A swollen, warm, red or tender calf, especially after travel, surgery or immobility, which can signal a blood clot.
- Fever, chills or spreading redness around a painful joint, which can indicate infection.
- Back pain with new bladder or bowel changes, numbness in the groin or inner thighs, or weakness in both legs: an emergency requiring immediate care.
- Any joint or muscle pain that has not clearly improved after two weeks of rest, activity modification and simple measures.
- Under the tape itself: blistering, skin that lifts or tears on removal, a rash that spreads beyond the tape edge, or any sign of infection.
None of these is a reason for alarm in itself, but each is a reason for a clinician to look before anything is applied over the area. For ongoing conditions such as osteoarthritis, tendon problems or chronic back pain, the person prescribing or supervising your treatment is the right one to ask whether tape fits into the plan, and how it should be used alongside the exercises and other therapies they have recommended. Any decision to change that plan belongs with them.
What matters most: putting kinesiology tape in its place
Strip away the marketing and the counter-marketing and a clear, modest verdict remains. Kinesiology tape is a safe, inexpensive-to-apply comfort measure that makes some people feel somewhat better for a short time. It has not been shown to heal tissue, drain swelling, build strength or prevent injury, and in the best-designed trials it has not clearly beaten a look-alike sham.
That verdict is less exciting than either camp wants, and it points to a sensible way to use the tape. If a strip on your knee gets you out the door for the walk your physiotherapist asked for, it has earned its place. If it makes a sore shoulder tolerable through a workday while you build up the strengthening program that will actually address the problem, good. If it is standing in for that program, or quieting a pain that should have been examined, it is doing harm by omission.
The larger lesson applies well beyond tape. Musculoskeletal pain responds best to load, movement and time: graded exercise, sensible activity, patience with tissue that heals on its own schedule. Those are unglamorous and hard to film in a 30-second clip. A bright fan of adhesive is easy to film, and so it dominates the feed.
The evidence has been remarkably consistent for over a decade now, across knees, shoulders, backs and ankles, across sham-controlled and open trials, across dozens of small studies and the few large reviews. Small effects, short duration, low certainty. That consistency is itself informative. It tells us the tape is not hiding a dramatic benefit that one more trial will uncover.
Wear it if it helps you move. Take it off if your skin complains. And let the strengthening exercises, not the strips, carry the weight of your recovery.
Frequently asked questions
Does kinesiology tape work for pain?
It can reduce pain slightly for a short time in some people, but randomized trials rarely show a benefit larger than sham tape. Where relief occurs, it likely comes from skin stimulation dampening pain signals and from expectation rather than from any change in the muscle or joint. Systematic reviews rate the evidence as low quality, and no major guidance recommends tape as a stand-alone treatment for musculoskeletal pain.
Is kinesiology tape good for knee pain?
For patellofemoral pain and knee osteoarthritis, small trials show at most a modest short-term reduction in pain and no added benefit once tape is combined with a proper exercise program. It does not change kneecap tracking, reduce joint fluid or slow cartilage loss. It is reasonable as a low-risk comfort measure, but hip and thigh strengthening prescribed by a physiotherapist is what the evidence supports for improving knee pain over time.
How long should you wear kinesiology tape?
Manufacturers state that a well-applied strip can stay on for three to five days, but that is a maximum rather than a goal. Remove it earlier at the first sign of itching, burning, redness spreading beyond the tape edge or blistering. Peel it off slowly in the direction of hair growth after softening the adhesive with oil or a warm shower, and give the skin a day to recover before reapplying.
What is the difference between kinesiology tape and athletic tape?
Athletic tape is rigid and used to restrict joint movement, which is why trainers wrap ankles with it before games and remove it afterward. Kinesiology tape is elastic, stretching by roughly half its length, and is meant to move with the body while stimulating the skin. Rigid taping and braces have better evidence for reducing repeat ankle sprains; elastic tape has not been shown to prevent injury.
Does kinesiology tape reduce swelling or bruising?
Trials in acute ankle sprains and post-surgical swelling have generally found no consistent difference in swelling between taped and untaped limbs, or between tape and standard compression. The popular claim that tape lifts skin to open lymphatic channels is not supported by imaging studies. Bruises fade on their own over one to two weeks, which explains most dramatic before-and-after photos.
Can kinesiology tape make muscles stronger or improve performance?
No. Dozens of small trials in healthy volunteers have measured grip strength, quadriceps force, jump height and sprint times with and without tape, and the pooled result is no meaningful change. Some laboratory studies show small shifts in muscle electrical activity, but these do not translate into measurable gains. Athletes who wear tape are generally using it for comfort or routine rather than for a performance edge.
Does the color of kinesiology tape matter?
The color is purely cosmetic. Manufacturers use the same cotton fabric and acrylic adhesive across their color ranges, and no trial has ever compared one color with another. Early proponents assigned warming or cooling properties to certain shades, but there is no physiological basis for the dye affecting muscle, skin or pain. Pick whichever color you prefer.
Is kinesiology tape safe for everyone?
Serious harm is rare, but some people should be cautious. Those with fragile skin, adhesive allergies, diabetes with reduced sensation, poor circulation or lymphedema are at higher risk of skin tears, contact dermatitis or unnoticed pressure injuries. It should never be applied over broken skin, infection, a healing incision or a limb that may have a blood clot. A 24-hour forearm patch test is sensible before regular use.
Can kinesiology tape replace physiotherapy or exercise?
No, and this is the most costly misunderstanding. Every well-designed trial that added tape to an exercise program found that the exercise produced the improvement and the tape added nothing measurable. Tape can help someone feel comfortable enough to do their prescribed movement, which has value, but relying on it instead of rehabilitation trades an effective treatment for an ineffective one.
Should I see a doctor before using kinesiology tape?
For a familiar minor ache, you generally do not need a consultation to try tape. Seek assessment first if you cannot bear weight, a joint looks deformed or gives way, you have numbness or weakness, pain wakes you at night, a calf is swollen and warm, or pain has not improved after two weeks. For ongoing conditions already under treatment, ask the clinician managing your care how tape fits into the plan.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Is Pain Managed After Hand Surgery? Elevation, Splints and Safe Relief
Pain after hand surgery is usually managed with a combination of measures: keeping the hand raised above heart level to limit swelling, wearing the…

Glucosamine, Collagen and the Arthritis Diet: What Trials Show for Joint Pain
Glucosamine is a natural building block of cartilage sold as a supplement for osteoarthritis. Large randomized trials show it works no better than placebo…
Pavlik Harness Warning Signs: Skin Redness, Swollen Feet and When to Call the Clinic
Mild pinkness under Pavlik harness straps that fades within about 30 minutes is common, but skin that stays red, weeps, cracks or smells needs…
The Hip Replacement Scar: Size, Placement and How It Fades
A hip replacement scar is typically a single straight or gently curved line, roughly 3 to 6 inches long with minimally invasive techniques and…

Toe Shortening Surgery Recovery: Surgical Shoes, Swelling and When Shoes Fit Again
Toe shortening surgery recovery typically means a stiff-soled surgical shoe for several weeks, careful heel-weighted walking from the first days if the surgeon allows…

The McGill Big 3: The Back-Pain Exercises Spine Researchers Recommend
The McGill Big 3 is a set of three low-load core endurance exercises for people with low back pain: the modified curl up, the…