

Recovery After Retinal or Glaucoma Laser Treatment: Blurry Hours, Follow-Up and Milestones

Key Takeaways
- First-day blur after retinal laser comes mainly from dilating drops, the treatment light and the contact lens gel, not from damage to central vision.
- Glaucoma lasers such as SLT and iridotomy include a pressure check before you leave because a temporary spike in the first hours is a recognized effect.
- SLT lowers pressure gradually and its effect is judged at a visit weeks later, so existing glaucoma drops are continued until the prescriber reviews them.
- Panretinal photocoagulation protects central sight at the cost of some peripheral and night vision, an expected trade-off described in NHS guidance.
- After laser retinopexy, new flashes, a shower of floaters or a spreading shadow are urgent symptoms because the seal takes time to mature.
- No patch, bed rest or head positioning is needed after these lasers, and flying is not restricted because no gas is placed inside the eye.
After most retinal or glaucoma laser treatments, vision is blurry or dazzled for a few hours, mainly because of dilating drops, the bright treatment light and the contact lens used during the procedure. Most people return to ordinary activities within a day or two, with follow-up visits to check eye pressure or the treated retina over the following weeks. The treating eye team sets the exact schedule and any drop instructions.
The waiting room looks different on the way out. The overhead lights have halos, the exit sign floats in a purple haze, and the sunglasses you were told to bring suddenly make sense. Someone else is driving you home, and your only real questions are whether this fog is normal and how long it lasts.
For most people, that is the whole story of retinal laser recovery: a strange, dazzled afternoon, a slightly achy eye, and then a return to ordinary life while the laser quietly does its work over the following weeks. Glaucoma lasers follow a similar arc, with one extra character in the plot: a pressure check before you are allowed to leave.
This explainer walks through what actually happens in the chair, why the first hours are blurry, what the days and weeks usually look like, which checks matter and which warning signs should never wait for the next appointment.
What actually happens during retinal and glaucoma laser treatment
A laser is simply a very focused beam of light that the eye’s tissues absorb and convert into a tiny, controlled amount of heat or energy. Where it lands, and how much energy it carries, is what separates one eye laser from another.
Retinal lasers aim at the retina, the light-sensing layer lining the back of the eye. In photocoagulation, small heat spots are placed to seal leaking blood vessels or to create a scar that anchors the retina. Panretinal photocoagulation, often shortened to PRP, scatters hundreds of these spots across the outer retina to calm the oxygen-starved tissue that drives new, fragile vessels in diabetic retinopathy. Focal or grid laser treats a smaller area of leakage near the center. Laser retinopexy rings a retinal tear with spots so the tear cannot progress to a detachment.
Glaucoma lasers aim at the eye’s drainage system instead. Selective laser trabeculoplasty, or SLT, delivers low-energy pulses to the trabecular meshwork, the spongy drain in the angle where the iris meets the cornea, to help fluid leave the eye more easily. Laser peripheral iridotomy, or LPI, makes a pinhole opening in the outer iris so fluid can bypass a blocked route in narrow or closed angles. Both are described in patient guidance from the NHS and the National Eye Institute.
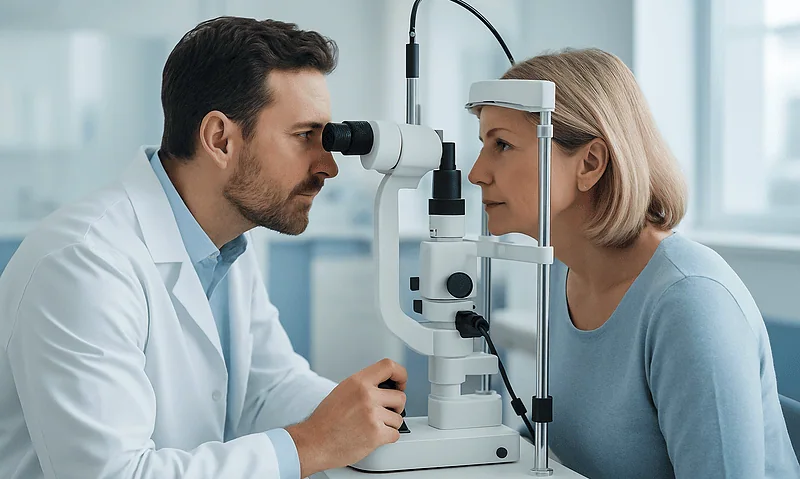
The routine in the chair is similar across all of them. Numbing drops go in, then either dilating drops (for retinal work) or drops that constrict the pupil (for iridotomy). A contact lens coated with clear gel is held against the eye to steady it and focus the beam. You rest your chin on the slit lamp and see flashes and hear clicks. Sessions typically last minutes rather than hours, though PRP may be split across more than one visit.
Why is vision blurry after laser eye treatment?
The blur has several overlapping causes, and knowing which is which makes the afternoon far less alarming.
Dilating drops are the biggest contributor after retinal laser. They relax the muscles that focus the lens and widen the pupil, so near objects smear and bright light feels harsh. Their effect commonly outlasts the procedure by several hours, which is why patient guidance from MedlinePlus advises arranging a driver and bringing sunglasses.
The treatment light itself briefly bleaches the photoreceptors, much as a camera flash leaves a floating spot. After PRP, where hundreds of flashes land in a few minutes, that afterimage can feel like looking through a pink or purple veil. It fades as the pigments regenerate.
The contact lens and gel leave a film over the cornea. Blinking clears most of it within minutes, but a slightly smeared quality can linger for an hour or so.
After iridotomy, the constricting drop does the opposite of dilation: the pupil becomes tiny, the world looks dim, and distance vision may seem off until it wears off. A small number of people later notice a thin line or glare from the new opening in certain lighting; this is discussed under side effects below.
Finally, mild inflammation. Any laser causes a small, expected reaction inside the eye. The anti-inflammatory drops many teams prescribe are there to settle it, and as it settles, clarity returns.
What the blur is not: it is not the laser damaging your central sight. Central vision is deliberately avoided during PRP and retinopexy, and SLT and iridotomy never touch the retina at all. If blur worsens rather than eases over the first day, that is a reason to call, not a normal part of retinal laser recovery.
Retinal laser recovery: what the first 24 hours usually look like
Picture the day in three acts.
The first hour after retinal photocoagulation is the haziest. Most people describe a dull ache rather than sharp pain, a sensation of pressure behind the eye, and strong light sensitivity. PRP tends to produce more ache than focal laser because more spots are placed and some land near nerves in the outer retina. A simple over-the-counter pain reliever is often suggested by the team; which one, and whether it suits you, is their call.
By the evening, the dilation is usually wearing off and reading becomes possible again, though many people find it tiring. Headache around the brow is common after PRP. Some notice new floaters, the small drifting specks caused by the laser stirring the vitreous gel; these often settle but should be mentioned at follow-up.
The next morning is generally close to baseline for focal laser and retinopexy. After PRP, a mild ache and a sense that the edges of vision are dimmer can persist longer, because the treatment intentionally sacrifices some peripheral function to protect the center. The NHS describes reduced peripheral and night vision as recognized effects of this treatment.
Practical points for the first day, as commonly advised in patient information:
- Rest the eyes, but ordinary screen use is not harmful once comfortable.
- Avoid rubbing the eye.
- Use any prescribed drops exactly as instructed.
- Do not drive until vision is clear and you feel confident, and never on the day of dilation.
No patch or bandage is normally needed after a laser, which surprises people who expect surgery-style aftercare. The eye’s surface is untouched; the work happened inside.
Recovery after glaucoma laser treatment: SLT and iridotomy
Glaucoma lasers usually feel gentler in the chair, but their recovery has one distinctive step: a pressure check before you leave.
Both SLT and iridotomy can cause a temporary rise in intraocular pressure, the fluid pressure inside the eye, in the hours after treatment. The Mayo Clinic notes that pressure is measured after laser and that drops to prevent a spike may be given. Expect to sit in the waiting area for a while, have a drop or two, and be examined again before you are discharged. This is routine, not a sign that something went wrong.
After SLT, the eye is often slightly red and gritty for a day or two. Vision is usually only mildly blurred, because the pupil is not widely dilated for this procedure. A short course of anti-inflammatory drops is common practice in some clinics and not in others; you should simply follow your own team’s plan.
Iridotomy tends to produce more ache in the first hours, partly from the constricting drop given beforehand, which can cause a brow headache, and partly from the iris reacting to the opening. Light sensitivity is common. Most people feel comfortable by the next day.
The effect of SLT is not immediate. The laser triggers a slow biological response in the drainage meshwork that lowers pressure over weeks. The National Eye Institute notes that SLT results are not permanent for everyone and that the treatment can sometimes be repeated. Iridotomy, by contrast, opens a physical pathway straight away; its purpose is prevention of an angle-closure attack rather than daily pressure lowering.
Neither laser changes glaucoma into a condition that no longer needs monitoring. Follow-up continues, and any existing pressure drops are continued or adjusted only on the prescriber’s instruction.
Who is usually offered laser, and who is usually asked to wait
Laser is chosen for a specific job, not as a general upgrade for tired eyes.
Retinal photocoagulation is typically offered when diabetic retinopathy has reached the stage of new vessel growth, or when leakage threatens the center of vision, as described in NHS guidance on diabetic retinopathy treatment. It is also used to seal retinal tears found on examination and to treat some blocked retinal veins. Laser retinopexy suits a tear that is flat; once the retina behind it has lifted into a detachment, a different operation is usually needed.
SLT is offered for open-angle glaucoma or raised pressure, either as a first treatment, alongside drops, or when drops are poorly tolerated. Iridotomy is offered when the drainage angle is narrow or has closed, to reduce the risk of a sudden pressure attack. The NHS glaucoma treatment page describes both options.
Who is commonly asked to wait or to consider an alternative:
- People with a significant cataract, corneal cloudiness or blood in the eye that blocks the laser’s view; the beam has to reach its target.
- People with active eye inflammation, which is usually settled first.
- People whose retinopathy has progressed to scarring or detachment, where laser alone cannot help and vitrectomy surgery is discussed instead.
- People with very advanced glaucoma, for whom the pressure lowering from SLT may be judged insufficient.
- People who cannot keep steady at the slit lamp, for whom a different setting or technique may be safer.
Alternatives are part of every honest conversation: injections of anti-VEGF medicines for diabetic macular swelling, drops or drainage surgery for glaucoma, and observation for a small, stable tear in a low-risk eye. Which path fits depends on the individual eye, and the decision sits with the treating team.
Eye lasers compared: what to expect from each
Patients often arrive expecting one experience because a friend had a different laser. The table below summarizes typical patterns described in patient guidance from MedlinePlus, the NHS and the National Eye Institute. Ranges are common experiences, not promises; your own team’s advice overrides them.
| Laser | Target | Typical first-day feel | Usual follow-up focus |
|---|---|---|---|
| Panretinal photocoagulation (PRP) | Outer retina, many spots | Hours of blur from dilation, ache, light sensitivity; may need more than one session | Regression of new vessels over weeks; peripheral and night vision |
| Focal or grid laser | Small area of leakage near center | Mild blur, little pain | Reduction of swelling on scans over weeks to months |
| Laser retinopexy | Around a retinal tear | Blur from dilation, mild ache | Scar seal forming; new floaters or flashes |
| Selective laser trabeculoplasty (SLT) | Drainage meshwork | Mild redness, gritty feel, little blur; pressure check before leaving | Pressure lowering measured over weeks |
| Laser peripheral iridotomy (LPI) | Outer iris | Brow ache, dim vision from constricting drop; pressure check before leaving | Opening staying patent; angle status |
Two threads run through the table. First, retinal lasers produce more blur because of dilation, while glaucoma lasers produce more waiting because of the pressure check. Second, every row lists follow-up measured in weeks, not days. The laser is a starting gun; the benefit unfolds afterward.
A third point the table cannot show: the same procedure can feel very different in two people. Pain thresholds, the number of spots placed, and the amount of pigment in the eye all change the experience. Comparing notes is fine; grading yourself against someone else’s recovery is not useful.
Retinal laser recovery timeline: days, weeks and milestones
Think of recovery as three overlapping timelines: comfort, vision and treatment effect.
Comfort is the fastest. Grittiness and ache usually settle within a few days after any of these lasers. Light sensitivity after PRP can take a little longer, and dark sunglasses remain useful outdoors for a week or two for some people.
Vision follows a longer curve. After focal laser, many people notice little change day to day; the benefit is slower progression of swelling rather than a sudden sharpening, and scans at follow-up track it. After PRP, central vision generally returns to its pre-laser level within days, but the reduction in peripheral and night vision described by the NHS is expected and usually permanent, because that is how the treatment spares the center. After retinopexy, sight is often unchanged from the start; the tear itself was not affecting central vision.
Treatment effect is the slowest and the one that matters most. Patient guidance describes the laser scar around a retinal tear strengthening over roughly one to two weeks, during which the team may advise limiting heavy exertion. New vessels after PRP shrink over several weeks, and sometimes more spots are added if they persist. SLT’s pressure-lowering effect is usually judged at a visit several weeks later.
Milestones that suggest things are on track:
- Day 1: blur clearing, pain controlled with simple measures.
- Week 1: comfortable in normal light, no new flashes or curtain in vision.
- First follow-up: retina flat or leakage improving on imaging; eye pressure at or below target.
- Later visits: stable findings and a plan for ongoing monitoring.
Missing a milestone is a prompt to ask questions, not a verdict. Retinal laser recovery rarely follows a straight line, and the team expects to adjust the plan.
Follow-up after laser eye treatment: what each check is for
Follow-up visits can feel repetitive: drops, chart, pressure, bright light, home. Each step has a purpose.
The vision chart establishes whether central sight is holding. A small drop in the first week is not unusual after PRP because of residual swelling; a larger or persistent drop is investigated.
Pressure measurement matters after every type of laser, not just glaucoma ones. Retinal lasers can occasionally nudge pressure up through inflammation, and glaucoma lasers exist to bring it down. The same pressure check is the primary outcome measure for SLT, which is why the visit several weeks after treatment is the important one for that procedure.
Dilated examination lets the doctor see the laser spots themselves. Fresh retinal spots look pale; over weeks they turn into small pigmented scars, which is the intended result. Around a retinal tear, the doctor is looking for a complete ring of pigment with no fluid creeping underneath.
Imaging fills in what the eye examination cannot. Optical coherence tomography, a scan that maps retinal thickness layer by layer, is the standard way to follow swelling after focal or grid laser. Fluorescein angiography, a dye test that shows leaking vessels, may be repeated after PRP to decide whether more treatment is needed. Gonioscopy, a mirrored lens view of the drainage angle, checks that an iridotomy is open and doing its job.
The Johns Hopkins patient guide on laser photocoagulation frames follow-up as part of the treatment rather than an afterthought, and that is the right mindset. Diabetic eye disease and glaucoma are long-term conditions; the laser treats a moment in their course. Keeping appointments, and keeping blood sugar and blood pressure managed with your wider medical team, protects the result more than anything you do in the first blurry hours.
Driving, screens, work and exercise after eye laser
These are the questions people actually ask on the way out, so here is the practical picture drawn from standard patient guidance.
Driving is the clearest rule. You should not drive on the day of a dilated laser, because focus and glare tolerance are impaired for hours; MedlinePlus and the NHS both advise arranging transport. After that, you may drive when your vision has returned to its usual standard and you feel safe. For glaucoma lasers without dilation, some people are cleared to drive the following day, but the constricting drop used before iridotomy dims vision enough that same-day driving is generally advised against. After PRP, longer-term changes to night and peripheral vision may affect whether you continue to meet driving standards; that is a conversation to have openly with your team.
Screens and reading cause no harm to the treated eye. They may simply be uncomfortable until the blur clears. Take breaks, enlarge text, and expect fatigue on the first evening.
Work depends on the job. Desk-based roles are commonly resumed the next day. Jobs involving dust, chemicals, heavy lifting or driving warrant a specific conversation, especially after retinopexy, where teams often advise avoiding strenuous activity for a week or two while the seal strengthens.
Exercise follows the same logic. Gentle walking is fine almost immediately. Contact sports, heavy weights and activities with a risk of a blow to the eye are typically paused after retinopexy for the period your doctor specifies. After SLT or focal laser, most people return to their normal routine within a few days.
Flying is not restricted by these lasers, because no gas is placed inside the eye. If travel is planned, the sensible step is to ensure the first follow-up visit is arranged before you go, and to know how to reach an eye service where you will be.
Eye drops after laser treatment: what they do and how long they are used
Drops are the part of aftercare people most often get muddled, so it helps to know the categories rather than memorizing bottle colors.
Anti-inflammatory drops, usually a corticosteroid or a non-steroidal anti-inflammatory, calm the expected reaction inside the eye after laser. They are commonly prescribed for a short course after retinal photocoagulation and after some glaucoma lasers. How many days, and how often, is set by the prescriber and depends on the amount of treatment given.
Pressure-lowering drops fall into several classes: beta-blockers and carbonic anhydrase inhibitors reduce fluid production, alpha agonists do both, and prostaglandin analogues improve outflow. If you already use one for glaucoma, the standard advice is to continue it unchanged after SLT until the team reviews the effect at follow-up. Stopping early can mask whether the laser is working and can allow pressure to rise.
Miotic drops, which constrict the pupil, are given before iridotomy to thin the iris and are not usually continued afterward. Their brow-ache side effect fades as they wear off.
Dilating drops are used in clinic only and are not sent home.
General technique matters more than brand: wash hands, tilt the head back, pull down the lower lid, place one drop without touching the tip to the eye, close gently for a minute, and wait a few minutes between different drops. Preserved drops can sting a fresh, irritated eye; mention persistent stinging rather than skipping doses.
Two things not to do without asking: adding a leftover bottle from a previous episode, and stopping a glaucoma drop because the laser is done. The National Eye Institute is explicit that laser may reduce the need for drops in some people but that continued monitoring, and any change to medicines, remains a decision for the prescribing clinician.
Side effects and risks of retinal and glaucoma laser, in plain terms
Laser is among the lower-risk procedures in eye care, but low risk is not no risk, and an honest list serves you better than reassurance.
Retinal photocoagulation carries effects that are intended and effects that are not. Intended: loss of some peripheral and night vision after PRP, and reduced color or contrast sensitivity in some people, described by the NHS as recognized consequences. Unintended but recognized: temporary worsening of macular swelling in the weeks after PRP, small blind spots if a focal spot lands closer to the center than planned, bleeding inside the eye if fragile new vessels break, and rarely a rise in eye pressure or inflammation. Very rarely, a laser burn can affect the center of vision directly.
Laser retinopexy’s main risk is that it does not hold: fluid can track under the retina before the seal matures, producing a detachment that needs surgery. This is why new flashes, a shower of floaters or a shadow in the days after treatment are treated as urgent.
SLT’s commonest effects are transient redness, ache and a pressure spike in the first hours, which is why the post-laser check exists. Inflammation is usually mild. The other limitation is not a side effect but a reality: the pressure-lowering effect may fade over time and may need repeating, as the National Eye Institute notes.
Iridotomy can leave a small percentage of people with visual disturbances such as a horizontal line, glare or a second image, thought to relate to light entering through the new opening. Most find these settle or become unnoticeable. Bleeding at the iris, a pressure spike and inflammation are the other recognized short-term effects.
Alternatives exist for each situation, from injections to surgery to monitoring, and weighing them is what the pre-treatment discussion is for. If you did not have that conversation, it is reasonable to ask for it at follow-up.
What people often get wrong about laser eye recovery
Some myths are harmless. A few lead to missed warning signs or abandoned treatment, so they are worth correcting directly.
Myth: the laser fixes the disease, so the appointments can stop. Retinal laser slows or halts a process driven by diabetes or vascular disease; it does not remove the driver. Glaucoma laser lowers pressure for a period; it does not repair the optic nerve. Both conditions require lifelong monitoring, and the NHS guidance on each is explicit on this point.
Myth: blur means the laser damaged my sight. First-day blur is overwhelmingly from drops, bright light and gel. Central vision is protected by design during retinal laser and untouched by glaucoma laser. Blur that worsens after the first day is the exception and warrants a call.
Myth: if my vision is unchanged, the laser did nothing. Focal laser, retinopexy and SLT are preventive. Success often looks like nothing happening: no further swelling, no detachment, pressure held at target. The measurement is on the scan or the tonometer, not in how sharp the chart looks.
Myth: SLT means the drops can go in the bin. Some people do reduce drop use after SLT, but only after the effect has been measured weeks later and the prescriber has agreed. Stopping early is one of the commonest reasons pressure creeps up unnoticed.
Myth: this is like laser vision correction, so I will see clearly tomorrow. Refractive lasers reshape the cornea to change focus. Retinal and glaucoma lasers treat disease inside the eye and are not designed to improve unaided vision at all.
Myth: I need to lie flat or keep the eye covered. No patch, no positioning and no bed rest are needed after these lasers, unlike some retinal surgeries. Ordinary activity, within any exertion limits your team sets, is the norm.
Questions to ask your care team before and after laser
A good consultation leaves you knowing what the laser is for, what will change and what will not. If any of these were not covered, the follow-up visit is the natural place to ask.
Before treatment:
- Which laser is being done, on what part of the eye, and what is the specific goal: sealing a tear, calming new vessels, lowering pressure, or opening the angle?
- What are the alternatives for my eye, including doing nothing for now, and how do they compare in this situation?
- Will this be one session or several, and how will you decide?
- What vision changes are expected and permanent, such as peripheral or night vision after PRP?
- Should I take my usual eye drops and other medicines on the day?
On the day:
- Which of my symptoms tonight would be normal, and which should prompt a call?
- Do I need any drops afterward, for how long, and should my existing drops change?
- When may I drive, return to work and exercise, and are there activities to avoid while a retinal seal matures?
- Who do I contact out of hours, and how?
At follow-up:
- What did the examination or scan show, and is it what you expected at this stage?
- Is the treatment complete, or is more laser or a different treatment being considered?
- What is my target eye pressure, and are we at it?
- How often will I be seen from here, and what would bring that forward?
- What can I do outside the clinic, such as blood sugar or blood pressure management, that protects this result?
Write the answers down or ask a companion to. Post-laser blur and a little anxiety make even simple instructions easy to forget, and the drops schedule in particular deserves to be on paper.
When to call your doctor after retinal or glaucoma laser
Most recoveries are uneventful, and the threshold for calling should be low rather than high; eye teams would far rather hear about a false alarm than see a delayed detachment or a missed pressure spike.
Contact your eye service the same day, or use the emergency route you were given, if you notice any of the following:
- A sudden increase in floaters, especially a shower of dark specks, or new flashes of light in the treated eye.
- A shadow, curtain or veil spreading across part of your vision from any direction. Both the Mayo Clinic and MedlinePlus list these as warning signs of retinal detachment, and they matter most in the weeks after retinopexy or PRP.
- Severe or steadily worsening eye pain, particularly with a headache, nausea or vomiting, or with a hazy cornea and halos around lights. This pattern can signal a sharp rise in eye pressure and needs urgent assessment.
- Vision that becomes significantly worse after the first day rather than steadily clearer.
- A marked increase in redness, discharge or light sensitivity several days after treatment, which can indicate inflammation or, rarely, infection.
- Any loss of central vision, even briefly.
Call during normal hours, without waiting for the scheduled visit, if mild ache is not settling after a few days, if you are unsure how to use your drops, if you have run out or reacted to a drop, or if you simply feel something is not right. Persistent uncertainty is itself a reason to check.
Do not delay because a follow-up is booked soon, because it is a weekend, or because the eye looks normal from the outside. Retinal problems rarely change the appearance of the eye, and pressure spikes can be painless in the early hours. The person who examined your eye is the right person to judge what a new symptom means, and that judgment is faster over the phone than after a night of worrying.
Frequently asked questions
How long does blurry vision after laser eye treatment last?
For most retinal lasers, blur lasts several hours and is mostly gone by the next morning, because it is driven by dilating drops and the bright treatment light. Glaucoma lasers usually cause milder blur. Vision that is worse on day two than on day one is not typical and should be reported to the eye team promptly.
What is a typical SLT laser recovery time?
Comfort usually returns within a day or two after selective laser trabeculoplasty, with mild redness and grittiness the main complaints. The pressure-lowering effect develops slowly and is normally measured at a follow-up visit several weeks later. Everyday activities, including desk work, are commonly resumed the next day, with driving once vision is clear.
What does laser iridotomy recovery involve?
Expect a brow ache and dim vision for some hours from the pupil-constricting drop, a pressure check before discharge, and light sensitivity for a day or so. Most people feel normal within a couple of days. A small number later notice a line or glare in certain light; mention it at follow-up rather than assuming it is permanent.
Is retinal laser treatment painful?
Focal laser and retinopexy are usually described as uncomfortable rather than painful, with brief pinprick sensations. Panretinal photocoagulation can cause a deeper ache during and after treatment because many spots are placed. Numbing drops are used, and the team can advise on simple pain relief and on splitting extensive treatment across sessions.
When is driving after laser eye treatment allowed?
Not on the day of a dilated laser; arrange a lift. After that, drive only once your vision has returned to its usual standard and you feel safe, which for many people is the next day. After extensive panretinal laser, changes to night and peripheral vision may affect driving longer term, so discuss it openly with your team.
Can I use screens and read after retinal laser?
Yes. Reading and screen use cannot harm the treated retina; they are simply tiring while the eye is dilated and light sensitive. Enlarge text, dim the screen, and take breaks on the first evening. Most people are back to normal reading comfort within a day or two, sooner after glaucoma lasers.
Will I need more than one laser session?
Often, for panretinal photocoagulation, which the NHS notes may be spread across more than one appointment and topped up if new vessels persist. Focal laser and retinopexy are frequently single sessions but can be repeated. SLT can be repeated if its effect fades. The decision is made at follow-up based on examination and scans.
Can I stop my glaucoma drops after SLT?
Not on your own. Standard advice is to continue existing drops unchanged until the effect of the laser has been measured at follow-up, usually several weeks later. Some people are then able to reduce drops on the prescriber’s instruction, others are not, and stopping early risks an unnoticed rise in pressure.
Does laser treatment remove the need for future eye appointments?
No. Laser treats a stage of diabetic retinopathy, a retinal tear or raised pressure, but the underlying condition continues and needs monitoring for life. Follow-up intervals are set by the treating team and may lengthen when findings are stable. Managing blood sugar and blood pressure with your wider medical team also protects the result.
What are the warning signs of a problem after retinal laser?
A sudden shower of floaters, new flashes, a shadow or curtain across vision, severe pain with nausea or halos, or vision that worsens after the first day. Any of these warrants same-day contact with the eye service or the emergency route you were given, even if a follow-up appointment is already booked.
References
- MedlinePlus: Laser photocoagulation – eye
- NHS: Diabetic retinopathy – Treatment
- National Eye Institute (NIH): Glaucoma Surgery
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Flap or Graft? How Reconstructive Surgeons Choose Between the Two Ways to Rebuild Tissue
A skin graft is tissue detached completely from one site and laid onto a wound, where it must grow a new blood supply from…
Recovery After Xanthelasma Removal: Eyelid Swelling, Ointments and Stitch Care Week by Week
Xanthelasma surgery recovery usually follows a predictable arc: eyelid swelling and bruising peak in the first two to three days and largely settle within…

Acne Scar Treatment for Darker Skin: Why Pigment Risk Changes the Method and the Prep
Acne scar treatment for darker skin usually starts by calming active acne and fading post-inflammatory hyperpigmentation before any resurfacing, because melanin-rich skin reacts to…

Realistic Results From Cellulite Treatment: Softer Texture, Not a Different Body
Realistic cellulite treatment results mean a softer, smoother skin texture and shallower dimples, not a different body and not permanent removal. Cellulite comes from…

Neck Laxity Surgery: Real Options for a Sagging Neck, From Lifts to Non-Surgical Care
Surgery for a sagging "turkey neck" usually means a neck lift (lower rhytidectomy), often combined with platysmaplasty to tighten the paired neck muscles, or…
Why Skin Grafts Sometimes Fail: Pressure, Infection, Smoking and the Signs Your Team Watches
Skin grafts fail most often because something separates the graft from the wound bed before new blood vessels can grow into it: a pocket…