

Recovery After Trauma Surgery: Why Physiotherapy Starts Early and How Milestones Are Set

Key Takeaways
- After hip fracture surgery, patients are usually helped out of bed the day after the operation, because muscle loss, clot risk and lung complications all rise within days of bed rest.
- Weight-bearing status describes how much load the healing bone can share with the hardware, and it is revised at follow-up based on imaging rather than on the calendar.
- Early fracture callus is often invisible on plain X-rays for several weeks, so an unchanged film does not mean healing has stalled.
- About one in four adults aged 65 and older falls each year, and more than 300,000 older Americans are hospitalized annually for hip fractures, making fracture fixation the most common trauma operation.
- Sudden breathlessness or chest pain after surgery can signal a pulmonary embolism and needs emergency care, while pain out of proportion to the injury with tightness or numbness may indicate compartment syndrome.
- Acute stress reactions after a traumatic injury are expected in the first weeks; symptoms that persist beyond a month and disrupt daily life are the threshold at which post-traumatic stress disorder is considered.
Trauma surgery recovery usually begins within a day of the operation, when a physiotherapist helps the patient sit, breathe deeply and, where the repair allows, stand or walk. Early movement lowers the risk of clots, chest infection, muscle loss and stiffness. Milestones are set by the surgeon and therapist together, based on how the bone or tissue was fixed, imaging, pain control and the individual's baseline health, and they are adjusted as healing progresses.
The morning after the operation, before the breakfast tray has arrived, a physiotherapist is already standing at the bedside with a walking frame. The patient, who was pulled from a crumpled car less than 36 hours earlier and still has a drain taped to one thigh, looks at the frame as if it were a dare. This is the moment many families find bewildering. Surely rest comes first?
In modern trauma care it does not, or at least not in the way most people imagine. Trauma surgery recovery is built around a counterintuitive idea: the body heals faster and more safely when it is asked to move early, within limits set deliberately by the surgical and therapy team. Those limits are the milestones, and they are more like a series of unlocked doors than a fixed calendar.
This explainer walks through why the frame appears so soon, how the team decides what is safe, what the first weeks tend to look like, and where the mind needs as much rehabilitation as the limb.
What actually happens in trauma surgery recovery
Trauma surgery is any operation performed to repair injuries caused by external force: a fall, a road collision, a crush, a penetrating wound. Most of it, in practice, is orthopedic. Bones are realigned and held with plates, screws, rods or external frames; torn skin and muscle are cleaned and closed; occasionally an organ or blood vessel is repaired in the same admission.
Recovery is the process of turning that mechanical fix into a working body part again. It has three overlapping layers. The first is biological: bone knits, soft tissue seals and inflammation settles. The second is functional: joints regain range, muscles rebuild strength, balance returns. The third is psychological: the person absorbs what happened and learns to trust the limb, and the world, again.
The biology sets the pace but does not need coaching. The other two layers do. Muscle begins to weaken within days of immobility, and a joint left still for even a couple of weeks can develop tightness that takes far longer to undo. That is why the therapy team appears so early, often the day after the operation, according to NHS guidance on hip fracture care, which notes that patients are encouraged to get up and move as soon as possible, usually the following day.
Recovery is also not a straight line. Swelling can worsen before it improves, a second procedure is sometimes planned from the outset (for example, to remove a temporary frame), and progress is checked against imaging rather than the calendar. Understanding this structure helps patients read the milestones as information rather than as tests they can fail.
What is the "golden hour" in trauma surgery, and does it shape recovery?
The “golden hour” is a phrase from emergency medicine describing the idea that a seriously injured person’s chance of a good outcome is highest when bleeding is controlled and definitive care starts within roughly the first hour after injury. It shaped how ambulance systems, trauma centers and surgical teams are organized around the world.

Patients and relatives often ask whether they “missed” it. The honest answer has two parts. First, the strict 60-minute figure is a rule of thumb rather than a physiological threshold; research over the past two decades has found that time matters most for specific problems such as uncontrolled bleeding and severe head injury, while for many stable injuries the exact minute count is far less important. Second, the golden hour is about survival and preventing secondary damage, not about the speed of later rehabilitation.
Where early care does shape recovery is through what it prevents. Prompt restoration of blood flow to a limb reduces tissue death. Early stabilization of a long-bone fracture lowers the risk of fat embolism and lung complications and lets the patient sit up and breathe deeply sooner. Timely surgery for hip fracture, which the NHS describes as usually taking place within 48 hours of admission, is linked with earlier mobilization.
The scale of the problem explains why systems are built this way. The World Health Organization estimates about 1.19 million road traffic deaths a year and between 20 and 50 million non-fatal injuries, many of them requiring surgery and prolonged rehabilitation. The point, for someone already through the doors, is simple: the emergency phase is finished. The recovery phase runs on a different clock, and it rewards steadiness rather than speed.
What is the most common trauma surgery?
Fracture fixation is by a wide margin the most common operation in trauma surgery, and hip fracture repair in older adults is the single largest group within it in most high-income countries. The Centers for Disease Control and Prevention reports that about one in four adults aged 65 and older falls each year and that more than 300,000 older people are hospitalized for hip fractures annually in the United States, the overwhelming majority caused by falls.
Hip fracture repair takes two main forms. When the break is in the neck of the femur, the thigh bone, the damaged ball of the joint is often replaced with a metal implant, a procedure called hemiarthroplasty. When the break is lower, near the trochanters, the bone is usually held with a sliding screw and plate or a rod inside the bone, known as an intramedullary nail. Both are designed to be strong enough for walking almost immediately.
In younger adults, the pattern shifts toward high-energy injuries: fractures of the tibia and femur from road collisions, ankle fractures from sport and falls, wrist and forearm breaks from outstretched hands. Open fractures, where bone has broken through the skin, need urgent cleaning and sometimes staged operations with a temporary external frame before final fixation.
Why does this matter for recovery? Because the operation dictates the rules. A hip that has been nailed can usually take full body weight from day one. A shattered heel bone held with a plate cannot. Patients frequently compare notes on a ward and worry that a neighbor is walking while they are not. The difference is almost always the injury and the hardware, not the effort.
Why physiotherapy after fracture surgery starts within 24 hours
The strongest argument for early movement is what happens when people stay still. Lying flat slows blood flow in the legs, which raises the risk of deep vein thrombosis, a clot in a deep leg vein; the Mayo Clinic lists recent surgery and prolonged bed rest among the leading causes. Shallow breathing in bed lets the lower parts of the lungs collapse slightly and collect secretions, inviting pneumonia. Skin over the heels and tailbone breaks down under sustained pressure. Muscle bulk falls measurably within the first week of immobility, and older adults lose it fastest.
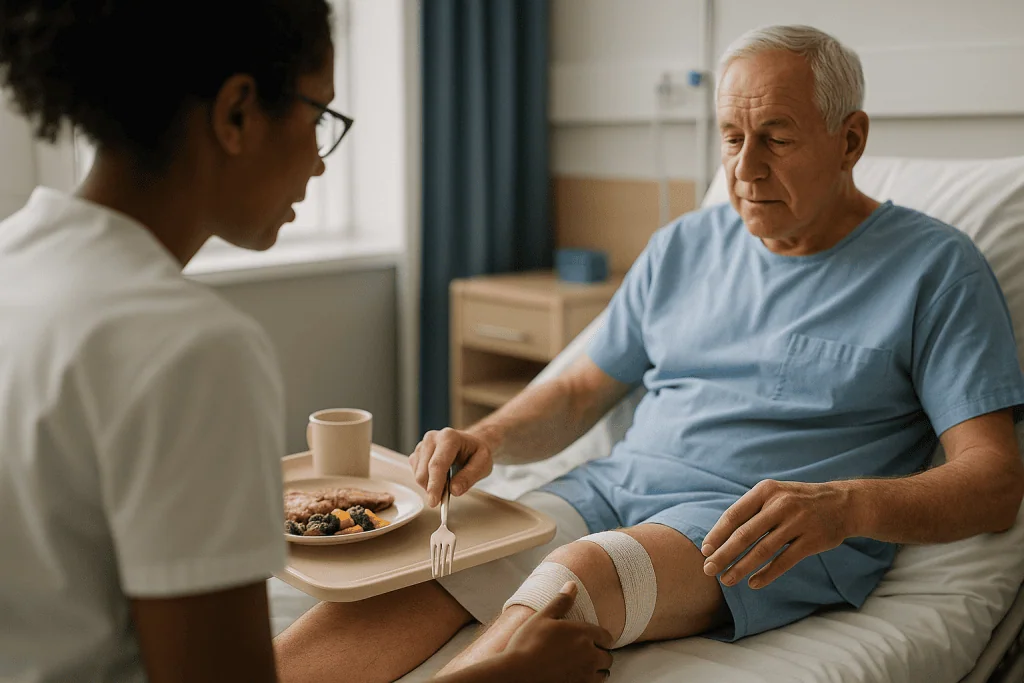
Early physiotherapy after fracture surgery targets each of those risks at once. Sitting on the edge of the bed drains the lungs and lets the heart adjust to being upright. Ankle pumps, tightening and relaxing the calf, squeeze the deep veins. Standing, even for a minute with a frame, loads the bones and reminds the nervous system what balance feels like. A short walk to the door does more for confidence than any reassurance from staff.
There is a second, quieter reason. The first session is an assessment as much as a treatment. The therapist watches how the patient transfers, how the operated limb tolerates load, whether dizziness or pain will limit progress, and how much help is needed at home. That observation feeds directly into the discharge plan.
None of this means pushing through warning signs. Early does not mean aggressive. A session might last five minutes and consist of breathing exercises and sitting up. The dose of movement, like the dose of any treatment, is set to the person and increased as tolerance grows.
Weight bearing after surgery: what the terms on your chart mean
Few instructions cause more confusion than weight-bearing status. The surgeon writes a short phrase in the notes and every subsequent decision about walking flows from it. The phrase reflects how stable the fixation is judged to be and how much load the healing bone can share with the metal before it knits.
| Term | Plain meaning | Typical everyday picture |
|---|---|---|
| Non-weight bearing | No load through the limb at all | Foot held off the ground; crutches, frame or wheelchair for every move |
| Toe-touch or touch-down | Foot rests on the floor for balance only | Like standing on an eggshell you must not crack |
| Partial weight bearing | A set fraction of body weight, often checked on scales | Leaning heavily on aids; the therapist shows the feel of it |
| Weight bearing as tolerated | As much as pain and confidence allow | Normal stepping, aids used for safety and reduced as able |
| Full weight bearing | No restriction from the repair | Walking limited only by strength and balance |
The status is a decision, not a constant. It can be relaxed at a follow-up appointment when X-rays show early healing, or tightened if hardware has shifted. Upper-limb injuries have equivalent rules about lifting and pushing through the hand.
Two practical points help. First, weight bearing after surgery usually refers to the healing bone; a patient who is non-weight bearing on one leg is often encouraged to work the rest of the body hard. Second, restrictions are only useful if they are understood, so it is entirely reasonable to ask the therapist to demonstrate exactly what the allowed amount feels like on bathroom scales before leaving hospital.
How recovery milestones are set after trauma surgery
Milestones are not pulled from a chart on the wall. They are negotiated between at least three sources of information, and understanding them demystifies the plan.
The first source is the injury and its fixation. The surgeon knows how many fragments there were, how well they came together, whether the bone quality was good or thin with osteoporosis, and how much the implant is being asked to carry. That knowledge produces the weight-bearing status and the range-of-motion limits, and it tells the team roughly when imaging should be repeated.
The second source is the person. Age, other conditions such as diabetes or heart disease, smoking, nutrition, prior mobility and home layout all change what is realistic and safe. A milestone such as “climb stairs with a rail” matters enormously for someone with a bedroom upstairs and not at all for someone in a single-story apartment.
The third source is what happens in the room. Therapists measure joint angles with a goniometer, a simple protractor for limbs, count steps or seconds standing, and record pain scores before and after sessions. Progress against those measures, more than the date, decides when the next door opens.
Milestones are usually framed in tiers: early goals within the first days (sit out of bed, transfer to a chair, breathe and cough effectively), intermediate goals over the first weeks (walk a set distance, manage stairs, dress independently), and later goals over months (return to driving, work or sport). Each tier has entry criteria. If a criterion is not met, the plan pauses and the reason is investigated rather than the patient being pushed harder. That is the safeguard built into the system.
Who is asked to move early, and who is asked to wait
Most people are surprised to be in the first group. Patients with a stable fixation of a hip, femur, tibia or ankle, an uncomplicated wound and adequate pain control are typically sat out of bed within a day. Older adults after hip fracture are a priority for early walking precisely because they have the most to lose from bed rest, in muscle, in lung function and in independence.
Some patients are asked to wait, or to move only in restricted ways, and the reasons are specific rather than cautious by habit. Unstable pelvic or spinal fractures may require a period of protected positioning until the fixation or the bone is judged safe. A limb with badly damaged soft tissue, skin grafts or a flap may need elevation and stillness for several days so the new tissue can establish a blood supply. Injuries to more than one limb can leave a person with no safe way to bear weight, so early therapy focuses on the trunk, breathing and upper body until one leg is cleared.
Medical instability also delays mobilization. Low blood pressure, uncontrolled heart rhythm problems, a fresh chest injury with rib fractures, or confusion after anesthesia all make standing unsafe until treated. In these cases movement still begins, but in bed: ankle pumps, deep breathing, gentle hand and shoulder work.
A separate group is asked to slow down rather than wait: people whose enthusiasm outruns their fixation. Someone who walks well on day two but has a repair that cannot yet tolerate full load will be reined in, not because they are doing badly but because the metal has limits. The rule is the same for both groups. The pace is chosen to match tissue, not temperament, and it is reviewed constantly.
How long to recover from trauma surgery: what the first days and weeks usually look like
Every injury has its own arc, so what follows is a typical shape rather than a schedule. In the first 48 hours the focus is on pain control, breathing, sitting out and, where permitted, standing. Swelling peaks around this time, and the limb may look worse before it looks better. The NHS notes that hip fracture surgery generally takes place within 48 hours of admission and that walking practice begins soon after, usually the next day.
Days three to seven are about transfers and short walks. The therapist adds exercises for the muscles around the repair, teaches stairs if the home requires them, and the team plans discharge, which may be home with outpatient therapy or to a rehabilitation unit. Bruising spreads and yellows; that is blood tracking under the skin, not new bleeding.
Weeks two to six are the plateau that tests patience. Bone is laying down soft callus, the early scaffold of repair, but X-rays may still look unchanged, so restrictions usually remain. Strength returns gradually and stiffness is the main enemy. Home exercises matter more than clinic visits in this phase.
From roughly six weeks onward, follow-up imaging often shows early bridging, and weight bearing is frequently relaxed. NHS guidance for common lower-limb fractures suggests many take around six to eight weeks to knit, while complex or hip injuries need months, and the NHS advises that full recovery from a hip fracture can take considerably longer. Return to work, driving and sport is decided individually and often falls between three and twelve months for high-energy injuries. How long to recover from trauma surgery is therefore a question with a range, not a number, and the treating team is the only source able to narrow it for a specific person.
Pain control after surgery: how the medicines work and why timing matters for therapy
Good pain control is not a comfort measure bolted onto rehabilitation; it is what makes rehabilitation possible. A person in severe pain breathes shallowly, guards the limb and cannot tolerate the movement that prevents complications. The aim is to bring pain down to a level where therapy is achievable, not to eliminate it entirely, which is rarely realistic in the first days.
Teams usually combine several classes so that each can be used at lower intensity. Simple analgesics such as acetaminophen work centrally on pain signaling. Anti-inflammatory medicines reduce the chemical messengers that make injured tissue tender, though they are avoided in some patients because of kidney, stomach or bleeding concerns and because of questions about their effect on bone healing. Opioids act on receptors in the brain and spinal cord and are typically reserved for the most severe early pain and tapered as quickly as the person can manage, because constipation, drowsiness and confusion all hinder mobilization. Nerve blocks, an injection of local anesthetic around a nerve, can numb a region for hours and are common after hip and lower-limb surgery.
Timing is a practical lever. Many wards deliberately schedule medicine so that its peak effect coincides with the therapy session, and patients at home can plan exercise similarly. Ice, elevation and positioning reduce swelling, which is itself a source of pain.
Every decision about which medicine, how much and for how long belongs to the prescribing clinician, who weighs the injury against the individual’s health history. Patients should never adjust or stop a prescribed medicine on their own; what they can usefully do is report honestly how pain limits movement, because that information changes the plan.
Preventing clots, stiffness and infection during recovery
Three complications account for most of the setbacks in the weeks after trauma surgery, and each has a prevention strategy that patients can actively join.
Deep vein thrombosis, a blood clot in a deep leg vein, is the one clinicians watch most closely. The Mayo Clinic identifies injury, surgery and immobility as major risk factors, and a fragment that travels to the lungs, a pulmonary embolism, can be life-threatening. Prevention layers several measures: early walking, calf-muscle exercises in bed, compression stockings or pneumatic sleeves, and, for many patients, an anticoagulant, a medicine that slows clot formation, prescribed for a period the surgeon decides. Hydration helps too.
Stiffness is quieter but can be just as disabling. A knee that loses the last 20 degrees of bend struggles with stairs and chairs; a shoulder that tightens after a collarbone repair may need months of work. The therapist’s range-of-motion exercises are the treatment, and their value lies in repetition several times a day rather than one heroic session. Scar tissue forms fastest in the first weeks, so this is when the gains are cheapest.
Infection risk is highest with open fractures and around external frame pins. Signs include spreading redness, increasing rather than decreasing pain, cloudy discharge and fever. Wound care instructions, keeping dressings dry and clean, and completing any prescribed antibiotic course as directed all matter.
A fourth problem deserves a name because it is an emergency: compartment syndrome, in which swelling inside a tight muscle compartment cuts off blood flow. The Cleveland Clinic describes pain out of proportion to the injury, worsened by stretching the muscle, with tightness, numbness and pallor. It requires immediate assessment, not a wait-and-see approach.
What is the hardest trauma to recover from?
People ask this hoping for a ranking, and clinicians resist giving one, because difficulty depends as much on the person as the injury. Still, some patterns are consistent enough to state plainly.
Injuries that involve the nervous system tend to be hardest. Spinal cord injury and severe traumatic brain injury change how the body is controlled, not just how it is built, and recovery involves relearning rather than simply reloading. Rehabilitation is measured in months to years and often shifts toward adaptation.
Among purely orthopedic injuries, high-energy fractures of the pelvis and acetabulum, the socket of the hip joint, are notoriously demanding: they involve large bones, nearby organs and vessels, long periods of restricted weight bearing and a real risk of later arthritis. Fractures around the ankle joint surface, such as the tibial plafond, and crushed heel bones can leave lasting stiffness. Open fractures with soft-tissue loss carry infection and non-union risks and may need several operations.
Multiple injuries at once, called polytrauma, are hard for a different reason: there is no uninjured limb to lean on, so the usual strategy of protecting one side while using the other fails, and the metabolic cost of healing several wounds is high.
Then there is the hip fracture in a frail older adult, which is rarely described as dramatic yet is among the most consequential. The CDC counts more than 300,000 such hospitalizations a year in the United States. The fracture itself is fixable; the challenge is that a person with little reserve can lose independence during weeks of reduced mobility. This is precisely why early physiotherapy is prioritized in that group. Hard, in trauma, usually means slow, not hopeless.
Mental recovery after surgery: how to rebuild confidence as well as bone
The limb is not the only thing that was injured. Many people who arrive in a trauma ward were, an hour earlier, going about an ordinary day. That suddenness leaves a mark. Vivid replaying of the event, jumpiness, trouble sleeping and a flat, detached feeling are common in the first weeks and are part of a normal stress response, not a sign of weakness.
The National Institute of Mental Health explains that most people recover from these acute reactions on their own, and that a diagnosis of post-traumatic stress disorder is considered when intrusive memories, avoidance, negative mood changes and heightened arousal persist for more than a month and interfere with daily life. Recognizing that timeline helps patients and families: distress in week one is expected, distress that is not easing by week six deserves a conversation.
Practical steps support mental recovery after surgery without any special program. Keeping a simple routine, including the therapy exercises, restores a sense of agency. Sleep protection matters; pain, medicines and hospital noise disrupt it, and asking the team about sleep is legitimate. Talking about the event with someone trusted, at the pace that feels right, tends to reduce its charge, while forcing oneself to relive it does not.
Fear of re-injury can quietly hold back physical progress. A patient who will not put weight on a cleared limb because it “feels wrong” is not being difficult; the nervous system is protecting a remembered threat. Therapists see this constantly and use graded exposure, small steps repeated until they feel ordinary. If low mood, panic, flashbacks or thoughts of self-harm appear, the treating team can involve psychological services; that referral is a standard part of trauma care, not a separate or lesser pathway.
What people often get wrong about trauma surgery recovery
“Rest heals; movement risks the repair.” The reverse is closer to the evidence. Controlled loading stimulates bone and keeps joints and muscles working, while prolonged rest raises the risk of clots, chest infection and permanent stiffness. The repair is protected by the weight-bearing rules, not by immobility.
“If the X-ray looks the same, nothing is happening.” Early callus is soft and often invisible on plain films for several weeks. Biology is working before the image changes.
“The metal means the bone is fixed.” Plates, screws and nails hold the pieces in position so the bone can heal itself. Until it does, the hardware is carrying load it was not designed to carry forever, which is the whole reason for restrictions.
“Pain means damage.” Post-operative pain during therapy usually reflects stiff tissue being moved, not harm. The exception is pain that is new, escalating, out of proportion or accompanied by numbness, swelling or fever, which must be reported.
“Everyone with the same fracture should be at the same stage.” Two people with the same named injury can have different fracture patterns, bone quality, fixation and health. Comparing progress on a ward is natural and almost always misleading.
“Supplements will speed bone healing.” Adequate protein, calcium and vitamin D matter, and deficiencies are corrected, but there is no robust evidence that extra doses of any supplement beyond correcting a deficiency accelerate fracture healing in otherwise well-nourished adults. Smoking, by contrast, has consistent evidence of slowing union.
“Once I can walk, I have recovered.” Walking is one milestone. Strength, balance, endurance, confidence and return to previous roles usually lag by months, and that later phase is where home exercise pays off most.
Questions to ask your care team about milestones and therapy
Good questions turn a plan into a shared plan. These are ones patients and families often wish they had asked before discharge.
- What exactly is my weight-bearing status, and can the therapist show me what that amount feels like on scales?
- Which movements or positions are restricted, for how long, and what would change that?
- What are my milestones for the next two weeks, and how will you measure whether I have reached them?
- When is my next X-ray or review, and what are you looking for on it?
- How should I time my pain medicine around exercise sessions, and who do I contact if pain stops me exercising?
- What is my clot-prevention plan, and for how long?
- Which signs would you want me to report the same day rather than wait for the next appointment?
- How should I care for the wound, dressings or pin sites, and when can I shower?
- Is there anything about my home, stairs, bathroom or bed, that I should change before discharge?
- When is it realistic to think about driving, work or sport, and who will make that call?
- If I am struggling with sleep, mood or memories of the accident, who on the team should I tell?
Writing the answers down, or having a companion do so, is worth the small awkwardness. Hospital information arrives quickly and often while a person is tired or medicated. A one-page summary of restrictions, exercises, contacts and dates is the single most useful object to leave with, and most therapy teams will help produce one if asked.
When to call your doctor
Most bumps in recovery are ordinary: aching after a long therapy session, a bruise that spreads, a day of low mood. Some are not, and the distinction is about pattern and pace rather than intensity alone.
Seek emergency care immediately for sudden breathlessness, chest pain or coughing up blood, which the Mayo Clinic lists as warning signs of a pulmonary embolism; for pain in the operated limb that is severe, rapidly worsening and out of proportion to the injury, especially with tightness, numbness, tingling or pale skin, which the Cleveland Clinic describes as features of compartment syndrome; and for a limb that becomes cold, white or blue.
Contact the surgical team the same day for a calf that is newly swollen, warm, tender or red, since these are typical signs of deep vein thrombosis; for fever with a wound that is increasingly red, hot, swollen or leaking cloudy fluid; for a sudden loss of function, a new grinding sensation or deformity around the repair after a slip or fall; for numbness or weakness that was not present before; and for pain that is climbing over days despite rest and prescribed medicine.
Do not hesitate to call about mental health. Persistent flashbacks, nightmares, panic, feeling detached from life, or thoughts of harming yourself warrant prompt contact with the team or an emergency service. Confusion, particularly in an older adult, should also be reported quickly, as it can signal infection, medicine effects or dehydration.
The general rule is simple. If something has changed for the worse and you cannot explain it, or your instinct says it is wrong, make the call. Trauma teams would far rather review ten false alarms than miss one clot or one infected wound. Every decision about what happens next belongs with the treating team, who know the injury and the repair.
Frequently asked questions
How to mentally recover from surgery after a traumatic injury?
Mental recovery follows a similar arc to physical recovery: expect turbulence early, then gradual settling. Keep a daily routine that includes your exercises, protect sleep, and talk about the event with someone you trust at your own pace. Intrusive memories or jumpiness in the first weeks are normal stress responses. If they persist beyond a month or interfere with life, tell your treating team, who can involve psychological support.
What is the hardest trauma to recover from?
Injuries to the nervous system, such as spinal cord injury and severe brain injury, are generally the hardest because they affect control of the body, not just its structure. Among bone injuries, high-energy pelvic and joint-surface fractures, open fractures with soft-tissue loss, and multiple simultaneous injuries are the most demanding. Difficulty also depends heavily on age, health and support, so rankings are only rough guides.
What is the most common trauma surgery?
Fixation of broken bones is the most common trauma operation, and hip fracture repair in older adults is the largest single group in most high-income countries. The CDC reports more than 300,000 hip fracture hospitalizations among older Americans each year, most from falls. Ankle, wrist, tibia and femur fractures follow, with patterns shifting toward high-energy injuries in younger adults.
What is the golden hour in trauma surgery?
The golden hour is the emergency-medicine principle that outcomes for severely injured people are best when bleeding is controlled and definitive care begins within roughly the first hour. The strict 60-minute figure is a rule of thumb rather than a biological threshold, and research shows it matters most for uncontrolled bleeding and head injury. It concerns survival, not the speed of later rehabilitation.
How long does it take to recover from trauma surgery?
It depends on the injury, the repair and the person. NHS guidance suggests many simple lower-limb fractures knit in roughly six to eight weeks, while hip and complex injuries take months, and return to work or sport after high-energy injuries often falls between three and twelve months. Only your treating team can narrow that range, and they will do so based on imaging and functional milestones.
Why does physiotherapy after fracture surgery start so soon?
Because the risks of staying still begin within days: clots in the leg veins, partial lung collapse and infection, pressure sores and rapid muscle loss. Early sessions are gentle, often just sitting up, breathing exercises and ankle pumps, and they double as an assessment of how you move and what help you will need at home. The dose of movement is increased as your tolerance grows.
What does weight bearing after surgery actually mean?
It describes how much of your body weight can go through the operated limb. Non-weight bearing means none; toe-touch means the foot rests for balance only; partial means a set fraction, often practiced on scales; weight bearing as tolerated means as much as comfort allows; full means no restriction from the repair. The status reflects how stable the fixation is judged to be and is revised at follow-up.
Is pain during physiotherapy a sign that I am damaging the repair?
Usually not. Discomfort while moving stiff joints and weak muscles is expected and typically eases after the session. The pattern to report is different: pain that is new, escalating over hours, out of proportion to what you are doing, or accompanied by numbness, tightness, marked swelling or fever. Those features need same-day assessment, and severe disproportionate pain with tightness is an emergency.
Do supplements or special diets speed up bone healing?
Correcting a genuine deficiency in protein, calcium or vitamin D supports healing, and teams check for these. There is no robust evidence that extra doses beyond correcting a deficiency make fractures knit faster in otherwise well-nourished adults. Stopping smoking, by contrast, has consistent evidence of improving bone union. Any supplement should be discussed with the treating team, particularly alongside prescribed medicines.
What should I do if I fall or slip on the operated leg at home?
Contact your surgical team the same day, even if it seems minor. A slip can loosen hardware or shift a healing fracture before it shows in obvious ways. Report any new deformity, grinding sensation, sudden inability to bear the weight you were previously allowed, or sharply increased pain. Severe pain with tightness, numbness or a cold, pale limb should be treated as an emergency.
References
- NHS: Broken hip (hip fracture)
- CDC: About Older Adult Fall Prevention
- WHO: Road traffic injuries fact sheet
- Cleveland Clinic: Compartment syndrome
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Total vs Partial Shoulder Replacement: Which Joint Surfaces Are Replaced and Why
A total shoulder replacement resurfaces both sides of the ball-and-socket joint: the rounded top of the upper arm bone and the shallow socket on…

Who Is a Candidate for Robotic Knee Replacement? What Orthopedic Surgeons Weigh
A robotic knee replacement candidate is generally an adult with advanced knee arthritis whose pain and stiffness limit daily life despite non-surgical care such…
What Do Feet Usually Look Like After Clubfoot Treatment? Realistic Long-Term Expectations
After successful clubfoot treatment, most feet look close to typical: the sole sits flat on the floor, the foot points forward, and ordinary shoes…

Hip Precautions After Hip Replacement: Which Movements Are Limited Early and for How Long
Hip precautions after hip replacement are movement limits that protect the new joint while the surrounding soft tissue heals. After a posterior approach they…

Does Foot Pain Always Need Surgery? Orthotics, Injections and When an Operation Makes Sense
No. Most foot pain is managed without an operation. Conditions such as plantar fasciitis, bunions, Morton's neuroma and many fractures usually respond to footwear…

Flying Home After Hand Surgery: Splints, Swelling and Timing Your Follow-Up Abroad
Most people can fly after minor hand surgery once the anesthetic has fully worn off, pain is controlled with the medicines they were prescribed,…