

Scar and Sun Care After Congenital Nevus Removal: Dressings, Sutures and the Months After
Key Takeaways
- Small congenital nevi occur in about 1 in 100 newborns, while the giant form (predicted adult size over 20 centimeters) affects roughly 1 in 20,000, according to MedlinePlus Genetics.
- Scars keep remodeling for 12 to 24 months, per the NHS, and commonly look redder and thicker at two months than at two weeks without anything being wrong.
- Surface stitches are typically removed within about 5 to 14 days, sooner on the face and later on the back and legs, while dissolving stitches are absorbed by the body over weeks.
- Sunscreen goes on only after the incision has sealed; until then, dressings, tape and clothing protect the wound, and shade plus reapplication every two hours protects it afterward.
- Keloids extend beyond the original incision and are more common on the chest, shoulders and upper back and in people with darker skin or a family history, so raise any past thick scars at the consultation.
- For giant nevi, MedlinePlus Genetics estimates a 5 to 10 percent lifetime melanoma risk that skin surgery does not remove entirely, which is why skin checks continue after the final operation.
After congenital nevus removal, scar care usually means keeping the incision covered and dry for the first day or two, following your surgeon's plan for suture removal or dissolving stitches, then shielding the maturing scar from sunlight for at least a year with clothing, shade and broad-spectrum sunscreen once the skin has sealed. Scars typically keep changing for 12 to 24 months, so patience and prompt review of any thickening matter.
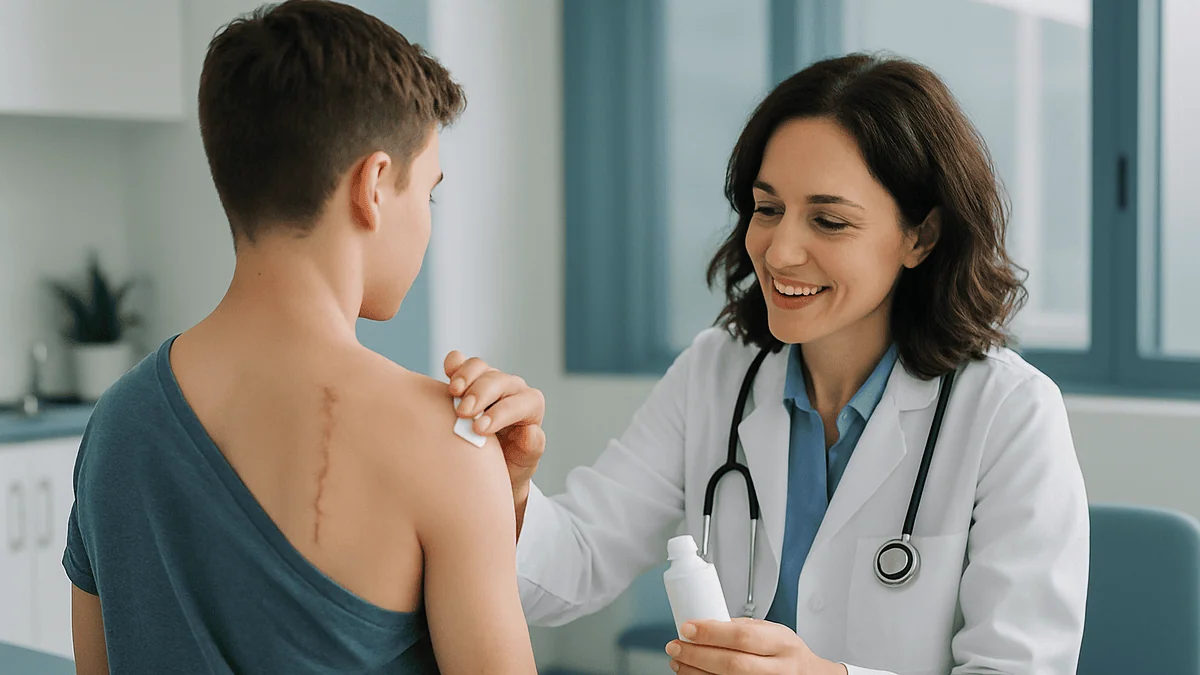
The dressing comes off tomorrow. Tonight, a father sits at the kitchen table reading the printed sheet for the third time, checking whether “keep dry” means no bath at all or just no soaking, while his eight-year-old sleeps upstairs with a neat strip of tape across her shoulder blade where the brown birthmark used to be. The operation was the short part. The long part, he is realizing, is congenital nevus scar care: the weeks of tape and ointment, and the summers of sunscreen ahead.
Surgeons tend to talk about margins and closure. Families tend to ask about the line that will be left behind. Both are right to care, because a scar that is protected, kept flat and shaded in its first year usually settles far better than one that is picked at, sunburned or forgotten.
This explainer walks through what actually happens under a healing wound, how dressings and stitches are managed, why a young scar tans so easily, and which parts of aftercare have real evidence behind them.
What is a congenital nevus, and why does the scar conversation start before surgery?
A congenital melanocytic nevus is a mole that is present at birth or appears within the first months of life; “melanocytic” simply means it is made of the pigment cells that give skin its color. Small ones are common. MedlinePlus Genetics puts small and medium nevi at roughly 1 in 100 newborns, while the giant form, defined by a predicted adult size larger than 20 centimeters, occurs in about 1 in 20,000 births.
Size drives almost everything about the scar. A coin-sized nevus on a forearm can be cut out in one visit and closed in a line. A nevus that wraps around a shoulder cannot; removing it may take several operations spaced months apart, with skin borrowed from neighboring areas. The final scar in those cases is not a line but a map, and families are usually shown drawings of it before anyone agrees to proceed.
That is why the scar conversation belongs at the first appointment, not the last. The NHS notes that removal of a congenital mole is sometimes recommended for larger lesions and sometimes chosen for appearance, and that the surgery itself leaves a scar. In plain terms, the trade is one visible mark for another, and the second mark is only worth it if the family understands what it will look like and how much care it needs.
People also ask how the surrounding skin behaves. Nevus skin is often thicker, hairier and less elastic than normal skin, which is one reason surgeons plan closures carefully and why tension on the wound edges becomes a recurring theme in the months that follow.
How congenital nevus scar care works: what actually happens under a healing wound
A scar is not a failure of healing. It is healing, viewed from the outside. Once the surgeon closes the skin, the body runs through three overlapping phases, and every aftercare instruction you receive maps onto one of them.

Inflammation comes first, over the opening days. Blood vessels leak fluid, immune cells arrive to clear debris, and the wound edges look pink and slightly puffy. This is why dressings matter most in the first 48 hours: they absorb ooze, keep bacteria out and stop clothing from tugging on fresh edges.
Proliferation follows, roughly from the end of week one through the first month. Cells called fibroblasts (the body’s builders of structural protein) lay down collagen quickly and somewhat messily, and new capillaries make the scar look red. Stitches are usually removed during this window, once the tissue can hold itself together.
Remodeling is the long tail. Over 12 to 24 months, according to the NHS, the disorganized collagen is slowly broken down and re-laid in tidier bundles, blood vessels retreat, and the scar fades from red to pink to something close to skin tone. Sun exposure interrupts this phase by stimulating pigment cells in the immature scar, and mechanical tension can push fibroblasts to keep building when they should be tidying.
Understanding these phases turns a list of rules into something logical. Keep it clean while it is inflamed. Support it while it is being built. Shade it and keep it supple while it is being remodeled. Almost everything else is detail.
Who is usually offered removal, and who is usually asked to wait?
Removal is a decision, not a default. The NHS describes congenital moles as usually harmless and notes that treatment is not generally needed, so the question becomes why a particular nevus should come off, and when.
Surgeons commonly discuss removal in a few situations: a large or giant nevus where the long-term melanoma risk is judged meaningful; a nevus in a spot that is hard to monitor, such as the scalp under thick hair; a lesion that has changed in a way the team wants examined under a microscope; or a nevus whose appearance is affecting a child’s or adult’s wellbeing. None of these is an automatic ticket to the operating room. Each is weighed against scar size, location and the number of procedures needed.
Some people are asked to wait. Newborns with very small lesions are often simply observed, since many small nevi are cosmetically minor and the melanoma risk is low. Children whose nevus sits on a joint or the face may be scheduled at an age when growth patterns are clearer or when they can take part in the decision. Anyone with an active skin infection near the site, poorly controlled medical conditions, or a recent history of problematic scarring may be asked to prepare first.
Timing arguments cut both ways. Infant skin is elastic and forgiving, which favors early staged surgery for giant nevi; on the other hand, an older child can express what bothers them and can cooperate with aftercare. The treating team, usually a dermatologist working with a plastic or pediatric surgeon, holds that balance. If you are unsure whether to proceed, the honest answer from most clinicians is that watchful monitoring is a legitimate plan, not a delay.
Congenital melanocytic nevus melanoma risk: what the evidence actually shows
Can a congenital nevus turn into melanoma? Yes, it can, and the risk depends heavily on size. That sentence deserves to be said calmly, because it is often either dismissed or dramatized.

For small and medium nevi, the risk is low and probably only modestly above that of the general population; most authorities, including the NHS, describe these moles as usually harmless. For giant nevi, MedlinePlus Genetics reports that an estimated 5 to 10 percent of affected people develop melanoma over their lifetime, with a notable share of those cases arising in childhood. Giant nevi with many satellite lesions, or those sitting over the spine, also carry a risk of neurocutaneous melanocytosis, in which pigment cells are present in the brain or spinal cord coverings; teams may recommend imaging in infancy for this reason.
Two points follow. First, surgery does not reset the risk to zero. Melanoma in people with giant nevi can arise in deep tissue or in the nervous system, places a skin excision never reaches, so follow-up continues after the last operation. Second, removal of a small nevus for appearance should not be sold to anyone as melanoma prevention; the numbers do not support that framing.
What monitoring looks like in practice is a full skin check with the same clinician at agreed intervals, photographs for comparison, and a low threshold for biopsy of any new lump, ulcer or color change within or near the nevus or its scar. Families sometimes worry that a healing scar hides trouble. It can be harder to read, which is one more reason the team wants to see it at each visit rather than relying on phone descriptions.
Excision, staged excision and tissue expansion: what each means for the scar
The technique the surgeon chooses shapes the aftercare you will be asked to do, so it helps to know the vocabulary.
Simple excision removes the nevus in one piece and stitches the skin edges together, leaving a line usually about three times the width of the mole. Serial or staged excision removes a strip from the middle of a larger nevus, lets the skin stretch over several months, then removes more at a later operation; the final scar is one line but the process takes longer. Tissue expansion places a deflating balloon under nearby healthy skin, which is gradually inflated over weeks at clinic visits; the stretched skin is then used to cover the area once the nevus is removed. Skin grafting takes a thin sheet of skin from elsewhere and lays it over the defect; grafts often leave a patch of different texture and a second donor-site wound.
| Approach | Typical use | Scar pattern | Aftercare emphasis |
|---|---|---|---|
| Simple excision | Small nevi | Single line | Suture care, tension relief, sun protection |
| Staged excision | Medium nevi | Single line after several operations | Repeated cycles of wound care over months |
| Tissue expansion | Large or giant nevi | Longer or curved lines, sometimes near the expander pocket | Expander site checks, infection watch |
| Skin graft | Areas without spare skin | Patch plus donor site | Graft immobilization, donor dressing |
Laser and dermabrasion have been used to lighten some nevi, but they leave pigment cells in the deeper skin and do not allow the tissue to be examined under a microscope. Most teams reserve them for selected cases and discuss the limits plainly.
Dressings and sutures: the first two weeks after congenital nevus removal
The printed sheet usually says the same three things, and they are worth following exactly. Keep the original dressing on and dry for the period the team specifies, commonly the first 24 to 48 hours according to MedlinePlus wound-care guidance. Wash hands before touching anything near the wound. Do not pick at scabs or tape.
Beneath the outer dressing there is often a second layer: thin adhesive strips laid across the incision, or a film of surgical glue. Both are designed to take tension off the stitches and both are meant to fall away on their own, usually over one to two weeks. Peeling them early is one of the most common ways a tidy line becomes a wide one.
Stitches come in two broad kinds. Dissolving sutures sit under the skin and are broken down by the body over weeks; nothing is removed, though a small knot end sometimes pokes through and is trimmed at clinic. Non-dissolving sutures on the surface are taken out at a follow-up visit, commonly within about 5 to 14 days depending on location, sooner on the face where blood supply is rich and later on the back or legs where skin is under more strain, per MedlinePlus.
Showering is usually allowed once the team says the wound has sealed; pat dry, do not rub. Soaking in baths, pools or the sea generally waits until sutures are out and any scabs have gone, because prolonged wetting softens the edges and invites bacteria.
A small amount of clear or pink fluid on the dressing in the first days is expected. Spreading redness, thick yellow drainage, a foul smell or a wound that gapes is not, and belongs in the red-flag section below.
Nevus removal scar healing time: what the weeks and months usually look like
People ask for a date on which the scar will be “done.” The honest answer is a curve rather than a date, and it is longer than most expect.
Weeks one and two are about closure. The line is red, slightly raised and tender; bruising around it fades from purple to yellow. Once the sutures are out, many teams ask you to keep supportive tape across the scar for several more weeks, especially on the chest, shoulders and back where skin pulls with every movement.
Weeks three to twelve are often the least reassuring. The scar may look more raised and redder than it did on the day the stitches came out. This is the proliferative phase doing its work, and it is not, by itself, a sign of trouble. Itching is common as nerve endings regrow.
From three months onward the scar should start to soften and pale. The NHS advises that scars can take up to two years to fade fully, and that a scar continues to change in color and texture throughout that time. A scar that is still growing thicker after about six months, or spreading beyond the original line, should be reviewed rather than watched.
Children add a twist: they grow. A scar placed on a five-year-old’s back will stretch as the child does, and a line that looked narrow at age six can widen by adolescence. Surgeons factor this into where they place incisions and sometimes into whether they suggest a scar revision later. Revision is a decision for a mature scar, generally not before 12 to 18 months, and always one the treating team makes with you.
Sun protection after mole removal: why a young scar burns and darkens
Fresh scar tissue has almost no working pigment cells of its own and a very thin outer layer. That combination means two things: it sunburns faster than the skin around it, and when the surrounding pigment cells do wake up, they respond to ultraviolet light unevenly. The result is a scar that turns darker than the neighboring skin, sometimes permanently.
Sun protection is therefore not a cosmetic extra. Most teams ask for strict shading of the scar for a full year, and many extend that advice to the entire remodeling window of up to two years described by the NHS. Practically, the CDC’s general sun-safety guidance transfers well: seek shade in the middle of the day when ultraviolet exposure peaks, cover with tightly woven clothing, wear a wide-brimmed hat for face and scalp scars, and use a broad-spectrum sunscreen of at least SPF 15 (many dermatologists favor 30 or higher), reapplied at least every two hours and after swimming or sweating.
Timing matters. Sunscreen goes on only after the wound has fully sealed and any scabs have gone; on an open or freshly closed incision it can irritate and, in theory, seed infection. Until then, the job belongs to clothing and tape.
For children, the easiest tool is often a rash vest or long-sleeved swim shirt, which also removes the daily negotiation about reapplication. Fabric with a stated ultraviolet protection factor is a bonus, though any dense, dark, dry fabric blocks far more than a wet white T-shirt. Winter does not cancel the rule; snow and altitude reflect and intensify ultraviolet light, and a scar does not know what month it is.
Silicone, massage and taping: which parts of scar care have evidence?
The aftercare aisle is crowded, and the evidence is thinner than the marketing. Here is how the main options stack up against mainstream guidance.
Silicone gel sheets and silicone gels are the most widely recommended first-line measure for reducing raised scarring. The NHS lists them among the treatments that may soften and flatten hypertrophic and keloid scars. Exactly how silicone works is debated; the leading explanation is that it keeps the outer layer hydrated and reduces signals that drive excess collagen. Reviews of the research describe the studies as small and of mixed quality, so the fair summary is “reasonable evidence of modest benefit, very low risk.” Sheets are usually started once the wound is closed and worn for many hours a day over several months.
Pressure, delivered by tape or garments, is used for scars over joints and after grafts. The NHS mentions pressure dressings as an option for keloids, usually under specialist direction.
Massage is widely taught by hand therapists and surgeons and is inexpensive and pleasant, but controlled evidence is weak. It probably helps mainly by keeping the scar mobile and by encouraging people to look at and care for it.
Vitamin E creams, cocoa butter and most “scar oils” have not shown benefit in good studies, and vitamin E in particular causes contact dermatitis in a proportion of users. Moisturizing with a plain emollient is sensible; expecting it to erase the line is not.
Corticosteroid injections, a class of anti-inflammatory medicine placed directly into thick scar tissue, are reserved for established hypertrophic scars and keloids and are given only by the treating clinician, who decides whether, when and how often.
Keloid after nevus removal: hypertrophic scars and who is at higher risk
Two kinds of thick scar get confused, and the distinction changes what your team will do. A hypertrophic scar is raised and red but stays within the boundaries of the original incision; it often improves on its own over a year or two. A keloid grows beyond the original wound, can keep enlarging for years, may itch or ache, and rarely settles without treatment. The NHS describes both, and notes that keloids are more common in people with darker skin and tend to run in families.
Location is a strong predictor. The chest, shoulders, upper back and earlobes are classic keloid territory, largely because skin there is under constant tension and moves with every breath and reach. Unfortunately, these are also common sites for medium and large congenital nevi. Surgeons planning an excision over the shoulder or sternum will often talk about this risk before the operation and may line the incision up with natural skin folds to reduce pull.
Personal history matters as much as geography. If you or your child formed a thick scar after a vaccination, ear piercing, chickenpox or a previous operation, say so at the consultation. Teams can plan closer follow-up, start silicone early and arrange review at the first sign of thickening.
Treatment of an established keloid is a specialist conversation. Options described by the NHS include silicone products, pressure, corticosteroid injections into the scar, and sometimes surgical removal combined with other measures, because cutting a keloid out on its own carries a real chance of it returning larger. Whether any of these is right for a particular scar sits with the dermatologist or plastic surgeon looking at it.
Congenital nevus scar care for children: comfort, itch and getting back to school
Children heal briskly and forget instructions instantly, which makes their aftercare both easier and harder. The practical goal is to make the right behavior automatic rather than negotiated.
Comfort comes first. Mild soreness for a few days is expected; the team will advise on simple pain relief and it is their call, not a guess from the medicine cabinet. Loose, soft clothing over the dressing prevents rubbing, and a short sleeve rolled over a shoulder dressing beats a strap sitting on top of it.
Itching arrives around the end of the first week and can be intense. Cool compresses over the intact dressing, a plain emollient once the wound is sealed, and keeping fingernails short all help. Some children do better with a thin cotton layer they are allowed to scratch through, rather than an outright ban on touching.
School and play usually resume within a few days for small excisions, with contact sports, swimming and gym paused until sutures are out and the wound is sealed. Larger or staged procedures, and anything involving a tissue expander, follow a slower path set by the surgeon. A brief letter for the teacher explaining the dressing and the no-swimming rule saves a great deal of playground debate.
Sun rules are easiest when they apply to the whole family. A child who sees everyone pull on a rash vest and hat learns the habit without feeling singled out. For scalp and facial scars, a broad-brimmed hat with a chin strap survives recess better than a cap.
Finally, let the child look. Seeing the scar change from red to pale over months turns something frightening into something they can describe, and it makes them far more likely to tell you when something feels different.
What people often get wrong about scars after nevus removal
Some misunderstandings show up in almost every follow-up clinic. Correcting them early saves worry and, occasionally, saves a scar.
“Let it breathe.” Wounds heal faster and with less scarring when kept covered and moist, not dried out in the air. The old advice to leave a cut open was reversed by decades of wound research, and modern dressings are designed around it.
“Redness means infection.” A healing scar is red because it is full of new blood vessels, and it often stays red for months. Infection looks different: spreading redness beyond the line, heat, swelling, thick discharge, fever. The color of the line itself is not the signal.
“The scar looked better at two weeks than at two months.” It probably did, and that is normal. Scars commonly thicken and redden during the proliferative phase before softening. The trend over six months matters more than any single snapshot.
“Sunscreen on day one.” Sunscreen belongs on sealed skin. Before then, clothing and dressings do the job.
“Vitamin E fixes everything.” It does not, and it irritates a meaningful minority of people. Plain moisturizer and silicone have a better case.
“Removing the mole removes the melanoma risk.” For small nevi the risk was low to begin with; for giant nevi, deep and neurological tissue is untouched by skin surgery, so surveillance continues. MedlinePlus Genetics is clear that the elevated risk with giant nevi is lifelong.
“The scar is finished at a year.” The NHS gives up to two years for maturation. Scar revision, if ever considered, waits for that maturity.
“A wide scar means the surgeon did a poor job.” Scar width is mostly decided by skin tension, location, genetics and aftercare, not by stitch count.
Questions to ask your care team before and after congenital nevus removal
Consultations are short and the questions that matter tend to arrive in the car afterward. Bringing a list changes that. These are the ones experienced families and patients wish they had asked.
- Which technique are you planning, and roughly what will the final scar look like and where will it run? Could you draw it?
- Will this take one operation or several, and over what typical span of months?
- Are the stitches dissolving or will they be removed, and when is that visit?
- Exactly when can the dressing come off, when can we shower, and when can we swim?
- Do you want tape or silicone on the scar after closure, and for how long each day and for how many months?
- How long should the scar be kept out of the sun, and when is sunscreen safe to apply?
- Given the site and our family history, what is the chance of a thick or keloid scar, and what would you do if one starts?
- Will the removed tissue be examined under a microscope, and when will we hear the result?
- How will the remaining skin, and any satellite moles, be monitored afterward, and how often?
- For a child: how will growth affect this scar, and might revision be discussed later?
- What signs should make us call the same day, and what number do we use out of hours?
Write the answers down, or ask whether they can be added to the discharge letter. Aftercare instructions vary between surgeons for good reasons, and the version that applies is the one given by the team that operated. If two pieces of advice seem to conflict, ask rather than average them.
When to call your doctor: red-flag signs after nevus removal
Most recoveries are uneventful, and most calls to the clinic are reassurance rather than emergency. Even so, a short list of signs should prompt a same-day call to the team that performed the surgery, or urgent care if they cannot be reached.
Call promptly for infection signs: redness spreading outward from the incision, increasing warmth or swelling, thick yellow or green discharge, a bad smell, a fever, or pain that is getting worse after the first few days rather than easing. Call if the wound edges separate or a stitch pulls through, if there is bleeding that does not stop after ten minutes of firm pressure, or if a skin graft or expander site changes color, becomes dusky or develops a fluid collection.
Later, contact the team if the scar keeps thickening or spreading beyond the original line after about six months, or if it becomes painful and hard rather than softening. Ask for review of any new lump, ulcer, bleeding point, or new pigment appearing in or beside the scar, or any change in remaining nevus tissue or satellite moles; these need to be seen, not described over the phone.
Seek emergency care if a child with a large or giant nevus develops persistent headache, repeated vomiting, seizures, unusual drowsiness or a change in movement or behavior, since MedlinePlus Genetics notes that pigment cells can also involve the brain and spinal cord coverings in this group.
Trust the instinct that something is not right. Surgical teams would far rather see a wound that turns out to be fine than hear about one a week too late. Every decision about treatment, revision or further tests rests with the clinicians who know the case, and a quick call is how that conversation begins.
Frequently asked questions
Can a congenital nevus turn into melanoma?
It can, and the risk rises with size. Small and medium congenital nevi are considered usually harmless by the NHS, with only a modest increase over general risk. For giant nevi, MedlinePlus Genetics estimates that 5 to 10 percent of affected people develop melanoma in their lifetime, sometimes in childhood. Regular skin checks by the same clinician, with photographs for comparison, are the standard way to monitor any congenital nevus.
How rare is a nevus birthmark?
Small congenital melanocytic nevi are not rare at all: MedlinePlus Genetics estimates about 1 in 100 newborns has one. The giant form, larger than 20 centimeters in predicted adult size, is uncommon, at roughly 1 in 20,000 births. So a pediatrician sees small congenital moles routinely, whereas giant nevi are usually managed by specialist dermatology and plastic surgery teams.
Should I get a congenital nevus removed?
There is no single right answer, and monitoring is a legitimate plan. Removal is more often discussed for large or giant nevi with meaningful melanoma risk, lesions that are hard to watch, moles that have changed, or appearance that affects wellbeing. Each reason is weighed against scar size, location and the number of operations. The decision belongs with you and the treating team after seeing the lesion in person.
How do you get rid of a nevus birthmark, and what scar does it leave?
Surgical excision is the standard method because it removes the pigment cells fully and allows the tissue to be examined under a microscope. Small nevi leave a line roughly three times the mole’s width; larger ones may need staged excision, tissue expansion or grafting, leaving longer or patch-shaped scars. Laser can lighten some nevi but leaves deeper cells behind, so most teams reserve it for selected cases.
What is the typical nevus removal scar healing time?
The wound itself usually closes within two weeks, but the scar continues to change for much longer. The NHS advises that scars can take up to two years to fade fully, softening and paling from around three months onward. Expect the line to look redder and more raised during the first couple of months before it settles; a scar still thickening after six months should be reviewed.
How long does sun protection after mole removal need to continue?
Most teams ask for strict shading of the scar for at least a year, and many extend that through the full maturation window of up to two years described by the NHS. Use shade, clothing and hats first, then broad-spectrum sunscreen once the skin has sealed, reapplying every two hours and after swimming, in line with CDC sun-safety guidance.
Why does my child's scar itch so much?
Itching is a normal part of healing, usually starting toward the end of the first week as nerve endings regrow and the scar tissue is built. Cool compresses over the intact dressing, a plain emollient once the wound is sealed, and short fingernails help. Itching with spreading redness, warmth, discharge or fever is different and should be reported to the team the same day.
What are the signs of a keloid after nevus removal?
A keloid is a scar that grows beyond the edges of the original incision, often feels firm and rubbery, and may itch or ache; it can keep enlarging for months or years. A hypertrophic scar is also raised but stays within the incision and usually improves on its own. The NHS notes keloids are more common on the chest and shoulders and in people with darker skin, so early review matters.
Do silicone sheets really help scars?
Silicone gel sheets and gels are the most commonly recommended first-line measure for raised scars, and the NHS lists them among treatments that may soften and flatten hypertrophic and keloid scars. The supporting studies are small and mixed in quality, so the fair description is modest benefit with very low risk. They are started once the wound is closed and worn for many hours daily over several months.
Does removing a giant nevus remove the melanoma risk?
No. Surgery removes pigment cells in the skin, but MedlinePlus Genetics notes that in giant congenital nevi melanoma can also arise in deeper tissue or in the coverings of the brain and spinal cord, which excision never reaches. The risk is reduced but not eliminated, so lifelong skin checks and, where advised, neurological follow-up continue after the last operation.
References
- MedlinePlus Genetics: Giant congenital melanocytic nevus
- NHS: Birthmarks
- NHS: Scars
- MedlinePlus: Surgical wound care – closed
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Collagen Banking: The Trend Explained: What Stimulates Collagen and What Is Marketing
Collagen banking is a marketing term, not a medical one, for starting collagen-protecting habits early so skin stays firmer for longer. The best-supported steps…

Can Dandruff Cause Hair Loss? The Link, the Real Causes and How to Treat Both
Ordinary dandruff does not damage hair follicles, so on its own it does not cause lasting hair loss. Persistent scalp inflammation and repeated scratching…

Can Rosacea Be Cured, or Go Away Permanently?
Rosacea cannot be cured, and it rarely disappears permanently on its own. It is a long-term inflammatory skin condition that tends to flare and…

How Long Is Impetigo Contagious? When Children and Adults Can Return to School or Work
Impetigo is usually considered contagious until the sores have dried and crusted over, or until 24 to 48 hours after starting an effective antibiotic,…

How to Get Rid of Stretch Marks: Honest Answers From Dermatology
Stretch marks cannot be completely removed, but they usually fade considerably on their own, shifting from red or purple to a pale silver over…
Slugging: What Occlusive Skincare Does, and Who Should Skip It
Slugging means sealing your face overnight with a thin layer of an occlusive ointment, usually petroleum jelly, applied over your usual moisturizer. It reduces…