

SMR or Septoplasty: What Is the Difference, and When Do Surgeons Choose Submucous Resection?
Key Takeaways
- Submucous resection removes most of the deviated septal cartilage and bone from beneath the lining, while modern septoplasty removes or reshapes only the obstructing part and preserves the rest.
- Surgeons protect an L-shaped band of cartilage along the top and front of the septum, roughly a centimeter wide, because removing it risks a sunken bridge or drooping tip.
- Up to 80 percent of people have some septal deviation, and most never need surgery; the operation is for those whose blockage persists despite medical treatment.
- Resection is still deliberately chosen for thick bony deviations, severe post-traumatic deformity, revision cases, and when cartilage is needed as graft material for rhinoplasty or reconstruction.
- A randomized trial found septoplasty gave better nasal-obstruction-related quality of life than continued medical management over two years of follow-up.
- Congestion typically peaks in the first week, splints usually come out around a week, and Mayo Clinic describes tissues as relatively stable only at three to six months.
SMR (submucous resection) and septoplasty are both operations that straighten the wall between the nostrils. SMR, the older technique, removes most of the deviated cartilage and bone from beneath the lining, while modern septoplasty removes or reshapes only the bent portion and preserves as much cartilage as possible. Surgeons today usually favor septoplasty, reserving SMR-style resection for thick bony deviations, severe deformities, or cases where cartilage is needed for grafting.
The consent form said one thing and the clinic letter said another. On the first page, in a surgeon’s quick hand, were three letters: SMR. On the second, typed neatly, was a word that had filled the search bar for a week: septoplasty. The man holding both pages had spent months breathing through one nostril at night and now wondered whether he had agreed to two different operations, or one operation with two names.
He is not the only one confused. The phrase SMR vs septoplasty gets typed into search engines by people in exactly this position, and the answers they find are often either too technical or quietly out of date. Part of the muddle is historical: one technique grew out of the other, and in some parts of the world the older name never went away.
What follows is a plain account of what each operation actually does inside the nose, why most surgeons lean one way today, and the specific situations in which the older approach still earns its place.
Why does a bent nasal septum cause trouble in the first place?
The nasal septum is the thin wall of cartilage and bone that divides the inside of your nose into a left and right passage. In front it is mostly flexible cartilage; toward the back it becomes bone. A lining called the mucosa covers both sides, warming and moistening the air you breathe and trapping dust before it reaches the lungs.
Almost nobody has a perfectly straight one. Cleveland Clinic estimates that up to 80 percent of people have some degree of septal deviation, most of it harmless. The septum can bend during growth, after a childhood knock that nobody remembers, or from a clear injury such as a sports collision. Sometimes a sharp ridge or spur forms where cartilage meets bone.
Trouble starts when the bend narrows one passage enough to matter. Air has to squeeze through a smaller gap, so breathing through that side feels effortful, especially lying down or during a cold when the lining swells. The wider side often compensates by growing a larger turbinate, the shelf of tissue on the outer wall of each passage, which can then block the good side too. People describe mouth breathing at night, a dry throat in the morning, recurring sinus pressure, or nosebleeds where dry air hits a spur.
None of these complaints, on its own, points to surgery. A surgeon looks inside with a light or a thin telescope called an endoscope, matches what they see to what you describe, and considers whether the lining, the turbinates, allergies, or the septum itself is the main culprit. Only when the crooked wall is clearly the bottleneck does the conversation turn to straightening it, and that is where the two names in your paperwork come in.
SMR vs septoplasty: what do the two terms actually mean?
SMR stands for submucous resection. Break it down and the name describes itself: submucous means beneath the lining, and resection means cutting out. The operation lifts the mucosa off both sides of the septum and removes the deviated cartilage and bone underneath, then lays the lining back down. It was described in the early 1900s and for half a century it was simply how a crooked septum was fixed.
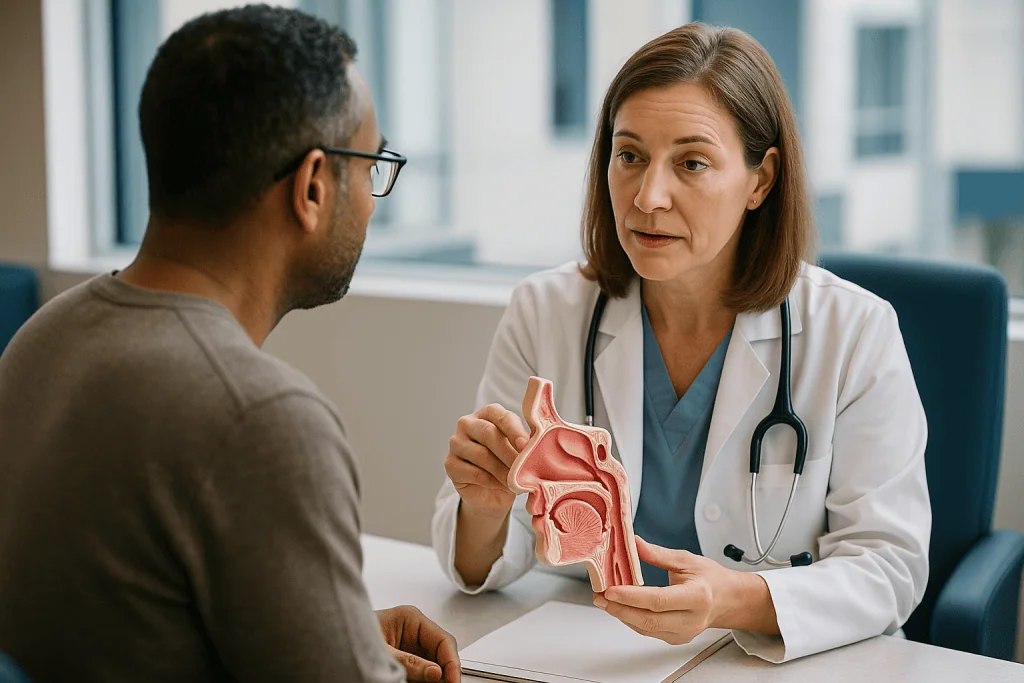
Septoplasty is the word most surgeons use now. The suffix -plasty means reshaping. Rather than taking out the bent framework, the surgeon removes only the piece that is actually causing obstruction, scores or thins cartilage so it will sit straight, and puts as much of it back as possible. The National Institutes of Health’s StatPearls chapter on septoplasty describes this as the conservative approach that replaced classic resection in most centers.
Here is the honest complication. In many hospitals, particularly across the United Kingdom, India, and parts of Africa and the Middle East, the letters SMR are still written on operating lists as a general term for any septal straightening, even when the surgeon intends a conservative, cartilage-sparing operation. Elsewhere, septoplasty is used as an umbrella that includes limited resection. The two words describe the ends of a spectrum more than two completely separate operations.
What matters for you is not the label but the plan: how much cartilage will come out, how much will stay, and why. A ten-second question to your surgeon, how much of the septum are you planning to remove?, tells you more than either abbreviation ever will.
What happens during a submucous resection of the nasal septum?
A classic submucous resection follows a fairly fixed sequence. You are usually asleep under general anesthesia, though some surgeons offer local anesthesia with sedation for straightforward cases. Everything happens inside the nostrils; there are no external cuts.
The surgeon makes an incision through the lining on one side, a little way back from the nostril rim, and then works a blunt instrument between the lining and the cartilage. Because the mucosa is only loosely attached, it peels away in a sheet, creating a pocket. The same is done on the opposite side, so the cartilage and bone sit exposed between two flaps of intact lining.
Now the resection itself. Large sections of the deviated cartilage and the bony plates behind it are cut free and lifted out. In the original technique, the goal was to remove nearly the whole central septum, leaving only a rim of cartilage along the top of the nose and along the front edge to hold the nasal tip up. The two flaps of lining are then laid back against each other, and with nothing rigid between them they eventually heal into a thin but complete wall.
The appeal is clear: whatever was crooked is simply gone, so the passage is reliably opened. The cost is structural. Without cartilage in the middle, the septum can flap slightly with breathing, and if both lining flaps are torn at the same spot during the operation, there is no cartilage between them to bridge the gap, which is how a septal perforation forms. Taking too much support along the top or front risks the bridge or tip of the nose sinking over time.
Surgeons learned these lessons the hard way, which is exactly why the operation evolved.
What happens during a modern septoplasty?
The first minutes look identical: anesthesia, an incision inside one nostril, lining lifted off the cartilage. The difference is in how the surgeon thinks about the framework once it is exposed.
Modern septoplasty treats septal cartilage as valuable real estate. The surgeon identifies the specific bend, spur, or thickened area that is narrowing the airway and deals with only that portion. A bony spur at the floor may be chiseled off. A curved section of cartilage may be scored on its concave side so the tension holding it bent is released and it springs straighter. A truly twisted piece may be removed, flattened on the back table, and slid back into the pocket as a straight graft.
Throughout, the surgeon protects what surgical texts call the L-strut: a continuous band of cartilage along the top of the septum and along its front edge, shaped like the letter L. StatPearls describes preserving at least about one centimeter in each limb so the nose keeps its shape. Everything inside the L is fair game; the L itself is left alone unless a rhinoplasty is planned alongside.
Many surgeons now do the whole procedure while watching through an endoscope, which magnifies the view and lets them reach deviations far back near the sinuses without disturbing the front of the septum at all. MedlinePlus puts the operating time for a typical septoplasty at about one to one and a half hours, and most people go home the same day.
At the end, the lining is closed with dissolving stitches, sometimes with soft silicone splints on either side of the septum to hold it straight while it heals. Nasal packing, once routine, is used far more selectively now.
SMR vs septoplasty at a glance: how the two techniques compare
The table below summarizes the classic descriptions of each operation. Individual surgeons blend elements of both, so treat this as a map of the territory rather than a promise of what your operation will contain.
| Feature | Submucous resection (SMR) | Modern septoplasty |
|---|---|---|
| Origin | Described early 1900s | Refined from the late 1940s onward |
| Core idea | Remove the deviated cartilage and bone | Remove only the obstructing part; reshape and preserve the rest |
| Cartilage left in place | Mainly a rim along the top and front | As much as possible, including a protected L-strut |
| Lining handling | Both sides lifted as flaps | Often one side lifted, the other left attached where feasible |
| Typical use today | Thick bony deviations, severe deformities, cartilage harvest | Most routine deviations, including endoscopic approaches |
| Main structural concern | Perforation, saddle or tip drooping, flapping septum | Residual deviation if too conservative |
| Use in children | Generally avoided | Used cautiously, cartilage-sparing |
A few points deserve a second look. The row on lining handling explains much of the difference in perforation risk: if the mucosa is only lifted on one side, a tear on that side still has intact lining opposite it, and the cartilage in between acts as a bridge while it heals. The row on cartilage left in place explains why some surgeons still choose resection deliberately. Septal cartilage is the best graft material in the nose, and an operation that removes a large, flat piece of it hands the surgeon exactly what a reconstruction may need.
Neither column is simply better. The right choice depends on where the bend is, what it is made of, and what else the nose needs.
When do surgeons still choose submucous resection?
If conservative septoplasty is the default, it is worth being specific about when a surgeon deliberately reaches for a more extensive resection. Several situations come up repeatedly in surgical teaching and in the StatPearls chapter.
The first is a deviation that is mostly bone rather than cartilage. Bone cannot be scored and coaxed straight the way cartilage can; a thick bony plate or a large spur along the floor has to be removed to open the airway. Since it sits behind the L-strut and offers no support to the outer nose, taking it out carries little structural penalty.
The second is severe, multi-directional deformity, often after significant trauma, where the cartilage is buckled in several planes and thickened by scar. Scoring one bend can worsen another. Removing the central block and replacing it with a straightened or reinforced piece is sometimes the more predictable route.
The third is planned grafting. In septorhinoplasty, where the outside of the nose is reshaped at the same time, or in reconstruction after injury, surgeons need strips of firm cartilage to support the tip, widen collapsed valves, or rebuild the bridge. Harvesting from the septum is standard, and the harvest itself is a submucous resection in all but name.
The fourth is revision surgery. When a previous operation has left scar tissue binding lining to cartilage, or has already removed part of the framework, the neat planes of a first-time septoplasty may not exist, and the surgeon adapts.
What has largely disappeared is routine resection for ordinary bends in otherwise healthy adults, and resection of any kind in growing children. The technique survives as a tool for particular problems, not as a first choice.
Who is deviated septum surgery usually for, and who is asked to wait?
Surgeons do not operate on crooked septums; they operate on people whose crooked septums are demonstrably causing trouble that has not responded to simpler measures. That distinction shapes who is offered an operation and who is asked to hold on.
The usual candidate is an adult with persistent nasal blockage on one or both sides, examined and found to have a deviation that plausibly explains it, who has already tried a period of medical treatment such as saline rinses and a nasal steroid spray without adequate relief. Recurrent nosebleeds from a dry spur, or a deviation that blocks access to the sinuses in someone who also needs sinus surgery, are other recognized reasons. Mayo Clinic notes that septoplasty is also sometimes performed to allow other procedures, such as sinus surgery or sleep-related airway surgery, to be carried out.
Several groups are commonly asked to wait or to consider alternatives first. Children and younger teenagers have septal cartilage that acts as a growth center for the mid-face, and removing it can affect how the nose and upper jaw develop; pediatric surgeons generally defer unless obstruction is severe, and when they operate they remove the minimum. People with uncontrolled allergic rhinitis are often treated for the allergy first, because swollen lining can mimic a septal problem and because surgery does nothing for the inflammation. Active smokers may be asked to stop beforehand, since smoking slows healing of the lining. Anyone with a bleeding disorder, on blood-thinning medicines, or with poorly controlled medical conditions needs those addressed and coordinated with the prescribing clinician before any elective operation.
Timing is also a matter of expectation. Surgery corrects a structural narrowing; it does not change how the lining reacts to pollen, smoke, or a cold. The best candidates are those whose main problem really is the wall.
Do sprays and other non-surgical options work as well as surgery?
This is the question behind the question, and the evidence is more nuanced than either camp likes to admit.
Medical treatment for nasal obstruction aims at the lining, not the framework. Saline rinses clear mucus and crusting. Intranasal corticosteroid sprays reduce inflammatory swelling of the mucosa over days to weeks, which widens the passage even though the septum has not moved. Antihistamines help when allergy is driving the swelling. Short courses of decongestant sprays shrink blood vessels in the lining quickly but cause rebound congestion if used for more than a few days, which is why clinicians limit them. None of these change a bent septum; they shrink the soft tissue around it. Whether that is enough depends on how much of the blockage was soft tissue to begin with. Decisions about starting, continuing, or stopping any of these belong with the prescribing clinician.
For years, surgery had surprisingly little trial evidence behind it. That changed with a randomized trial in the Netherlands, published in a major medical journal and indexed in PubMed, that assigned adults with symptomatic septal deviation either to septoplasty (with or without turbinate surgery) or to continued non-surgical management. Over two years of follow-up, the surgical group reported better nasal-obstruction-related quality of life than the medical group, and the benefit persisted at the two-year point. The authors were careful: this was one trial, in one health system, and it measured how people felt rather than airflow alone.
The sensible reading is that medical treatment is the right first step for almost everyone, that a fair proportion will be satisfied with it, and that for those who are not, surgery has trial-level support. It is not a case of one option being a myth.
Septoplasty vs rhinoplasty: will my nose look different afterward?
People often arrive at a consultation with two mixed-up fears: that septoplasty will change the shape of their nose, or that it will fix a shape they dislike. Usually neither is true.
Rhinoplasty is surgery on the outside framework of the nose, the bones and cartilages you can see and feel, undertaken to change appearance or to repair a collapsed or injured outer nose. Septoplasty is surgery on the inner dividing wall. Because a conservative septoplasty protects the L-strut and leaves the outer structure alone, the external shape should be unchanged. Cleveland Clinic describes the operation as one done entirely inside the nose with no visible scars.
The two operations do meet in the middle. When the outer nose is visibly twisted because the septum beneath it is twisted, straightening one without the other rarely works, and surgeons combine them as a septorhinoplasty. This is also the situation where a larger submucous resection becomes useful, since the cartilage removed from inside can be reused as grafts on the outside. If your surgeon has raised the possibility of a combined operation, ask specifically what they intend to change externally and why.
Where shape can change unintentionally is the rare complication rather than the plan. Removing too much support along the top of the septum can let the bridge sink slightly, called a saddle deformity; taking too much from the front edge can let the tip droop or the columella, the strip of skin between the nostrils, pull upward. These were more common in the era of aggressive resection and are precisely what the L-strut rule exists to prevent. They remain on every consent form because no rule eliminates risk entirely.
A practical note: swelling inside and around the nose in the first weeks can make the tip look slightly fuller or the nostrils uneven. Mayo Clinic notes that tissues continue to settle for months, so early appearance is not final appearance.
What are the risks, and how do they differ between SMR and septoplasty?
Every operation on the septum shares a core set of risks, and both Mayo Clinic and Cleveland Clinic list them in similar terms. Bleeding is the most common, usually minor oozing in the first days, occasionally heavier. Infection is uncommon in the nose because of its rich blood supply but can occur, particularly around splints or packing. A collection of blood under the lining, a septal hematoma, needs prompt drainage because it can starve the cartilage of nutrients. Temporary numbness of the front teeth or the tip of the nose, from small nerves that run along the septum, is common and usually resolves over weeks to months. A reduced sense of smell is reported by some and is usually temporary. There are also the general risks of anesthesia.
Two complications behave differently between techniques. Septal perforation, a hole through the wall between the two passages, requires the lining to be breached on both sides at the same spot with nothing between them to heal across. A wide resection that lifts both flaps and removes the cartilage beneath sets that stage more readily than a conservative operation that leaves cartilage in place. A small perforation may cause nothing more than a whistle on breathing; a larger one can cause crusting, bleeding, and a sensation of dryness, and repairing it is a more difficult operation than the original.
External shape change, the saddle or drooping tip described earlier, is the second technique-sensitive risk and is tied directly to how much supporting cartilage is preserved.
The flip side is the risk of doing too little. A very conservative septoplasty can leave a residual bend, and persistent obstruction after surgery is one of the more common reasons for dissatisfaction and for revision. Surgeons weigh these opposing risks for each nose, which is why the same surgeon may operate quite differently on two people with the same diagnosis.
Septoplasty recovery time: what the first days and weeks usually look like
Most people are surprised by the sequence: the nose feels worse before it feels better. Knowing the typical shape of recovery makes the early days less alarming. The ranges below come from Mayo Clinic and Cleveland Clinic patient guidance and are typical, not guaranteed.
Day of surgery: you wake with a blocked, stuffy nose from swelling, splints, and dried blood. A gauze dressing under the nostrils catches oozing and is changed as needed. Most people go home the same day once they are eating and drinking and bleeding has settled. Sleeping with the head raised on two or three pillows helps swelling drain.
Days two to seven: congestion is at its peak and breathing is often through the mouth. Mild aching, a dull headache, and a sore throat from mouth breathing are common. You will be asked not to blow your nose, to sneeze with the mouth open, and to avoid bending, lifting, or anything that raises blood pressure to the head. Saline sprays or rinses are usually encouraged to keep crusts soft; the surgical team will say when to start. Cleveland Clinic notes that many people return to desk-based work within about a week.
Around one week: the follow-up visit where splints, if used, are removed. Many describe this as the moment breathing noticeably opens up, though swelling of the lining still limits the full effect.
Weeks two to six: gradual clearing of internal swelling. Strenuous exercise, contact sports, and anything that risks a knock to the nose are usually restricted for several weeks; your team gives the specific date.
Three to six months: Mayo Clinic describes nasal tissues as relatively stable by this point, with subtle changes continuing for up to a year. Judging the result before then tends to be premature.
Turbinate reduction and other add-ons: why one operation is often two
Look closely at an operating list and septoplasty rarely appears alone. The commonest companion is turbinate reduction, and understanding why explains a lot about outcomes.
The inferior turbinates are the fleshy shelves running along the outer wall of each nasal passage. They swell and shrink through the day, alternating sides in a cycle most people never notice. When a septum bends to one side for years, the turbinate on the roomier side often enlarges to fill the extra space. Straighten the septum and that enlarged turbinate is suddenly in the way of the newly centered airway. Surgeons therefore often reduce it in the same session, by shrinking the tissue with heat or radiofrequency energy, trimming it, or removing some of the bone within it while keeping the lining intact.
The Dutch trial mentioned earlier deliberately allowed turbinate surgery alongside septoplasty because that is how the operation is done in practice. The two procedures address different parts of the same bottleneck.
Other pairings appear for specific reasons. Sinus surgery is sometimes combined when a deviation blocks access to the sinus openings. Nasal valve repair, which addresses collapse of the soft side walls of the nose on inhalation, is added when the surgeon identifies that problem on examination. Adenoid removal is a common companion in children whose obstruction is mostly at the back of the nose rather than the septum.
Why this matters to the SMR-versus-septoplasty question: the choice of septal technique is one decision among several. A conservative septoplasty combined with a well-judged turbinate reduction may open a nose that a wide resection alone would not, while avoiding the structural downsides of removing cartilage. Ask what else is planned, not just which septal technique.
What people often get wrong about SMR and septoplasty
Some misunderstandings surface at almost every consultation. Correcting them tends to make the actual decision easier.
SMR is obsolete or dangerous. Neither. Routine wide resection for simple bends has fallen out of favor because conservative techniques carry fewer structural risks, but targeted resection remains the right tool for bony deviations, severe deformity, and cartilage harvest. A surgeon who writes SMR on your list may be using a traditional label for a modern operation.
Septoplasty will stop snoring or treat sleep apnea. It may help a person breathe through the nose more comfortably at night and can make a mask for sleep apnea treatment easier to tolerate, but obstructive sleep apnea is usually a problem of the throat, not the nose. Mayo Clinic lists improving airflow, not resolving sleep apnea, as the aim.
Breathing will be clear the moment I wake up. The opposite. Swelling and splints block the nose for days, and the true result is only judged months later.
A deviated septum always needs fixing. Most do not. With up to 80 percent of people having some deviation, the question is whether yours is causing symptoms that persist despite medical treatment.
The operation changes how the nose looks. A properly performed septoplasty should not. Appearance is the province of rhinoplasty, which is a separate decision.
Nasal packing is always needed and always agonizing. Packing is used far more selectively now, and many surgeons rely on soft splints or dissolving materials instead.
Once it is straight, it stays straight forever. Cartilage has memory and can drift slightly during healing; a later injury can bend it again. Some people need revision, which is a recognized part of the picture, not a failure of the idea.
Questions to ask your care team before septal surgery
A good consultation leaves you knowing not just what the operation is called but what it will do. These questions are phrased so the answers are concrete.
- Which part of my septum is causing the obstruction, and is it mainly cartilage, bone, or both?
- How much of the septum do you plan to remove, and how much will you preserve? Do you expect to lift the lining on one side or both?
- If you are calling this SMR, do you mean a wide resection or a general term for septal straightening?
- Are you planning turbinate reduction, valve repair, sinus surgery, or any change to the outside of my nose at the same time, and why?
- Will you use an endoscope, splints, or packing, and when would they be removed?
- What have I not yet tried medically that might make surgery unnecessary, and how long should a trial of that reasonably last?
- What is your approach to protecting against perforation and changes in nasal shape?
- Which of my current medicines, supplements, or health conditions need attention before surgery, and who coordinates that?
- What does recovery typically look like in your practice, and when could I expect to return to work, exercise, and travel?
- What would make you consider the result unsatisfactory, and what would the options be then?
Bring someone with you if you can; two sets of ears catch more. Ask for the plan in writing if the paperwork uses one term and the conversation another. And remember that a surgeon who says I will decide the exact extent once I see the cartilage is being honest rather than evasive; the final technique often does depend on what is found. The decision about whether and how to operate rests with you and the treating team together, informed by examination rather than by a search result.
When to call your doctor after septoplasty or SMR
Some oozing, congestion, mild pain, and a low mood in the first week are expected. A handful of signs are not, and they warrant a call to the surgical team or, if severe, urgent care. Your discharge sheet will have specific contact numbers; use them.
Call promptly for bleeding that soaks through dressings repeatedly or runs steadily down the throat and does not slow with sitting upright, leaning forward, and gentle pressure on the soft part of the nose. Brisk, bright-red bleeding that will not stop is an emergency.
Call for a fever, worsening rather than easing pain, or a foul smell or thick discolored discharge from the nose, which can signal infection or a problem around splints or packing. A sudden increase in blockage on one side with pain and a feeling of pressure can indicate a hematoma, a blood collection under the lining that needs draining.
Call the same day for clear, watery fluid dripping steadily from the nose, especially when leaning forward, or a severe headache with a stiff neck. These are rare but can indicate a leak of the fluid that surrounds the brain, and they need assessment.
Seek urgent care for changes in vision, swelling or bruising around the eyes that is getting worse, or numbness spreading across the cheek. Chest pain, breathlessness, or a painful swollen calf after any operation should be treated as an emergency because of the possibility of a blood clot.
Finally, if the outside of your nose looks noticeably different, if you notice a whistling sound on breathing, or if obstruction has not improved once the months of healing have passed, bring it to your follow-up appointment. These are not emergencies, but they are exactly the things your surgeon wants to know about, and they are far easier to address when raised early.
Frequently asked questions
Is SMR the same as septoplasty?
Not exactly, though the terms overlap. Submucous resection is the older technique that removes most of the deviated cartilage and bone beneath the nasal lining. Septoplasty is the modern, cartilage-sparing approach that corrects only the obstructing portion. In some countries SMR is still used as a general label for any septal straightening, so ask your surgeon how much cartilage they intend to remove rather than relying on the abbreviation.
What is a submucous resection of the nasal septum used for today?
Mainly for problems that conservative reshaping cannot solve. Surgeons choose a fuller resection when the deviation is largely bone, which cannot be scored straight; when cartilage is severely buckled after injury; in some revision operations where scar has altered the anatomy; and when septal cartilage is needed as graft material for septorhinoplasty or reconstruction. It is generally avoided in growing children.
How long is septoplasty recovery time before I can breathe normally?
Longer than most people expect. Swelling and splints block the nose for the first week, and splints are commonly removed at a follow-up around one week. Cleveland Clinic notes many people return to desk work within about a week, while strenuous activity is restricted for several weeks. Mayo Clinic describes nasal tissues as relatively stable by three to six months, with subtle changes continuing for up to a year.
Does deviated septum surgery change the shape of my nose?
A properly performed septoplasty should not. The operation is done entirely inside the nose, protects the supporting cartilage along the bridge and front edge, and leaves the external framework untouched. Shape changes such as a sunken bridge or drooping tip are recognized but uncommon complications, historically linked to removing too much cartilage. Deliberate changes to appearance require rhinoplasty, which is a separate decision sometimes combined with septal surgery.
What is the difference between septoplasty vs rhinoplasty?
Septoplasty straightens the internal dividing wall of the nose to improve airflow and leaves the outside unchanged. Rhinoplasty reshapes the external bones and cartilages for appearance or to repair a collapsed or injured outer nose. When a visibly twisted nose sits over a twisted septum, surgeons combine the two as a septorhinoplasty, and cartilage removed from the septum is often reused as graft material outside.
Can a deviated septum be treated without surgery?
Often, yes. Medical treatment does not straighten the septum but shrinks the swollen lining around it, which can open the passage enough for many people. Saline rinses, intranasal corticosteroid sprays, and allergy treatment are the usual first steps, decided with your clinician. A randomized trial found septoplasty gave better quality-of-life results than continued medical management, but guidelines still expect a fair trial of non-surgical treatment first.
Why is septal surgery usually delayed in children?
Because septal cartilage acts as a growth center for the mid-face. Removing or extensively disturbing it during childhood may affect how the nose and upper jaw develop. Pediatric surgeons therefore prefer to wait until facial growth is largely complete and, when obstruction is severe enough to justify earlier surgery, use the most cartilage-sparing technique possible. Adenoid enlargement is often a bigger cause of blockage in children.
What is a septal perforation and which technique carries more risk of it?
A septal perforation is a hole through the wall between the nostrils. It forms when the lining is torn on both sides at the same spot with no cartilage between them to bridge the gap while healing. Wide submucous resection, which lifts both lining flaps and removes the cartilage beneath, sets that stage more readily than a conservative septoplasty that leaves cartilage in place. Small perforations may cause only a whistle; larger ones cause crusting and bleeding.
Will septoplasty help my snoring or sleep apnea?
It may help you breathe more comfortably through the nose at night and can make a sleep apnea mask easier to tolerate, but it does not reliably treat obstructive sleep apnea, which usually involves the throat rather than the nose. Mayo Clinic lists improving nasal airflow, not resolving sleep apnea, as the aim. If snoring or daytime sleepiness is your main concern, ask for a sleep assessment before assuming surgery on the septum will address it.
Do I need nasal packing after septoplasty?
Not necessarily. Packing was once routine but is now used selectively, often only when bleeding is a concern. Many surgeons instead place soft silicone splints on either side of the septum for about a week, use dissolving materials, or close the lining with stitches alone. Your surgeon can tell you their usual approach and what, if anything, will be removed at the follow-up visit.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
When Is an Intratympanic Steroid Injection Considered for Sudden Hearing Loss?
An intratympanic steroid injection is usually considered for sudden sensorineural hearing loss in two situations: as initial treatment when oral corticosteroids are unsuitable, unwanted…

Is FESS the Next Step? When Chronic Sinusitis Stops Responding to Medical Treatment
FESS (functional endoscopic sinus surgery) is usually considered only after chronic sinusitis, meaning symptoms lasting 12 weeks or more, has failed a full course…

Sinusitis Warning Signs: High Fever, Facial Swelling and Vision Changes That Need Urgent Care
Most sinusitis improves on its own within about 7 to 10 days and can be managed at home. Seek urgent care the same day…

Does SMR Help Snoring and Nasal Obstruction? What Results Submucous Resection Can Bring
SMR (submucous resection) straightens a deviated nasal septum or reduces swollen turbinates to improve airflow through the nose. It reliably treats nasal obstruction, but…

How Long Does Adenoid Surgery Recovery Take in Children? Discomfort, Bad Breath and Swimming
Most children recover from adenoid surgery within about one to two weeks, with the first few days being the most uncomfortable. A sore throat,…

Does Septoplasty Improve Breathing? Realistic Results and How Long Full Benefit Takes
Septoplasty straightens a crooked nasal septum, and for people whose blockage comes mainly from that deviation, breathing through the nose usually improves once swelling…