

Transvaginal Ultrasound: What It Shows and Whether It Hurts
Key Takeaways
- A transvaginal probe sits within a few centimeters of the uterus and ovaries, which is why it produces sharper images than an abdominal scan but cannot see as deep.
- You should arrive with an empty bladder for a transvaginal scan; a full bladder is needed only for the abdominal part of a pelvic ultrasound.
- Healthy fallopian tubes are usually invisible on ultrasound, so a visible tube generally means it is filled with fluid or blood.
- Most functional ovarian cysts disappear on their own within a few months, which is why a repeat scan rather than treatment is the common first step.
- A normal pelvic ultrasound does not rule out endometriosis, because the scan sees the condition mainly when it forms an ovarian endometrioma or a deep nodule.
- Ultrasound cannot diagnose cancer; it identifies features such as solid tissue and blood flow that decide whether a biopsy or further imaging is needed.
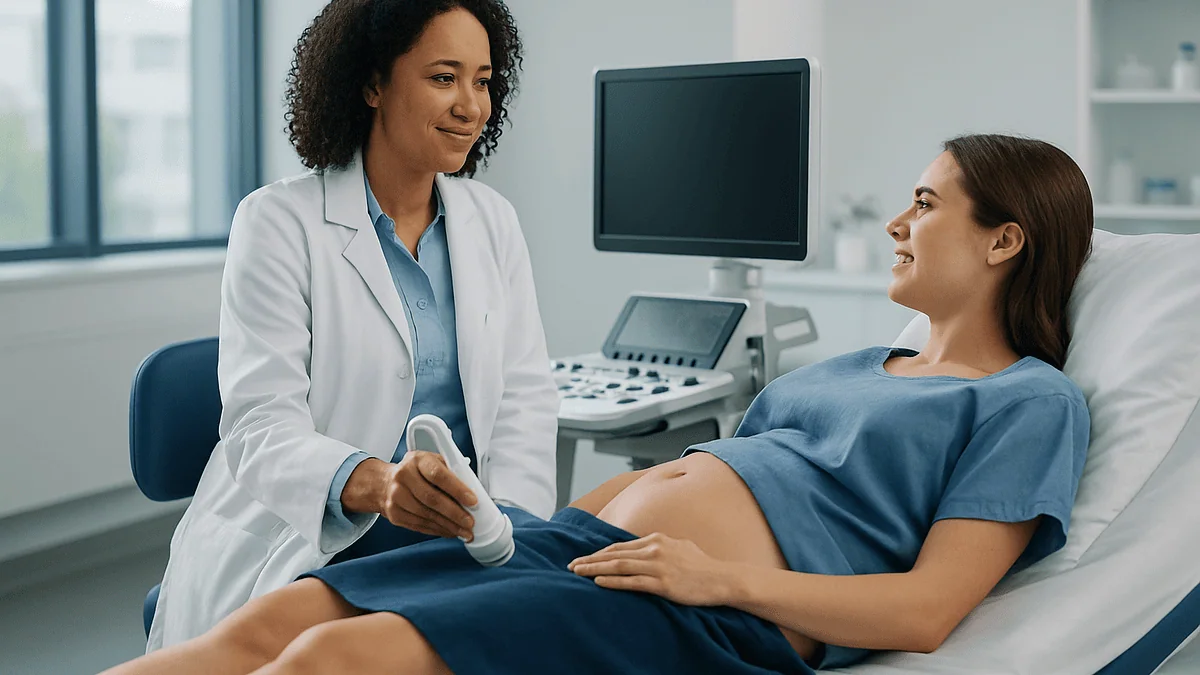
A transvaginal ultrasound shows the uterus, its inner lining (the endometrium), the cervix, both ovaries and the space around them in close detail, using a slim probe placed inside the vagina. Clinicians use it to look for fibroids, ovarian cysts, causes of pelvic pain or unusual bleeding, and early pregnancy. Most people feel pressure rather than pain, and the scan itself usually takes 15 to 45 minutes.
The paper sheet crinkles. The lights are dimmed so the screen reads better, the sonographer says something about “a bit of pressure,” and for a few seconds your whole attention narrows to one question: is this going to hurt, and what is she seeing that I can’t?
Plenty of people walk into that room having read very little that was honest. Online, the transvaginal scan tends to be described either as a formality or as an ordeal. Neither is true. The probe is roughly the width of a tampon, the organs it is looking at sit only a couple of centimeters away from its tip, and the images it produces are among the most useful in everyday gynecology, precisely because nothing gets in the way.
Here is what the scan can genuinely show, what it can’t, why it is chosen over a scan through the abdomen, and how to make the appointment as comfortable as the evidence says it can be.
What does a transvaginal ultrasound show?
Ultrasound works by sending high-frequency sound waves into the body and timing their echoes. Fluid lets sound pass and appears black; dense tissue bounces it back and appears white; most organs land somewhere in the gray between. Placed inside the vagina, the probe sits within a few centimeters of the pelvic organs, so the picture is unusually crisp.
The uterus is the first landmark. The scan records its size, shape and position; a uterus that tilts backward toward the spine is a normal variation that surprises many people when they see it written on a report. Inside the uterus, the endometrium shows as a distinct stripe whose thickness and texture change through the menstrual cycle, and that stripe is where polyps, some fibroids and an unusually thick lining reveal themselves.
The ovaries appear on either side as small ovals, often dotted with dark circles. Those circles are follicles, the fluid-filled sacs that hold developing eggs, and seeing several of them is expected in someone who menstruates. Measurements of each ovary, any cyst within it and blood flow around it are standard.
Healthy fallopian tubes are usually invisible on ultrasound because they are thin and empty. They become visible only when filled with fluid or blood, which is itself a finding. The scan also captures the cervix, part of the bladder, the position of an intrauterine device if one is in place, and any free fluid pooled in the pelvis. A small amount of fluid around ovulation is normal; a large amount is not.
What it does not show well is the bowel, the far side of a large mass, or tissue behind bone. Those limits explain why an abdominal scan or other imaging is sometimes added.
Why choose a transvaginal scan instead of a pelvic ultrasound through the abdomen?
Both scans use the same physics, so the difference comes down to distance and obstacles. A transabdominal probe glides over the lower belly and has to send sound through skin, fat, muscle and gas-filled bowel before it reaches the uterus. Bowel gas scatters sound badly, which is why that scan asks you to arrive with a full bladder: the bladder pushes bowel aside and acts as a clear window.
The transvaginal probe skips all of that. Because it is so close to the target, it can use a higher frequency, and higher frequency means finer detail. The trade-off is depth. High-frequency sound fades quickly, so a very large fibroid or a mass reaching up toward the navel may extend beyond what the internal probe can capture.
In practice the two approaches are complementary, and many appointments include both. The abdominal view gives the wide shot; the transvaginal view provides the close-up of the endometrium, the ovaries and anything small. Clinicians tend to reach for the internal scan when they need to:
- measure the endometrium precisely, particularly after menopause or during fertility care
- look closely at an ovarian cyst to judge whether it is simple or complex
- confirm and date an early pregnancy, when the embryo is still tiny
- find the source of pelvic pain when the abdominal view is unclear
- check the placement of an intrauterine device
The choice is not about severity. Being sent for a transvaginal scan does not mean something is more likely to be wrong; it usually means the question being asked needs a sharper picture.
Does a transvaginal ultrasound hurt?
For most people, no. The honest word is pressure, with a moment of coolness from the gel and an odd, unfamiliar sensation as the probe is angled toward each side to bring the ovaries into view. Patient-information pages from major medical centers consistently describe the experience as mildly uncomfortable rather than painful, and the probe is slim, covered with a protective sheath and lubricated before it is inserted.
That said, discomfort is real for some, and it is worth being candid about who is more likely to feel it. People with conditions that already cause pelvic pain, such as endometriosis or pelvic inflammatory disease, may find the scan tender, especially when the probe presses near the affected area. Vaginal dryness after menopause can make insertion sting. Anyone with a history of sexual trauma, or with vaginismus, may find the position and the intrusion distressing in a way that has nothing to do with the physical size of the probe.
Several things help, and you are entitled to all of them. You can ask to insert the probe yourself, which many people find restores a sense of control. You can request a chaperone, ask for the procedure to be paused, or stop it entirely. Slow breathing and letting your knees fall outward relaxes the pelvic floor, which reduces the pressure sensation more than any technique.
The scan is not usually recommended for someone who has never had vaginal intercourse, and it is never mandatory. A transabdominal scan, sometimes with a fuller bladder to compensate, is the standard alternative. Discussing this before the appointment, rather than on the table, gives everyone time to plan.
What happens during the scan, step by step
Knowing the sequence takes much of the anxiety out of it. You will be asked to empty your bladder, undress from the waist down and lie on an examination couch, usually on your back with knees bent and slightly apart. A sheet covers your lap throughout.
The sonographer, or sometimes the clinician who ordered the test, covers the probe with a single-use sheath and a layer of gel, then inserts it gently a few inches into the vagina. From there the work is mostly small movements: tilting the handle forward to see the uterus lengthwise, rotating it to see the uterus in cross-section, then angling it to the left and right to find each ovary. Each position produces a still image and, often, a short clip.
Measurements happen as they go. You may hear clicks as calipers are placed on the screen and see numbers appear; these are the routine dimensions of the uterus, the endometrial stripe and each ovary. If a cyst or fibroid is found, it is measured in three planes. A color overlay may flicker on and off when blood flow is being checked.
The NHS notes that an ultrasound scan usually takes between 15 and 45 minutes, and the transvaginal portion is often at the shorter end. It runs longer when an ovary is hard to locate, when there is a lot to document, or when a full pelvic examination combines abdominal and internal views. Afterward you wipe away the gel, dress, and the images go to whoever will write the report. There is no recovery period and no restriction on driving, working or exercise.
What not to do before an internal ultrasound
The preparation for a transvaginal scan is almost the opposite of what people expect, because most of the folklore comes from abdominal scans. A few clear rules cover it.
Do not arrive with a full bladder unless you have been told to. For the internal scan a full bladder pushes the uterus out of position and makes the probe far less comfortable. If your appointment combines an abdominal and a transvaginal view, you will typically be scanned through the belly first with a full bladder, then sent to empty it.
Do not skip meals or fast. Unlike some abdominal imaging, a pelvic ultrasound has no dietary preparation, and turning up hungry and lightheaded helps nobody.
Do not cancel because your period has started. The scan can be done while you are bleeding, and for some questions, such as checking the endometrium or counting follicles in fertility care, clinicians deliberately schedule it in the first days of the cycle. Remove a tampon or menstrual cup beforehand; a pad is fine.
Do not douche or use vaginal products the day of the scan. Douching is not recommended for vaginal health in general, and creams or gels can smear the image and irritate tissue. Ordinary washing is all that is needed.
Do not stop prescribed medicines on your own account. Nothing about the scan requires it, and any question about hormonal medicines and timing is one for the prescribing clinician, not for the day of the appointment.
One thing you can do: bring the date your last period started. Almost every report is interpreted against the day of your cycle, and a guess costs precision.
Can a sonographer tell if something is wrong?
Very often, yes, and very often they will not say so, and that gap is where a great deal of unnecessary fear lives. In many settings the person holding the probe is a sonographer whose job is to acquire a complete, high-quality set of images; a radiologist or gynecologist then reads those images and writes the report. Sonographers are typically trained not to give diagnoses, both because interpretation is the physician’s legal responsibility and because a partial comment can do real harm if the final read differs.
So a quiet room means little. Extra images do not mean trouble; a thorough sonographer takes them routinely, and an ovary hiding behind bowel needs several attempts. A sonographer stepping out to consult a colleague is usually about protocol, not alarm. The absence of reassurance is not information.
There are exceptions. When the clinician who ordered the scan performs it, as many gynecologists and fertility specialists do, they will usually talk you through the screen in real time. In an emergency setting, a scan showing something that needs urgent action, such as a pregnancy outside the uterus, is acted on straight away rather than waiting for a written report.
What you can reasonably ask, in any setting: whether the images were complete, when and how the report will reach you, and who to contact if you have not heard by that date. Those questions get real answers. “Is everything OK?” often does not, and not because anything is being hidden.
What would be abnormal on a pelvic ultrasound?
“Abnormal” on an ultrasound report covers everything from a finding that will never matter to one that needs action within days, and reports rarely make the distinction plain. The table below lists the findings that appear most often, what they look like to the person reading the scan, and what usually follows.
| Finding | What it looks like | What usually happens |
|---|---|---|
| Fibroid | Round, well-defined mass in the uterine wall, often several | Measured and tracked; acted on only if causing symptoms |
| Simple ovarian cyst | Thin-walled, fluid-filled, black inside, no solid parts | Frequently resolves on its own; repeat scan may be arranged |
| Complex ovarian cyst | Internal echoes, thick walls, septations or solid areas | Further assessment, sometimes blood tests or other imaging |
| Endometrioma | Cyst with uniform, ground-glass gray interior | Suggests endometriosis; managed according to symptoms |
| Endometrial polyp | Small bright growth inside the uterine cavity | Often confirmed with saline scan or hysteroscopy |
| Thickened endometrium | Lining measures more than expected for cycle stage or after menopause | Biopsy usually offered after menopause |
| Hydrosalpinx | Fluid-filled, tubular structure beside the ovary | Indicates a blocked tube; relevant to fertility and pain |
| Free pelvic fluid | Dark fluid pooled behind the uterus | Small volumes normal; large volumes prompt investigation |
Two features carry more weight than any single diagnosis: whether a mass has solid components or internal blood flow, and whether it changes over time. A cyst that is smaller or gone at a follow-up scan has largely answered the question itself. A mass that grows, or that has solid, vascular parts, is what moves the conversation toward further testing. The scan describes structure; it is the pattern across findings, symptoms and, when needed, biopsy that yields a diagnosis.
What does a transvaginal ultrasound show in early pregnancy?
In the first weeks after a positive test, the embryo is smaller than a grain of rice, and the internal scan is the only imaging that can reliably find it. Because the probe sits so close, it detects a pregnancy earlier than a scan through the abdomen can, which is why it is the standard tool for early pregnancy assessment.
The sequence of what appears follows a predictable order. First comes the gestational sac, a small dark circle within the endometrium. Next, inside it, the yolk sac, a tiny ring that nourishes the embryo before the placenta takes over. Then the embryo itself, seen as a thickening beside the yolk sac, and finally the flicker of a heartbeat. Seeing these structures in the right place and in the right order is the reassurance the scan is designed to provide.
Location is the other reason clinicians reach for this scan early. Confirming that the pregnancy is inside the uterus rules out an ectopic pregnancy, one growing in a fallopian tube or elsewhere, which is a medical emergency. Pelvic pain or bleeding with a positive test is the classic prompt for an urgent internal scan.
The scan also dates the pregnancy by measuring the embryo from crown to rump, checks for twins, and may show a small pocket of blood beside the sac, called a subchorionic hemorrhage, which often resolves without consequence. Ultrasound uses sound, not ionizing radiation, and decades of use have found no harm to the developing baby when performed for medical reasons; the NHS and Mayo Clinic both describe it as safe in pregnancy. A vaginal probe does not reach the cervix or the pregnancy itself and does not raise the risk of miscarriage.
What cancers can a pelvic ultrasound detect, and what it cannot
This is the question behind most of the anxiety in the waiting room, so it deserves a plain answer. An ultrasound cannot diagnose cancer. It shows shapes, textures and blood flow, and some of those patterns are more worrying than others. A diagnosis comes from tissue examined under a microscope.
With that caveat, the scan is genuinely useful for three gynecological cancers. Ovarian tumors tend to appear as complex masses with solid areas, thick internal walls, finger-like projections into the cyst fluid, or increased blood flow on Doppler, sometimes accompanied by fluid in the abdomen. Endometrial cancer most often presents as bleeding after menopause, and the scan’s job there is to measure the lining; a thin lining makes cancer unlikely, while a thickened one leads to a biopsy that gives the real answer. Cancer of the fallopian tube is rare and looks much like an ovarian mass.
Cervical cancer is where ultrasound is weak. The cervix sits right against the probe, and early changes in its surface cells are invisible to sound waves. Screening for cervical cancer is done with a smear test and HPV testing, not imaging.
A second honest point: ultrasound is not a screening test for ovarian cancer in people at average risk. Large trials that scanned healthy women regularly, sometimes alongside a blood test, did not reduce deaths from the disease, while producing false alarms that led to surgery in people who turned out to have nothing. That is why no major health agency recommends routine scans for those without symptoms or a strong family history. When the scan is ordered because something is wrong, it earns its place. As a reassurance ritual for the well, the evidence does not support it.
Ovarian cysts on ultrasound: why most of them are not a problem
If your report mentions a cyst, you are in a very large company. Every menstrual cycle, an ovary grows a follicle that fills with fluid, releases an egg and collapses; sometimes it keeps growing instead, or fills with blood after ovulation. These are functional cysts, and the NHS describes them as common, usually harmless and typically disappearing within a few months without any treatment.
On the screen, the reassuring version is easy to recognize: a single round sac with a thin, smooth wall and completely black fluid inside. Radiologists call this a simple cyst, and its size is the main detail that determines whether anyone wants to see it again. A cyst that has bled into itself, a hemorrhagic cyst, can look dramatic, with a lacy web of internal echoes, yet it behaves the same way and usually vanishes by the next scan. That is why a repeat scan after a cycle or two is such a common recommendation: time is the test.
Other cysts have a story of their own. An endometrioma, a pocket of endometriosis on the ovary, has a characteristic uniform gray interior sometimes compared to ground glass. A dermoid cyst can contain fat, hair or calcium and shows bright, mixed echoes. Polycystic ovaries carry many small follicles arranged around the edge, a pattern that, on its own, does not diagnose polycystic ovary syndrome; that requires symptoms and blood tests too.
Size, solid tissue and blood flow are what shift a cyst from “watch” to “investigate.” A large cyst can twist the ovary or rupture, which is why sudden severe one-sided pain with a known cyst is treated as urgent. Absent those features, the most useful response to the word cyst is patience, not alarm.
What the endometrium reveals about bleeding, periods and menopause
The endometrial stripe is a moving target, and reading it correctly depends entirely on timing. Just after a period it is thin and bright. Through the first half of the cycle it thickens into a layered, three-line pattern. After ovulation it becomes uniformly thick and bright, ready for a pregnancy that usually does not arrive, then sheds. A thickness that is normal on day 25 would be unusual on day 5, which is why the sonographer wanted your period date.
After menopause the picture simplifies. Without cyclic hormones the lining should stay thin, and a thin, even stripe is strongly reassuring in someone with postmenopausal bleeding. When the lining is thicker than the accepted cutoff, or when it looks irregular, the next step is usually a sample of the tissue, because ultrasound can suggest but not distinguish between benign thickening, a polyp and cancer.
Heavy or prolonged periods bring their own findings. Fibroids pressing into the cavity distort the stripe. Adenomyosis, in which endometrial tissue grows into the muscular wall, thickens the uterus asymmetrically and gives the muscle a streaky, cystic texture. Polyps appear as small bright bulges, best confirmed by filling the cavity with saline so they stand out against fluid.
One myth needs retiring here. A normal pelvic ultrasound does not rule out endometriosis. The condition most often consists of tiny deposits on the lining of the pelvis, which are too small and too flat for sound waves to detect. Ultrasound sees endometriosis mainly when it forms an ovarian endometrioma or a deep nodule. A clean scan alongside persistent, cyclic pelvic pain is a reason to keep talking to your clinician, not a reason to stop.
Doppler, saline and 3D: the extras you might hear about
Several add-ons ride on the same probe, and knowing what they do saves confusion when they appear in a report.
Doppler measures movement, specifically the movement of blood. Switched on, it paints flowing vessels in color over the gray image. Its value in gynecology is in characterizing a mass: benign cysts have little internal flow, whereas solid tissue with rich blood supply attracts more scrutiny. Doppler also assesses the blood supply to a twisted ovary and to a fibroid.
Saline infusion sonography, sometimes called a sonohysterogram, adds a thin catheter through the cervix and a small volume of sterile saline into the uterine cavity while the scan runs. Fluid outlines the cavity so polyps, small fibroids and scar tissue stand out sharply. It causes cramping similar to a period for some, and it is scheduled after bleeding has stopped and before ovulation.
Three-dimensional ultrasound reconstructs the uterus as a volume, which is mainly useful for judging its shape. Congenital variations, such as a partition running down the middle of the cavity, are far easier to see this way, and 3D is also used to confirm that an intrauterine device sits correctly.
In fertility care the transvaginal probe becomes a monitoring tool: repeated scans count and measure follicles as they grow, and the same probe guides needle retrieval of eggs and, in some clinics, embryo transfer. None of these extras changes how the scan feels; each just answers a more specific question than the standard pictures can.
After the scan: reading the report and knowing what comes next
Reports are written for the clinician who ordered them, in a shorthand that can read harshly to anyone else. A few translations help. “Unremarkable” means normal. “Incidental” means a finding unrelated to the question asked, which is very often harmless. “Cannot exclude” describes the limits of the image rather than a suspicion. “Recommend correlation with clinical findings” is the radiologist saying the picture needs your symptoms to make sense, which is always true.
Measurements are the trap. A number for endometrial thickness or ovarian volume means nothing without your cycle day, your age and whether you have gone through menopause, and the same figure can be ordinary in one person and significant in another. Searching a measurement in isolation tends to deliver the worst-case interpretation first.
The follow-up pathways are fairly standard. A simple cyst may earn a repeat scan after a cycle or two. A thickened postmenopausal lining leads toward a biopsy. A complex mass may prompt blood tests and MRI. An early pregnancy that is too small to show a heartbeat is rescanned after an interval, because a single early scan can be inconclusive and a second one usually is not. A normal scan with ongoing symptoms is a legitimate result that redirects the search rather than closing it.
Timelines for receiving results vary widely between settings, so ask before you leave. Written results delivered through a patient portal can arrive before anyone has had a chance to explain them; if you see one at eleven at night, the sensible move is to note your questions and wait for the person who can answer them.
When to see a doctor: symptoms that should not wait for a routine scan
Most transvaginal scans are booked calmly, for questions that have been building for weeks. Some symptoms should skip that queue. Seek urgent care the same day for sudden, severe pelvic or lower abdominal pain, particularly on one side; pain with fever, vomiting or a swollen, tender abdomen; any pelvic pain or vaginal bleeding alongside a positive pregnancy test or a missed period, which can signal an ectopic pregnancy; bleeding heavy enough to cause dizziness, fainting or a racing heart; or a known ovarian cyst with abrupt new pain, because an ovary can twist and lose its blood supply.
Other symptoms warrant an ordinary appointment rather than the emergency department, but they do warrant one. Bleeding after menopause, even a single episode of spotting, should always be evaluated; the scan is usually the first step and the finding is often benign, yet this is the symptom that catches endometrial cancer early. Periods that have become heavier, longer or closer together, bleeding between periods or after sex, pelvic pressure or a persistent feeling of fullness, pain during intercourse, difficulty conceiving after a year of trying, and persistent bloating with a change in appetite all justify a conversation and, very likely, a scan.
A reasonable rule: sudden and severe means today; new and persistent means soon; and anything that frightens you enough to search for it at two in the morning is worth saying out loud to a clinician. The scan exists to replace guessing with a picture. It works best when the question gets asked early.
Frequently asked questions
What does a transvaginal ultrasound show that a pelvic exam cannot?
It shows the inside of the uterus and the ovaries themselves, which a hand examination can only estimate by feel. The scan measures the endometrial lining, counts follicles on each ovary, characterizes cysts as simple or complex, identifies fibroids and polyps, detects fluid in the pelvis and confirms the location of an early pregnancy. A pelvic exam can detect tenderness or a large mass; the ultrasound explains what that mass is made of.
Does a transvaginal ultrasound hurt?
For most people it feels like pressure rather than pain, with brief odd sensations as the probe is angled toward each ovary. Discomfort is more likely with pelvic pain conditions, vaginal dryness after menopause, vaginismus or a history of trauma. You can insert the probe yourself, ask for a chaperone, request a pause or stop entirely, and a scan through the abdomen is always an alternative if you prefer.
Can I have a transvaginal ultrasound on my period?
Yes. Menstrual bleeding does not prevent the scan, and for some questions, such as measuring the endometrium or counting follicles in fertility care, clinicians deliberately time it to the first days of the cycle. Remove a tampon or menstrual cup before the appointment. If you would rather reschedule for comfort reasons, ask whether the timing matters for your particular question before you do.
Do I need a full bladder for a transvaginal ultrasound?
No. For the internal scan you will be asked to empty your bladder first, because a full bladder pushes the uterus out of position and makes the probe uncomfortable. The full-bladder instruction applies to the abdominal pelvic scan, where the bladder acts as a window past gas-filled bowel. When both are done in one visit, the abdominal view comes first, then you empty your bladder for the transvaginal part.
What cancers can a pelvic ultrasound detect?
It can identify features suspicious for ovarian, endometrial and, rarely, fallopian tube cancer, such as solid masses with blood flow or a thickened uterine lining after menopause. It cannot confirm cancer; that requires a biopsy. Ultrasound is poor at detecting cervical cancer, which is screened by smear and HPV testing, and it is not recommended as a routine ovarian cancer screen for people at average risk because trials did not show it saves lives.
Can the sonographer tell me my results during the scan?
Usually not, and silence is not a sign of bad news. In most settings the sonographer captures the images and a radiologist or gynecologist interprets them and writes the report, so sonographers are trained not to offer diagnoses. When the clinician who ordered the scan performs it, they often discuss findings in real time. Ask when and how you will receive results, and whom to contact if they are delayed.
What would be abnormal on a pelvic ultrasound?
Common abnormal findings include fibroids, ovarian cysts, endometrial polyps, a lining thicker than expected for your cycle stage or menopausal status, a fluid-filled fallopian tube, and larger volumes of free fluid in the pelvis. Most of these are benign. The features that prompt further testing are solid tissue within a mass, increased blood flow on Doppler, and growth between scans, rather than the presence of a finding by itself.
Is a transvaginal ultrasound safe in early pregnancy?
Yes. Ultrasound uses sound waves rather than ionizing radiation, and the NHS and Mayo Clinic both describe it as safe during pregnancy when performed for medical reasons. The probe does not reach the cervix or the pregnancy and does not raise miscarriage risk. It is the standard way to confirm that an early pregnancy is inside the uterus, to check for a heartbeat and to date the pregnancy accurately.
Can a transvaginal ultrasound detect endometriosis?
Only sometimes. Most endometriosis consists of small, flat deposits on the pelvic lining that sound waves cannot see, so a normal scan does not exclude the condition. Ultrasound detects it when it forms an endometrioma on the ovary, which has a characteristic uniform gray interior, or a deep nodule behind the uterus. Persistent cyclic pelvic pain with a clear scan is a reason to continue the conversation with your clinician.
What if I have never had sex or find internal exams distressing?
You can decline a transvaginal scan, and it is generally not recommended for anyone who has not had vaginal intercourse. A scan through the abdomen with a full bladder is the usual alternative and answers many of the same questions, though with less detail. Telling the booking team or clinician in advance allows them to plan, offer a chaperone, or let you insert the probe yourself if you choose to proceed.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Often You Need a Smear Test (UK, EU and US Intervals)
In the UK, cervical screening (a smear test) is offered every five years between ages 25 and 64, with earlier recall if HPV is…
Myomectomy vs Hysterectomy for Fibroids: How Pregnancy Plans Shape the Choice
Myomectomy removes fibroids while keeping the uterus, so it is usually the surgical option for people who may want a future pregnancy, though fibroids…

Fibroid Surgery Recovery: Bleeding Checks, Early Walking and Lifting Limits Week by Week
Fibroid surgery recovery time depends mainly on the route the surgeon used. Hysteroscopic removal through the cervix usually needs a few days; laparoscopic or…
Smear Tests During Pregnancy: Are They Safe, and When Should You Have One?
Yes, a smear test (Pap smear) can be done safely at any stage of pregnancy. The sample is taken from the surface of the…

Normal Period Cycle Length: What Counts as Regular (It’s a Range)
A normal menstrual cycle typically ranges from 21 to 35 days in adults, counted from the first day of one period to the first…

Hysterectomy Myths: Does It Always Bring On Menopause, and Is Recovery Always Long?
A hysterectomy does not always bring on menopause. Menopause follows immediately only when both ovaries are removed during the same operation; if the ovaries…